Osteogenesis imperfecta (OI) is inherited bone fragility; about 80-90% of cases come from an autosomal dominant variant in COL1A1 or COL1A2, the two genes for type I collagen. In type I OI, the mildest and most common form, cells make about half the normal amount of normal collagen; the more severe types (II, III and IV) usually carry glycine substitutions that make structurally abnormal collagen. The classic picture is fractures after little or no trauma, blue or gray sclerae and progressive hearing loss in adults, with dentinogenesis imperfecta (gray-brown teeth that wear easily) mainly in the more severe types. Treatment is bisphosphonates (IV pamidronate or zoledronic acid, or oral alendronate) to raise bone density and cut bone pain and fractures, plus intramedullary rodding, physical therapy and hearing care. The must-know differential is child abuse, which can produce the same pattern of multiple fractures of different ages.
OI types at a glance
| Type | Severity | Collagen defect | Sclerae | Other clues |
|---|---|---|---|---|
| I (classic non-deforming) | Mildest, most common | Less collagen: a null COL1A1 allele halves the amount of normal type I collagen | Blue or gray | First fractures usually come when the infant starts to walk and fall; they heal without deformity and become less frequent after puberty; normal or near-normal height; progressive hearing loss in more than half of adults; dentinogenesis imperfecta rare |
| II (perinatally lethal) | Most severe | Abnormal collagen, usually a glycine substitution | Dark blue | Multiple fractures at birth, soft skull; nearly always a new (de novo) variant |
| III (progressively deforming) | Most severe that survives | Abnormal collagen | Blue in infancy, lightening with age | Fractures from minimal handling (as many as 200), progressive deformity, very short stature, scoliosis, basilar invagination, Wormian bones in 96%; dentinogenesis imperfecta common |
| IV (common variable, normal sclerae) | Moderate, most variable | Abnormal collagen | Light blue or gray at birth, then near normal | Variable deformity and short stature; Wormian bones in 78%; dentinogenesis imperfecta common but may be mild |
| V and beyond | Mild to moderate (type V) | Other genes | Variable | Type V: interosseous membrane calcification; at least 19 types exist, mostly rare and recessive |
Board shortcut: type I = Intact shape (mild, blue sclerae); type II = lethal at birth; type III = III-fated deformity; type IV = Variable with normal sclerae.
Exam framing vs current source: dental problems are taught as a classic OI feature alongside blue sclerae and hearing loss (NIAMS also lists brittle, discolored teeth among OI symptoms), so a question may still use that pattern. GeneReviews (2025) is more specific: only a small minority of people with type I OI have dentinogenesis imperfecta; it is more common in type III and common, but often mild, in type IV.
Why a collagen defect breaks bones and turns sclerae blue
- The molecule. Type I collagen is a rope of three chains: two pro-α1(I) chains from COL1A1 and one pro-α2(I) chain from COL1A2. It is the main structural protein of bone, tendon, skin and the sclera.
- The repeat. Each chain is built on a Gly-X-Y repeat, so glycine, the smallest amino acid, sits at every third position of the triple helix.
- Less collagen (type I). A variant that stops production from one COL1A1 copy leaves half the normal amount of otherwise normal collagen: weaker bone, but a mild disease.
- Bad collagen (types II-IV). Replacing a glycine with a bulkier amino acid makes abnormal chains that still get built into the helix and fibrils, spoiling the normal chains too (a dominant-negative effect). The result is far more severe.
- Exam hook: a little less good collagen is better than a lot of bad collagen. Mild OI = quantitative defect; severe OI = qualitative defect.
- Blue sclerae: the deficient connective tissue of the sclera lets the underlying vessels show through.
- Hearing loss: conductive, sensorineural or mixed; in type I it is rarely noted in childhood and becomes progressive in adulthood, while in type III it generally begins in the teenage years.
Type I collagen is one of four collagen types to know cold; see collagen types I-IV.
OI vs other collagen and connective tissue disorders
Classic (COL1A1/COL1A2) OI is a problem with the collagen chains themselves, not with a vitamin or a cofactor. The step-by-step pathway, with each cofactor, is in collagen synthesis steps.
| Disorder | Defect | Inheritance | Clues that separate it from OI |
|---|---|---|---|
| Osteogenesis imperfecta | Type I collagen (COL1A1, COL1A2) | AD (rare recessive and X-linked forms) | Fractures with minor trauma, blue sclerae, hearing loss, dentinogenesis imperfecta |
| Scurvy | Vitamin C deficiency, so connective tissue, bone and dentin form poorly | Acquired | Swollen, bleeding gums, perifollicular hemorrhages, coiled hair, poor wound healing, bruising; infants have painful limbs from subperiosteal bleeding |
| Menkes disease | ATP7A copper-transport defect starves copper-dependent enzymes | X-linked recessive | Infant boy with sparse kinky hair, poor growth, hypotonia, seizures and neurologic decline |
| Classic Ehlers-Danlos | Type V collagen (COL5A1, COL5A2) | AD | Soft, stretchy, fragile skin, hypermobile joints, wide "cigarette paper" scars |
| Vascular Ehlers-Danlos | Type III collagen (COL3A1) | AD | Unpredictable rupture of blood vessels and organs: internal bleeding, intestinal perforation, stroke, uterine rupture |
| Marfan syndrome | Fibrillin-1 (FBN1), the protein of microfibrils | AD | Tall, long fingers, arm span greater than height, lens dislocation, aortic aneurysm and dissection |
Menkes now has a disease-specific drug: copper histidinate (Zycubo) was FDA-approved for it in January 2026.
OI vs child abuse
This is where OI matters most in practice. GeneReviews lists the overlap: multiple or recurrent fractures, fractures that don't match the history, and fractures of different ages. Points that help:
- Fractures that keep happening after the child leaves a possibly abusive setting support OI.
- Metaphyseal and rib fractures are thought to be almost pathognomonic for abuse, but they can rarely occur in OI.
- Blue sclerae are unreliable for telling the two apart (unaffected infants often have blue sclerae until about 18 months, and children with OI may not have them), and a negative family history doesn't exclude OI (de novo variants, mild relatives).
- One study suggested considering OI testing in suspected abuse only when there are blue sclerae, osteopenia or a positive family history.
On a Step 1 question, a child with fractures plus blue sclerae, hearing loss, dental problems or an affected parent is OI; fractures of different ages with an inconsistent story and no OI features point to abuse.
Diagnosis
- Clinical: fracture history, blue or gray sclerae, dentinogenesis imperfecta, hearing loss, short stature, joint laxity, bowing or scoliosis, and family history.
- X-rays: fractures in different stages, deformity, and Wormian bones (extra small bones in the skull sutures).
- Confirmation: a heterozygous COL1A1 or COL1A2 variant on molecular testing (sequencing plus deletion/duplication analysis, or a multigene panel or exome). Merck also lists analysis of type I procollagen from cultured skin fibroblasts.
- Inheritance for counseling: autosomal dominant, so an affected parent has a 50% chance of passing it on to each child. About 60% of people with mild OI, and virtually all with type II or III, are the only affected person in their family (usually because of a de novo variant); but up to 16% of parents of children with COL1A1/COL1A2 OI are mosaic, so a "new" variant can recur.
- Frequency: about 6-7 per 100,000 people.
Treatment
- Bisphosphonates are the main drug treatment: IV pamidronate (cycles every 4-6 months), IV zoledronic acid (every 3-6 months) or oral alendronate. They aim to increase bone density and reduce bone pain, fractures and scoliosis, and are used most in people with vertebral fractures, frequent long-bone fractures or more severe OI. (Review the class in bisphosphonates and bone drugs.)
- Intramedullary rodding straightens and stabilizes bowed long bones.
- Physical therapy builds strength and mobility and helps prevent contractures.
- Hearing: audiology every 3 years from age 5 until loss appears; hearing aids, and cochlear implants for selected patients.
- Also: vitamin D for those who are deficient, dental care for dentinogenesis imperfecta, and genetic counseling.
Practice question
An 8-year-old girl is brought in after her fourth fracture in 2 years, a right radius fracture from tripping while walking. Each earlier fracture also followed minor trauma and healed without deformity. She is at the 40th percentile for height. Her sclerae are blue-gray, and her teeth look normal. Her mother had several fractures as a child and started wearing hearing aids at age 34. Which best describes the molecular basis of this girl's condition?
A. A glycine substitution that produces structurally abnormal type I collagen B. A variant that halves the production of normal type I collagen C. Deficient dietary vitamin C impairing collagen formation D. A copper-transport defect in the ATP7A gene E. A defect in fibrillin-1
Answer: B. Recurrent low-trauma fractures that heal without deformity, normal height, blue-gray sclerae, no dentinogenesis imperfecta, and a mother with fractures and early adult hearing loss make this type I OI, the mild form caused by a null COL1A1 allele that halves the amount of normal type I collagen (autosomal dominant).
- A: Glycine substitutions cause the structurally abnormal collagen of the more severe types (II, III, IV), with deformity, short stature and often dentinogenesis imperfecta.
- C: Scurvy is acquired; it causes bleeding gums, perifollicular hemorrhages and poor wound healing, and wouldn't explain blue sclerae or the family history.
- D: Menkes disease is X-linked, affects infant boys and causes kinky hair and neurologic decline.
- E: Fibrillin-1 defects cause Marfan syndrome: tall stature, long fingers, lens dislocation and aortic aneurysm, not recurrent fractures.
Key takeaways
- OI = type I collagen defect (COL1A1/COL1A2), usually autosomal dominant: fractures with minor trauma, blue sclerae, hearing loss, dentinogenesis imperfecta.
- Type I = less normal collagen (mild); types II-IV = abnormal collagen from glycine substitutions (severe).
- Type II is perinatally lethal; type III is progressively deforming; type IV has near-normal sclerae.
- Hearing loss in type I is rare in childhood and progressive in adulthood; dentinogenesis imperfecta is more common in severe types.
- Bisphosphonates are the drug answer; rodding, physical therapy and hearing care complete management.
- Always weigh child abuse: both cause fractures of different ages; blue sclerae alone don't settle it.
Sources
- COL1A1/2 Osteogenesis Imperfecta — GeneReviews, NCBI Bookshelf (2025)
- Osteogenesis Imperfecta — Merck Manual Professional Edition (2026)
- Osteogenesis imperfecta — MedlinePlus Genetics (2020)
- COL1A1 gene — MedlinePlus Genetics (2019)
- Osteogenesis Imperfecta — NIAMS, National Institutes of Health
- Vitamin C Deficiency — Merck Manual Professional Edition (2026)
- Ehlers-Danlos syndrome — MedlinePlus Genetics (2022)
- Menkes syndrome — MedlinePlus Genetics (2019)
- Marfan syndrome — MedlinePlus Genetics (2018)
- Novel Drug Approvals for 2026 — U.S. Food and Drug Administration (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
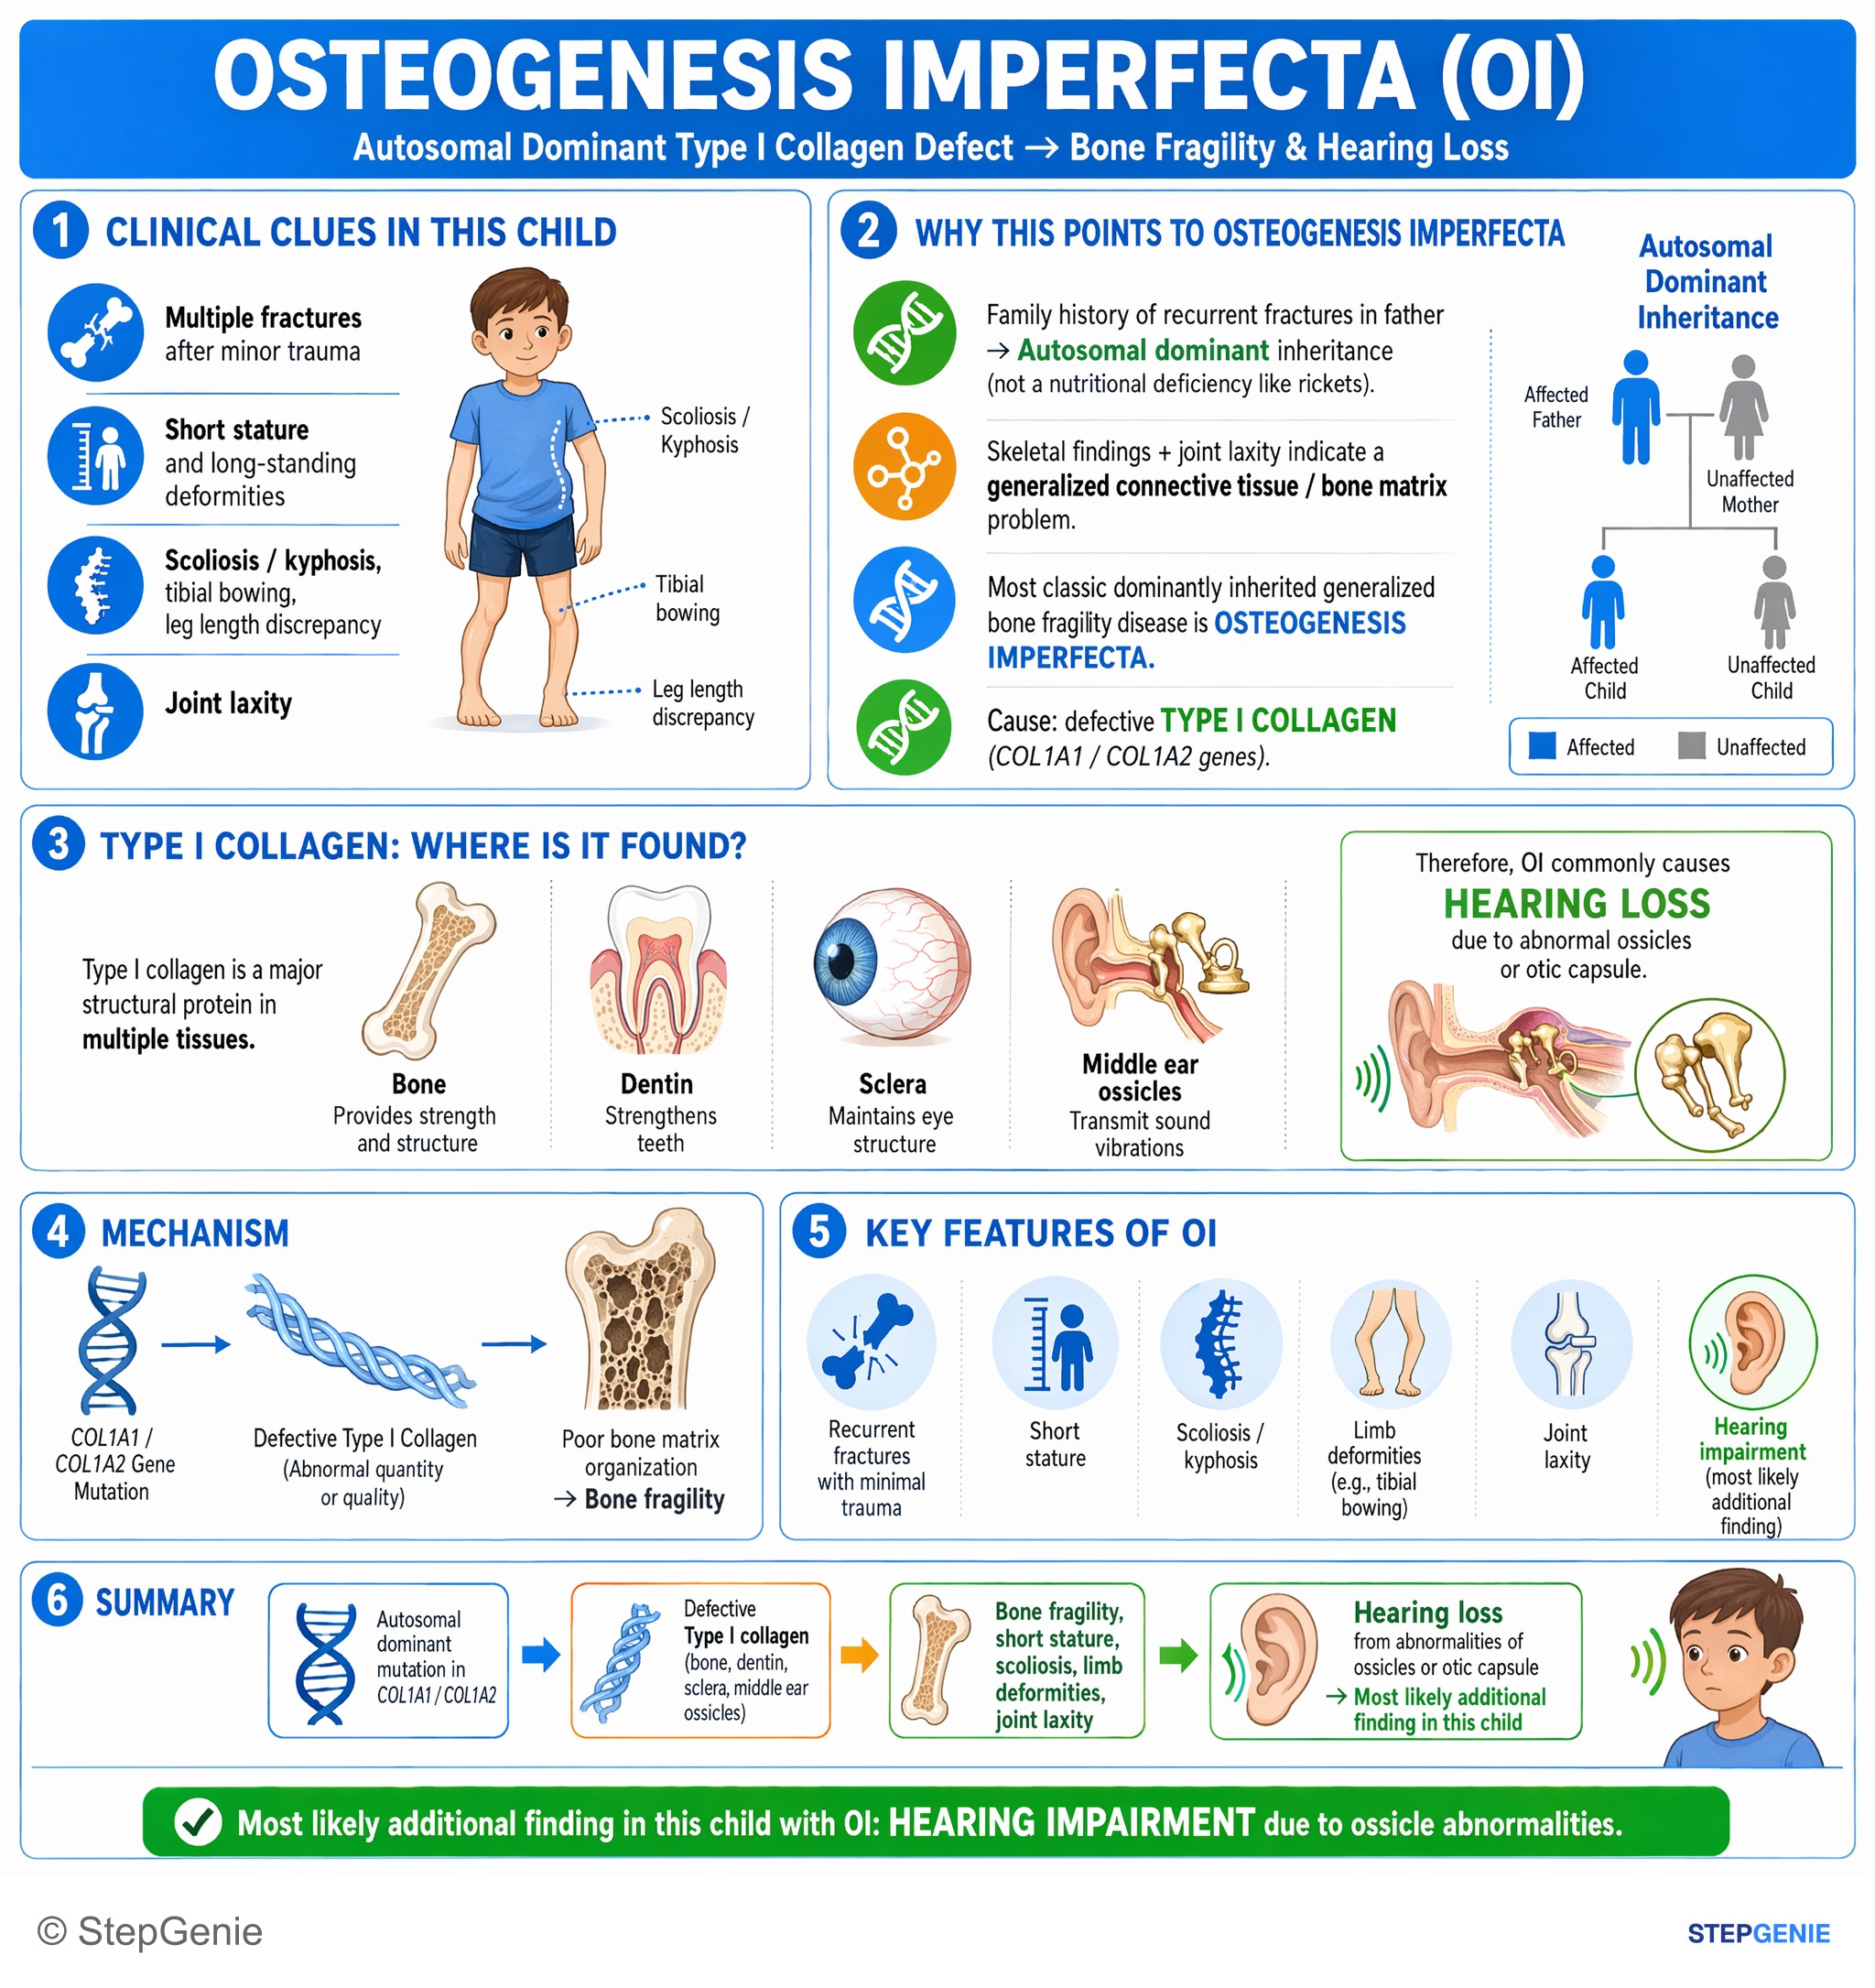
Osteogenesis imperfecta: autosomal dominant collagen I defect → bone fragility, short stature, scoliosis, limb deformities, and hearing…
USMLE Step 1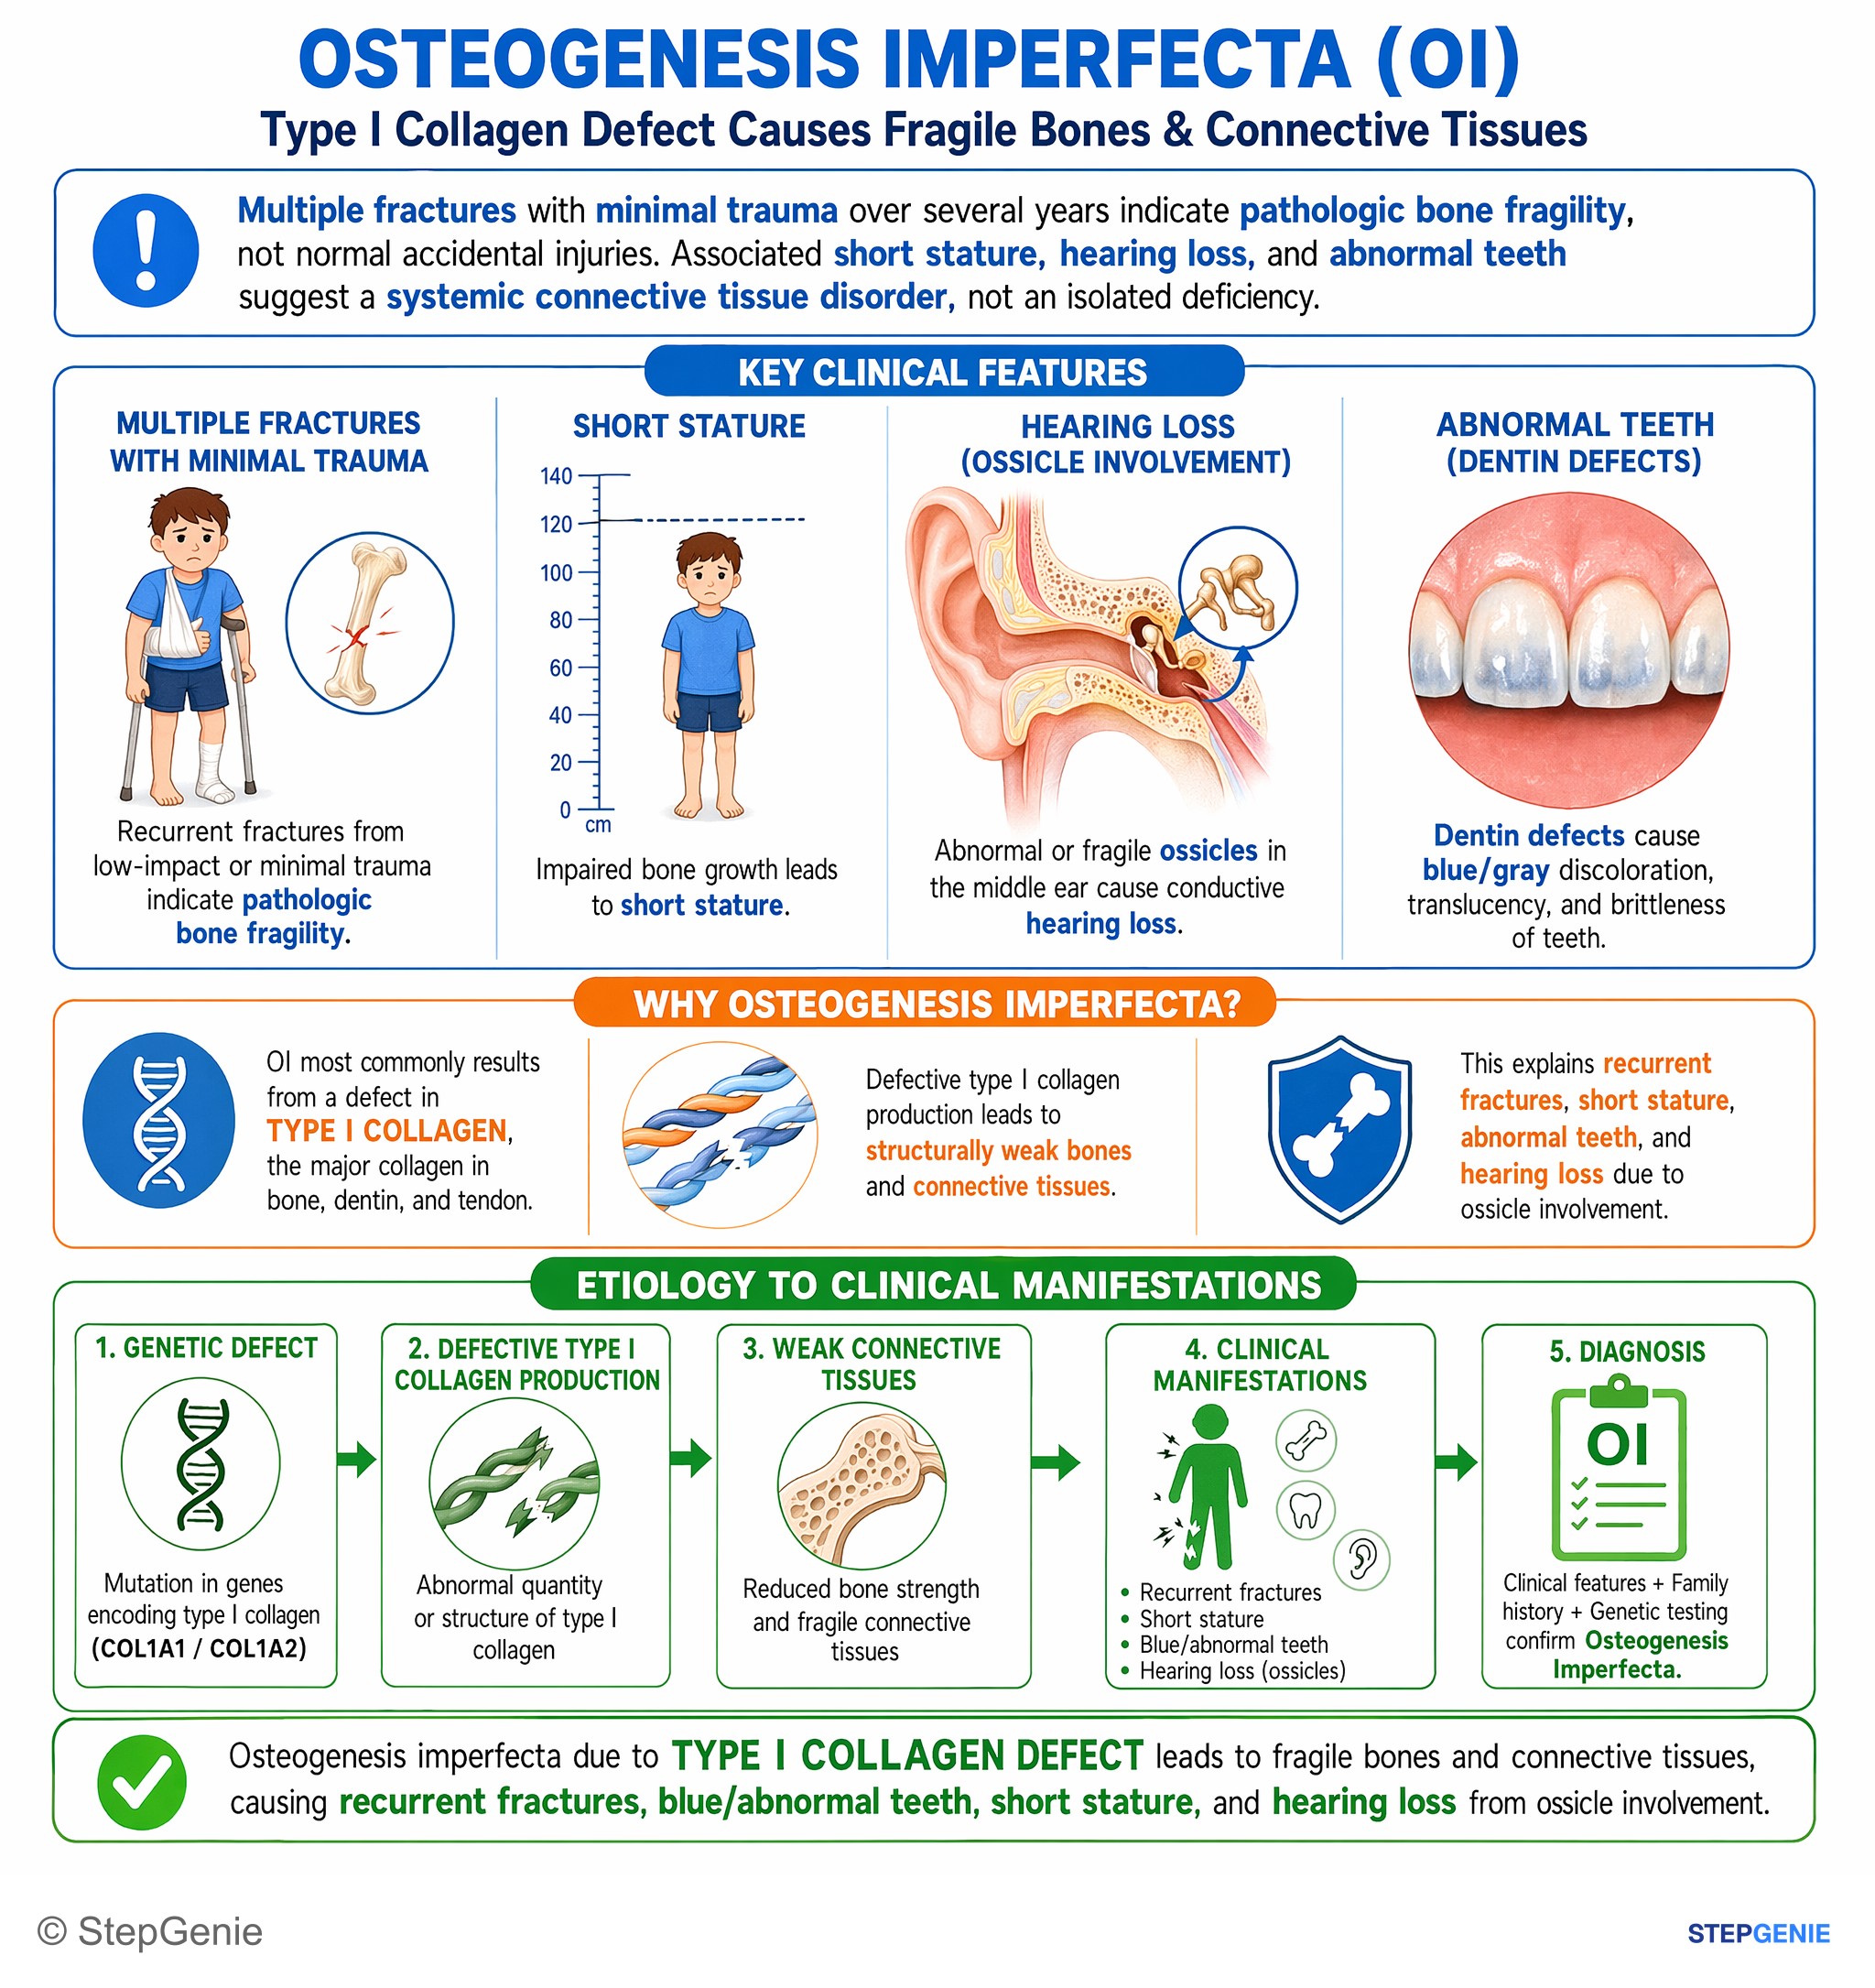
Osteogenesis imperfecta from type I collagen defect → recurrent fractures, blue/abnormal teeth, short stature, and hearing loss due to…
USMLE Step 1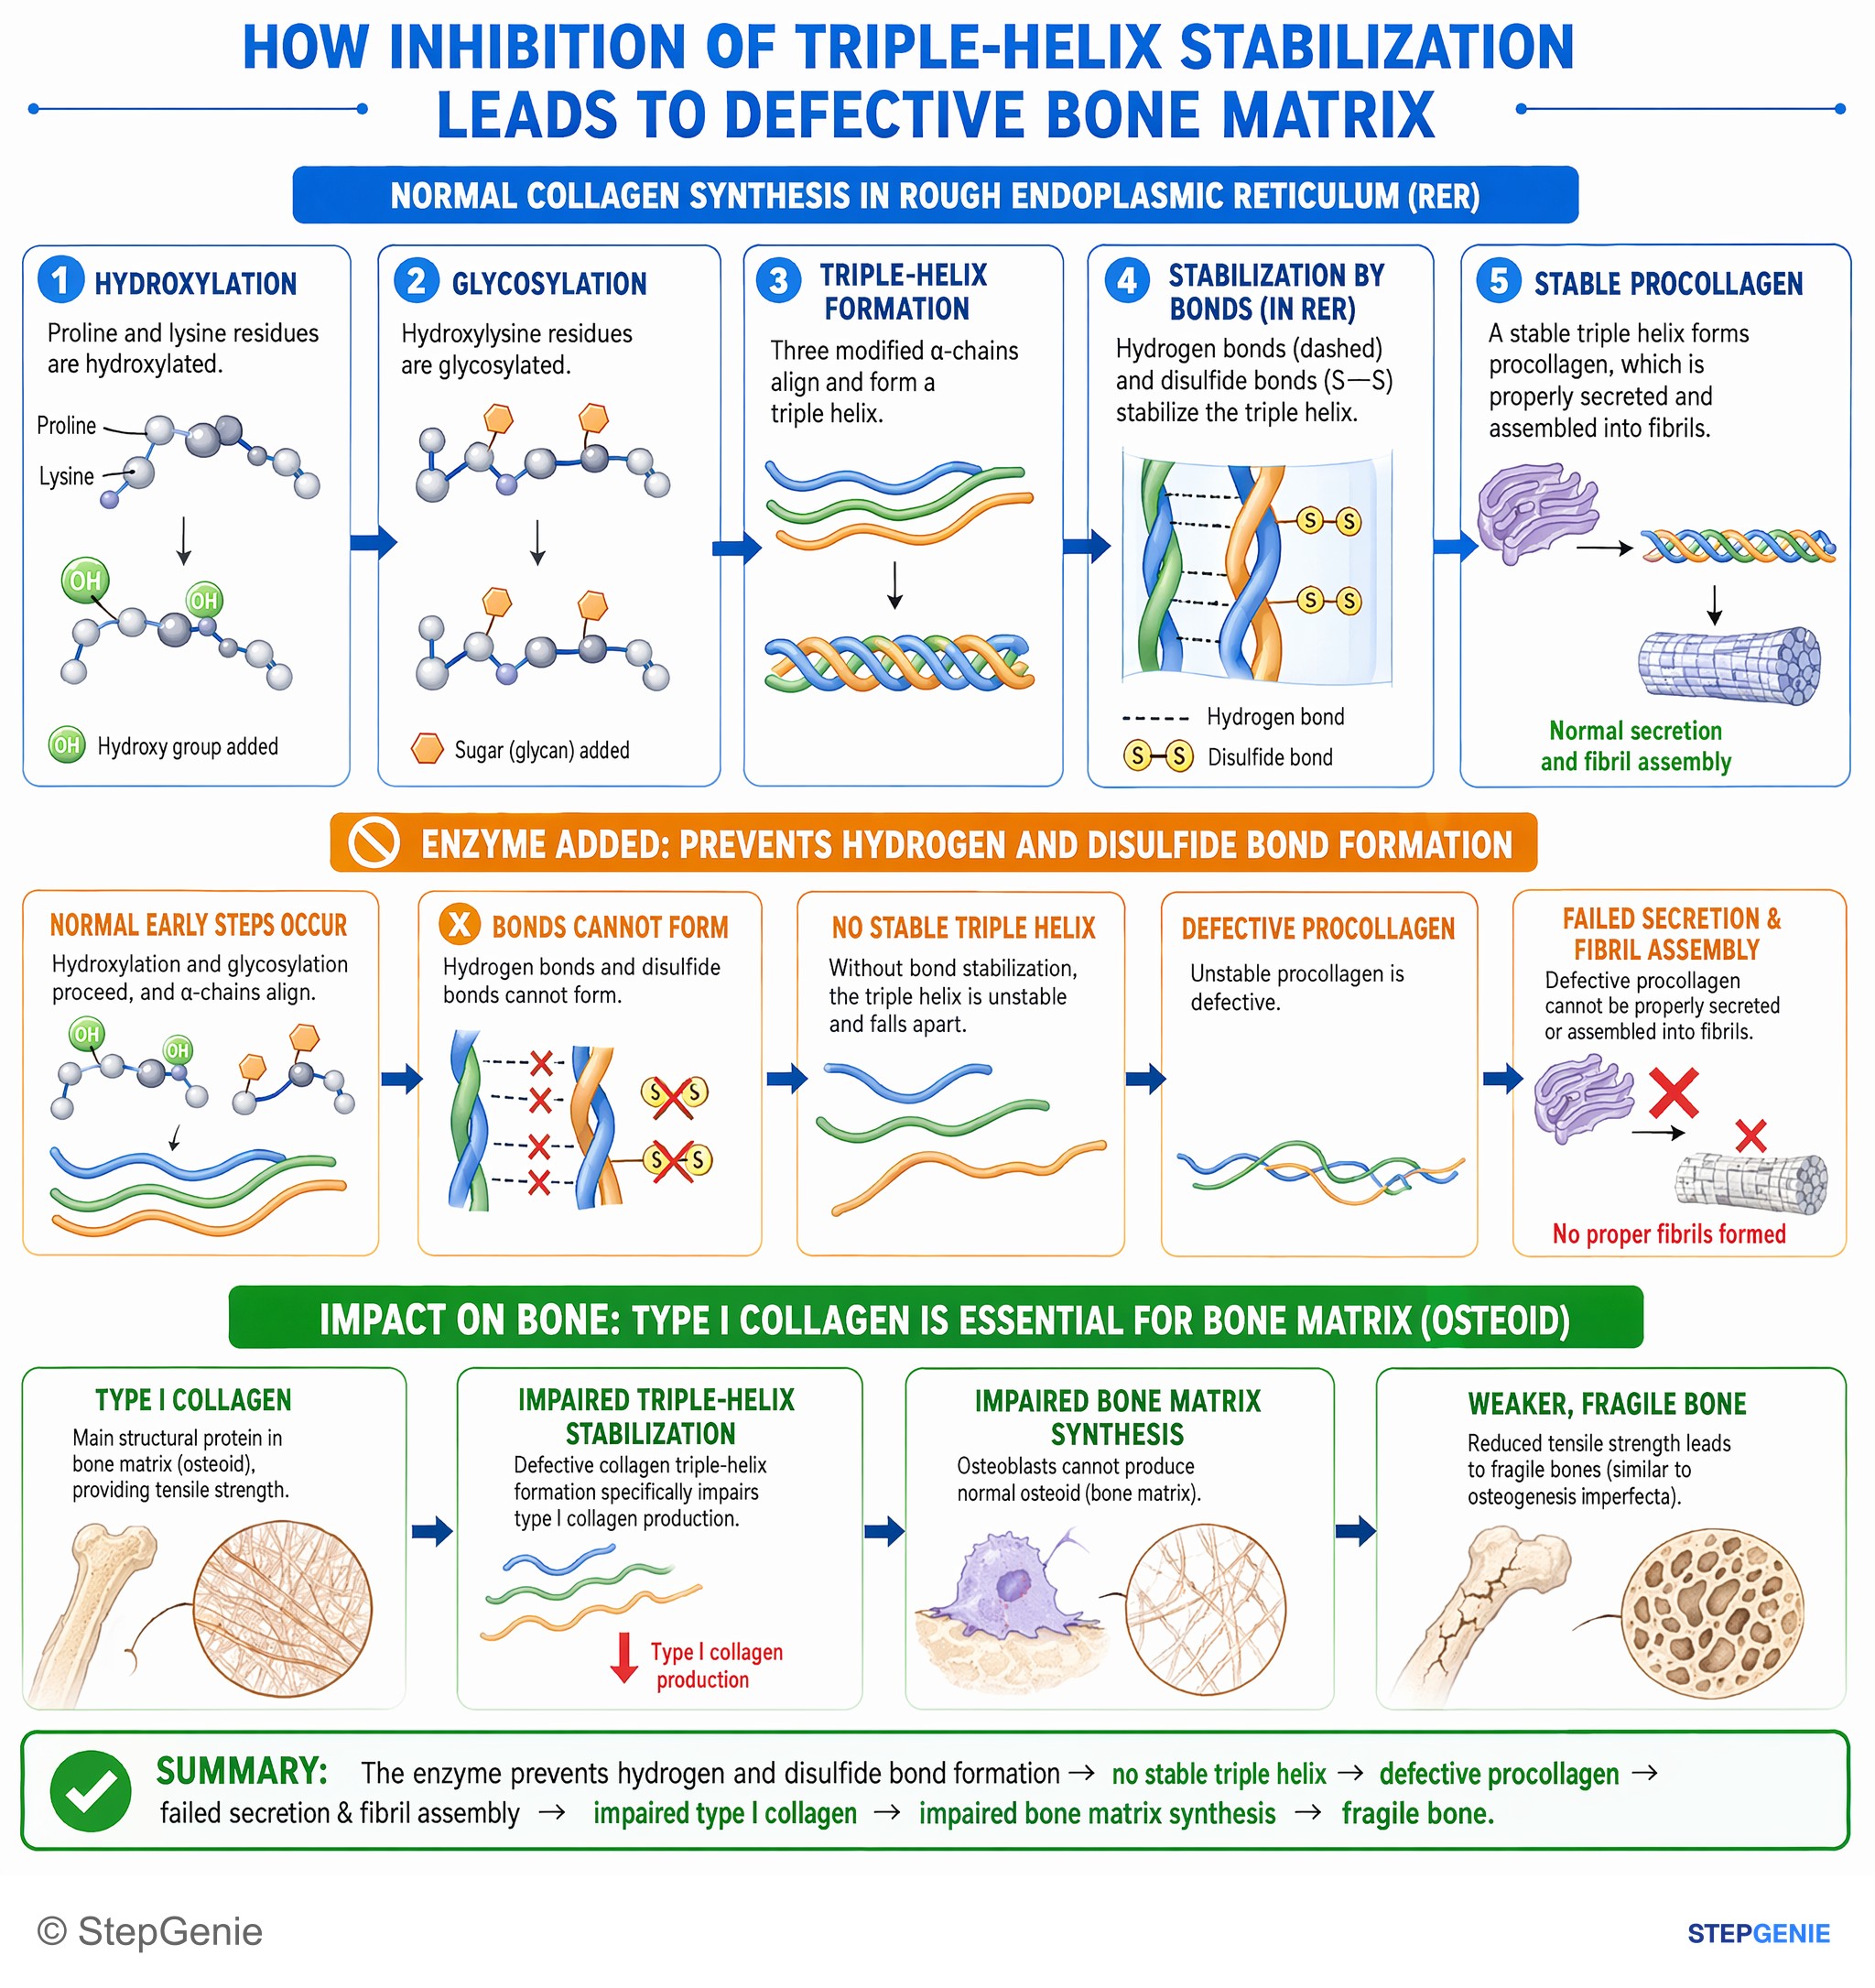
Defective collagen triple-helix formation impairs type I collagen production, leading to impaired bone matrix synthesis (similar to…
USMLE Step 1Frequently Asked Questions
What causes osteogenesis imperfecta?
About 80-90% of cases are caused by autosomal dominant variants in COL1A1 or COL1A2, the genes for the two kinds of chains in type I collagen, the main structural protein of bone. Variants that halve the amount of normal collagen cause mild type I OI, while glycine substitutions that make structurally abnormal collagen cause the more severe types. More than a dozen other genes cause rarer forms, most of them autosomal recessive, and at least one form is X-linked.
Why are the sclerae blue in osteogenesis imperfecta?
The sclera is rich in type I collagen. In OI its connective tissue is deficient, so the underlying vessels show through and the sclera looks blue or gray. Blue or gray sclerae are typical of type I OI and are dark blue in the lethal type II; in type III they are blue in infancy and lighten with age, and in type IV they become near normal soon after birth. Blue sclerae alone cannot separate OI from child abuse.
What are the four main types of osteogenesis imperfecta?
Type I is the mildest and most common: fractures that heal without deformity, blue sclerae, near-normal height and hearing loss in adulthood. Type II is perinatally lethal, with multiple fractures at birth. Type III is the most severe form that survives, with fractures from minimal handling, progressive deformity and very short stature. Type IV is moderate and variable, with near-normal sclerae. At least 19 types are now recognized, most of them rare.
How is osteogenesis imperfecta treated?
Treatment aims to prevent fractures and preserve function. Bisphosphonates, given as IV pamidronate or zoledronic acid in cycles or as oral alendronate, are used to increase bone density and reduce bone pain, fractures and scoliosis, especially in more severe OI. Intramedullary rods stabilize bowed long bones, physical therapy builds strength and mobility, hearing is checked every 3 years from age 5, and vitamin D is given to people who are deficient.
How can you tell osteogenesis imperfecta from child abuse?
It can be hard, because both cause multiple fractures, fractures that do not match the story and fractures of different ages. Fractures that continue after a child leaves a possibly abusive setting support OI, and testing for COL1A1 and COL1A2 variants can confirm it; one study suggested testing only when there are blue sclerae, osteopenia or a positive family history. Metaphyseal and rib fractures strongly suggest abuse but can rarely occur in OI, and blue sclerae alone are unreliable because many unaffected infants have them until about 18 months.
Is hearing loss common in osteogenesis imperfecta?
Yes. GeneReviews reports progressive hearing loss in more than half of adults with type I OI; it is rarely noted in childhood, while in progressively deforming (type III) OI it generally begins in the teenage years. The loss can be conductive, sensorineural or mixed. Hearing is screened every 3 years from age 5 until a loss is found, and hearing aids or, in selected patients, cochlear implants are used.