Thiamine (vitamin B1) works as thiamine pyrophosphate (TPP), the cofactor for pyruvate dehydrogenase, α-ketoglutarate dehydrogenase, branched-chain α-ketoacid dehydrogenase and transketolase. Deficiency causes dry beriberi (symmetric peripheral neuropathy), wet beriberi (high-output heart failure) and Wernicke encephalopathy (confusion, ataxia and eye movement abnormalities), which, if untreated, often leads to Korsakoff syndrome (amnesia with confabulation). The classic patient has alcohol use disorder, but bariatric surgery, hyperemesis gravidarum, starvation and refeeding all qualify. Wernicke is treated on suspicion with IV thiamine, given before glucose or together with it.
Thiamine at a glance
| Item | High-yield answer |
|---|---|
| Active form | Thiamine pyrophosphate (TPP), also called thiamine diphosphate |
| Daily need (RDA) | 1.2 mg for adult men, 1.1 mg for adult women, 1.4 mg in pregnancy and lactation (NIH ODS) |
| Stores | Small, mainly in the liver; short half-life, so intake must be continuous |
| Deficiency syndromes | Dry beriberi, wet beriberi (including Shoshin), infantile beriberi, Wernicke-Korsakoff syndrome |
| Functional test | Erythrocyte transketolase activity (low in deficiency) |
| Emergency treatment | IV thiamine before (or with) glucose, plus magnesium |
The TPP enzymes and what fails without them
| Enzyme | Pathway | Reaction | What deficiency looks like |
|---|---|---|---|
| Pyruvate dehydrogenase (PDH) | Link from glycolysis to the TCA cycle | Pyruvate → acetyl-CoA | Pyruvate backs up into lactate: lactic acidosis, worse after a glucose load |
| α-Ketoglutarate dehydrogenase | TCA cycle | α-Ketoglutarate → succinyl-CoA | Less ATP from the TCA cycle |
| Branched-chain α-ketoacid dehydrogenase (BCKDH) | Breakdown of leucine, isoleucine, valine | Branched-chain α-ketoacids → acyl-CoAs | Inherited BCKDH deficiency is maple syrup urine disease (autosomal recessive) |
| Transketolase | Pentose phosphate (HMP) shunt, nonoxidative arm | Moves 2-carbon units between sugars | Its activity in red cells is the classic lab test for thiamine status |
| 2-Hydroxyacyl-CoA lyase | α-Oxidation of branched-chain fatty acids | Rarely tested |
Mnemonic: "Think ATP + B": Alpha-ketoglutarate DH, Transketolase, Pyruvate DH, plus Branched-chain ketoacid DH. The three dehydrogenase complexes share their cofactor set, so a TPP problem hits all three; see the PDH cofactors mnemonic and the pentose phosphate pathway visual hack.
Why the brain and heart fail first
Thiamine is involved in carbohydrate, fat and amino acid metabolism (Merck). Without it, glucose-derived pyruvate cannot enter the TCA cycle efficiently, ATP falls and lactate rises. Merck describes the damage: degeneration of peripheral nerves, the thalamus, the mammillary bodies and the cerebellum; swollen, fragmented myocardial fibers; and peripheral vasodilation that can cause edema.
The glucose trap. A carbohydrate load raises the demand for thiamine. That is why IV dextrose in a high-risk patient and refeeding after starvation can precipitate Wernicke encephalopathy (Merck; Linus Pauling Institute), and why Merck advises giving thiamine 100 mg IV before IV glucose to people with alcohol use disorder and others at risk. The order matters, but it never justifies withholding glucose from a hypoglycemic patient: thiamine can go in together with the glucose (Medscape: "prior to or concurrently"), or as soon as possible afterward (Australian alcohol treatment guidelines).
Who becomes deficient
- Alcohol use disorder: up to 80% of people with chronic alcoholism develop thiamine deficiency, because ethanol reduces intestinal absorption, liver stores and thiamine phosphorylation (NIH ODS); poor diet adds to it.
- Bariatric surgery (malabsorption), hyperemesis gravidarum, starvation and refeeding syndrome.
- Diets of polished rice or other highly refined carbohydrates (classic beriberi).
- Higher demand or losses: hyperthyroidism, pregnancy, lactation, fever, prolonged diarrhea, recurrent dialysis.
- Cancer and AIDS (Merck), and the groups NIH ODS flags as at risk of inadequacy: older adults, people with HIV/AIDS and people with diabetes.
- Breastfed infants of thiamine-deficient mothers (infantile beriberi).
Beriberi: dry vs wet
| Dry beriberi | Wet beriberi | |
|---|---|---|
| System | Peripheral nerves | Heart and blood vessels |
| Early signs | Paresthesias in the toes, burning feet, calf tenderness, difficulty rising from a squat | Vasodilation, tachycardia, wide pulse pressure, sweating, warm skin, lactic acidosis |
| Progression | Symmetric stocking-glove sensorimotor neuropathy, legs before arms; reduced reflexes and wasting | High-output heart failure: orthopnea, pulmonary and peripheral edema, a dilated heart |
| Severe form | Shoshin beriberi: acute fulminant wet beriberi that can progress to shock | |
| Treatment (Merck) | Mild: 10-20 mg orally daily for 2 weeks; moderate or advanced: 20-30 mg daily, continued for weeks after symptoms resolve | 100 mg IV daily for several days |
Infantile beriberi appears in breastfed infants of thiamine-deficient mothers, usually by 3-4 weeks of age, with heart failure that may come on suddenly, aphonia and absent deep tendon reflexes (Merck).
Exam tip: "warm extremities, bounding pulses and edema" in a malnourished patient is wet beriberi, a high-output failure, not the cold, clamped-down low-output failure of a failing ventricle.
Wernicke encephalopathy
An acute neurologic emergency from thiamine deficiency plus continued carbohydrate intake (Merck).
The classic triad, not always complete:
- Eye findings: horizontal or vertical nystagmus, lateral rectus (abducens) palsy, conjugate gaze palsies, sluggish or unequal pupils
- Ataxia: a wide-based, slow, short-stepped gait
- Confusion: disorientation, apathy and drowsiness, which can progress to stupor and coma
Autonomic signs (hypothermia, postural hypotension, syncope) can join them. Not every patient has all three, so a risk factor plus one or two findings is enough to treat.
Where the lesions are: symmetric, around the third and fourth ventricles and the aqueduct: mammillary bodies, dorsomedial thalamus, periaqueductal gray, locus ceruleus, and the ocular motor and vestibular nuclei (Merck).
Diagnosis is clinical. Thiamine levels are not routinely measured, because serum levels do not always reflect cerebrospinal fluid levels (Merck); labs and imaging mainly rule out other causes. Do not wait for any test before treating.
Treatment:
- IV thiamine immediately. Doses differ between sources: Merck's thiamine chapter (2026) gives 500 mg IV over 30 minutes three times daily for 2 days, then 250 mg IV or IM daily for 5 days, while its Wernicke chapter gives 100 mg IV or IM daily for at least 3-5 days. Australia's alcohol treatment guidelines also use high doses (at least 500 mg a day for at least 3-5 days). Either way, the exam answer is parenteral thiamine now.
- Magnesium, a cofactor thiamine needs to work (Merck: magnesium sulfate 1-2 g IV or IM every 6-8 hours).
- Thiamine before (or with) glucose, then fluids, multivitamins, nutrition and alcohol cessation. For prevention, Merck's alcohol chapter gives intoxicated patients who need IV fluids a single 100 mg IV dose of thiamine.
Prognosis. Eye signs often improve within 24 hours of thiamine; ataxia and confusion can take days to months. Untreated, mortality is 10-20%, and 80% of untreated survivors develop Korsakoff psychosis (Merck). For a memorable way to hold the triad, use the Wernicke-Korsakoff memory palace.
Wernicke vs Korsakoff
| Wernicke encephalopathy | Korsakoff syndrome | |
|---|---|---|
| Timing | Acute | Chronic; follows untreated or undertreated Wernicke |
| Core features | Confusion, ataxia, eye movement abnormalities | Anterograde and retrograde amnesia with confabulation |
| Response to thiamine | Eye signs can improve within a day | Improvement can take 1-3 months and is often incomplete |
| Priority | Emergency IV thiamine | Thiamine, abstinence, long-term support |
Practice question
A 52-year-old man with alcohol use disorder is brought to the emergency department confused and unsteady. He has horizontal nystagmus and a wide-based gait. Labs show an anion gap metabolic acidosis with a raised lactate. He is given IV dextrose, and over the next hour his confusion worsens. Reduced activity of which enzyme best explains the lactic acidosis and his worsening after glucose?
A. Lactate dehydrogenase B. Methylmalonyl-CoA mutase C. Pyruvate carboxylase D. Pyruvate dehydrogenase E. Transketolase
Answer: D. This is Wernicke encephalopathy from thiamine deficiency. PDH needs TPP to turn pyruvate into acetyl-CoA. When it fails, a glucose load pushes more pyruvate into a blocked gateway, so pyruvate is diverted to lactate and brain energy failure worsens. He needs IV thiamine now, before any more glucose.
- A. Lactate dehydrogenase is not deficient; it is the escape route. It converts the backed-up pyruvate to lactate, which is why lactate rises.
- B. Methylmalonyl-CoA mutase needs vitamin B12, not thiamine. B12 deficiency brings megaloblastic anemia and neurologic changes such as numbness and tingling in the hands and feet, with raised methylmalonic acid and homocysteine (NIH ODS). Compare the subacute combined degeneration flowchart.
- C. Pyruvate carboxylase needs biotin; it is one of biotin's carboxylases, alongside propionyl-CoA and acetyl-CoA carboxylase. Its deficiency can also raise lactate, but nothing in this stem points to biotin, and the glucose-triggered decline is a thiamine story. Biotin deficiency (raw egg whites: avidin blocks absorption) causes thinning hair, a scaly red rash around the eyes, nose and mouth, and paresthesias. See the biotin guide.
- E. Transketolase is also TPP-dependent and is reduced here too, but it works in the pentose phosphate pathway and does not explain lactate building up after glucose. Pick it when the stem asks how to test thiamine status (erythrocyte transketolase activity).
How USMLE tests it
- Alcohol use disorder + confusion + ataxia + nystagmus = Wernicke: give IV thiamine before (or with) glucose.
- Same patient days after fast correction of low sodium, with dysarthria and quadriparesis = osmotic demyelination, not Wernicke (see central pontine myelinolysis).
- Malnourished patient with edema, warm skin and tachycardia = wet beriberi (high-output failure).
- Burning feet and symmetric distal neuropathy in someone without diabetes = dry beriberi.
- Lactic acidosis worse after glucose = PDH; "how do you confirm it?" = erythrocyte transketolase activity.
- Amnesia with confabulation after an episode like this = Korsakoff (mammillary bodies, thalamus).
Key takeaways
- TPP is the cofactor for PDH, α-KG dehydrogenase, BCKDH and transketolase ("ATP + B").
- Dry beriberi = symmetric stocking-glove neuropathy with burning feet; wet beriberi = high-output heart failure with vasodilation, warm skin and edema; Shoshin = fulminant wet beriberi with shock.
- Wernicke = confusion, ataxia, nystagmus or ophthalmoplegia; the triad is not always complete, so treat on suspicion.
- Lesions: mammillary bodies, dorsomedial thalamus, periaqueductal gray.
- IV thiamine before or with glucose (never hold glucose from a hypoglycemic patient), plus magnesium; ocular signs can improve within 24 hours.
- Untreated Wernicke: 10-20% mortality, and 80% of survivors develop Korsakoff (anterograde and retrograde amnesia, confabulation).
- Risk groups: alcohol use disorder (up to 80% deficient), bariatric surgery, hyperemesis, starvation and refeeding, polished-rice diets.
Sources
- Thiamin Deficiency — Merck Manual Professional Edition (2026)
- Wernicke Encephalopathy — Merck Manual Professional Edition (2025)
- Thiamin: Fact Sheet for Health Professionals — NIH Office of Dietary Supplements (2023)
- Thiamin — Linus Pauling Institute Micronutrient Information Center, Oregon State University (2021)
- Alcohol Toxicity and Withdrawal — Merck Manual Professional Edition (2025)
- Wernicke Encephalopathy Treatment & Management — Medscape Reference (2018)
- Preventing and Treating Wernicke's Encephalopathy — Guidelines for the Treatment of Alcohol Problems (Australia)
- Maple syrup urine disease — MedlinePlus Genetics
- Biotin: Fact Sheet for Health Professionals — NIH Office of Dietary Supplements (2022)
- Vitamin B12: Fact Sheet for Health Professionals — NIH Office of Dietary Supplements (2025)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
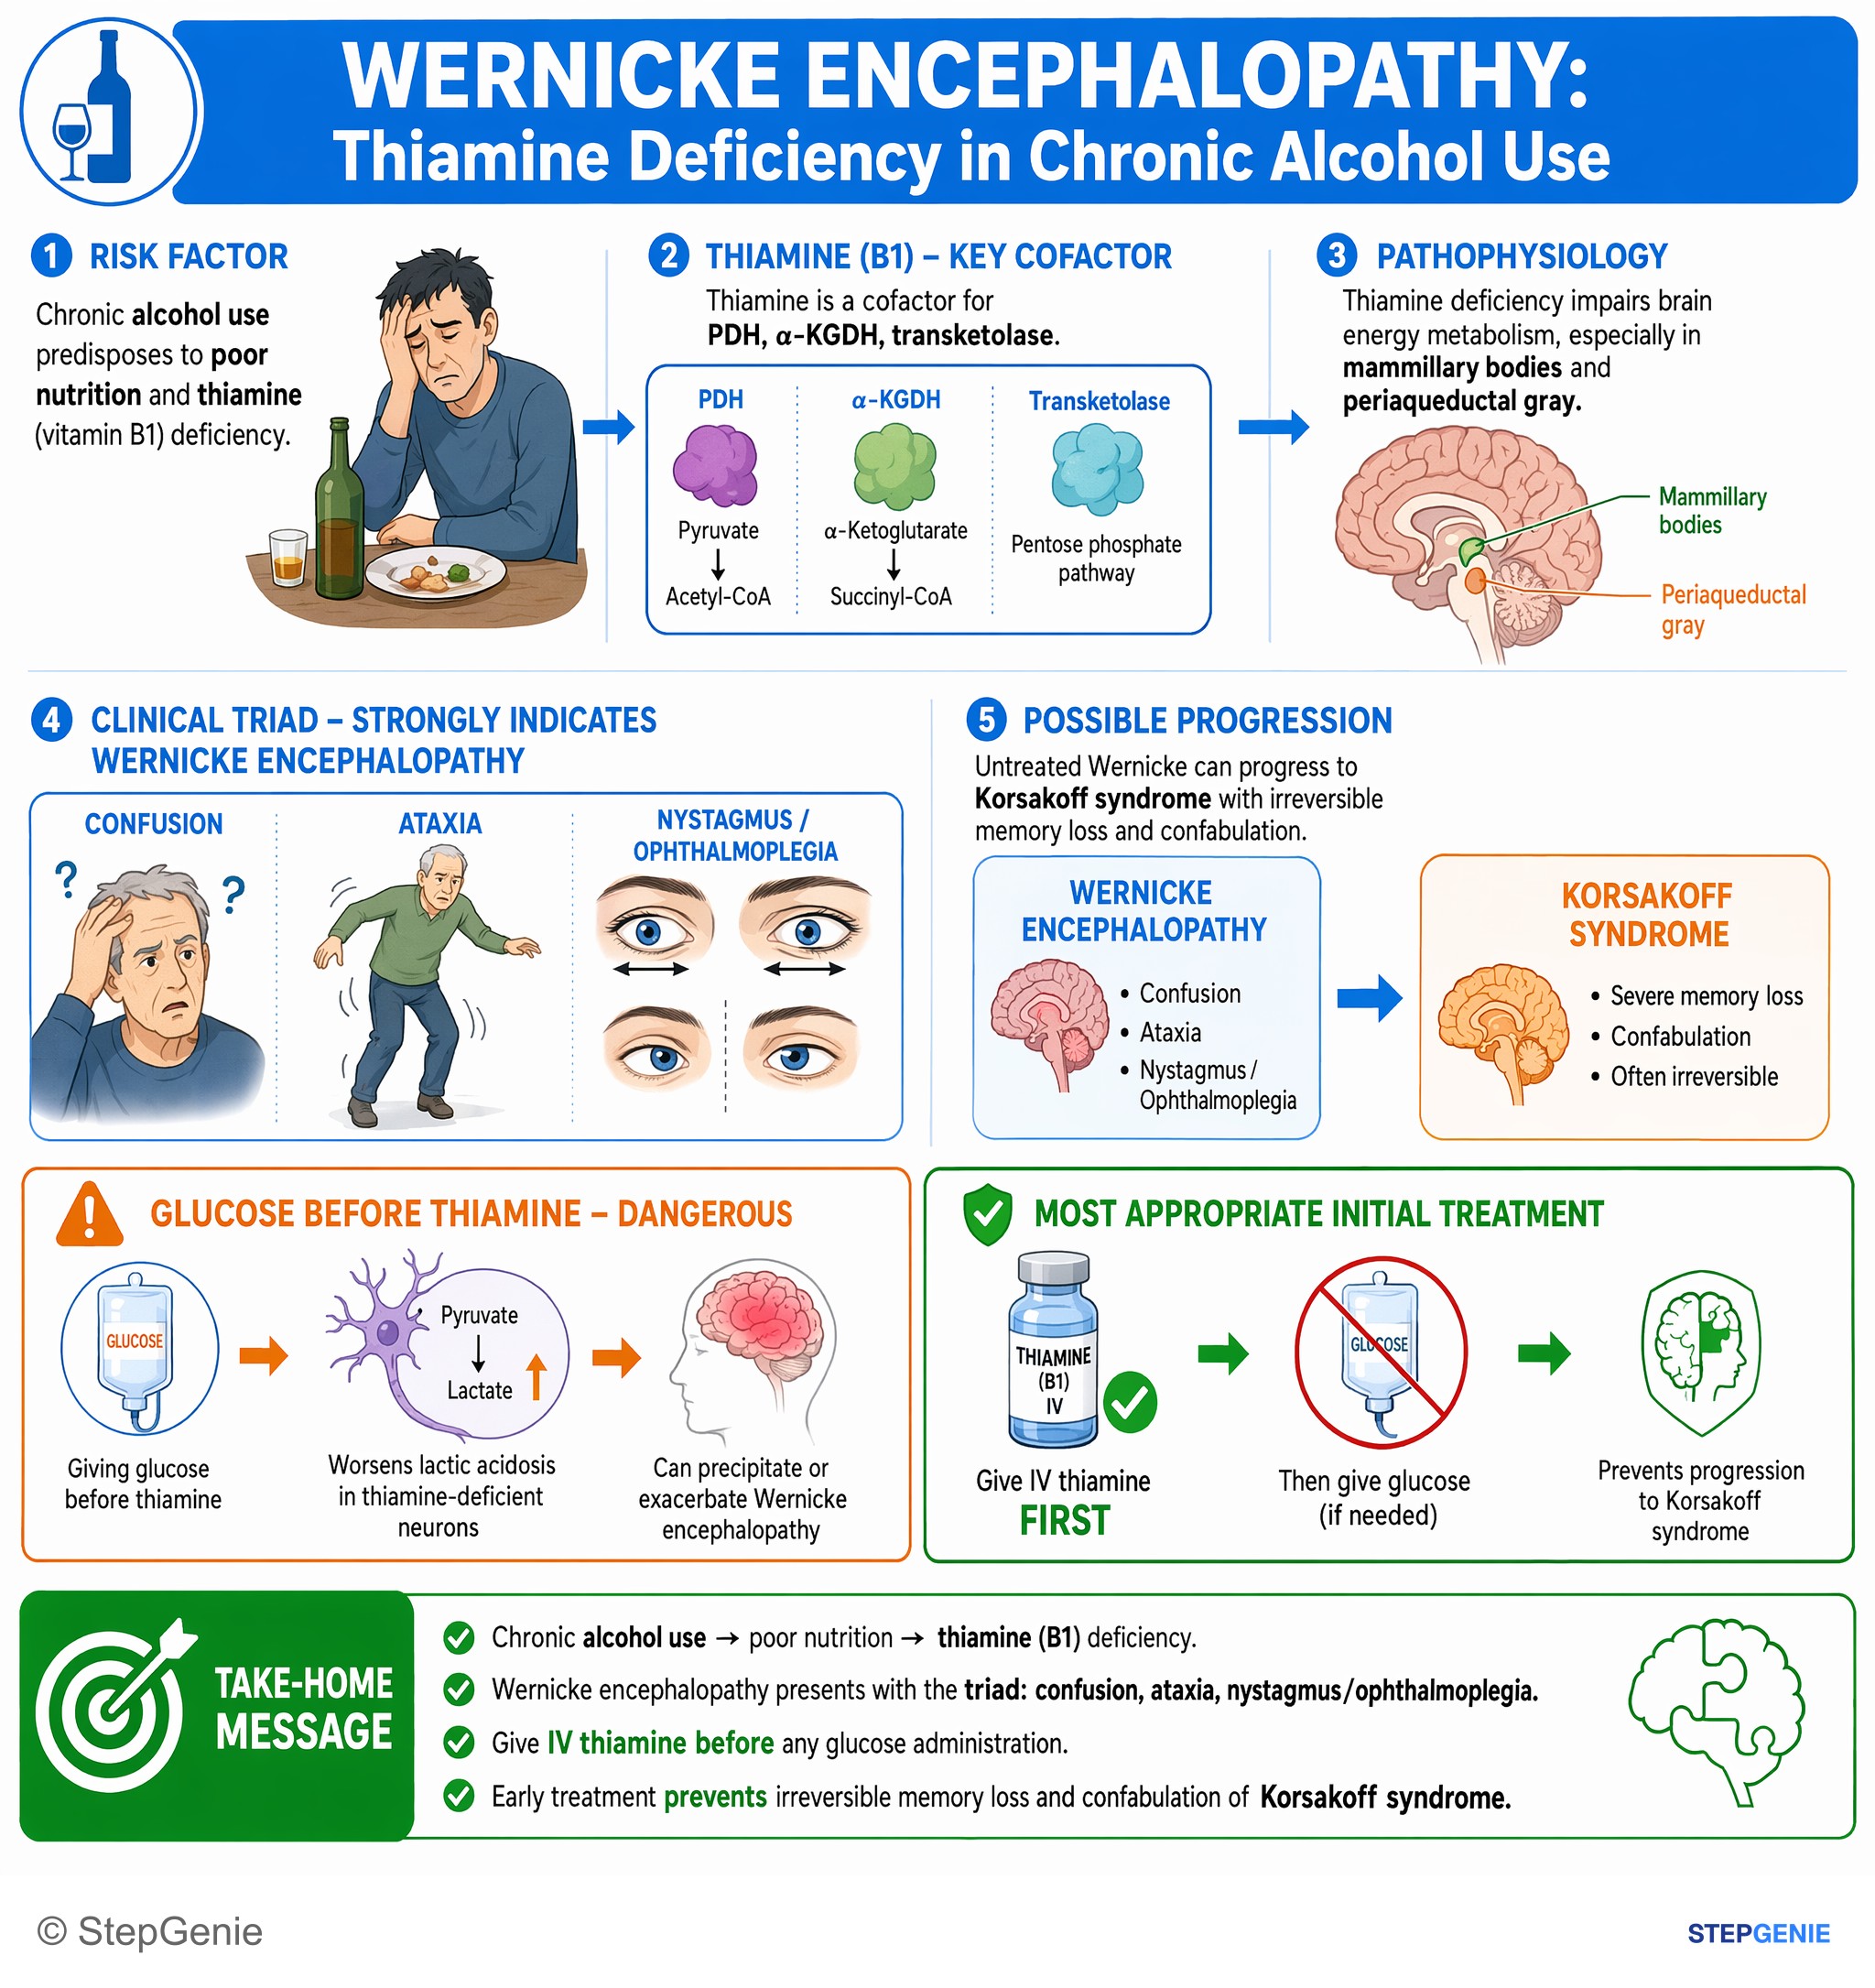
Wernicke encephalopathy from thiamine deficiency in an alcoholic: confusion, ataxia, nystagmus/ophthalmoplegia. Give IV thiamine before…
USMLE Step 2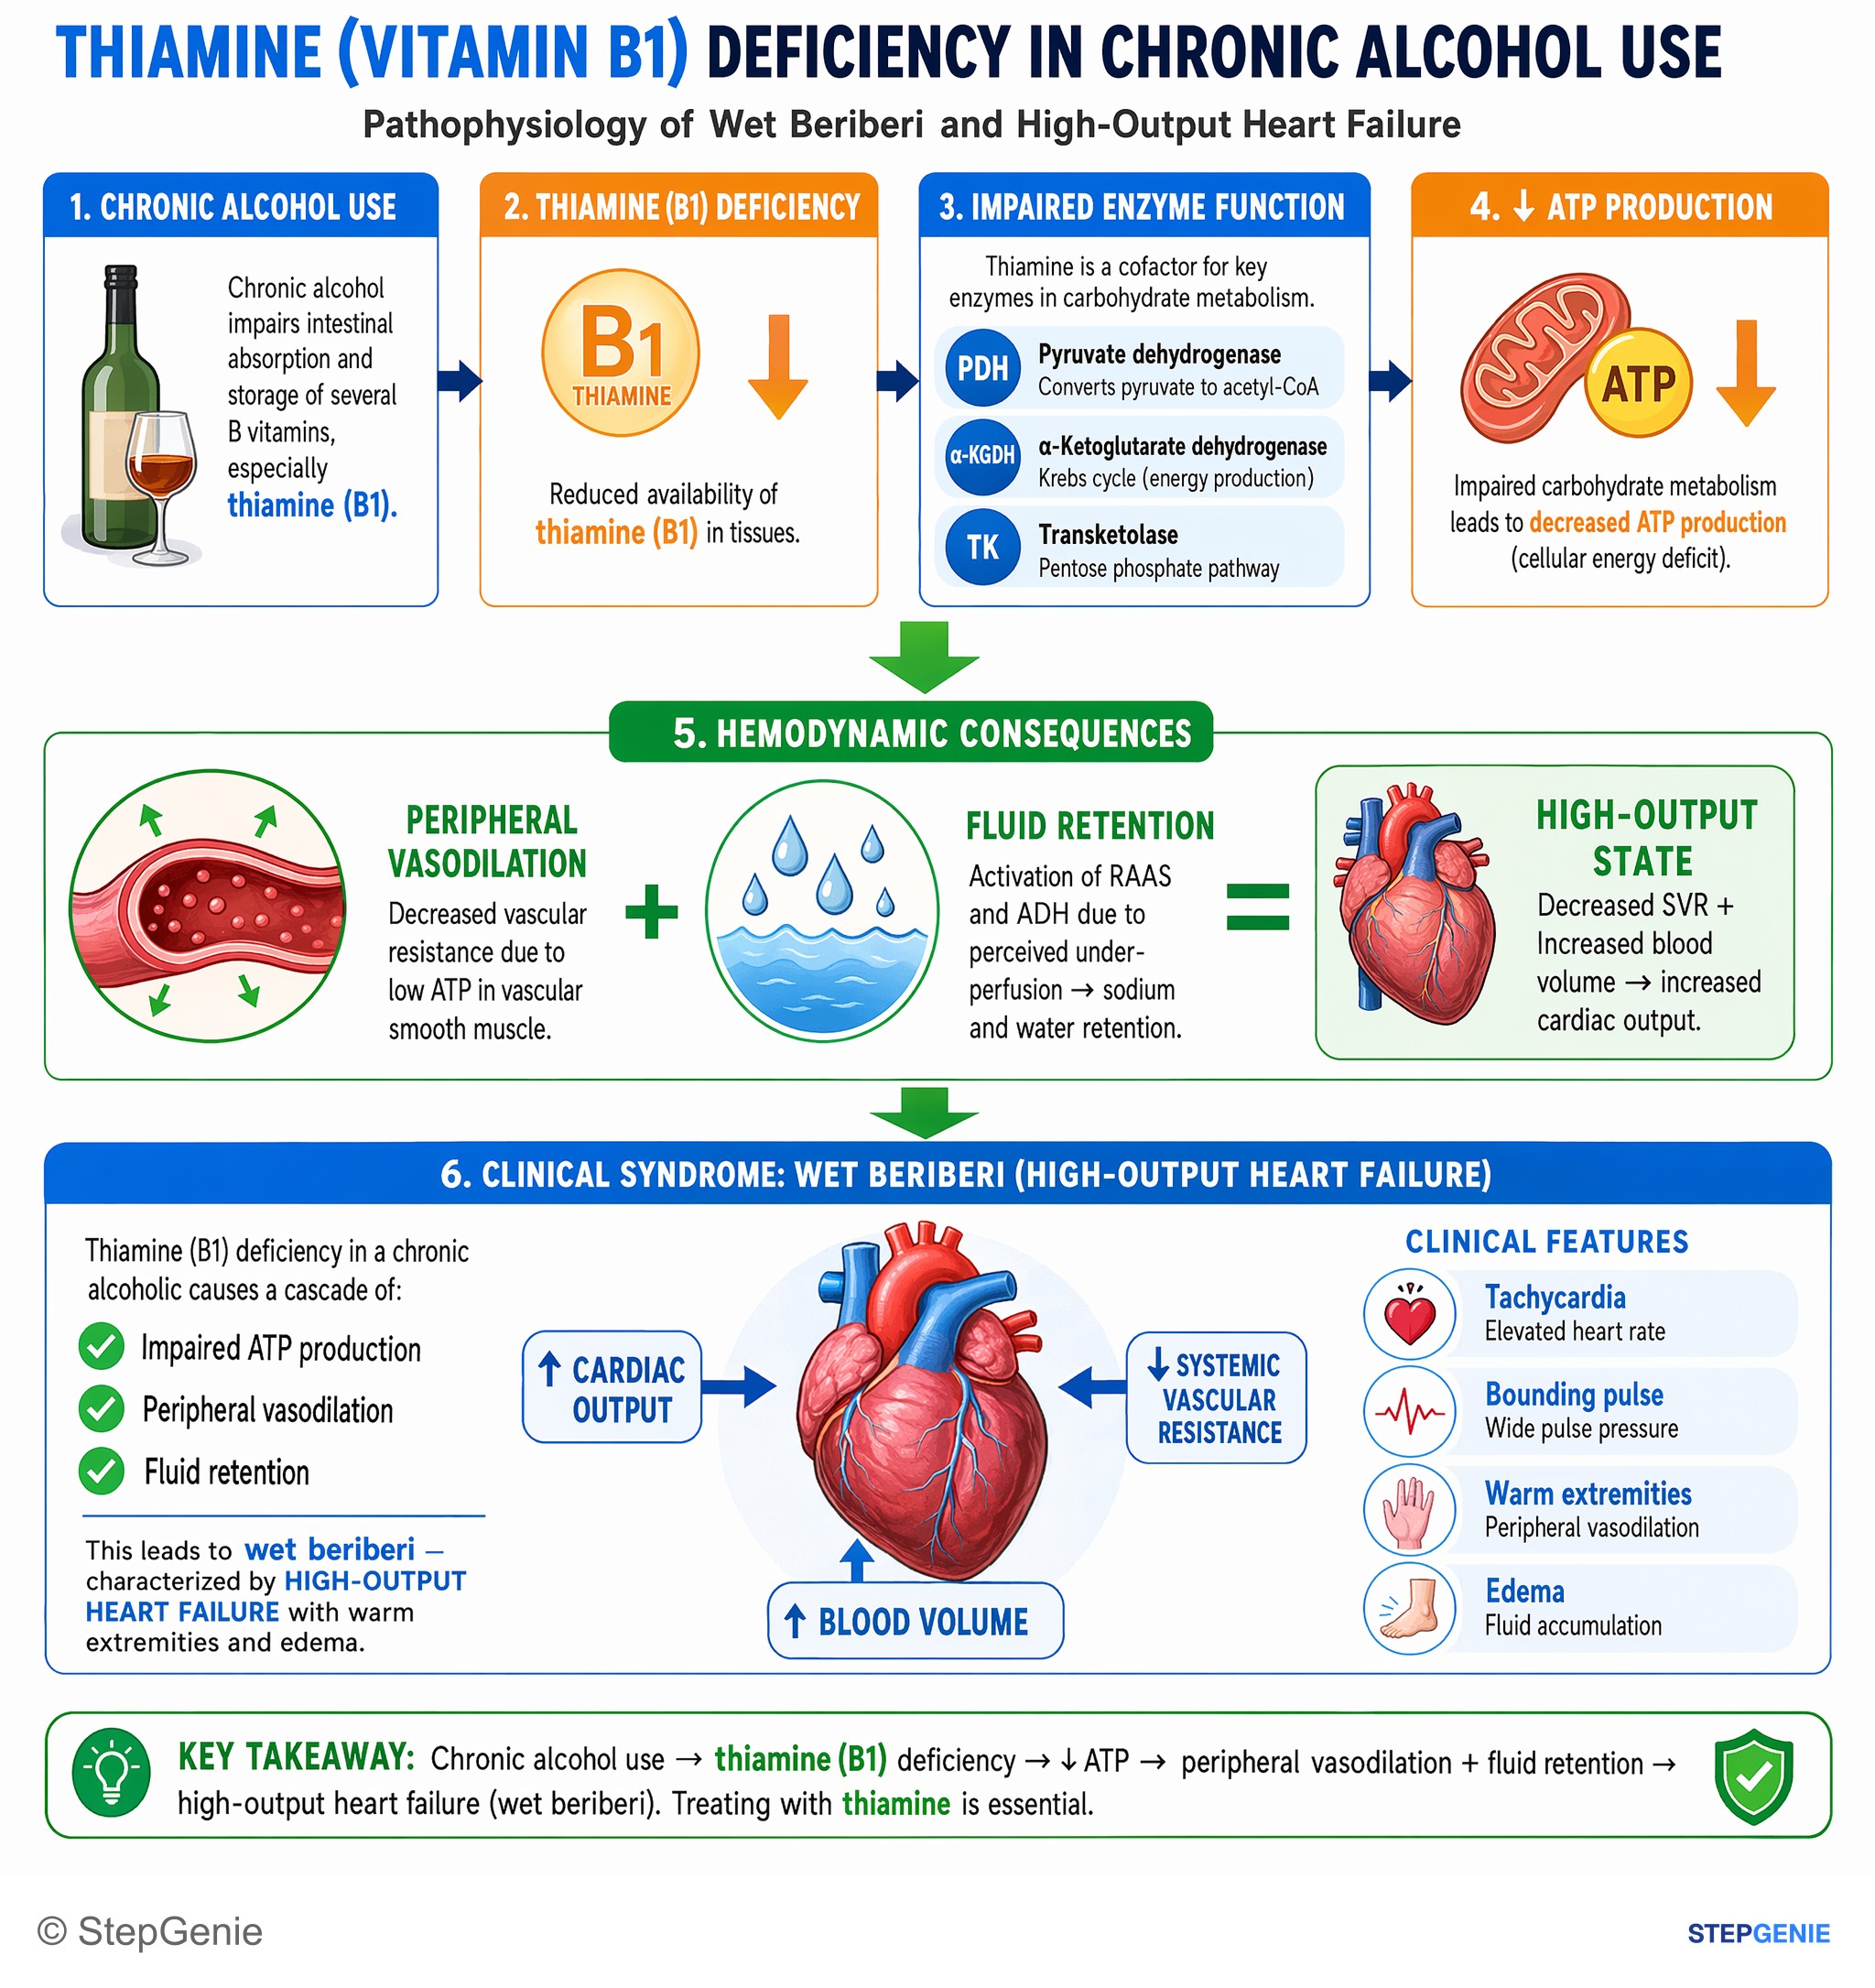
Wet beriberi from thiamine (B1) deficiency in a chronic alcoholic causes peripheral vasodilation and high-output heart failure with warm…
USMLE Step 1Frequently Asked Questions
What enzymes require thiamine?
Thiamine works as thiamine pyrophosphate (TPP), the cofactor for pyruvate dehydrogenase, which links glycolysis to the TCA cycle; alpha-ketoglutarate dehydrogenase in the TCA cycle; branched-chain alpha-ketoacid dehydrogenase, which breaks down leucine, isoleucine and valine; and transketolase in the pentose phosphate pathway. It also serves 2-hydroxyacyl-CoA lyase in alpha-oxidation of branched-chain fatty acids. A common memory aid is ATP + B: alpha-ketoglutarate dehydrogenase, transketolase, pyruvate dehydrogenase, plus branched-chain ketoacid dehydrogenase.
What is the difference between wet and dry beriberi?
Dry beriberi is the neurologic form: a symmetric, stocking-glove peripheral neuropathy that starts with tingling toes and burning feet, calf tenderness and trouble rising from a squat, and spreads from the legs to the arms. Wet beriberi is the cardiovascular form: vasodilation, tachycardia, a wide pulse pressure, warm skin and lactic acidosis, progressing to high-output heart failure with edema. Shoshin beriberi is a fulminant wet form that can cause shock.
What are the symptoms of Wernicke encephalopathy?
The classic triad is eye movement abnormalities (nystagmus, lateral rectus palsy or conjugate gaze palsy), a wide-based ataxic gait, and confusion with apathy and drowsiness that can progress to coma. Not every patient has all three, so an at-risk patient with one or two of these findings should be treated. The lesions sit around the third and fourth ventricles and the aqueduct, including the mammillary bodies, dorsomedial thalamus and periaqueductal gray.
Why do you give thiamine before glucose?
Glucose metabolism runs through thiamine-dependent enzymes, especially pyruvate dehydrogenase, so a carbohydrate load raises the demand for thiamine. In a patient whose stores are already low, IV dextrose or refeeding can trigger or worsen Wernicke encephalopathy. That is why at-risk patients, such as those with alcohol use disorder or malnutrition, receive IV thiamine before glucose. A hypoglycemic patient still gets glucose without delay; the thiamine goes in with it or as soon as possible afterward.
How is Wernicke encephalopathy treated?
Treat on suspicion with parenteral thiamine, without waiting for tests. Merck's thiamine chapter gives 500 mg IV three times daily for 2 days, then 250 mg IV or IM daily for 5 days, while its Wernicke chapter gives 100 mg IV or IM daily for at least 3 to 5 days. Magnesium is replaced too, thiamine goes in before or with any glucose, and nutrition support and alcohol cessation follow. Eye signs often improve within 24 hours.
What is Korsakoff syndrome?
Korsakoff syndrome is the chronic memory disorder that follows untreated or inadequately treated Wernicke encephalopathy. Patients have anterograde and retrograde amnesia and confabulate to fill the gaps in memory. According to Merck, about 80% of untreated survivors of Wernicke encephalopathy develop it. Improvement with thiamine and abstinence can take 1 to 3 months and is often incomplete, so treating Wernicke early is the real prevention.