Fat-soluble vitamins are classic USMLE bait because they travel together (with fat), fail together (in malabsorption), and show up together in “weird bruising + night blindness” style stems. Here’s a one-page, shareable cheat sheet for A, D, E, K with mnemonics, one-liners, and the highest-yield associations.
The Big Picture (What makes ADEK “fat-soluble”?)
Key rule: A, D, E, K are absorbed with dietary fat and require bile salts → problems when fat absorption is impaired.
High-yield causes of deficiency (think: “can’t absorb fat”):
- Pancreatic insufficiency (e.g., cystic fibrosis, chronic pancreatitis) → low lipase
- Cholestasis / biliary obstruction (e.g., gallstones, PBC/PSC) → low bile salts
- Celiac disease or other small bowel malabsorption
- Orlistat (blocks pancreatic lipases) → ADEK deficiency risk
- Bariatric surgery (malabsorptive procedures)
Storage: Fat-soluble vitamins are stored in the liver and adipose → deficiencies develop more slowly than water-soluble ones (but toxicity risk is higher, especially A and D).
Visual / Mnemonic Device (fast recall)
“A DEK” = A is DEKing out your body
- A = A vision/epithelium (“Aye!”)
- D = D bones (calcium/phosphate)
- E = Erythrocytes & neurons (oxidative protection)
- K = Klotting (coagulation)
One-liner anchor:
“ADEK need fat to get in; if fat can’t get absorbed, neither can ADEK.”
One-Page Table: What each vitamin does, deficiency, and classic USMLE clues
| Vitamin | Key functions (Step-friendly) | Deficiency = what you see | Toxicity = what you see | High-yield notes |
|---|---|---|---|---|
| A (Retinol/Retinal/Retinoic acid) | Vision (11-cis-retinal in rhodopsin), epithelial differentiation, immune function | Night blindness, xerophthalmia, Bitot spots, hyperkeratosis, ↑ infection risk | Teratogenicity, dry skin, hepatotoxicity, pseudotumor cerebri | Isotretinoin = vitamin A derivative (acne) → teratogenic |
| D (Cholecalciferol/Ergocalciferol → Calcitriol) | ↑ Ca and PO absorption in gut; bone mineralization; PTH interplay | Rickets (kids), osteomalacia (adults); bone pain, fractures | Hypercalcemia: stones, constipation, confusion; soft tissue calcification | Sunlight converts precursor in skin; kidney activates to calcitriol |
| E (α-tocopherol) | Antioxidant: protects cell membranes from oxidative damage | Hemolytic anemia, acanthocytosis; posterior column/spinocerebellar signs, peripheral neuropathy | Rare; may ↑ bleeding risk | Think: RBCs + neurons are oxidation-sensitive |
| K (Phylloquinone/Menaquinone) | γ-carboxylation of glutamate on clotting factors → binds Ca | Bleeding, ↑ PT/INR, easy bruising | Rare | Needed for factors II, VII, IX, X, C, S (“1972 + C&S”) |
Vitamin A (Retinoids): “Vision + epithelium”
The one-liner
Vitamin A keeps you seeing at night and keeps epithelium from turning into dry, keratinized pavement.
Highest-yield facts
- 11-cis-retinal is part of rhodopsin in rods → low A = night blindness (often the earliest clue).
- Deficiency causes:
- Xerophthalmia (dry eyes)
- Bitot spots (foamy, keratinized conjunctival plaques)
- Hyperkeratosis
- ↑ susceptibility to infections (impaired mucosal barriers, immune function)
- Toxicity (classic Step association):
- Teratogenic (important: pregnancy counseling)
- Hepatotoxicity
- Pseudotumor cerebri (increased intracranial pressure symptoms)
Stem triggers
- “Child with poor diet + trouble seeing in dim light”
- “Dry eyes + foamy conjunctival patches”
Vitamin D: “Build bone; regulate calcium/phosphate”
The one-liner
Vitamin D raises calcium and phosphate absorption to mineralize bone—too little bends bones; too much calcifies everything.
Pathway (USMLE-level)
- Skin: UV converts precursor → cholecalciferol (D3)
- Liver: 25-hydroxylation → 25-OH D
- Kidney: 1α-hydroxylation → 1,25-(OH) D (calcitriol)
Stimulated by PTH and low phosphate (classically tested)
Deficiency findings
- Rickets (kids): bone deformities, bowed legs, rachitic rosary
- Osteomalacia (adults): bone pain, fractures, low mineralization
Toxicity
- Hypercalcemia symptoms: kidney stones, abdominal pain/constipation, neuropsychiatric changes
- Can cause soft tissue calcifications
Stem triggers
- “Dark-skinned person, little sun exposure, bone pain”
- “Chronic kidney disease + bone issues” (impaired activation)
Vitamin E: “Antioxidant for RBCs and neurons”
The one-liner
Vitamin E protects membranes from oxidative damage—without it, RBCs pop and long tracts malfunction.
Deficiency = 2 buckets
- Hematologic: hemolytic anemia, fragile RBCs (oxidative damage)
- Neurologic: posterior column/spinocerebellar signs
- Ataxia
- Loss of vibration/proprioception
- Peripheral neuropathy
Stem triggers
- “Premature infant” (limited stores) or “fat malabsorption + neuro symptoms”
- “Hemolysis with acanthocytes” (membrane abnormalities)
Vitamin K: “Clotting factor activation”
The one-liner
Vitamin K activates clotting factors via γ-carboxylation—low K means you can’t clot, so PT/INR rises.
Must-know list
Vitamin K–dependent factors: II, VII, IX, X, protein C, protein S
Mnemonic: “1972 + C&S” (as in years, not labs)
Mechanism tested on Step
- Vitamin K is a cofactor for γ-glutamyl carboxylase → adds carboxyl groups so factors can bind Ca and attach to phospholipid surfaces.
Deficiency scenarios
- Newborns: sterile gut (no bacterial synthesis) + low vitamin K in breast milk → hemorrhagic disease of newborn
→ prevent with vitamin K injection - Broad-spectrum antibiotics: wipe out gut flora (less menaquinone)
- Fat malabsorption: obstructive jaundice, pancreatic insufficiency
Drug tie-ins (very testable)
- Warfarin inhibits vitamin K epoxide reductase → ↓ active vitamin K → ↑ PT/INR
- Warfarin effect is first seen with protein C decline (short half-life) → transient hypercoagulability early.
Rapid-Fire USMLE Associations (quick review bullets)
- Fat malabsorption → deficiency of ADEK (think biliary obstruction, CF, celiac, orlistat).
- Night blindness + Bitot spots → Vitamin A deficiency
- Bone pain + fractures + low sunlight/CKD → Vitamin D deficiency
- Hemolytic anemia + neuro signs in malabsorption → Vitamin E deficiency
- Bleeding + ↑ PT/INR (especially newborn/antibiotics/cholestasis) → Vitamin K deficiency
- Toxicity risks: mainly A and D (stored, accumulate)
Mini Self-Check (30 seconds)
- Patient with CF develops neuropathy and hemolysis → which vitamin? E
- Newborn bleeding without prophylaxis → which vitamin? K
- Night blindness and xerophthalmia → which vitamin? A
- Osteomalacia in CKD → which vitamin pathway impaired? D activation in kidney
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
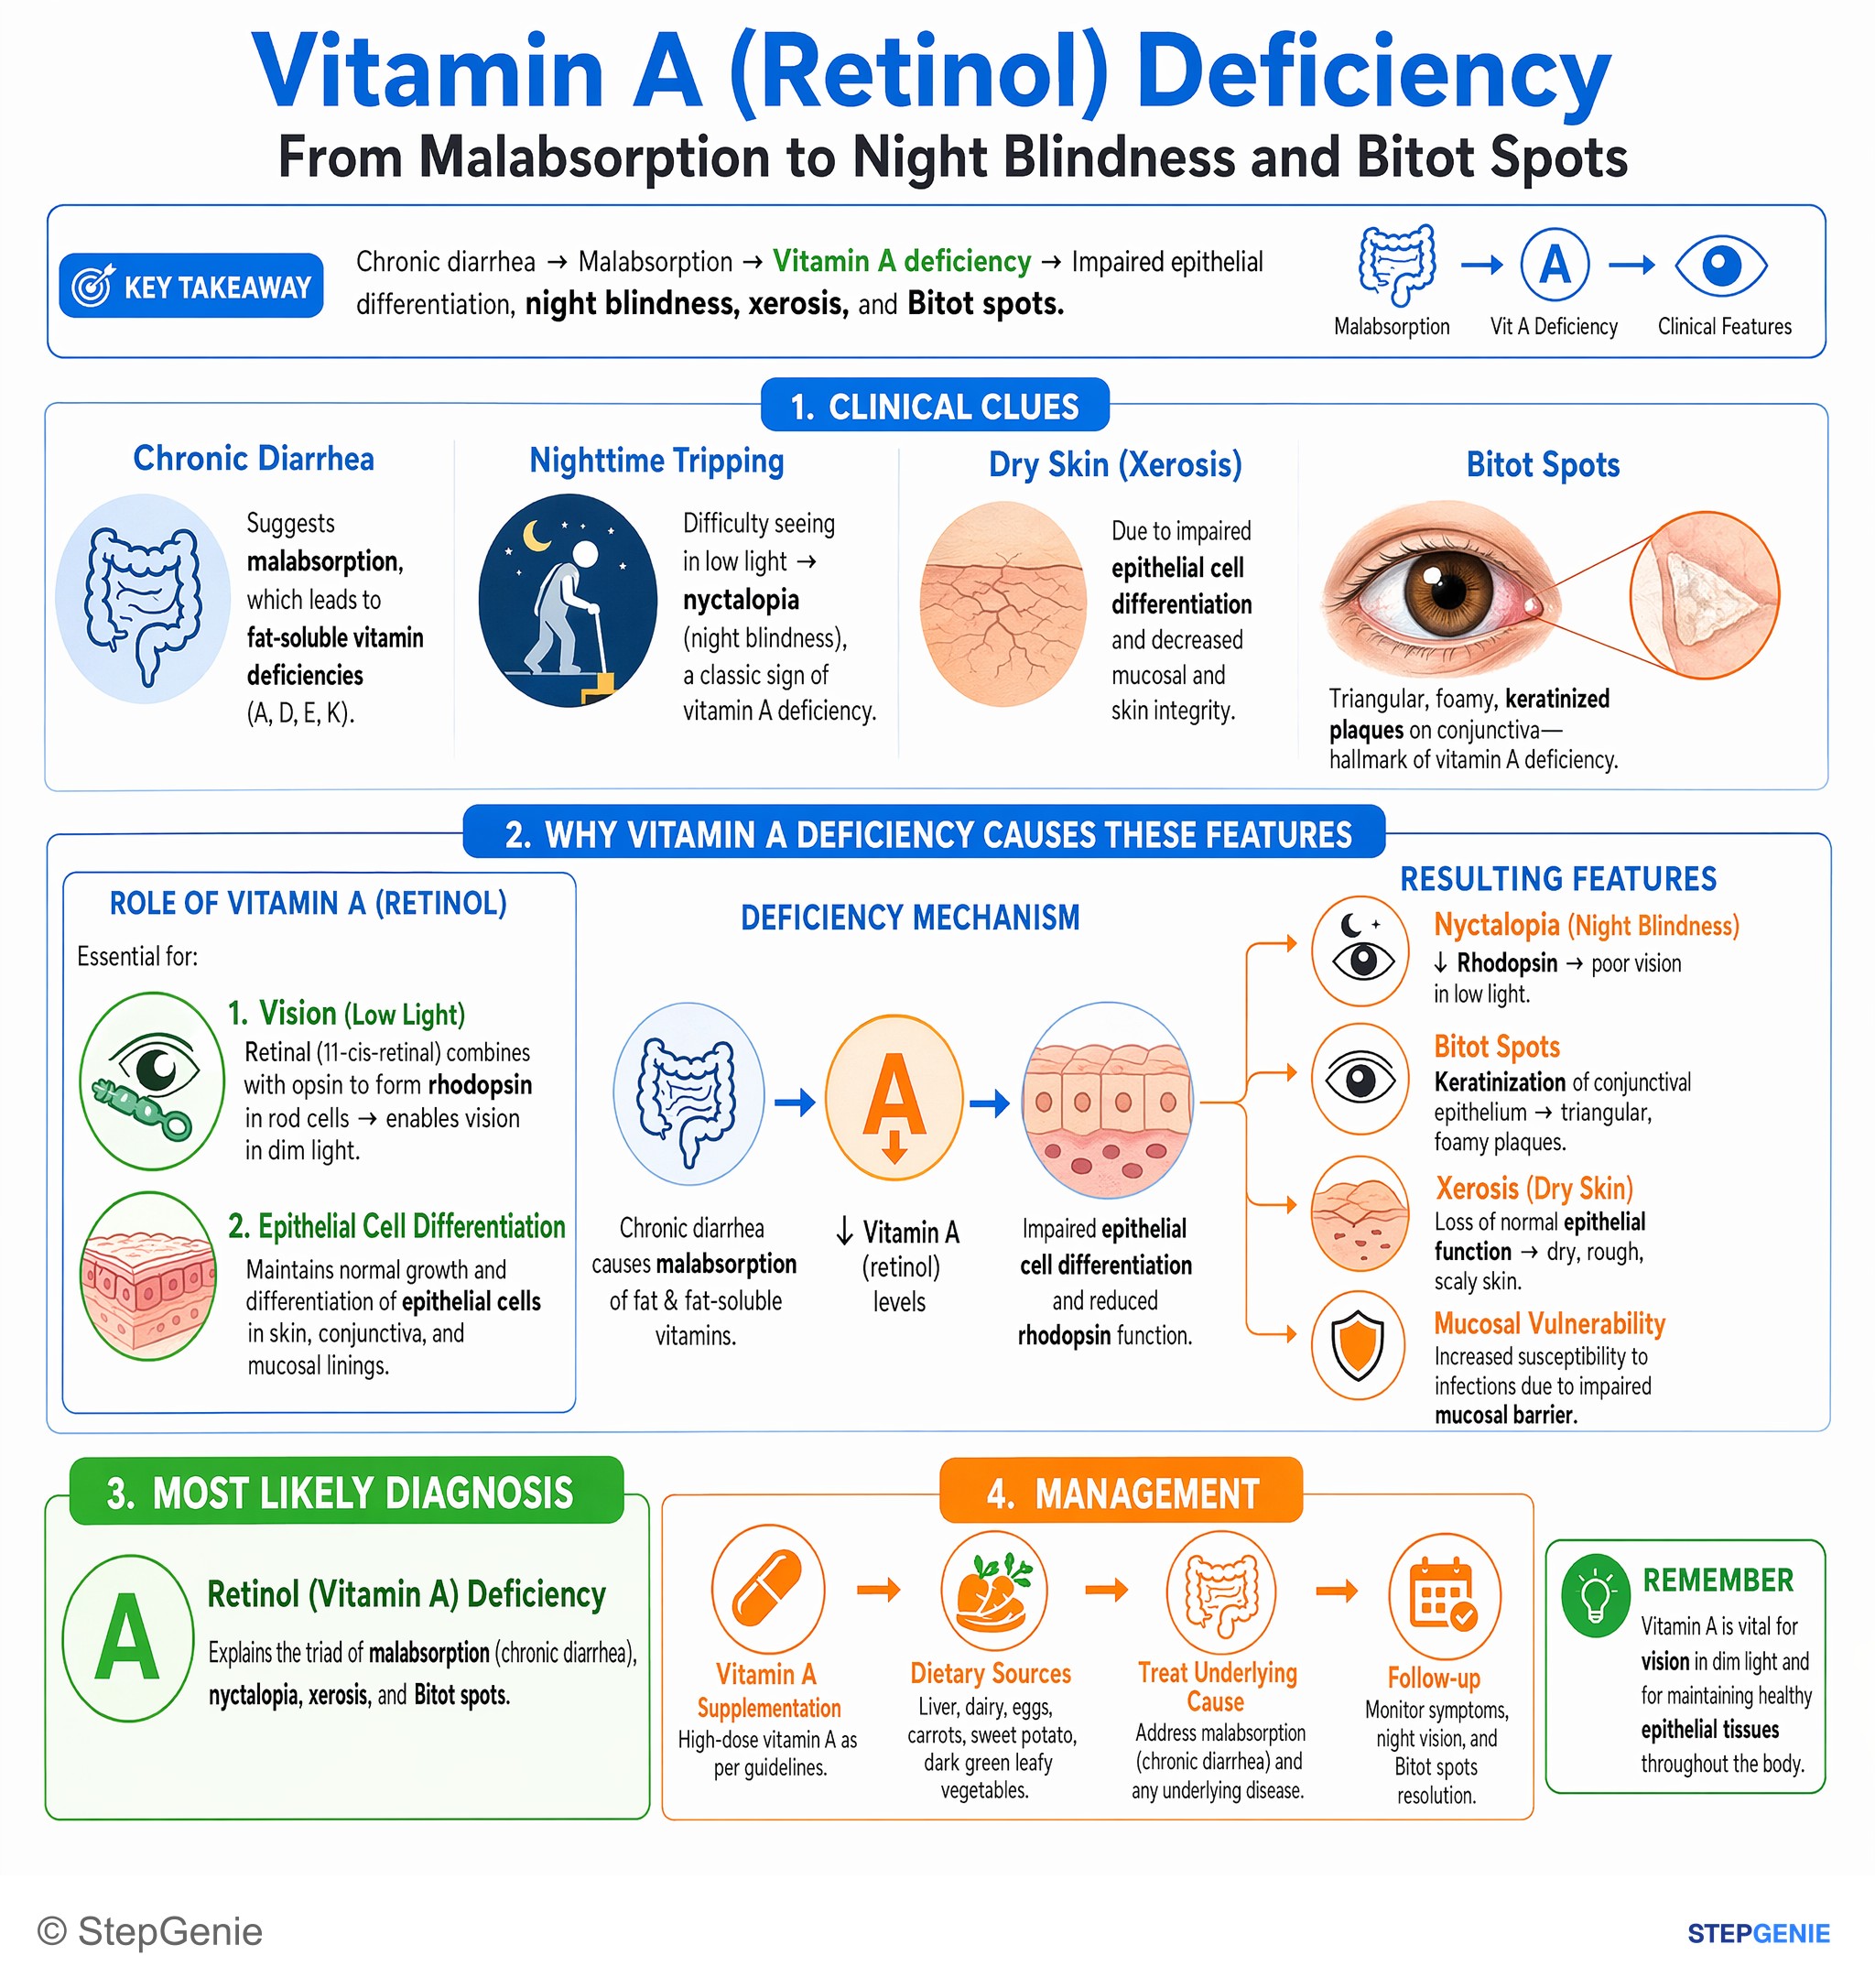
Vitamin A (retinol) deficiency → impaired epithelial differentiation, night blindness, xerosis, and Bitot spots (triangular keratin…
USMLE Step 1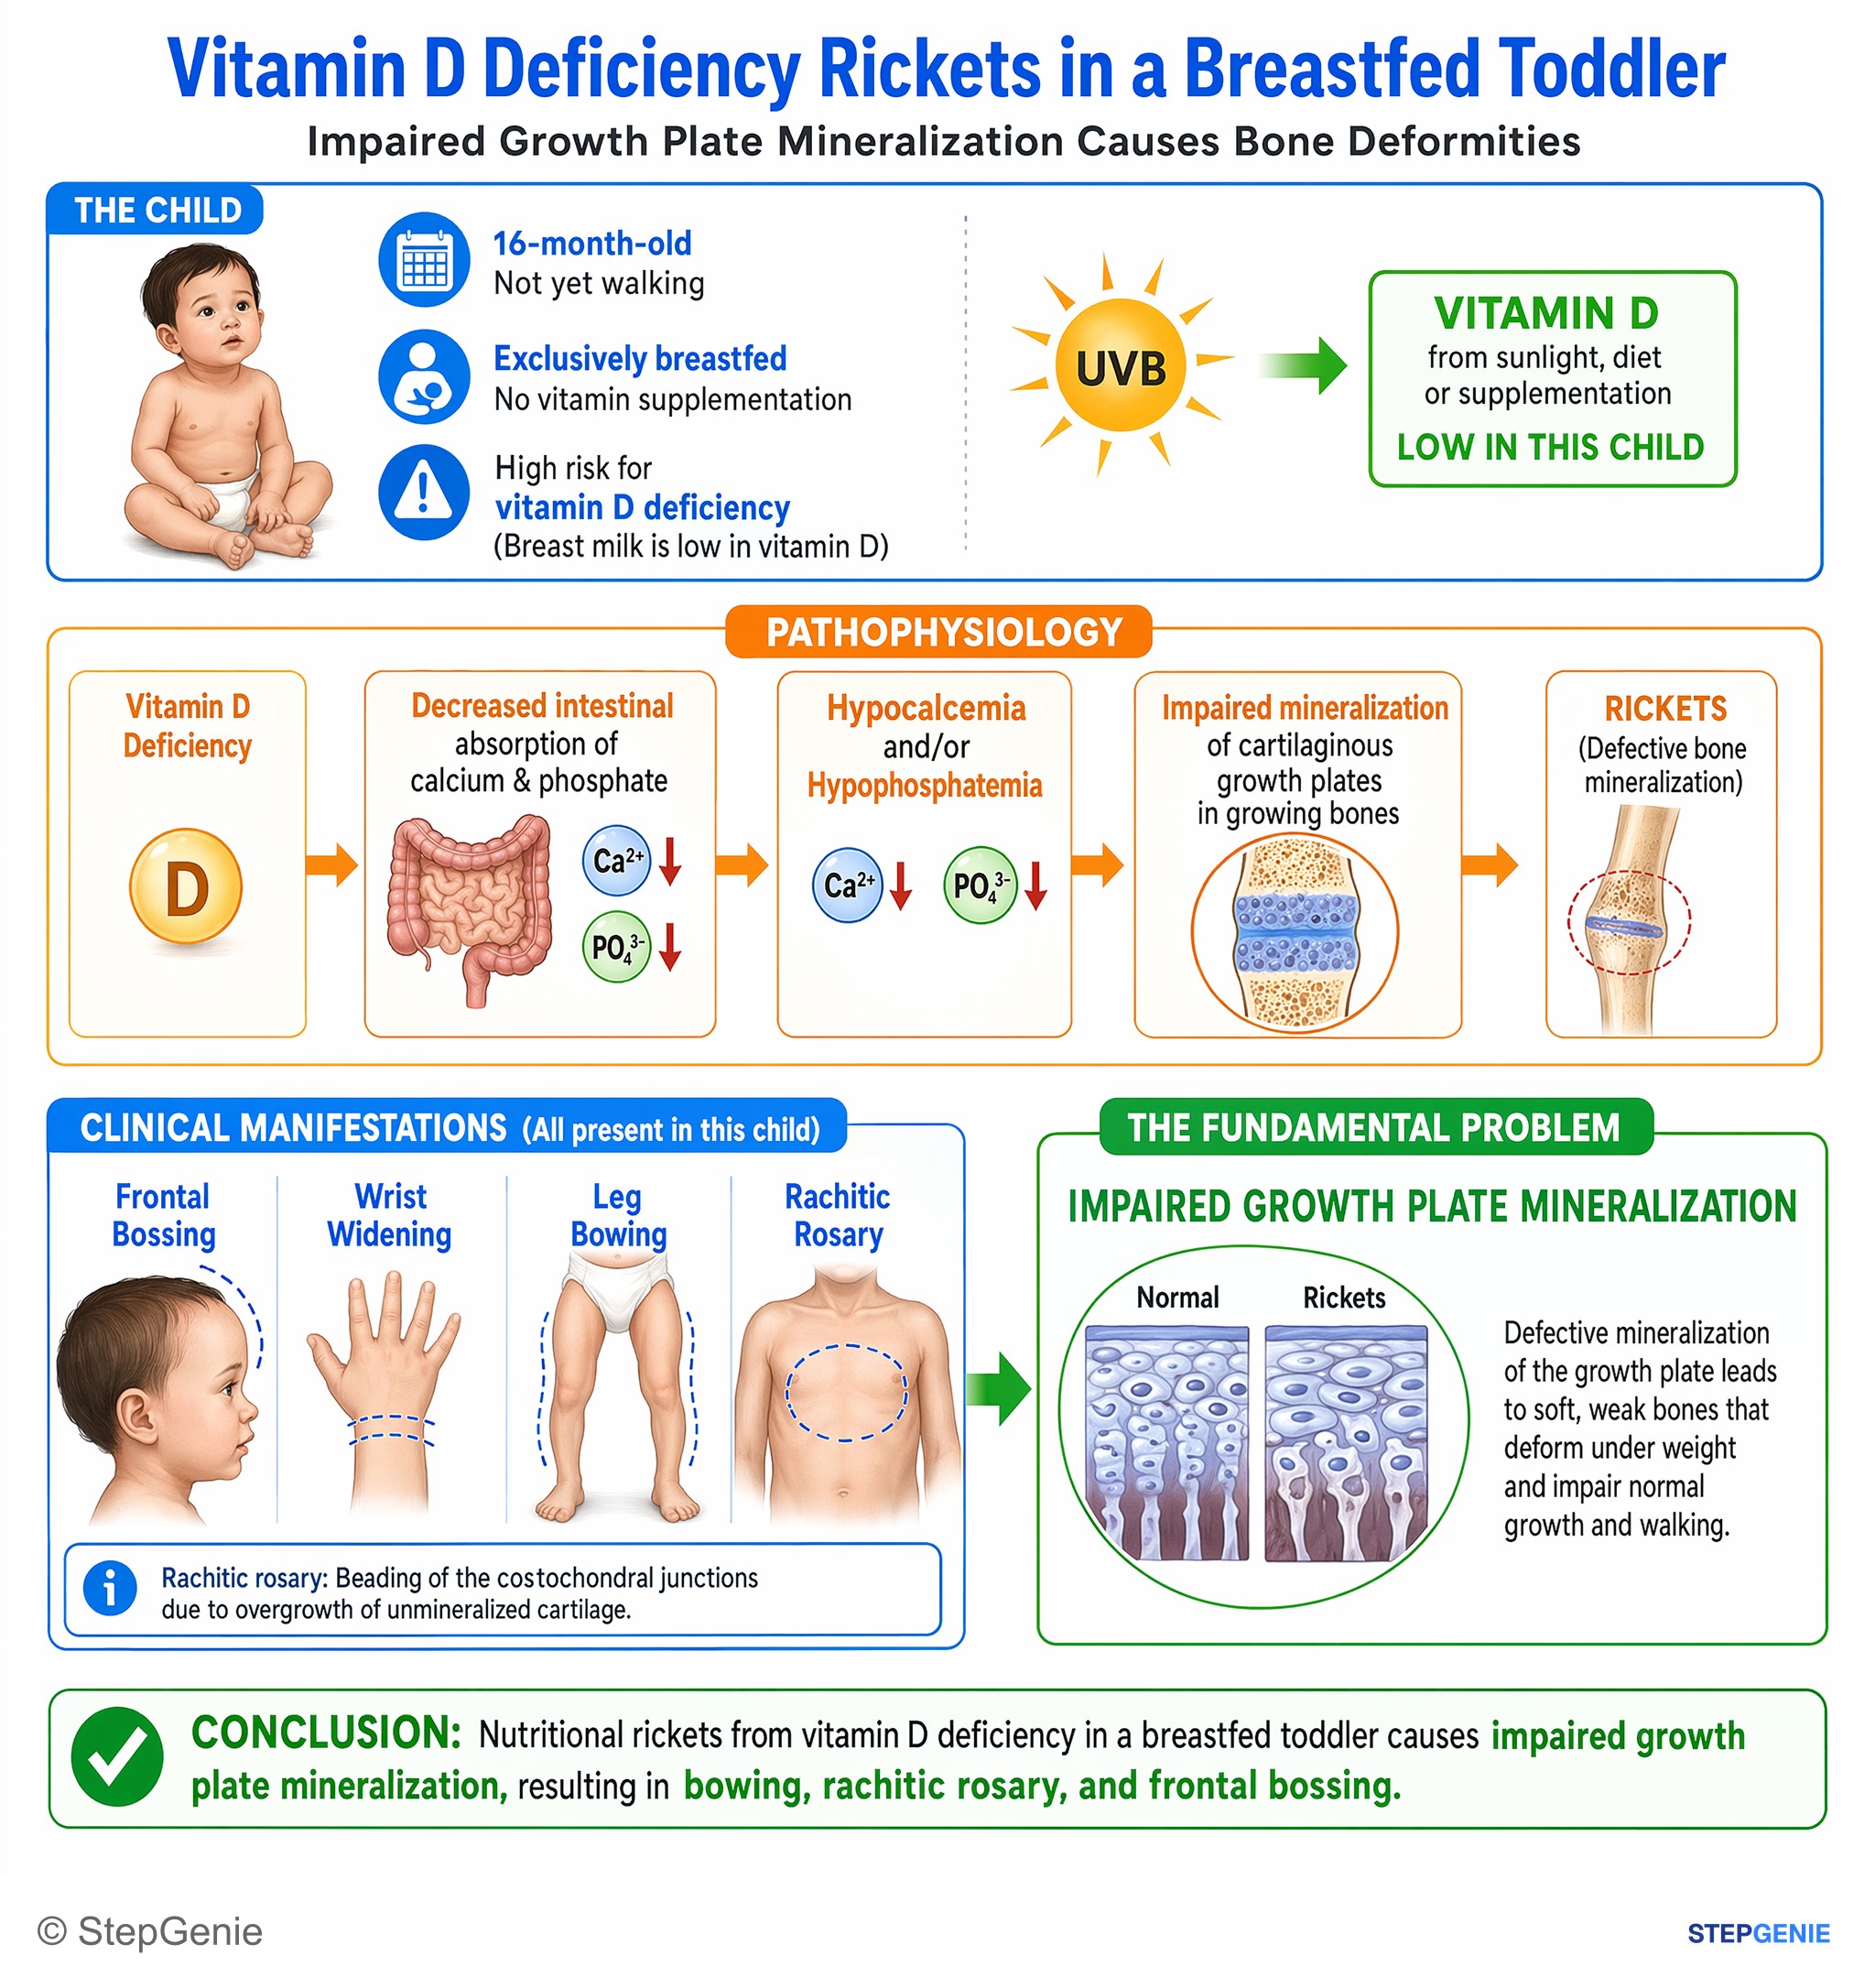
Nutritional rickets from vitamin D deficiency in a breastfed toddler causes impaired growth plate mineralization with bowing, rachitic…
USMLE Step 1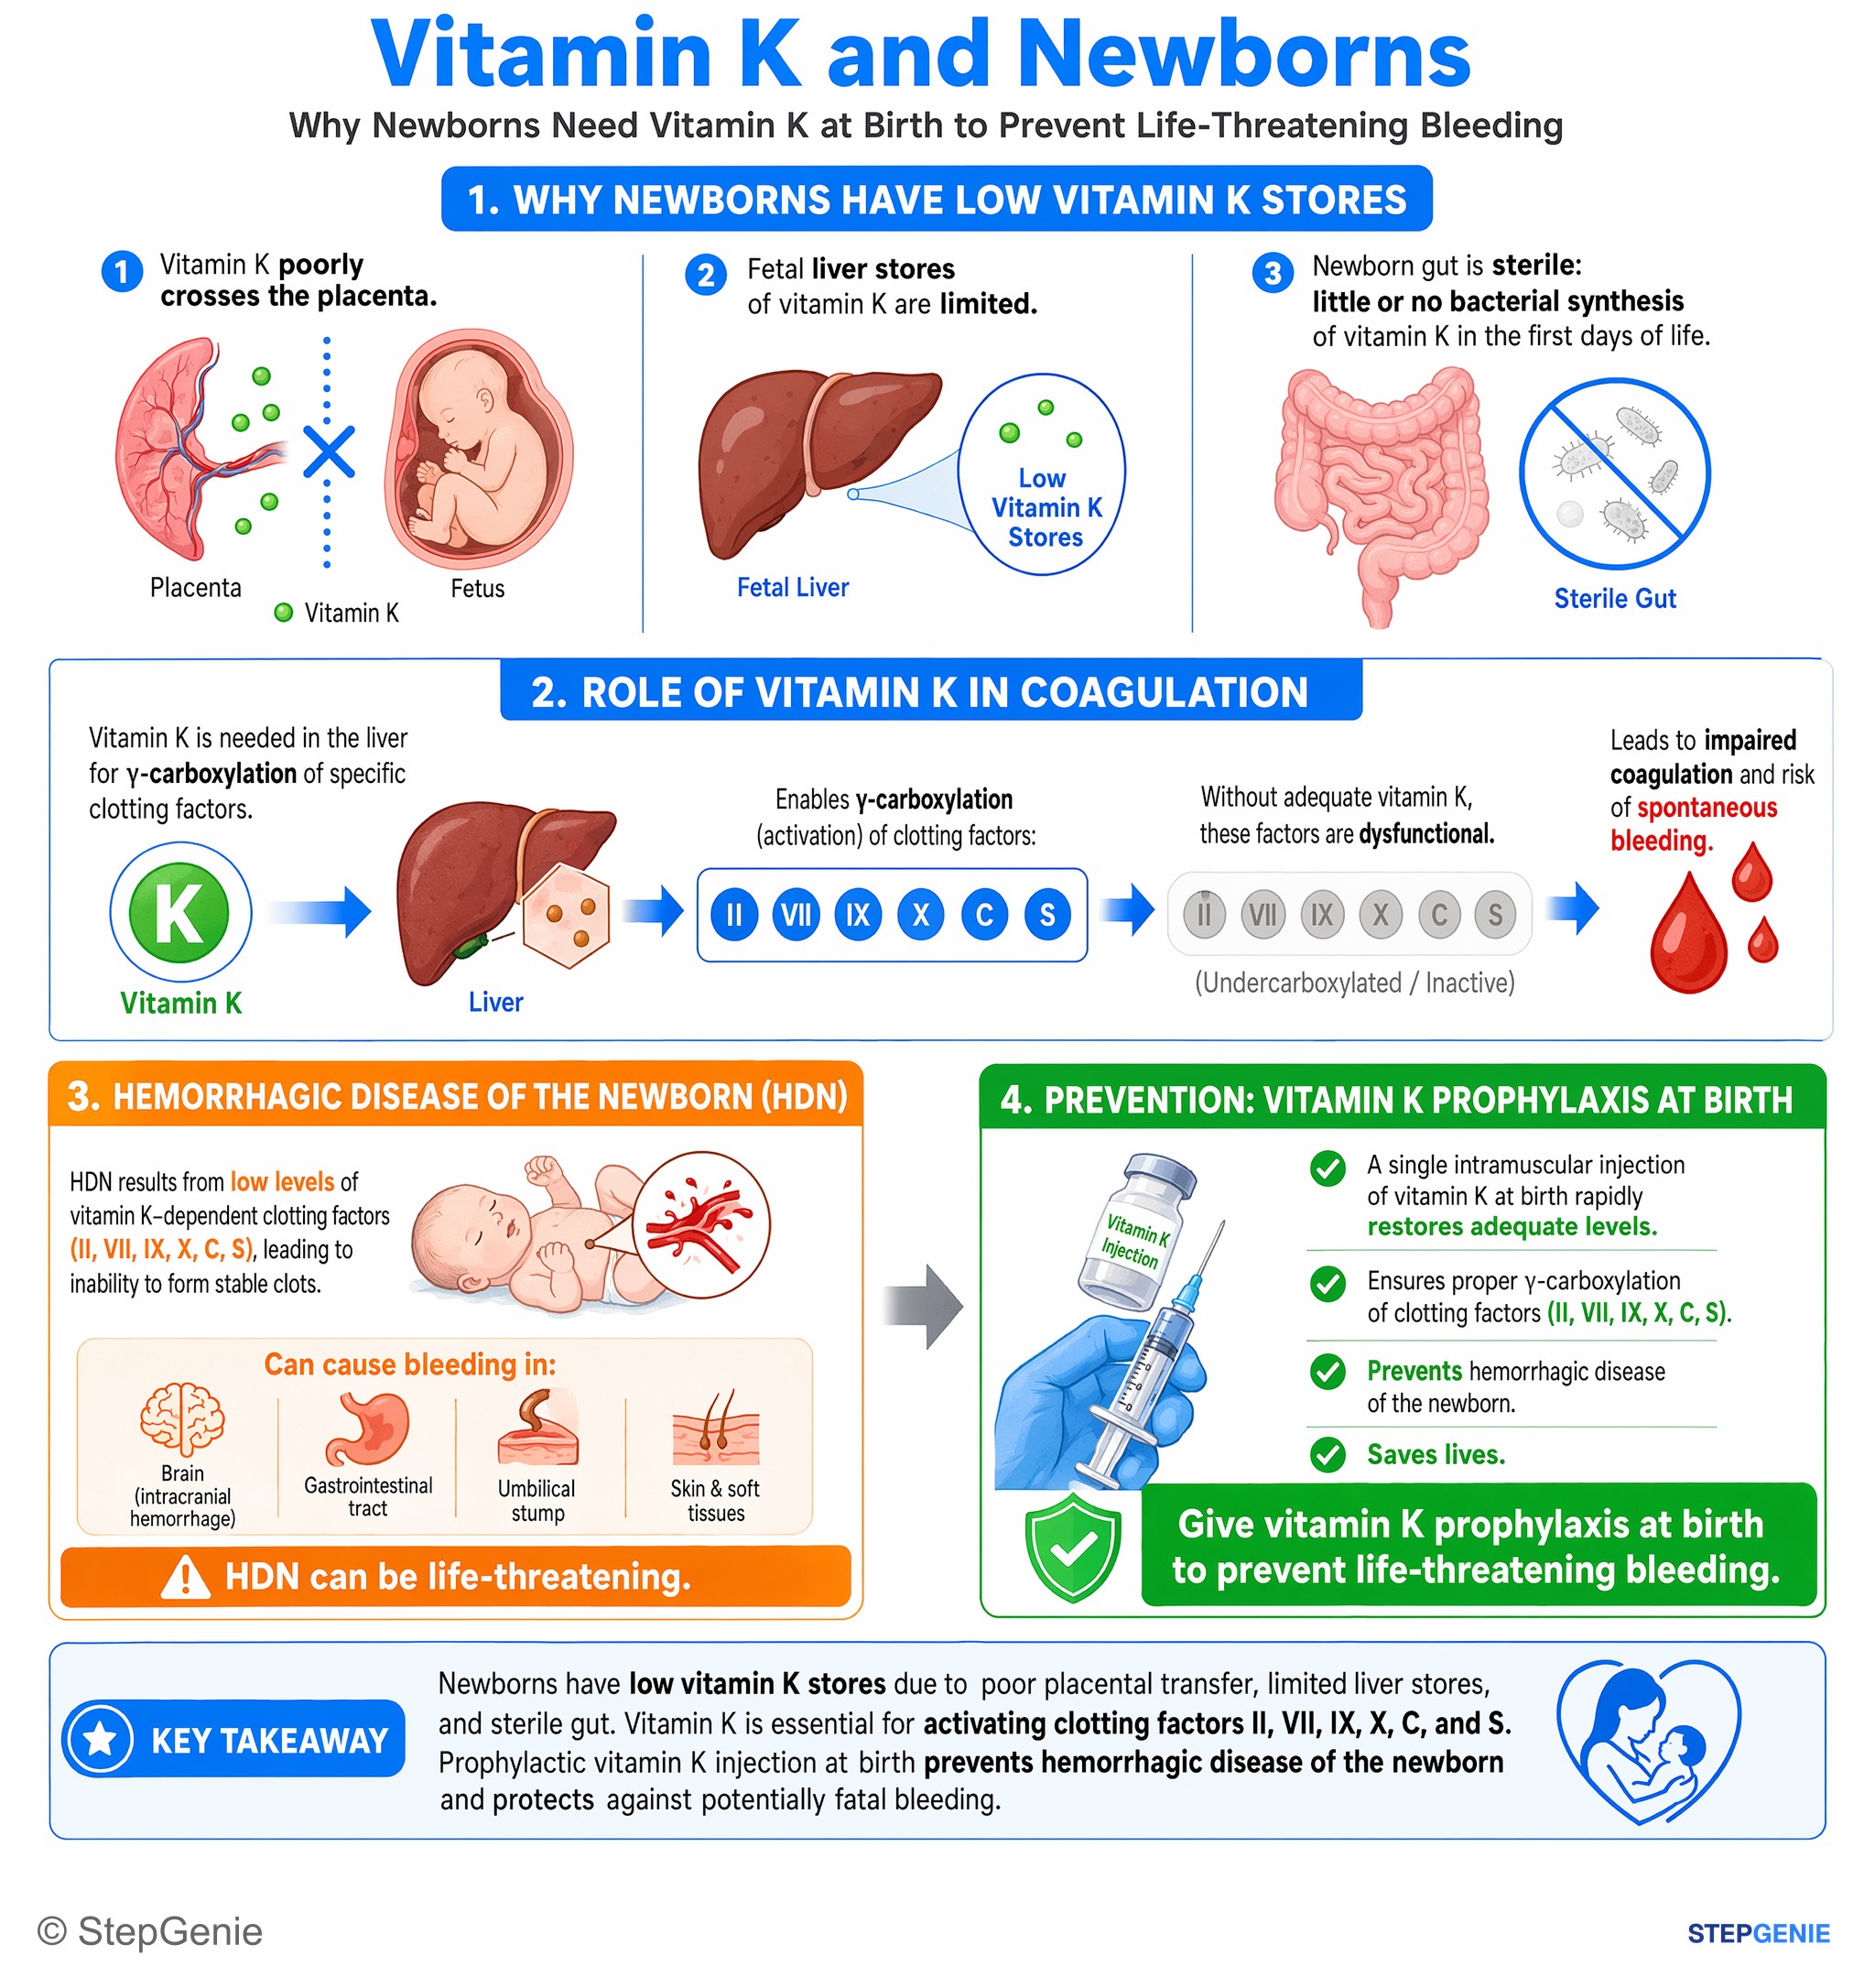
Hemorrhagic disease of the newborn results from low vitamin K–dependent clotting factors; give vitamin K prophylaxis to prevent…
USMLE Step 2Frequently Asked Questions
Why do fat-soluble vitamin deficiencies happen in pancreatic insufficiency, cholestasis, or after orlistat?
Fat-soluble vitamin deficiencies happen because vitamins A, D, E, and K are absorbed with dietary fat and require bile salts. When fat absorption is impaired, these vitamins are not absorbed well either. Classic causes include pancreatic insufficiency with low lipase, cholestasis or biliary obstruction with low bile salts, small bowel malabsorption, orlistat use, and malabsorptive bariatric surgery.
How do you tell vitamin A deficiency from vitamin A toxicity on exam questions?
Vitamin A deficiency classically causes night blindness and dry, keratinized epithelial findings, while toxicity causes teratogenicity, hepatotoxicity, dry skin, and pseudotumor cerebri. Deficiency clues include xerophthalmia, Bitot spots, hyperkeratosis, and increased infection risk because vitamin A supports vision, epithelial differentiation, and immune function. Toxicity is a classic association with retinoids such as isotretinoin.
What are the classic signs of vitamin D deficiency and toxicity?
Vitamin D deficiency causes poor bone mineralization, while toxicity causes hypercalcemia. Deficiency presents as rickets in children, with findings like bowed legs and rachitic rosary, or osteomalacia in adults, with bone pain and fractures. Toxicity causes kidney stones, constipation, confusion or other neuropsychiatric changes, and can also lead to soft tissue calcifications.
Why does vitamin E deficiency cause hemolytic anemia and neurologic problems?
Vitamin E deficiency causes hemolytic anemia and neurologic deficits because vitamin E normally protects cell membranes from oxidative damage. Red blood cells are vulnerable to oxidative injury, so deficiency can lead to hemolysis and acanthocytosis. Neurons are also affected, producing posterior column and spinocerebellar findings such as ataxia, loss of vibration and proprioception, and peripheral neuropathy.
Why does vitamin K deficiency increase PT/INR and cause bleeding?
Vitamin K deficiency increases PT/INR and causes bleeding because vitamin K is required for gamma-carboxylation of glutamate residues on clotting factors. This modification allows factors II, VII, IX, X and proteins C and S to bind calcium and function on phospholipid surfaces. Without enough vitamin K, clotting is impaired, leading to easy bruising, bleeding, and an elevated PT/INR.