The cholesterol synthesis pathway builds cholesterol from acetyl-CoA in the cytosol and endoplasmic reticulum, mostly in the liver: acetyl-CoA → HMG-CoA → mevalonate → isopentenyl pyrophosphate (IPP) → geranyl-PP → farnesyl-PP → squalene → lanosterol → cholesterol. The rate-limiting step is HMG-CoA reductase (HMG-CoA → mevalonate, using 2 NADPH), the enzyme statins inhibit.
Memorize the order as "All Hungry Med Interns Find Some Leftover Cake" and the carbon counts as 2 → 6 → 5 → 10 → 15 → 30 → 27. HMG-CoA reductase is switched on when cell sterols are low (through SREBP-2) and after a meal, and switched off by high sterols, which speed its degradation, and by AMPK when ATP runs low.
The same map explains nitrogen-containing bisphosphonates, which block farnesyl-PP synthase, and two classic enzyme defects: mevalonate kinase deficiency and Smith-Lemli-Opitz syndrome.
The cholesterol synthesis pathway in one line (mnemonic)
All Hungry Med Interns Find Some Leftover Cake = Acetyl-CoA → HMG-CoA → Mevalonate → Isopentenyl pyrophosphate (IPP) → Farnesyl-PP (by way of geranyl-PP) → Squalene → Lanosterol → Cholesterol.
Then count carbons. The number falls only twice: mevalonate loses its carboxyl carbon as CO₂ on the way to IPP (6 → 5), and lanosterol loses three methyl groups on the way to cholesterol (30 → 27).
| Intermediate | Carbons | How you get there |
|---|---|---|
| Acetyl-CoA | 2 | Cut from citrate in the cytosol by ATP-citrate lyase |
| HMG-CoA, mevalonate | 6 | 2 acetyl-CoA → acetoacetyl-CoA, plus a third acetyl-CoA |
| IPP (and its isomer DMAPP) | 5 | Mevalonate is phosphorylated twice, then decarboxylated |
| Geranyl-PP | 10 | DMAPP + IPP |
| Farnesyl-PP | 15 | Geranyl-PP + IPP |
| Squalene | 30 | Two farnesyl-PP joined tail to tail |
| Lanosterol | 30 | Squalene is epoxidized, then cyclized into four rings |
| Cholesterol | 27 | About 19 more reactions remove three methyl groups |
Cholesterol biosynthesis steps: enzymes, location and cofactors
The textbook outline has three stages: acetyl-CoA to IPP, six IPP to squalene, squalene to cholesterol.
| Step | Reaction | Enzyme (location) | Cofactor or tie-in |
|---|---|---|---|
| 0 | Citrate → acetyl-CoA + oxaloacetate | ATP-citrate lyase (cytosol) | ATP; bempedoic acid |
| 1 | 2 acetyl-CoA → acetoacetyl-CoA | Cytosolic acetoacetyl-CoA thiolase | Ketogenesis starts the same way |
| 2 | Acetoacetyl-CoA + acetyl-CoA → HMG-CoA | HMG-CoA synthase 1 (cytosol) | The mitochondrial isoform is rate-limiting for ketogenesis |
| 3 | HMG-CoA → mevalonate | HMG-CoA reductase (ER membrane) | 2 NADPH; rate-limiting; statins |
| 4 | Mevalonate → mevalonate-5-P → mevalonate-5-PP | Mevalonate kinase, phosphomevalonate kinase | 1 ATP each; mevalonate kinase deficiency |
| 5 | Mevalonate-5-PP → IPP + CO₂; IPP ⇄ DMAPP | Diphosphomevalonate decarboxylase; IPP isomerase | 1 ATP |
| 6 | DMAPP + IPP → geranyl-PP; + IPP → farnesyl-PP | Farnesyl-PP synthase | Nitrogen-containing bisphosphonates |
| 7 | 2 farnesyl-PP → squalene | Squalene synthase (ER) | NADPH; first step committed to sterols |
| 8 | Squalene → 2,3-oxidosqualene | Squalene epoxidase (ER) | O₂ and NADPH; terbinafine (fungal enzyme) |
| 9 | 2,3-Oxidosqualene → lanosterol | Lanosterol synthase, or oxidosqualene cyclase (ER) | Forms the four-ring sterol nucleus |
| 10 | Lanosterol → … → cholesterol | CYP51 (14α-demethylase) … 7-dehydrocholesterol reductase (ER) | Azoles (fungal CYP51); Smith-Lemli-Opitz (DHCR7) |
Where cholesterol synthesis takes place. Almost all cells can make some cholesterol, but the liver is the major site. The enzymes work in the cytosol and smooth endoplasmic reticulum: HMG-CoA reductase is an integral ER membrane protein, as are squalene synthase and the enzymes after it. Mitochondria only supply the acetyl-CoA.
Stoichiometry. Each mevalonate takes 3 acetyl-CoA and 2 NADPH (not NADH), and making IPP from it costs 3 ATP. Six IPP form one squalene, and squalene synthase uses 1 more NADPH; later steps use more O₂ and NADPH.
Rate-limiting step: HMG-CoA reductase and its regulation
HMG-CoA reductase (ER membrane, 2 NADPH) catalyzes the irreversible, rate-limiting and committed step for cholesterol and the other isoprenoids.
Sterol sensing: SREBP-2, SCAP and INSIG
- Low ER cholesterol: SCAP escorts SREBP-2 to the Golgi in COPII vesicles, where site-1 and site-2 proteases release the transcription factor, which enters the nucleus.
- Nuclear SREBP-2 turns on the reductase and the other synthesis enzymes, the LDL receptor, PCSK9 and INSIG-1.
- High cholesterol: cholesterol binds SCAP, and oxysterols such as 25-hydroxycholesterol bind INSIG (insulin-induced gene). SCAP then binds INSIG, SCAP-SREBP-2 stays in the ER, and transcription falls.
SREBP-2 is the cholesterol isoform; SREBP-1c, induced by insulin, mainly drives fatty acid synthesis.
Sterol-accelerated degradation
When sterols accumulate in the ER, the reductase binds INSIG, which recruits ubiquitin ligases such as gp78 (AMFR); the tagged enzyme is pulled out of the membrane and destroyed by the proteasome. The key sterol trigger is lanosterol, the first sterol of the pathway, not cholesterol (25-hydroxycholesterol also works), so a backlog of intermediates throttles the enzyme that feeds them. Nonsterol isoprenoids add a brake by slowing translation of reductase mRNA.
Hormones and energy
| Signal | Effect on the reductase | Mechanism |
|---|---|---|
| Insulin, fed state | ↑ | Raises enzyme mRNA and protein; insulin and glucose also activate mTORC1, which phosphorylates USP20, a deubiquitylase that shields the reductase from degradation |
| Thyroxine | ↑ | Upregulates the enzyme |
| Glucagon | ↓ | Blocks insulin's rise in reductase mRNA and protein |
| Low ATP | ↓ | AMPK phosphorylates Ser872, inactivating the enzyme; a phosphatase reverses this |
| Statins | ↓ | Competitive inhibition |
AMPK switches off acetyl-CoA carboxylase, which catalyzes the committed step of fatty acid synthesis, the same way. Compare every rate-limiting enzyme in this rate-limiting enzymes table.
Acetyl-CoA supply: the citrate shuttle and two HMG-CoA synthases
Acetyl-CoA is made in mitochondria, but cholesterol is built in the cytosol, so acetyl groups travel as citrate:
- The mitochondrial citrate carrier (SLC25A1) exports citrate in exchange for malate.
- ATP-citrate lyase spends ATP to split citrate into acetyl-CoA and oxaloacetate. Bempedoic acid blocks this step; SREBP-1c induces the enzyme.
- The shuttle also turns the reducing power of NADH into NADPH: malic enzyme converts malate to pyruvate, CO₂ and NADPH. The pentose phosphate pathway (rate-limiting enzyme G6PD) also supplies NADPH.
Fatty acid synthesis uses the same shuttle (fatty acid synthesis overview).
Tracing labeled carbons. Konrad Bloch's isotope-labeled acetate experiments showed that acetate builds both the rings and the side chain; all 27 carbons of cholesterol come from acetyl-CoA. The only carbon lost before squalene is mevalonate's carboxyl carbon (C1), released as CO₂, so a label there never reaches IPP.
| Cholesterol synthesis | Ketogenesis | |
|---|---|---|
| Where | Cytosol, then ER | Liver mitochondria |
| HMG-CoA made by | HMG-CoA synthase 1 (cytosolic) | HMG-CoA synthase 2 (mitochondrial), the first irreversible, rate-limiting step of ketogenesis |
| HMG-CoA becomes | Mevalonate (HMG-CoA reductase) | Acetoacetate + acetyl-CoA (HMG-CoA lyase) |
| When | Fed state | Fasting; glucagon stimulates ketogenesis |
More on the ketone side in the ketogenesis overview.
Mevalonate pathway to isoprenoids: IPP, farnesyl-PP and branch products
Three ATP-using enzymes turn mevalonate into IPP, the 5-carbon isoprene unit, and farnesyl-PP synthase builds geranyl-PP (C10), then farnesyl-PP (C15), from IPP and its isomer DMAPP. Farnesyl-PP and geranyl-PP feed back on mevalonate kinase by competing for its ATP site, and farnesyl-PP is the branch point:
| Branch product | How it is made | Job | Exam link |
|---|---|---|---|
| Squalene, then sterols | Squalene synthase joins two farnesyl-PP | Cholesterol, bile acids, steroid hormones, vitamin D | First committed sterol step |
| Dolichol phosphate | Dehydrodolichyl-PP synthase adds many IPP to farnesyl-PP | Sugar carrier for protein glycosylation in the ER | — |
| Coenzyme Q10 (ubiquinone) | PDSS1/2 extend farnesyl-PP with 7 IPP; COQ2 attaches the chain to 4-hydroxybenzoate | Electron carrier in the respiratory chain | Electron transport chain mnemonic |
| Farnesyl and geranylgeranyl groups | Transferases attach them to a cysteine in a C-terminal CaaX motif | Needed to activate small GTPases such as Ras, Rho and Rac | Nitrogen-containing bisphosphonates block farnesyl-PP synthase in osteoclasts |
Statins act upstream of every branch, so they lower these isoprenoids too: the basis of their "pleiotropic" effects and one proposed cause of statin muscle symptoms.
Squalene, lanosterol and the last steps to cholesterol
- Squalene synthase joins two farnesyl-PP through presqualene-PP and reduces the product with NADPH: the first step committed to sterols.
- Squalene epoxidase uses O₂ and NADPH to make 2,3-oxidosqualene. Cholesterol triggers its degradation; terbinafine blocks the fungal enzyme, and the human enzyme is only slightly inhibited.
- Lanosterol synthase (oxidosqualene cyclase) folds 2,3-oxidosqualene into lanosterol, the first sterol: the four rings appear here, not at squalene.
- Lanosterol to cholesterol takes about 19 ER reactions. Three methyl groups are removed (CYP51 strips the 14α-methyl as formate, the reaction azoles block in fungi). The last step is either desmosterol → cholesterol (DHCR24, Bloch pathway) or 7-dehydrocholesterol → cholesterol (DHCR7, Kandutsch-Russell); in mice, the Bloch share ranges from 8% to 97% by tissue.
What cholesterol becomes:
- Bile acids: cholesterol 7α-hydroxylase (CYP7A1) is the rate-limiting step. This is one way the body disposes of cholesterol, which it cannot break down.
- Steroid hormones: side-chain cleavage to pregnenolone (CYP11A1) is the rate-limiting step.
- Vitamin D3: UVB converts 7-dehydrocholesterol in the skin to previtamin D; follow it on in vitamin D metabolism.
LDL receptor regulation: synthesis vs uptake
Cells get cholesterol two ways: make it, or take up LDL. The LDL receptor recognizes apoB-100 and apoE, clusters in clathrin-coated pits and carries LDL in; lysosomes free the cholesterol, which leaves through NPC2 and NPC1 (defective in Niemann-Pick type C) toward the ER. Rising cell cholesterol then:
- turns off SREBP-2, so fewer reductase molecules and LDL receptors are made;
- speeds reductase degradation;
- activates ACAT (SOAT1) to store the excess as cholesteryl ester;
- through oxysterols and LXR, induces IDOL, a ubiquitin ligase that degrades the LDL receptor.
About 70% of circulating LDL is cleared by hepatic LDL receptors, and each receptor returns to the surface more than 100 times unless PCSK9 binds it and diverts it to the lysosome. PCSK9 is itself an SREBP-2 target, so drugs that lower liver cholesterol, statins included, raise PCSK9. Particle traffic is mapped in lipoprotein metabolism.
Familial hypercholesterolemia is a clearance defect, not a synthesis defect. Most cases are LDLR variants; APOB and PCSK9 variants also cause autosomal dominant disease, and LDLRAP1 variants a recessive form; about 1 in 200 to 250 people are affected. Homozygotes with almost no working receptors respond poorly to statins, ezetimibe and PCSK9 inhibitors, because all three work through receptors. Compare the other lipid disorders in the familial dyslipidemias mnemonic.
Drugs that act on the cholesterol pathway
| Drug | Target | LDL-C effect | High-yield points |
|---|---|---|---|
| Bempedoic acid | ATP-citrate lyase, upstream of the reductase | Down about 15–25% | Prodrug activated in liver (ACSVL1), not muscle; hyperuricemia, gout, tendon rupture; 13% fewer major cardiovascular events in statin-intolerant patients (CLEAR Outcomes) |
| Statins | HMG-CoA reductase (competitive) | Down by as much as 50–60% | Myalgia, rare rhabdomyolysis, immune-mediated necrotizing myopathy (anti-HMG-CoA reductase antibodies), raised transaminases and HbA1c; CYP3A4 interactions (lovastatin, simvastatin, atorvastatin) |
| Nitrogen-containing bisphosphonates (alendronate, risedronate, zoledronic acid) | Farnesyl-PP synthase in osteoclasts | None | Block prenylation, so osteoclasts stop resorbing bone; non-nitrogen agents (etidronate, clodronate) form toxic ATP analogs instead |
| Terbinafine | Fungal squalene epoxidase | None | Squalene builds up and kills the fungus |
| Azoles (fluconazole) | Fungal lanosterol 14α-demethylase (CYP51) | None | 14α-methyl sterols build up; mammalian demethylation is much less sensitive |
| Ezetimibe (contrast) | NPC1L1: intestinal cholesterol absorption | Down about 15–20% | Less cholesterol reaches the liver, so LDL receptors rise |
| Evolocumab, alirocumab; inclisiran (contrast) | PCSK9 protein (antibodies); PCSK9 mRNA (siRNA) | Down about 50% | Spare LDL receptors from degradation; the antibodies work better in patients on statins, which raise PCSK9 |
| Bile acid sequestrants (contrast) | Bile acid reabsorption | Down | The liver turns more cholesterol into bile acids, so SREBPs raise synthesis enzymes and LDL receptors |
- How statins lower LDL: mainly by raising hepatic LDL receptors through SREBP-2, not just by cutting synthesis.
- CoQ10: statins lower CoQ10, but CoQ10 supplements for statin muscle symptoms have not consistently helped in randomized trials.
- Pregnancy: in July 2021 the FDA asked for removal of the class-wide contraindication; most patients should still stop statins once pregnancy is recognized.
Practice the classic question in this HMG-CoA reductase breakdown, and the bone side in bisphosphonates and bone drugs.
Disorders of the pathway: Smith-Lemli-Opitz and mevalonate kinase deficiency
| Smith-Lemli-Opitz syndrome | Mevalonate kinase deficiency (mild form: HIDS) | |
|---|---|---|
| Gene and step | DHCR7: 7-dehydrocholesterol → cholesterol, the last step | MVK: mevalonate → mevalonate-5-phosphate |
| Inheritance | Autosomal recessive | Autosomal recessive |
| Lab clue | High 7-dehydrocholesterol; cholesterol usually low (normal in about 10%) | Urinary mevalonic acid, highest during flares |
| Picture | Microcephaly, intellectual disability, ptosis, cleft palate, heart defects, hypospadias or ambiguous genitalia, Y-shaped 2–3 toe syndactyly (over 99%), postaxial polydactyly, autistic behaviors, UVA photosensitivity | Fevers from infancy lasting 3–6 days with lymphadenopathy, abdominal pain, diarrhea, rash and joint pain, set off by vaccines, surgery or stress; the severe form (mevalonic aciduria) adds developmental delay, ataxia and seizures |
| Frequency | About 1 in 20,000 to 60,000 newborns | Rare; more than 200 people reported |
| Treatment | Cholesterol supplementation; avoid haloperidol, which can worsen the sterol abnormalities | IL-1 blockade (canakinumab is FDA-approved; anakinra is off-label); statins and bisphosphonates are not recommended |
USMLE traps: classic teaching vs current evidence
| Trap | What's actually true |
|---|---|
| HMG-CoA synthase is rate-limiting for cholesterol | HMG-CoA reductase is; mitochondrial HMG-CoA synthase is rate-limiting for ketogenesis |
| The committed step is squalene synthase | Mevalonate formation commits carbon to isoprenoids; squalene synthase is the first step committed to sterols |
| Statins are contraindicated in pregnancy (category X) | In 2021 the FDA asked for the class contraindication to be removed from labels; most pregnant patients should still stop, and breastfeeding is not recommended |
| Insulin turns the reductase on by dephosphorylation, glucagon off by phosphorylation | Partly true: in rat liver insulin outweighs glucagon in setting its phosphorylation, but over longer periods both also change enzyme mRNA and protein; AMPK is the kinase that inactivates it, and feeding shields it from degradation |
| High IgD diagnoses HIDS | IgD is often high, but the 2024 SHARE update advises against IgD testing; use urinary mevalonic acid during a flare and MVK testing |
| The rings form at squalene | Squalene is linear; lanosterol is the first ring-containing sterol |
Browse more pathway reviews on the Biochemistry hub.
Worked USMLE-style vignettes
Vignette 1: the muscle aches. A 58-year-old man with an LDL cholesterol of 190 mg/dL starts a new drug. Six weeks later his LDL has fallen by about half, but his thighs ache and his creatine kinase is mildly raised. The drug most likely inhibits which reaction?
Answer: HMG-CoA → mevalonate (HMG-CoA reductase; a statin).
Why the distractors are wrong:
- Acetoacetyl-CoA + acetyl-CoA → HMG-CoA (HMG-CoA synthase): the step before the statin target.
- Citrate → acetyl-CoA (ATP-citrate lyase): bempedoic acid is activated in liver, not muscle, and lowers LDL only about 15–25%.
- Cholesterol uptake by NPC1L1: ezetimibe lowers LDL only about 15–20%.
If weakness and a high creatine kinase persist for months after stopping the statin, think immune-mediated necrotizing myopathy (anti-HMG-CoA reductase antibodies).
Vignette 2: the newborn with fused toes. A newborn boy has microcephaly, ptosis, a cleft palate, hypospadias, Y-shaped fusion of the second and third toes and an extra digit on each foot. Serum cholesterol is low and 7-dehydrocholesterol is markedly raised. Which enzyme is deficient?
Answer: 7-dehydrocholesterol reductase (DHCR7), the last step: Smith-Lemli-Opitz syndrome, autosomal recessive.
Why the distractors are wrong:
- HMG-CoA reductase: a block there would deplete every downstream intermediate, so 7-dehydrocholesterol could not pile up.
- Mevalonate kinase: causes periodic fevers and mevalonic aciduria, not 7-dehydrocholesterol excess.
- Lanosterol 14α-demethylase (CYP51): acts well upstream of 7-dehydrocholesterol; the azole target in fungi.
Vignette 3: fevers after vaccines. A 2-year-old girl has had fevers every few weeks since her 2-month vaccines, each lasting about 4 days, with tender cervical lymph nodes, abdominal pain, diarrhea and a rash. She is well between episodes, and urinary mevalonic acid is raised during a fever. Which enzyme is deficient, and what is the long-term treatment?
Answer: Mevalonate kinase (mevalonate → mevalonate-5-phosphate), the mild form of mevalonate kinase deficiency (HIDS); long-term treatment is IL-1 blockade such as canakinumab.
Why the distractors are wrong:
- HMG-CoA reductase: it makes mevalonate, so its loss would lower mevalonate, not raise it; statins are not recommended here.
- Mitochondrial HMG-CoA synthase: its deficiency causes hypoketotic hypoglycemia with encephalopathy and hepatomegaly, not periodic fevers.
- 7-dehydrocholesterol reductase: Smith-Lemli-Opitz presents with malformations at birth.
Confirm with MVK genetic testing, not a serum IgD level.
Vignette 4: the bone drug. A 67-year-old woman with osteoporosis starts weekly alendronate. Which enzyme does the drug inhibit inside osteoclasts?
Answer: Farnesyl-PP synthase; without farnesyl and geranylgeranyl groups, osteoclasts cannot prenylate small GTPases and stop resorbing bone.
Why the distractors are wrong:
- HMG-CoA reductase: the statin target, upstream of farnesyl-PP synthase.
- Squalene epoxidase: terbinafine blocks the fungal enzyme.
- Making nonfunctional ATP analogs: how non-nitrogen bisphosphonates such as etidronate act; alendronate contains nitrogen.
Key takeaways
- Order: acetyl-CoA → HMG-CoA → mevalonate → IPP → geranyl-PP → farnesyl-PP → squalene → lanosterol → cholesterol ("All Hungry Med Interns Find Some Leftover Cake"; carbons 2 → 6 → 5 → 10 → 15 → 30 → 27).
- Where: cytosol and smooth ER, mainly in the liver; acetyl-CoA arrives from mitochondria as citrate.
- Rate-limiting: HMG-CoA reductase (2 NADPH); on with low sterols (SREBP-2) and feeding, off with INSIG-driven degradation, AMPK and statins.
- Drug map: bempedoic acid (ATP-citrate lyase), statins (reductase), nitrogen-containing bisphosphonates (farnesyl-PP synthase); ezetimibe and PCSK9 inhibitors raise LDL receptors without blocking synthesis.
- Diseases: Smith-Lemli-Opitz (DHCR7, high 7-dehydrocholesterol); mevalonate kinase deficiency (periodic fevers, IL-1 blockade); familial hypercholesterolemia is a receptor defect.
Sources
- Craig M, et al. Biochemistry, Cholesterol — StatPearls, NCBI Bookshelf (2023)
- Berg JM, et al. Biochemistry, 8th ed., Section 26.2 (cholesterol synthesis) — Macmillan Learning
- Berg JM, et al. Biochemistry, 8th ed., Section 26.3 (regulation) — Macmillan Learning
- Berg JM, et al. Biochemistry, 8th ed., Figure 22.29 — Macmillan Learning
- Bloch K. The Biological Synthesis of Cholesterol, Nobel Lecture — NobelPrize.org (1964)
- Feingold KR. Cholesterol Lowering Drugs — Endotext, NCBI Bookshelf (2026)
- Feingold KR. Introduction to Lipids and Lipoproteins — Endotext, NCBI Bookshelf (2024)
- Sizar O, et al. Statin Medications — StatPearls, NCBI Bookshelf (2024)
- Bansal AB, Cassagnol M. HMG-CoA Reductase Inhibitors — StatPearls, NCBI Bookshelf (2023)
- Ganesan K, et al. Bisphosphonate — StatPearls, NCBI Bookshelf (2023)
- Rahimi N, Gupta S. Biochemistry, Ketogenesis — StatPearls, NCBI Bookshelf (2025)
- Chauhan K, et al. Vitamin D — StatPearls, NCBI Bookshelf (2023)
- Nowaczyk MJM, Wassif CA. Smith-Lemli-Opitz Syndrome — GeneReviews, NCBI Bookshelf (2020)
- Lengvári L, et al. Mevalonate Kinase Deficiency: An Updated Clinical Overview and Revision of the SHARE Recommendations — Front Immunol (2024)
- Mevalonate Kinase Deficiency — MedlinePlus Genetics, NLM
- Smith-Lemli-Opitz Syndrome — MedlinePlus Genetics, NLM
- Familial Hypercholesterolemia — MedlinePlus Genetics, NLM
- Horton JD, et al. SREBPs: Activators of the Complete Program of Cholesterol and Fatty Acid Synthesis in the Liver — J Clin Invest (2002)
- Radhakrishnan A, et al. Sterol-Regulated Transport of SREBPs from Endoplasmic Reticulum to Golgi: Oxysterols Block Transport by Binding to Insig — PNAS (2007)
- Song BL, et al. Insig-Mediated Degradation of HMG CoA Reductase Stimulated by Lanosterol, an Intermediate in the Synthesis of Cholesterol — Cell Metab (2005)
- Ness GC, et al. Insulin and Glucagon Modulate Hepatic 3-Hydroxy-3-Methylglutaryl-Coenzyme A Reductase Activity by Affecting Immunoreactive Protein Levels — J Biol Chem (1994)
- Easom RA, Zammit VA. Acute Effects of Starvation and Treatment of Rats with Anti-Insulin Serum, Glucagon and Catecholamines on the State of Phosphorylation of Hepatic 3-Hydroxy-3-Methylglutaryl-CoA Reductase In Vivo — Biochem J (1987)
- Lu XY, et al. Feeding Induces Cholesterol Biosynthesis via the mTORC1–USP20–HMGCR Axis — Nature (2020)
- Gill S, et al. Cholesterol-Dependent Degradation of Squalene Monooxygenase, a Control Point in Cholesterol Synthesis beyond HMG-CoA Reductase — Cell Metab (2011)
- Mitsche MA, et al. Flux Analysis of Cholesterol Biosynthesis In Vivo Reveals Multiple Tissue and Cell-Type Specific Pathways — eLife (2015)
- Kavanagh KL, et al. The Molecular Mechanism of Nitrogen-Containing Bisphosphonates as Antiosteoporosis Drugs — PNAS (2006)
- FDA Requests Removal of Strongest Warning Against Using Cholesterol-Lowering Statins During Pregnancy — U.S. Food and Drug Administration (2021)
- Atorvastatin Calcium Tablets Label — DailyMed, NLM (2025)
- NEXLETOL (Bempedoic Acid) Label — DailyMed, NLM (2026)
- ZETIA (Ezetimibe) Label — DailyMed, NLM (2025)
- ILARIS (Canakinumab) Label — DailyMed, NLM (2026)
- Terbinafine Tablets Label — DailyMed, NLM (2026)
- Fluconazole Tablets Label — DailyMed, NLM (2025)
- HMG-CoA Reductase, P04035 — UniProtKB
- Mevalonate Kinase, Q03426 — UniProtKB
- Farnesyl Pyrophosphate Synthase, P14324 — UniProtKB
- Squalene Synthase, P37268 — UniProtKB
- Squalene Monooxygenase, Q14534 — UniProtKB
- Lanosterol 14-Alpha Demethylase, Q16850 — UniProtKB
- Dehydrodolichyl Diphosphate Synthase, Q86SQ9 — UniProtKB
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
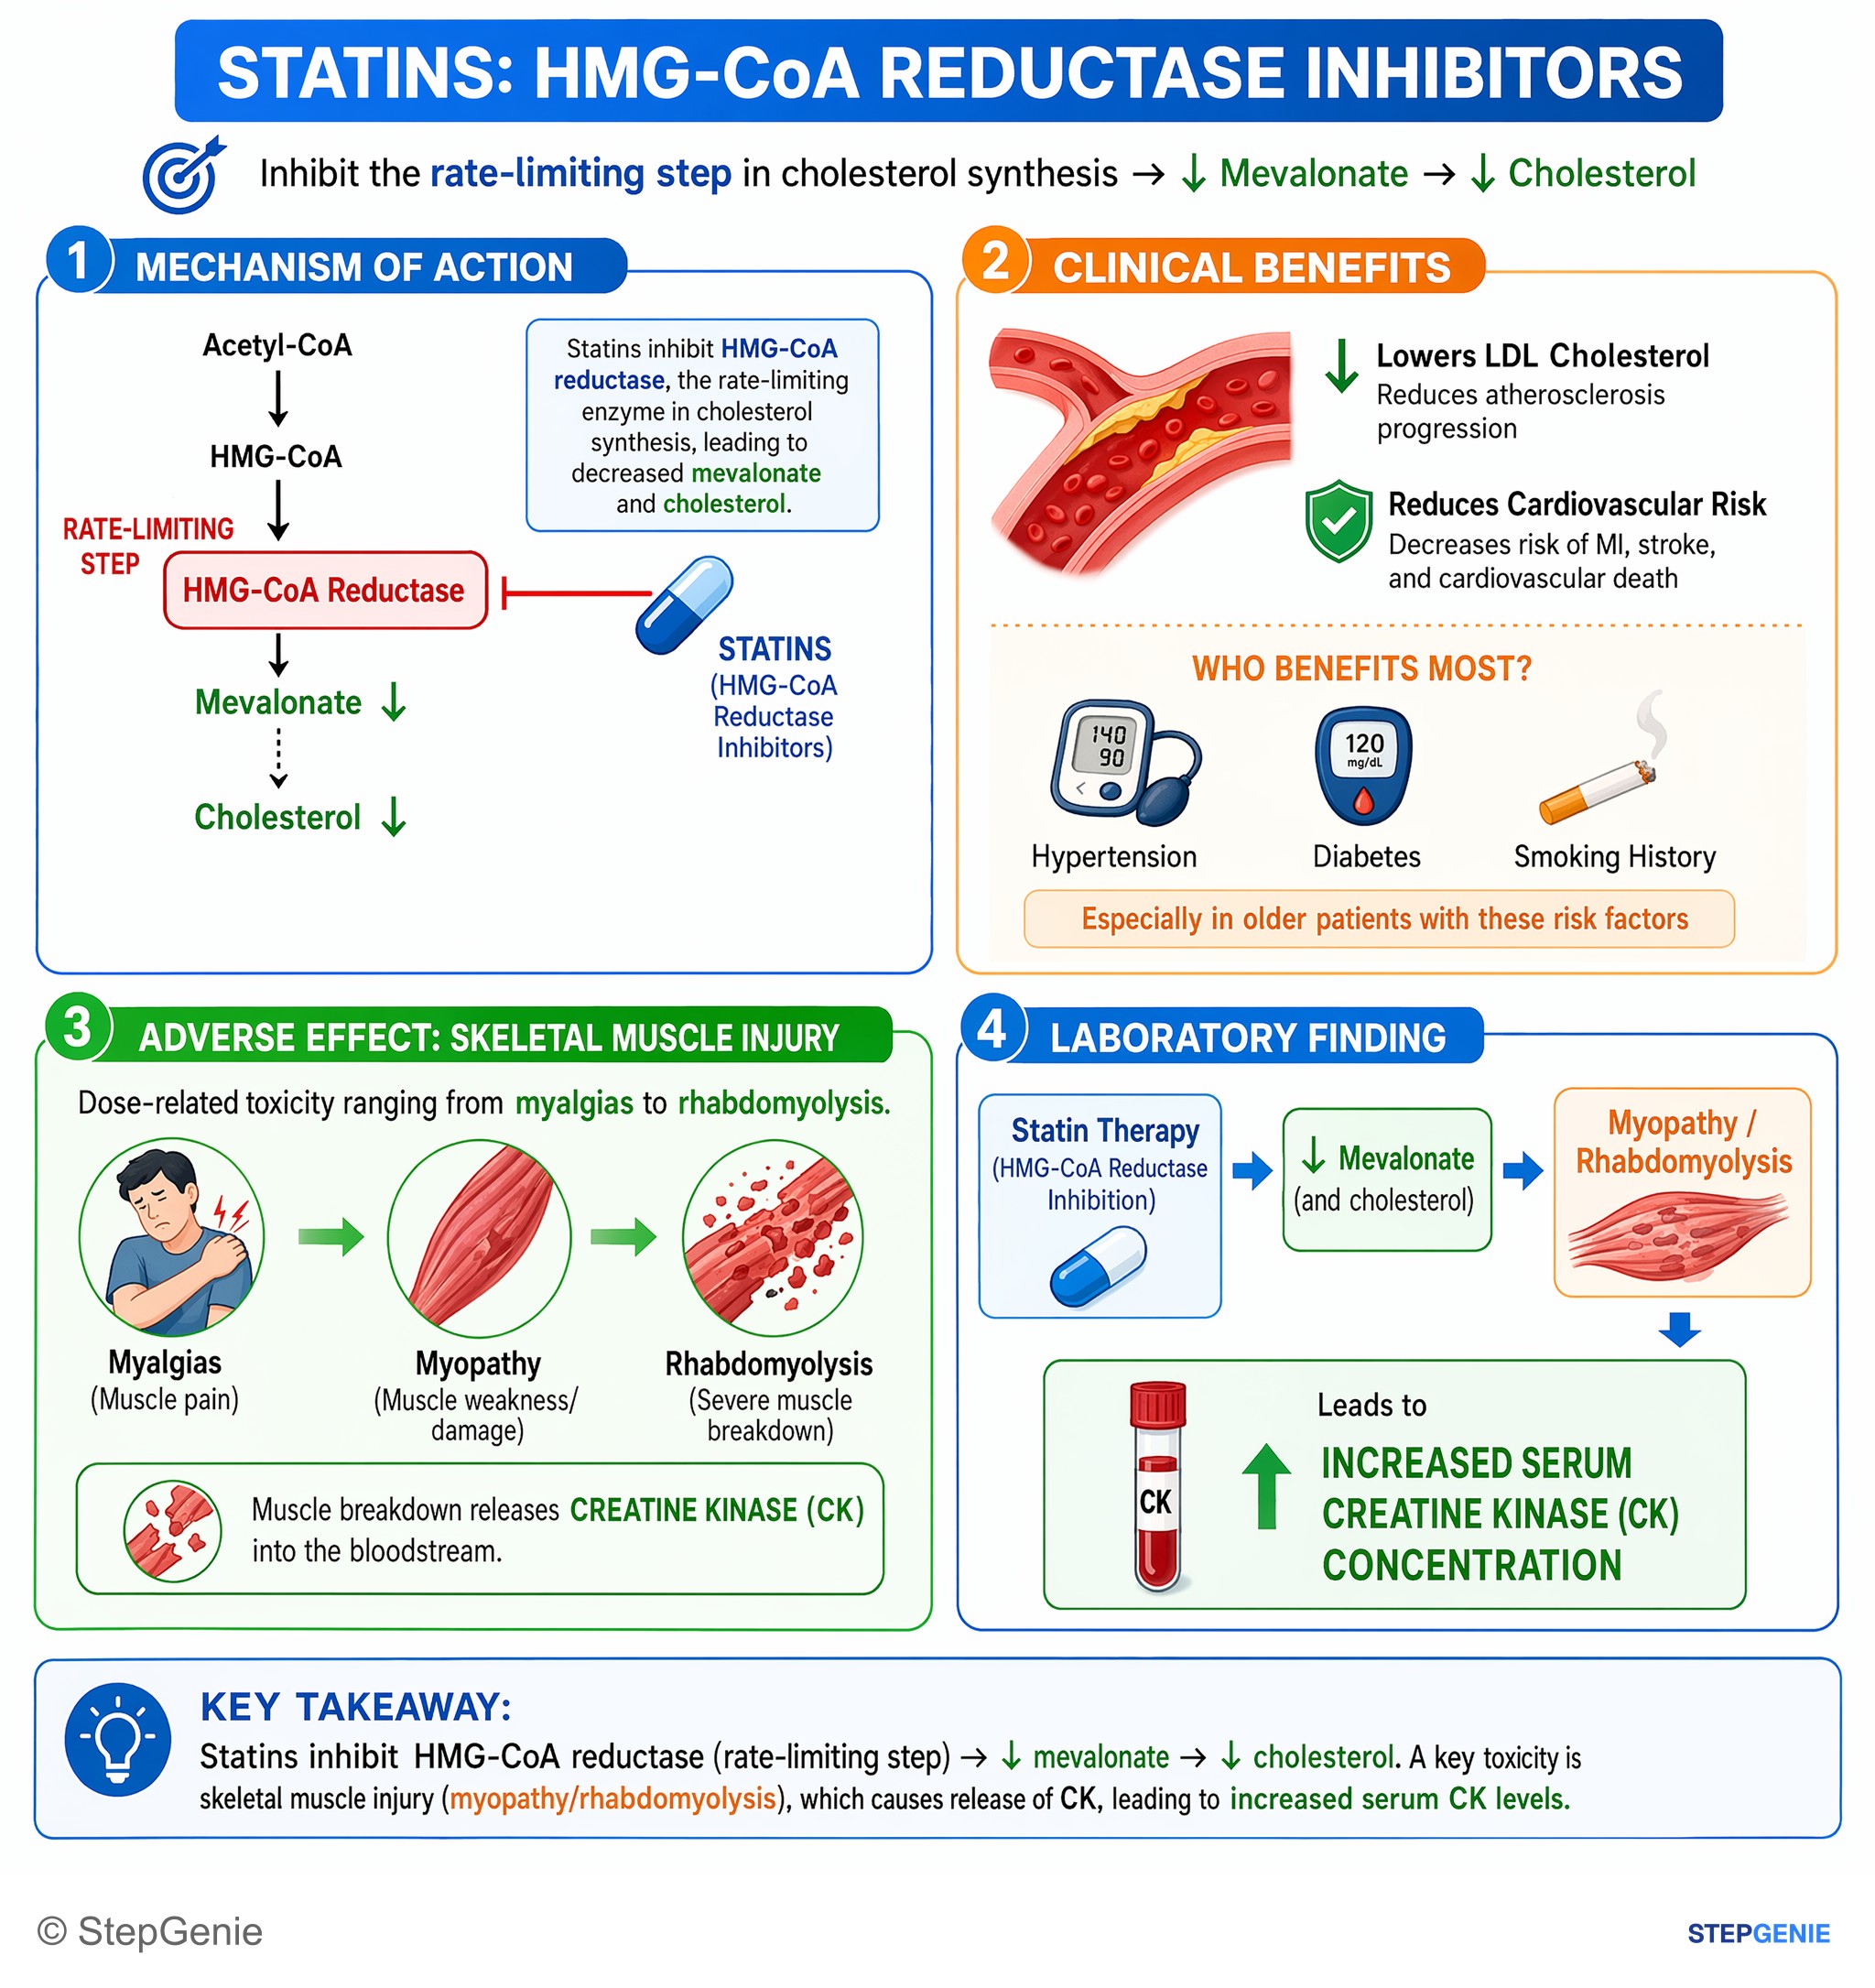
Statin therapy (HMG-CoA reductase inhibition → ↓mevalonate) can cause myopathy/rhabdomyolysis, leading to elevated serum creatine kinase.
USMLE Step 1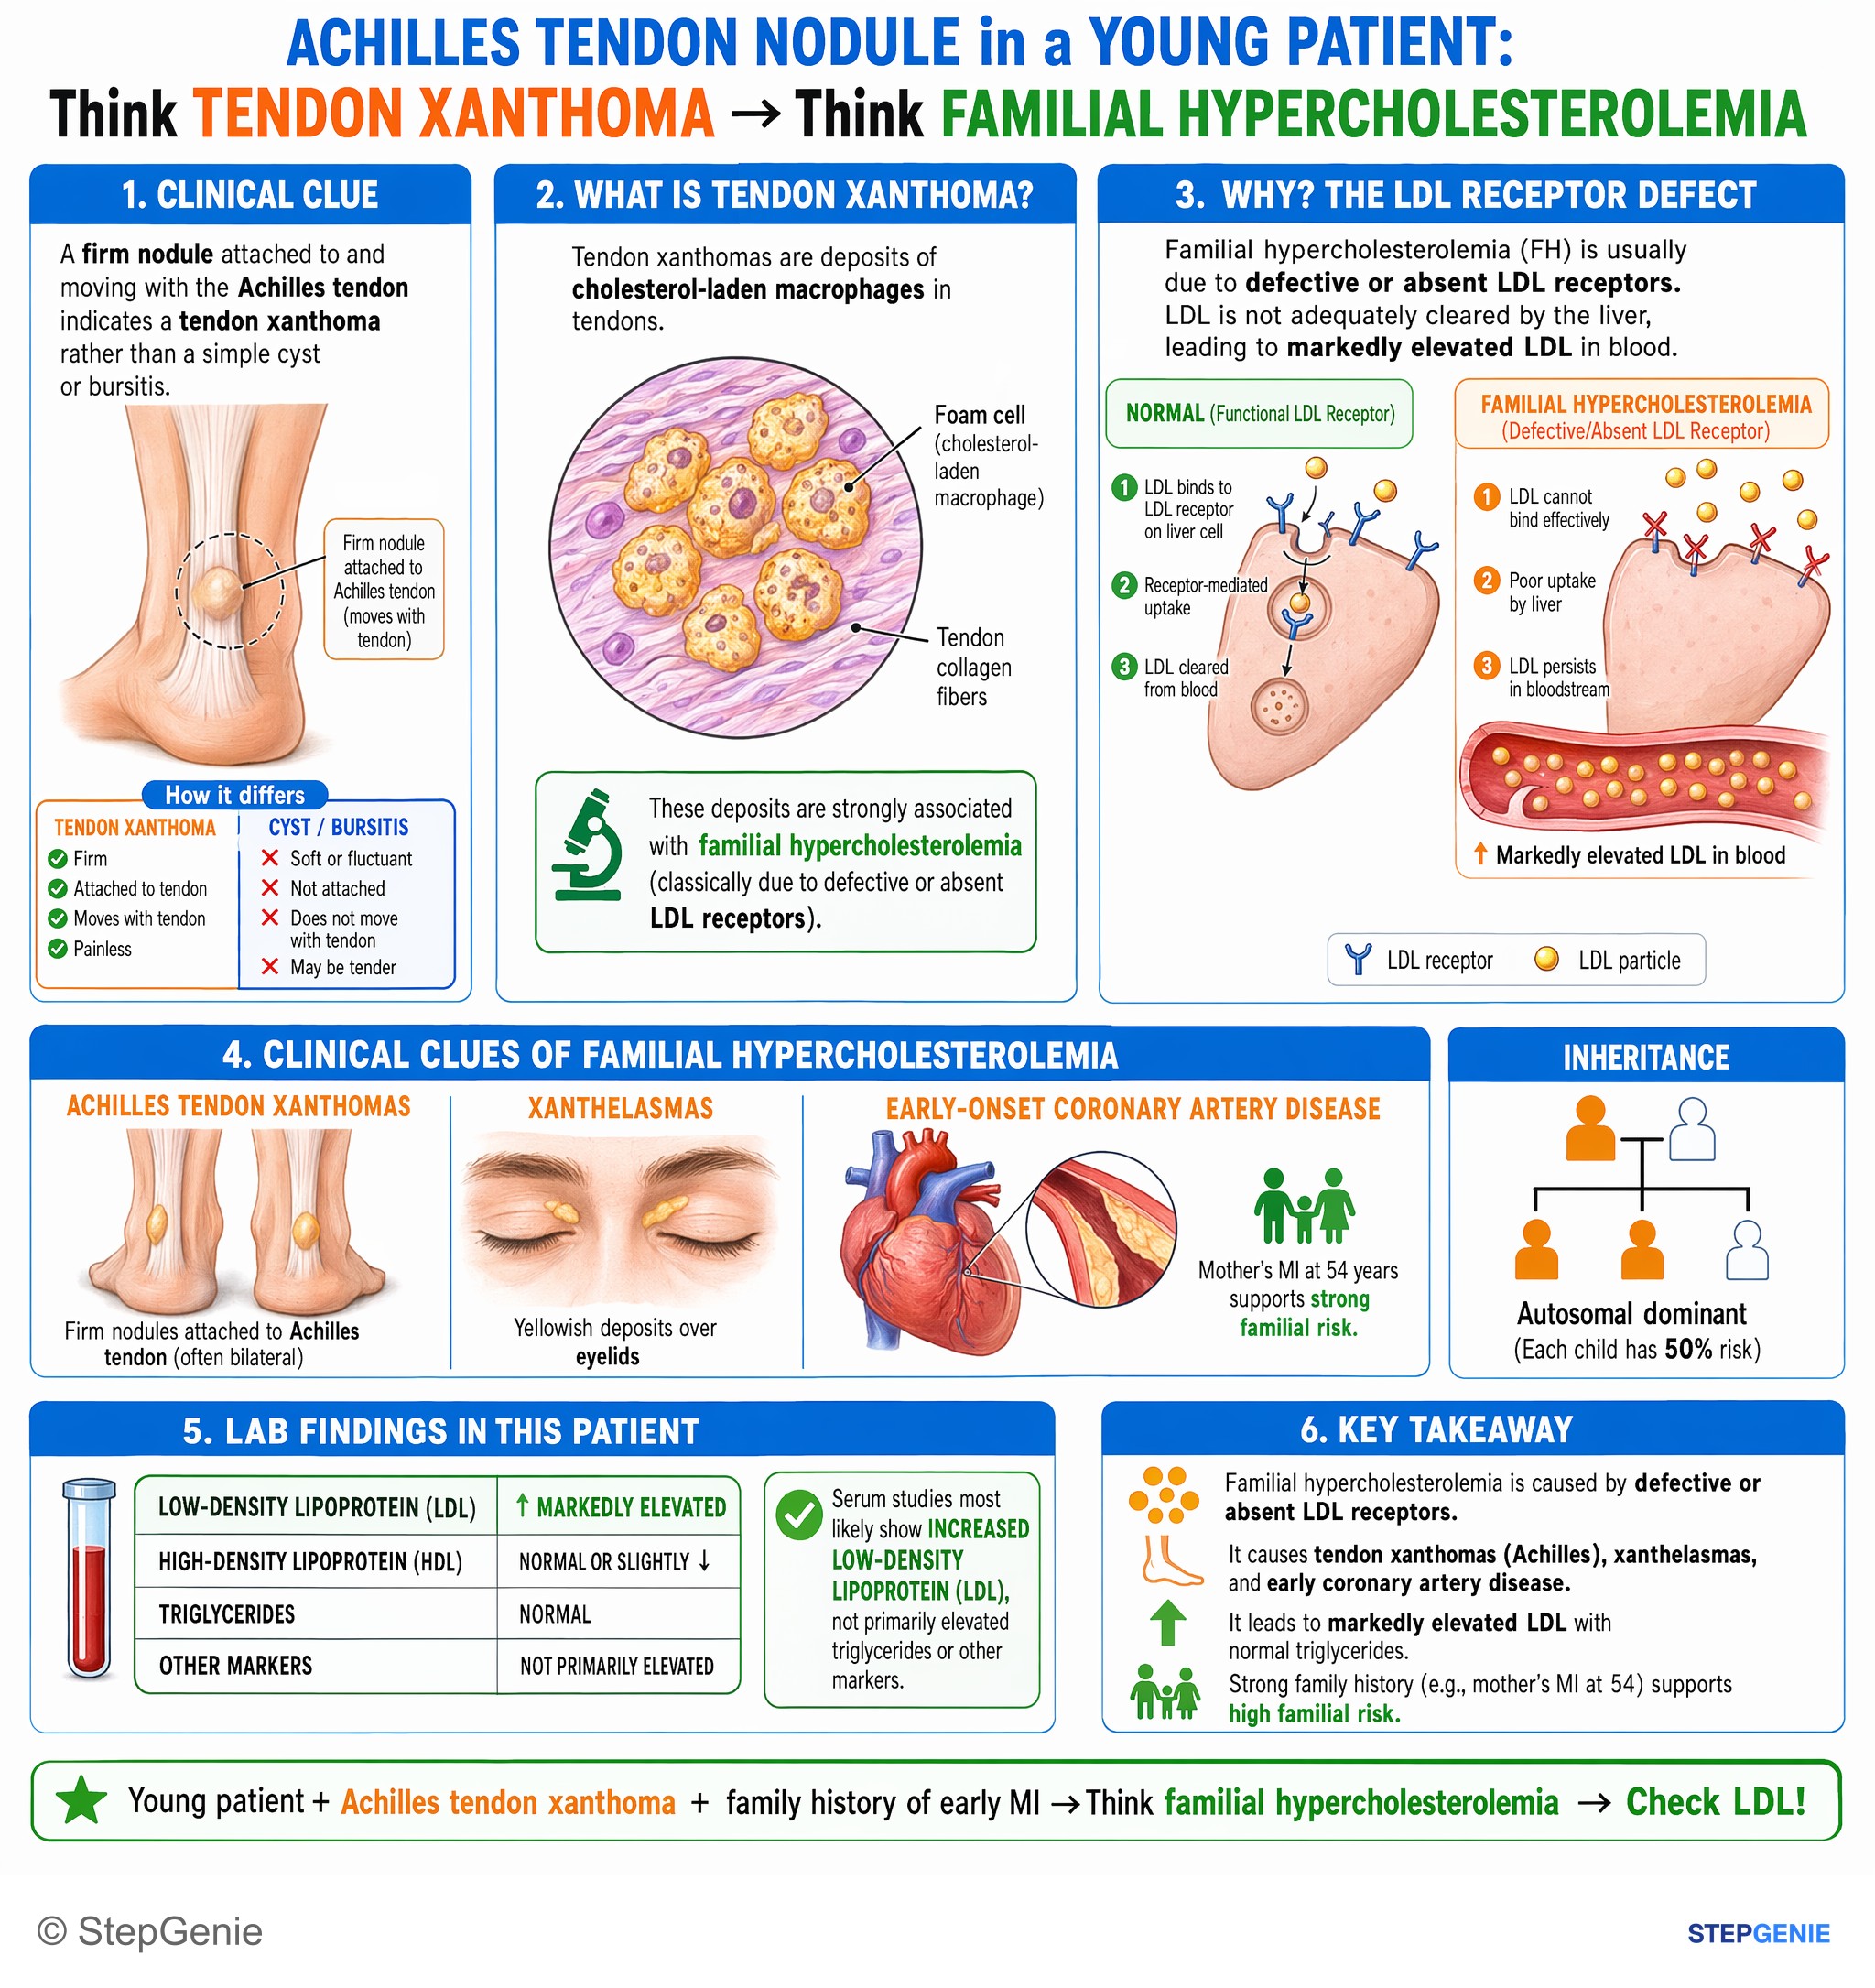
Familial hypercholesterolemia causes tendon xanthomas (Achilles), early CAD, and markedly elevated LDL with normal triglycerides.
USMLE Step 1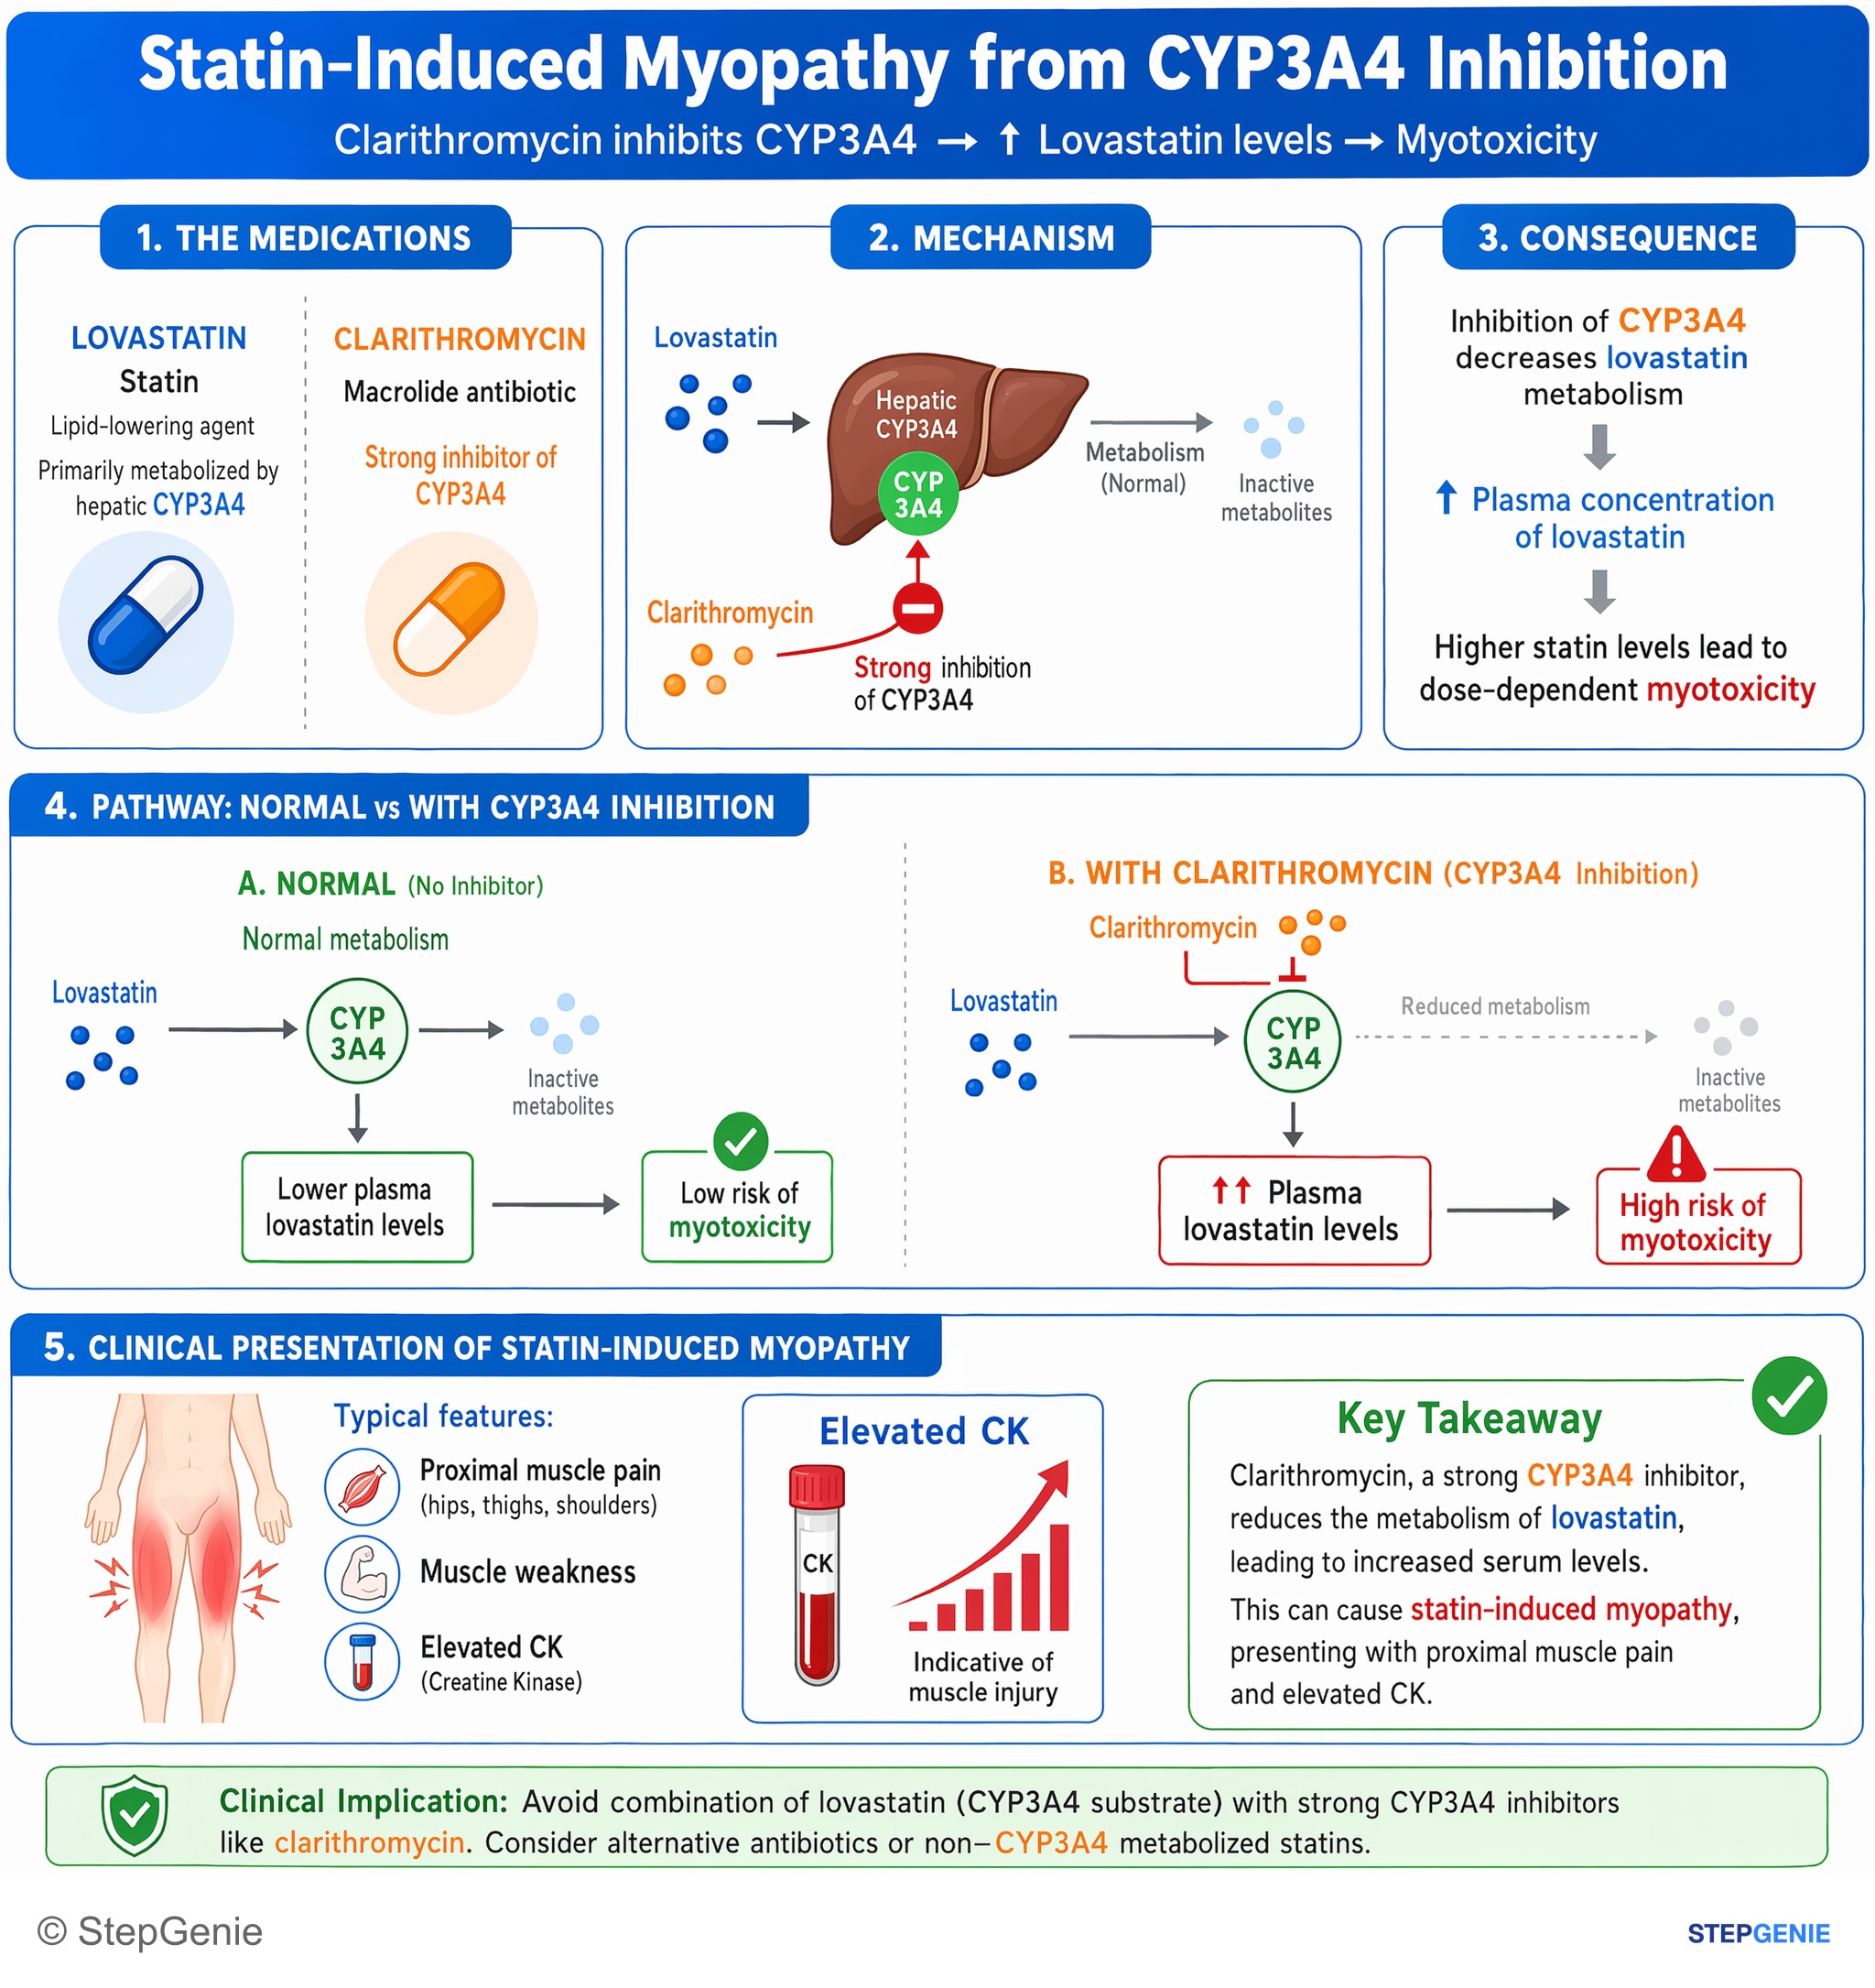
Statin-induced myopathy due to clarithromycin inhibition of CYP3A4, increasing serum lovastatin and causing proximal muscle pain and…
USMLE Step 1Frequently Asked Questions
What are the steps of the cholesterol synthesis pathway?
Cholesterol is built from acetyl-CoA in the cytosol and endoplasmic reticulum, mainly in the liver. Two acetyl-CoA form acetoacetyl-CoA, a third makes HMG-CoA, and HMG-CoA reductase reduces it to mevalonate. Mevalonate becomes isopentenyl pyrophosphate, the 5-carbon unit that builds geranyl pyrophosphate and farnesyl pyrophosphate. Two farnesyl pyrophosphates join to form squalene, which is epoxidized and cyclized to lanosterol, the first sterol. About 19 more reactions turn lanosterol into cholesterol.
What is the rate-limiting step of cholesterol synthesis?
The rate-limiting step is HMG-CoA reductase, an endoplasmic reticulum enzyme that reduces HMG-CoA to mevalonate using two NADPH. Low cell sterols raise its transcription through SREBP-2, and feeding protects it from degradation. High sterols, especially lanosterol, make it bind INSIG proteins and be degraded, and AMP-activated protein kinase inactivates it by phosphorylation when energy is low. Statins inhibit it competitively. Do not confuse it with mitochondrial HMG-CoA synthase, the rate-limiting enzyme of ketogenesis.
Where does cholesterol synthesis take place?
Almost all cells can make some cholesterol, but the liver is the major site. The enzymes work in the cytosol and the smooth endoplasmic reticulum: HMG-CoA reductase is an integral membrane protein of the endoplasmic reticulum, and squalene synthase and the later enzymes are bound there too. Mitochondria only supply the acetyl-CoA, which leaves them as citrate and is released in the cytosol by ATP-citrate lyase, the enzyme bempedoic acid inhibits.
What is a mnemonic for the cholesterol synthesis pathway?
Use All Hungry Med Interns Find Some Leftover Cake: acetyl-CoA, HMG-CoA, mevalonate, isopentenyl pyrophosphate, farnesyl pyrophosphate (by way of geranyl pyrophosphate), squalene, lanosterol and cholesterol. Then count carbons along the line: 2, 6, 5, 10, 15, 30 and 27. The count falls only twice, when mevalonate loses carbon dioxide on the way to isopentenyl pyrophosphate and when lanosterol loses three methyl groups on the way to cholesterol.
What does the mevalonate pathway make besides cholesterol?
Farnesyl pyrophosphate is the branch point. Extending it with more isoprene units makes the side chain of coenzyme Q10 and dolichol phosphate, the sugar carrier for protein glycosylation in the endoplasmic reticulum. Farnesyl and geranylgeranyl groups are also attached to small GTPases such as Ras and Rho, a step called prenylation; nitrogen-containing bisphosphonates block it in osteoclasts. Cholesterol itself becomes bile acids and steroid hormones, and its precursor 7-dehydrocholesterol becomes vitamin D3.
How do statins lower LDL cholesterol?
Statins competitively inhibit HMG-CoA reductase, so liver cells make less cholesterol. The fall in liver cholesterol activates SREBP-2, which raises the number of LDL receptors, so more LDL is cleared from the blood; LDL cholesterol can fall by as much as 50 to 60%. SREBP-2 also raises PCSK9, so PCSK9 antibodies work even better in patients taking statins. Muscle symptoms are the most common side effect, and transaminases and HbA1c can rise.