The Fredrickson types name the lipoprotein that accumulates: type I chylomicrons, IIa LDL, IIb LDL plus VLDL, III remnants (IDL), IV VLDL, and V chylomicrons plus VLDL. The usual disorders behind them are familial chylomicronemia syndrome (I), familial hypercholesterolemia (IIa), familial combined hyperlipidemia (IIb), familial dysbetalipoproteinemia (III), familial hypertriglyceridemia (IV) and multifactorial chylomicronemia (V).
The mnemonic: I scream for cream (chylomicrons float as a cream layer), IIa = LDL alone, IIb = both LDL and VLDL, III = E written backwards (apoE), IV = Increased VLDL, and 1 + 4 = 5 (type I's chylomicrons plus type IV's VLDL).
Then sort by danger: chylomicron types (I, V) cause pancreatitis, LDL and remnant types (IIa, IIb, III) cause premature atherosclerosis, and type IV raises cardiovascular risk and can tip into pancreatitis.
Familial dyslipidemias mnemonic: Fredrickson types I–V at a glance
| Type and hook | Lipoprotein up | Disorder today | Cause | Signature clues | Main risk |
|---|---|---|---|---|---|
| I: "I scream for cream" | Chylomicrons | Familial chylomicronemia syndrome (FCS) | Biallelic LPL (most), APOC2, APOA5, GPIHBP1 or LMF1; recessive | Child or teen with pancreatitis, eruptive xanthomas, lipemia retinalis, hepatosplenomegaly | Pancreatitis |
| IIa: "a = alone" | LDL | Familial hypercholesterolemia (FH) | LDLR (most), APOB or gain-of-function PCSK9; dominant | Tendon xanthomas, corneal arcus before 45, early MI | Premature ASCVD |
| IIb: "b = both" | LDL + VLDL | Familial combined hyperlipidemia (FCHL) | Polygenic; liver overproduces apoB-containing VLDL | High apoB; relatives with IIa, IIb or IV patterns | Premature ASCVD |
| III: "E backwards is 3" | Remnants (beta-VLDL, IDL) | Familial dysbetalipoproteinemia | APOE ε2/ε2 plus a second hit; about 10% dominant APOE variants | Cholesterol and triglycerides about equal; palmar crease and tuberoeruptive xanthomas | Premature CAD and PAD |
| IV: "Increased VLDL" | VLDL | Familial hypertriglyceridemia | Polygenic; liver overproduces VLDL | TG 250 to 1,000 mg/dL with normal LDL and apoB; obesity, insulin resistance | ASCVD; pancreatitis if TG soars |
| V: "1 + 4 = 5" | Chylomicrons + VLDL | Multifactorial chylomicronemia syndrome (MCS) | Polygenic background plus diabetes, obesity, alcohol or drugs | Adult with TG in the thousands and pancreatitis | Pancreatitis and ASCVD |
Large chylomicrons may be too big to enter the artery wall, but triglyceride-rich remnants enter it easily, so very high triglycerides do not always add atherosclerotic risk (Endotext).
What the Fredrickson classification is, and why it is dated
Fredrickson, Levy and Lees grouped hyperlipidemias in the late 1960s by paper electrophoresis and by whether chylomicrons persisted in fasting plasma (Endotext); a 1970 World Health Organization memorandum co-authored by Fredrickson made it an international classification.
- It describes phenotypes, not genes. One family with FCHL can show IIa, IIb and IV patterns, and secondary causes can produce the same patterns.
- Most triglyceride types are polygenic. Apart from type I, types IV and V reflect many small-effect variants plus triggers; Endotext calls the scheme "dated" and little used.
- Newer schemes are simpler. A European Atherosclerosis Society panel split hypertriglyceridemia into mild-to-moderate (2 to 10 mmol/L, about 175 to 885 mg/dL) and severe (above 10 mmol/L), where monogenic causes become likelier (Hegele 2014); apoB helps sort them: high in FCHL, not raised in familial hypertriglyceridemia, low in FCS (Endotext; Spagnuolo 2025). Review the pathways in lipoprotein metabolism.
| Disorder (usual type) | Approximate frequency |
|---|---|
| FCHL (IIb, also IIa or IV) | About 1 in 100 |
| Familial hypertriglyceridemia (IV) | About 1% |
| Heterozygous FH (IIa) | About 1 in 250 (older texts: 1 in 500) |
| Dysbetalipoproteinemia (III) | About 0.4% of men and 0.2% of women |
| MCS (V) | About 1 in 600 to 1,000 |
| Homozygous FH (IIa) | About 1 in 160,000 to 400,000 |
| FCS (I) | About 1 in 300,000 to 1,000,000 |
Type I: familial chylomicronemia syndrome (FCS)
FCS, formerly type I hyperlipoproteinemia, is autosomal recessive. LPL deficiency is the most common form; the others knock out proteins LPL needs (GeneReviews; Endotext):
| Gene | Normal job |
|---|---|
| LPL | Hydrolyzes triglyceride in chylomicrons and VLDL on the capillary endothelium of fat, heart and muscle |
| APOC2 | Apo C-II, the activating cofactor of LPL (apo C-III inhibits it) |
| APOA5 | Stabilizes the lipoprotein-enzyme complex and enhances lipolysis |
| GPIHBP1 | Carries LPL into the capillary lumen and anchors chylomicrons beside it |
| LMF1 | Endoplasmic reticulum chaperone needed to activate LPL |
- Presentation: LPL deficiency usually starts in childhood (about 25% before age 1) with abdominal pain, recurrent pancreatitis, eruptive xanthomas (about half of patients, once TG exceeds about 2,000 mg/dL) and hepatosplenomegaly; lipemia retinalis appears above about 4,000 mg/dL (GeneReviews). The rarer forms often present later. In FCS, pregnancy raises pancreatitis risk about 120-fold.
- Labs: fasting plasma stays milky, untreated TG usually exceeds 2,000 mg/dL, and apoB is low. Absent post-heparin LPL activity confirms LPL deficiency; validated clinical FCS scores can stand in for a genetic diagnosis.
- Diet: fat no more than 20 g/day or 15% of energy; medium-chain triglycerides reach the portal vein without forming chylomicrons (GeneReviews).
- Drugs: the usual lipid drugs, fibrates included, do not work in LPL deficiency, and fish oil supplements are contraindicated because they can raise triglycerides (GeneReviews; Endotext). Two apoC-III-silencing drugs, which lower triglycerides even without LPL (Endotext), are FDA-approved as an adjunct to diet in adults with FCS: olezarsen (Tryngolza, a monthly antisense oligonucleotide, December 2024) and plozasiran (Redemplo, an siRNA given every 3 months, November 2025).
- Avoid: alcohol, oral estrogens, diuretics, isotretinoin, glucocorticoids, SSRIs and beta-blockers.
Is type I really non-atherogenic? Classic teaching says yes: chylomicrons are too large to enter the artery wall and LDL is low. Cardiovascular disease is uncommon in FCS, but premature atherosclerosis is documented (Endotext); all four LPL-deficient adults studied by Benlian and colleagues had coronary or peripheral atherosclerosis before 55. Heterozygous LPL carriers and many MCS patients have more ASCVD (GeneReviews; Endotext). Drill the apolipoprotein roles in apolipoprotein functions.
Type IIa: familial hypercholesterolemia (FH)
FH is all A's:
- Autosomal dominant: about 1 in 250 people are heterozygous.
- Achilles (and hand extensor) tendon xanthomas: historically 30% to 50% of patients, fewer now with widespread statin use.
- Arcus, corneal, before 45 suggests FH.
- Atherosclerosis early: untreated men carry a 50% risk of a coronary event by 50, women 30% by 60.
- ApoB-100, LDL receptor or PCSK9: LDL clearance fails.
| Gene | Defect | Share of FH | Inheritance |
|---|---|---|---|
| LDLR | Absent or faulty LDL receptors | Over 50% | Dominant |
| APOB | ApoB-100 binds the receptor poorly (familial defective apoB-100) | About 5% to 10% | Dominant |
| PCSK9 | Gain of function speeds LDL receptor degradation | Under 1% | Dominant |
| LDLRAP1 | Adaptor needed to internalize the receptor | Under 1% | Recessive |
| None found | Polygenic or unknown | About 40% of clinical FH | Not applicable |
Untreated LDL is typically above 190 mg/dL in adults (above 160 mg/dL in children). Genotype matters: with LDL above 190 mg/dL, an FH variant raises coronary risk about 22-fold versus 6-fold without one (GeneReviews).
Homozygous FH (HoFH) means two defective alleles: LDL often above 500 mg/dL, interdigital and tendon xanthomas in childhood, atherosclerosis of the aortic root and coronary ostia, and severe CAD by the mid-20s in most (GeneReviews; EAS). The 2023 EAS consensus lowered the flag to untreated LDL above 400 mg/dL, supported by xanthomas before age 10 or FH-range LDL in both parents.
Treating FH in 2026
The 2026 multisociety guideline replaced the 2018 cholesterol guideline and brings back LDL goals:
- LDL 190 mg/dL or more: exclude secondary causes, then a maximally tolerated statin, which blocks HMG-CoA reductase in the cholesterol synthesis pathway. Population risk calculators do not apply to FH (GeneReviews).
- Goals: LDL under 100 mg/dL at borderline or intermediate risk, under 70 at high risk or with any ASCVD, and under 55 with very high-risk ASCVD. If a statin is not enough, add ezetimibe, bempedoic acid or a PCSK9 antibody such as evolocumab (ACC). Inclisiran (an siRNA against PCSK9) lacked outcome data in March 2026.
- Genetic testing: a variant confirms FH and marks higher risk at the same LDL; cascade-screen relatives (GeneReviews).
- HoFH: statins, ezetimibe, bempedoic acid and PCSK9 antibodies act by raising LDL receptor expression, so they work poorly or not at all when both alleles are null (GeneReviews; EAS 2023). Receptor-independent options are evinacumab (an ANGPTL3 antibody, FDA-approved from age 1), lomitapide (an MTP inhibitor, from age 2, with a hepatotoxicity boxed warning and REMS) and lipoprotein apheresis.
Type IIb: familial combined hyperlipidemia (FCHL)
FCHL is the most common inherited dyslipidemia, about 1 in 100 people (Endotext), and 10% to 20% of survivors of premature MI have it (StatPearls). Once thought to be a dominant single-gene disease, it is polygenic. The liver overproduces apoB-containing VLDL, with small dense LDL, fatty liver and insulin resistance.
Clues are a high apoB (sometimes with otherwise normal lipids), relatives with IIa, IIb or IV patterns and, unlike FH, few xanthomas. Statin-based therapy with lifestyle change is the foundation; when triglycerides are high, non-HDL-C goals and optional apoB testing help guide treatment once LDL is at goal (2026 ACC/AHA).
Type III: familial dysbetalipoproteinemia
Also called broad beta disease or remnant removal disease. ApoE2 differs from apoE3 by one amino acid (cysteine for arginine at residue 158) and is poorly recognized by the LDL receptor (Endotext), so chylomicron and VLDL remnants (IDL, or beta-VLDL) pile up.
- Genotype is necessary but not sufficient. ApoE2/E2 occurs in 0.2% to 1.3% of people, yet under 20% become hyperlipidemic; most are normolipidemic or even hypolipidemic (Endotext). Disease needs a second hit: obesity, diabetes or insulin resistance, hypothyroidism (fewer LDL receptors), alcohol, or loss of estrogen at menopause. About 10% of cases come from dominant APOE variants such as APOE-Leiden.
- Lipids: total cholesterol and triglycerides rise roughly equally; Endotext suggests suspecting it when both lie between 300 and 1,000 mg/dL. True LDL is almost always low and cannot be measured or calculated reliably (a classic trap), so follow non-HDL-C.
- Skin: palmar crease xanthomas (xanthoma striata palmaris) are characteristic but appear in fewer than half of patients; tuberous or tuberoeruptive xanthomas over knuckles, elbows, knees and buttocks may be more common.
- Risk: coronary risk roughly 5 to 10 times normal and PAD risk 13 times normal, 3 times that of FH (peripheral artery disease); pancreatitis occasionally.
- Treatment: fix the second hit, then statins for cholesterol and fibrates for triglycerides. It usually responds well.
Types IV and V: familial hypertriglyceridemia and multifactorial chylomicronemia
Type IV (familial hypertriglyceridemia): the liver overproduces VLDL; triglycerides run about 250 to 1,000 mg/dL with normal LDL and apoB, usually with obesity and insulin resistance (Endotext). It is often described as autosomal dominant, but recent evidence points to a polygenic basis (StatPearls).
Type V (MCS): a polygenic background, sometimes with one heterozygous variant in an FCS gene (about 10% of MCS patients carry an LPL variant), meets secondary triggers until triglyceride clearance saturates. Triggers include poorly controlled diabetes, obesity or weight regain, alcohol, pregnancy, hypothyroidism, kidney disease, and drugs such as thiazides, beta-blockers, oral estrogens, isotretinoin, glucocorticoids, HIV protease inhibitors and atypical antipsychotics (Endotext; GeneReviews).
| Feature | FCS (type I) | MCS (type V) |
|---|---|---|
| Mean age at symptom onset | 15 | 38 |
| Pancreatitis | 82% | 35% |
| ApoB | Low | Normal to high |
| After triggers are fixed | Triglycerides stay very high | Triglycerides fall toward relatives' levels |
| ASCVD | Uncommon | Increased in many |
Numbers: one genotyped cohort of 193 patients (Spagnuolo 2025).
Pancreatitis thresholds. Hypertriglyceridemia is the third most common cause of acute pancreatitis after alcohol and gallstones (Endotext). The 2026 ACC/AHA guideline makes pancreatitis prevention the priority at 1,000 mg/dL or more; Endotext puts the usual tipping point at 1,500 to 2,000 mg/dL, and keeping TG under 500 mg/dL should prevent attacks.
Treatment (2026 ACC/AHA):
- Lifestyle first: cut alcohol, added sugars and saturated fat, exercise, fix secondary causes (ACC), and switch oral estrogen to a transdermal route (Endotext).
- Statins remain first line for ASCVD risk when TG is under 1,000 mg/dL; at 1,000 mg/dL or more, preventing pancreatitis comes first.
- At 1,000 mg/dL or more, a fibrate (lowers TG 30% to 50%) is a first-line option to cut pancreatitis risk; prescription omega-3s treat residual high triglycerides after statin and diet (ACC). Since June 2026, olezarsen is also FDA-approved for adults with severe hypertriglyceridemia (TG of 500 mg/dL or more).
- Niacin is not recommended, and bile acid sequestrants can raise triglycerides (Endotext).
Read the plasma: the refrigerator test
Chylomicrons are the least dense lipoproteins (below 0.930 g/mL), so in plasma left overnight at 4°C they float as a cream layer, while VLDL (pre-beta lipoprotein) stays suspended and turns plasma opalescent (Endotext; Labcorp). Test after a fast of more than 12 hours: chylomicrons are normal after meals and persist in fasting plasma usually only when TG exceeds about 800 mg/dL.
| Refrigerated plasma and electrophoresis | Lipoproteins | Type |
|---|---|---|
| Cream layer over clear plasma | Chylomicrons only | I |
| Cream layer over opalescent to lipemic plasma | Chylomicrons + VLDL | V |
| No cream layer; raised pre-beta band | VLDL | IV |
| Usually no cream layer; broad beta band, cholesterol and TG about 1:1 | Remnants | III |
| No cream layer; raised beta and pre-beta bands | LDL + VLDL | IIb |
| No cream layer; raised beta band, normal pre-beta | LDL | IIa |
On electrophoresis chylomicrons stay at the origin, LDL runs as beta, VLDL as pre-beta, and type III remnants blur the two into a broad beta band (Labcorp; Endotext).
Look-alikes and secondary causes
| Condition | Defect | Clues | Key difference |
|---|---|---|---|
| Abetalipoproteinemia | MTTP, recessive | Infant with steatorrhea and failure to thrive; acanthocytes; vitamin E deficiency causing ataxia and retinopathy | LDL, TG and apoB absent or very low: the opposite problem |
| Sitosterolemia | ABCG5 or ABCG8, recessive | Childhood tendon xanthomas, hemolysis, thrombocytopenia | Plant sterols; poor statin response; ezetimibe and a low-sterol diet work |
| Cerebrotendinous xanthomatosis | CYP27A1, recessive | Xanthomas, cataracts, ataxia, dementia | Normal LDL |
| Lipoprotein(a) | Mostly set by the LPA gene | Premature ASCVD | Measure once in every adult; 125 nmol/L (50 mg/dL) or more adds risk |
Lomitapide inhibits the same MTP protein, so its label requires vitamin E and fatty acid supplements; see fat-soluble vitamins.
Secondary causes come first. Hypothyroidism, obstructive liver disease, kidney disease including nephrotic syndrome, diabetes, obesity and glucocorticoids raise LDL, and the type V triggers raise triglycerides (GeneReviews; Endotext). Check TSH before calling hypercholesterolemia familial; for the protein-losing pattern see nephrotic vs nephritic syndrome.
USMLE traps: classic teaching vs current evidence
| Classic line | What current sources say |
|---|---|
| "Type I carries no atherosclerosis risk" | ASCVD is uncommon in FCS, but premature atherosclerosis is documented; heterozygous LPL carriers and many MCS patients have more ASCVD |
| "Type I is LPL or apoC-II deficiency" | Also APOA5, GPIHBP1 and LMF1 |
| "Give type I a fibrate or fish oil" | Neither works in FCS, and fish oil supplements are contraindicated; use diet, plus olezarsen or plozasiran in adults |
| "FH affects 1 in 500" | About 1 in 250 |
| "HoFH means LDL above 500 mg/dL" | Untreated LDL above 400 mg/dL suggests HoFH (EAS 2023) |
| "Statins and PCSK9 inhibitors treat every FH patient" | They need working LDL receptors; null/null HoFH needs evinacumab, lomitapide or apheresis |
| "Type III is apoE2/E2 in 90%" | Under 20% of apoE2/E2 carriers become hyperlipidemic, and in a 524-patient Canadian cohort only 38% of type III patients were ε2/ε2 (Endotext 2025) |
| "Palmar xanthomas are pathognomonic" | Characteristic, but present in fewer than half and seen in other conditions |
| "Xanthelasma means FH" | Only about half of adults with xanthelasma have abnormal lipids |
Four practice vignettes
Vignette 1. A 7-year-old boy has acute pancreatitis after months of epigastric pain. Crops of yellow papules cover his buttocks and elbows, his liver and spleen are enlarged, and his retinal vessels look pale pink. Fasting triglycerides are 4,200 mg/dL; refrigerated plasma forms a cream layer over clear plasma. His parents are first cousins. Which defect is most likely?
A. LDL receptor. B. Lipoprotein lipase. C. Apolipoprotein E2 homozygosity. D. Microsomal triglyceride transfer protein. E. Hepatic VLDL overproduction.
Answer: B. Childhood pancreatitis, eruptive xanthomas, lipemia retinalis and a cream layer over clear plasma mean type I FCS, usually from biallelic LPL variants (recessive, hence consanguinity). A causes type IIa with tendon xanthomas. C causes type III in adults. D is abetalipoproteinemia, with near-absent lipids. E is type IV, with no cream layer. Treat with a very-low-fat diet; olezarsen and plozasiran are approved only for adults.
Vignette 2. A 9-year-old girl has yellow plaques between her fingers and over her Achilles tendons. Untreated LDL is 620 mg/dL; both parents have LDL near 250 mg/dL. She carries two null LDLR variants, and on a high-dose statin plus ezetimibe her LDL is 480 mg/dL. Which drug lowers LDL independently of the LDL receptor?
A. Evolocumab. B. Inclisiran. C. Evinacumab. D. Bempedoic acid. E. Fenofibrate.
Answer: C. Evinacumab blocks ANGPTL3 and lowers LDL without LDL receptors by speeding VLDL processing upstream of LDL; it is approved for HoFH from age 1. A and B reduce PCSK9 activity and need working receptors. D also acts by raising receptor expression. E mainly lowers triglycerides.
Vignette 3. A 55-year-old man with newly diagnosed hypothyroidism has yellow-orange discoloration in his palmar creases and firm yellow nodules over both elbows. Total cholesterol is 390 mg/dL and triglycerides are 410 mg/dL. He has calf pain after walking two blocks. Which genotype is most likely?
A. APOE ε2/ε2. B. Heterozygous LDLR variant. C. Biallelic LPL variants. D. APOC2 deficiency. E. PCSK9 loss of function.
Answer: A. Palmar crease and tuberoeruptive xanthomas with cholesterol and triglycerides raised about equally mean type III; hypothyroidism is the second hit that unmasked apoE2/E2, and claudication fits the high PAD risk. B raises LDL with tendon, not palmar, xanthomas. C and D cause chylomicronemia, not equal rises. E lowers LDL. Treat the hypothyroidism, then add a statin and, if needed, a fibrate.
Vignette 4. A 46-year-old woman with poorly controlled type 2 diabetes, heavy alcohol use and new oral estrogen has acute pancreatitis with triglycerides of 2,900 mg/dL; refrigerated plasma shows a cream layer over turbid plasma. After she stops alcohol and estrogen and starts insulin, fasting triglycerides stay at 1,400 mg/dL despite diet. Which added drug is most appropriate?
A. Cholestyramine. B. Fenofibrate. C. Niacin. D. Ezetimibe. E. Lomitapide.
Answer: B. This is type V MCS; with triglycerides still above 1,000 mg/dL, a fibrate is a first-line option to cut pancreatitis risk (2026 ACC/AHA), and olezarsen is now another option. A can raise triglycerides. C is not recommended. D mainly lowers LDL. E is approved only for HoFH and carries a hepatotoxicity warning. More practice is on the Biochemistry hub.
Key takeaways
- Name the type by the lipoprotein: I chylomicrons, IIa LDL, IIb LDL plus VLDL, III remnants, IV VLDL, V chylomicrons plus VLDL.
- Pancreatitis types are the chylomicron types (I, V); atherosclerosis types carry LDL or remnants (IIa, IIb, III).
- Genes: FCS from LPL, APOC2, APOA5, GPIHBP1 or LMF1; FH from LDLR, APOB or PCSK9; type III from APOE ε2/ε2 plus a second hit; IIb, IV and V are mostly polygenic.
- Xanthomas localize: tendon means FH, palmar crease means type III, eruptive means very high triglycerides.
- 2026 treatment: LDL goals are back (under 100, 70 or 55 mg/dL by risk); evinacumab or lomitapide for HoFH; a very-low-fat diet plus olezarsen or plozasiran for adults with FCS.
Sources
- Lipoprotein Lipase Deficiency — GeneReviews, NCBI Bookshelf (2026)
- Familial Hypercholesterolemia — GeneReviews, NCBI Bookshelf (2025)
- Abetalipoproteinemia — GeneReviews, NCBI Bookshelf (2022)
- Hypertriglyceridemia: Pathophysiology, Role of Genetics, Consequences, and Treatment — Endotext, NCBI Bookshelf (2024)
- Genetics and Dyslipidemia — Endotext, NCBI Bookshelf (2023)
- Dysbetalipoproteinemia (Type 3 Hyperlipoproteinemia) — Endotext, NCBI Bookshelf (2025)
- Introduction to Lipids and Lipoproteins — Endotext, NCBI Bookshelf (2024)
- Familial Hypertriglyceridemia — StatPearls, NCBI Bookshelf (2024)
- Familial Combined Hyperlipidemia — StatPearls, NCBI Bookshelf (2023)
- Sitosterolemia (Phytosterolemia) — StatPearls, NCBI Bookshelf (2023)
- Xanthelasma Palpebrarum — StatPearls, NCBI Bookshelf (2026)
- Blumenthal RS, et al. 2026 ACC/AHA Multisociety Guideline on the Management of Dyslipidemia — J Am Coll Cardiol (2026)
- ACC/AHA Issue Updated Guideline for Managing Lipids, Cholesterol — American College of Cardiology (2026)
- Getting to Goals: Applying the 2026 Dyslipidemia Guideline in High-Risk Patients — American College of Cardiology (2026)
- Top Things to Know: Guideline on the Management of Dyslipidemia — American Heart Association (2026)
- Cuchel M, et al. 2023 Update on European Atherosclerosis Society Consensus Statement on Homozygous Familial Hypercholesterolaemia — Eur Heart J (2023)
- Hegele RA, et al. The Polygenic Nature of Hypertriglyceridaemia — Lancet Diabetes Endocrinol (2014)
- Beaumont JL, et al. Classification of Hyperlipidaemias and Hyperlipoproteinaemias — Bull World Health Organ (1970)
- Benlian P, et al. Premature Atherosclerosis in Patients with Familial Chylomicronemia Caused by Mutations in the Lipoprotein Lipase Gene — N Engl J Med (1996)
- Spagnuolo CM, et al. Comparison of Patients With Familial Chylomicronemia Syndrome and Multifactorial Chylomicronemia Syndrome — J Clin Endocrinol Metab (2025)
- Lipoprotein Phenotyping Profile (Test 235036) — Labcorp
- Tryngolza (Olezarsen) Prescribing Information — DailyMed, NLM (2026)
- Redemplo (Plozasiran) Prescribing Information — DailyMed, NLM (2026)
- Evkeeza (Evinacumab) Prescribing Information — DailyMed, NLM (2025)
- Juxtapid (Lomitapide) Prescribing Information — DailyMed, NLM (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
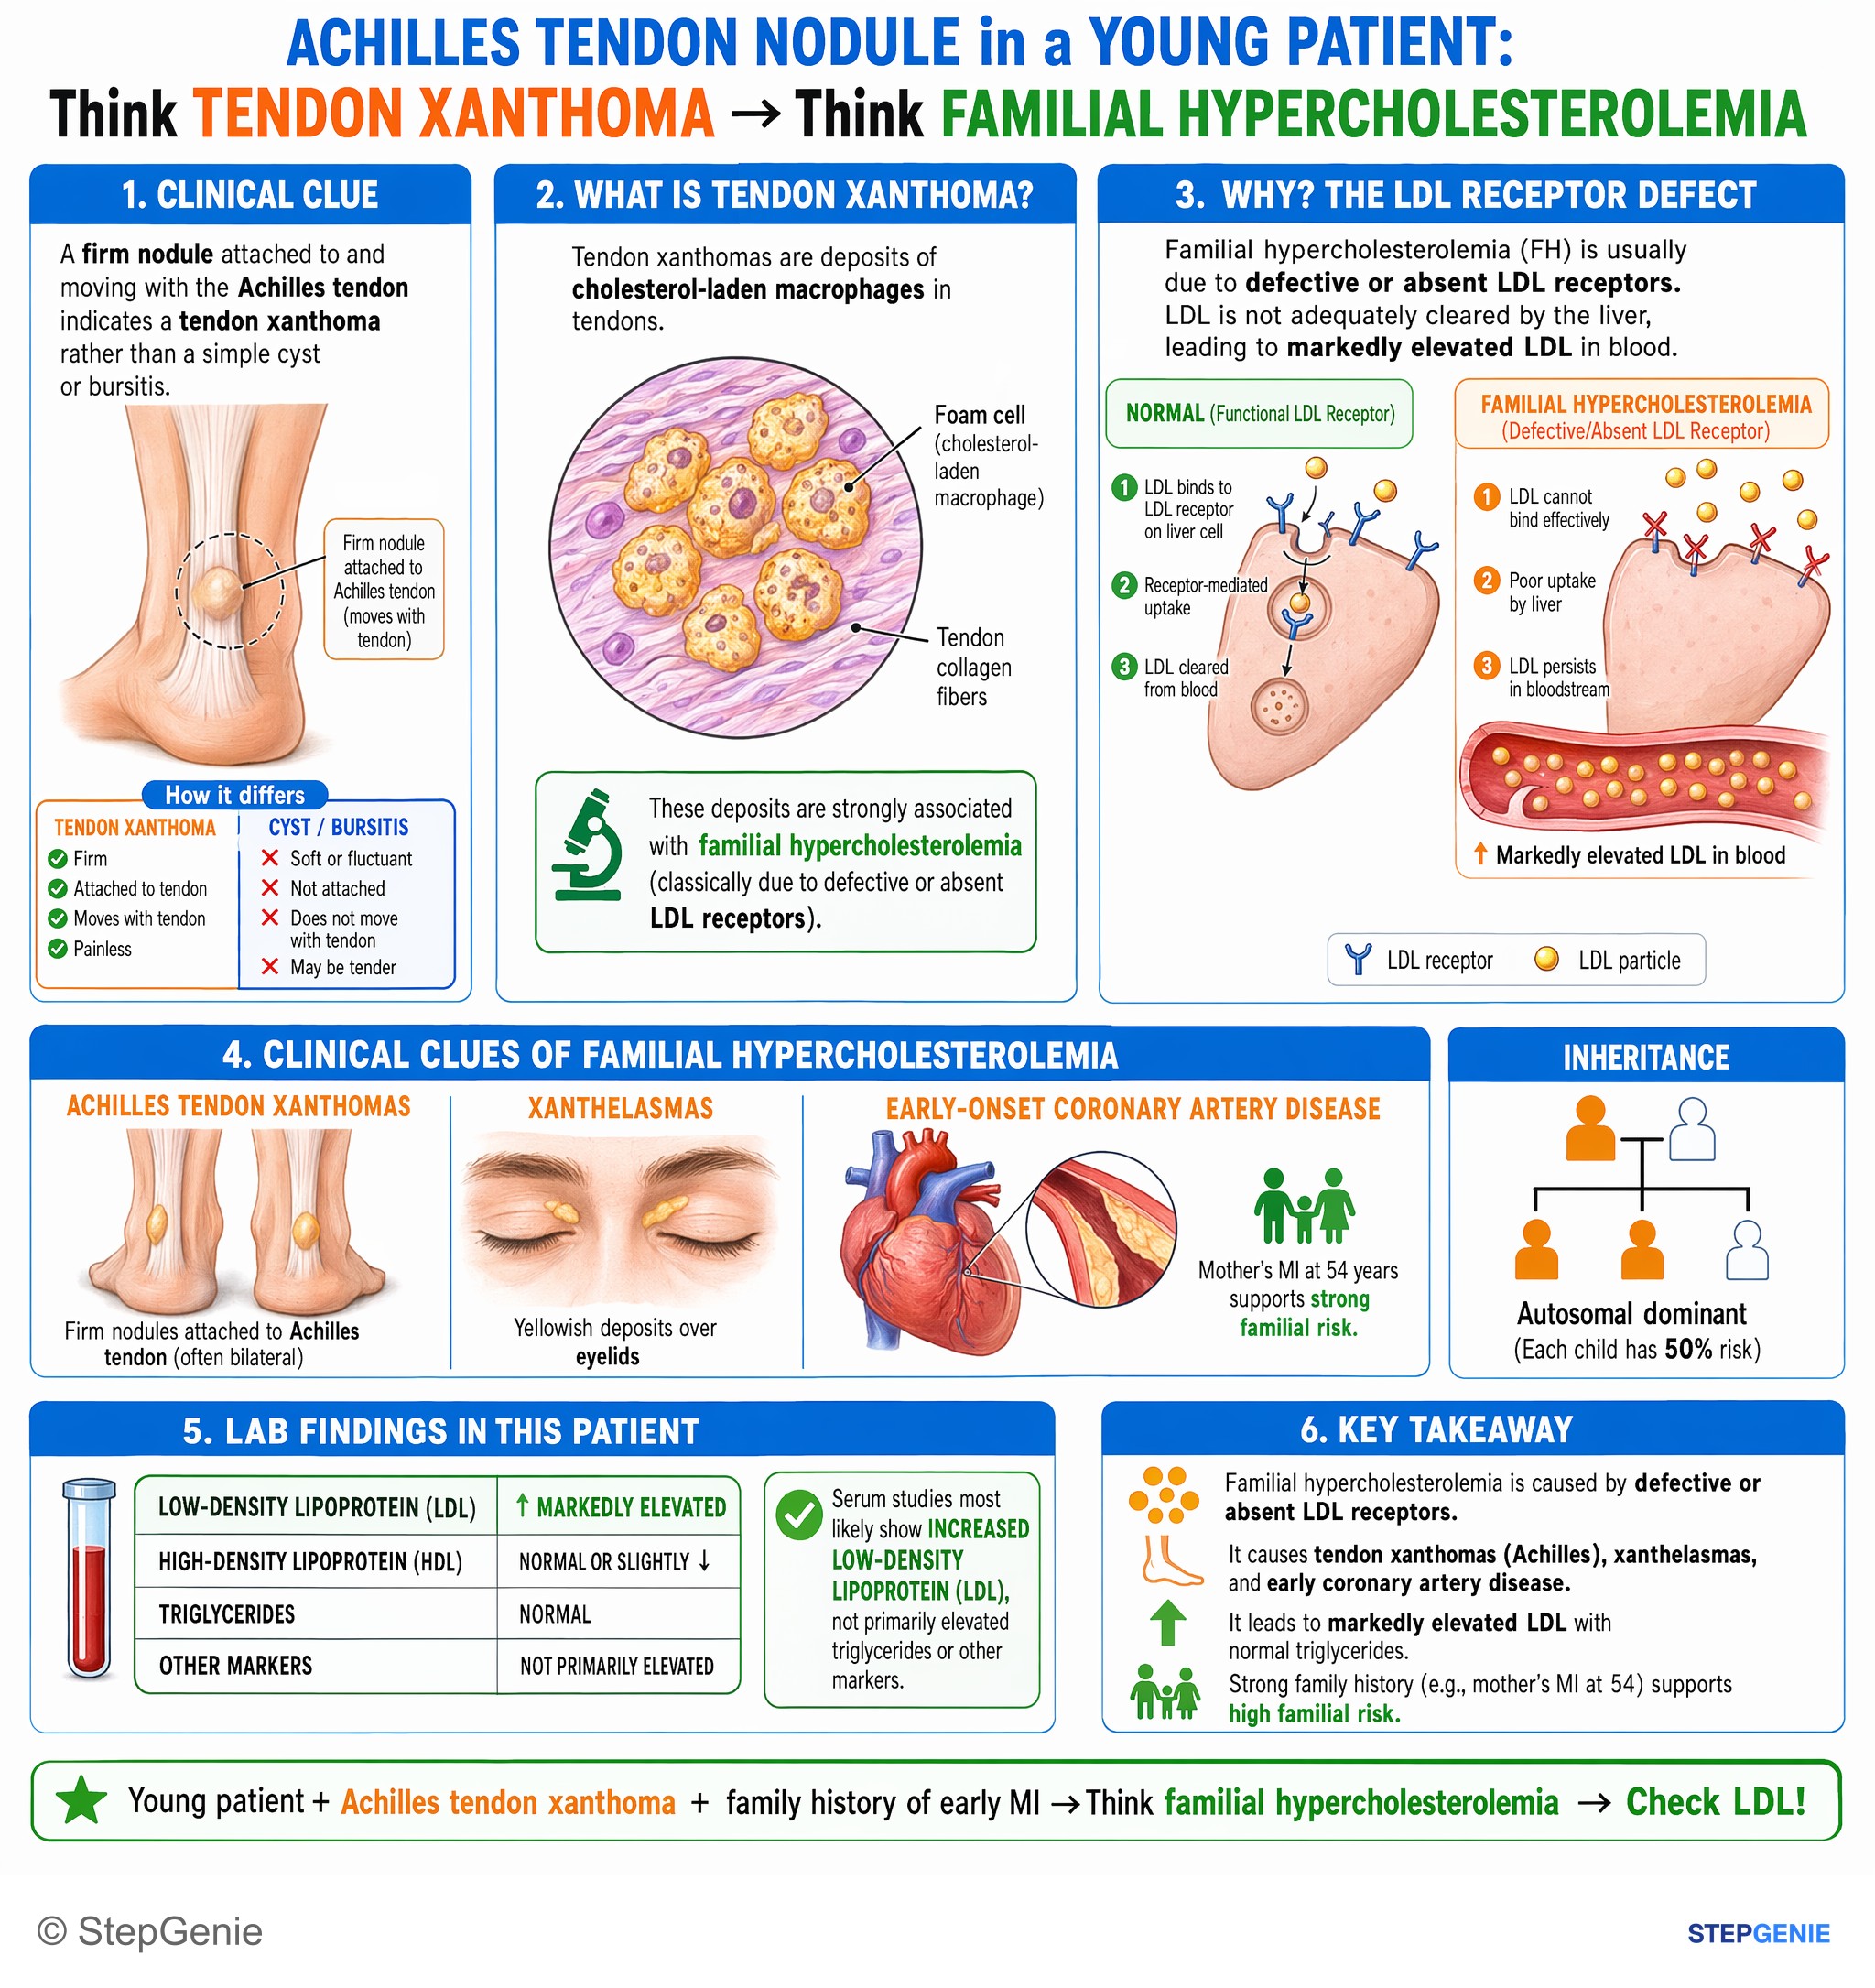
Familial hypercholesterolemia causes tendon xanthomas (Achilles), early CAD, and markedly elevated LDL with normal triglycerides.
USMLE Step 1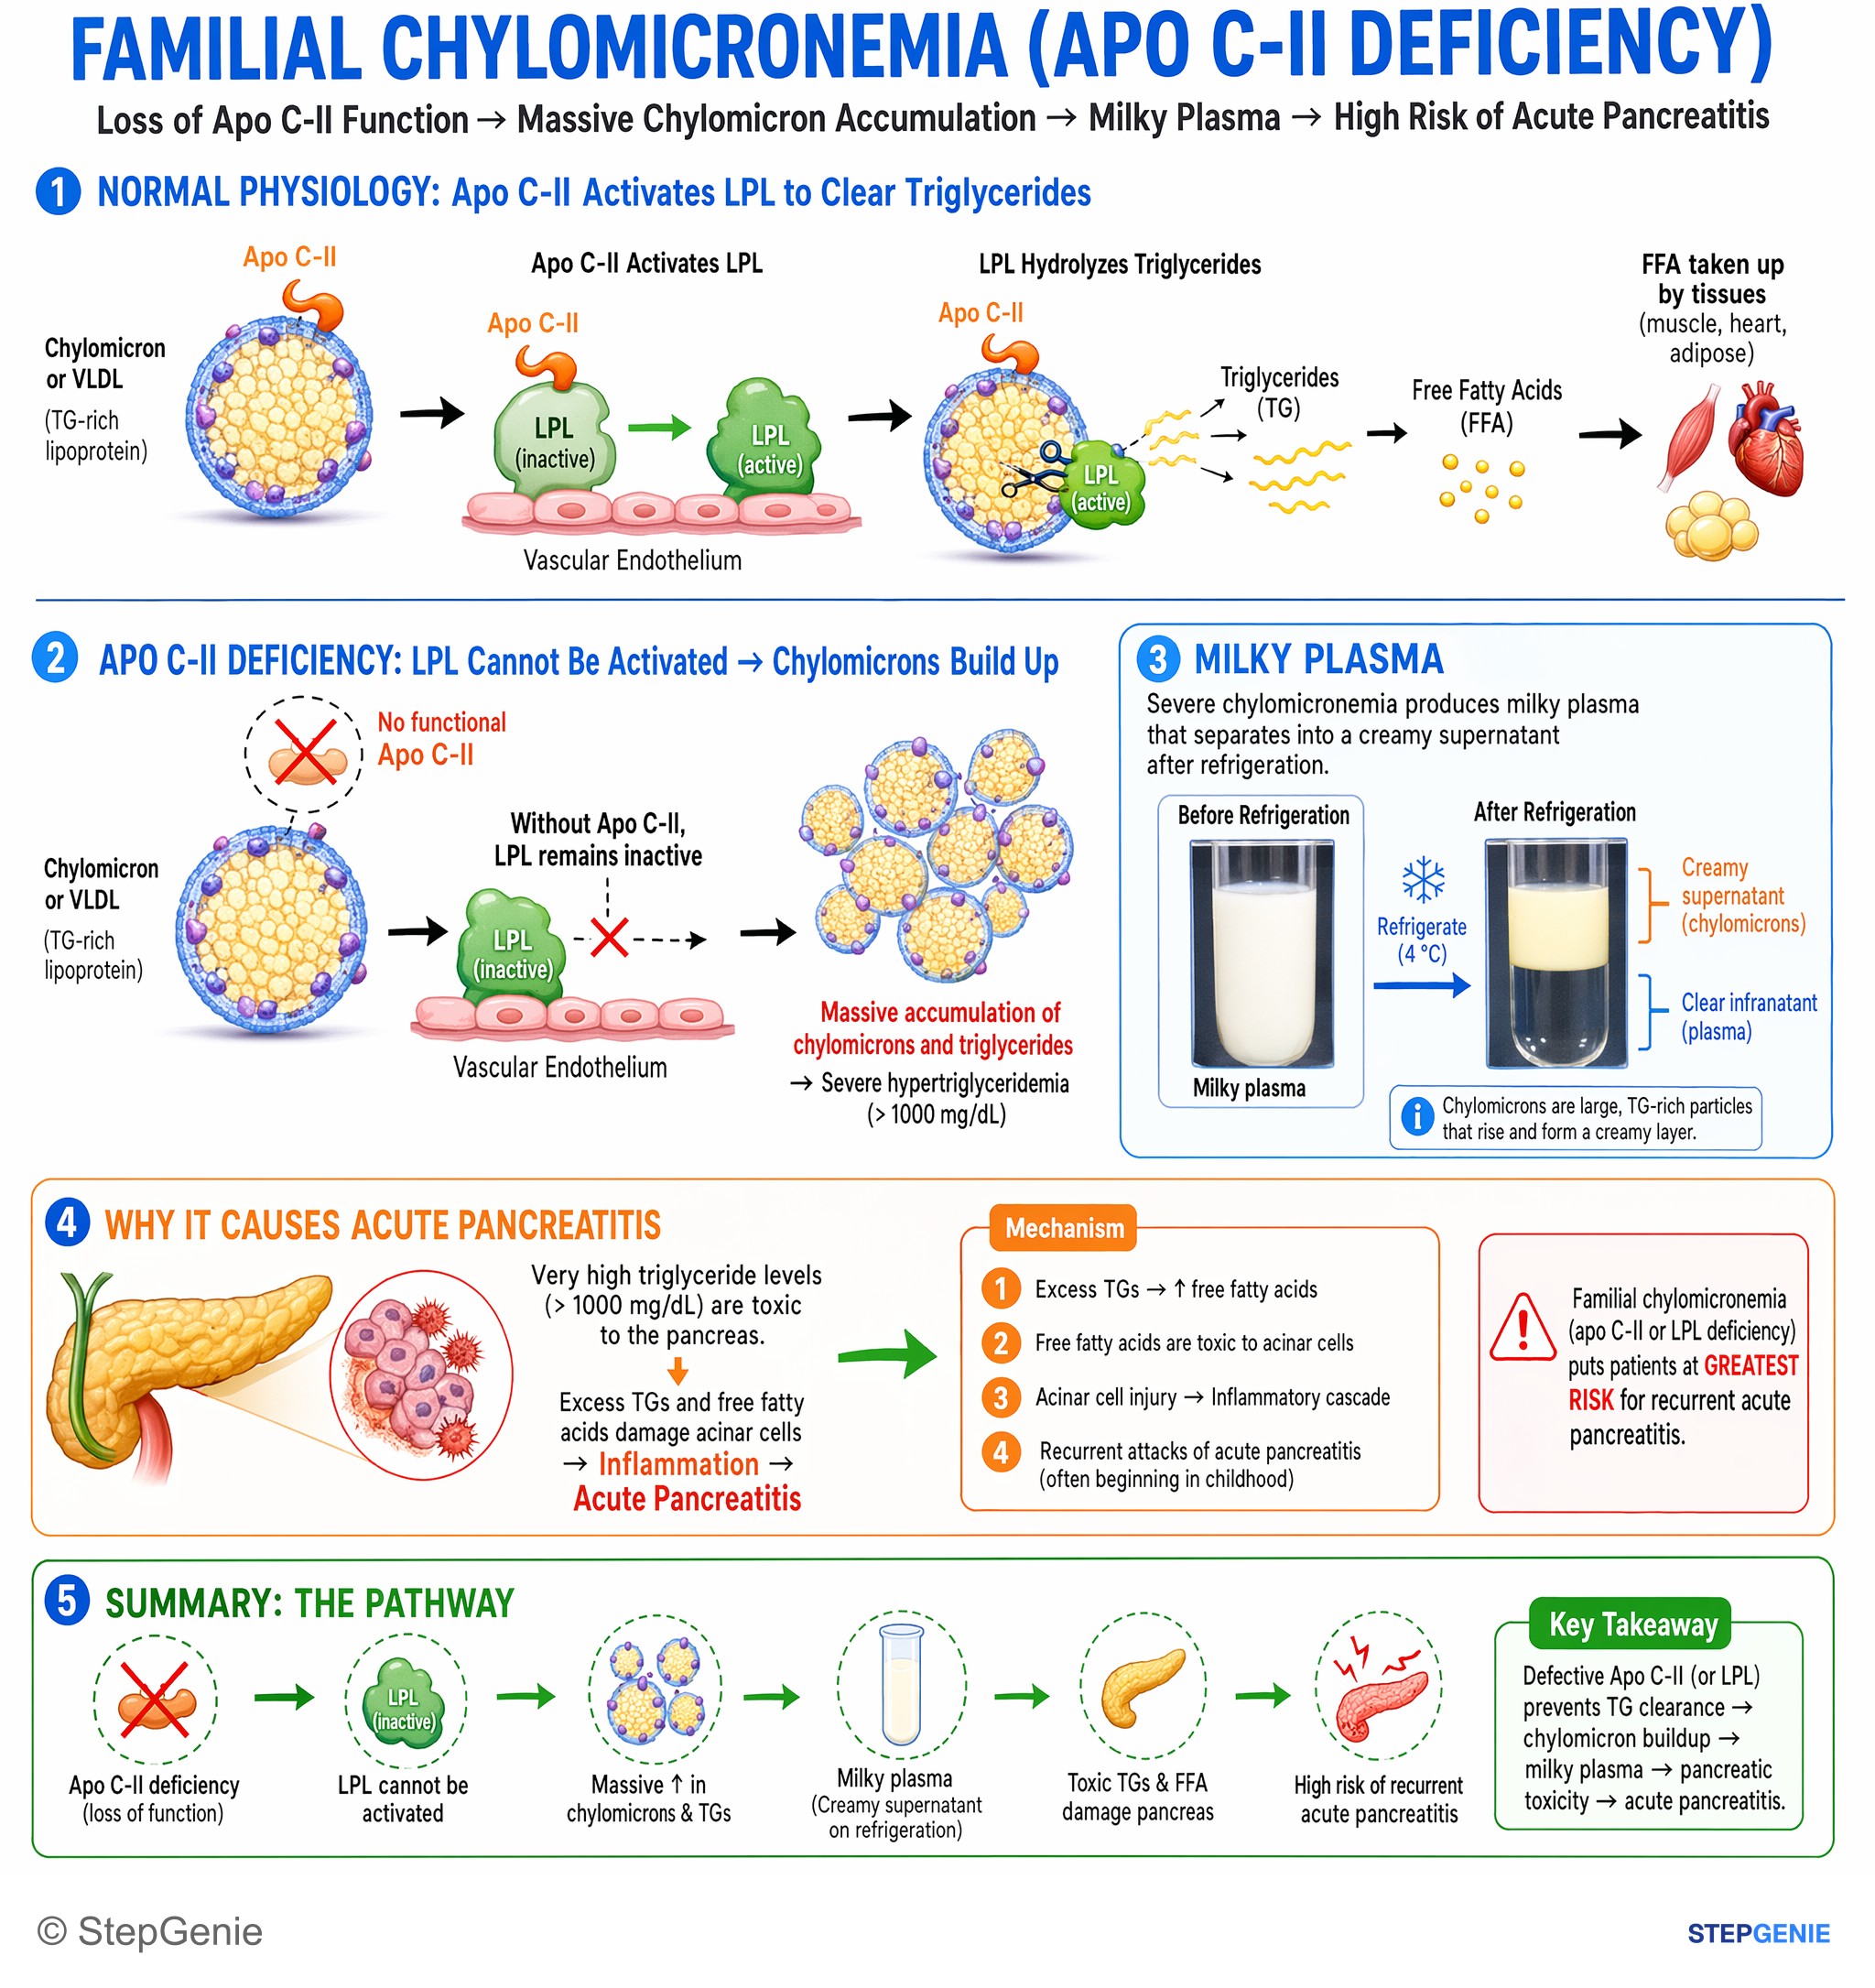
Familial chylomicronemia (apo C-II or LPL deficiency) → massively elevated triglycerides & chylomicrons → milky plasma → high risk of…
USMLE Step 1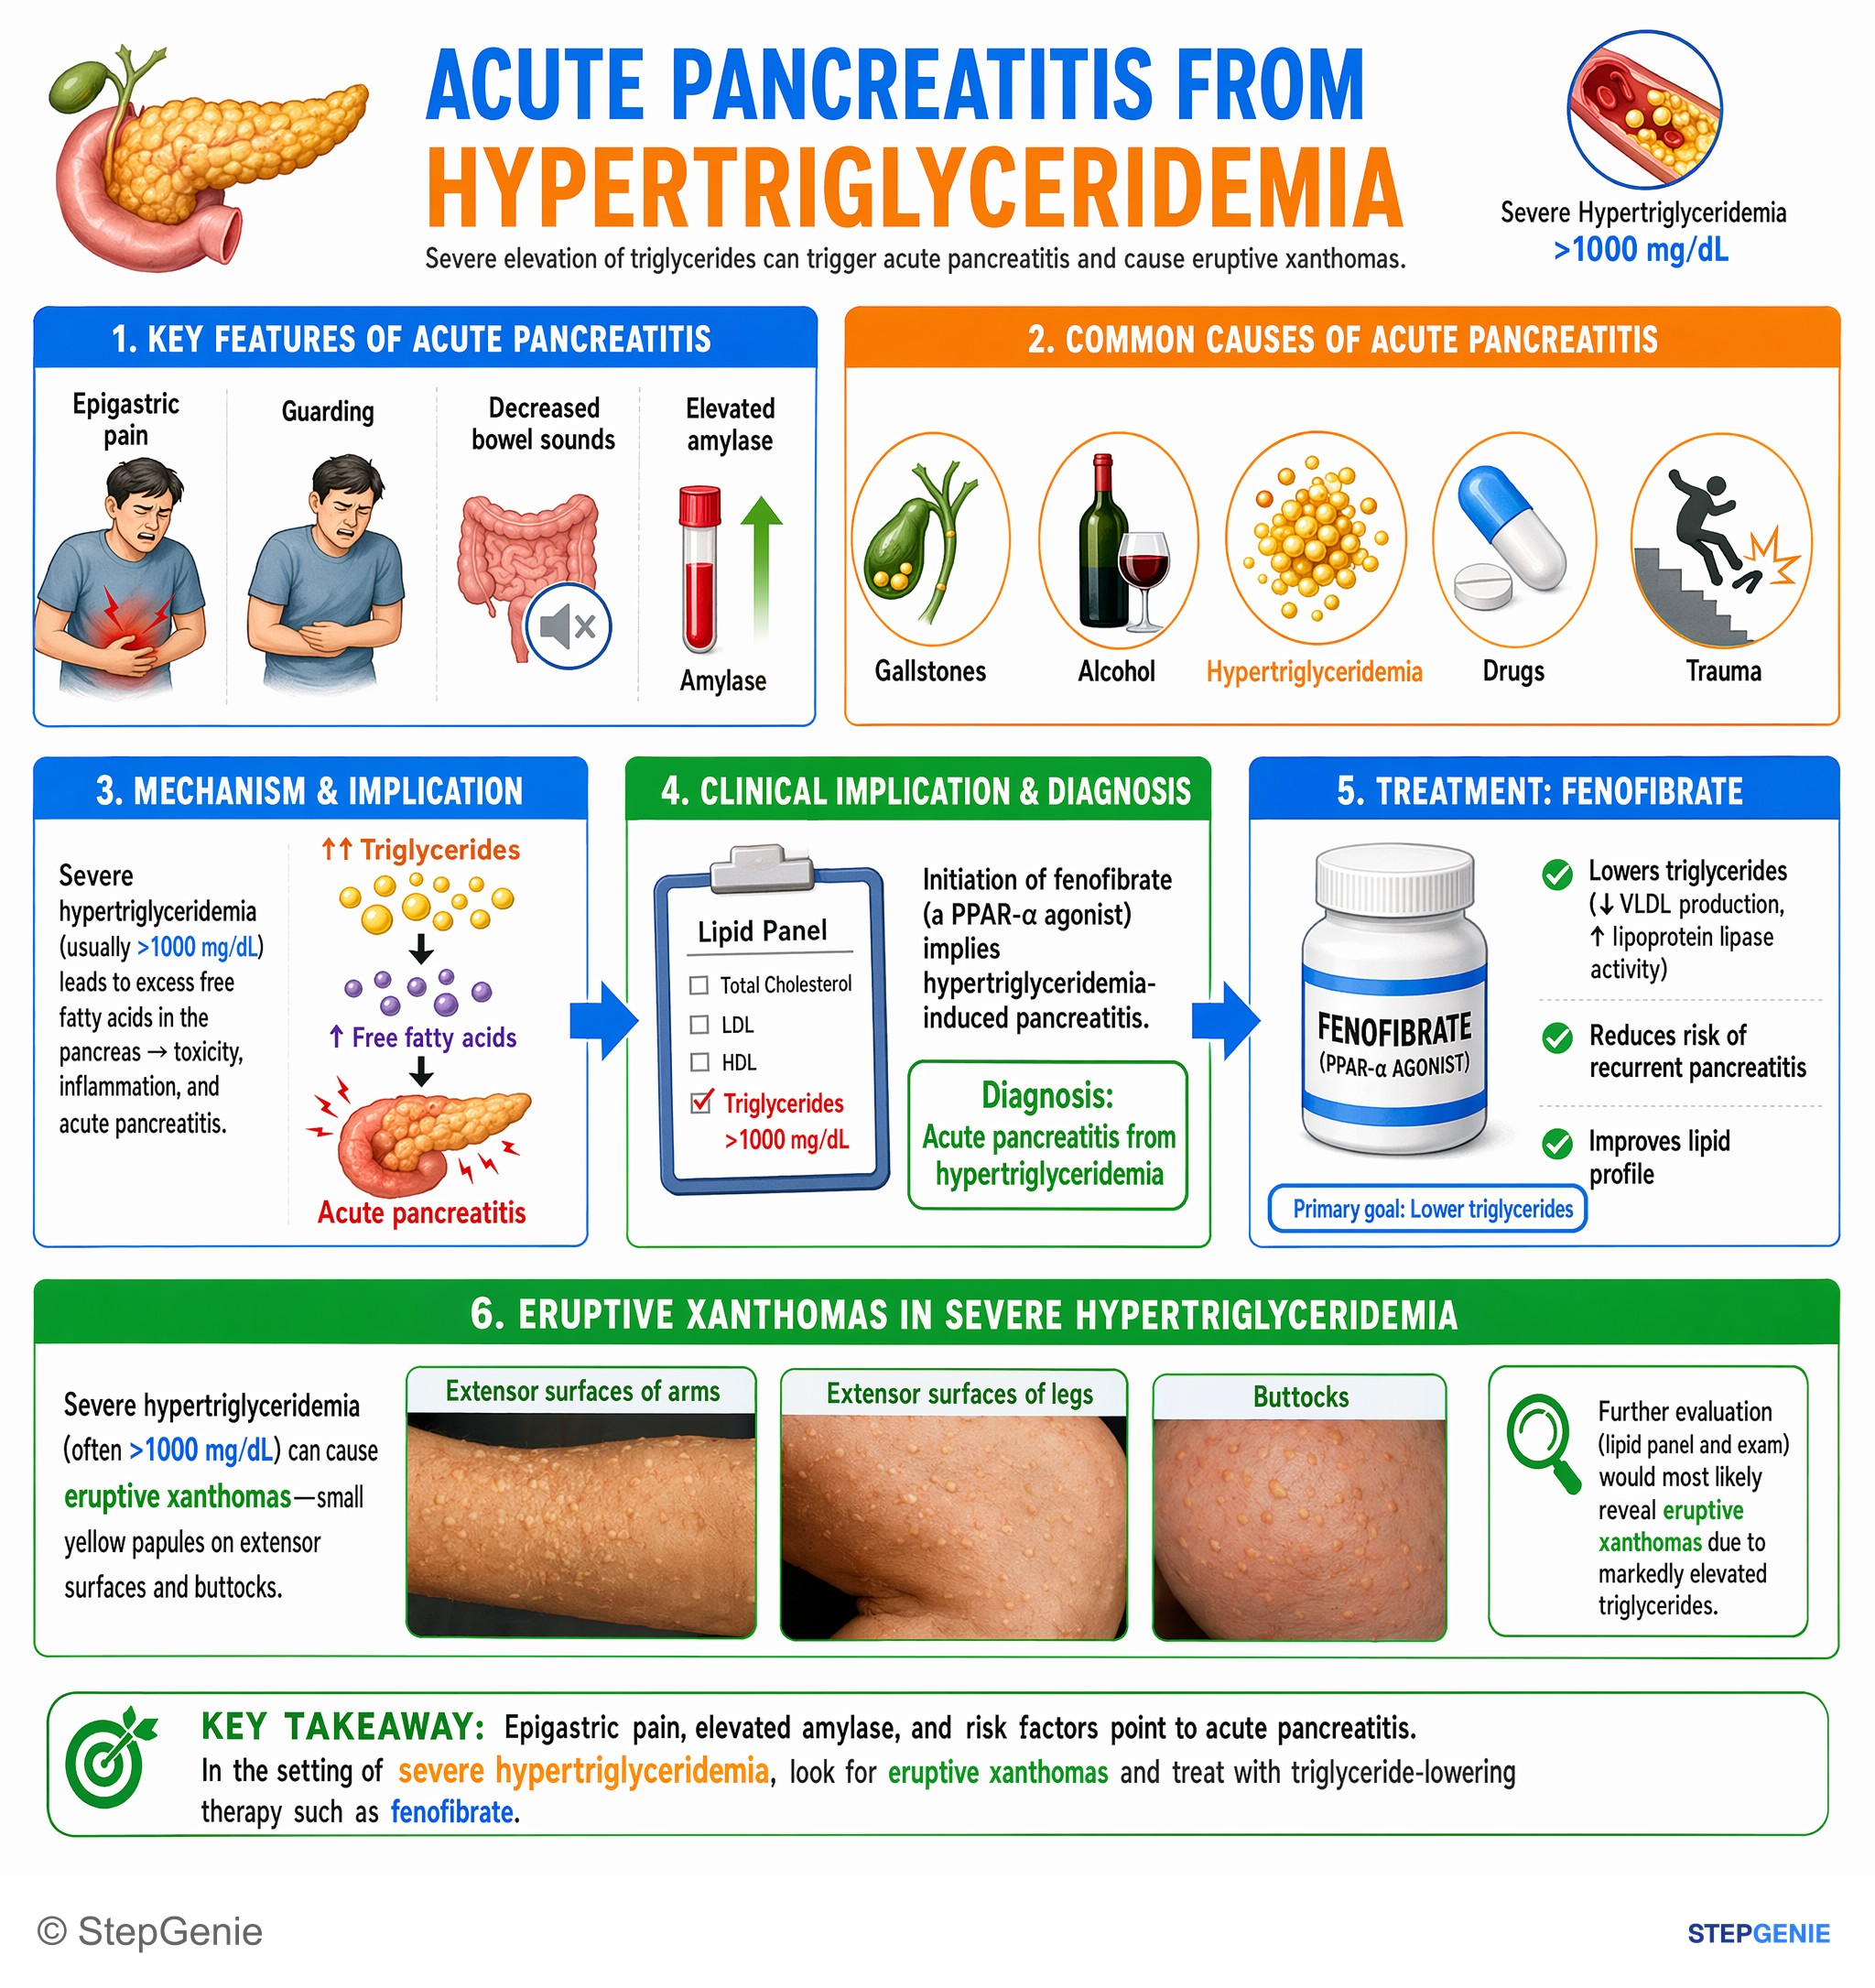
Acute pancreatitis from hypertriglyceridemia; fenofibrate lowers triglycerides. Severe hypertriglyceridemia causes eruptive xanthomas on…
USMLE Step 1Frequently Asked Questions
What is the Fredrickson classification of hyperlipoproteinemia?
It is a phenotype system from the late 1960s, made an international classification by a 1970 World Health Organization memorandum, that sorts hyperlipidemias by the lipoprotein that is raised: chylomicrons (type I), LDL (IIa), LDL plus VLDL (IIb), remnants or IDL (III), VLDL (IV), or chylomicrons plus VLDL (V). It describes the lipid pattern rather than the gene, so one family can show several types, and current references prefer disease names such as FCS, FH and FCHL.
What is a mnemonic for the familial dyslipidemias?
Name each type by its lipoprotein. I scream for cream: type I chylomicrons float as a cream layer. IIa means LDL alone, IIb means both LDL and VLDL, III is the letter E written backwards for apolipoprotein E, IV means increased VLDL, and 1 plus 4 equals 5, so type V carries type I chylomicrons plus type IV VLDL. For familial hypercholesterolemia, remember all A's: autosomal dominant, Achilles xanthomas, arcus, early atherosclerosis and apoB-100.
Which familial dyslipidemias cause pancreatitis?
The chylomicron disorders do: type I familial chylomicronemia syndrome and type V multifactorial chylomicronemia, plus type IV when triglycerides climb high enough for chylomicrons to accumulate. Hypertriglyceridemia is the third most common cause of acute pancreatitis after alcohol and gallstones, and the 2026 ACC/AHA guideline makes preventing pancreatitis the priority once triglycerides reach 1,000 mg/dL. Types IIa, IIb and III present mainly with premature atherosclerosis.
How common is familial hypercholesterolemia and how is it inherited?
Heterozygous familial hypercholesterolemia affects about 1 in 250 people, not the 1 in 500 once taught. It is autosomal dominant, usually from LDL receptor variants and less often from apoB-100 or gain-of-function PCSK9 variants; a rare recessive form involves LDLRAP1. Untreated LDL is usually above 190 mg/dL. Homozygous FH, about 1 in 160,000 to 400,000, is suspected when untreated LDL exceeds 400 mg/dL and often causes severe coronary disease by the mid-20s.
What causes type III hyperlipoproteinemia (familial dysbetalipoproteinemia)?
The classic cause is homozygosity for apolipoprotein E2, which the LDL receptor recognizes poorly, so chylomicron and VLDL remnants accumulate; about 10% of cases come from dominant APOE variants. Fewer than 20% of E2/E2 carriers become hyperlipidemic, because disease needs a second hit such as obesity, diabetes, hypothyroidism or menopause. Clues are cholesterol and triglycerides raised about equally, palmar crease or tuberoeruptive xanthomas, and premature coronary and peripheral artery disease.
How do you tell type I from type V hyperlipoproteinemia?
Both carry excess chylomicrons and can cause pancreatitis and eruptive xanthomas. Type I, familial chylomicronemia syndrome, is a recessive LPL-pathway disorder that usually starts in childhood in a lean patient; refrigerated plasma shows a cream layer over clear plasma, and post-heparin lipase activity is low or absent. Type V is usually an adult with obesity, diabetes, alcohol or triglyceride-raising drugs, with opalescent plasma under the cream layer because VLDL is high too.