Grade describes how abnormal a tumor's cells look under the microscope; stage describes how far the cancer has spread in the body. The National Cancer Institute (NCI) defines grade as a description of a tumor based on how abnormal the cancer cells and tissue look and how quickly they are likely to grow and spread, from grade 1 (well differentiated, low grade) to grade 4 (undifferentiated, high grade); stage is the extent of the cancer, usually summarized with TNM: the primary tumor (T), regional lymph nodes (N) and distant metastasis (M). For most solid tumors, stage, above all distant metastasis, predicts survival better than grade, but grade is built into the stage of some cancers (prostate, soft tissue sarcoma, breast) and leads for brain tumors, where TNM does not apply.
Grade vs stage at a glance
| Feature | Grade | Stage |
|---|---|---|
| NCI definition | How abnormal the cancer cells and tissue look under a microscope and how quickly they are likely to grow and spread | The extent of the cancer: tumor size, whether lymph nodes contain cancer, and whether it has spread to other parts of the body |
| Question it answers | How aggressive does this tumor look? | How far has it gone? |
| Who assigns it | Pathologist, from a biopsy or resection specimen | Care team, from examination, imaging, endoscopy and biopsies (clinical stage) plus surgical findings (pathologic stage) |
| Vocabulary | Well, moderately or poorly differentiated; undifferentiated (anaplastic); mitoses; pleomorphism; necrosis | T, N, M; stage 0 to IV; in situ, localized, regional, distant |
| Usual scale | GX, G1–G4, or a cancer-specific system | Tis or T1–T4, N0–N3, M0 or M1, grouped into stage 0–IV |
| Weight in prognosis | Important, especially within the same stage | Usually the stronger predictor for solid tumors |
Memory hook: grade is about the glass slide; stage is about spread.
Grading: what the pathologist scores
- Differentiation: how closely the tumor resembles its tissue of origin. Well-differentiated cells look close to normal and tend to grow and spread slowly; the NCI calls cells that divide rapidly and have little or no resemblance to normal cells anaplastic.
- Nuclear features: pleomorphism (variation in the size and shape of cells or nuclei) and abnormal-looking nuclei and nucleoli.
- Mitotic activity: how many cells are dividing (mitotic count or index); cancer tissue generally has more mitotic activity than normal tissue.
- Necrosis: areas of dead tumor, which push the grade up in systems such as the sarcoma and brain tumor grades.
- Architecture: for example, how well a breast cancer still forms tubules.
The general NCI scale is GX (cannot be assessed), G1 well differentiated (low grade), G2 moderately differentiated (intermediate), G3 poorly differentiated (high grade) and G4 undifferentiated (high grade). Many cancers use their own system:
| Cancer | Grading system | How it is scored |
|---|---|---|
| Breast | Nottingham (modified Scarff-Bloom-Richardson) | Tubule formation, nuclear pleomorphism and mitotic count add up to 3–9 points: 3–5 = G1, 6–7 = G2, 8–9 = G3 |
| Prostate | Gleason score → Grade Group 1–5 | The two most prevalent patterns (1 to 5) are added; is Grade Group 2, is Grade Group 3, and a score of 9–10 is Grade Group 5 |
| Soft tissue sarcoma | FNCLCC | Differentiation (1–3) + mitotic count (1–3) + necrosis (0–2): 2–3 = G1, 4–5 = G2, 6–8 = G3 |
| Brain and spinal cord | WHO grade 1–4 | From tumors with low proliferative potential that resection alone may cure (grade 1) to mitotically active, necrosis-prone tumors that progress rapidly (grade 4) |
The Gleason example shows why the order matters: in , a 4+3 tumor has more of the poorly differentiated pattern than a 3+4 tumor, even though both total 7. Anaplasia and the other features of malignancy are reviewed in the benign vs malignant neoplasia Q-bank, and the undifferentiated end of the spectrum appears in the thyroid cancer types guide.
Staging: TNM and stage groups
| Category | Meaning |
|---|---|
| T (primary tumor) | TX cannot be measured; T0 no primary found; Tis in situ; T1–T4 increasing size and/or extent into nearby tissue |
| N (regional nodes) | NX cannot be assessed; N0 no nodal cancer; N1–N3 increasing number and location of involved nodes |
| M (distant metastasis) | M0 no distant spread; M1 spread to other parts of the body |
- Stage groups: stage 0 is carcinoma in situ (abnormal cells that have not spread into nearby tissue); stages I–III reflect a larger or more locally spread tumor; stage IV means distant spread.
- T is not always size. In colon cancer, T is depth of invasion: T1 into the submucosa, T2 into the muscularis propria, T3 through it into pericolorectal tissue, T4a through the visceral peritoneum.
- Editions: the TNM details on this page follow the AJCC 8th edition, which is still current for colon, breast, prostate, bone and soft tissue sarcoma; AJCC now updates cancers site by site as Version 9 (for example lung, cervix, anus, and brain and spinal cord).
- Clinical vs pathologic stage: clinical stage (prefix c) comes from examination, imaging, endoscopy and biopsies; pathologic stage (p) adds what surgery finds and is more precise. A y prefix marks staging after neoadjuvant therapy and r after recurrence.
- The stage at diagnosis never changes. If the cancer later spreads, the new information is added, but the original stage stays on record.
- Registries simplify: SEER summary stage groups cancers as in situ, localized, regional or distant.
- Not everything uses TNM: brain and spinal cord tumors are classified by type and grade, lymphomas have their own staging systems, gynecologic cancers also use FIGO, and most leukemias are not staged the way solid tumors are.
- Routes of spread: many carcinomas reach nearby lymph nodes before distant organs, which is why N carries so much weight; soft tissue sarcomas metastasize most often to the lung. Organ-specific patterns are drilled in the metastasis patterns Q-bank.
Which matters more for prognosis?
Stage, for most solid tumors. The American Cancer Society calls stage, along with cancer type, one of the most important factors in prognosis, and the NCI notes that colon cancer outcome is clearly related to depth of invasion, nodal involvement and distant metastasis, the three elements of its staging. SEER data for colorectal cancer (2016–2022) make the point:
| SEER summary stage | Share of cases | 5-year relative survival |
|---|---|---|
| Localized | 34% | 91.3% |
| Regional (nodes or nearby tissue) | 37% | 75.2% |
| Distant (metastatic) | 23% | 16.9% |
A well-differentiated carcinoma that has already seeded the liver is stage IV; a poorly differentiated one that is still confined to the bowel wall may be cured by surgery. Once cancer has reached distant sites, treatment usually has to be systemic rather than local.
Grade still matters, in three ways:
- Within a stage, a higher-grade tumor tends to grow and spread faster and may need more aggressive treatment, even when grade does not change the stage.
- Grade is written into some stages. In prostate cancer, Grade Group 5 disease without nodal or distant spread is stage IIIC whatever the T category, yet any N1 disease is stage IVA and any M1 disease is stage IVB whatever the grade, so spread still wins. Soft tissue sarcoma stages combine T, N, M and FNCLCC grade, and small low-grade sarcomas are often cured by surgery alone. Breast cancer prognostic stage groups add grade, ER, PR and HER2 to TNM. Grade also enters bone sarcoma staging, as noted in the osteosarcoma vs Ewing sarcoma guide.
- Where TNM does not work, grade leads. TNM was dropped for brain tumors because histology and location matter more than size, the brain has no lymphatics for an N category, and metastasis is rare. WHO grade, tumor type and molecular markers carry the prognosis instead.
How the exam tests it
- "Most important prognostic factor" for a carcinoma → stage, and distant metastasis (M1) outranks size, depth, nodes and grade.
- "Poorly differentiated, frequent atypical mitoses, marked pleomorphism" → a statement about grade, not stage.
- A biopsy gives grade; stage needs imaging, endoscopy, node sampling or surgery (sentinel node biopsy stages breast cancer, melanoma and others).
- Carcinoma in situ is stage 0 (Tis), not a grade; an in situ lesion can still be high grade (for example, high-nuclear-grade DCIS of the breast).
- Stage does not change after diagnosis, even if the cancer later spreads.
Practice question
Vignette. A 63-year-old man undergoes resection of a sigmoid colon adenocarcinoma. The pathology report describes a moderately differentiated tumor 4.5 cm across with frequent mitoses that invades through the muscularis propria into pericolorectal fat, with cancer in 3 of 17 lymph nodes. A staging CT shows two lesions in the liver, and biopsy of one confirms metastatic adenocarcinoma. Which finding is the strongest predictor of his survival?
- A. Moderate differentiation
- B. Frequent mitotic figures
- C. Tumor diameter of 4.5 cm
- D. Three positive regional lymph nodes
- E. Liver metastases
Answer: E. Distant metastasis makes this stage IV (any T, any N, M1), and in SEER data 5-year relative survival for distant colorectal cancer is 16.9%, compared with 75.2% for regional disease.
Why not the others?
- A and B: differentiation and mitotic activity are grading features. They describe how aggressive the tumor looks, but they do not change a stage IV cancer's outlook as much as its spread does.
- C: in colon cancer, T is set by depth of invasion, not diameter; this tumor is T3 because it has invaded through the muscularis propria.
- D: nodal disease (N1) would make this stage III on its own and is a major prognostic factor, but distant metastasis outranks it.
Key takeaways
- Grade = how abnormal the cells look (differentiation, pleomorphism, mitoses, necrosis); assigned by a pathologist, G1 (well differentiated) to G4 (undifferentiated).
- Stage = how far the cancer has spread, usually TNM grouped into stages 0–IV; stage IV means distant metastasis.
- For most solid tumors, stage predicts prognosis better than grade, and M1 outranks everything else.
- Grade is built into some stages (prostate Grade Group, sarcoma FNCLCC grade, breast prognostic stage) and adds information within a stage.
- Brain tumors use grade, not TNM; lymphomas have their own systems, gynecologic cancers also use FIGO, and most leukemias are not staged like solid tumors.
- The stage at diagnosis is permanent; later findings are recorded as restaging.
Sources
- Tumor Grade — National Cancer Institute
- Grade (definition) — NCI Dictionary of Cancer Terms
- Anaplastic (definition) — NCI Dictionary of Cancer Terms
- Cancer Staging — National Cancer Institute
- Cancer Staging — American Cancer Society (2024)
- AJCC Current Staging System: 8th Edition or Version 9 — American College of Surgeons (2026)
- Cancer Stat Facts: Colorectal Cancer — NCI SEER Program
- Colon Cancer Treatment (PDQ), Health Professional Version — National Cancer Institute
- Prostate Cancer Treatment (PDQ), Health Professional Version — National Cancer Institute
- Breast Cancer Treatment (PDQ), Health Professional Version — National Cancer Institute
- Soft Tissue Sarcoma Treatment (PDQ), Health Professional Version — National Cancer Institute
- Central Nervous System Tumors Treatment (PDQ), Health Professional Version — National Cancer Institute
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
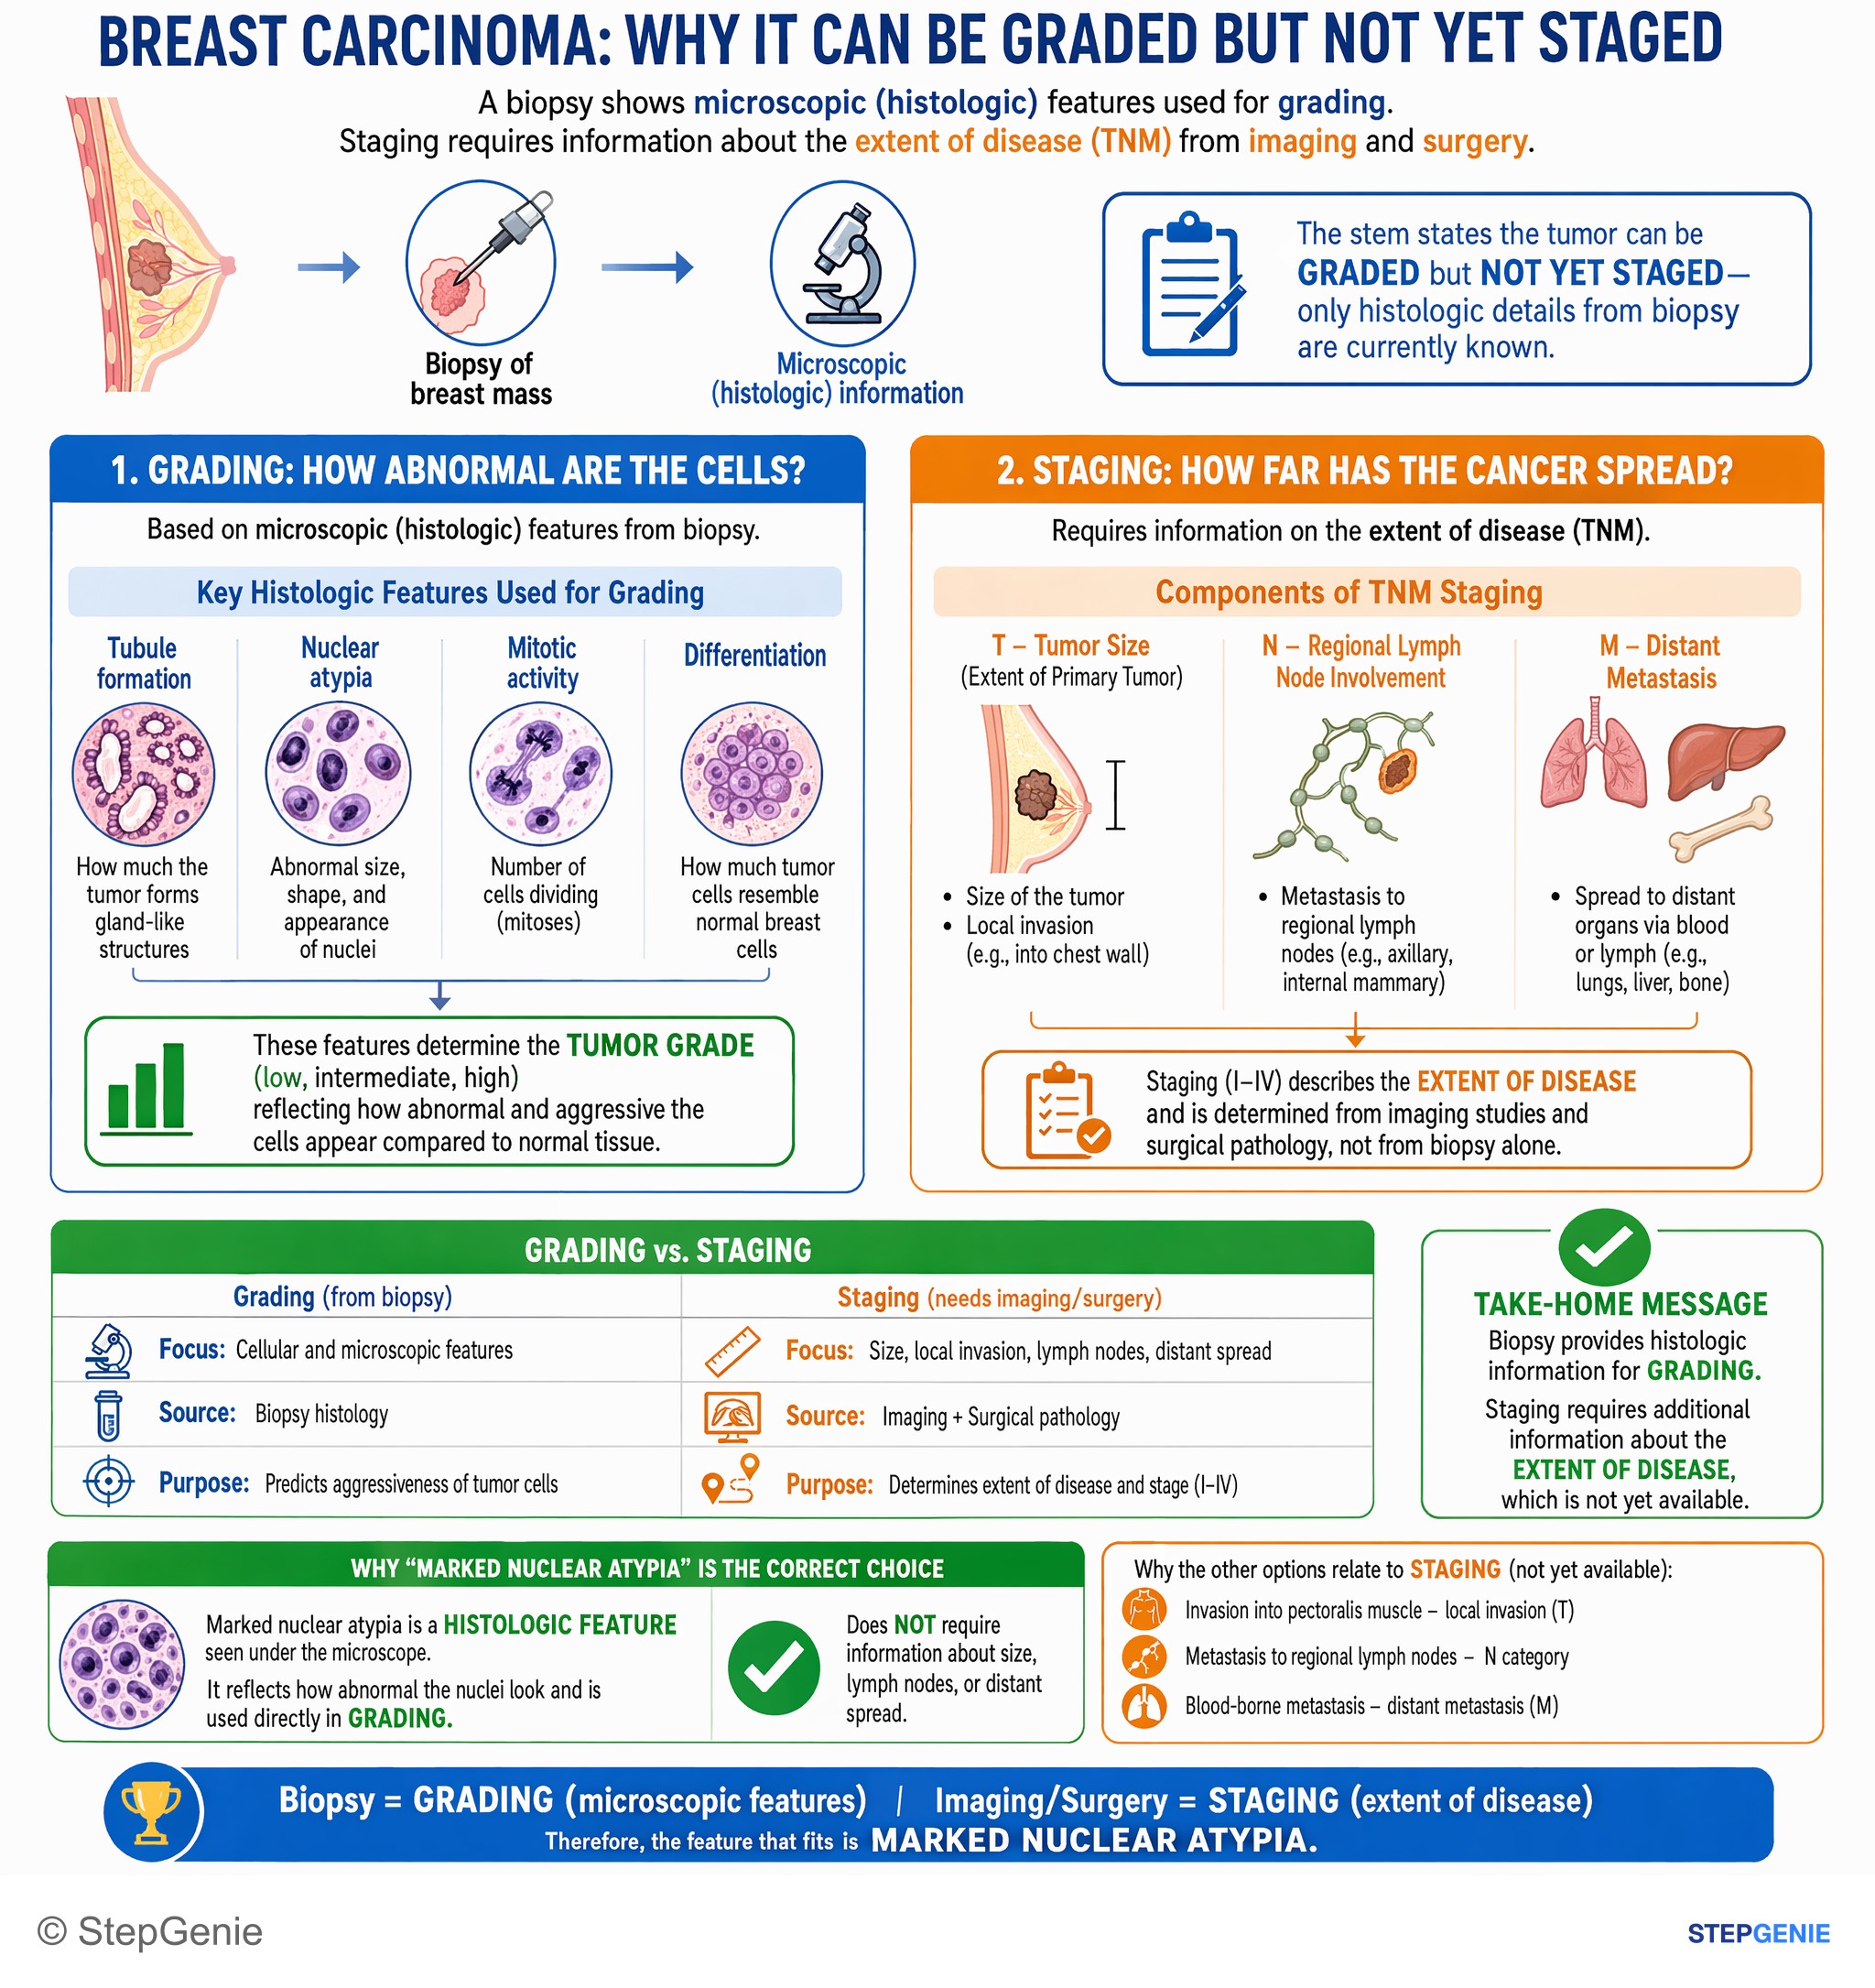
Breast carcinoma prognosis depends on grade (cellular atypia, differentiation) and stage (extent of spread); biopsy alone provides…
USMLE Step 1Frequently Asked Questions
What is the difference between tumor grade and stage?
Grade describes how abnormal the cancer cells and tissue look under a microscope and how quickly they are likely to grow and spread; a pathologist assigns it from a biopsy or surgical specimen. Stage describes the extent of the cancer in the body, usually with the TNM system: the size or depth of the primary tumor, whether regional lymph nodes contain cancer, and whether it has spread to distant sites. A tumor can be low grade but high stage, or high grade but low stage.
Which is more important for prognosis, grade or stage?
For most solid tumors, stage is the stronger predictor of survival, and distant metastasis outweighs every other feature. SEER data for colorectal cancer, for example, show 5-year relative survival of 91.3% for localized, 75.2% for regional and 16.9% for distant disease. Grade still adds information within a stage, is built into the stage of cancers such as prostate cancer and soft tissue sarcoma, and leads for brain tumors, which are not staged with TNM.
What do the letters in TNM staging mean?
T describes the primary tumor: its size and/or how far it has grown into nearby tissue, from T1 to T4, with Tis for carcinoma in situ. N describes spread to regional lymph nodes, from N0 (none) to N3. M describes distant metastasis: M0 means none has been found and M1 means the cancer has spread to other parts of the body. The TNM combinations are then grouped into stages 0 through IV.
What does poorly differentiated or anaplastic mean?
Differentiation describes how much a tumor looks like the normal tissue it came from. Well-differentiated tumors look close to normal and tend to grow slowly, while poorly differentiated tumors look much less like their tissue of origin. The NCI describes anaplastic cells as cells that divide rapidly and have little or no resemblance to normal cells; poorly differentiated and undifferentiated tumors are high grade (grades 3 and 4).
Does a cancer's stage change if it spreads later?
No. The stage assigned at diagnosis stays with the cancer even if it later grows or spreads. New information is recorded as restaging, marked in the TNM system with prefixes such as y after neoadjuvant therapy or r after recurrence, and survival statistics refer to the stage at diagnosis.
Why are brain tumors graded but not staged with TNM?
TNM does not fit most brain and spinal cord tumors: the NCI notes that tumor size matters less than histology and location, that the brain and spinal cord have no lymphatics for an N category, and that distant metastasis is rare. These tumors are instead classified by tumor type, molecular features and WHO grade, from grade 1 (low proliferative potential, sometimes cured by resection alone) to grade 4 (mitotically active, necrosis-prone and rapidly progressive).