Amyloidosis is the extracellular deposition of misfolded protein as β-pleated sheet fibrils, proven on biopsy by Congo red staining with apple-green birefringence under polarized light. The type is named for the precursor protein: AL is a monoclonal immunoglobulin light chain from a plasma cell clone, AA is serum amyloid A from chronic inflammation, and ATTR is transthyretin, either an inherited variant (hereditary ATTR, the cause of familial amyloid polyneuropathy) or normal "wild-type" TTR that builds up mainly in the hearts of older men. Work it up in order: suspect it from the organ pattern, prove it on biopsy, look for a monoclonal light chain, then type the deposit before you treat.
Step 1: Suspect amyloid from the organ pattern
Think of amyloid when unrelated organs fail together.
- Kidney: new proteinuria, often in the nephrotic range (AL and AA). For the glomerular side, see nephrotic vs nephritic syndrome.
- Heart: a restrictive cardiomyopathy that looks like heart failure with preserved ejection fraction. The echo shows thick ventricular walls while the ECG shows low voltage.
- Nerves: a length-dependent neuropathy that starts in the feet, plus autonomic failure (orthostatic hypotension, diarrhea alternating with constipation, erectile dysfunction). Typical of AL and hereditary ATTR.
- Soft tissue: macroglossia and periorbital purpura ("raccoon eyes") point to AL. Carpal tunnel syndrome, biceps tendon rupture or lumbar spinal stenosis can precede ATTR cardiomyopathy by years.
- Liver and spleen: hepatomegaly or splenomegaly.
Step 2: Prove it is amyloid
- Biopsy the easiest tissue first. An abdominal fat pad aspirate finds amyloid in about 80% of AL cases but in fewer than 25% of wild-type ATTR, so a negative fat pad does not exclude cardiac ATTR. Biopsy the affected organ if suspicion stays high.
- On H&E, amyloid is extracellular, eosinophilic and amorphous. With Congo red it shows apple-green birefringence under polarized light, a property of the β-pleated sheet.
Step 3: Look for a monoclonal light chain
- Order serum free light chains plus serum and urine immunofixation, with a bone marrow biopsy as part of the AL evaluation.
- AL usually comes from a small clone: it is most often diagnosed with fewer than 10% marrow plasma cells, below the threshold for myeloma, although it can also accompany full-blown multiple myeloma.
- A monoclonal protein does not prove AL: up to 10% of patients present with AA or hereditary amyloidosis plus an incidental monoclonal gammopathy.
Step 4: Type the deposit
- Mass spectrometry of the amyloid is the most sensitive and specific typing method; immunohistochemistry is an alternative.
- Heart shortcut: a technetium pyrophosphate scan with grade 2 or 3 cardiac uptake, together with no monoclonal protein on free light chains and immunofixation, diagnoses ATTR cardiac amyloidosis without a biopsy. AL shows little or no uptake.
- If the deposit is ATTR, TTR gene sequencing separates hereditary (variant) from wild-type disease and identifies at-risk relatives.
Step 5: Match the protein to the story
Use the comparison table below: a plasma cell clone means AL, chronic inflammation means AA, a family history or a neuropathy without a monoclonal protein suggests hereditary ATTR, and an older man with a stiff heart suggests wild-type ATTR.
Step 6: Treat by type
- AL: treat the plasma cell clone. Initial therapy is typically daratumumab (anti-CD38) with cyclophosphamide, bortezomib and dexamethasone ("Dara-CyBorD"). High-dose melphalan with autologous stem cell transplant suits selected patients.
- AA: lower serum amyloid A by controlling the underlying disease: colchicine for familial Mediterranean fever, and anti-TNF or IL-6-blocking biologics for inflammatory arthritis.
- ATTR: TTR stabilizers (tafamidis, acoramidis, diflunisal) keep the tetramer intact. TTR silencers cut hepatic production: patisiran and vutrisiran are small interfering RNAs; inotersen and eplontersen are antisense oligonucleotides. Liver transplant, which removes the main source of variant TTR, was the older option for hereditary disease.
AL vs AA vs ATTR: comparison table
| Feature | AL | AA | Hereditary ATTR (ATTRv) | Wild-type ATTR (ATTRwt) |
|---|---|---|---|---|
| Precursor protein | Monoclonal immunoglobulin light chain | Serum amyloid A, an acute-phase reactant made by hepatocytes under TNF, IL-1 and IL-6 | Variant (mutant) transthyretin | Normal transthyretin |
| Underlying cause | Plasma cell clone, usually small; sometimes multiple myeloma | Chronic inflammation: RA, juvenile idiopathic arthritis, IBD, familial Mediterranean fever, chronic infection (tuberculosis is the classic one) | Autosomal dominant TTR variant (chromosome 18) | Aging |
| Typical patient | Adult with a monoclonal protein | Long-standing chronic inflammatory disease | Family history; V30M clusters in Portugal, Sweden and Japan; V122I is carried by about 3–4% of African Americans | Older adult, mainly men |
| Dominant organs | Kidney, heart, liver, nerves, GI tract, soft tissue | Kidney (proteinuria in most patients at presentation); also liver, spleen, adrenals | Peripheral and autonomic nerves, heart, eyes, kidney | Heart; ligaments and tendons |
| Signature clue | Macroglossia, periorbital purpura, nephrotic syndrome | New proteinuria in long-standing RA or FMF | Familial amyloid polyneuropathy; V122I causes late-onset cardiomyopathy | HFpEF with thick walls and low ECG voltage, often after carpal tunnel syndrome |
| Key test | Free light chains, immunofixation, bone marrow | Biopsy with typing | TTR gene sequencing | Pyrophosphate scan with no monoclonal protein |
| Treatment | Anti–plasma cell therapy (Dara-CyBorD; stem cell transplant) | Treat the inflammation (colchicine in FMF) | TTR silencers or stabilizers | TTR stabilizers (tafamidis, acoramidis) |
The one-line version: AL = light chains, AA = acute-phase reactant, ATTR = transthyretin (inherited variant or aging).
Familial amyloid polyneuropathy (hereditary ATTR)
Familial amyloid polyneuropathy (FAP) is the older name for hereditary transthyretin (ATTRv) amyloidosis presenting as neuropathy.
- Genetics: autosomal dominant variants in TTR on chromosome 18. The most common, V30M (now written p.Val50Met), clusters in Portugal, Sweden and Japan. Penetrance and age of onset vary widely: in two Japanese endemic foci the mean onset is about 40 years, versus about 63 years in unrelated carriers.
- Mechanism: transthyretin is a tetramer made mainly by the liver (small amounts come from the choroid plexus and retina). It carries thyroxine and, through retinol-binding protein, vitamin A (retinol). Variants destabilize the tetramer, and the freed monomers misfold into fibrils.
- Neuropathy: slowly progressive, length-dependent sensorimotor neuropathy that starts in the feet. Pain and temperature sensation are lost before vibration and position sense.
- Autonomic failure: orthostatic hypotension, constipation alternating with diarrhea, erectile dysfunction and bladder problems.
- Other clues: carpal tunnel syndrome (sometimes the first sign), cardiomyopathy and vitreous opacities.
- Treatment logic: silencers lower hepatic TTR production and stabilizers hold the tetramer together. Liver transplant halts progression of the neuropathy but does not treat cardiac, leptomeningeal or eye disease. Genetic testing of at-risk adult relatives lets treatment start early.
Other amyloid types the boards ask about
| Fibril (precursor) | Setting | Classic clue |
|---|---|---|
| Aβ2M (β2-microglobulin) | Years of hemodialysis | Late-onset carpal tunnel syndrome, bilateral arthropathy, bone destruction |
| Aβ (amyloid β protein) | Alzheimer disease; cerebral amyloid angiopathy | Lobar intracerebral hemorrhage in older adults |
| AIAPP (islet amyloid polypeptide, also called amylin) | Pancreatic islets in type 2 diabetes | Islet amyloid |
| ACal (calcitonin) | Medullary thyroid carcinoma (C-cell tumor) | Amyloid within the thyroid tumor |
| AANP (atrial natriuretic peptide) | Cardiac atria | Isolated atrial amyloidosis |
β2-microglobulin amyloid comes from a circulating protein that builds up on long-term dialysis and deposits mainly in bones and joints; the other rows are classic localized forms.
Exam traps
- A monoclonal protein is not proof of AL. Type the deposit; up to 10% of patients have AA or hereditary amyloidosis with an incidental monoclonal gammopathy.
- AL does not require myeloma. Most patients have fewer than 10% marrow plasma cells.
- Low voltage with thick walls means infiltration, not hypertensive hypertrophy.
- A negative fat pad does not exclude wild-type ATTR, which it detects in fewer than 25% of cases.
- Dialysis plus carpal tunnel syndrome means β2-microglobulin, not AL.
- Liver transplant for hereditary ATTR does not fix the heart, eyes or leptomeninges.
- Macroglossia and periorbital purpura point to AL; a stiff heart after carpal tunnel surgery in an older man points to wild-type ATTR.
Worked example
Vignette. A 48-year-old man of Portuguese descent has 3 years of burning pain and numbness that began in his feet and has climbed to his knees. He is lightheaded when he stands, alternates between diarrhea and constipation, and has erectile dysfunction. He had carpal tunnel release last year, and his father died in his 50s of a similar illness. Serum free light chains and serum and urine immunofixation are normal. A fat pad aspirate shows Congo red–positive deposits with apple-green birefringence. What is the most likely precursor protein, and what test confirms it?
Answer: Variant transthyretin (hereditary ATTR amyloidosis, or familial amyloid polyneuropathy), confirmed by TTR gene sequencing.
Reasoning: A length-dependent neuropathy with early pain and temperature loss, autonomic failure, carpal tunnel syndrome and an affected parent fits an autosomal dominant TTR variant such as V30M, which clusters in Portugal. Normal light chain studies make AL unlikely, there is no chronic inflammation for AA and no dialysis for β2-microglobulin. Treatment is a TTR silencer or stabilizer, and his adult relatives should be offered genetic testing.
Key takeaways
- Flowchart: suspect → biopsy with Congo red → free light chains and immunofixation → type the deposit (mass spectrometry, or a pyrophosphate scan for the heart) → treat by type.
- AL = light chains from a plasma cell clone; macroglossia and periorbital purpura; treat the clone.
- AA = serum amyloid A from chronic inflammation; the kidney is the usual target; treat the inflammation (colchicine in FMF).
- Hereditary ATTR = autosomal dominant TTR variants; V30M causes familial amyloid polyneuropathy, V122I causes late-onset cardiomyopathy.
- Wild-type ATTR = older men with HFpEF, thick walls and low voltage, often after carpal tunnel syndrome.
- β2-microglobulin = dialysis; Aβ = Alzheimer disease and cerebral amyloid angiopathy; IAPP = islets in type 2 diabetes; calcitonin = medullary thyroid carcinoma.
Sources
- Amyloidosis — StatPearls, NCBI Bookshelf
- Cardiac Amyloidosis — StatPearls, NCBI Bookshelf
- Hereditary Transthyretin Amyloidosis — GeneReviews, NCBI Bookshelf
- Amyloidosis — Merck Manual Professional Edition
- Transthyretin amyloidosis — MedlinePlus Genetics
- Thorne J, et al. Serum amyloid A protein–associated kidney disease: presentation, diagnosis, and management — Kidney Medicine, 2022
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
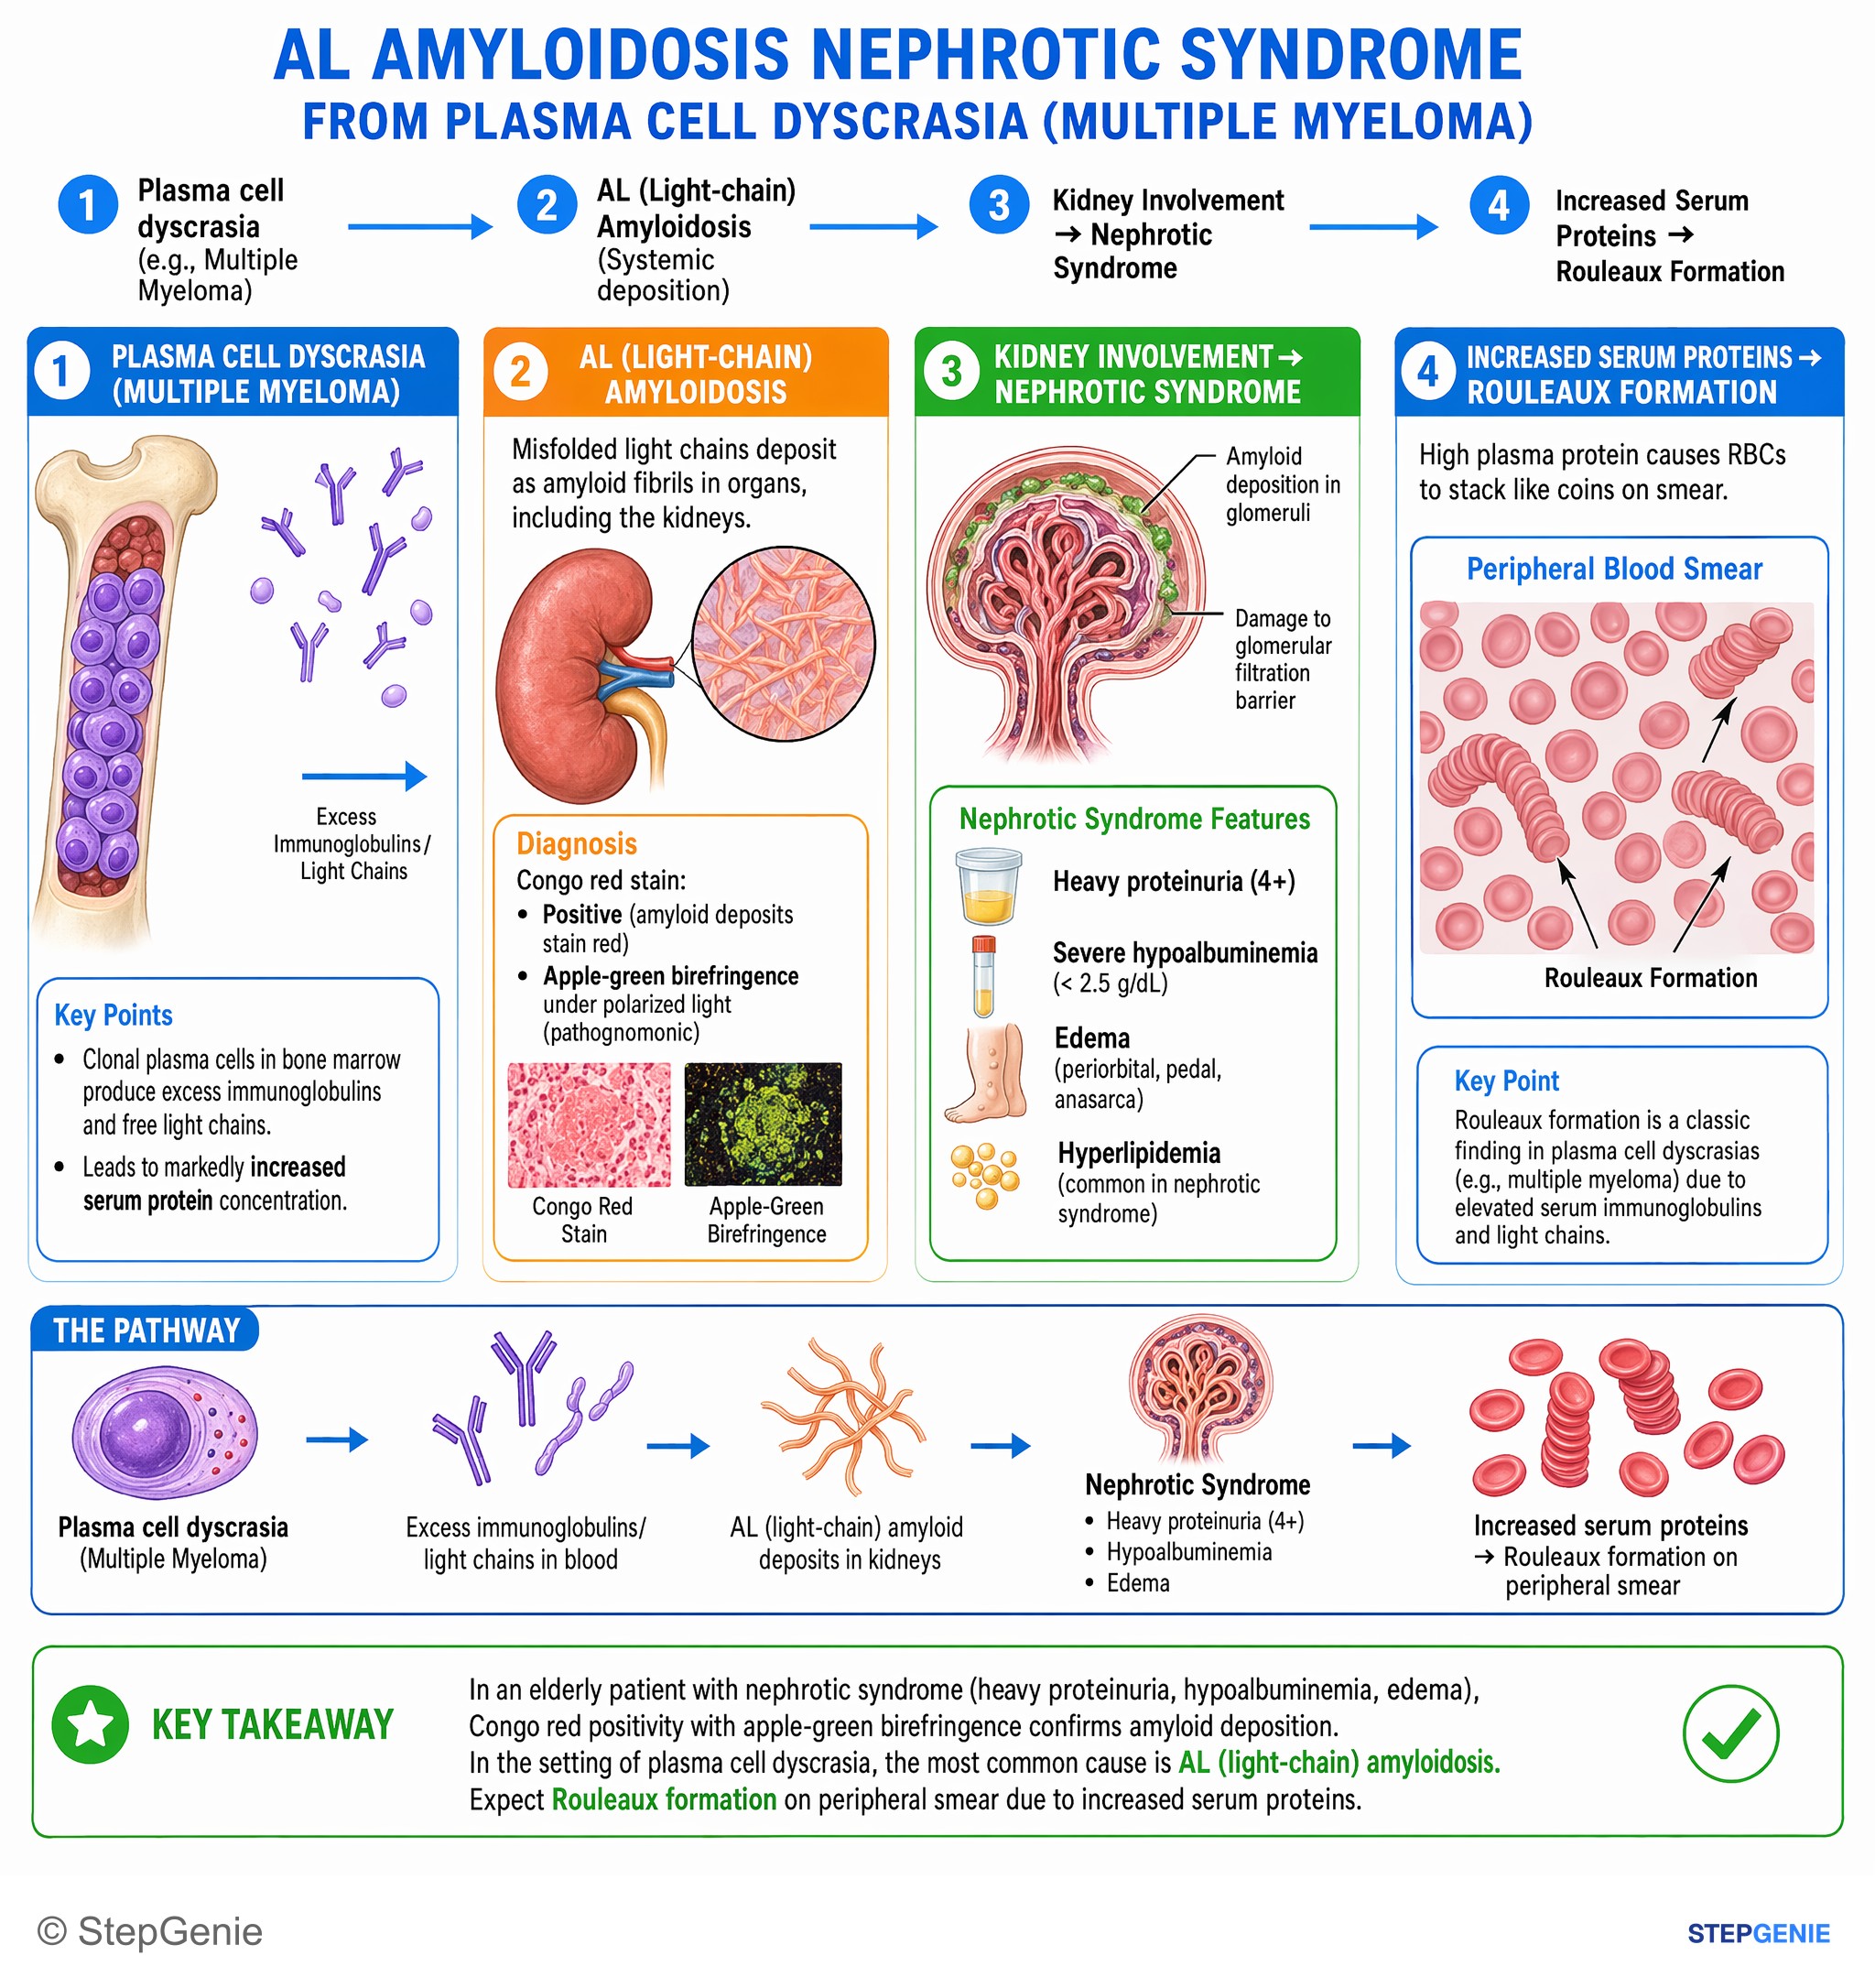
AL amyloidosis nephrotic syndrome from plasma cell dyscrasia → massive proteinuria, hypoalbuminemia, edema; expect Rouleaux formation due…
USMLE Step 1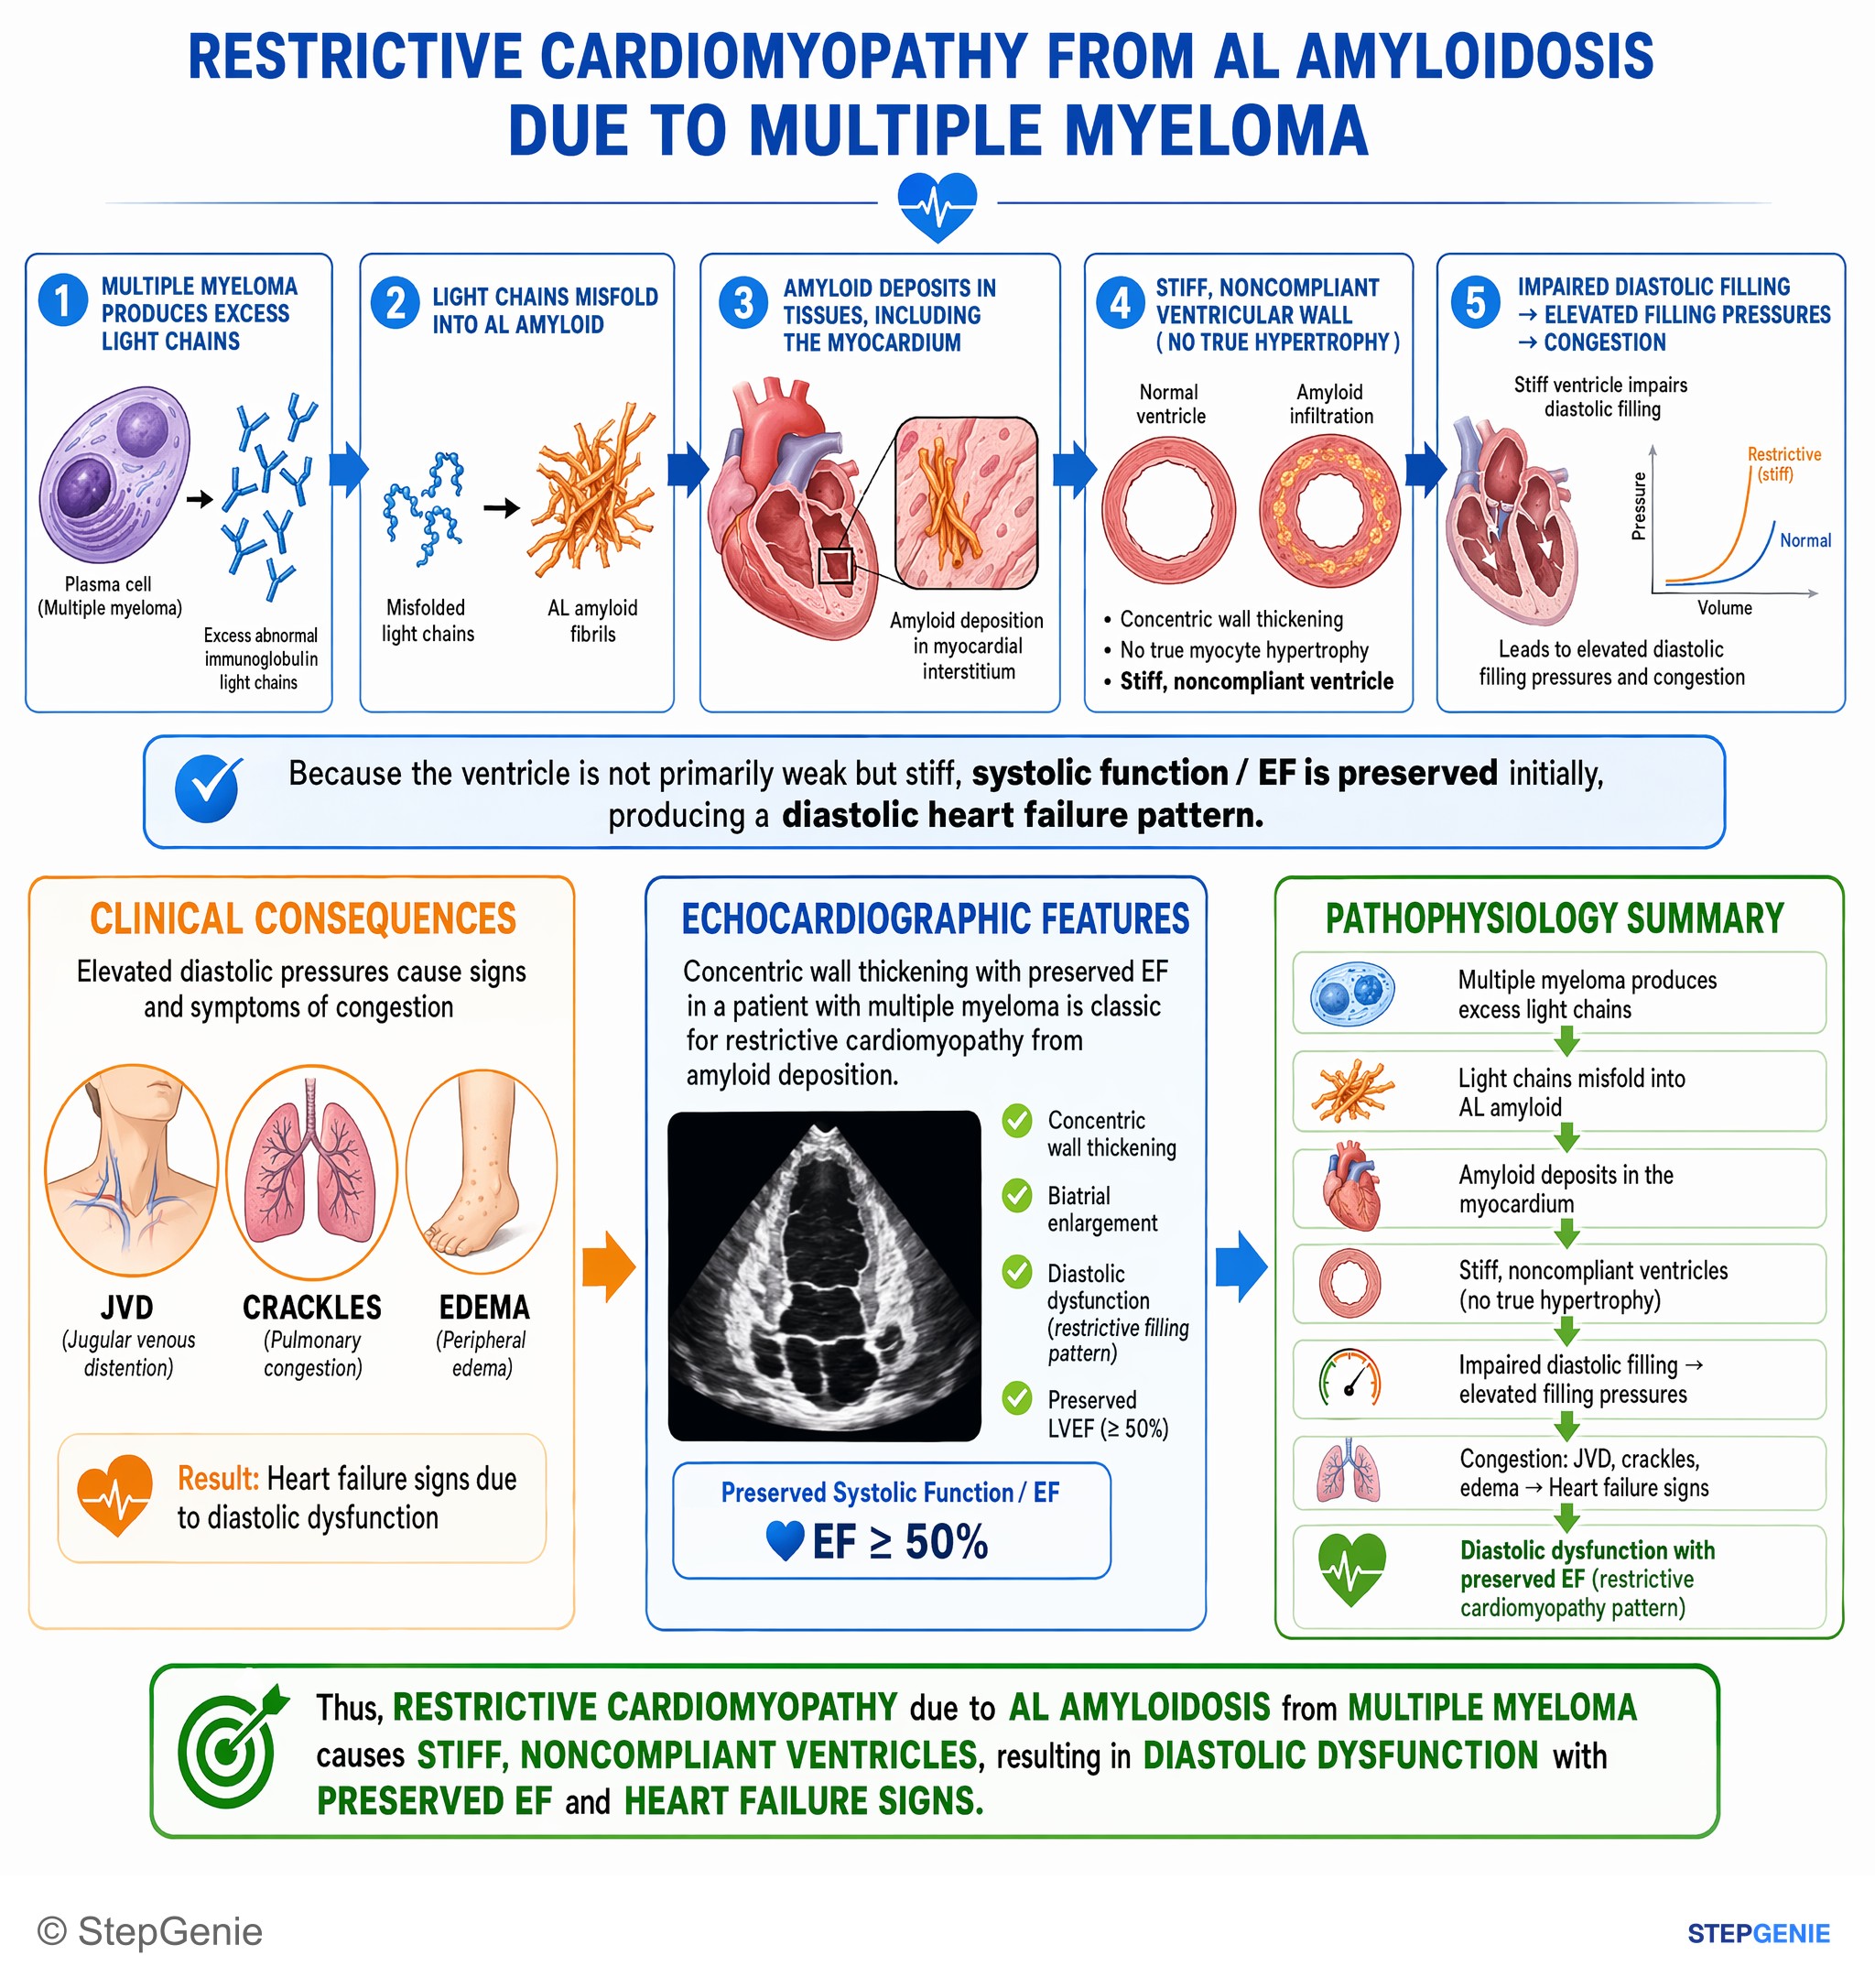
Restrictive cardiomyopathy due to AL amyloidosis from multiple myeloma causes stiff, noncompliant ventricles → diastolic dysfunction with…
USMLE Step 1Frequently Asked Questions
What is the difference between AL and AA amyloidosis?
AL amyloid is made of monoclonal immunoglobulin light chains from a plasma cell clone, while AA amyloid is made of serum amyloid A, an acute-phase reactant produced by the liver during chronic inflammation. AL points to a monoclonal protein and classically causes macroglossia, periorbital purpura, nephrotic syndrome, heart and nerve disease. AA follows years of conditions such as rheumatoid arthritis, inflammatory bowel disease, familial Mediterranean fever or tuberculosis and most often presents with proteinuria. AL is treated with plasma cell–directed therapy, whereas AA is treated by controlling the underlying inflammation.
What is familial amyloid polyneuropathy?
Familial amyloid polyneuropathy is the older name for hereditary transthyretin (ATTRv) amyloidosis presenting with neuropathy. It is autosomal dominant, caused by variants in the TTR gene on chromosome 18, and the most common variant, V30M, clusters in Portugal, Sweden and Japan. Patients develop a length-dependent neuropathy that starts in the feet with early loss of pain and temperature sensation, plus autonomic failure such as orthostatic hypotension, alternating diarrhea and constipation, and erectile dysfunction. Treatment uses TTR gene silencers or tetramer stabilizers.
How is amyloidosis diagnosed?
Amyloidosis is diagnosed by biopsy, often starting with an abdominal fat pad aspirate, showing Congo red–positive deposits with apple-green birefringence under polarized light. Serum free light chains and serum and urine immunofixation are then used to look for the monoclonal protein of AL amyloidosis. The deposit itself is typed, ideally by mass spectrometry, because a monoclonal protein can be incidental. In the heart, a technetium pyrophosphate scan with strong uptake and no monoclonal protein can diagnose ATTR amyloidosis without a biopsy.
What is wild-type ATTR amyloidosis?
Wild-type ATTR amyloidosis, previously called senile systemic amyloidosis, is caused by deposition of normal, non-mutated transthyretin and mainly affects the hearts of older men. It causes a restrictive cardiomyopathy that looks like heart failure with preserved ejection fraction, with thick ventricular walls on echocardiography but low voltage on the ECG. Carpal tunnel syndrome, biceps tendon rupture or lumbar spinal stenosis can appear years before the heart disease. It is treated with TTR stabilizers such as tafamidis or acoramidis.
Which type of amyloidosis is caused by long-term dialysis?
Long-term hemodialysis causes dialysis-related amyloidosis, in which beta-2 microglobulin accumulates and deposits mainly in the musculoskeletal system. It classically causes late-onset carpal tunnel syndrome, bilateral arthropathy and bone destruction. In a dialysis patient with carpal tunnel syndrome, beta-2 microglobulin is a more likely explanation than AL amyloidosis.