Inflammation is one of those “you either see it everywhere or nowhere” topics on USMLE—until you memorize the patterns. The key is to stop thinking of it as a vague immune response and start treating acute vs chronic inflammation like two different clinical-pathologic programs with predictable triggers, cells, mediators, timing, and outcomes.
The one-liner (use this to anchor everything)
- Acute inflammation = rapid, neutrophil-predominant, exudative response to injury/infection → aims to eliminate the insult and start repair.
- Chronic inflammation = prolonged, mononuclear (macrophages/lymphocytes/plasma cells) response with tissue destruction + repair (fibrosis/angiogenesis) happening at the same time.
Visual mnemonic: “N² vs M²” (fast recall)
Think of inflammation like two modes of your immune system:
Acute = N²
- Now (minutes–days)
- Neutrophils
Chronic = M²
- Months (weeks–years)
- Mononuclear cells (macrophages + lymphocytes + plasma cells)
Cheat image in your head:
Acute = a flash flood (sudden, leaky vessels, lots of “stuff” pours out).
Chronic = a construction site (demolition + rebuilding + scar).
Acute vs Chronic — side-by-side table (the “one page” core)
| Feature | Acute inflammation | Chronic inflammation |
|---|---|---|
| Onset/duration | Rapid; minutes–days | Insidious; weeks–years |
| Major triggers | Infections (esp bacteria), tissue necrosis (MI), foreign bodies, hypersensitivity | Persistent infection (TB, fungi, H. pylori), autoimmune disease (RA, IBD), prolonged toxin exposure (silica), foreign body |
| Dominant cells | Neutrophils (early), then macrophages later | Macrophages, lymphocytes, plasma cells (± eosinophils) |
| Hallmarks | Vascular leakage (exudate) + neutrophil recruitment | Tissue destruction + fibrosis + angiogenesis |
| Key mediators | Histamine, prostaglandins, leukotrienes, bradykinin, complement, IL-1/TNF | IFN-γ, IL-12, TNF, TGF-β (fibrosis), growth factors |
| Common morphologic patterns | Serous, fibrinous, purulent, ulcers | Chronic active inflammation, granulomatous inflammation |
| Outcomes | Resolution, abscess, scarring, progression to chronic | Fibrosis/scarring, organ dysfunction, granulomas |
High-yield buzzword:
- Exudate = protein-rich (inflammation ↑ vascular permeability)
- Transudate = protein-poor (hydrostatic/oncotic imbalance)
Acute inflammation: what Step questions love
1) Vascular changes (the “leaky hose”)
Sequence you should picture:
- Vasodilation → ↑ blood flow → rubor/calor
- ↑ Vascular permeability → fluid/proteins leave vessel → tumor
- Stasis → leukocytes marginate to vessel wall
Mechanisms of increased permeability (high yield):
- Histamine (mast cells) → endothelial contraction in postcapillary venules (immediate, transient)
- Leukotrienes (C4/D4/E4) → ↑ permeability, bronchospasm
- Direct endothelial injury (burns) → immediate and sustained leak
2) Neutrophil recruitment (the adhesion molecule ladder)
Use the classic Step sequence:
Margination → Rolling → Adhesion → Diapedesis → Chemotaxis
| Step | Key molecules | High-yield detail |
|---|---|---|
| Rolling | Selectins (E-, P-, L-) | E-selectin induced by IL-1/TNF |
| Adhesion | Integrins (LFA-1, Mac-1) binding ICAM-1/VCAM-1 | Integrins activated by chemokines |
| Diapedesis | PECAM-1 (CD31) | Through postcapillary venules |
| Chemotaxis | C5a, IL-8, LTB4, bacterial products | “C5a calls cells” is a common memory hook |
3) Neutrophil timing (a classic testable pivot)
- Neutrophils dominate early (first 24 hours-ish)
- Macrophages dominate later (24–48+ hours)
USMLE pearl: Some infections flip the script (e.g., viral → lymphocytes; TB → macrophages/granulomas).
Acute morphology patterns (buzzwords → diagnosis)
| Pattern | What it is | Where you see it |
|---|---|---|
| Serous | watery, low-cell fluid | skin blister, serous cavities |
| Fibrinous | fibrin-rich exudate | pericarditis/pleuritis (“bread and butter”) |
| Purulent (suppurative) | pus = neutrophils + necrotic debris | abscess, bacterial infections (Staph aureus) |
| Ulcer | loss of epithelium + inflamed base | peptic ulcer, colitis |
Chronic inflammation: the “3 big components”
Chronic inflammation is defined by:
- Mononuclear infiltrate (macrophages, lymphocytes, plasma cells)
- Tissue destruction
- Repair attempts (angiogenesis + fibrosis)
Macrophages are the main character
Macrophages don’t just “clean up”—they direct the whole show.
Activation pathways (high yield):
- M1 macrophages (“microbicidal”): triggered by IFN-γ and microbial products → make ROS, NO, IL-1, TNF (inflammation)
- M2 macrophages (“repair”): driven by IL-4/IL-13 → make TGF-β, growth factors (fibrosis)
Translation for exams: Chronic inflammation often means ongoing injury plus scarring.
Granulomatous inflammation (frequent Step target)
A granuloma is a collection of activated macrophages (epithelioid histiocytes) often with multinucleated giant cells, usually surrounded by lymphocytes.
Two major types
- Caseating granulomas: classically TB, some fungi (Histoplasma)
- “Caseating” = cheesy necrosis
- Noncaseating granulomas: sarcoidosis, Crohn disease, berylliosis
- No central necrosis
Mechanism (high yield):
- Th1 response: IL-12 promotes Th1 → Th1 produces IFN-γ → macrophage activation → granuloma
Acute vs chronic: exam-style “tell me which one” clues
Clues for acute
- Sudden onset pain/swelling
- Neutrophils
- Edema/exudate
- Bacterial infection, abscess, fibrinous pericarditis
Clues for chronic
- Long-standing symptoms
- Lymphocytes + plasma cells + macrophages
- Fibrosis, angiogenesis, tissue destruction
- Autoimmune disease, TB, chronic osteomyelitis
Micro-rapid facts (memorize these bullets)
- IL-1 and TNF = “endogenous pyrogens” → fever; also increase adhesion molecule expression.
- C3a and C5a = anaphylatoxins (mast cell degranulation); C5a is also chemotactic.
- Bradykinin = pain + ↑ vascular permeability.
- PGE2 contributes to fever and pain; NSAIDs reduce PGE2 by inhibiting COX.
- Resolution is more likely when injury is short-lived and tissue can regenerate; fibrosis dominates when damage is severe or tissue cannot regenerate.
Ultra-condensed “shareable” cheat sheet (copy/paste)
Acute (N²): Now + Neutrophils → vasodilation + ↑ permeability → exudate → resolve/abscess/scar
Chronic (M²): Months + Mononuclear → macrophages/lymphocytes/plasma cells → destruction + fibrosis + angiogenesis (± granulomas)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
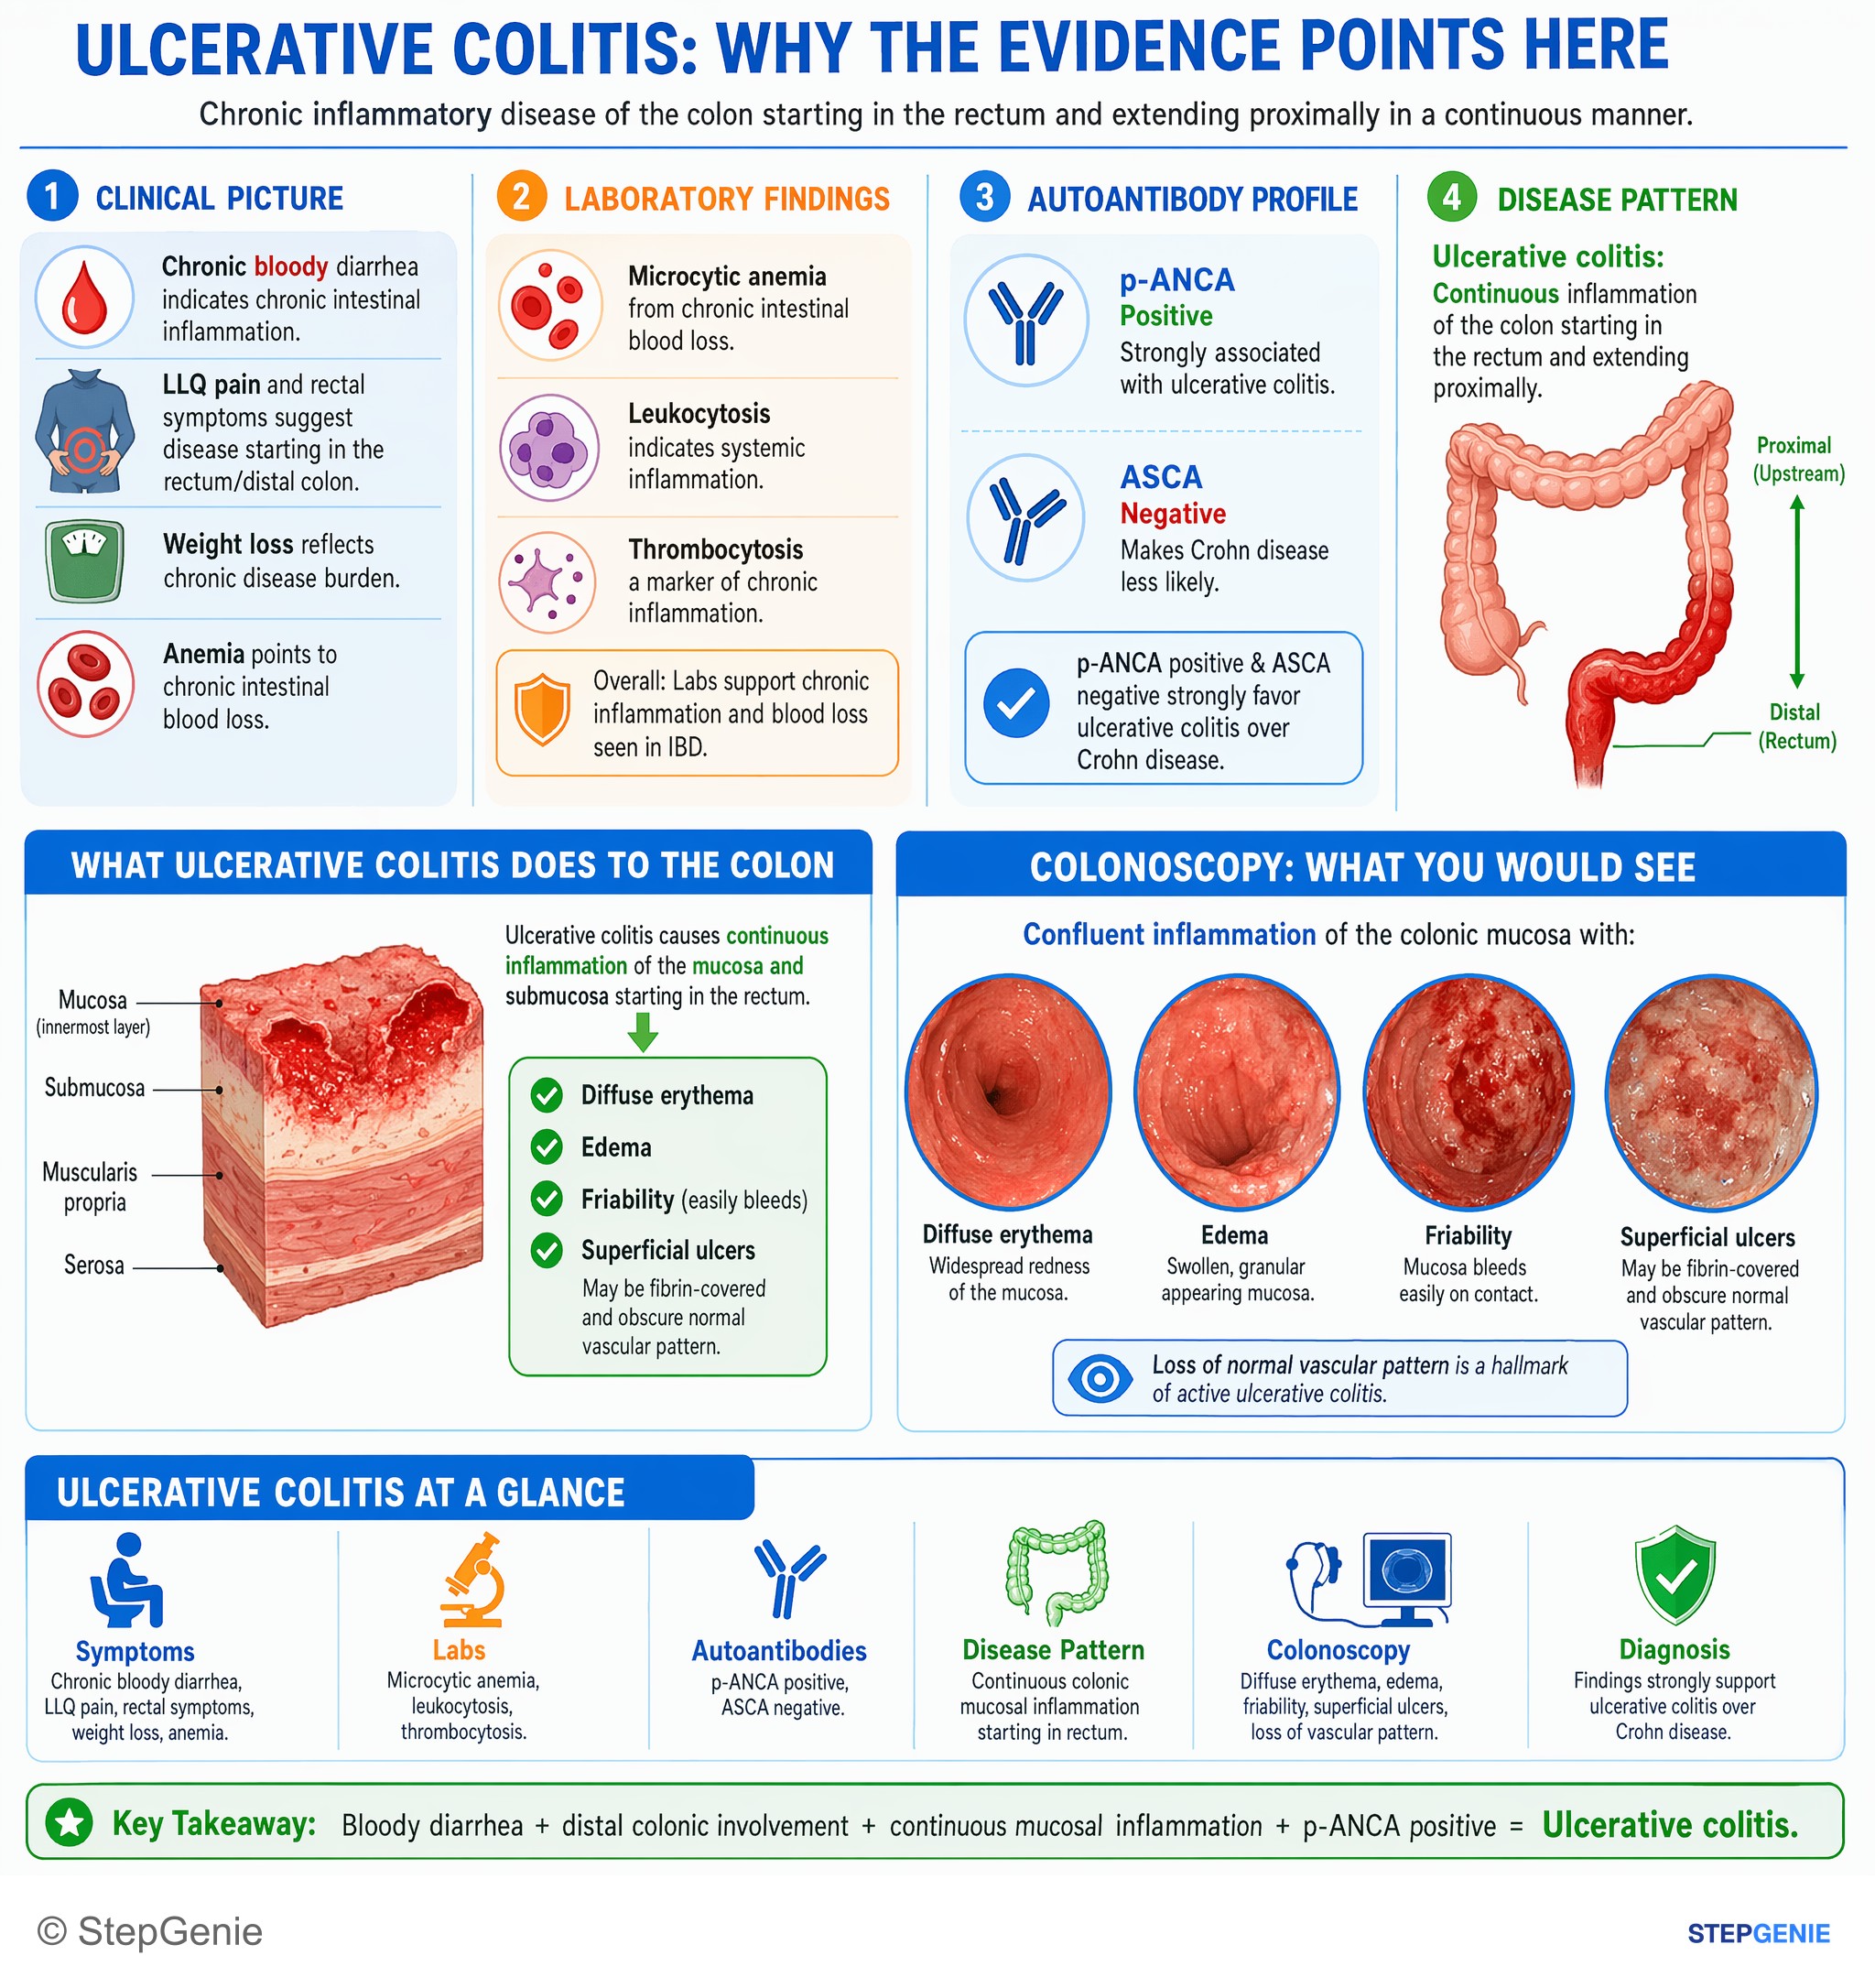
Ulcerative colitis: continuous colonic mucosal inflammation, bloody diarrhea, weight loss, positive p-ANCA; colonoscopy shows diffuse…
USMLE Step 1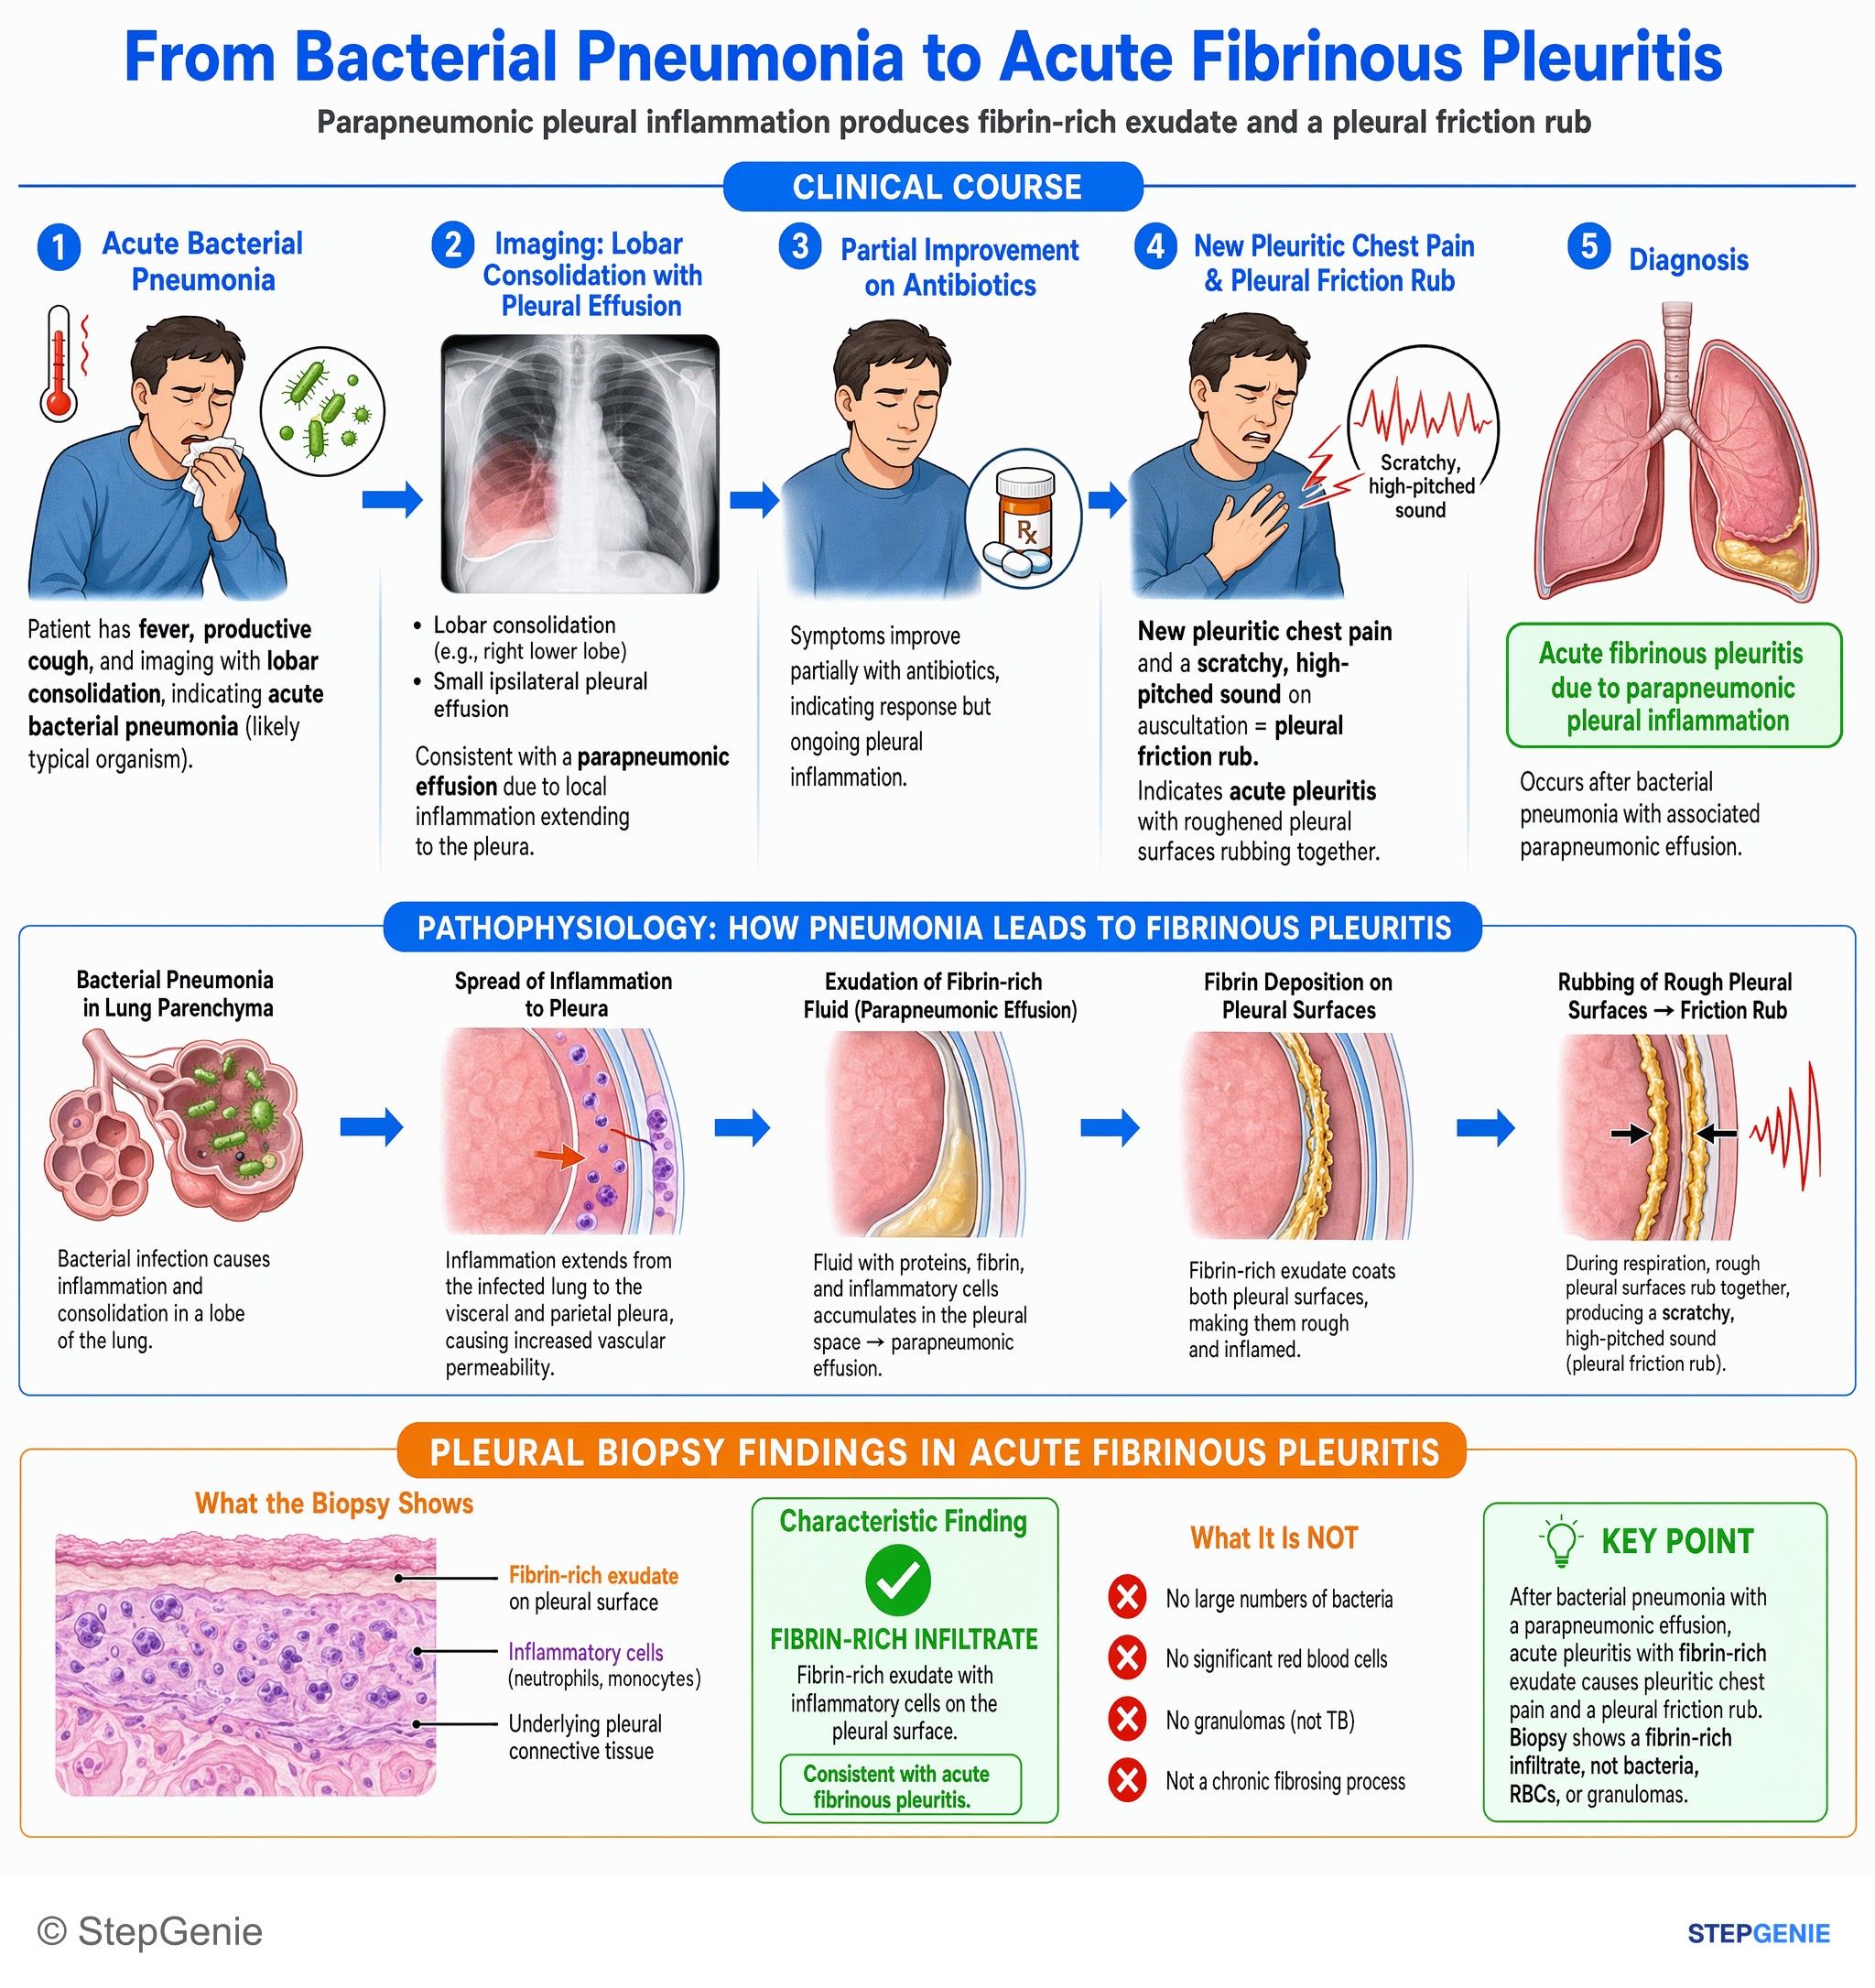
Acute fibrinous pleuritis from parapneumonic pleural inflammation shows a fibrin-rich exudate on the pleural surface after bacterial…
USMLE Step 1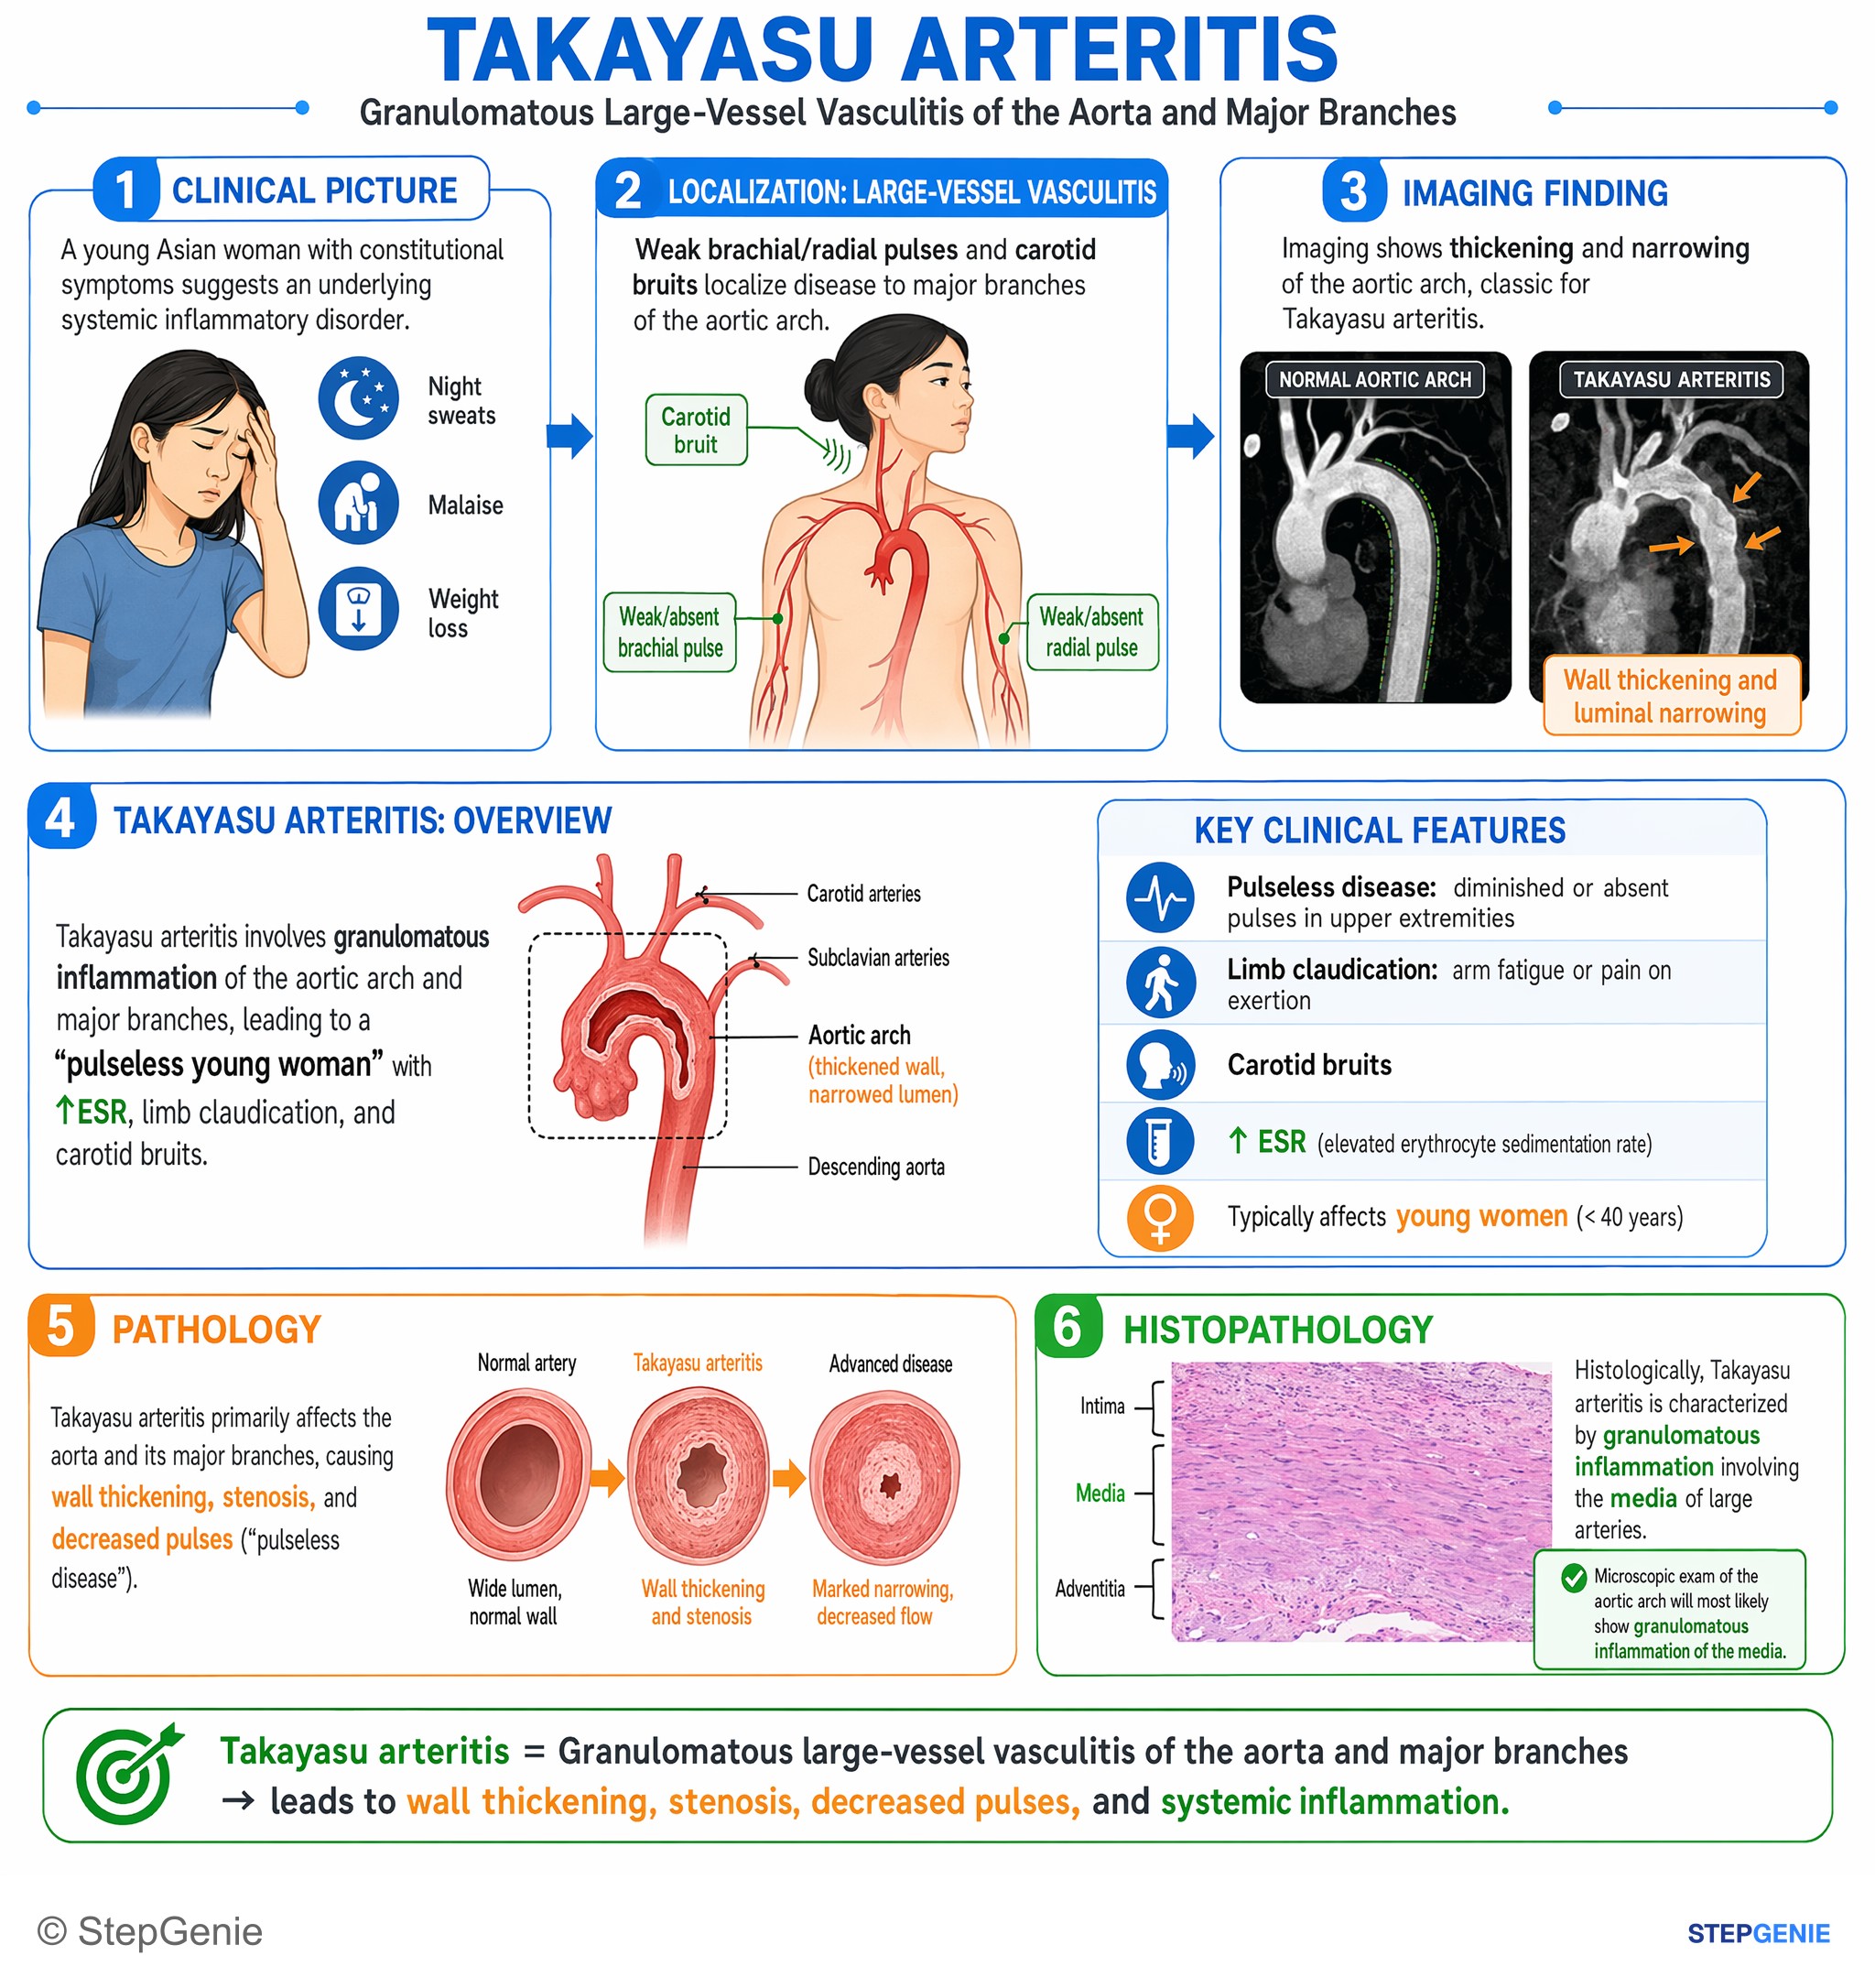
Takayasu arteritis: granulomatous inflammation of aortic arch and major branches → pulseless young woman, ↑ESR, limb claudication, carotid…
USMLE Step 1Frequently Asked Questions
How do you tell acute inflammation from chronic inflammation on pathology questions?
Acute inflammation is a rapid, neutrophil-predominant, exudative response that develops over minutes to days, while chronic inflammation is a prolonged mononuclear response that lasts weeks to years. Acute inflammation is marked by vascular leakage and neutrophil recruitment. Chronic inflammation is identified by macrophages, lymphocytes, and plasma cells along with tissue destruction, fibrosis, and angiogenesis happening at the same time.
Why is exudate protein-rich but transudate protein-poor?
Exudate is protein-rich because inflammation increases vascular permeability, allowing fluid and proteins to leave the vessel. That is a hallmark of acute inflammation, where leaky vessels produce edema and protein-rich fluid. Transudate, in contrast, is protein-poor because it results from hydrostatic or oncotic imbalance rather than an inflammatory increase in vascular permeability.
What is the sequence of neutrophil recruitment in acute inflammation?
The classic sequence is margination, rolling, adhesion, diapedesis, and chemotaxis. Rolling is mediated by selectins, with E-selectin induced by IL-1 and TNF. Adhesion uses integrins such as LFA-1 and Mac-1 binding ICAM-1 and VCAM-1. Diapedesis occurs through postcapillary venules via PECAM-1, and chemotaxis is driven by C5a, IL-8, LTB4, and bacterial products.
When do neutrophils vs macrophages predominate in acute inflammation?
Neutrophils predominate early, and macrophages predominate later. In acute inflammation, neutrophils are the dominant cells in the first roughly 24 hours, then macrophages become more prominent after about 24 to 48 hours. Some infections can shift the expected pattern, such as viral infections favoring lymphocytes and tuberculosis favoring macrophages and granulomas.
How do you recognize granulomatous inflammation and what causes caseating vs noncaseating granulomas?
Granulomatous inflammation is recognized by collections of activated macrophages called epithelioid histiocytes, often with multinucleated giant cells and surrounding lymphocytes. Caseating granulomas are classically seen in tuberculosis and some fungal infections such as Histoplasma and have cheesy necrosis. Noncaseating granulomas lack central necrosis and are associated with sarcoidosis, Crohn disease, and berylliosis.