Surrogate decision-making is how treatment is decided for a patient who lacks decision-making capacity. The first choice is someone with formal authority: the health care agent the patient named in a durable power of attorney for health care, or a court-appointed guardian; otherwise most states' laws name a default surrogate, typically a spouse or domestic partner, then adult children, parents and adult siblings, although the order varies by state. The surrogate must decide as the patient would have (substituted judgment), starting from any living will or clear prior wishes, and uses the patient's best interest only when those wishes cannot be known. Persistent conflict goes to the ethics committee and, as a last resort, to court; in a true emergency with no one available, the physician treats.
Step 1: Does the patient really lack capacity?
A surrogate is needed only when the patient cannot make this decision now.
- The four abilities (AFP 2018): communicate a choice; understand the benefits, risks and alternatives; appreciate how they apply to them; reason about the options. Any physician can assess capacity.
- Capacity is clinical; competence is legal. Health care professionals judge capacity; only a court can find an adult legally incompetent and appoint a guardian (Merck).
- It fluctuates. Capacity "may be intermittent, variable, and affected by the environment," and patients impaired by intoxication, delirium, depression or agitation may regain it (Merck). If the decision can wait, treat the cause and reassess.
- Keep the patient involved. Physicians should engage patients with impaired capacity "to the greatest extent possible" (AMA Opinion 2.1.2). When capacity returns, the patient decides again.
More: capacity vs competence.
Step 2: Who decides
| Rank | Decision-maker | Key rules |
|---|---|---|
| 1 | Health care agent named in a durable power of attorney for health care (health care proxy), or a court-appointed guardian with health care authority | Acts within the scope of the document or court order; outranks default relatives |
| 2 | Default surrogate under state law, typically: spouse or domestic partner → adult children → parents → adult siblings → possibly other relatives or a close friend | "Most states authorize default surrogate decision makers," but scope and priority "vary by state" (Merck) |
| 3 | Nobody available | Emergency: treat. Otherwise: an institutional process with the ethics committee, sometimes guardianship |
State laws really differ. Washington (RCW 7.70.065, amended 2022) ranks a guardian above the health care agent; after spouse or state-registered domestic partner, adult children, parents and adult siblings come adult grandchildren, nieces and nephews, and aunts and uncles (each only if familiar with the patient), and last an adult close friend who has shown special care and concern and signs a declaration under penalty of perjury. Washington requires all available members of a class to agree unanimously and bars anyone from consenting if a higher-priority person has refused; some states let clinicians follow a majority (Merck). On the exam, use the typical order unless the stem says otherwise.
Who-decides traps:
- Knowledge is not authority. The relative with the most vivid account of the patient's wishes supplies evidence; the legal surrogate decides.
- "Next of kin" is not a rank. Work down the order: an adult child, estranged or not, does not outrank a spouse.
- Lower tiers don't outvote a higher one. Three adult children cannot overrule the spouse.
- A friend decides only if named as agent or listed in the state's default order.
- Physicians don't replace an available surrogate. They give "advice, guidance, and support," and the surrogate "is entitled to the same respect as the patient" (AMA 2.1.2).
Step 3: How the surrogate decides
| Order | Standard | The question | What it rests on |
|---|---|---|---|
| 1 | The patient's own instructions | Did the patient already decide this? | A living will or other clear instructions from the patient, written or oral, that fit the situation |
| 2 | Substituted judgment | What would the patient choose now? | "The patient's views about life and how it should be lived," "how the patient constructed their life story," "attitudes toward sickness, suffering, and certain medical procedures" |
| 3 | Best interest | What best serves the patient? | "The pain and suffering associated with the intervention," "the degree of and potential for benefit," "impairments that may result from the intervention," "quality of life as experienced by the patient" |
Quotes from AMA 2.1.2, which treats preferences in an advance directive or the medical record as the first evidence for substituted judgment.
- Substituted judgment is not the surrogate's own preference: it is "the choice she believes the patient would have wanted, which may not be the choice the decision-maker would have chosen for herself" (UW).
- A living will counts only when the situation it describes has arisen; see advance directives.
- Best interest is used when wishes can't be known, including for children: "The substituted judgment standard may not apply because the minor patient never had decision-making capacity" (UW).
What a surrogate can and cannot do
- Can refuse or stop treatment, including life-sustaining treatment, "in keeping with ethics guidance for surrogate decision making," and "there is no ethical difference between withholding and withdrawing treatment" (AMA 5.3). Honoring that refusal is not assisted death; see physician-assisted death.
- Cannot demand ineffective care. Physicians need not provide interventions that "cannot reasonably be expected to yield the intended clinical benefit or achieve agreed-on goals for care," because "respecting patient autonomy does not mean that patients should receive specific interventions simply because they (or their surrogates) request them" (AMA 5.5). Fair process: clarify goals, promise symptom management, involve the ethics committee, offer transfer.
- Cannot override the patient. If the patient regains capacity, the patient decides. If an agent's choice seems to conflict directly with the patient's living will or other clear instructions, the outcome depends on how much discretion the document gave the agent (Merck); involve the ethics committee. Background: autonomy, beneficence, nonmaleficence and justice.
Conflicts: ethics committee first, court last
Consult the ethics committee (AMA 2.1.2) when:
- no surrogate is available, or there is disagreement about who it is;
- disagreement about a treatment decision persists;
- the surrogate's decision is clearly not what the patient would have chosen, could not reasonably be judged in the patient's best interest, or mainly serves the surrogate's or others' interests.
Ethics consultants act "as advisors and educators rather than decision makers," and no one is required to accept their recommendations (AMA 10.7.1). Many institutions make the ethics committee available on short notice, while "judicial review is typically more time-consuming"; if no ethically and legally sound resolution can be agreed, the institution "may need to request court review" (Merck).
Emergencies, unrepresented patients and minors
- Emergency exception. "In emergencies, when a decision must be made urgently, the patient is not able to participate in decision making, and the patient's surrogate is not available, physicians may initiate treatment without prior informed consent," then inform the patient or surrogate at the earliest opportunity (AMA 2.1.1; more on informed consent exceptions). Keep trying to reach the surrogate.
- Unrepresented ("unbefriended") patients lack capacity, an applicable advance directive and an available surrogate. ATS/AGS (2020): "diligently search" for family and friends; decide through collaboration with an interprofessional committee "rather than ad hoc by treating clinicians," using any known preferences and otherwise the best-interest standard; consider guardianship; and don't wait for an emergency so that consent is implied.
- Minors. Parents or guardians decide, by the child's best interests. Outside an emergency, a parent's decision "can be overridden only if a court determines that the decision constitutes neglect or abuse" (Merck), so seek a court order when time allows; in an emergency, treat under implied consent and document it (UW). Emancipated minors (married, on active military duty, or living apart and managing their own finances; laws vary by state) can consent to or refuse their own care, and very few states recognize a "mature minor" doctrine (StatPearls). In most states minors can consent to STI treatment, birth control, substance use treatment and mental health care (Merck).
How USMLE tests it
| Stem | Best answer |
|---|---|
| Intubated patient, no directive; wife and adult children disagree | Wife is the surrogate (typical order); meet about what he would want; ethics consult if conflict persists |
| Patient named his sister as health care agent; his wife objects | The agent (sister) decides |
| No spouse; three adult children split 2-1 | Seek consensus; majority vs unanimity rules vary by state; ethics consult |
| Surrogate's choice clearly contradicts the patient's known wishes | Remind the surrogate to decide as the patient would; ethics committee if it persists |
| Surrogate demands treatment that cannot achieve the patient's goals | Not obligated; fair process (ethics, offer transfer) |
| Unconscious patient, life-threatening emergency, nobody reachable | Treat now; keep trying to reach family |
| Delirious patient; the decision can wait | Treat the cause, then reassess capacity |
| No family or friends; nonurgent decision | Institutional process (ethics committee); possibly guardianship |
Practice question
A 68-year-old man is intubated in the ICU after a large intracerebral hemorrhage. He is sedated and cannot communicate, and the neurology team expects a poor neurologic recovery. He has no written advance directive and never named a health care agent. His wife of 30 years says, "Do everything. He's a fighter." His adult daughter reports that last year, after visiting a friend on long-term life support, he told her he would "never want to be kept alive on machines like that." His adult son, who has not seen him in years, agrees with the wife. Which of the following is the most appropriate next step?
A. Ask the daughter to make decisions, because she has the clearest evidence of his wishes B. Follow the majority of the family and continue all treatment indefinitely C. Meet with his wife as the surrogate, explain that her role is to decide as he would, and review the daughter's account of his wishes together D. Let the ICU team decide based on his best interest, because the family disagrees E. Petition the court to appoint a guardian before any further decisions are made
Answer: C. He lacks capacity and has no agent, so under the typical default order his wife is the surrogate. Her task is substituted judgment: what he would choose, which may differ from what she wants for him. His remark to the daughter is specific evidence of his values (so is "he's a fighter"); help the wife weigh it, and involve the ethics committee if the conflict persists.
- A: the daughter's report is evidence, not authority; adult children rank below a spouse.
- B: surrogates don't decide by family vote, and majority rules (where they exist) apply only among relatives of the same rank; the standard is what he would want.
- D: physicians don't replace an available surrogate, and best interest is used only when his wishes cannot be known.
- E: a court is slow and a last resort, after the surrogate pathway and ethics consultation fail.
Key takeaways
- A surrogate is needed only when the patient lacks capacity for this decision now; treat reversible causes and reassess if you can wait.
- Who: the patient's chosen agent (or a guardian), then the state's default surrogate: typically spouse or domestic partner, adult children, parents, adult siblings. Order and tie-break rules vary by state.
- How: the patient's own instructions, then substituted judgment, then best interest (used for children and whenever wishes can't be known).
- Who decides is not who knows best: relatives with stories supply evidence, not authority.
- Ethics committee for no surrogate, disputes or surrogate decisions that betray the patient's wishes or interests; court last.
- Emergency, nobody available: treat, then inform. Surrogates may refuse or withdraw life-sustaining treatment but cannot demand ineffective care.
Sources
- Opinion 2.1.2: Decisions for Adult Patients Who Lack Capacity — AMA Code of Medical Ethics
- Opinion 2.1.1: Informed Consent — AMA Code of Medical Ethics
- Opinion 5.3: Withholding or Withdrawing Life-Sustaining Treatment — AMA Code of Medical Ethics
- Opinion 5.5: Medically Ineffective Interventions — AMA Code of Medical Ethics
- Opinion 10.7.1: Ethics Consultations — AMA Code of Medical Ethics
- Consent and Surrogate Decision Making — Merck Manual Professional Edition (2025)
- Capacity (Competence) and Incapacity — Merck Manual Professional Edition (2025)
- Evaluating Medical Decision-Making Capacity in Practice — American Family Physician (2018)
- Clinical Ethics and Law — UW Department of Bioethics & Humanities
- RCW 7.70.065: Informed Consent, Persons Authorized to Provide for Patients Who Do Not Have Capacity — Washington State Legislature (2022)
- Making Medical Treatment Decisions for Unrepresented Patients in the ICU: ATS/AGS Policy Statement — American Journal of Respiratory and Critical Care Medicine (2020)
- Emancipated Minor — StatPearls, NCBI Bookshelf (2023)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
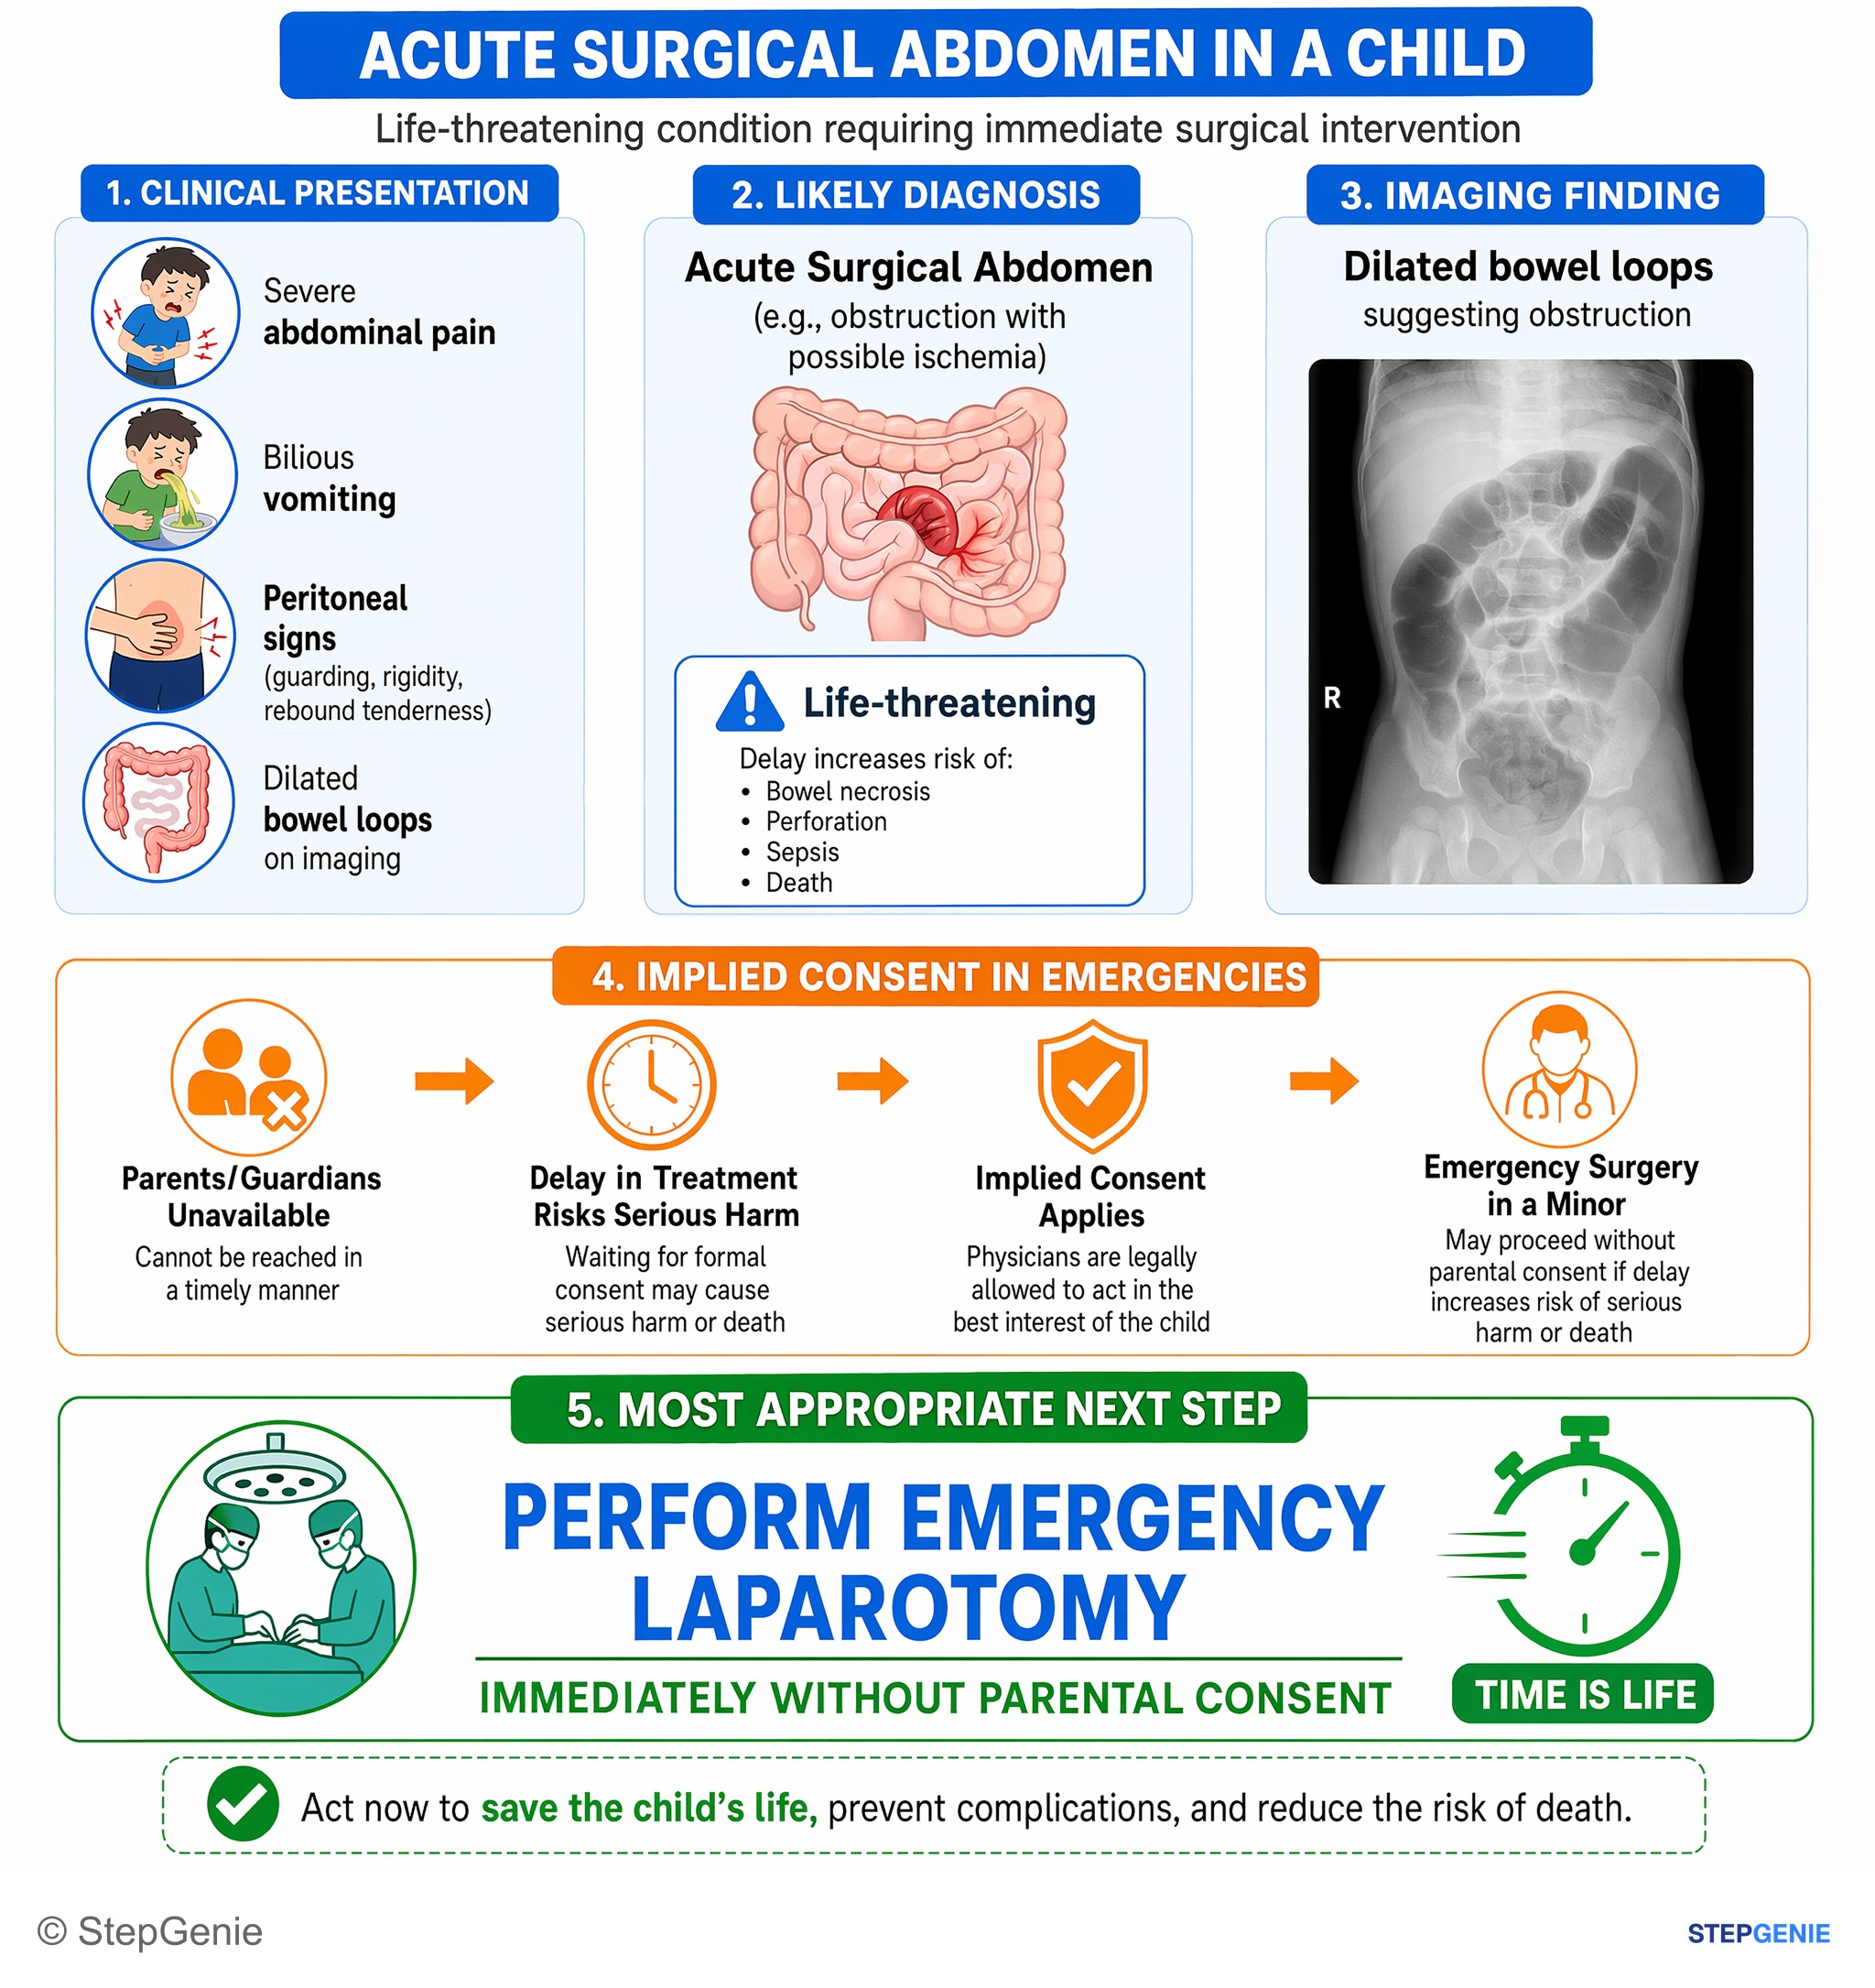
Emergency surgery in a minor: life-threatening condition → physicians may treat without parental consent if delay increases risk of…
USMLE Step 2Frequently Asked Questions
What is surrogate decision-making?
Surrogate decision-making is when another person makes medical decisions for a patient who lacks decision-making capacity for a particular decision. The surrogate may be a health care agent the patient named in a durable power of attorney for health care, a court-appointed guardian, or a default surrogate named by state law, usually a close family member. The surrogate's job is to decide as the patient would have decided, not to substitute their own preferences.
What is the order of surrogate decision makers?
If the patient named a health care agent, that person decides, and a court-appointed guardian with health care authority also outranks family. Otherwise most states have a default surrogate law, typically ranking a spouse or domestic partner first, then adult children, parents and adult siblings, then possibly other relatives or a close friend. The exact order and rules vary by state; Washington, for example, ranks a guardian above the agent and requires relatives of the same rank to agree unanimously.
What is the difference between substituted judgment and best interest?
Substituted judgment asks what the patient would choose if able to decide, based on prior statements, values, life story and attitudes toward illness and treatment. It is the preferred standard. The best-interest standard is used only when the patient's wishes cannot be known or the patient never had capacity, as with young children. It weighs the pain and suffering of the intervention, the likely benefit, resulting impairments and quality of life as experienced by the patient.
What happens if family members disagree about a patient's treatment?
The highest-ranking surrogate keeps authority, so lower-ranking relatives cannot outvote a spouse. Among relatives of equal rank, consensus is preferred; some states let clinicians follow a majority, while others, such as Washington, require unanimity. The team should hold a family meeting focused on what the patient would want and consult the ethics committee if disagreement persists. Court review is a last resort because it is slower.
Who makes medical decisions if a patient has no family or surrogate?
In a true emergency, physicians may treat without consent when the decision is urgent, the patient cannot participate and no surrogate is available, then inform the patient or surrogate at the earliest opportunity. For nonurgent decisions, the team should search diligently for family and friends. If none are found, decisions should go through an institutional process with an interprofessional committee, using the patient's known preferences or best interest, and sometimes a court-appointed guardian.
Can a surrogate refuse life-sustaining treatment or demand any treatment?
A surrogate can decline or ask to stop life-sustaining treatment, such as mechanical ventilation, when that reflects the patient's wishes or best interest; withholding and withdrawing are ethically equivalent. A surrogate cannot demand interventions that cannot reasonably achieve the intended benefit or the agreed goals of care. Disputes go through a fair process: discuss goals, ensure symptom management, involve the ethics committee and offer transfer to a willing clinician or institution.