The four principles of medical ethics are autonomy (respect the informed, voluntary choices of a patient with decision-making capacity, including refusal of life-saving treatment), beneficence (act in the patient's best interest), nonmaleficence (avoid harm, weighing risks against benefits) and justice (treat patients fairly and allocate scarce resources by medical need, never by social worth). The principles are not ranked, but USMLE resolves their conflicts with one hinge, capacity: a capable adult's informed refusal beats the physician's judgment and the family's wishes. When the patient cannot decide, a surrogate extends the patient's own values; the best-interest standard (beneficence) takes over in emergencies, when the patient's wishes are unknown and for children, whose parents decide by that standard.
The four principles at a glance
| Principle | Core duty | What it requires | Classic stem | Best answer |
|---|---|---|---|---|
| Autonomy | Respect a capable patient's choices | Informed consent and refusal, truth-telling, confidentiality | Capable adult refuses a life-saving transfusion | Respect the refusal; keep treating with what they accept |
| Beneficence | Act for the patient's good | Recommend the best option; treat when no one can consent | Unconscious trauma patient, nobody reachable | Treat now (emergency exception) |
| Nonmaleficence | Do not harm | Avoid tests and treatments whose harms outweigh benefits | Patient wants antibiotics for a cold | Explain why not; treat the symptoms |
| Justice | Be fair | Allocate by medical need; no discrimination | Wealthy patient asks to jump the transplant list | Decline; follow the allocation policy |
Fast framing: autonomy = who decides; beneficence and nonmaleficence = what is best; justice = who gets what.
Research look-alike: the Belmont Report (1979) names three principles for research: respect for persons, beneficence ("do not harm" and "maximize possible benefits and minimize possible harms") and justice (fair selection of research subjects).
Autonomy: a capable patient decides
- Definition. A patient able to act "intentionally, with understanding, and without controlling influences" makes their own choices (UW). Autonomy is the basis of informed consent and informed refusal.
- Refusal is a right. A patient with capacity "has the right to decline any medical intervention," even when death may result (AMA Opinion 5.3). Disagreeing with you is not evidence of incapacity.
- Family cannot override a capable patient, and a capable patient's current wishes beat their own earlier advance directive.
- Truth-telling. Withholding information without the patient's knowledge or consent "is ethically unacceptable" except in an emergency (AMA 2.1.3). If relatives say "don't tell her it's cancer," ask the patient how much she wants to know.
- Leaving against medical advice follows the same rule: confirm capacity, explain the risks, document, offer follow-up.
Capacity is the hinge (and it is not competence)
| Decision-making capacity | Competence | |
|---|---|---|
| Type | Clinical judgment | Legal status |
| Who decides | Any physician | A judge |
| Scope | One decision at one time; can fluctuate | Set by the court |
| If absent | A surrogate decides | A court-appointed guardian decides |
The four abilities (AFP 2018): communicate a choice, understand the benefits, risks and alternatives, appreciate how they apply to the patient, and reason about the options. Capacity is decision-specific: a patient may be able to consent to a new medication but not to high-risk surgery. Dementia, delirium or a psychiatric diagnosis is a reason to assess capacity, not proof that it is absent. Full vignette: capacity vs competence.
Jehovah's Witness patterns: adult, pregnant patient, child
| Patient | Best answer | Why |
|---|---|---|
| Capable adult refuses blood, even if death is likely | Respect the refusal; manage without blood | "Competent adults can refuse medical treatment, even life-sustaining treatment" |
| Capable pregnant patient refuses transfusion | Respect the refusal | In re Fetus Brown (Illinois appellate court, 1997): "a woman's right to refuse treatment does not diminish during pregnancy" |
| Child needs an emergency transfusion; parents refuse | Transfuse and document | Courts have generally held that a parent "cannot refuse life-sustaining treatment for a child who has not reached the age of consent"; emergency consent is implied |
| Child's transfusion can wait (e.g., planned chemotherapy) | Seek a court order | A court can authorize treatment over the parents' refusal |
| Emancipated minor refuses | Treat like an adult | Emancipation puts the minor "on equal consent footing as an adult" |
Quotes: AMA Journal of Ethics (rows 1-3) and UW Clinical Ethics and Law (row 5). On the exam, birth is the dividing line: before birth, respect the capable pregnant patient's refusal; once the baby is born, the baby can be given life-sustaining treatment over the parents' religious objections.
Beneficence: act for the patient's good, not over their head
- Definition. "A duty to be of a benefit to the patient, as well as to take positive steps to prevent and to remove harm" (UW). It is why you recommend the best option clearly.
- When beneficence (best interest) governs:
- Emergencies. When a decision is urgent, the patient cannot participate and no surrogate is available, treat without prior consent, then inform the patient or surrogate "at the earliest opportunity" (AMA 2.1.1). Implied consent assumes the patient would consent (UW), so it never overrides a known, valid refusal.
- Children. Parents or guardians decide by the child's best interest, because a minor never had decision-making capacity (UW), and they cannot refuse life-saving treatment for the child (table above).
- Unknown wishes. A surrogate falls back on the patient's best interest.
- Imminent suicide risk. Treating suicidal patients "who are a clear and present danger to themselves" is "the most clear cut case of justified paternalism" (UW).
- Paternalism means overriding a patient's wishes for their perceived benefit. With a capable patient it is the classic wrong answer: persuade, but don't coerce, deceive, sedate or transfuse.
Nonmaleficence: first, do no harm
- Definition. Do not "intentionally create a harm or injury to the patient, either through acts of commission or omission," which includes practicing competently (UW).
- When every option carries harm, choose the lesser harm; the patient "alone is the authority" on which harm is greater for them (UW).
- No tests or drugs without an indication: antibiotics don't treat colds or flu but still cause side effects and resistance. Physicians may even decline to take on a prospective patient who requests care that "has no medical indication" (AMA 1.1.2).
- Withholding = withdrawing. "There is no ethical difference between withholding and withdrawing treatment" (AMA 5.3).
The doctrine of double effect
An act with a good and a bad effect is permissible if (UW):
- The act itself is not intrinsically wrong.
- Only the good effect is intended, even though the bad one is foreseen.
- The bad effect is not the means to the good effect.
- The good effect outweighs the bad (proportionality).
How it is tested: titrating opioids or sedatives to relieve pain or dyspnea in a dying patient is acceptable even though respiratory depression is a foreseen risk. Palliative sedation differs from euthanasia and assisted suicide in "intention and the desired outcome," and is "not associated with a shortened life span" (StatPearls). Intending death is a different act: see physician-assisted death vs euthanasia.
Justice: fair treatment and fair allocation
- Definition. Fairness, "giving to each that which is his due" (UW): equal treatment and fair distribution of scarce resources.
- Scarce resources (AMA 11.1.3). Allocate on medical need: "urgency of need, likelihood and anticipated duration of benefit, and change in quality of life," occasionally the resources required. Never on "social worth, perceived obstacles to treatment, patient contribution to illness, past use of resources, or other non-medical characteristics." When patients don't differ substantially, use "an objective, flexible, transparent mechanism."
- Nondiscrimination (AMA 1.1.2). No declining patients because of "race, gender, sexual orientation or gender identity," other clinically irrelevant traits, or "solely" infectious disease status (for example, HIV).
- Emergency access (EMTALA). Medicare-participating hospitals with emergency services must provide a medical screening examination and stabilizing treatment, or an appropriate transfer, "regardless of an individual's ability to pay" (CMS).
When principles collide: the USMLE tie-breakers
In theory each principle is a prima facie duty weighed case by case (UW). Exam stems break ties predictably:
| Conflict | Stem | Best answer |
|---|---|---|
| Autonomy vs beneficence | Capable patient refuses the surgery you recommend | Autonomy: explain, document informed refusal, keep offering care |
| Autonomy vs beneficence | Delirious patient refuses urgent treatment; nobody reachable | Beneficence: emergency exception; treat the delirium; reassess capacity |
| Confidentiality vs harm to others | Patient credibly threatens an identifiable person | Protecting that person can justify disclosure: see confidentiality exceptions |
| Justice vs advocacy | VIP wants an ICU bed or organ sooner | Justice: objective allocation criteria |
Practice question
A 52-year-old man is brought to the emergency department after vomiting a large amount of blood. He is pale and diaphoretic. Pulse is 128/min and blood pressure 82/48 mm Hg; hemoglobin is 6.4 g/dL. Large-bore IV lines are placed, IV fluids and an IV proton pump inhibitor are started, and the team recommends red blood cell transfusion and urgent endoscopy. He is alert and oriented and says, "I am a Jehovah's Witness. I will not accept blood, even if I could die." He explains the risks, benefits and alternatives in his own words and repeats his decision consistently. His adult daughter says, "Please give him blood. He isn't thinking straight." Which of the following is the most appropriate next step?
A. Transfuse red blood cells, because the transfusion is life-saving B. Request an emergency court order authorizing transfusion C. Respect his refusal, proceed with urgent endoscopy and non-blood resuscitation, and ask which blood-sparing measures he accepts D. Obtain his daughter's consent for transfusion as his next of kin E. Request a psychiatric consultation to assess his capacity before treating
Answer: C. He communicates a consistent choice, understands the information, appreciates that he could die and reasons about the options: he has capacity, and a capable adult may refuse any treatment, including a life-saving one (autonomy). Respecting the refusal is not abandoning him: stop the bleeding endoscopically, continue fluids and the PPI, ask exactly which blood-sparing measures he accepts, involve the hospital's Jehovah's Witness liaison committee if there is one, and document the informed refusal.
- A: beneficence used to override a capable patient is paternalism; "life-saving" does not make treatment without consent permissible.
- B: a court is not a workaround for a capable adult's decision. Courts come in for minors, disputed capacity or unresolvable surrogate conflict.
- D: surrogates decide only when the patient lacks capacity, and the daughter's distress does not make his choice irrational.
- E: any physician can assess capacity, and he clearly has it; a consult would only delay endoscopy.
Twists: a 10-year-old who needs an emergency transfusion gets it despite the parents' refusal; an unconscious patient with no known wishes and nobody reachable is treated under the emergency exception.
Key takeaways
- Capacity is the hinge (communicate, understand, appreciate, reason): a capable adult may refuse anything, and family cannot override.
- Best interest (beneficence) governs only in emergencies, for children and when wishes are unknown; overriding a capable patient is paternalism.
- Jehovah's Witnesses: a capable adult (pregnant or not) may refuse blood; parents cannot refuse a life-saving transfusion for their child.
- Nonmaleficence: no unindicated care; withholding = withdrawing; double effect allows a foreseen, unintended risk, never an intended death.
- Justice: allocate by medical need, never by social worth or ability to pay; EMTALA guarantees emergency screening and stabilization.
Sources
- Principles of Bioethics — UW Department of Bioethics & Humanities
- Clinical Ethics and Law — UW Department of Bioethics & Humanities
- Opinion 2.1.1: Informed Consent — AMA Code of Medical Ethics
- Opinion 2.1.3: Withholding Information from Patients — AMA Code of Medical Ethics
- Opinion 5.3: Withholding or Withdrawing Life-Sustaining Treatment — AMA Code of Medical Ethics
- Opinion 11.1.3: Allocating Limited Health Care Resources — AMA Code of Medical Ethics
- Opinion 1.1.2: Prospective Patients — AMA Code of Medical Ethics
- Evaluating Medical Decision-Making Capacity in Practice — American Family Physician (2018)
- When a Parent's Religious Belief Endangers Her Unborn Child — AMA Journal of Ethics (2005)
- Palliative Sedation in Patients With Terminal Illness — StatPearls, NCBI Bookshelf (2024)
- Emergency Medical Treatment & Labor Act (EMTALA) — CMS (2026)
- The Belmont Report — HHS Office for Human Research Protections (1979)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
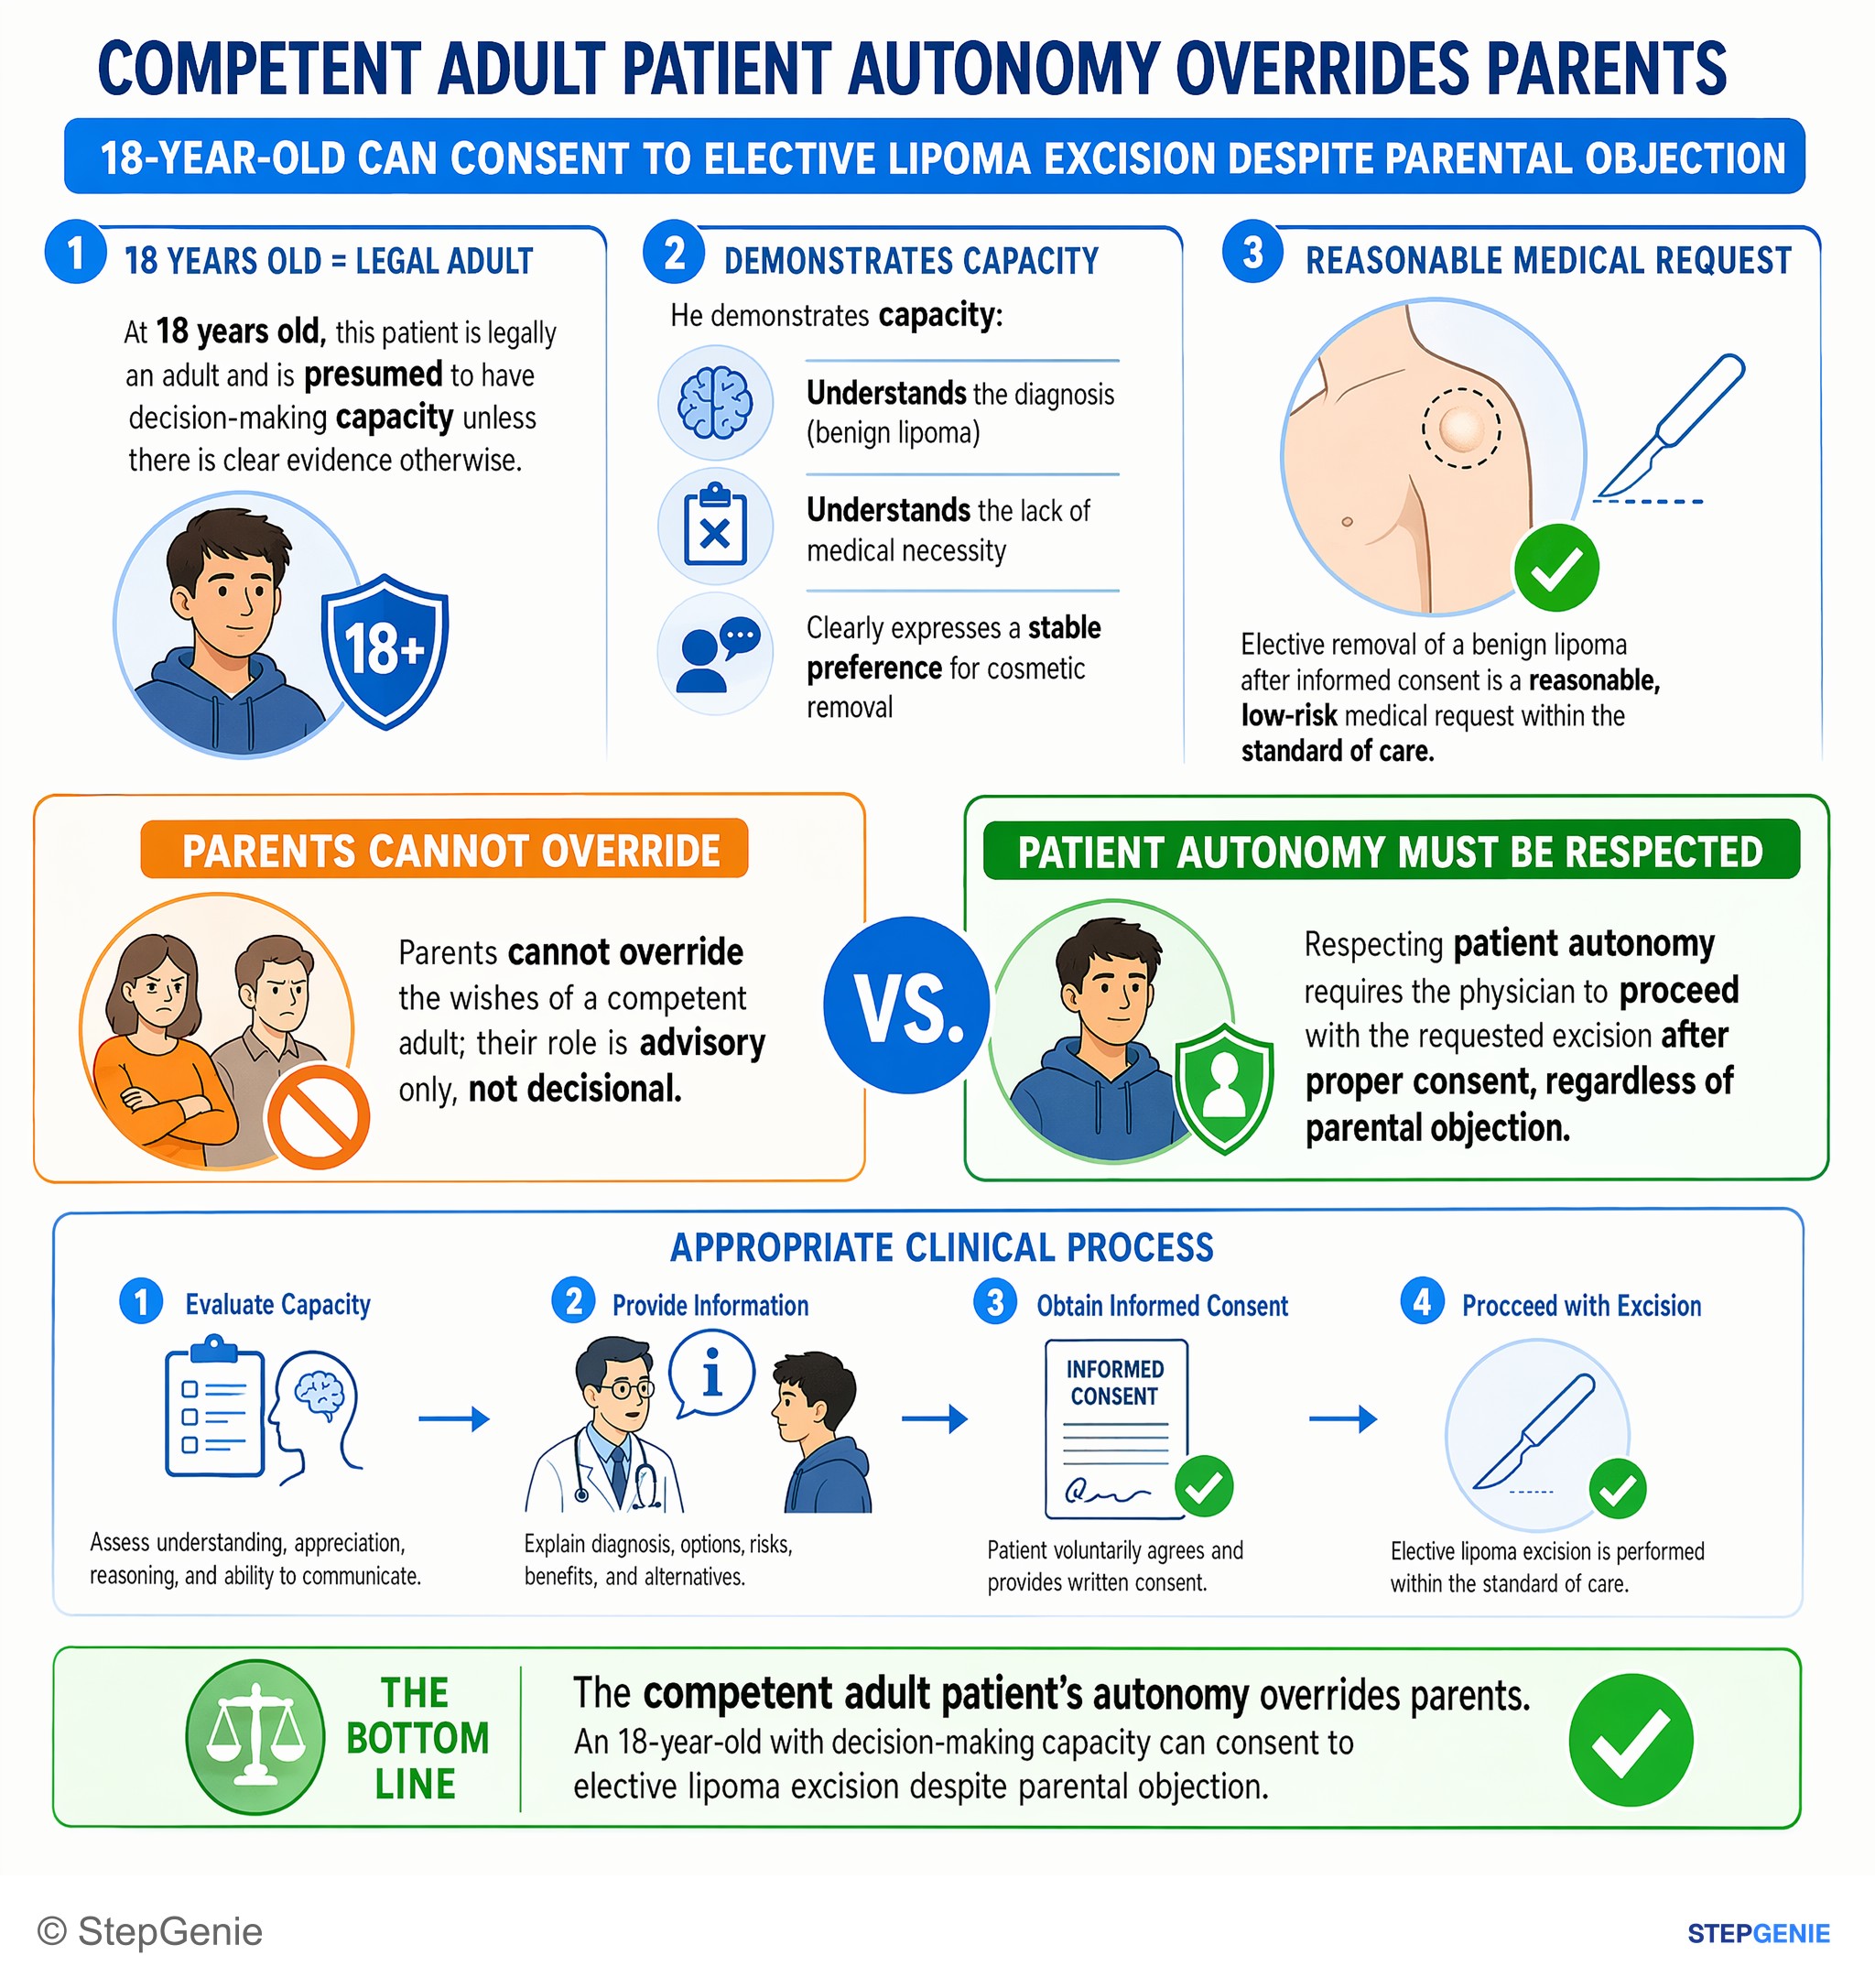
Competent adult patient autonomy overrides parents; 18-year-old can consent to elective lipoma excision despite parental objection.
USMLE Step 2Frequently Asked Questions
What are the four principles of medical ethics?
The four principles are autonomy, beneficence, nonmaleficence and justice. Autonomy means respecting the informed, voluntary choices of a patient who has decision-making capacity, including refusal of treatment. Beneficence is the duty to act in the patient's best interest. Nonmaleficence is the duty to avoid causing harm and to weigh risks against benefits. Justice means treating patients fairly and allocating scarce resources by medical need rather than social worth or ability to pay. None automatically outranks the others; they are weighed case by case.
What is the difference between beneficence and nonmaleficence?
Beneficence is a positive duty to do good for the patient: recommend and provide treatment that benefits them, and take steps to prevent or remove harm. Nonmaleficence is the duty not to cause harm, whether by action or by omission. Most clinical decisions involve both, because nearly every test or treatment carries some risk. They are balanced by proportionality: the expected benefit must outweigh the foreseeable harm, judged in light of the patient's own values and goals.
What is an example of autonomy in medical ethics?
The classic example is a capable adult Jehovah's Witness who refuses a blood transfusion, even one that may be life-saving. If the patient can communicate a choice, understand the information, appreciate the consequences and reason about the options, the physician must respect the refusal, continue other treatment and document an informed refusal. Family members cannot override the decision. Other examples include informed consent, truthful disclosure of a diagnosis, confidentiality, and a capable patient leaving against medical advice.
What is an example of justice in medical ethics?
Justice is fairness in how patients are treated and how scarce resources are shared. Examples include allocating ICU beds or organs by medical criteria such as urgency, likelihood and duration of benefit, and change in quality of life rather than wealth, fame or social worth; refusing to discriminate by race, gender, sexual orientation, gender identity or HIV status; and providing emergency screening and stabilizing treatment regardless of ability to pay, as EMTALA requires of Medicare-participating hospitals that offer emergency services.
What is paternalism, and is it ever justified?
Paternalism is overriding or bypassing a patient's wishes because the physician believes it is for the patient's own good. With a capable adult it is not acceptable: physicians may recommend and try to persuade, but not coerce, deceive or treat over a refusal. The clearest case of justified paternalism is treating a suicidal patient who is a clear and present danger to themselves. Emergency treatment of a patient who cannot decide is usually framed as implied consent instead, because no known wishes are being overridden.
What is the principle of double effect?
The principle of double effect allows an action with both a good and a bad effect if the act itself is not wrong, only the good effect is intended, the bad effect is not the means to the good effect, and the good outweighs the bad. On exams it justifies titrating opioids or sedatives to relieve pain or breathlessness in a dying patient even though respiratory depression is a foreseen risk. It never permits an act intended to cause death, such as euthanasia.