Caseating granulomas have a necrotic, cheese-like center and point first to infection, above all tuberculosis and endemic fungi; noncaseating granulomas lack central necrosis and suggest sarcoidosis, Crohn disease, berylliosis, foreign material or a drug reaction. The pattern is only a clue: stain and culture for mycobacteria and fungi before calling any granuloma sarcoidosis.
Granulomatous inflammation is a distinct form of chronic inflammation: compact nodules of activated (epithelioid) macrophages, often fused into multinucleated giant cells and ringed by lymphocytes, that form when the body cannot clear a persistent trigger. Most immune granulomas are a Th1-driven, type IV hypersensitivity response: IL-12 drives Th1 cells, IFN-γ activates macrophages and TNF-α holds the granuloma together, which is why TNF inhibitors can reactivate latent TB.
Pathology texts sort granulomas into necrotizing and non-necrotizing; "caseous" describes the cheese-like gross look of one kind of necrotizing granuloma (Shah 2017).
Caseating vs noncaseating granulomas: the comparison table
| Feature | Caseating (necrotizing) | Noncaseating (non-necrotizing) |
|---|---|---|
| Center | Necrosis: white, soft and cheesy to the eye; uniformly eosinophilic under the microscope | No necrosis: tightly packed epithelioid macrophages and giant cells |
| Rim | Epithelioid macrophages, Langhans giant cells, lymphocytes and plasma cells | Often a sparse lymphocyte rim ("naked" granulomas in sarcoidosis) |
| Prototype | Tuberculosis | Sarcoidosis |
| Think next | Nontuberculous mycobacteria; Histoplasma, Coccidioides, Blastomyces, Cryptococcus | Crohn disease, berylliosis, foreign material, drug reactions, hypersensitivity pneumonitis, tuberculoid leprosy |
| Exceptions | Necrosis also in GPA, rheumatoid nodules, cat-scratch disease and syphilitic gummas | TB, fungi and nontuberculous mycobacteria can form non-necrotizing granulomas; nodular sarcoidosis can show necrosis |
| Workup | Acid-fast (Ziehl-Neelsen) and fungal (GMS, PAS) stains, culture, molecular tests | The same stains and cultures plus exposure and drug history; sarcoidosis is a diagnosis of exclusion |
Three more patterns complete the picture (Shah 2017):
- Suppurative granulomas (neutrophil-filled microabscesses in the center): cat-scratch disease (stellate), but also blastomycosis, tularemia, lymphogranuloma venereum and Yersinia.
- Foreign-body granulomas: giant cells around visible material (sutures, talc, fillers) that is often birefringent under polarized light, with no adaptive immune response.
- Sheets of macrophages without true granulomas: lepromatous leprosy (foamy macrophages packed with bacilli), Whipple disease, and some Histoplasma and nontuberculous mycobacterial infections.
GPA adds necrotizing vasculitis to necrotizing granulomatous inflammation; the triad is in GPA (Wegener).
What is granulomatous inflammation?
Shah and colleagues call it "a distinctive form of chronic inflammation" defined by macrophages (histiocytes); StatPearls defines a granuloma as a focal aggregate of immune cells around a persistent stimulus that macrophages cannot remove.
- Epithelioid macrophages: activated macrophages with oval nuclei, abundant pink cytoplasm and interdigitating membranes, so they resemble epithelium.
- Multinucleated giant cells: fused macrophages (Langhans vs foreign-body types below).
- A cuff of lymphocytes with some plasma cells and, as lesions mature, fibrosis; a healed TB focus can calcify.
- Two broad kinds: immune granulomas to persistent antigens, and foreign-body granulomas to inert material.
- Not the same as acute inflammation (neutrophils) or nonspecific chronic inflammation (loose mixtures of macrophages, lymphocytes and plasma cells); well-formed granulomas narrow the differential.
Noncaseating granuloma causes
| Cause | Clinching clue | Confirm or next step |
|---|---|---|
| Sarcoidosis | Age 20-40; bilateral hilar adenopathy, uveitis, erythema nodosum, lupus pernio, hypercalcemia | Biopsy (EBUS-guided node aspiration first) plus exclusion of other causes |
| Chronic beryllium disease | Alloy machining, aerospace, electronics, nuclear or defense work; can start over 30 years after exposure ends | Beryllium lymphocyte proliferation test (BeLPT) on blood or lavage cells |
| Crohn disease | Transmural ileocolitis, skip lesions, fistulas, perianal disease | Endoscopic biopsy; granulomas in up to a third |
| Foreign body | Sutures, injected or aspirated talc, tattoo ink, fillers | Material inside giant cells, often birefringent |
| Drug-induced sarcoid-like reaction | New hilar nodes or skin nodules on PD-1, PD-L1 or CTLA-4 inhibitors, TNF antagonists, interferon or antiretroviral therapy | Biopsy; it can mimic cancer progression |
| Hypersensitivity pneumonitis | Birds, molds or hot tubs; small, poorly formed interstitial granulomas, inflammation around bronchioles | Exposure history; lavage, biopsy |
| Tuberculoid leprosy | Few well-demarcated, hypopigmented, anesthetic patches; thickened nerves | Skin biopsy: compact granulomas, few or no bacilli |
| Giant cell arteritis | Over 50; new headache, jaw claudication, visual symptoms, high ESR | Temporal artery biopsy: granulomatous arteritis, giant cells |
| Sarcoid-like reaction to cancer | Granulomas in a patient with a tumor | Biopsy; PET guides the site but cannot diagnose |
- Noncaseating does not mean noninfectious. Shah's list of infectious causes of non-necrotizing granulomas includes TB, nontuberculous mycobacteria, Coccidioides, Toxoplasma and Schistosoma.
- Checkpoint inhibitors: the pembrolizumab and nivolumab labels list sarcoidosis among immune-mediated reactions reported in under 1% of patients or with other PD-1/PD-L1 blockers; published series report 0.2% to 5%, highest with ipilimumab (Nykaza 2025). In a literature review of 26 published cases (77% melanoma), lesions appeared a median of 6 months into treatment, 96% resolved or improved, and 71% had tumor response, stable disease or remission (Tetzlaff 2018); in a 12-patient series, all but one had a radiographic response (Nykaza 2025). Biopsy before calling progression.
- Crohn disease: absent granulomas do not exclude it; see Crohn vs UC.
Caseating and other necrotizing granulomas
| Cause | Pattern | Clinching clue | Confirm with |
|---|---|---|---|
| Tuberculosis | Caseating; Langhans giant cells | Reactivation: apical-posterior upper lobes, cavities, night sweats, weight loss | AFB smear, culture and NAAT; IGRA or skin test for latent infection |
| Nontuberculous mycobacteria (MAC) | With or without caseation | Cavities in structural lung disease, or nodules in thin women with chest-wall anomalies | Culture or molecular identification |
| Histoplasma | Necrotizing or not | Ohio, Mississippi and Missouri River valleys; bird or bat droppings | Small (2-4 µm) yeasts in macrophages; urine or serum antigen |
| Coccidioides | Necrotizing; organisms in the necrotic center | Southwestern US (San Joaquin Valley fever) | Spherules with endospores; serology |
| Blastomyces | Mixed suppurative and granulomatous (pyogranulomatous) | Ohio and Mississippi valleys, Great Lakes, southeastern US; skin and bone lesions | Large (8-15 µm) thick-walled yeasts with broad-based buds |
| Cat-scratch disease (Bartonella henselae) | Stellate microabscesses: necrotic center, palisading histiocytes | Kitten scratch, papule, then a tender regional node over 1-2 weeks | Serology or PCR; Warthin-Starry silver stain |
| GPA | Poorly formed necrotizing granulomas that begin as neutrophil microabscesses, plus small-vessel vasculitis | Sinusitis, saddle nose, lung nodules, glomerulonephritis | PR3-ANCA (about 75%); biopsy |
| Gumma (tertiary syphilis) | Rubbery nodule with a necrotic center; plasma cells, endarteritis | Skin, liver, bone or testis lesion years after untreated syphilis | Serology; spirochetes rarely seen |
- Necrosis is a clue, not a diagnosis. Mycobacteria are the most common cause of necrotizing granulomas worldwide, but species cannot be identified by morphology; culture or molecular tests are needed (Shah 2017).
- Cat-scratch histology evolves: lymphoid hyperplasia with neutrophils, then irregular granulomas with stellate abscesses, then fibrosis (StatPearls).
- Gummas mimic sarcoid and TB: giant cells and caseating necrosis may be present (StatPearls). Stage review in syphilis stages.
Langhans vs foreign-body giant cells
Both are fused macrophages; they differ in look and setting (Ahmadzadeh 2022).
| Feature | Langhans giant cell | Foreign-body giant cell |
|---|---|---|
| Nuclei | Usually fewer than 20, in a ring or horseshoe at the cell edge | Up to hundreds, scattered through the cytoplasm |
| Shape | Round or oval | Irregular; the largest giant cells, up to 1 mm |
| Setting | First described in TB granulomas (1868); now known in many infectious and noninfectious granulomas | Reactions to inert material such as sutures and implants |
| Fusion signals in the lab | IFN-γ with IL-3 or GM-CSF | IL-4 and IL-13 |
- A giant cell never names the cause. Look for organisms on special stains or for material under polarized light.
- Langhans is not Langerhans. Langerhans cell histiocytosis is a neoplasm of CD1a- and S100-positive myeloid dendritic cells; ATS 2020 lists it in the granuloma differential ("eosinophilic granulomas"), but Shah 2017 classes it as a histiocytic proliferation without true granulomas.
- Asteroid and Schaumann bodies are classic sarcoidosis answers but nonspecific inclusions (Shah 2017).
How a granuloma forms: IL-12, IFN-γ and TNF-α
- A persistent antigen, classically mycobacteria surviving inside macrophages, is presented on MHC class II to CD4+ T cells.
- Activated macrophages secrete IL-12, which directs naive CD4+ T cells to become Th1 cells.
- Th1 cells release IFN-γ and use CD40 ligand to activate macrophages, which become epithelioid cells and fuse into giant cells.
- TNF-α synergizes with IFN-γ, recruits cells and plays a central role in building and maintaining the granuloma.
- The granuloma either contains the organism (latent TB) or its center dies, "probably from a combination of lack of oxygen and the cytotoxic effects of activated macrophages" (Janeway's Immunobiology); the caseous center can erode into an airway and cavitate.
StatPearls classes this as type IVa (delayed-type) hypersensitivity, with sarcoidosis, TB and Crohn disease as examples; the tuberculin skin test reads a type IV response. Compare the four types in type IV hypersensitivity.
When the axis fails:
- Advanced HIV (CD4 count below 200/μL): TB cavitation becomes uncommon and extrapulmonary disease common (StatPearls).
- Inherited IL-12 or IFN-γ pathway defects: severe or disseminated mycobacterial and BCG infection; see IL-12 receptor deficiency.
- Leprosy is the Th1-Th2 spectrum: tuberculoid lesions are rich in IL-2 and IFN-γ messenger RNA, lepromatous lesions in IL-4, IL-5 and IL-10 (Yamamura 1991). Background in Th1 vs Th2.
- The same cytokines explain sarcoid hypercalcemia: macrophage 1α-hydroxylase is switched on mainly by IFN-γ and TNF-α rather than PTH (Endotext).
Anti-TNF drugs: screen for latent TB first
CDC lists TNF antagonists among the factors that raise the risk of TB disease once infected, and the infliximab, adalimumab and etanercept labels carry boxed warnings for serious infections, including TB.
- Before the first dose: assess TB risk and test for latent infection (tuberculin skin test or IGRA); if positive, treat latent TB before starting the drug.
- Skin-test cutoff: on the infliximab label, induration of 5 mm or more counts as positive in this setting, even after BCG vaccination.
- During therapy: monitor for active TB even after a negative test, and retest periodically.
- Atypical disease: TB on these drugs is frequently disseminated or extrapulmonary, and invasive fungal infections (histoplasmosis, coccidioidomycosis, blastomycosis and others) may present disseminated.
- Latent TB regimens: CDC preferentially recommends short rifamycin-based courses: 3HP (once-weekly isoniazid plus rifapentine for 3 months), 4R (daily rifampin for 4 months) or 3HR (daily isoniazid plus rifampin for 3 months), with 6 or 9 months of isoniazid as alternatives. Exclude active TB first.
- The paradox: infliximab treats refractory sarcoidosis (Merck), yet anti-TNF drugs also appear on the ATS list of causes of drug-induced granulomas.
Drug-class rules in one place: infliximab and adalimumab 5-second rule.
Sarcoidosis: ACE, hypercalcemia and bilateral hilar adenopathy
Sarcoidosis most often affects people aged 20-40, is most prevalent in Black Americans and northern Europeans, especially Scandinavians (Merck), and affects women more often than men (Merck; NHLBI). Bilateral hilar adenopathy is the most common imaging finding, and spontaneous remission falls by radiographic stage: 60-80% in stage I (nodes alone), 50-65% in stage II (nodes plus infiltrates), under 30% in stage III (infiltrates alone) and 0% in stage IV (fibrosis) (Merck).
- Three criteria: a compatible picture, non-necrotizing granulomas in tissue and exclusion of other causes; the diagnosis "is never fully secure" (ATS 2020).
- Classic pictures skip the node biopsy: ATS suggests not sampling nodes in Löfgren syndrome (bilateral hilar adenopathy with erythema nodosum and/or periarticular arthritis), lupus pernio or Heerfordt syndrome. Löfgren is self-limited and usually treated with NSAIDs (Merck).
- Erythema nodosum is the wrong biopsy: it contains no granulomas (Merck); see erythema nodosum.
- ACE is supportive, not diagnostic: it also rises in hyperthyroidism, diabetes, Gaucher disease, silicosis, mycobacterial and fungal infection, hypersensitivity pneumonitis and lymphoma (Merck). ATS 2020 lists an elevated ACE only as a "probable" feature, a tier below hypercalcemia or hypercalciuria with abnormal vitamin D metabolism ("highly probable"). Glucocorticoids suppress ACE, so it can track adherence.
- Other clues: a lavage CD4:CD8 ratio above 3.5 supports it (Merck).
- Treatment: many patients need none; glucocorticoids come first, methotrexate is the usual steroid-sparing drug, and infliximab is for refractory disease (Merck).
Why sarcoidosis causes hypercalcemia
- Granuloma macrophages express 1α-hydroxylase and convert 25-hydroxyvitamin D to 1,25-dihydroxyvitamin D (calcitriol) without normal regulation (Merck; ATS 2020).
- The macrophage enzyme responds mainly to IFN-γ and TNF-α rather than PTH, and macrophages lack working CYP24A1, the enzyme that degrades calcitriol (Endotext).
- Calcitriol raises gut calcium absorption, so hypercalciuria can occur with a normal serum calcium (Merck). In the ATS review, 6% had hypercalcemia; in the one cohort that tracked them, 42% of those patients had renal insufficiency (Baughman 2013). PTH-related protein and cytokines may also contribute (ATS 2020).
- Expected labs: low or normal PTH, normal or high 1,25(OH)₂D, normal or low 25(OH)D (ATS 2020), the opposite of primary hyperparathyroidism's high PTH.
- ATS strongly recommends a baseline serum calcium for everyone. Glucocorticoids cut calcitriol production (Merck); hypercalcemia improves or resolves in over 90% of patients on immune suppression (ATS 2020), and moderate to severe hypercalcemia is itself an indication to treat (Merck). Calcium and vitamin D supplements can provoke it.
- Other causes: granulomatous disorders (TB, histoplasmosis, coccidioidomycosis, leprosy, silicosis, berylliosis) and some lymphomas; in leprosy calcitriol is sometimes low, so other mechanisms operate (Merck). More in vitamin D metabolism.
Sarcoidosis vs TB: the chest granuloma face-off
| Feature | Tuberculosis | Sarcoidosis |
|---|---|---|
| Granuloma | Caseating; acid-fast bacilli on stain or culture | Noncaseating; stains and cultures negative |
| Typical imaging | Reactivation: apical-posterior upper-lobe consolidation; cavities in 20-45% of adults | Bilateral hilar adenopathy with or without lung infiltrates |
| Other clues | Night sweats, weight loss, hemoptysis, TB exposure | Uveitis, erythema nodosum, lupus pernio, heart block, parotid swelling |
| Treatment | Multidrug anti-TB therapy | Often none; glucocorticoids for organ-threatening disease |
| Danger | Glucocorticoids for "sarcoid" that is really TB | Skipping stains, cultures and TB testing |
Primary vs reactivation TB (Ghon complex vs apical cavity) is broken down in TB primary vs reactivation.
USMLE traps
| Trap | What is actually true |
|---|---|
| "Caseating means TB" | Mycobacteria lead, but fungi, cat-scratch disease, GPA and gummas also necrotize; culture or PCR names the organism |
| "Noncaseating means sarcoidosis" | TB, fungi, Toxoplasma and Schistosoma can form non-necrotizing granulomas; sarcoidosis is a diagnosis of exclusion |
| "Langhans giant cells prove TB" | Seen in many infectious and noninfectious granulomas; Langhans is not Langerhans |
| "Asteroid or Schaumann bodies prove sarcoidosis" | Nonspecific inclusions |
| "A high ACE confirms sarcoidosis" | Nonspecific; only a "probable" feature in ATS 2020 |
| "Negative IGRA, so not TB" | Anergy can cause false negatives in active TB and sarcoidosis (ATS 2020) |
| "No granulomas, so not Crohn" | Granulomas appear in up to a third of patients |
| "Berylliosis looks different from sarcoidosis" | Histologically indistinguishable; ask about work and order a BeLPT |
| "New hilar nodes on immunotherapy mean progression" | Checkpoint-inhibitor sarcoid-like reactions mimic it; biopsy |
| "Chronic granulomatous disease is a granuloma pattern" | It is an NADPH oxidase killing defect; granulomas are a by-product |
Chronic granulomatous disease in brief: phagocyte NADPH oxidase cannot make reactive oxygen species (X-linked CYBB in about two-thirds), so phagocytes fail to kill a narrow set of microbes, in North America mainly Staphylococcus aureus, Burkholderia cepacia complex, Serratia marcescens, Nocardia and Aspergillus, the "catalase-positive" organisms of classic teaching. Dysregulated granulomas can obstruct the urinary tract and gastric outlet. Diagnosis starts with the DHR test; prophylaxis is daily antibacterial and antifungal drugs, often with IFN-γ (GeneReviews 2026). See chronic granulomatous disease.
Practice vignettes
Vignette 1: the shelter volunteer. A 52-year-old man who volunteers nightly at a homeless shelter has 3 months of cough, night sweats, low-grade fevers and a 6-kg weight loss. CT shows a cavity in the apical segment of the right upper lobe. Biopsy shows nodules of epithelioid macrophages and multinucleated giant cells rimmed by lymphocytes, each with an amorphous, eosinophilic, acellular center; a Ziehl-Neelsen stain shows red rods. Which term best describes the lesion?
A. Abscess with liquefactive necrosis. B. Caseating granulomatous inflammation. C. Noncaseating granulomatous inflammation. D. Nonspecific chronic inflammation. E. Acute inflammation.
Answer: B. Epithelioid macrophages and giant cells make a granuloma, the necrotic center is caseous, and acid-fast rods in an apical cavity mean reactivation TB. A: an abscess is liquefactive necrosis packed with neutrophils, usually after aspiration of oral anaerobes into the posterior upper or superior lower segments. C: these granulomas are necrotic. D: nonspecific chronic inflammation lacks organized epithelioid nodules. E: acute inflammation is neutrophilic and early.
Vignette 2: the high calcium. A 34-year-old woman has a dry cough and painful, blurred eyes. Chest x-ray shows bilateral hilar adenopathy. Calcium is 12.1 mg/dL with suppressed PTH, low-normal 25-hydroxyvitamin D and high 1,25-dihydroxyvitamin D. What explains the hypercalcemia?
A. PTH-related protein from lung cancer. B. Macrophage 1α-hydroxylase activity driven by IFN-γ. C. Parathyroid adenoma. D. Vitamin D supplement toxicity. E. Osteolytic metastases.
Answer: B. Granuloma macrophages make calcitriol outside PTH control, and uveitis plus hilar nodes suggests sarcoidosis. A: calcitriol is low in most solid tumors. C: PTH would be high or high-normal. D: supplement toxicity raises 25-hydroxyvitamin D. E: metastases resorb bone directly rather than raising calcitriol. Next comes tissue diagnosis with stains and cultures; moderate hypercalcemia warrants glucocorticoids.
Vignette 3: the machinist. A 47-year-old man who has machined beryllium-copper alloy for an aerospace supplier for 15 years has a year of exertional dyspnea. CT shows hilar adenopathy and upper-zone nodules; biopsy shows non-necrotizing granulomas, and acid-fast and fungal stains and cultures are negative. Which test best separates his disease from sarcoidosis?
A. Serum ACE. B. Beryllium lymphocyte proliferation test. C. Serum calcium. D. Interferon-γ release assay. E. Repeat biopsy.
Answer: B. Chronic beryllium disease is a cell-mediated hypersensitivity whose granulomas are histologically indistinguishable from sarcoidosis; the BeLPT detects beryllium sensitization and is recommended in every suspected case (Merck). A: ACE is nonspecific. C: berylliosis is itself a granulomatous cause of hypercalcemia. D: an IGRA detects TB infection. E: more tissue shows the same granulomas. Remove him from exposure.
Vignette 4: the restaging scan. A 61-year-old woman has received pembrolizumab for metastatic melanoma for 4 months. PET-CT shows shrinking liver metastases but new, symmetric hilar and mediastinal nodes. EBUS aspiration shows non-necrotizing granulomas, no tumor cells, and negative acid-fast and fungal stains. What is the most likely explanation?
A. Melanoma progression. B. Drug-induced sarcoid-like reaction. C. Reactivation TB. D. Histoplasmosis. E. Lymphoma.
Answer: B. PD-1 inhibitors can cause sarcoid-like granulomas that mimic progression, often while the tumor responds. A: the nodes hold no tumor and the liver lesions are shrinking. C: TB granulomas usually caseate and grow acid-fast bacilli. D: histoplasmosis would show yeasts on fungal stain, culture or antigen testing. E: lymphoma shows a clonal cell population. More practice is on the Pathology hub.
Key takeaways
- Caseating (necrotizing) → infection first: TB, nontuberculous mycobacteria and endemic fungi; cat-scratch disease (stellate, suppurative), GPA (with vasculitis) and gummas also necrotize.
- Noncaseating → sarcoidosis, Crohn disease, berylliosis, foreign bodies, drug reactions (including checkpoint inhibitors), hypersensitivity pneumonitis, tuberculoid leprosy, but stain and culture first.
- Mechanism: IL-12 → Th1 → IFN-γ → epithelioid and giant cells; TNF-α maintains the granuloma (type IV hypersensitivity).
- Before any TNF inhibitor: test for latent TB (skin test of 5 mm or more, or IGRA) and treat it first, preferably with 3HP, 4R or 3HR.
- Sarcoid hypercalcemia: macrophage 1α-hydroxylase → high calcitriol, low PTH; check calcium in everyone; glucocorticoids usually correct it.
- Chronic granulomatous disease is an NADPH oxidase killing defect, not a granuloma pattern.
Sources
- Granuloma — StatPearls, NCBI Bookshelf (2022)
- Histopathologic review of granulomatous inflammation — J Clin Tuberc Other Mycobact Dis (2017)
- Multinucleated Giant Cells: Current Insights — Front Cell Dev Biol (2022)
- Macrophage activation by armed CD4 TH1 cells — Immunobiology, 5th ed. (2001)
- Type IV Hypersensitivity Reaction — StatPearls (2025)
- Pathogenesis — Tuberculosis in Adults and Children, Springer (2015)
- Tuberculosis Overview — StatPearls (2024)
- Cell Liquefactive Necrosis — StatPearls (2025)
- Diagnosis and Detection of Sarcoidosis: ATS Clinical Practice Guideline — Am J Respir Crit Care Med (2020)
- Sarcoidosis — Merck Manual Professional (2025)
- Sarcoidosis: Causes and Risk Factors — NHLBI (2022)
- Calcium and vitamin D metabolism in sarcoidosis — Sarcoidosis Vasc Diffuse Lung Dis (2013)
- Hypercalcemia — Merck Manual Professional (2025)
- Vitamin D: Production, Metabolism, and Mechanism of Action — Endotext (2025)
- Beryllium Disease — Merck Manual Professional (2026)
- Crohn Disease — StatPearls (2025)
- REMICADE (infliximab) label — DailyMed (2025)
- HUMIRA (adalimumab) label — DailyMed (2025)
- ENBREL (etanercept) label — DailyMed (2026)
- Treatment for Latent Tuberculosis Infection — CDC (2025)
- Clinical Overview of Tuberculosis — CDC (2025)
- KEYTRUDA (pembrolizumab) label — DailyMed (2026)
- OPDIVO (nivolumab) label — DailyMed (2026)
- Granulomatous/sarcoid-like lesions associated with checkpoint inhibitors — J Immunother Cancer (2018)
- Sarcoid-like reactions in patients treated with checkpoint inhibitors — Oncologist (2025)
- Leprosy — StatPearls (2026)
- Cytokine profiles in leprosy lesions — Science (1991)
- Histoplasmosis — StatPearls (2026)
- Coccidioidomycosis — StatPearls (2023)
- Blastomycosis — StatPearls (2026)
- Cat Scratch Disease — StatPearls (2025)
- Granulomatosis With Polyangiitis — StatPearls (2024)
- Syphilis — StatPearls (2024)
- Giant Cell Arteritis — StatPearls (2024)
- Chronic Granulomatous Disease — GeneReviews (2026)
- Lung Abscess — StatPearls (2024)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
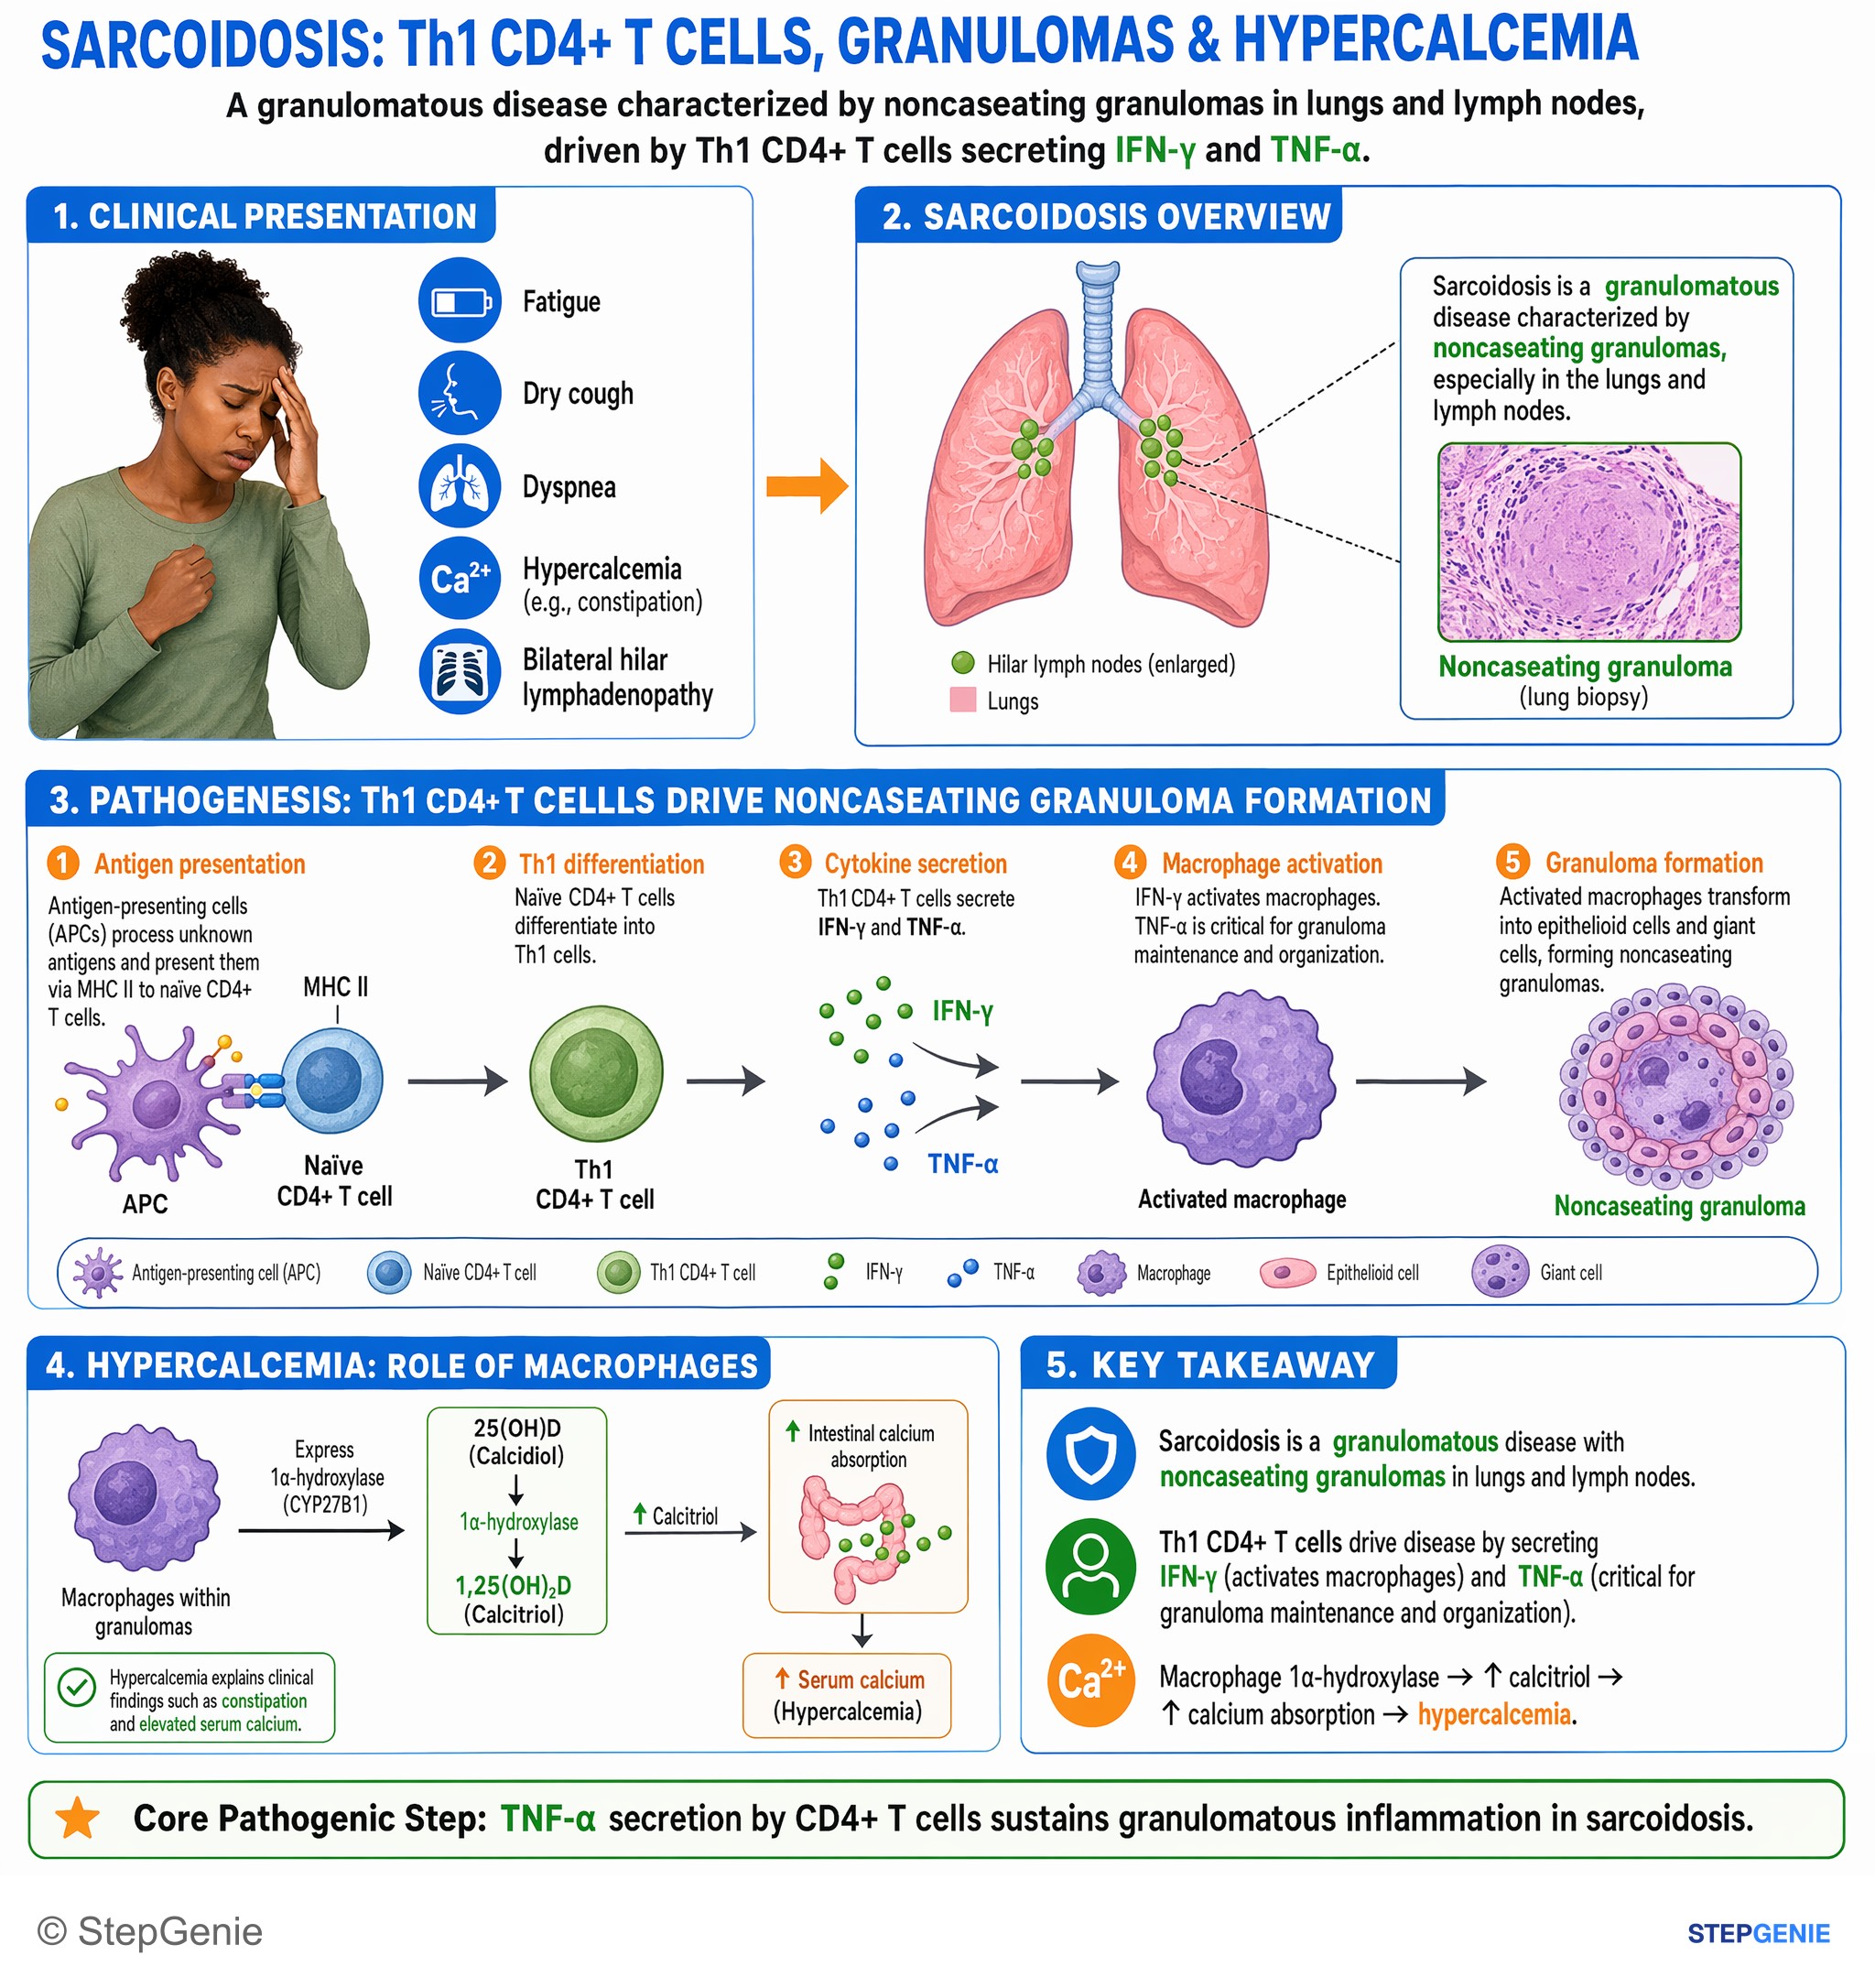
Sarcoidosis: noncaseating granulomas driven by Th1 CD4+ T cells secreting IFN-γ and TNF-α, causing hypercalcemia and bilateral hilar…
USMLE Step 1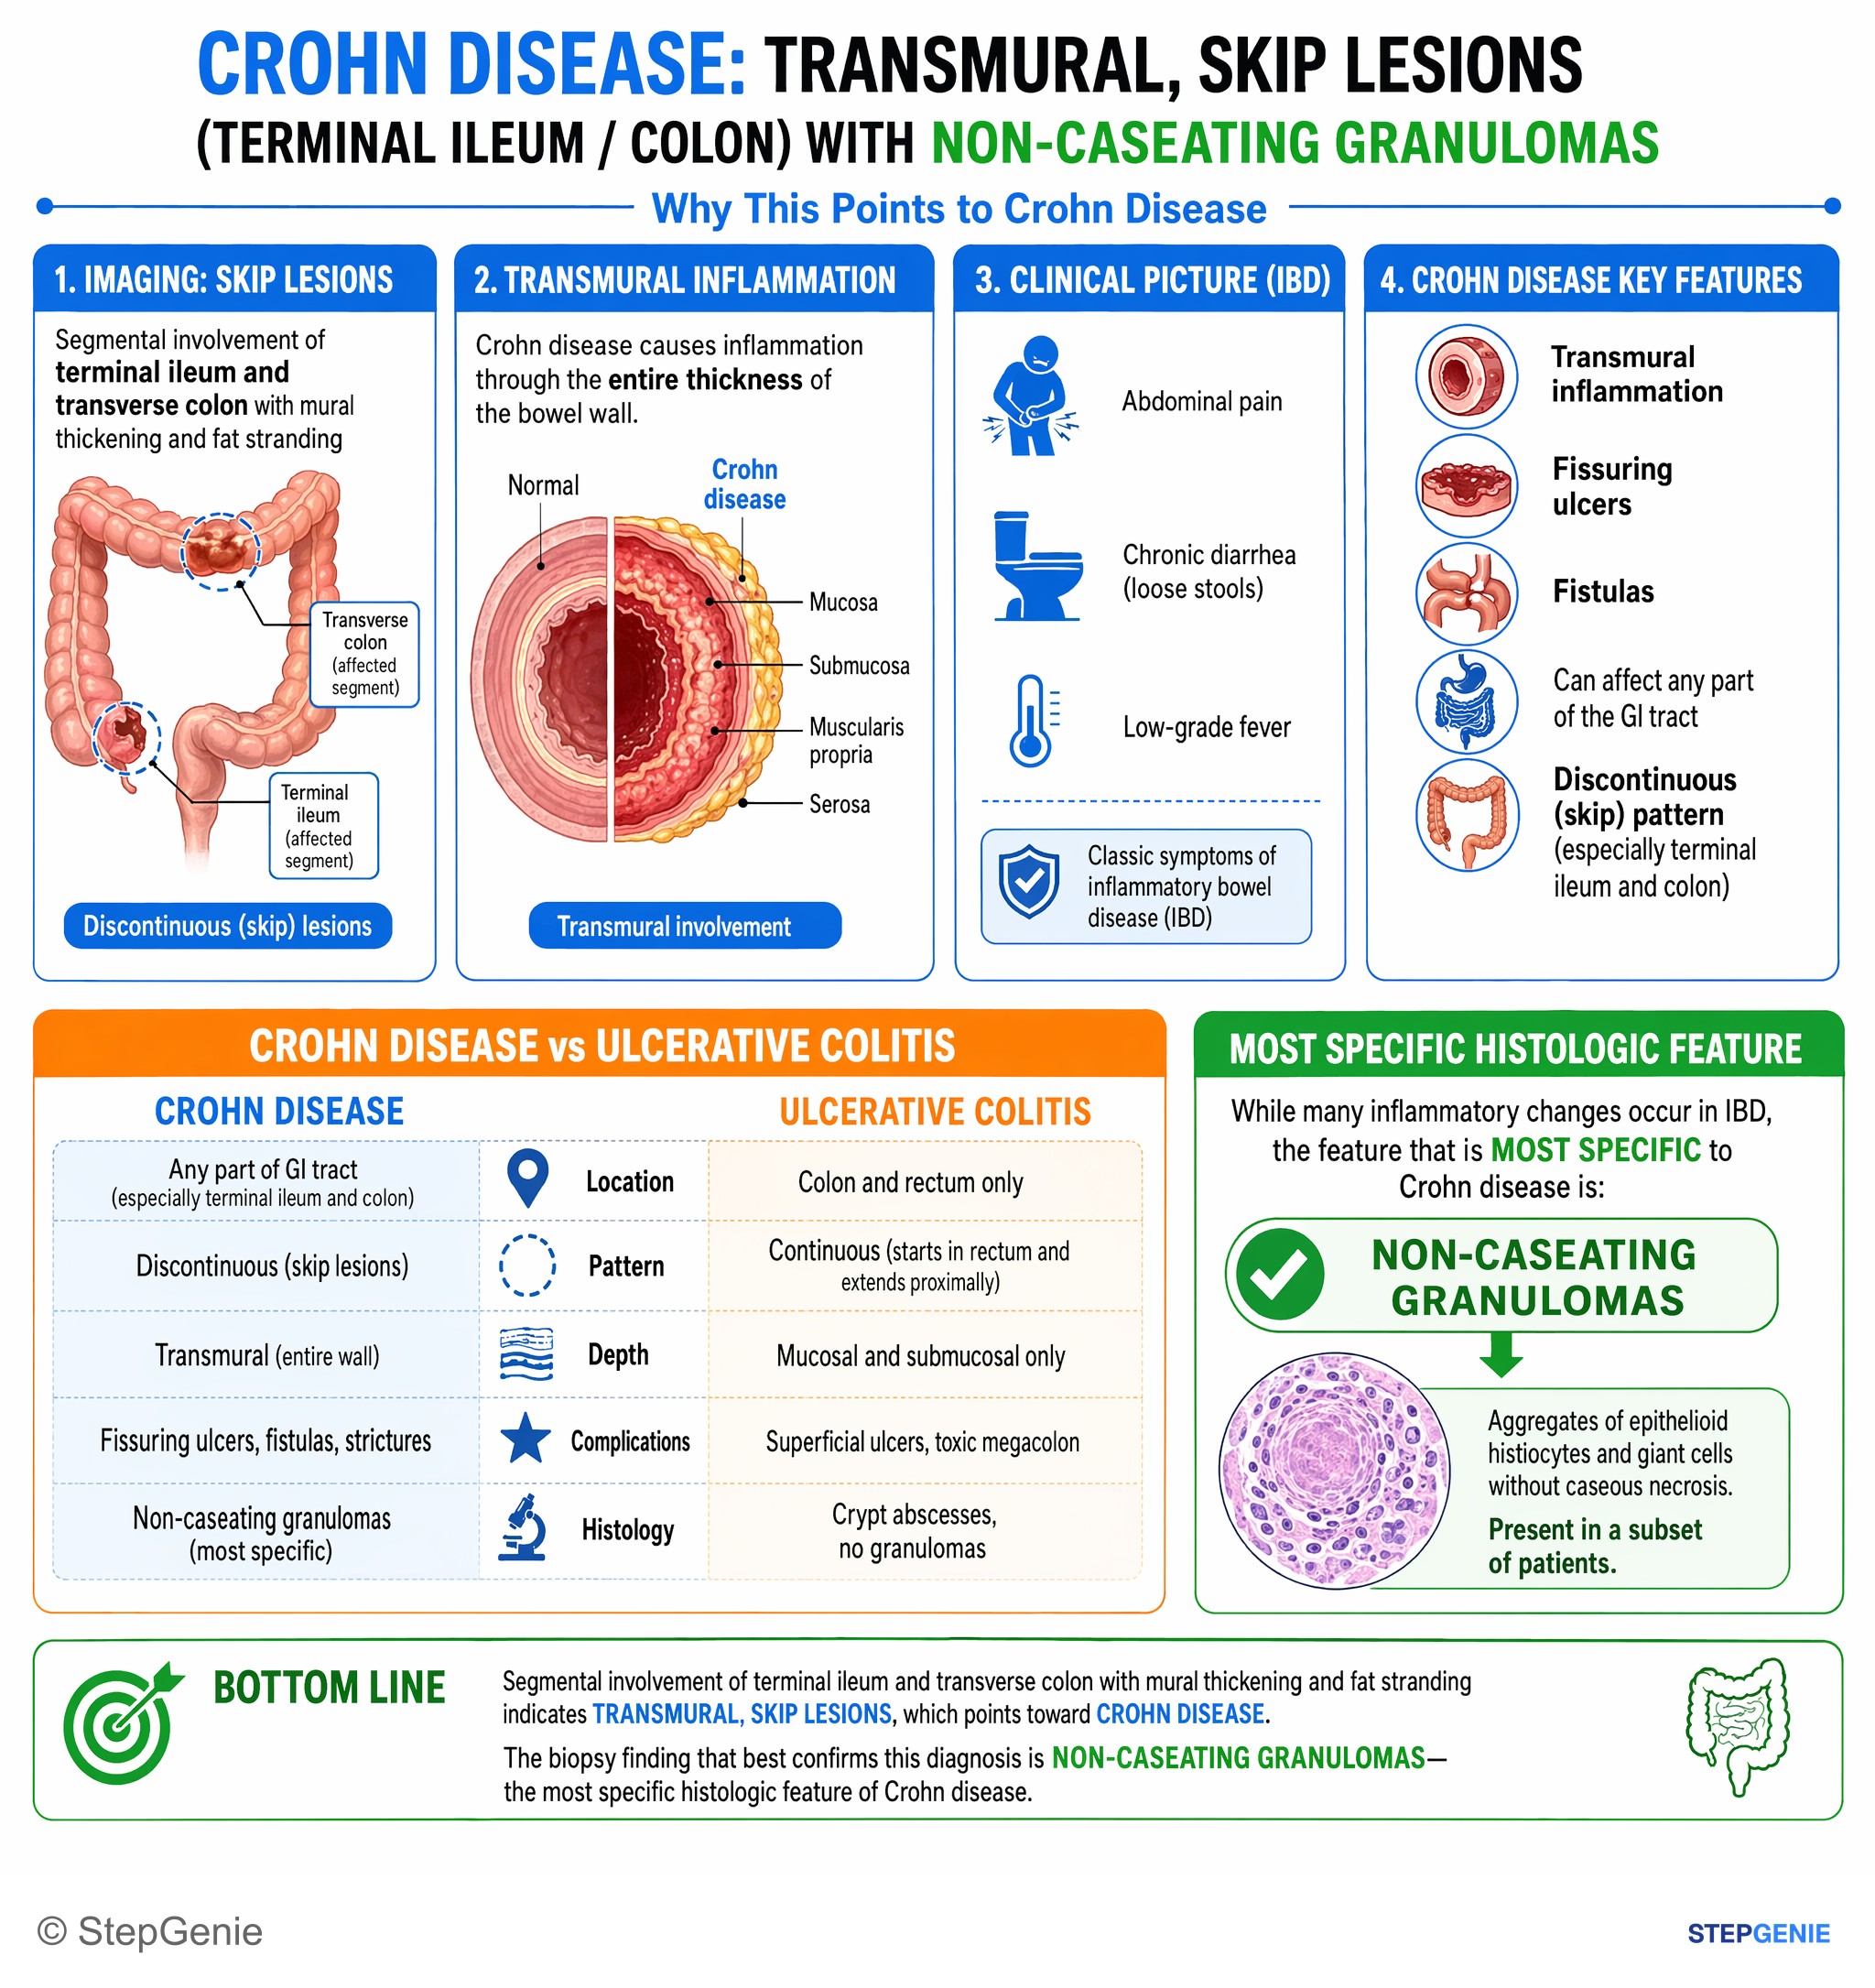
Crohn disease: transmural, skip lesions (terminal ileum/colon) with non-caseating granulomas—most specific histologic feature.
USMLE Step 1Frequently Asked Questions
What is the difference between caseating and noncaseating granulomas?
Caseating granulomas have central necrosis that looks white, soft and cheese-like to the naked eye and uniformly eosinophilic under the microscope. They point first to infection, especially tuberculosis and endemic fungi such as Histoplasma and Coccidioides. Noncaseating granulomas have no central necrosis and suggest sarcoidosis, Crohn disease, berylliosis, foreign material or a drug reaction. The pattern is only a clue: tuberculosis and fungi can also form noncaseating granulomas, so stains and cultures are still needed.
What is granulomatous inflammation?
Granulomatous inflammation is a distinctive pattern of chronic inflammation in which activated macrophages, called epithelioid cells, cluster into compact nodules, often with multinucleated giant cells formed by fused macrophages and a surrounding cuff of lymphocytes. It forms when the immune system cannot eliminate a persistent trigger, such as mycobacteria, fungi, inert foreign material or the unknown antigen of sarcoidosis. Granulomas are described as caseating (necrotizing), noncaseating, suppurative or foreign-body type.
What causes noncaseating granulomas?
Sarcoidosis is the prototype, but noncaseating granulomas also occur in Crohn disease, chronic beryllium disease, hypersensitivity pneumonitis, giant cell arteritis, tuberculoid leprosy and reactions to foreign material such as sutures or injected talc. Drugs can cause sarcoid-like granulomas too, including checkpoint inhibitors such as pembrolizumab and nivolumab, TNF antagonists and interferon. Tuberculosis, nontuberculous mycobacteria and some fungi can also form noncaseating granulomas, so infection must be excluded before sarcoidosis is diagnosed.
Which cells and cytokines form a granuloma?
Macrophages that cannot clear a persistent antigen present it to CD4+ T cells and secrete IL-12, which drives those T cells to become Th1 cells. Th1 cells release interferon-gamma, which activates macrophages into epithelioid cells that can fuse into multinucleated giant cells. Tumor necrosis factor-alpha works with interferon-gamma to recruit cells and maintain the granuloma. This sequence is a type IV, delayed-type hypersensitivity response, the kind of cell-mediated reaction the tuberculin skin test measures.
Why do patients need latent TB screening before TNF inhibitors?
TNF-alpha is central to building and maintaining the granulomas that wall off Mycobacterium tuberculosis, so drugs such as infliximab, adalimumab and etanercept can let latent infection reactivate, often as disseminated or extrapulmonary disease. Patients are tested with a tuberculin skin test or interferon-gamma release assay first, with 5 mm of induration counted as positive on the infliximab label, and latent infection is treated before the drug starts, preferably with 3HP, 4R or 3HR.
Why does sarcoidosis cause hypercalcemia?
Macrophages in sarcoid granulomas express 1-alpha-hydroxylase and convert 25-hydroxyvitamin D into 1,25-dihydroxyvitamin D (calcitriol) without normal regulation, because the enzyme responds to interferon-gamma and TNF-alpha rather than PTH. Calcitriol raises intestinal calcium absorption, causing hypercalciuria and sometimes hypercalcemia with suppressed PTH. Guidelines recommend a baseline serum calcium in every patient, and glucocorticoids lower calcitriol production. Tuberculosis, histoplasmosis, berylliosis and other granulomatous diseases can also cause hypercalcemia.