Drug–drug interactions are one of those “looks easy, misses hard” Step topics: the stem gives you two meds, you spot a famous enzyme, and you pick the obvious answer… then the explanation says the real issue was protein binding, gastric pH, or a prodrug. The fastest way to level up is to treat every answer choice like it’s teaching you a mechanism.
Tag: Pharmacology > General Principles
The Vignette (Q-bank style)
A 63-year-old man with atrial fibrillation and chronic heart failure comes to clinic for follow-up. He takes warfarin and recently started amiodarone for rhythm control. One week later, he reports easy bruising and bleeding when brushing his teeth. Vitals are stable. Exam shows scattered ecchymoses. Labs show:
- PT prolonged
- INR: 6.2 (previously 2.3)
- Platelets normal
Which mechanism best explains this change?
Answer choices
A. Amiodarone induces CYP2C9, increasing warfarin clearance
B. Amiodarone inhibits CYP2C9, decreasing warfarin clearance
C. Amiodarone displaces warfarin from albumin, increasing free warfarin long-term
D. Amiodarone increases intestinal vitamin K absorption
E. Amiodarone decreases warfarin absorption via increased gastric pH
Step Strategy: What are they really testing?
This stem is screaming: warfarin + new drug + INR spikes = interaction increasing warfarin effect. Your job is to identify how.
Two big Step heuristics:
- Warfarin is a CYP substrate (especially CYP2C9 for the more potent S-warfarin).
- Amiodarone is a CYP inhibitor (and a notorious interaction machine).
Correct Answer: B. Amiodarone inhibits CYP2C9, decreasing warfarin clearance
Why it’s correct
- Warfarin is metabolized by hepatic CYP enzymes (high yield: CYP2C9).
- Amiodarone inhibits CYP450 (including CYP2C9), which:
- decreases warfarin metabolism
- raises warfarin levels
- increases PT/INR
- increases bleeding risk
Clinical pearl (USMLE-friendly)
When you start an inhibitor, toxicity typically appears after:
- Days to weeks, depending on drug half-life and time to steady state
- Amiodarone is especially tricky because it has a very long half-life (effects can persist).
Management language that shows up in questions:
- “Reduce warfarin dose and monitor INR closely.”
- For significant bleeding: vitamin K ± PCC/FFP depending on severity (Step 2 loves this).
Now, why every distractor is tempting (and how to eliminate it)
A. Amiodarone induces CYP2C9, increasing warfarin clearance — Wrong
This would cause:
- Lower warfarin levels
- Decreased INR
- Increased clotting risk
High-yield inducer list (classic Step memorization):
- Rifampin
- Carbamazepine
- Phenytoin
- Phenobarbital
- St. John’s wort
- (Also chronic alcohol use induces CYP2E1)
If the question had warfarin + rifampin, the INR would drop, not spike.
C. Amiodarone displaces warfarin from albumin, increasing free warfarin long-term — Wrong (as written)
This choice is sneaky because protein binding displacement is real, but the time-course and durability matter.
Key principle:
- Displacement from albumin increases the free fraction of drug transiently
- The body usually compensates as:
- more free drug is metabolized/cleared
- a new equilibrium forms
- So displacement alone rarely explains a sustained INR of 6+ unless combined with decreased clearance
Test-taking tip:
When an answer choice says “protein binding displacement → long-term effect” with no clearance change, be suspicious.
Classic displacement examples they like to mention:
- Warfarin displaced by some NSAIDs/sulfonamides (but clinically, CYP effects often dominate the big INR changes)
- Valproate can increase free phenytoin (free level matters)
D. Amiodarone increases intestinal vitamin K absorption — Wrong
More vitamin K would:
- counteract warfarin
- decrease INR
Vitamin K is required for -carboxylation of:
- II, VII, IX, X
- Protein C and S
So increased vitamin K → more functional clotting factors → less anticoagulation.
If they wanted vitamin K decreased, you’d expect something like:
- Broad-spectrum antibiotics → decrease gut flora → ↓ vitamin K production → increase warfarin effect → ↑ INR
That’s a classic Step interaction.
E. Amiodarone decreases warfarin absorption via increased gastric pH — Wrong
Raising gastric pH is a common interaction mechanism, but it’s famous for drugs that require acidic environments for absorption.
High-yield “needs acid” examples:
- Azole antifungals (e.g., ketoconazole, itraconazole—absorption can drop with PPIs)
- Iron
- Some forms of calcium carbonate, etc.
Warfarin isn’t the poster child for pH-dependent absorption on Step. And decreased absorption would lower INR, not raise it.
High-Yield Interaction Framework (what Step wants you to recognize)
1) CYP Inhibition vs Induction (most tested)
| Mechanism | Onset | Effect on substrate drug | Common examples |
|---|---|---|---|
| CYP inhibition | Fast (days) | Increased drug levels → toxicity | Amiodarone, macrolides, azoles, cimetidine, ritonavir, isoniazid, grapefruit juice |
| CYP induction | Slow (1–2 weeks) | Decreased drug levels → therapeutic failure | Rifampin, carbamazepine, phenytoin, phenobarbital, St. John’s wort |
Mnemonic you may already use (still works):
Inhibitors: “SICKFACES.COM” (varies by resource) — what matters is recognizing the big hitters: amiodarone, azoles, macrolides, ritonavir, cimetidine, grapefruit.
2) Warfarin interactions you should be able to predict quickly
INR goes UP (bleeding risk):
- CYP inhibitors (amiodarone, azoles, macrolides)
- Decreased vitamin K (broad-spectrum antibiotics, malnutrition)
- Liver dysfunction (less clotting factor synthesis)
INR goes DOWN (clotting risk):
- CYP inducers (rifampin, carbamazepine, phenytoin)
- Increased vitamin K intake (diet changes, supplements)
3) Don’t forget pharmacodynamics (same pathway, different mechanism)
Sometimes the interaction isn’t PK (CYP/absorption) at all—it’s additive physiological effect:
- Warfarin + aspirin/NSAIDs
- INR may not skyrocket, but bleeding risk increases via platelet inhibition and GI mucosal damage.
- Nitrates + PDE-5 inhibitors (sildenafil)
- Profound hypotension (synergistic vasodilation via cGMP).
- ACE inhibitor + spironolactone
- Hyperkalemia risk (Step 2 loves the lab trend).
If the question emphasizes a clinical effect without an INR/level change, consider pharmacodynamics.
Quick “One-Liner” Takeaways (burn these in)
- Amiodarone inhibits CYP2C9 → warfarin levels rise → INR rises.
- Inducers lower INR; inhibitors raise INR.
- Protein binding displacement is often transient unless clearance also changes.
- Antibiotics can raise INR by reducing gut vitamin K.
- Always ask: is this PK (CYP/absorption/protein binding) or PD (additive effects)?
Mini-Drill: How this vignette could be rewritten (and what would change)
| New stem twist | Likely correct concept |
|---|---|
| Warfarin + rifampin, INR falls | CYP induction → increased clearance |
| Warfarin + TMP-SMX, INR rises | CYP inhibition ± displacement (net ↑ warfarin effect) |
| Warfarin + broad-spectrum antibiotics, INR rises | ↓ gut flora → ↓ vitamin K |
| Warfarin + aspirin, more bleeding but INR ~same | Pharmacodynamic increased bleeding risk |
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
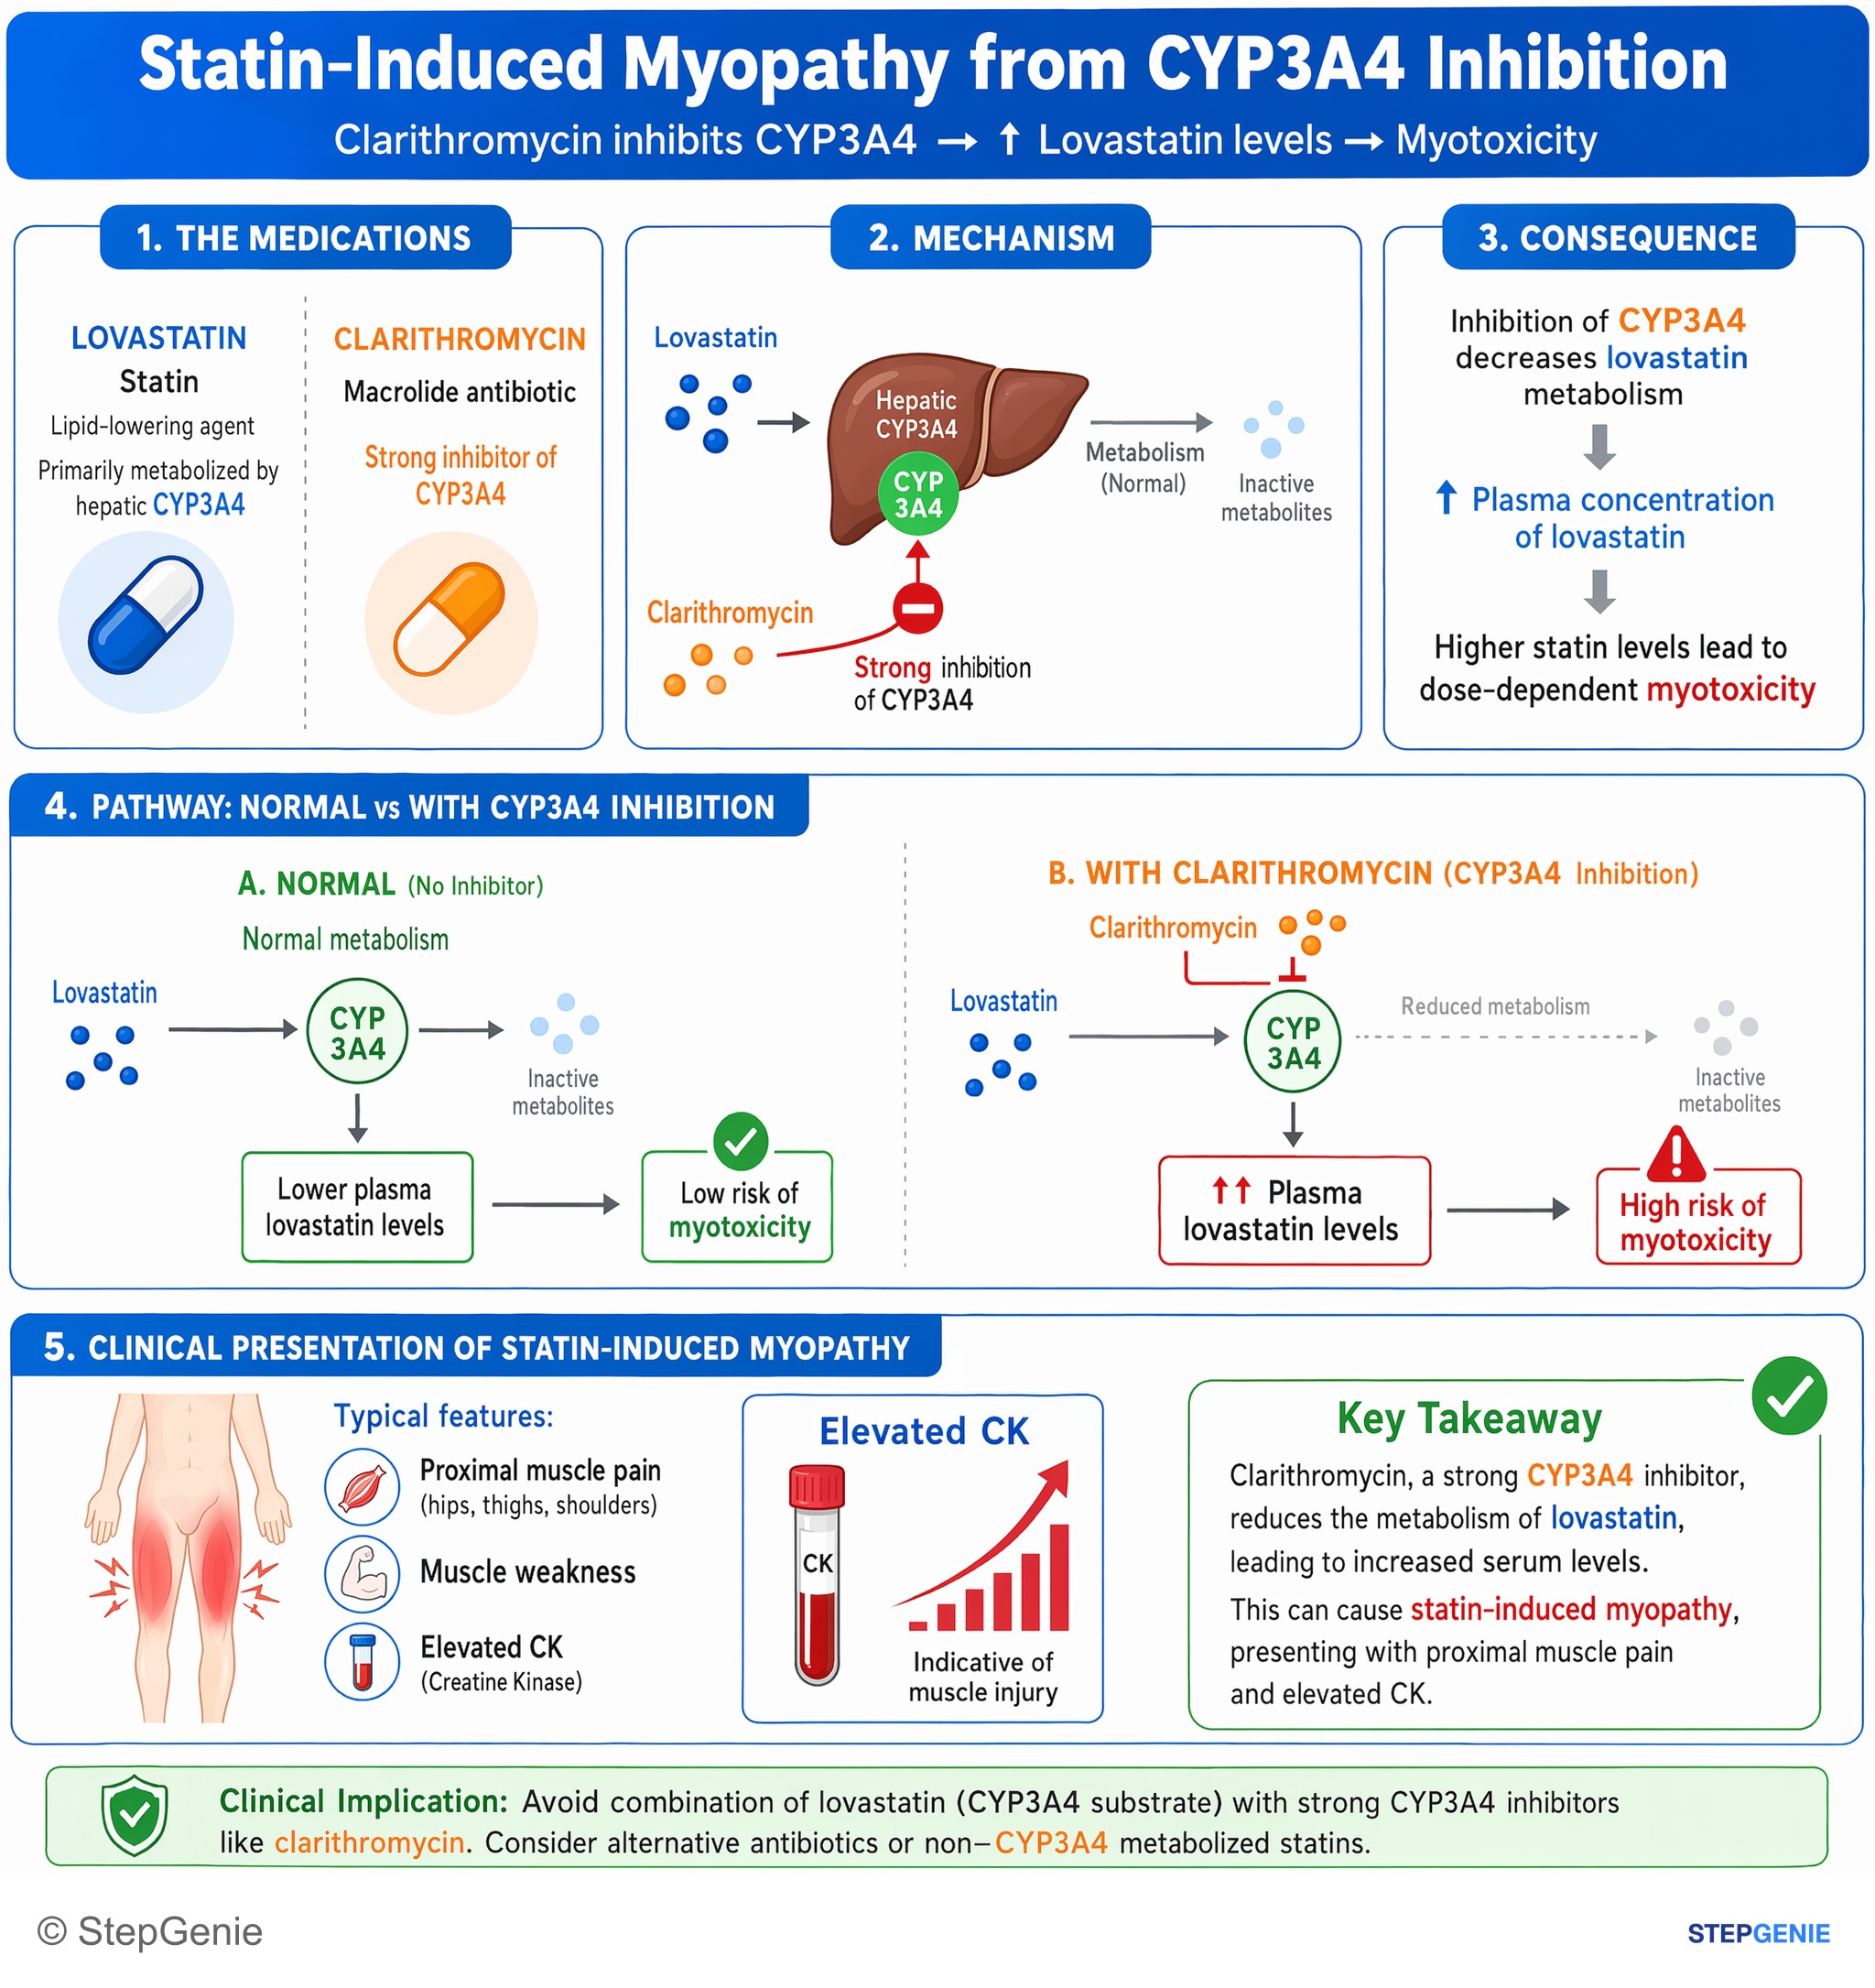
Statin-induced myopathy due to clarithromycin inhibition of CYP3A4, increasing serum lovastatin and causing proximal muscle pain and…
USMLE Step 1Frequently Asked Questions
Why does amiodarone make the INR go up in a patient taking warfarin?
Amiodarone raises the INR by inhibiting CYP2C9 and decreasing warfarin clearance. Warfarin, especially the more potent S-warfarin, is metabolized by hepatic CYP enzymes, and amiodarone is a well-known CYP inhibitor. That slows warfarin metabolism, increases warfarin levels, prolongs PT/INR, and increases bleeding risk, which fits bruising and mucosal bleeding after starting the new drug.
How do you tell CYP inhibition from CYP induction in a warfarin drug-interaction question?
Use the direction of the INR change and the time course. CYP inhibition causes increased substrate drug levels and toxicity, often over days, so warfarin questions show a rising INR and bleeding. CYP induction causes decreased substrate drug levels and therapeutic failure, usually over 1 to 2 weeks, so warfarin questions show a falling INR and increased clotting risk. Amiodarone is an inhibitor, not an inducer.
Why is protein-binding displacement a weak explanation for a sustained high INR with warfarin?
Protein-binding displacement usually causes only a transient increase in free drug, not a durable long-term effect by itself. When a drug is displaced from albumin, the extra free fraction is typically metabolized or cleared until a new equilibrium forms. That is why an answer choice claiming protein-binding displacement alone explains a sustained INR above 6 should make you suspicious unless decreased clearance is also present.
Why would increased vitamin K absorption lower the INR instead of raising it?
Increased vitamin K would counteract warfarin and lower the INR. Vitamin K is required for gamma-carboxylation of clotting factors II, VII, IX, and X, as well as proteins C and S, so more vitamin K means more functional clotting factors and less anticoagulation. In contrast, decreased vitamin K, such as after broad-spectrum antibiotics reduce gut flora, increases warfarin effect and raises the INR.
What is the usual management when warfarin toxicity happens after starting amiodarone?
The usual management is to reduce the warfarin dose and monitor the INR closely. This interaction reflects increased warfarin effect from reduced clearance, and amiodarone can be especially tricky because it has a very long half-life, so effects can persist. If bleeding is significant, vitamin K may be given, with PCC or FFP depending on severity.