An agonist binds a receptor and activates it, an antagonist binds without activating it and blocks agonists, a partial agonist produces only a submaximal response even when every receptor is occupied, and an inverse agonist lowers a receptor's baseline (constitutive) activity. On a dose-response curve, efficacy (Emax) is how high the curve rises and potency (EC50) is where it sits on the dose axis. A competitive antagonist shifts the agonist curve to the right with the same Emax, while a noncompetitive or irreversible antagonist lowers Emax. Next to a full agonist, a partial agonist behaves as an antagonist, which is why buprenorphine can precipitate opioid withdrawal.
The mnemonic: All, Part, Absent, Reverse
Every drug in this family binds the receptor; that is affinity, usually expressed as the KD, the concentration that occupies half the receptors (the lower the KD, the tighter the binding). What separates the four types is intrinsic efficacy, what happens after binding:
| Drug type | Mnemonic | Intrinsic efficacy | Given alone, it... | Given with a full agonist, it... | Examples |
|---|---|---|---|---|---|
| Full agonist | All the action | Maximal | Produces the maximal response the system can give | Adds to it | Morphine, heroin (μ-opioid receptor) |
| Partial agonist | Part of the action | Low, between zero and full | Gives a submaximal response, even at full occupancy | Displaces it and lowers the response | Buprenorphine (μ), varenicline (α4β2 nicotinic), aripiprazole (D2) |
| Antagonist | Absent action | Zero | Does nothing on its own | Blocks it | Naloxone (opioid receptors), flumazenil (benzodiazepine site of the GABA-A receptor) |
| Inverse agonist | Action in Reverse | Negative | Pushes activity below baseline, if the receptor is constitutively active | Blocks it | Histamine H2 blockers such as cimetidine; most atypical antipsychotics at serotonin 5-HT2 receptors |
Picture it as a car. Affinity is getting into the driver's seat; efficacy is how hard you press the gas. A full agonist floors it, a partial agonist presses halfway, an antagonist sits in the seat with its foot off the pedal so no one else can drive, and an inverse agonist puts the car in reverse.
Potency vs efficacy: position vs elevation
- Potency = position. The EC50 is the concentration that produces half of the maximal effect. A curve further to the left means a more potent drug, one that needs less drug for the same effect. Potency reflects affinity and efficacy together, plus how many spare receptors the tissue has.
- Efficacy = elevation. Emax is the largest response the drug can produce, its ceiling.
- They vary independently. Two drugs can share the same Emax while their EC50 values differ tenfold, and a high-affinity partial agonist can sit to the left of a full agonist yet plateau lower.
"More potent" means a smaller dose does the job, not that the drug can do more. When a question asks which drug achieves the greater maximal effect, compare plateaus, not positions. For more graph practice, see dose-response curve tips.
How antagonists change the agonist's curve
| Antagonist | How it binds | Overcome by more agonist? | Agonist EC50 | Agonist Emax | Example |
|---|---|---|---|---|---|
| Competitive (reversible) | Same site as the agonist, short-lasting bonds | Yes (surmountable) | ↑, curve shifts right | Unchanged | Naloxone, flumazenil |
| Noncompetitive | Agonist and antagonist can bind at the same time; the antagonist prevents the response | No | Classically unchanged | ↓ | — |
| Irreversible | Stable, often covalent, bond to the receptor | No | May rise first where spare receptors exist | ↓ | Phenoxybenzamine (α1 and α2) |
The classic exam picture: competitive = the agonist curve slides right with the same plateau (the agonist loses potency, not efficacy); noncompetitive = the plateau drops (efficacy falls). Real curves are messier. The IUPHAR teaching resource notes that noncompetitive antagonists can shift the curve right as well as lowering Emax. And in tissues with spare receptors, an irreversible antagonist can shift the curve right before the maximum falls, because the agonist can still reach Emax with the receptors that remain.
In words: more agonist overcomes a reversible competitive antagonist but not a noncompetitive or irreversible one. Phenoxybenzamine, an irreversible, nonselective α blocker, is the classic example and the classic preoperative drug for pheochromocytoma.
Partial agonists in the clinic
- Buprenorphine is a partial μ-opioid agonist with high affinity and slow dissociation. It has a ceiling on respiratory depression, but given to someone whose receptors are still occupied by heroin or methadone, it displaces the full agonist and precipitates withdrawal. Induction therefore waits for withdrawal signs, usually 12–18 hours after a short-acting opioid and 24–48 hours after methadone. The naloxone in buprenorphine-naloxone is there to deter injection.
- Varenicline is a partial agonist at α4β2 nicotinic receptors: enough activation to ease craving and withdrawal, while it blocks nicotine from those receptors and from triggering mesolimbic dopamine reward.
- Aripiprazole is a partial agonist at D2 and 5-HT1A receptors. It acts as a functional antagonist where dopamine is high (the mesolimbic pathway) while largely sparing pathways with normal dopamine tone.
- The tissue matters. A partial agonist can look almost like a full agonist in a tissue with a large receptor reserve and like an antagonist where the reserve is small.
The opioid applications, including methadone and naloxone, are covered in opioid use disorder for Step 1.
Inverse agonists and constitutive activity
Many receptors signal a little even when nothing is bound; this is constitutive activity. An inverse agonist has negative intrinsic efficacy: it stabilizes the inactive conformation and lowers that baseline, the opposite of what an agonist does. If a receptor has little constitutive activity, an inverse agonist behaves like a simple competitive antagonist, which is why many drugs long labeled antagonists turned out to be inverse agonists. Examples include H2 blockers such as cimetidine and ranitidine, whose loss of effect over weeks may reflect receptor upregulation, and most atypical antipsychotics at serotonin 5-HT2 receptors.
Exam clue: a drug that produces the opposite of the agonist's effect when no agonist is present is an inverse agonist, not a neutral antagonist.
Spare receptors (receptor reserve)
A full agonist can often produce its maximal response while occupying only a fraction of the receptors; the rest are called spare receptors or the receptor reserve. Three consequences are testable:
- EC50 is lower than KD: a half-maximal response needs less than half of the receptors occupied.
- Irreversible antagonists unmask the reserve: small amounts shift the agonist curve right, and Emax falls only once the reserve is used up.
- Partial agonists look stronger in tissues with a large reserve.
The term is a slight misnomer: all the receptors take part in the response, even though not all are needed to reach the maximum.
Exam traps
- "More potent" is not "more effective." Potency is position; efficacy is the plateau.
- Right shift with the same plateau = competitive; lower plateau = noncompetitive or irreversible (phenoxybenzamine).
- Partial agonist plus full agonist = less effect: buprenorphine given too soon after heroin precipitates withdrawal.
- Naloxone can wear off first. Its half-life (30–80 minutes) is shorter than that of methadone or fentanyl, so patients need monitoring for re-sedation.
- Flumazenil competitively reverses benzodiazepines but can provoke seizures in chronic benzodiazepine users and in tricyclic antidepressant overdose.
- An "antagonist" that has an effect with no agonist present is an inverse agonist.
Worked example
Vignette. A 29-year-old man with opioid use disorder last injected heroin 3 hours ago. To start treatment, he is given sublingual buprenorphine. Within 30 minutes he has rhinorrhea, lacrimation, yawning, piloerection, diarrhea, sweating and tachycardia. Which property of buprenorphine best explains this reaction?
Answer: High affinity with low intrinsic efficacy at μ-opioid receptors (partial agonism).
Reasoning: Buprenorphine displaces heroin from μ receptors but activates them less, so net opioid signaling drops and withdrawal is precipitated. Induction should wait until the patient shows withdrawal, typically 12–18 hours after a short-acting opioid such as heroin.
Key takeaways
- All, Part, Absent, Reverse: full agonist, partial agonist, antagonist, inverse agonist.
- All four have affinity; they differ in intrinsic efficacy (maximal, partial, zero, negative).
- Potency = position (EC50); efficacy = elevation (Emax).
- Competitive: right shift, same Emax, surmountable. Noncompetitive or irreversible: Emax falls, insurmountable.
- A partial agonist blocks a full agonist, which is how buprenorphine precipitates withdrawal.
- Spare receptors let a full agonist reach Emax at partial occupancy, so its EC50 is lower than its KD.
Sources
- Receptors — IUPHAR Pharmacology Education Project
- Pharmacodynamics — IUPHAR Pharmacology Education Project
- Drug–Receptor Interactions — Merck Manual Professional Edition
- Dose-Response Relationships — Merck Manual Professional Edition
- Berg KA, Clarke WP. Making Sense of Pharmacology: Inverse Agonism and Functional Selectivity — International Journal of Neuropsychopharmacology, 2018
- Buprenorphine — StatPearls, NCBI Bookshelf
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
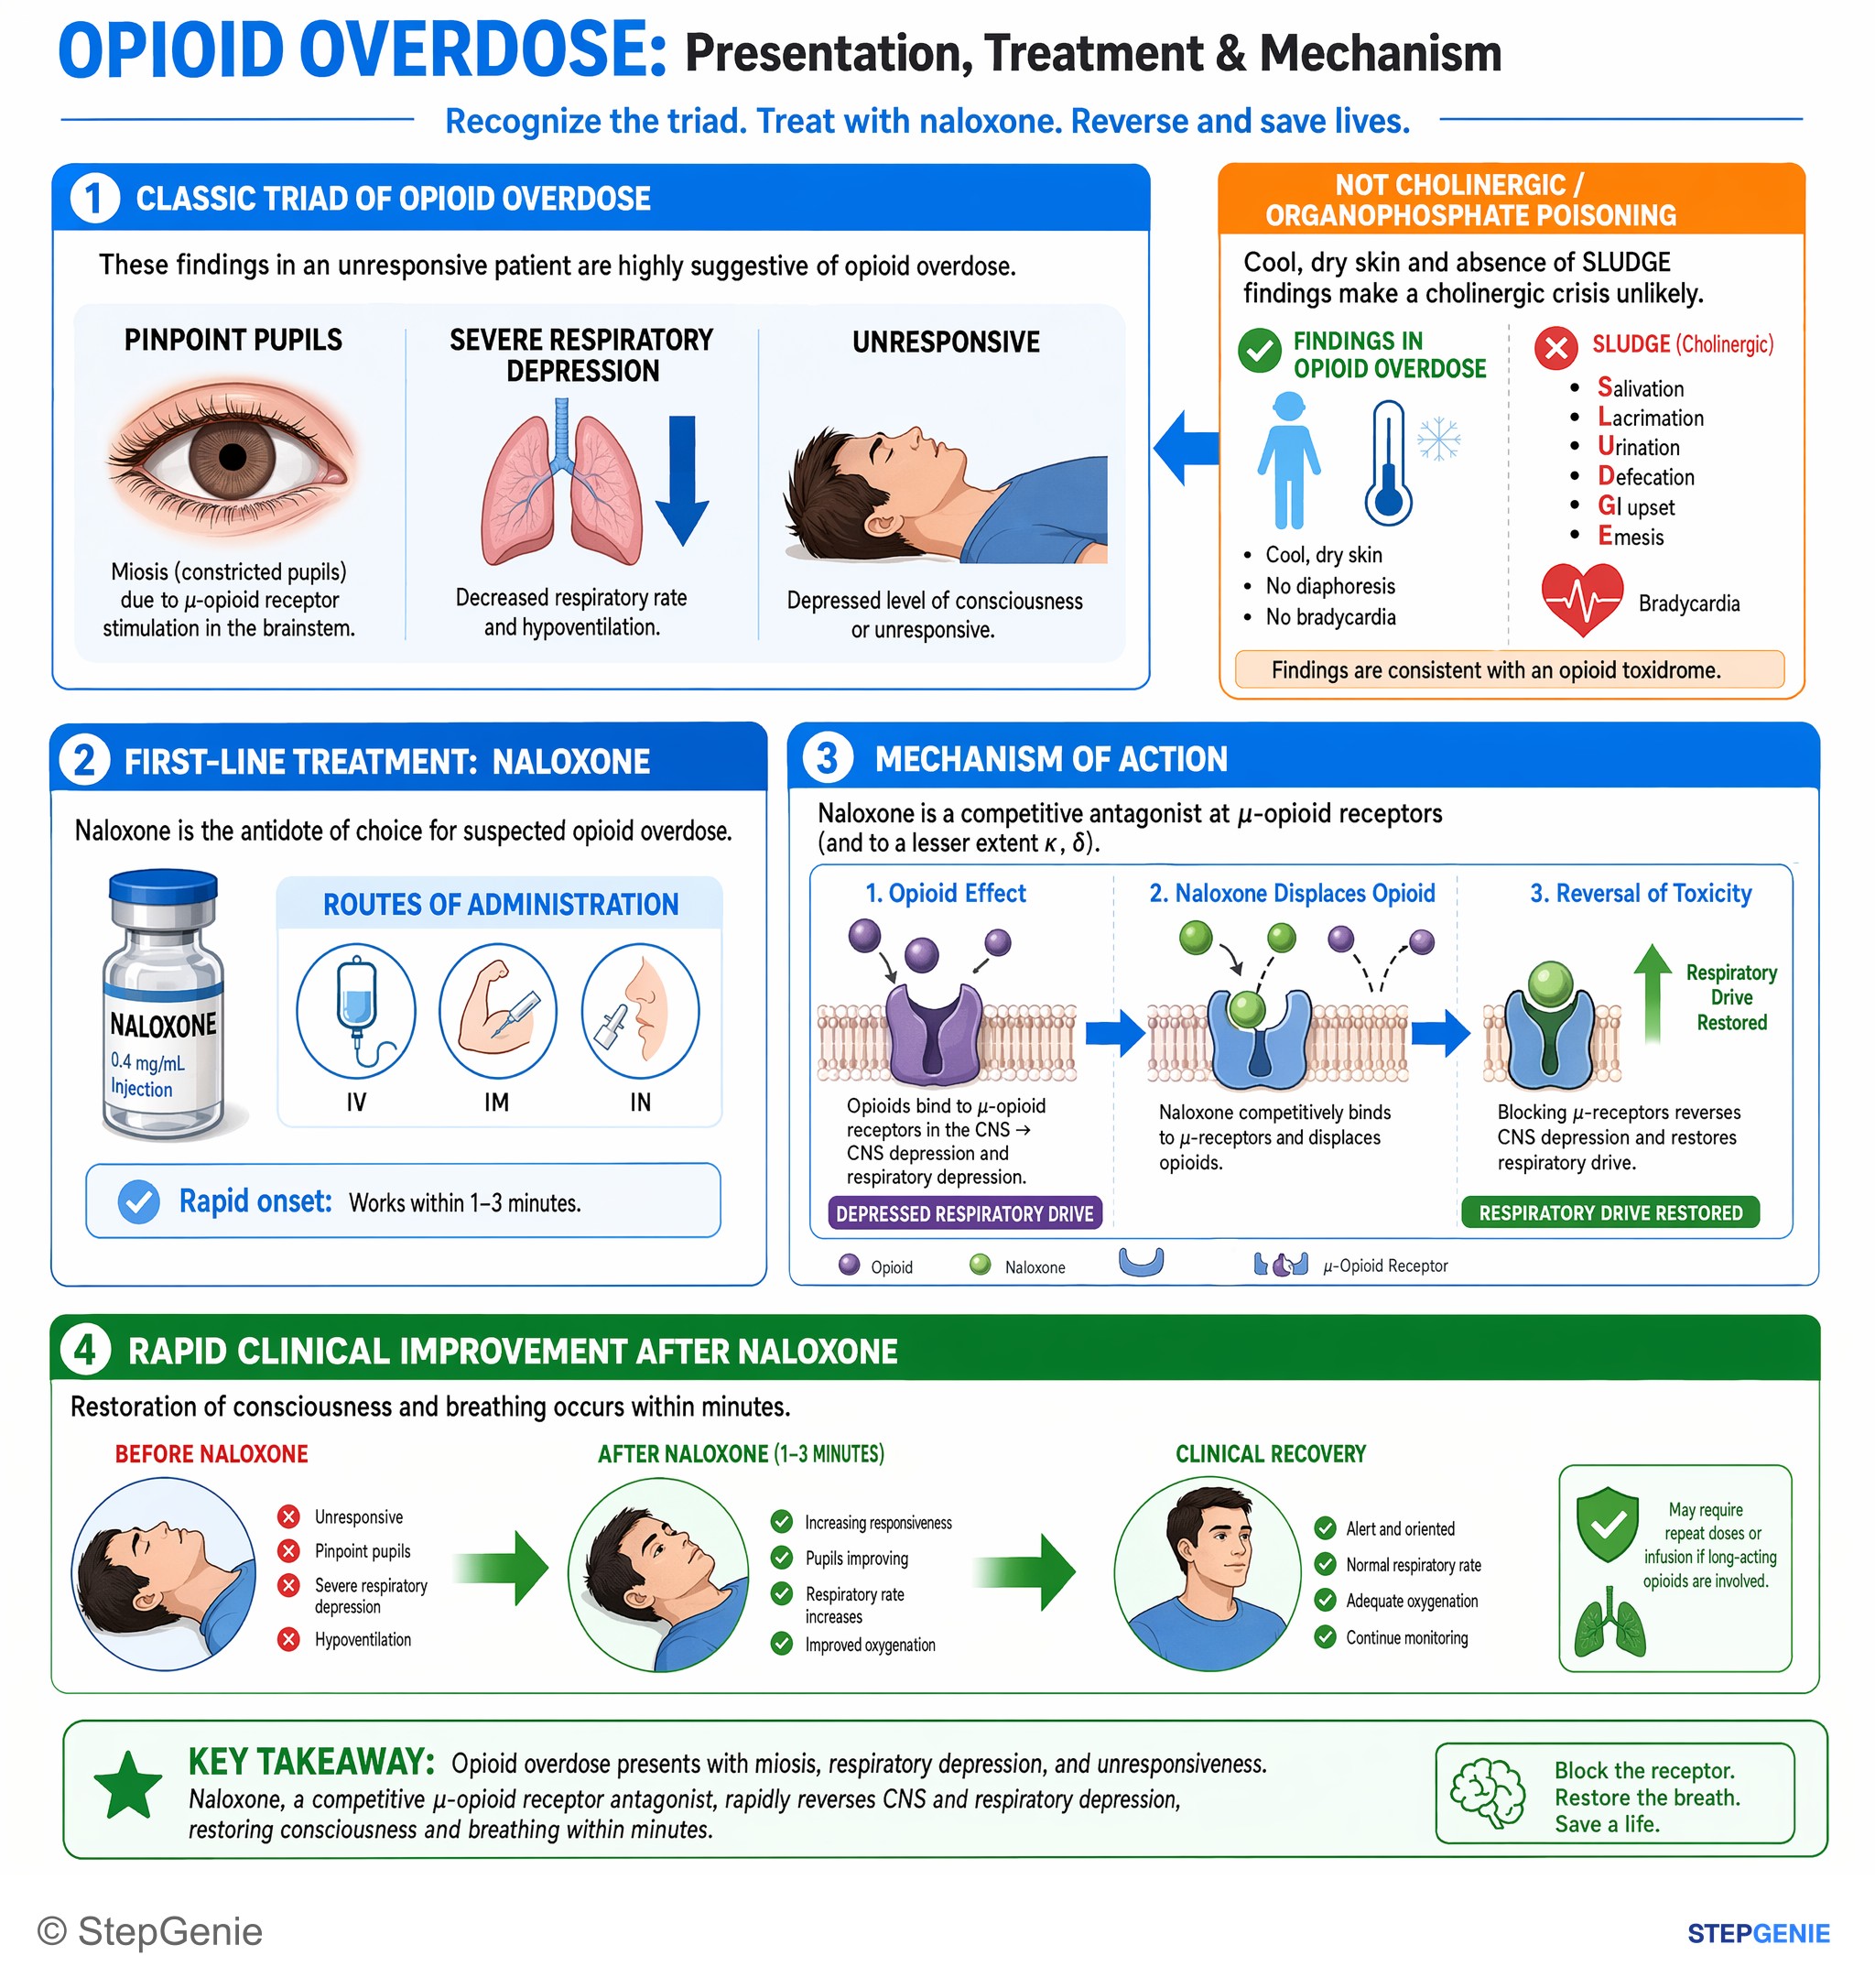
Opioid overdose (miosis, respiratory depression) reversed by naloxone, a competitive μ-opioid receptor antagonist, rapidly restores…
USMLE Step 1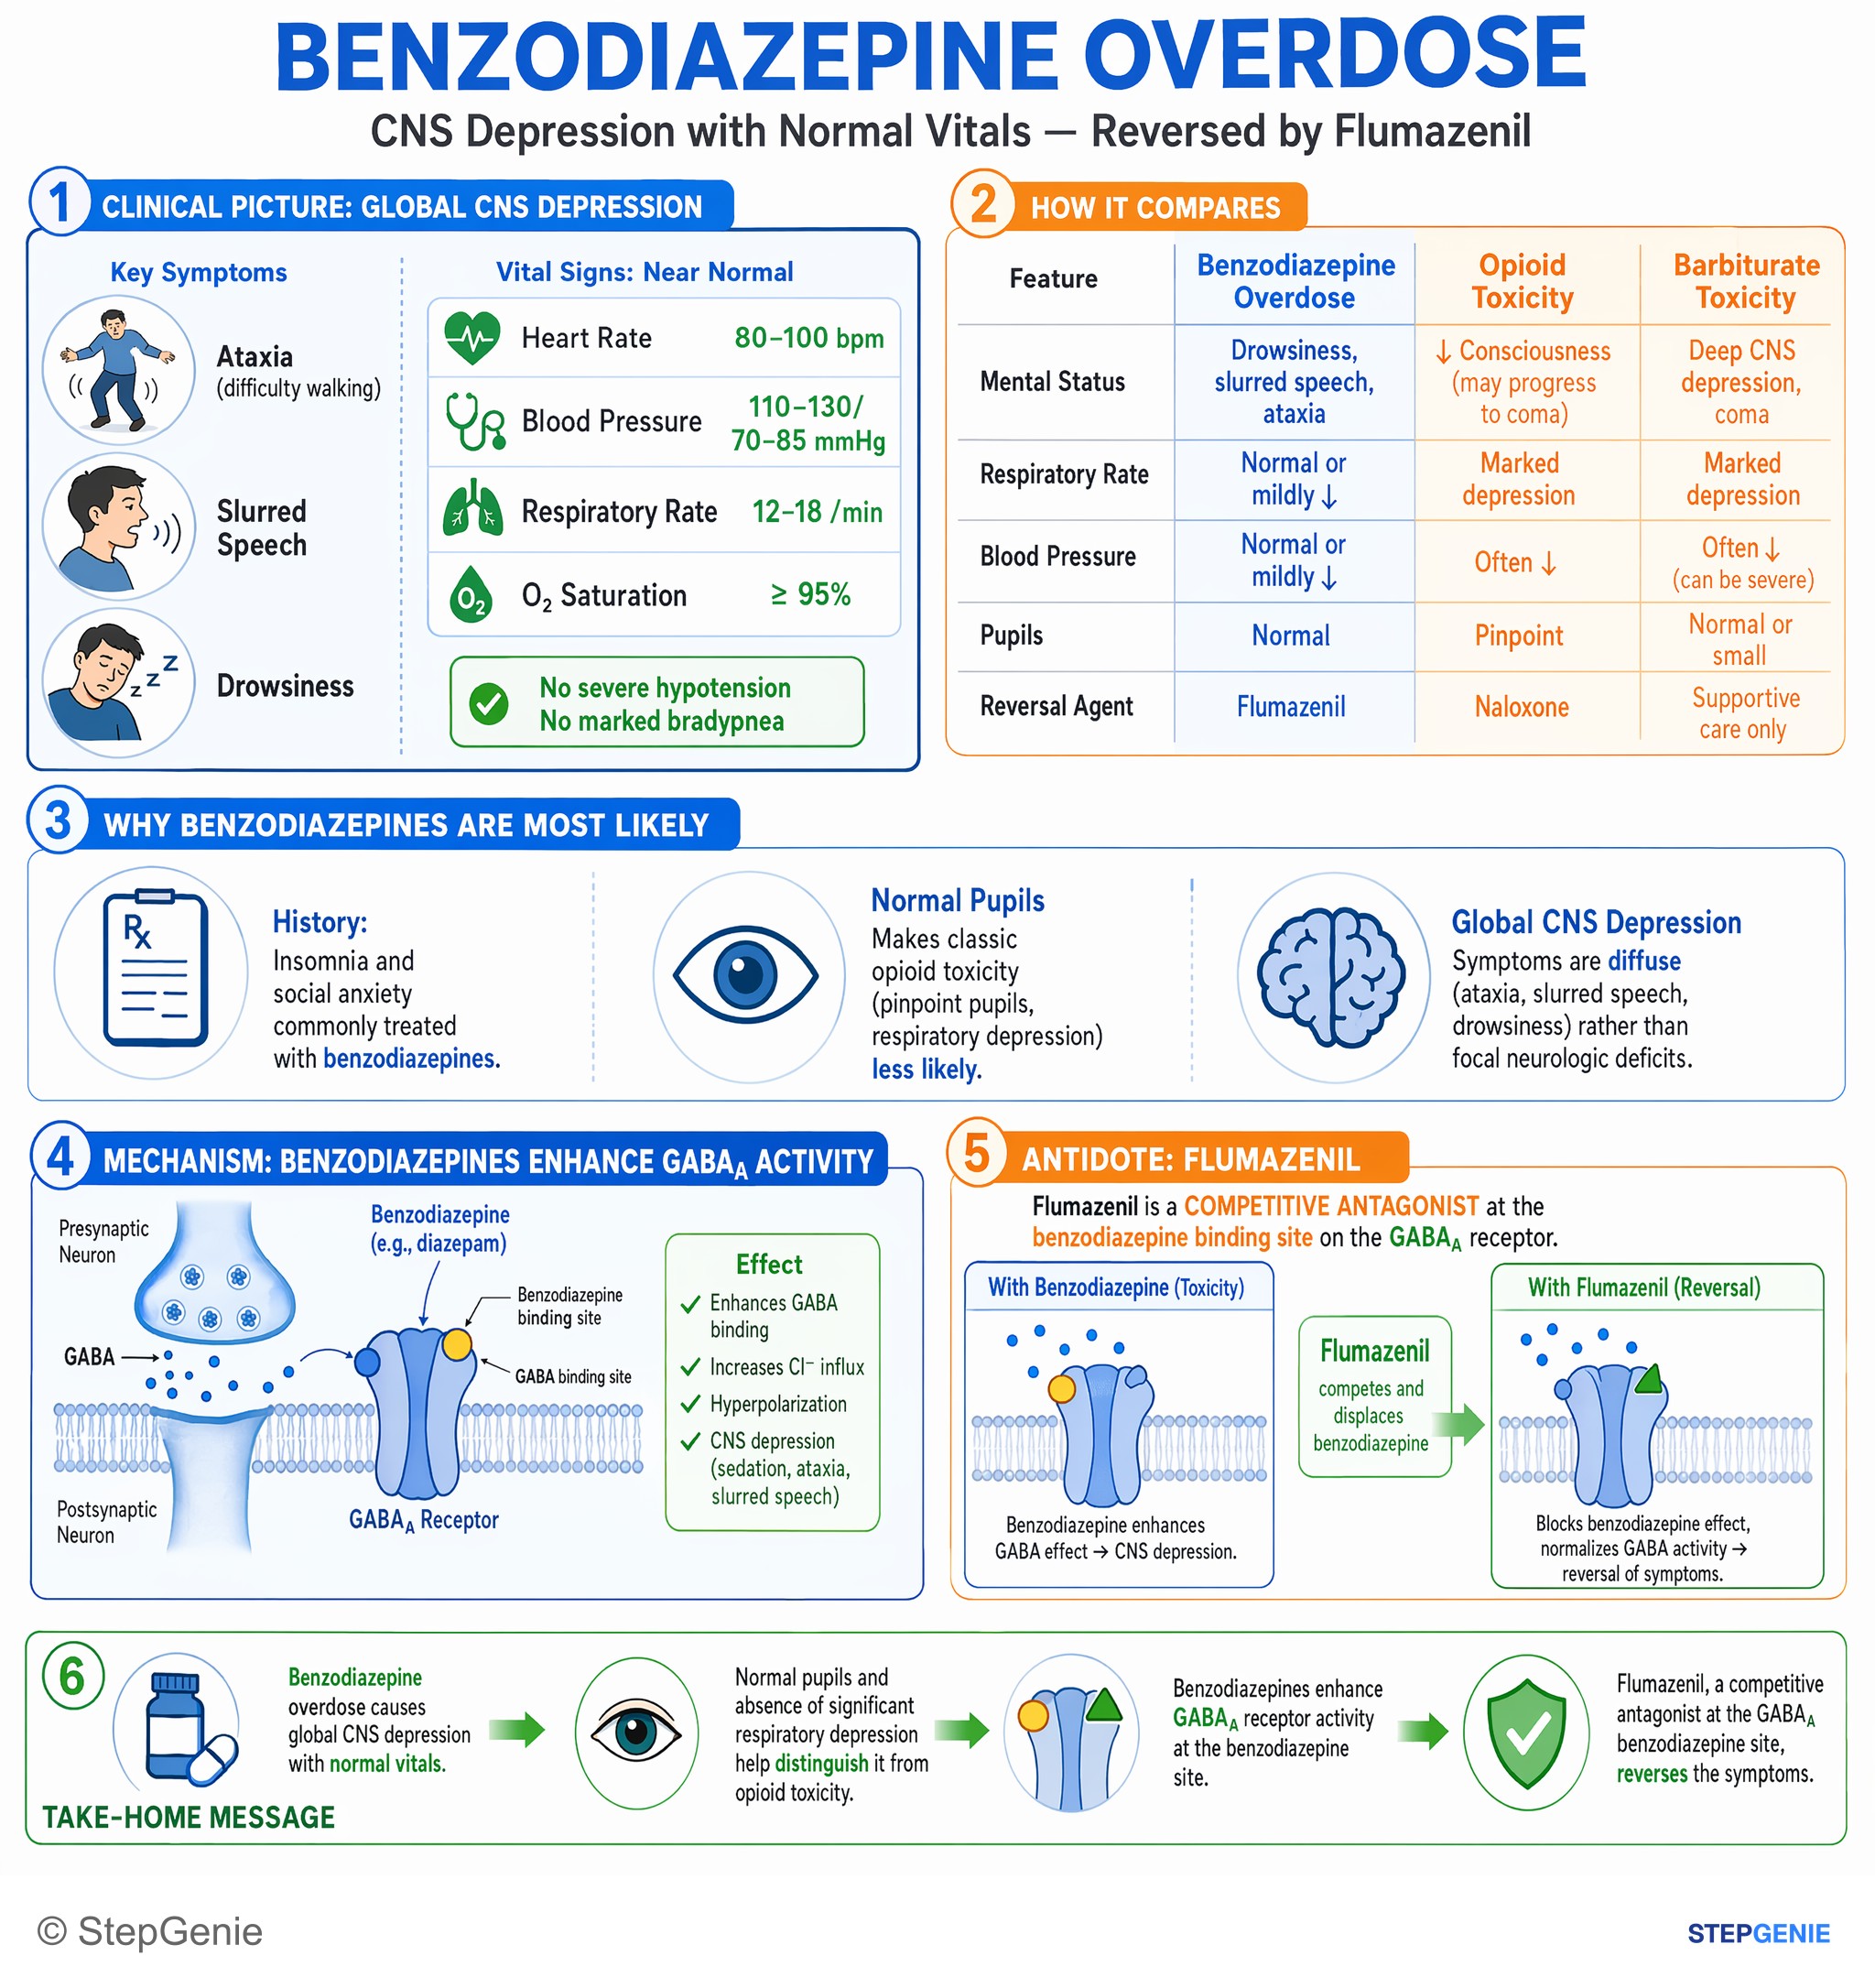
Benzodiazepine overdose causes CNS depression with normal vitals; reversed by flumazenil, a competitive GABAA receptor antagonist at the…
USMLE Step 1Frequently Asked Questions
What is the difference between potency and efficacy?
Efficacy is the maximal response a drug can produce (Emax), the height of the dose-response plateau. Potency is the amount of drug needed for a given effect, usually expressed as the EC50, the concentration producing half the maximal effect; a more potent drug's curve sits further to the left. The two vary independently, so a more potent drug is not necessarily more effective.
How do competitive and noncompetitive antagonists change the dose-response curve?
A competitive antagonist binds reversibly at the agonist's site, so enough agonist can overcome it: the curve shifts right (higher EC50) with the same Emax. A noncompetitive or irreversible antagonist cannot be overcome by more agonist, so Emax falls. Exam graphs classically draw the noncompetitive EC50 as unchanged, although real curves can also shift right.
Why does buprenorphine cause precipitated withdrawal?
Buprenorphine is a partial agonist at mu-opioid receptors with high affinity and slow dissociation. Given while heroin, methadone or another full agonist still occupies the receptors, it displaces the full agonist but activates the receptors less, so the net opioid effect drops and withdrawal begins. Induction therefore waits until the patient shows withdrawal, usually 12 to 18 hours after a short-acting opioid.
What is an inverse agonist?
An inverse agonist binds a receptor and reduces its constitutive (baseline) activity, producing the opposite effect of an agonist; it has negative intrinsic efficacy. The effect is only visible when the receptor signals without a ligand; otherwise an inverse agonist behaves like a competitive antagonist. Many drugs once labeled antagonists, including H2 blockers and most atypical antipsychotics at serotonin 5-HT2 receptors, have inverse agonist activity.
What are spare receptors in pharmacology?
Spare receptors, or receptor reserve, exist when a full agonist can produce its maximal response while occupying only some of the receptors. As a result, the agonist's EC50 is lower than its KD, and an irreversible antagonist first shifts the dose-response curve to the right before it lowers the maximum. Partial agonists also look more effective in tissues with a large receptor reserve.