Valid informed consent needs four things: a patient with decision-making capacity; disclosure of the diagnosis and of the nature, purpose, risks, benefits and alternatives of the intervention, including no treatment; real understanding (with a qualified interpreter when needed); and a voluntary decision. The signed form only documents that conversation. The classic exceptions are an emergency in which neither the patient nor a surrogate can decide in time, incapacity (a surrogate decides), a capable patient's explicit waiver, and a very narrow therapeutic privilege. Capacity is a clinical, decision-specific judgment that any physician can make; competence is a legal status decided by a court. Minors generally need a parent's permission, with exceptions that vary by state.
The memory palace: walk through the Consent Clinic
Picture a small clinic and walk the same route every time. Each room holds one requirement, and the exits hold the exceptions.
| Stop | Room | Requirement | One-liner |
|---|---|---|---|
| 1 | Front door with a bouncer | Capacity | "Can you make this decision, today?" |
| 2 | Waiting-room posters | Disclosure | Every poster is the same BRAND |
| 3 | Interpreter desk | Understanding | Qualified interpreter, then teach-back |
| 4 | Narrow hallway of pressure | Voluntariness | No coercion; talk to the patient alone |
| 5 | Signature room | Decision and documentation | Signature is not consent; consent can be withdrawn |
| 6 | Glowing emergency exit | Emergency exception | Treat when no one can consent in time |
| 7 | Curtained booth with a locked safe | Waiver and therapeutic privilege | Honor "don't tell me"; the safe almost never opens |
| 8 | Back door marked "No thanks" | Informed refusal | A capable adult may refuse anything |
| 9 | Pediatric wing | Minors | Parents give permission, children assent; exceptions vary by state |
Stop 1, the front door: capacity
The bouncer checks four abilities. The patient must:
- Communicate a choice
- Understand the benefits, risks and alternatives
- Appreciate how they apply to their own situation
- Reason about the options
Traps the bouncer won't fall for:
- Any physician can assess capacity; psychiatry helps in hard cases but is not required.
- Capacity is decision-specific and can fluctuate; riskier decisions demand more capacity (a sliding scale).
- Depression, delirium, dementia or a psychiatric diagnosis may impair capacity but do not automatically remove it. Assess the four abilities.
- A refusal is "not considered to be attempted suicide or evidence by itself of diminished capacity" (Merck).
| Capacity | Competence | |
|---|---|---|
| Type | Clinical judgment | Legal status |
| Who decides | Any physician | A court |
| Scope | One decision, at one time | Set by the court |
| If absent | A surrogate decides | A court-appointed guardian decides |
For a full vignette, see capacity vs competence.
Stop 2, the waiting-room posters: disclosure (BRAND)
Every poster comes from the same BRAND:
- Benefits expected
- Risks and burdens
- Alternatives, with their own risks and benefits
- No treatment: what happens if the patient declines
- Diagnosis and Description: the condition, and the nature and purpose of the intervention
This matches the AMA Code: the diagnosis (when known), "the nature and purpose of recommended interventions," and "the burdens, risks, and expected benefits of all options, including forgoing treatment." How much to say is judged by one of three standards: subjective (what this patient needs), the reasonable patient (what an average patient would need to decide; used by many states) or the reasonable clinician. On the exam, think "what would a reasonable patient want to know?"
Stop 3, the interpreter desk: understanding
- Limited English proficiency: use a qualified medical interpreter (and, for a deaf patient who signs, a qualified sign language interpreter), then confirm understanding with teach-back ("Can you tell me in your own words what we're going to do?"). A nod is not understanding.
- Federal rule (45 CFR 92.201, in force since July 2024 and unchanged as of September 2026): health programs covered by Section 1557 (mainly those receiving federal funds) must offer a qualified interpreter when one is needed and may not make patients bring or pay for their own. They may not rely on an untrained adult except as a temporary measure in an emergency or when the patient privately asks for a companion to interpret (with a qualified interpreter present), and may not rely on a minor child except temporarily in an emergency.
- Culture shapes how patients want information delivered; see the cultural competency flowchart.
Stop 4, the hallway of pressure: voluntariness
The decision must be independent and voluntary: free of coercion, manipulation and undue influence. If a relative is steering the answer, speak with the patient alone. A choice made under threat (for example, being told care will stop unless they agree) is not voluntary.
Stop 5, the signature room: the decision and the paperwork
- "Informed consent is more than merely a signature on a document; it is a communication process" (StatPearls). A signed form after no real discussion is not valid consent.
- Document the conversation and the decision in the record: the nature of the procedure, its risks and benefits, reasonable alternatives with their risks and benefits, and the patient's understanding.
- The patient can refuse or withdraw consent at any time, even after signing.
- Low-risk routine care such as phlebotomy is usually covered by implied consent.
Stops 6 and 7, the exits: proceeding without full informed consent
| Exit | When it applies | What you do |
|---|---|---|
| Emergency (implied or presumed consent) | A decision is needed urgently, the patient cannot participate, and no surrogate is available | Treat; inform the patient or surrogate at the earliest opportunity and get consent for ongoing care |
| Incapacity | The patient lacks capacity for this decision | A surrogate consents: health care agent, then the default surrogate under state law (see surrogate decision-making) |
| Waiver | A capable patient explicitly declines information | Honor it, or give the information to a person the patient designates; document |
| Therapeutic privilege | Classic definition: disclosure itself would be so harmful as to be medically contraindicated | Almost never the answer; never used just because the patient might refuse |
- The emergency exit never opens onto a known refusal. It covers unknown wishes, not a capable patient's refusal or a valid, applicable advance directive (see advance directives).
- The safe stays locked. The classic definition above comes from the older AMA Code (quoted in a 2004 AMA Journal of Ethics article), which barred using it merely because the patient might forgo treatment. The current Code (Opinion 2.1.3) no longer names the privilege: withholding information without the patient's knowledge or consent is "ethically unacceptable," except in an emergency when the patient cannot make an informed decision. You may pace disclosure to what the patient can absorb, but with a definite plan for full disclosure.
- Family requests are not an exit. If relatives say "don't tell her it's cancer," ask the patient how much she wants to know and who should receive the information.
Stop 8, the back door: informed refusal
A capable adult has the right to decline any intervention, or to stop one, even when death is the expected result. Make the refusal informed: explain the consequences, check capacity, document, and keep offering other care. A Jehovah's Witness with capacity who refuses a transfusion is the classic example: respect the refusal.
Stop 9, the pediatric wing: minors
- Children, typically those younger than 18, cannot give informed consent; parents or guardians give informed permission, and the child gives assent when developmentally able.
- Exceptions (state law varies; check local law):
- Emergencies, when a parent cannot be reached in time.
- Emancipated minors can consent to all their own medical care; the criteria are set by state law.
- STI testing and treatment: all 50 states and DC allow minors to consent, though 8 states set a minimum age (12 to 14) and 16 have parental-notification provisions, mostly optional (Guttmacher, as of August 2026; it flags a 2024 Idaho parental-consent law whose effect is unsettled).
- Contraception is less uniform: 23 states and DC explicitly let minors consent, 16 more allow it only in specific circumstances, and 2 require parental consent (Guttmacher, as of August 2026).
- Substance use treatment and mental health care: many states let minors consent, with rules and age thresholds that vary widely.
How USMLE tests it
| Stem | Best answer |
|---|---|
| Patient nods "yes" but can't explain the plan; her son has been interpreting | Bring in a qualified medical interpreter, re-explain, use teach-back |
| Family asks you not to tell the patient she has cancer | Ask the patient how much she wants to know and who should be told |
| Capable Jehovah's Witness refuses blood | Respect the refusal, document, offer alternatives |
| Unconscious trauma patient, no surrogate reachable | Treat under the emergency exception |
| Calm patient with schizophrenia explains the risks and benefits | Has capacity; respect the decision |
| 16-year-old wants STI treatment without telling her parents | Treat; every state lets minors consent to STI care (age limits, where they exist, are 14 or younger) |
| Signed form, but no one explained the procedure | Not valid consent; have the discussion |
Practice question
A 52-year-old man with type 2 diabetes has fever, right upper quadrant pain and leukocytosis, and ultrasound shows acute cholecystitis. The surgeon recommends laparoscopic cholecystectomy within the next day and starts to explain the operation. The patient interrupts: "I trust you and I want the surgery, but please don't tell me about the risks. Hearing them will only make me anxious." He is alert and oriented, can describe what the operation is and why it is recommended, and knows he could decline it. Which of the following is the most appropriate next step?
A. Review the major risks with him before he signs the consent form B. Ask his wife to give consent on his behalf C. Honor his request and document that he waived the risk discussion D. Request a psychiatric consultation to assess his capacity E. Proceed under the emergency exception to informed consent
Answer: C. A capable patient may waive detailed information. The AMA Code tells physicians to honor a request "not to receive certain medical information or to convey the information to a designated surrogate," provided it reflects the patient's genuine wishes. He still understands the nature and purpose of the operation and that he could decline it, so his decision is informed and voluntary. Tell him he can ask about the risks at any time, offer to share them with someone he chooses, and document the waiver.
- A: overrides a capable patient's explicit choice; forcing unwanted detail on him is paternalistic.
- B: surrogates consent only when the patient lacks capacity, and this patient is deciding for himself.
- D: nothing suggests impaired capacity; any physician can assess it, and wanting fewer details is not a sign of incapacity.
- E: the emergency exception requires a patient who cannot participate and no available surrogate; this patient can consent.
Key takeaways
- Valid consent = capacity + disclosure (BRAND) + understanding + a voluntary decision, documented in the record.
- Capacity (communicate, understand, appreciate, reason) is clinical and decision-specific; competence is decided by a court.
- Signature is not consent, and the patient can withdraw consent at any time.
- Qualified interpreter, not family or children (a child only briefly, in an emergency), plus teach-back.
- Exceptions: emergency, incapacity (surrogate), waiver; therapeutic privilege is rare and never a tool to secure agreement.
- A capable adult may refuse any treatment; refusal alone does not prove incapacity.
- Minors: parental permission plus the child's assent; exceptions (emergencies, emancipation, STI care in every state, and in many states contraception, substance use or mental health care) vary by state.
Sources
- Opinion 2.1.1: Informed Consent — AMA Code of Medical Ethics
- Opinion 2.1.3: Withholding Information from Patients — AMA Code of Medical Ethics
- Opinion 2.2.1: Pediatric Decision Making — AMA Code of Medical Ethics
- Informed Consent — StatPearls, NCBI Bookshelf (2024)
- Informed Consent — Merck Manual Professional Edition (2025)
- Capacity (Competence) and Incapacity — Merck Manual Professional Edition (2026)
- Consent and Surrogate Decision Making — Merck Manual Professional Edition (2025)
- Evaluating Medical Decision-Making Capacity in Practice — American Family Physician (2018)
- 45 CFR 92.201: Meaningful Access for Individuals With Limited English Proficiency — eCFR (2026)
- Minors' Access to STI Testing and Treatment — Guttmacher Institute (2026)
- Minors' Access to Contraceptive Services — Guttmacher Institute (2026)
- Invoking Therapeutic Privilege — AMA Journal of Ethics (2004)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
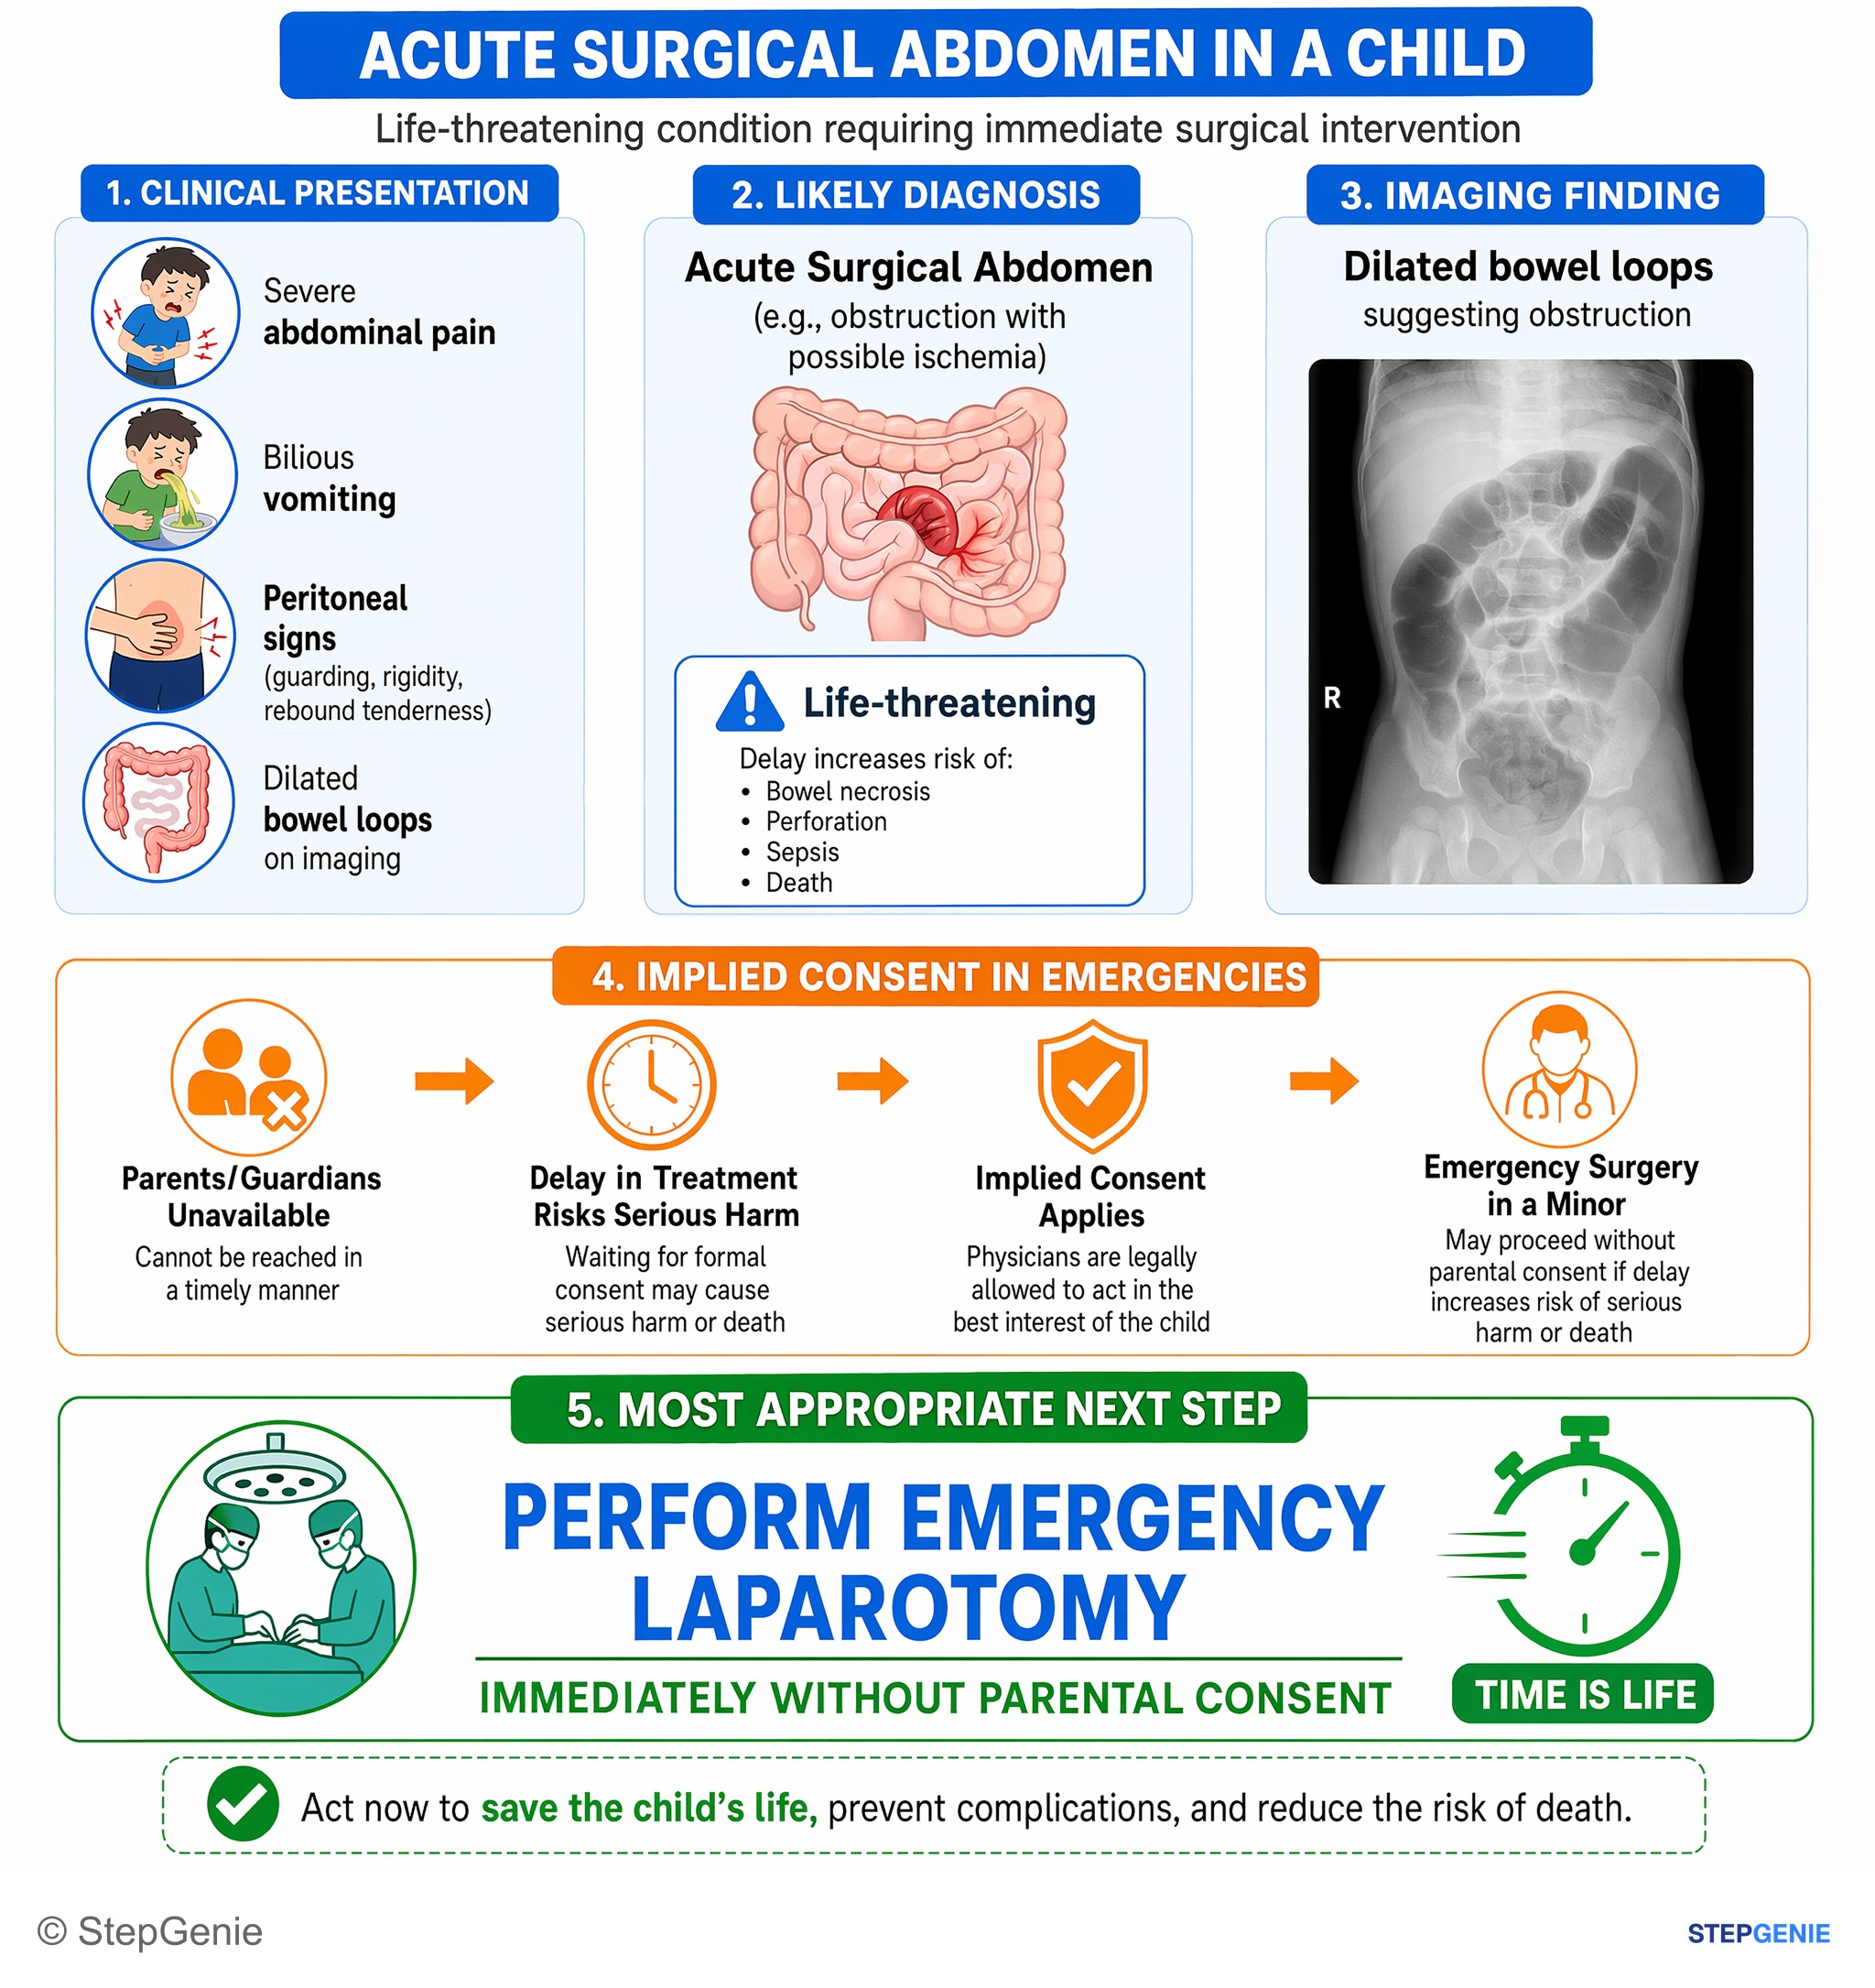
Emergency surgery in a minor: life-threatening condition → physicians may treat without parental consent if delay increases risk of…
USMLE Step 2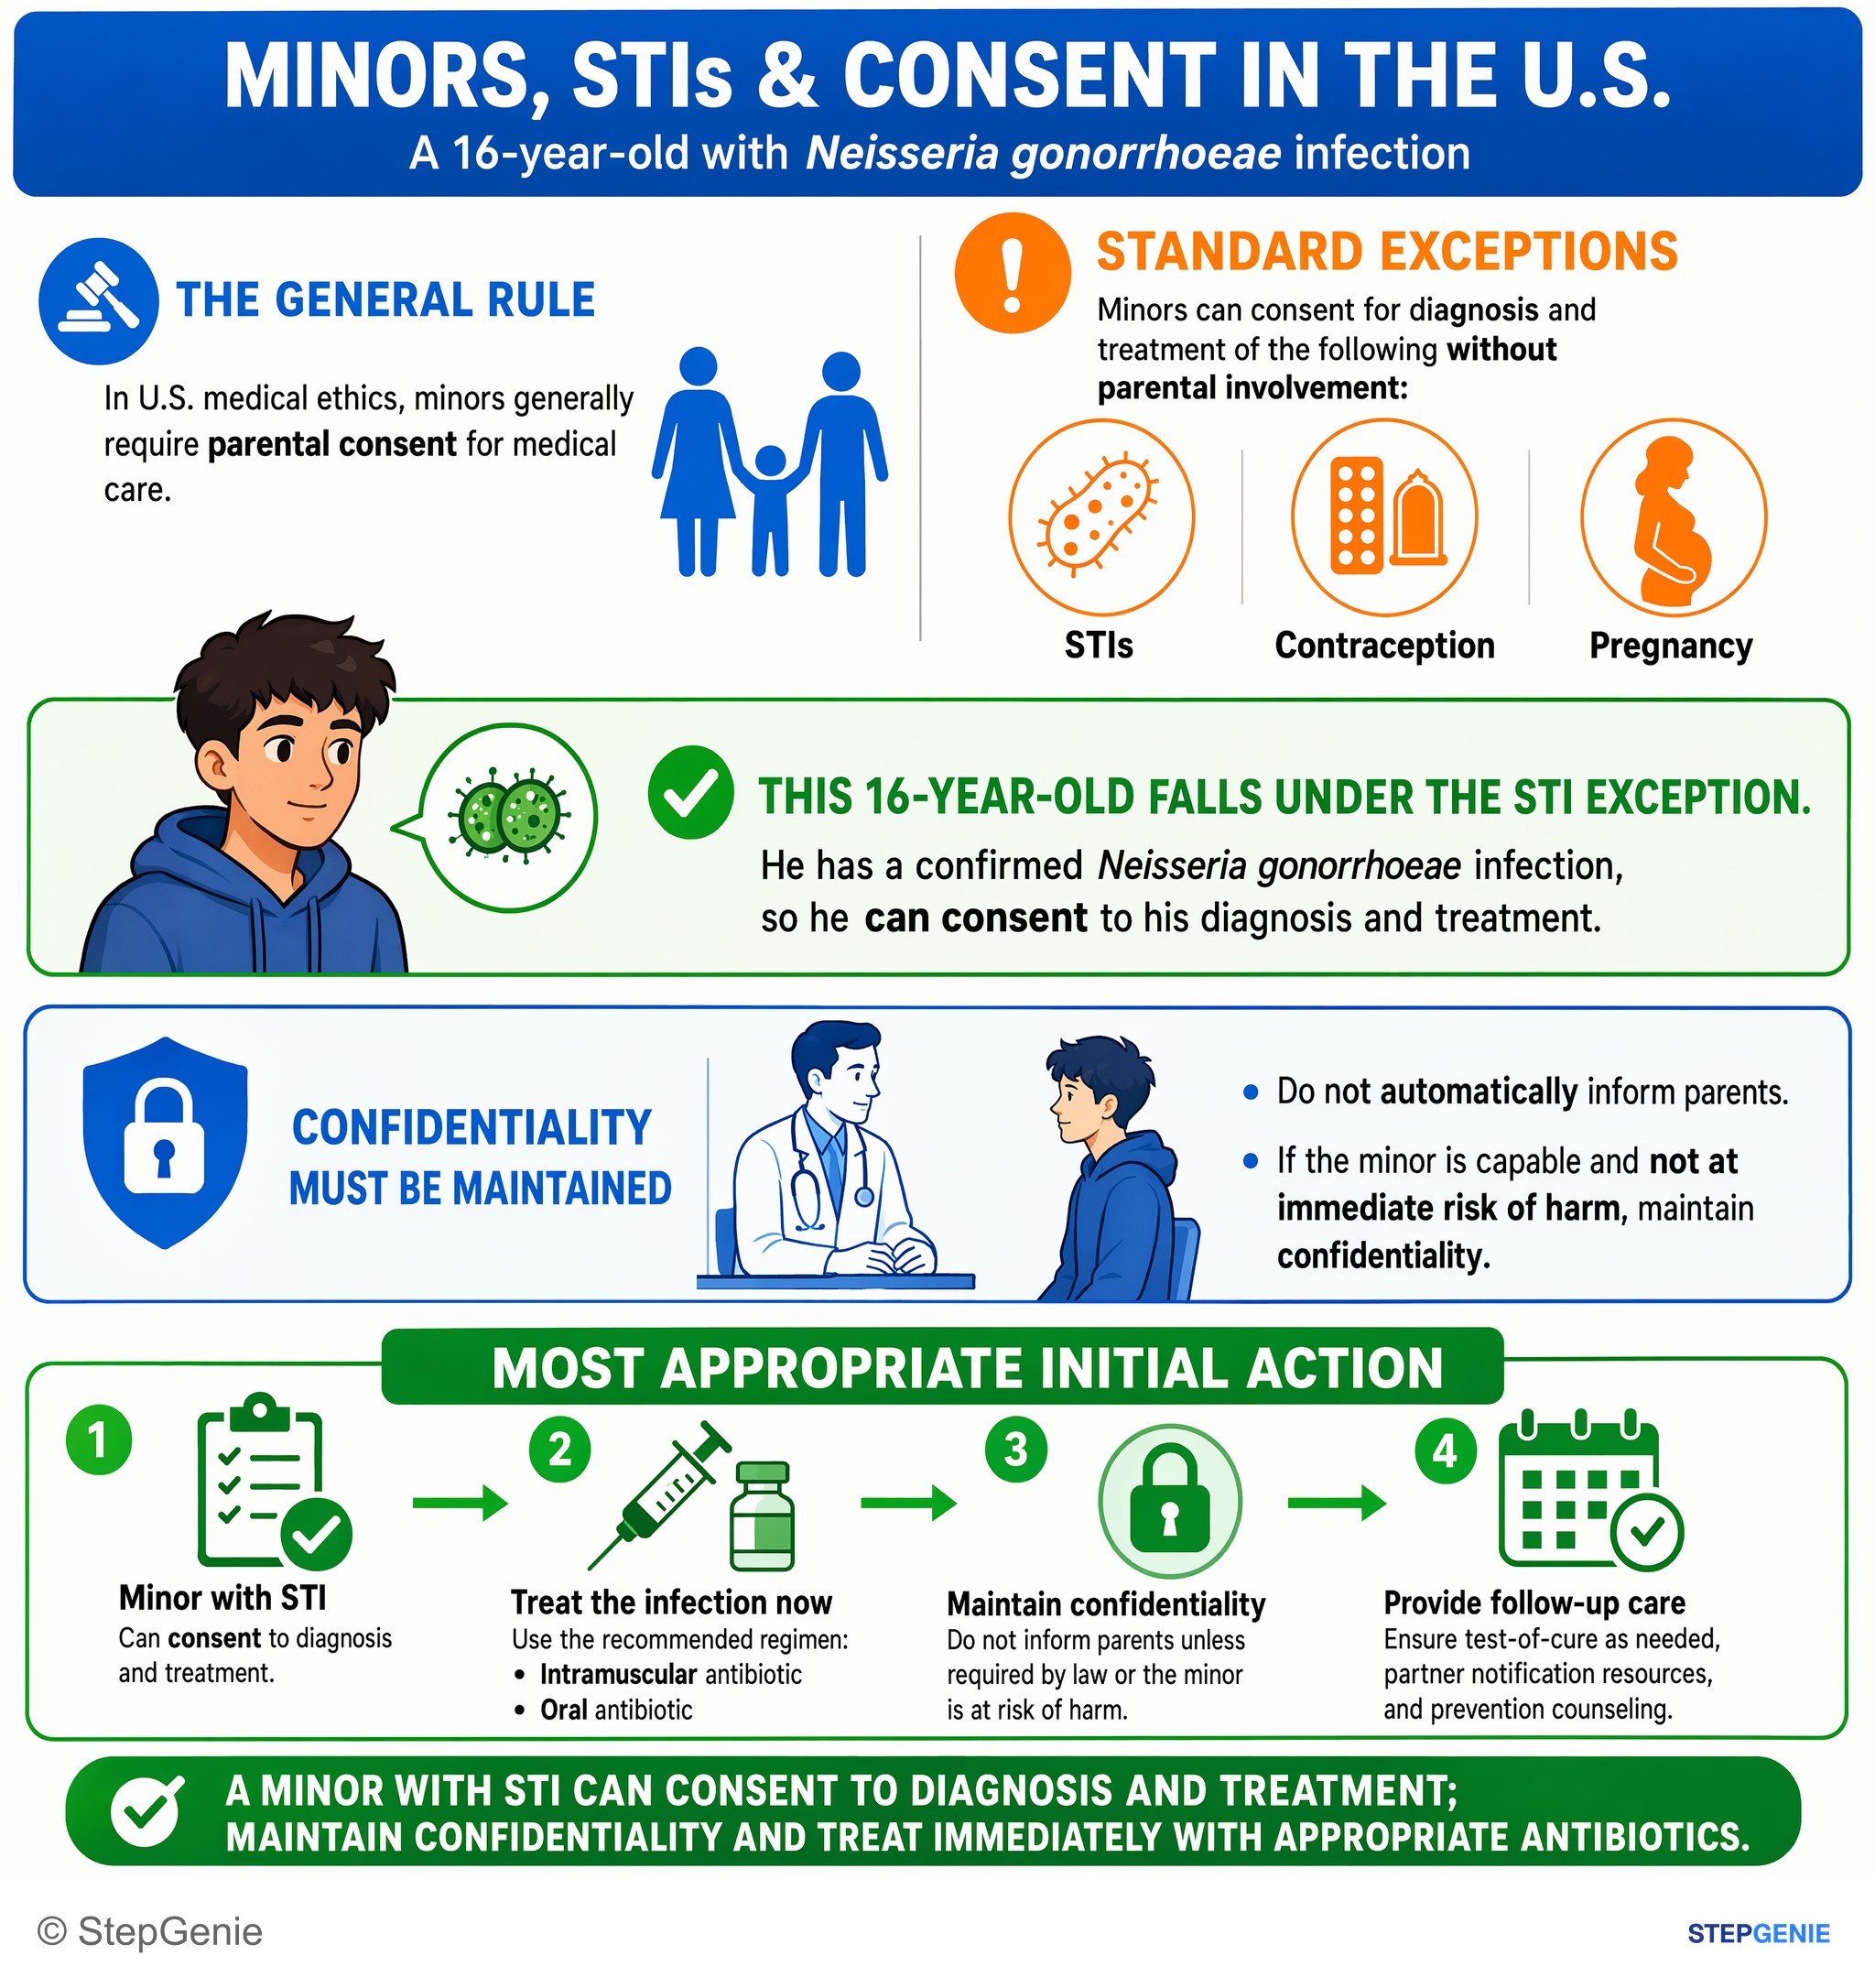
Minor with STI can consent to diagnosis and treatment; maintain confidentiality and treat immediately with appropriate antibiotics.
USMLE Step 2Frequently Asked Questions
What are the elements of informed consent?
Valid informed consent needs a patient with decision-making capacity; disclosure of the diagnosis and of the nature, purpose, risks, benefits and alternatives of the proposed intervention, including no treatment; genuine understanding of that information; and a voluntary decision free of coercion. The conversation and the decision are documented in the medical record. A signed form is evidence of the process, not a substitute for it, and the patient can withdraw consent at any time.
What is the difference between capacity and competence?
Capacity is a clinical judgment that any physician can make about one specific decision: whether the patient can communicate a choice, understand the information, appreciate how it applies to them and reason about the options. It can change over time, for example with delirium. Competence is a legal status that only a court can decide. When a patient lacks capacity, a surrogate decides; when a court finds a person incompetent, it appoints a guardian.
What are the exceptions to informed consent?
The classic exceptions are an emergency, when a decision is needed urgently, the patient cannot participate and no surrogate is available; incapacity, when a surrogate consents for the patient; waiver, when a capable patient explicitly declines information or asks that it go to someone else; and therapeutic privilege, a very narrow and rarely justified exception when disclosure itself would be medically contraindicated. A family request to withhold information is not an exception.
Can a family member act as an interpreter for informed consent?
Generally no. Patients with limited English proficiency should have a qualified medical interpreter, and understanding should be confirmed with teach-back. Federal rules for health programs covered by Section 1557 (45 CFR 92.201, unchanged as of September 2026) bar relying on an untrained adult, such as a relative, except as a temporary measure in an emergency or when the patient privately asks for it with a qualified interpreter present, and bar relying on a minor child except temporarily in an emergency.
Can a patient refuse to hear the risks of a procedure?
Yes. A capable patient may waive detailed information, and the AMA Code tells physicians to honor a request not to receive certain information, or to have it given to a designated person, when that reflects the patient's genuine wishes. The physician should confirm that the patient understands what the procedure is and why it is recommended and that they can ask for the details at any time, and should document the waiver.
When can minors consent to their own medical care?
The rules vary by state. In general, parents or guardians give permission and the child gives assent. Common exceptions include emergencies when a parent cannot be reached, emancipated minors, and specific services. All 50 states and DC let minors consent to STI testing and treatment, although some set a minimum age. Contraception is less uniform: as of August 2026, 23 states and DC explicitly allow minors to consent, and others allow it only in certain circumstances. Many states also let minors consent to substance use or mental health care.