A cross-sectional study measures exposure and outcome in the same individual people at one point in time, so it links each person's exposure to that person's outcome and gives prevalence, plus a prevalence ratio or odds ratio. An ecological study compares groups, such as counties, states or countries, using aggregate rates or averages, so it gives only a group-level correlation and is open to the ecological fallacy: assuming that a pattern seen across groups holds for the individuals in them.
Neither design shows that the exposure came first, and both are quick, cheap and mainly hypothesis-generating. On the exam, the unit of analysis decides: if each row of data is a person, the study is cross-sectional; if every number is a rate, average or percentage for a place, it is ecological, even when everything was measured in the same year. The USMLE content outline draws the same line, listing "cross-sectional (individuals)" and "ecological (populations)" among observational designs.
Ecological vs cross-sectional study: the difference at a glance
| Feature | Cross-sectional study | Ecological study |
|---|---|---|
| Unit of analysis | Individual person | Group: county, state, country or time period |
| What is recorded | Each person's own exposure and outcome, at the same time | Group rates, averages or proportions (deaths per 100,000, per capita intake) |
| Links exposure to outcome in the same person? | Yes | No |
| Main measures | Prevalence; prevalence ratio or prevalence odds ratio | Correlation or regression across groups |
| Timing | A snapshot: one point or a short period | One period, or rates followed over time |
| Shows exposure came first? | No | No |
| Signature pitfall | Reverse causation; cases reflect survival as well as cause | Ecological fallacy; confounding between groups |
| Typical data | Survey, questionnaire, exam or lab test | Census, registries, published statistics, tax records, air monitors |
| Best for | Disease burden, planning, hypotheses | Population-level exposures and policies, hypotheses |
A cross-sectional study can show that exposed people are more (or less) likely to have the condition; an ecological study can show only that places with more exposure have more disease. Robinson, whose 1950 paper described the gap mathematically, concluded that an ecological correlation "is almost certainly not equal to its corresponding individual correlation."
Trust the data structure over the label: Wu and colleagues' April 2020 preprint on long-term fine particulate matter (PM2.5) and COVID-19 deaths called its design "a nationwide, cross-sectional study using county-level data," yet the peer-reviewed version describes an ecological regression, because only area-level death counts were available. Ask whether one row of data is a person or a place.
Cross-sectional studies: an individual-level snapshot
In a cross-sectional study, a sample of people is enrolled and each person's exposures and outcomes are measured simultaneously, by questionnaire, interview, examination or lab test. Participants are chosen only by inclusion and exclusion criteria, not by exposure status (as in a cohort) or disease status (as in a case-control study). With no follow-up, it is the fastest and cheapest individual-level design, and many exposures and outcomes can be studied at once.
Its descriptive job is documenting how common something is: smoking, measles vaccination, hypertension or diabetes in a community, or the coronary risk factors in a workforce before an occupational physician plans a prevention program. Its analytic job is comparing prevalence between exposed and unexposed people, which generates hypotheses.
Its limits:
- Temporality: you cannot tell whether the exposure or the outcome came first.
- No incidence: nobody is followed, so new cases are never counted and relative risk cannot be calculated.
- Survival mixed with cause: prevalent cases include long-term survivors and the newly diagnosed, so the design usually cannot separate risk factors for getting a disease from risk factors for surviving with it.
- Poor fit for rare or short-lived diseases, which few people have on any given day.
- Selection: non-responders may differ from responders, and people may leave because of the outcome: an asthma survey of animal handlers underestimates risk if workers with respiratory symptoms have already changed jobs.
Serial cross-sectional studies repeat the snapshot with a new sample each round: NHANES, PRAMS and BRFSS are cross-sectional surveys repeated with a new sample each year. They show population trends, not change within individuals, so they are not cohorts.
What each design measures: prevalence and odds ratios vs group correlations
Prevalence is the proportion of people who have a disease or attribute at a specified point in time or over a specified period. It counts all cases, new and preexisting; incidence counts only new cases in an initially disease-free population. The two are linked: prevalence ≈ incidence × average duration. High prevalence can reflect high incidence, prolonged survival without cure, or both; low prevalence can reflect low incidence, a rapidly fatal course or rapid recovery. So HIV prevalence in a community can rise even while incidence falls, as cases accumulate among people surviving with the infection.
Associations in a cross-sectional study are expressed as a prevalence ratio (prevalence in the exposed ÷ prevalence in the unexposed) or a prevalence odds ratio. Methodologists have debated which is better; for the exam, know that the odds ratio lies farther from 1 than the prevalence ratio, and the gap widens as the outcome becomes more common. A worked 2 × 2 from a teaching example in Setia's methods paper, in which 300 patients at a sexually transmitted infection (STI) clinic are tested for HIV at their first visit:
| HIV positive | HIV negative | Total | Prevalence | |
|---|---|---|---|---|
| Men | 50 | 150 | 200 | 25% |
| Women | 10 | 90 | 100 | 10% |
| All | 60 | 240 | 300 | 20% |
- Prevalence = 60/300 = 20%.
- Prevalence odds ratio = (50 × 90)/(10 × 150) = 3.0.
- Prevalence ratio = 25%/10% = 2.5.
- Not available: incidence or relative risk.
Ecological studies measure how group averages move together: a correlation coefficient across groups (Robinson's 48 states, below) or an ecological regression slope, such as the change in a county's death rate per unit of county air pollution (vignette 1). These numbers describe places, not the risk of anyone living in them. (Prevalence also drives predictive values: see prevalence and PPV/NPV.)
Ecological studies: the group is the unit
In an ecological study, the units of analysis are groups of people, often defined geographically, and exposures and outcomes are aggregated, often known only at the population level. Morgenstern classified these studies on two dimensions: whether exposure is measured (exploratory studies compare outcome rates across groups without exposure data; analytic studies relate exposure levels to outcome rates) and whether groups are formed by place (multiple-group), by time (time-trend) or by both (mixed). Common forms:
- Geographic comparisons. Coronary heart disease mortality in local areas of England and Wales has been correlated with neonatal mortality in the same places 70 and more years earlier, generating the hypothesis that coronary disease may result from impaired development in fetal life and infancy.
- Time trends. Rising melanoma incidence in Britain was linked with greater sun exposure from fashions in dress and holidays abroad; changes in diagnostic criteria and techniques can bias such trends.
- Mixed designs combine the two, comparing many groups over time; one study related cash-transfer and primary care coverage to new leprosy cases in 1,358 Brazilian municipalities from 2004 to 2011.
- Migrant studies. Second-generation Japanese migrants to the USA have substantially lower stomach cancer rates than people in Japan, pointing to an environmental cause.
Strengths. Ecological studies are quick and cheap, often built from published statistics. Aggregate data can even beat individual measurement: alcohol tax revenue records may describe drinking more accurately than personal reports, and air pollution is more feasibly measured by ambient monitors. They are the right design when the question is about groups, such as a policy's effect on a community's health, and Freedman credits them with important insights for Snow (cholera), Goldberger (pellagra) and Dean (fluorosis and dental caries).
Weaknesses. Exposure is a group average, as if everyone in a county had the same exposure. Areas differ in how they diagnose and report disease: general practitioner consultations for back pain were more frequent in northern than southern Britain, yet back symptoms were similarly common, because consultation habits differed. Age and sex can be allowed for by standardizing rates, but other individual-level confounders cannot be adjusted for person by person.
The ecological fallacy: Robinson's classic example
The ecological fallacy is the mistaken assumption that an association observed between two group-level variables equals the association between the corresponding variables in individuals; it is sometimes called aggregation bias or cross-level bias. Aggregates give the margins of each group's 2 × 2 table (how many are exposed, how many are ill) but not the cells inside it, so they never show whether the exposed people are the ill ones.
Robinson (1950). For each of the 48 US states in the 1930 census, Robinson took the percentage of residents aged 10 or older who were foreign-born and the percentage who were literate.
| Level of analysis | Correlation between foreign birth and literacy |
|---|---|
| 48 states | +0.53 |
| Individual people | −0.12 |
The state-level correlation suggests that the foreign-born were more literate; in individuals the association was negative, because the foreign-born tended to live in states where the native-born were relatively literate.
Other classics:
- Durkheim: in 19th-century Europe, suicide rates were higher in more heavily Protestant countries, but Protestant and Catholic countries differed in many ways besides religion, and the data never tied individual suicides to any faith.
- Dietary fat and breast cancer: breast cancer death rates were higher in countries where fat made up more of the diet; later individual-level data cast serious doubt on the link.
- Chocolate and Nobel prizes: a tongue-in-cheek analysis correlated per capita chocolate consumption with Nobel laureates in 23 countries; its author noted that a correlation can mean X influences Y, Y influences X (reverse causation), or both share a common mechanism (confounding).
When a stem asks why group-level results cannot be applied to individual patients, the answer is the ecological fallacy. The fix is individual-level data: a cohort or case-control study, or individual records linked to each person's own exposure.
Temporality: the limit both designs share
The USMLE outline lists temporality and reverse causality under causation, and neither design establishes temporality.
- Cross-sectional: an association can run backward. If milk drinking is linked to peptic ulcer, milk might cause ulcers, or people with ulcers may drink milk to relieve symptoms; in a survey, people with obesity may report eating more salads because they have already changed their habits. The exception is an exposure fixed before the outcome, such as a lifelong attribute; causal inference also requires a stable population, no selective survival, equal disease duration across exposure groups and no reverse causation.
- Ecological: group data add temporal ambiguity and an unknown lag between exposure and outcome. Loney and Nagelkerke argue that time series of short-term changes, such as daily air pollution against hospital admissions, are more defensible, because largely the same people are observed across periods and confounders such as temperature can be measured.
Establishing temporality takes exposure measured before outcome in individuals: a cohort study, or a randomized controlled trial, the gold standard when assigning the exposure is ethical. See the RCT design breakdown.
Where cohort, case-control, serial cross-sectional and multilevel designs fit
| Design | Unit and how participants are chosen | Direction in time | Main measure | Best for | Classic weakness |
|---|---|---|---|---|---|
| Cross-sectional | Individuals, by inclusion criteria only | One point in time | Prevalence; prevalence ratio or odds ratio | Disease burden, planning, hypotheses | No temporality; mixes cause with survival |
| Serial cross-sectional | A new sample of individuals each round (NHANES, BRFSS) | Repeated snapshots | Prevalence over time | Monitoring trends | No one is followed, so no individual incidence |
| Ecological: multiple-group, time-trend or mixed | Groups: places or periods | One period or over time | Correlation or regression across groups | Population-level exposures and policies | Ecological fallacy; group-level confounding |
| Multilevel | Individuals nested in groups (people in areas) | Any | Individual and group-level (contextual) effects together | Separating personal from contextual effects | Needs individual data linked to groups |
| Case-control | Individuals, by outcome: cases vs controls | From disease back to past exposure | Odds ratio | Rare diseases, long latency | Recall bias; choosing controls |
| Cohort, prospective or retrospective | Individuals, by exposure | From exposure forward to new disease | Incidence; relative risk | Rare exposures; several outcomes | Cost and time; losses to follow-up |
Multilevel analysis models individuals (level 1) within groups (level 2) simultaneously, estimating personal and group-level effects and their interactions instead of forcing a choice between an individual-only and a group-only analysis.
Drill the individual-level designs with the cohort vs case-control Q-bank breakdown, the draw-it-out method and relative risk vs odds ratio, and pooled evidence with the meta-analysis breakdown.
How USMLE stems signal each design
| Stem clue | Design | What they usually ask next |
|---|---|---|
| "Survey," "questionnaire," "at one point in time," "a representative sample was telephoned and asked whether they currently have heart disease" | Cross-sectional | Which measure (prevalence); why causation can't be inferred |
| "A new national sample each year," NHANES or BRFSS data across years | Serial cross-sectional | Trend in prevalence; why it isn't a cohort |
| "Country-level data," "rates by state," "county death rates," "per capita consumption," "correlation across 23 countries" | Ecological | Main limitation (ecological fallacy); which study would test it in individuals |
| "Rates in one population before and after a law or tax" | Ecological time-trend | Bias from changes in diagnosis or recording over the period |
| "Patients with new-onset disease and controls without it were asked about past exposures" | Case-control | Odds ratio; recall bias |
| "Troops who served in a war zone and troops who served elsewhere were tracked for cancer" | Cohort | Incidence; relative risk |
More biostatistics practice questions and study-design guides are collected on the Biostatistics & Epidemiology hub.
Pitfalls and USMLE traps
| Trap | What's actually true |
|---|---|
| Data from a single year make it cross-sectional | Group rates or averages make it ecological, whatever the timing |
| An odds ratio means case-control | Cross-sectional studies report odds ratios too; check how participants were selected |
| An annual national survey is a cohort | A new sample each round makes it serial cross-sectional |
| Ecological studies are always inferior | For group-level questions, such as a policy's effect on a community, they are the most appropriate design |
Prevalence-incidence (Neyman) bias. Studies of existing (prevalent) cases miss people who died quickly or recovered. As Sackett wrote in 1979, a late look at those exposed or affected early "will miss fatal and other short episodes, plus mild or 'silent' cases and cases in which evidence of exposure disappears with disease onset." Excluding deaths makes a disease look milder; excluding recoveries makes it look more severe. Case-control studies are the most susceptible, but cross-sectional studies are affected too; the remedy is to study incident cases. More named biases are in bias types for Step 1.
Group-level confounding. Groups differ in many ways besides the exposure: Durkheim's Protestant and Catholic countries differed in far more than religion. Ecological confounding can sit at the individual level, the group level or across levels, a group-level confounder need not be associated with the exposure in every group, and ecological adjustment can even worsen the bias.
The atomistic (individualistic) fallacy is the mirror image of the ecological fallacy: analyzing only individuals and ignoring context, so that important group-level effects are missed, as when unemployment is studied with personal characteristics alone while local labor market conditions are ignored. Some exposures act through the group: the risk of a sexually transmitted infection depends on personal behavior and on how common the infection is in the population. Multilevel models help avoid both fallacies.
Worked vignettes
Vignette 1. Investigators ask whether long-term exposure to fine particulate matter (PM2.5) worsens COVID-19 outcomes. Only area-level death counts are publicly available, so for 3,089 US counties they obtain the 2000–2016 average PM2.5 concentration and the cumulative COVID-19 death rate through June 2020. After adjustment for 20 county-level covariates, each 1 μg/m³ increase in PM2.5 is associated with an 11% higher county mortality rate. Which statement is most accurate?
- A. A cross-sectional study, so each resident's risk of dying rises 11% per 1 μg/m³
- B. An ecological study, whose result cannot be applied directly to individual patients
- C. A prospective cohort study, because exposure preceded the deaths
- D. A case-control study comparing high-death and low-death counties
- E. Proof that PM2.5 causes COVID-19 deaths, because confounders were adjusted for
Answer: B. Every variable is a county aggregate, so the result cannot be applied to individuals (that would be the ecological fallacy), and individual risk factors such as age, sex and race cannot be adjusted for. The next step is individual-level health records, with each patient's address linked to air pollution data.
- A is the tempting distractor: the authors' own preprint called the design cross-sectional, but no person's exposure is linked to that person's death.
- C: nobody was enrolled by exposure and followed.
- D: a case-control study selects individual cases and controls by disease status.
- E: county-level adjustment leaves individual-level confounding untouched.
Vignette 2. At an STI clinic, 300 patients are tested for HIV antibodies at their first visit, and their sex is recorded. Of 200 men, 50 test positive; of 100 women, 10 test positive. Name the design, the HIV prevalence and the measures of association between male sex and HIV.
Answer: Cross-sectional; prevalence 20% (60/300); prevalence odds ratio 3.0, (50 × 90)/(10 × 150); prevalence ratio 2.5 (25% vs 10%).
Reasoning: Patients were selected neither by HIV status nor by sex, and both were recorded at one visit. Nobody was followed, so incidence and relative risk are unavailable, and with a common outcome the odds ratio overstates the prevalence ratio. Sex is fixed long before infection, so reverse causation is not the worry; the bigger limitation is that a clinic sample may not generalize to the community.
Key takeaways
- The unit of analysis decides it: individuals point to cross-sectional; groups point to ecological, even with single-year data.
- Cross-sectional = prevalence (prevalence ratio or odds ratio); no incidence, relative risk or temporality.
- Prevalence ≈ incidence × duration, so snapshots overrepresent long-lasting cases.
- Ecological = group correlations; watch for the ecological fallacy (Robinson: +0.53 across states, −0.12 across individuals) and group-level confounding.
- The atomistic fallacy is the reverse error; multilevel analysis handles both levels.
- Cohort studies (rare exposures, incidence, relative risk) and case-control studies (rare diseases, odds ratio) test the hypotheses both designs generate.
Sources
- USMLE Content Outline — Federation of State Medical Boards and NBME (2026)
- Principles of Epidemiology, Lesson 1, Section 7: Analytic Epidemiology — CDC (2012)
- Principles of Epidemiology, Lesson 3, Section 2: Morbidity Frequency Measures — CDC (2012)
- Coggon D, Rose G, Barker DJP. Epidemiology for the Uninitiated, 4th ed., Chapter 2: Quantifying disease in populations — The BMJ (1997)
- Coggon D, Rose G, Barker DJP. Epidemiology for the Uninitiated, 4th ed., Chapter 6: Ecological studies — The BMJ (1997)
- Coggon D, Rose G, Barker DJP. Epidemiology for the Uninitiated, 4th ed., Chapter 8: Case-control and cross sectional studies — The BMJ (1997)
- Epidemiology Of Study Design — StatPearls, NCBI Bookshelf (2023)
- Bovbjerg ML. Study Designs Revisited, Foundations of Epidemiology — Oregon State University (2020)
- Introduction to study designs: cross-sectional studies — Health Knowledge, Faculty of Public Health (n.d.)
- Setia MS. Methodology Series Module 3: Cross-sectional Studies — Indian Journal of Dermatology (2016)
- Reichenheim ME, Coutinho ESF. Measures and models for causal inference in cross-sectional studies — BMC Medical Research Methodology (2010)
- Freedman DA. Ecological Inference and the Ecological Fallacy — UC Berkeley Department of Statistics (1999)
- Robinson WS. Ecological correlations and the behavior of individuals — American Sociological Review (1950)
- Subramanian SV, et al. Revisiting Robinson: the perils of individualistic and ecologic fallacy — International Journal of Epidemiology (2009)
- Morgenstern H. Ecologic studies in epidemiology: concepts, principles, and methods — Annual Review of Public Health (1995)
- Neumark Y. What can ecological studies tell us about death? — Israel Journal of Health Policy Research (2017)
- Loney T, Nagelkerke NJ. The individualistic fallacy, ecological studies and instrumental variables — Emerging Themes in Epidemiology (2014)
- Wu X, et al. Air pollution and COVID-19 mortality in the United States: Strengths and limitations of an ecological regression analysis — Science Advances (2020)
- Wu X, et al. Exposure to air pollution and COVID-19 mortality in the United States: A nationwide cross-sectional study — medRxiv preprint of the Science Advances paper (2020)
- Nery JS, et al. Effect of the Brazilian conditional cash transfer and primary health care programs on the new case detection rate of leprosy — PLoS Neglected Tropical Diseases (2014)
- Tranmer M. Multilevel models for macro and micro data, 5.4 — University of Manchester, via National Centre for Research Methods ReStore (2007, updated 2014)
- Spencer EA, Heneghan C. Prevalence-incidence (Neyman) bias — Catalogue of Bias (2017)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
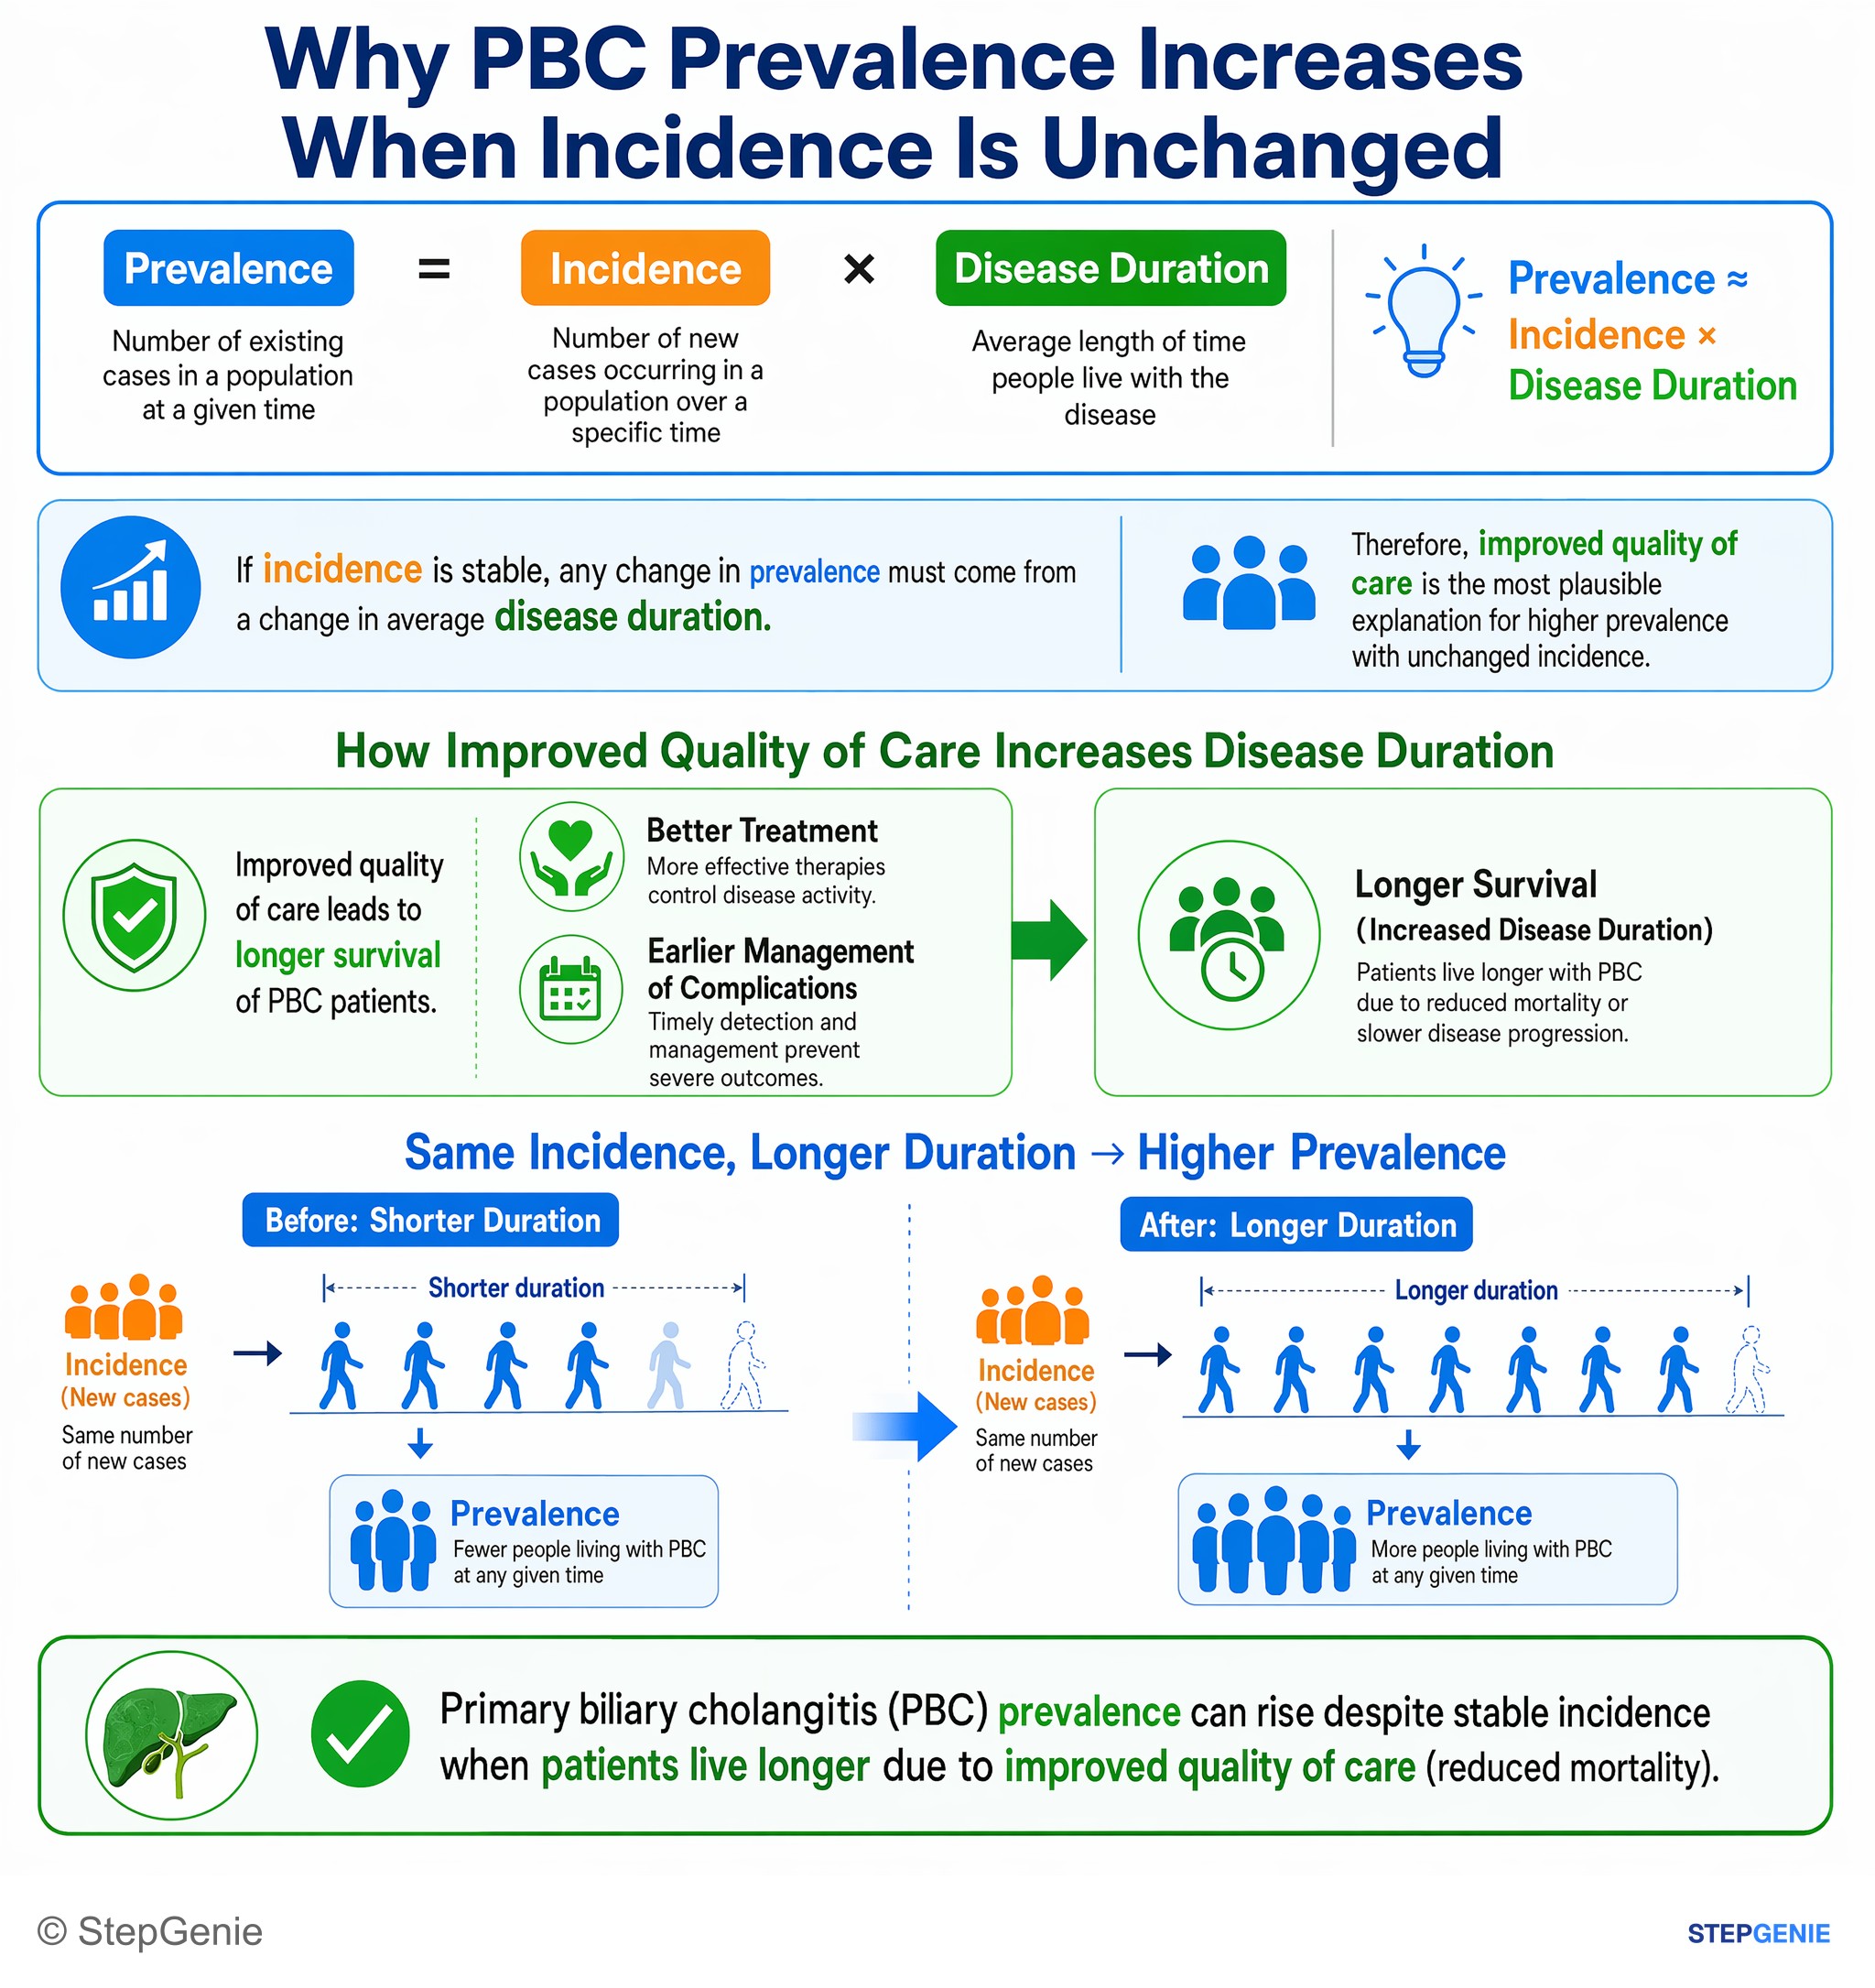
Primary biliary cholangitis prevalence can rise despite stable incidence when patients live longer due to improved quality of care…
USMLE Step 1Frequently Asked Questions
What is the difference between a cross-sectional study and an ecological study?
The difference is the unit of analysis. A cross-sectional study measures exposure and outcome in individual people at one point in time, so it can link each person's exposure to that person's outcome and yields prevalence, a prevalence ratio or a prevalence odds ratio. An ecological study compares groups such as counties, states or countries using aggregate rates or averages, so it yields only group-level correlations and is open to the ecological fallacy.
Is an ecological study the same as a cross-sectional study?
No. An ecological study often uses data from a single period, and some authors even label such analyses cross-sectional, but its unit of analysis is the group, not the person. If a question gives only state, county or country rates and averages, the design is ecological even when exposure and outcome were measured in the same year. A cross-sectional study needs exposure and outcome data for each individual participant.
What is the ecological fallacy?
The ecological fallacy is assuming that an association seen between groups also holds for the individuals in those groups. In Robinson's classic analysis of the 1930 US census, states with a higher percentage of foreign-born residents had higher literacy (correlation +0.53), yet among individuals, foreign birth was associated with lower literacy (correlation −0.12), because immigrants tended to live in states where native-born residents were relatively literate.
Does a cross-sectional study measure prevalence or incidence?
A cross-sectional study measures prevalence, the proportion of people who have a condition at a point in time or over a short period, and expresses associations as a prevalence ratio or prevalence odds ratio. It cannot measure incidence or relative risk, because nobody is followed to count new cases; that requires a cohort study. Because prevalence reflects both incidence and how long a disease lasts, snapshots overrepresent long-lasting cases.
Can a cross-sectional or ecological study prove causation?
No. A cross-sectional study measures exposure and outcome at the same time, so it cannot show which came first and is open to reverse causation, as when people change their habits after developing a condition. An ecological study adds the ecological fallacy, an unknown lag between exposure and outcome, and confounding by other differences between groups. Both mainly generate hypotheses, which cohort studies and randomized trials then test in individuals.
How do USMLE questions signal a cross-sectional versus an ecological study?
Cross-sectional stems describe individuals measured once: a survey or questionnaire, data collected at one point in time, or a representative sample asked whether they currently have a disease. Ecological stems give only group numbers: country-level data, rates by state or county, per capita consumption, or a correlation across countries. Typical follow-up questions ask what a cross-sectional study measures (prevalence) or the main limitation of an ecological study (the ecological fallacy).