Septic arthritis is infection of a joint space, usually by bacteria, and it is an emergency: nongonococcal infection can destroy articular cartilage within hours or days. Staphylococcus aureus is the most common cause in adults, while Neisseria gonorrhoeae is the classic cause in sexually active young adults, often with tenosynovitis and pustular skin lesions. The key step is urgent arthrocentesis: a synovial white cell count usually above 50,000/µL with neutrophil predominance, plus Gram stain, culture and crystal analysis (crystals do not exclude infection). Then start empiric IV antibiotics chosen by the Gram stain (vancomycin, plus ceftriaxone when gram-negative or gonococcal infection is possible) and drain the joint.
Organisms by host: who gets what
| Host or setting | Most likely organisms | Exam clue |
|---|---|---|
| Adults overall | S. aureus (most common); beta-hemolytic streptococci, pneumococci | Hot knee in an older adult or a patient with RA or diabetes |
| Sexually active young adult | N. gonorrhoeae (classic exam answer; Merck: only slightly over 1% of all cases) | Migratory polyarthralgia, tenosynovitis, skin pustules; often no genital symptoms |
| Injection drug use, indwelling catheters | S. aureus, gram-negative rods (e.g., Pseudomonas aeruginosa), streptococci, Candida | Axial joints: sternoclavicular, sacroiliac, symphysis pubis |
| Immunosuppressed or serious comorbidity | Gram-negative rods; Salmonella (particularly in SLE); mycobacteria, fungi | Ask for mycobacterial and fungal cultures |
| Prosthetic joint | Early (within 3 months): S. aureus in about half; delayed (3-12 months, acquired at surgery): low-virulence coagulase-negative staphylococci, Cutibacterium acnes (shoulder); late (over 12 months): hematogenous seeding | Biofilm; lower synovial WBC cut-offs |
| Sickle cell disease | Salmonella (linked to sickle cell); S. aureus | See the caveat below |
| Neonates | Group B streptococcus, E. coli, S. aureus | Pseudoparalysis of a limb, irritability, poor feeding |
| Young children | S. aureus, S. pyogenes, S. pneumoniae, Kingella kingae | Kingella is now a major cause (Merck) |
The sickle cell caveat. Salmonella is the classic sickle cell organism for osteomyelitis (Merck), and StatPearls links Salmonella infection to sickle cell disease, but S. aureus remains the most frequent cause of septic arthritis in adults, so a hot joint in sickle cell disease still needs aspiration and S. aureus coverage. Compare the osteomyelitis guide and the sickle cell disease question.
Why it is an emergency
- Routes in: direct penetration (trauma, surgery, arthrocentesis, bites), spread from adjacent infection (osteomyelitis, soft-tissue abscess, infected wound), or hematogenous spread from a remote site.
- Damage: organisms multiply in the synovial fluid and lining, and articular cartilage can be destroyed within hours or days (Merck). After 10-14 days untreated, x-rays may show joint-space narrowing and erosions.
- Risk factors (Merck): older age, rheumatoid arthritis, immunosuppressive therapy, diabetes, cancer, hemodialysis, alcohol use disorder, injection drug use, prosthetic joints, prior joint infection, arthrocentesis, bacteremia, skin infections, hemophilia, sickle cell disease.
- Outcome: 90-day mortality about 7% and poor function in about 24-33% (AAFP); worse in RA, while gonococcal arthritis does not usually damage joints permanently (Merck).
Presentation
- Acute (hours to days) moderate to severe joint pain, warmth, tenderness, effusion and restricted active and passive motion.
- Monoarticular in about 80% of adults with nongonococcal arthritis, most often the knee, then the hip and shoulder; in children at least 90% are monoarticular (knee, hip, ankle).
- Fever: many, but not all, patients are febrile, so a normal temperature does not exclude infection.
Disseminated gonococcal infection (DGI)
DGI follows bloodstream spread in under 1% of gonococcal infections, mostly in women (Merck). It presents in two overlapping ways:
- Arthritis-dermatitis syndrome (the classic triad): fever with migratory polyarthralgia, tenosynovitis (often several tendons of the hands and wrists) and skin lesions: small, slightly painful pustules, papules, petechiae or hemorrhagic vesicles on an erythematous base, mainly on the limbs.
- Purulent mono- or oligoarthritis of a knee, ankle, wrist or elbow.
Diagnosis. AAFP gives synovial counts of about 34,000-68,000/µL, a Gram stain positive in fewer than half and a culture positive in roughly 25-70%; Merck's gonorrhea chapter is more optimistic, saying joint-fluid cultures are usually positive in the purulent-arthritis form. CDC advises NAAT and culture from every exposed site (urethra or cervix, rectum, pharynx) plus specimens from disseminated sites (blood, skin lesions, synovial fluid). Blood cultures are positive in about 30-40% in the first week (Merck), and synovial PCR can be positive when culture is negative.
Treatment (CDC 2021 STI guidelines, still current in 2026). Ceftriaxone 1 g IV or IM every 24 hours, switching to an oral agent guided by susceptibility testing 24-48 hours after substantial improvement, for at least 7 days in total; add doxycycline 100 mg twice daily for 7 days if chlamydia has not been excluded. More in the Neisseria gonorrhoeae visual hack.
Arthrocentesis first: reading the tap
Merck: arthrocentesis is indicated for every acute or unexplained monoarticular effusion, and synovial fluid examination is the most accurate way to exclude infection. AAFP advises sending cell count with differential, Gram stain, culture and crystals before starting antibiotics.
| Fluid (AAFP) | WBC/µL | Neutrophils | Gram stain | Culture |
|---|---|---|---|---|
| Normal | <200 | <25% | Negative | Negative |
| Noninflammatory (e.g., osteoarthritis) | 200-2,000 | <25% | Negative | Negative |
| Crystal disease | 2,000-100,000 | >50% | Negative | Negative |
| Gonococcal | 34,000-68,000 | >75% | Positive in <50% | Positive in 25-70% |
| Nongonococcal septic | >50,000 (>100,000 more specific) | >75% | Positive in 60-80% | Positive in >90% |
Traps in the numbers:
- A count below 50,000/µL does not exclude infection: counts can be lower early or after partial treatment (Merck); above 100,000 is more specific (AAFP). Merck's general classification puts infectious fluid anywhere from 5,000 to more than 100,000/µL, usually with more than 85% neutrophils.
- Prosthetic joints use lower cut-offs: typically above 10,000/µL in early and above 3,000/µL in delayed or late infection (Merck).
- Gram stain shows organisms in only 50-75% of acute bacterial arthritis (Merck); culture is definitive.
- Crystals do not exclude infection: gout or pseudogout can coexist with a septic joint.
- Blood cultures are usually drawn, but negative results do not exclude infection. ESR and CRP are sensitive at low cut-offs but nonspecific; serum procalcitonin is more specific (AAFP).
Treatment: antibiotics by Gram stain, plus drainage
| Gram stain or setting | Empiric choice |
|---|---|
| Gram-positive cocci | Vancomycin (covers MRSA); narrow to nafcillin or cefazolin for MSSA |
| No organisms seen, infection still suspected | Vancomycin (Merck: when S. aureus is suspected), usually plus gram-negative cover: a third-generation cephalosporin such as ceftriaxone (StatPearls) or ceftazidime or an aminoglycoside (AAFP) |
| Gram-negative diplococci, or a DGI picture | Ceftriaxone, plus doxycycline if chlamydia is not excluded |
| Gram-negative rods (injection drug use, immunosuppression) | Antipseudomonal agent: ceftazidime, cefepime or piperacillin-tazobactam |
- Drain the joint: large-bore needle aspiration at least daily, arthroscopic lavage or arthrotomy; Merck notes arthroscopy seems preferable because of fewer complications. AAFP: in cohort studies medical management was not inferior to surgery, but about 30% ultimately needed surgery, including about half of hip and shoulder cases.
- Duration (nongonococcal): IV until improvement is clear, then high-dose oral therapy for another 2-4 weeks; staphylococcal infections need at least 3, often 4 or more, weeks (Merck). Children who improve quickly without osteomyelitis may need only 10-14 days.
Children: septic hip vs transient synovitis (Kocher criteria)
Transient synovitis is the main look-alike in a limping child, and hip aspiration is the gold standard whenever septic arthritis is suspected (AAFP). The Kocher criteria are:
- Fever (oral temperature above 38.5°C, or 101.3°F)
- Refusal or inability to bear weight
- ESR of 40 mm/h or more
- Peripheral WBC above 12,000/mm³
In Kocher's validation study, having none of the four effectively ruled septic arthritis out and having all four virtually ruled it in (AAFP summary). Caird later added CRP above 2.0 mg/dL (20 mg/L) as a fifth predictor.
Septic arthritis vs gout, pseudogout and reactive arthritis
| Feature | Septic (nongonococcal) | Gout | Pseudogout (CPPD) | Reactive arthritis |
|---|---|---|---|---|
| Typical joint | One large joint, often the knee | First MTP (podagra) | Knee, wrist | Asymmetric oligoarthritis of legs and toes; enthesitis, dactylitis |
| Setting | RA, prosthesis, drug injection, immunosuppression | Serum urate normal in at least 30% during a flare | Hyperparathyroidism, hemochromatosis, hypomagnesemia, hypophosphatasia | Days to weeks after a GU or GI infection |
| Synovial WBC | Usually >50,000/µL | 2,000-100,000/µL, >80% neutrophils | Inflammatory range | Inflammatory range |
| Crystals | None, but crystals can coexist | Needle-shaped, strongly negatively birefringent | Rhomboid or rod-shaped, weakly positive or non-birefringent | None |
| Gram stain and culture | Often positive | Negative | Negative | Negative; organisms cannot be cultured from the joint |
| First move | Antibiotics plus drainage | NSAID, colchicine or glucocorticoid once infection is excluded | Exclude infection and gout | NSAIDs; look for conjunctivitis, urethritis |
Crystal details are in the gout vs pseudogout breakdown; the post-infectious picture is in the reactive arthritis guide.
How USMLE tests it
- Hot swollen joint: the next step is arthrocentesis, not imaging or empiric gout treatment.
- An RA patient with one joint far worse than the rest (especially on methotrexate, prednisone or a TNF inhibitor) has septic arthritis until proven otherwise.
- Young woman with wrist tenosynovitis, hand pustules and migratory joint pain: DGI; send mucosal NAATs and give ceftriaxone.
- Joint replacement 3-12 months ago, now pain and a modest effusion: low-virulence coagulase-negative staphylococci forming biofilm; a sudden infection years later suggests hematogenous seeding.
Practice question
A 67-year-old man has had pain and swelling of the right knee for 1 day, with fever and chills. He has rheumatoid arthritis treated with methotrexate and prednisone. Temperature is 38.9°C (102°F). The knee is hot, swollen and exquisitely tender, and both active and passive motion are severely painful. Arthrocentesis yields turbid fluid with a WBC count of 85,000/µL (90% neutrophils) and no crystals; Gram stain shows gram-positive cocci in clusters. Cultures are pending.
Which is the most appropriate next step in management?
- A. Oral colchicine and an NSAID
- B. Intra-articular triamcinolone injection
- C. Increase the prednisone dose for a rheumatoid flare
- D. IV vancomycin and urgent drainage of the joint
- E. Withhold antibiotics until culture and susceptibility results return
Answer: D. Fever, acute monoarthritis, a synovial WBC of 85,000/µL with neutrophil predominance and gram-positive cocci in clusters mean septic arthritis, most likely S. aureus; RA and immunosuppression raise the risk. Vancomycin covers MRSA until susceptibilities return, and the joint needs drainage by repeated aspiration, arthroscopy or arthrotomy.
- A: colchicine and NSAIDs treat gout, but there are no crystals and the Gram stain shows bacteria; even when crystals are present, infection can coexist.
- B: injecting a corticosteroid into an infected joint worsens the infection and delays treatment.
- C: RA flares are usually polyarticular and never show organisms on Gram stain; one disproportionately inflamed joint in RA is septic until proven otherwise.
- E: cultures are already drawn, so there is no reason to wait; delay risks cartilage destruction and sepsis.
Key takeaways
- Septic arthritis is an emergency: cartilage can be destroyed within hours or days.
- S. aureus is the most common cause in adults; N. gonorrhoeae in sexually active young adults; coagulase-negative staphylococci in delayed (3-12 month) prosthetic infections; Kingella in young children; Salmonella with sickle cell disease, classically as osteomyelitis.
- Arthrocentesis first (cell count, Gram stain, culture, crystals), ideally before antibiotics.
- Nongonococcal fluid is usually >50,000 WBC/µL with >75% neutrophils, but a lower count, a negative Gram stain or crystals do not exclude infection.
- Treat by Gram stain plus drainage: vancomycin for gram-positive cocci, ceftriaxone for gonococcus, antipseudomonal cover for gram-negative rods.
- DGI (CDC 2021): ceftriaxone 1 g IM or IV daily, at least 7 days in total, plus doxycycline unless chlamydia is excluded.
- Pediatric hip: Kocher criteria (fever, non-weight-bearing, ESR ≥40 mm/h, WBC >12,000/mm³), and aspirate when in doubt.
Sources
- Acute Infectious Arthritis — Merck Manual Professional Edition (2024)
- Prosthetic Joint Infectious Arthritis — Merck Manual Professional Edition (2024)
- Osteomyelitis — Merck Manual Professional Edition (2024)
- Gonorrhea — Merck Manual Professional Edition (2026)
- Gonococcal Infections Among Adolescents and Adults — CDC STI Treatment Guidelines (2021)
- Septic Arthritis: Diagnosis and Treatment — American Family Physician (2021)
- Septic Arthritis — StatPearls, NCBI Bookshelf (2023)
- Evaluation of the Patient With Joint Symptoms — Merck Manual Professional Edition (2025)
- Gout — Merck Manual Professional Edition (2025)
- Calcium Pyrophosphate Deposition Disease — Merck Manual Professional Edition (2025)
- The Limping Child: A Systematic Approach to Diagnosis — American Family Physician (2009)
- Septic Arthritis or Transient Synovitis of the Hip? — American Family Physician (2004)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
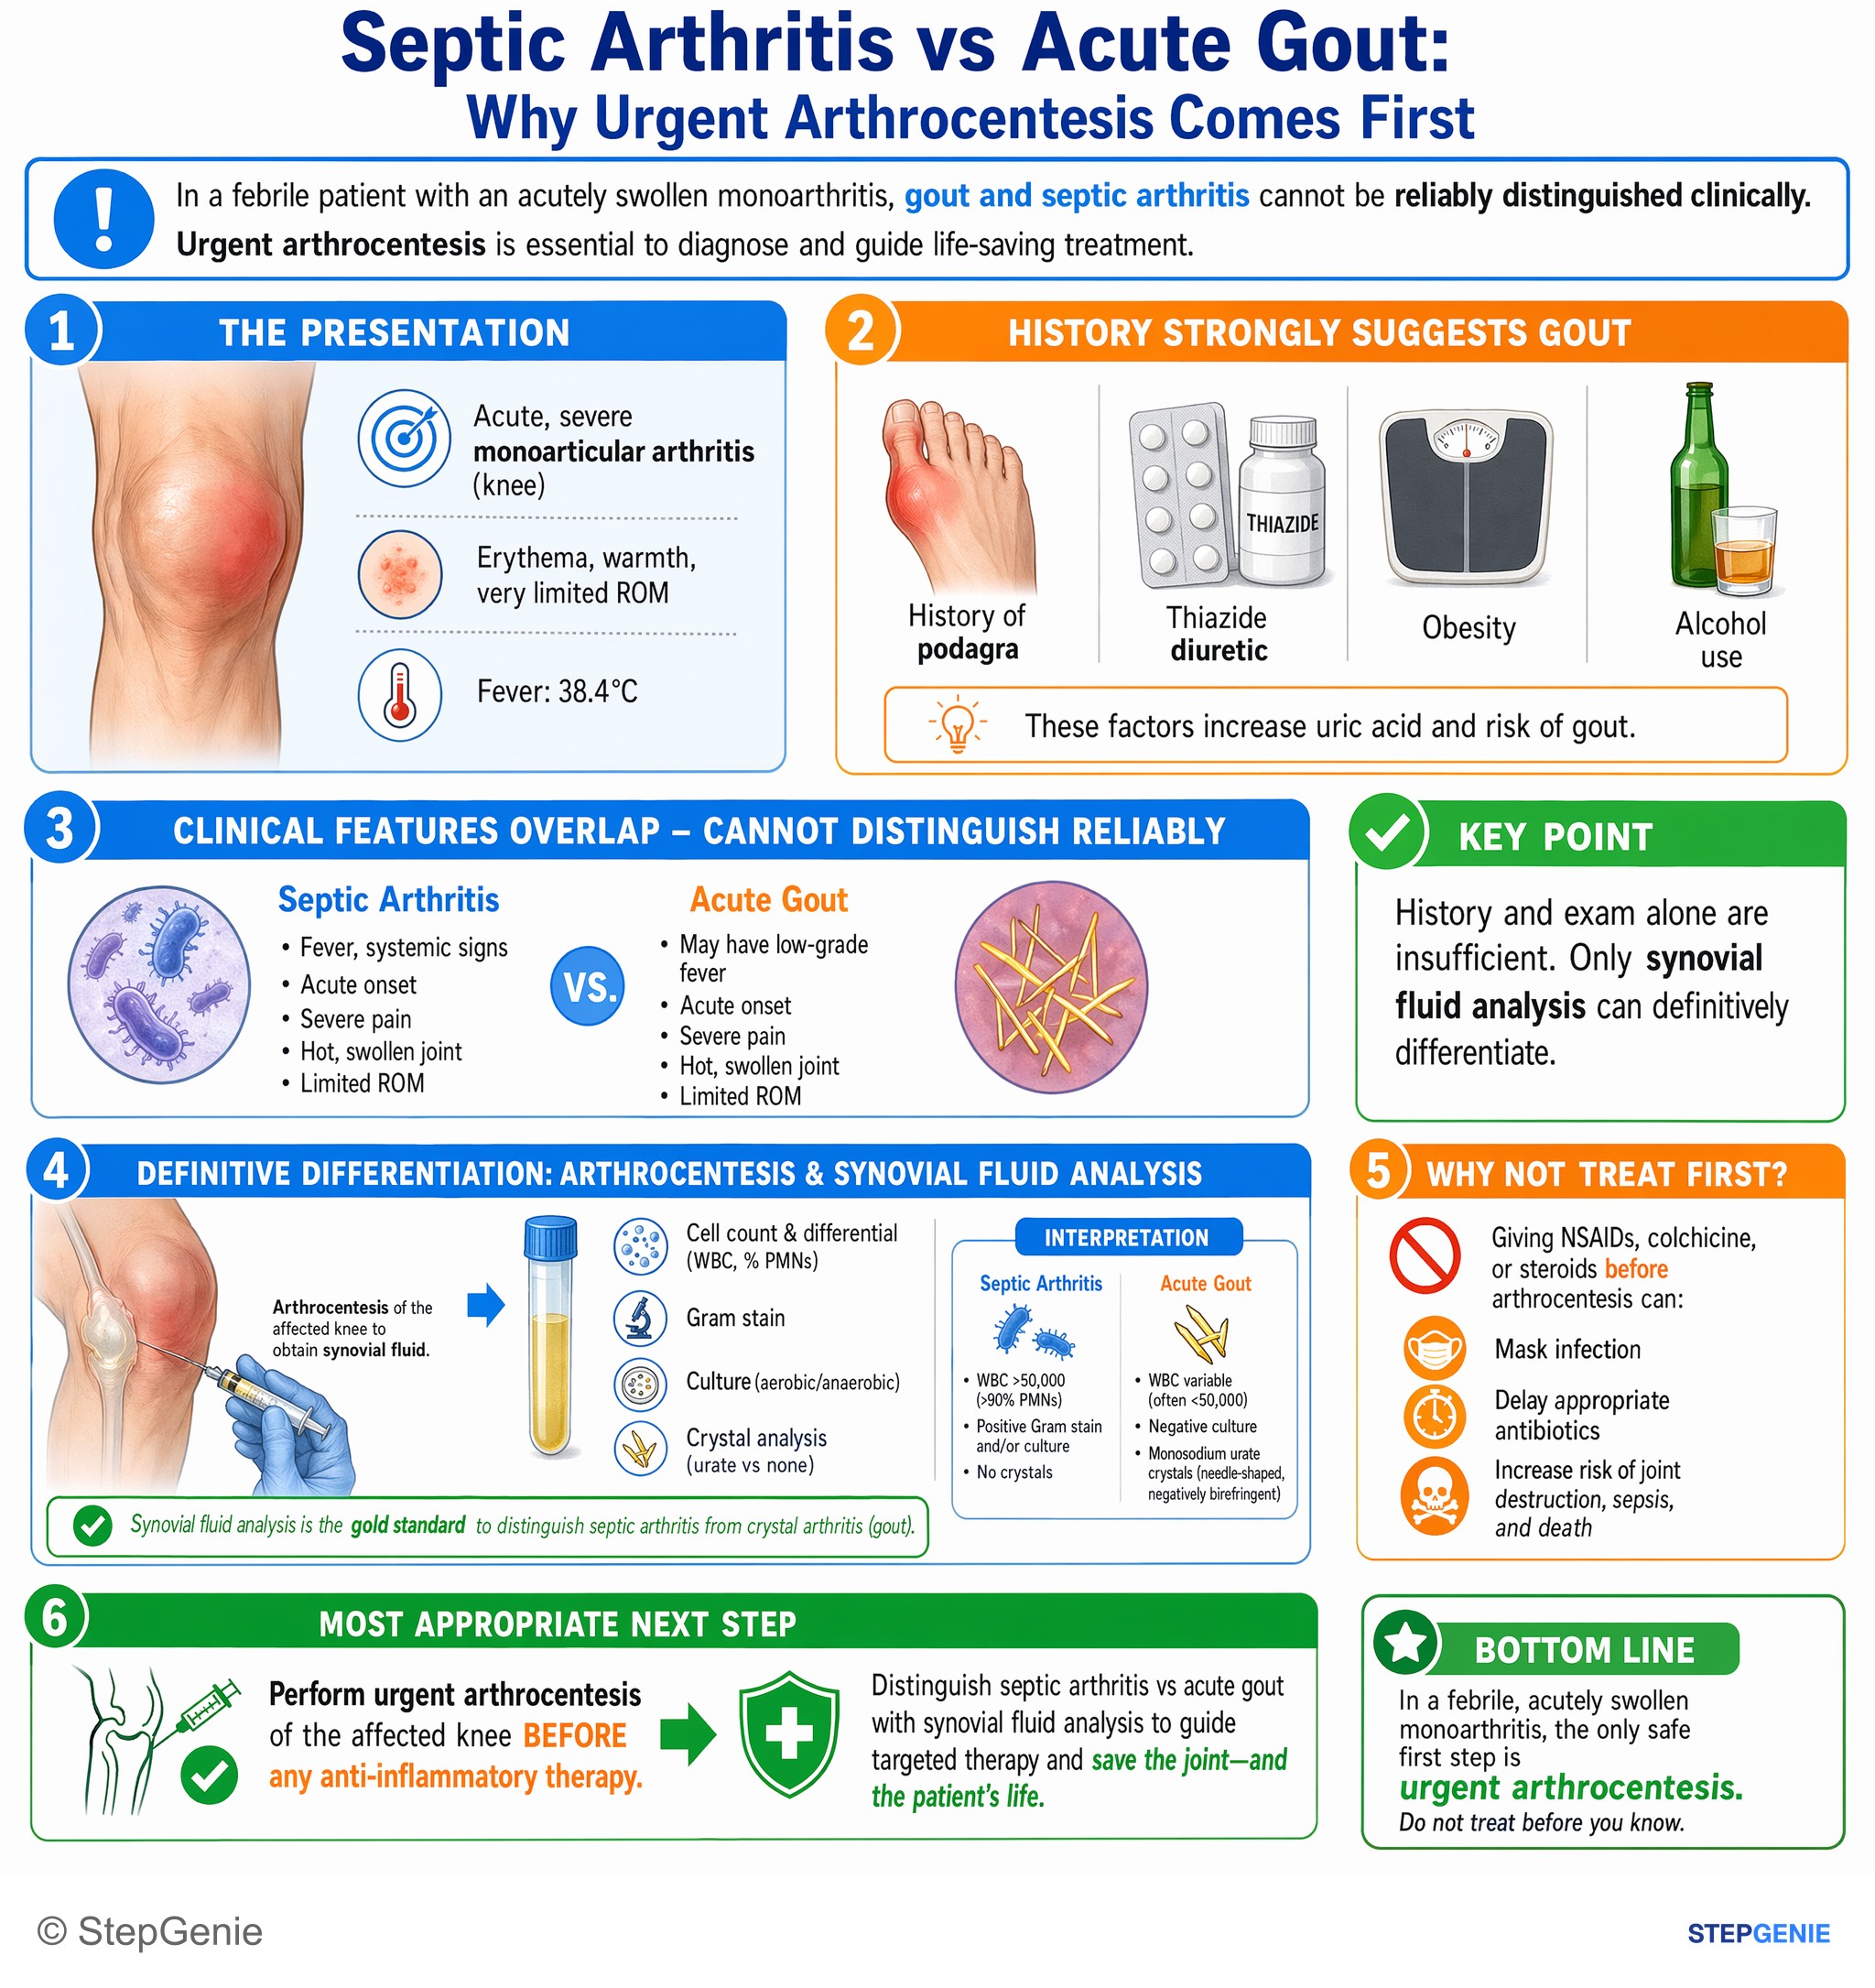
Septic arthritis vs acute gout in a febrile, acutely swollen monoarthritis must be distinguished by urgent arthrocentesis before giving…
USMLE Step 2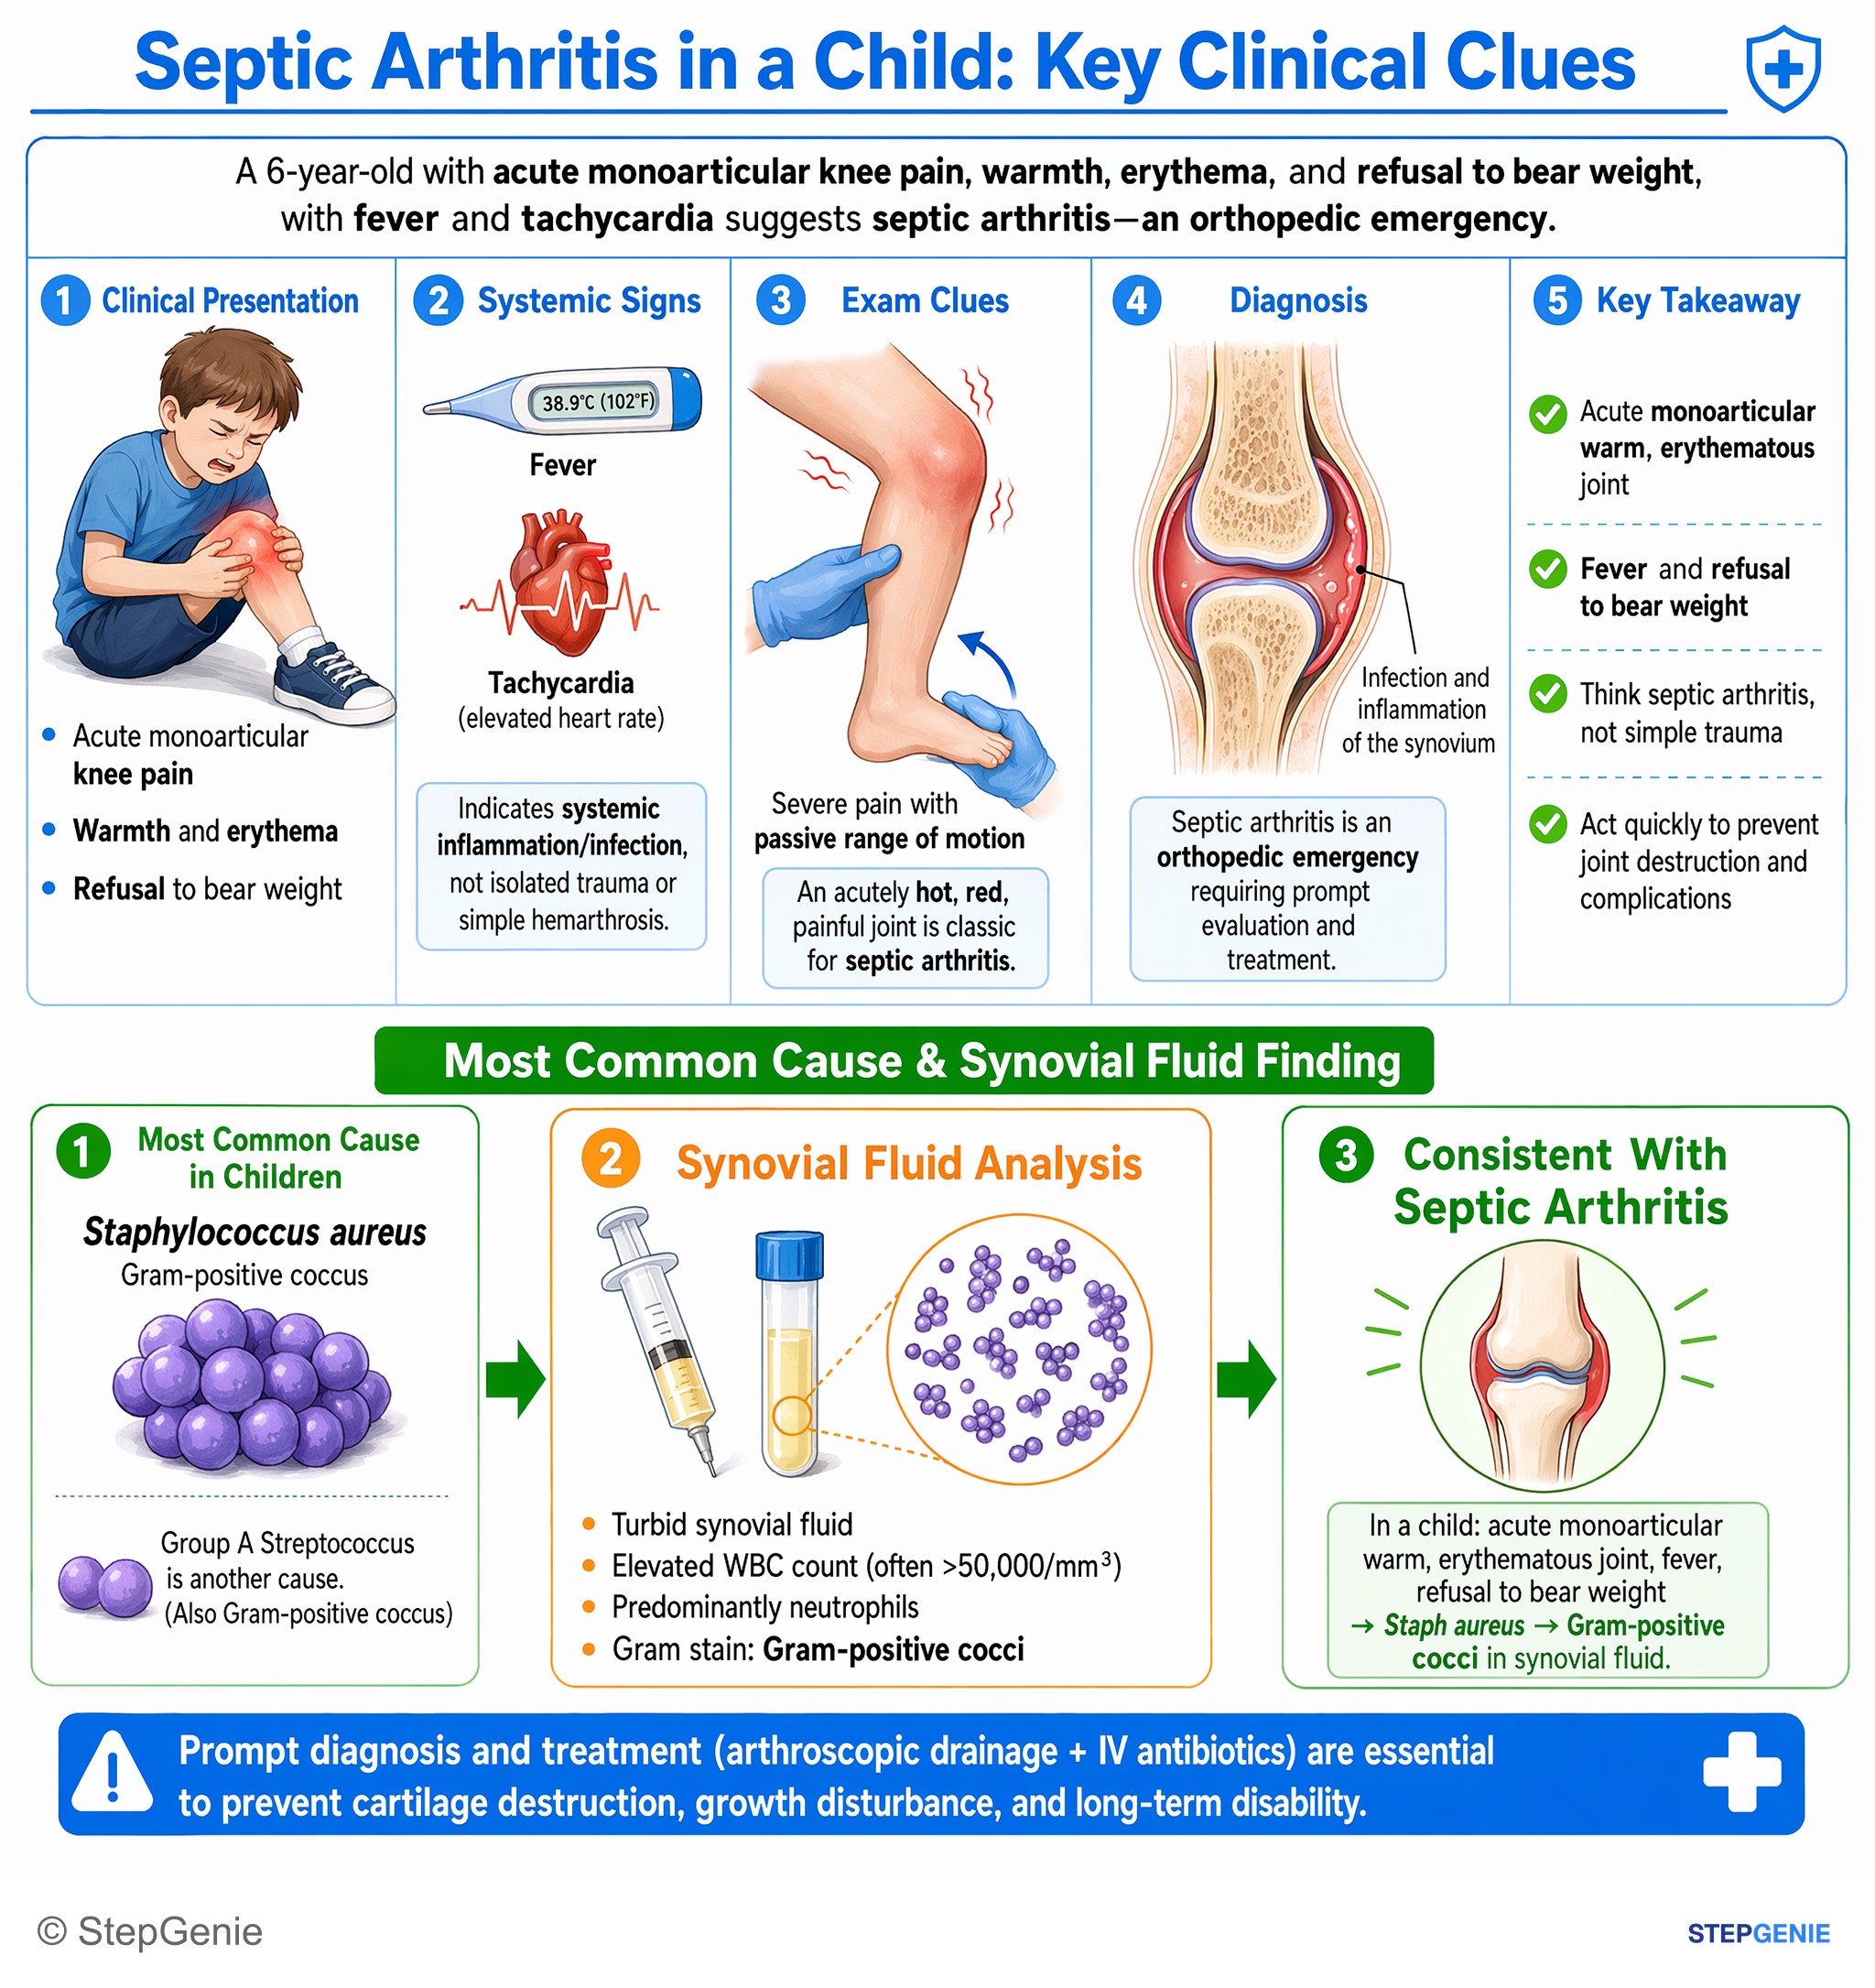
Septic arthritis in a child: acute monoarticular warm, erythematous joint, fever, refusal to bear weight → Staph aureus → Gram-positive…
USMLE Step 2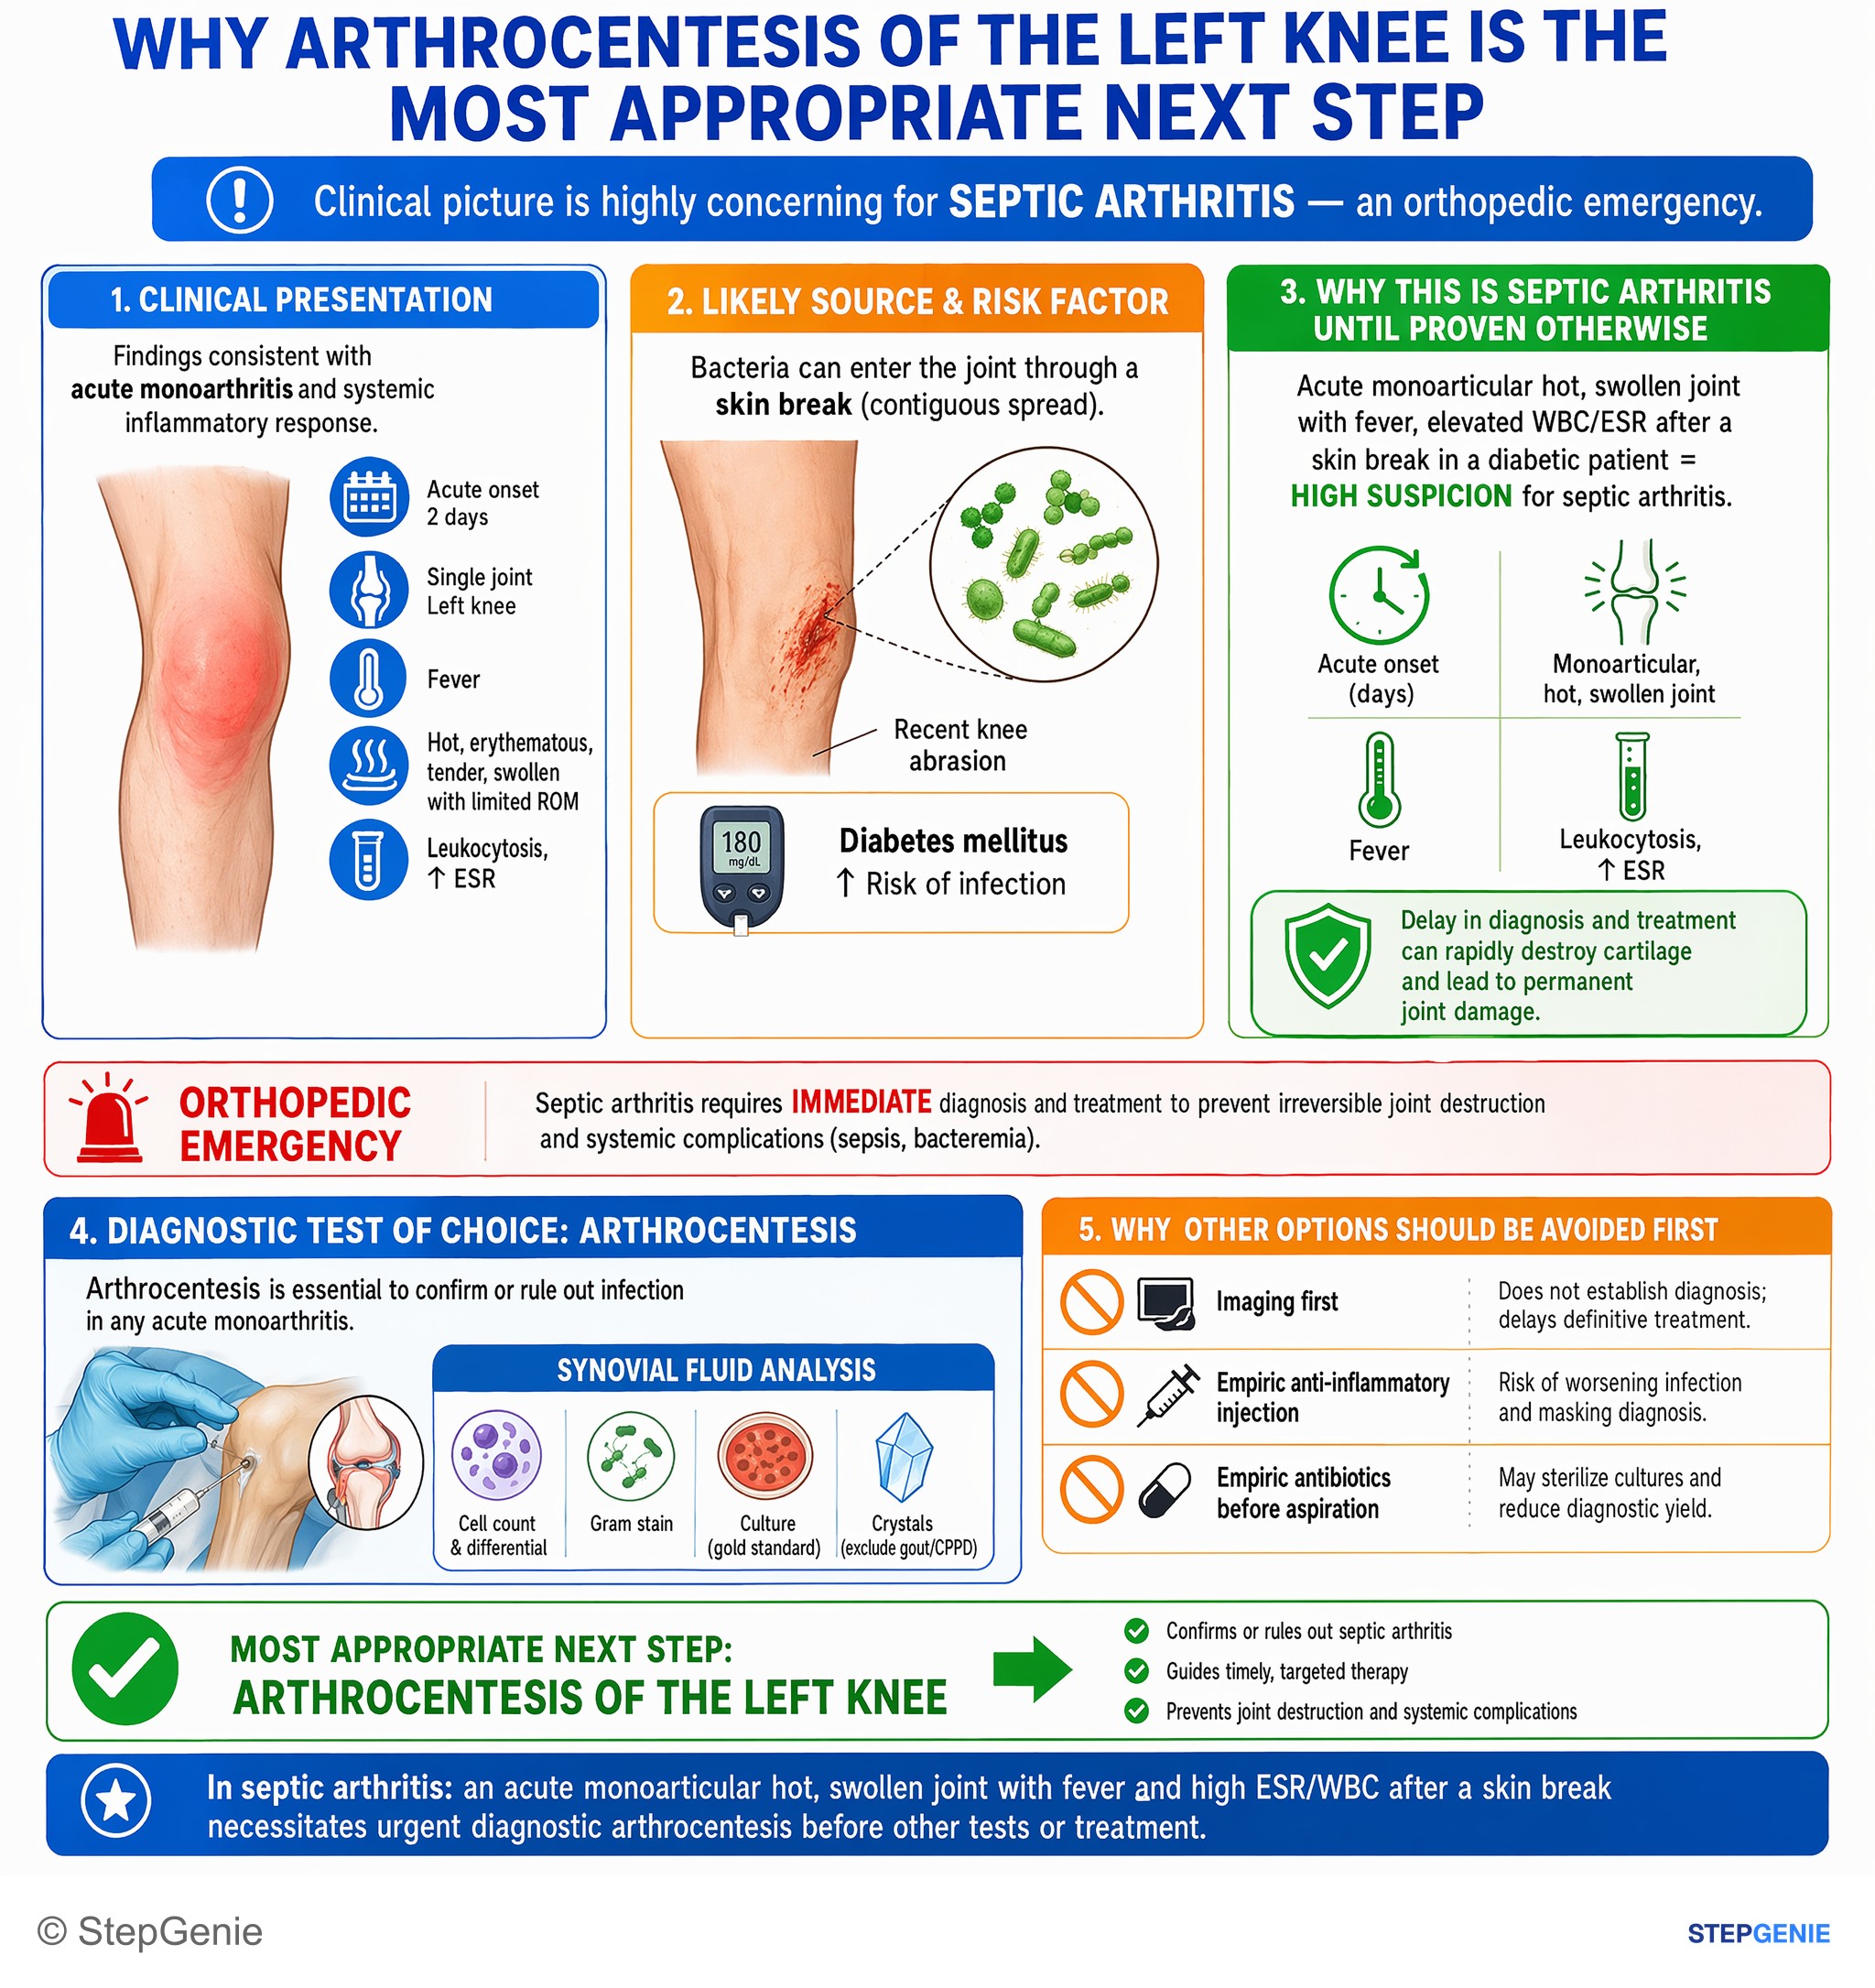
Septic arthritis: acute monoarticular hot, swollen joint with fever and high ESR/WBC after skin break → do urgent diagnostic…
USMLE Step 2Frequently Asked Questions
What is the most common cause of septic arthritis?
Staphylococcus aureus is the most common cause of septic arthritis in adults. Neisseria gonorrhoeae is the classic cause in sexually active young adults, usually with migratory joint pain, tenosynovitis and pustular skin lesions. Other host clues: Pseudomonas and other gram-negative rods in injection drug users, coagulase-negative staphylococci in delayed prosthetic joint infections, Kingella kingae in young children, group B streptococcus in neonates, and Salmonella in sickle cell disease, where it is best known for causing osteomyelitis.
What synovial fluid WBC count indicates septic arthritis?
Nongonococcal septic arthritis usually produces turbid fluid with more than 50,000 white cells per microliter (counts above 100,000 are more specific) and more than 75% neutrophils. A count below 50,000 does not exclude infection, especially in early or partially treated disease, gonococcal arthritis (often about 34,000 to 68,000) or a prosthetic joint, where counts above 3,000 to 10,000 can mean infection. Gram stain finds organisms in only about 50% to 80% of cases depending on the source, so culture is the definitive test.
Do crystals in joint fluid rule out septic arthritis?
No. Merck and AAFP both state that finding crystals does not exclude infection, because gout or pseudogout can coexist with a septic joint. Monosodium urate crystals are needle-shaped and strongly negatively birefringent; calcium pyrophosphate crystals are rhomboid or rod-shaped and weakly positively birefringent or non-birefringent. If the patient is febrile, has risk factors or has a very high synovial white cell count, the Gram stain and culture still decide, and antibiotics should not wait for culture results.
What is the empiric antibiotic treatment for septic arthritis?
After arthrocentesis, choose IV antibiotics by Gram stain: vancomycin for gram-positive cocci, switching to nafcillin or cefazolin if the isolate is methicillin-sensitive. If no organisms are seen but infection is still suspected, vancomycin is usually combined with gram-negative cover such as ceftriaxone or ceftazidime. Gram-negative rods need ceftazidime, cefepime or piperacillin-tazobactam. The joint must also be drained by repeated needle aspiration, arthroscopy or arthrotomy. Staphylococcal infections usually need at least 3 to 4 weeks of therapy.
How does disseminated gonococcal infection present?
Disseminated gonococcal infection develops in under 1% of gonococcal infections, mostly in women. The classic arthritis-dermatitis syndrome combines fever, migratory polyarthralgia, tenosynovitis of the hands and wrists, and small pustular or hemorrhagic skin lesions on the limbs; genital symptoms are often absent. Others have a purulent knee, ankle, wrist or elbow arthritis. Diagnose with NAAT and culture of the urethra or cervix, rectum and pharynx plus blood, skin-lesion and joint-fluid specimens. CDC treatment is ceftriaxone 1 g IM or IV daily, with an optional susceptibility-guided oral switch after substantial improvement, for at least 7 days in total.
What are the Kocher criteria for septic arthritis of the hip?
The Kocher criteria help separate septic arthritis of the hip from transient synovitis in children: fever above 38.5°C, refusal to bear weight, an ESR of 40 mm/h or more, and a peripheral white count above 12,000/mm³. In Kocher's validation study, having none of the four effectively ruled septic arthritis out, and having all four virtually ruled it in. Caird later added CRP above 2.0 mg/dL as a fifth predictor. Hip aspiration remains the gold standard whenever septic arthritis is suspected.