Paget disease of bone (osteitis deformans) is a focal disorder of excessive, disorganized bone remodeling: oversized osteoclasts resorb bone, osteoblasts rush to replace it, and the result is bone that is bigger and more vascular but weaker. The classic patient is an older adult with an isolated high alkaline phosphatase (ALP) and normal calcium and phosphate, plus bone pain, an enlarging skull, a bowed tibia or hearing loss; many people have no symptoms at all. Radiographs and ALP make the diagnosis, and a bone scan maps the extent. Painful disease is treated with a bisphosphonate, and a single 5 mg IV infusion of zoledronic acid is the preferred first-line drug. Osteosarcoma develops in under 1%.
Pathophysiology: three phases
- Osteolytic phase: large osteoclasts with many nuclei (sometimes dozens) resorb bone at an accelerated rate.
- Mixed phase: hyperactive osteoblasts rush to repair the defects.
- Osteosclerotic phase: the repair leaves coarsely woven, thickened trabeculae and cortex.
- The result is enlarged, partly sclerotic bone that is structurally weak, so it bows and fractures despite looking dense.
- Pagetic lesions are metabolically active and highly vascular, and the marrow fills with vascularized fibrous tissue. That explains warmth and redness over affected bone and, rarely, high-output heart failure.
- Histology: irregular bone fragments fitted together like jigsaw-puzzle pieces, the "mosaic" pattern that is the histologic hallmark.
- Cause: genes plus an environmental trigger. Familial clustering occurs in 15-30% of patients, with autosomal dominant inheritance and incomplete penetrance. About 10% of patients carry pathogenic SQSTM1 variants, which increase NF-κB activity in osteoclasts. Inclusions in pagetic osteoclasts resemble paramyxovirus-infected cells, but no virus has been proven to cause the disease.
Who gets it, and which bones
- About 1-2% of the US population, mainly people in middle and older age: the incidence nearly doubles with each decade after 50, and men are affected about 1.5 times as often as women.
- Common in the UK, Spain, France, Italy, Australia, New Zealand and Canada; rare in Scandinavia and Asia; prevalence is falling in many Western countries.
- Most commonly affected bones: pelvis, femur and skull, then tibia, vertebrae, clavicle and humerus. Involvement is usually asymmetric, and single-bone (monostotic) disease is now more common than polyostotic disease.
- Paget disease does not spread to new bones; it progresses within the bones already involved.
Clinical features and complications
| Finding | Explanation |
|---|---|
| No symptoms | Often found from a high ALP or an incidental X-ray |
| Bone pain | Deep and aching, occasionally severe, sometimes worse at night |
| Warm, red skin over bone | Hypervascular pagetic bone |
| Larger head, frontal bossing, dilated scalp veins | Skull involvement; "his hats no longer fit" is the classic stem |
| Hearing loss | Sensorineural, conductive or mixed, from involvement of the petrous temporal bone and cochlea |
| Bowed femur or tibia, pathologic fractures | Enlarged but mechanically weak bone |
| Osteoarthritis | Up to 50% of patients, in joints next to affected bone |
| Spinal stenosis or cord compression | Overgrown vertebral bone |
| High-output heart failure | Rare; large or numerous hypervascular lesions |
| Hypercalcemia | Typically only in immobilized patients; in a walking patient, look for coexisting hyperparathyroidism |
| New severe pain, swelling or a destructive lesion | Osteosarcoma (under 1%) or, rarely, giant cell tumor |
Diagnosis
- ALP is the first-line biochemical test. In Paget disease, ALP of bone origin is high while GGT and 5'-nucleotidase are normal, which points to bone rather than liver. Bone-specific ALP helps when total ALP is ambiguous, and turnover markers such as P1NP and CTX may also be raised.
- Calcium and phosphate are normal (calcium rises only with immobilization). Secondary hyperparathyroidism occurs in about 10% of patients.
- Plain radiographs of painful or suspicious areas show osteolysis, coarse trabeculae, cortical thickening and sclerosis, bone enlargement and bowing. In the skull, patchy sclerosis and lucency produce the classic "cotton wool" appearance.
- Radionuclide bone scan defines every affected bone, with targeted radiographs of the areas that light up.
- Biopsy is not part of the routine diagnosis, which rests on radiographs and ALP. A biopsy is done when the diagnosis is uncertain, to exclude metastases, and CT, MRI or biopsy is used when symptoms worsen at a pagetic site, to exclude osteosarcoma or giant cell tumor.
- Before any bisphosphonate: check calcium, 25-hydroxyvitamin D and creatinine.
Paget disease vs the look-alikes
| Condition | Lab pattern | Bone and clinical clues |
|---|---|---|
| Paget disease | High ALP; normal calcium and phosphate | Older adult; enlarged, bowed, warm bone; skull growth; hearing loss; mixed lytic and sclerotic X-ray |
| Osteomalacia (vitamin D deficiency) | Calcium low or normal, phosphate usually low, PTH normal or high, ALP usually high, low 25-hydroxyvitamin D | Bone pain and muscle weakness; Looser lines (pseudofractures) |
| Primary hyperparathyroidism | High calcium, low phosphate, inappropriately high PTH; ALP raised when bone turnover is increased | Subperiosteal resorption in the phalanges and distal clavicles; osteitis fibrosa cystica |
| Osteoporosis | Labs are used to search for secondary causes | Silent until a fragility fracture (vertebrae, hip, distal radius); bone is thin, not enlarged |
| Multiple myeloma | Hypercalcemia in about 10% at diagnosis; anemia, renal insufficiency | Punched-out lytic lesions or diffuse osteoporosis; radionuclide bone scans usually unhelpful |
The full metabolic bone comparison is in osteoporosis vs osteomalacia vs rickets, the PTH-driven pattern in the primary hyperparathyroidism sketch, and the lytic-lesion workup in the multiple myeloma breakdown.
Treatment
Who needs a drug? Not everyone: localized disease that causes no symptoms may not need treatment. The 2019 international guideline (Paget's Association, endorsed by the ASBMR) recommends bisphosphonates for bone pain caused by Paget disease, and favors treating symptoms over a "treat-to-target" strategy that aims to normalize ALP. US references (the 2014 Endocrine Society guideline and Merck) also treat:
- asymptomatic active disease at sites where complications could develop,
- patients scheduled for elective surgery on pagetic bone, to reduce bleeding,
- bone ALP more than twice normal, even without symptoms (Merck).
| Drug | Regimen | Key points |
|---|---|---|
| Zoledronic acid (first line) | Single 5 mg IV infusion over at least 15 minutes | Beat oral risedronate head to head (ALP normalized in 89% vs 58% at 6 months), with a long remission after one dose; the bisphosphonate most likely to relieve pain. Contraindicated with creatinine clearance below 35 mL/min, acute renal impairment or uncorrected hypocalcemia |
| Alendronate | 40 mg orally once daily for 6 months | Oral alternative when zoledronic acid is not suitable |
| Risedronate | 30 mg orally once daily for 2 months | Oral alternative |
| Pamidronate | IV | Second-line option |
| Calcitonin-salmon injection | 100 units SC or IM daily | Second-line; labeled only for symptomatic disease when other treatments are not suitable; possible malignancy link, so its need is re-evaluated periodically |
Around a zoledronic acid infusion:
- Replete vitamin D and calcium first. Hypocalcemia after zoledronic acid has been reported with 25-hydroxyvitamin D of 10 ng/mL or less, and Merck suggests a level above 25 ng/mL. The label advises 1,500 mg of elemental calcium daily in divided doses and 800 IU of vitamin D daily, particularly in the 2 weeks after the infusion.
- Warn about an acute phase reaction (fever, myalgia, headache) within 3 days; acetaminophen can help. Osteonecrosis of the jaw and atypical femoral fractures are rare, and an oral examination comes first.
- Recheck total ALP 3-6 months later; re-treat for relapse or recurrent symptoms.
- Set expectations: bone pain improves in most patients, but drugs do not reverse existing deformity, hearing loss or nerve damage.
What not to give: teriparatide (the label says to avoid it in Paget disease of bone because of osteosarcoma concerns) and denosumab, which lacks enough data for routine use. More bone drugs are compared in the bisphosphonates and bone drugs breakdown.
Supportive and surgical care: analgesics or NSAIDs, orthotics for gait problems, staying weight-bearing rather than on bed rest, joint replacement for osteoarthritis that does not respond to medical therapy, and spinal decompression.
Practice question
A 72-year-old man has 6 months of deep, aching pain in his pelvis and right thigh that is worse at night. His hats no longer fit, and his hearing in the right ear has declined. His right tibia is bowed and warm. Serum ALP is 410 U/L (reference 40-120); GGT, calcium, phosphate and PTH are normal, 25-hydroxyvitamin D is 32 ng/mL and creatinine clearance is 70 mL/min. Pelvic radiographs show bone enlargement, cortical thickening, coarse trabeculae and mixed lytic and sclerotic areas. Which is the most appropriate treatment?
A. A single 5 mg IV infusion of zoledronic acid B. Daily subcutaneous teriparatide C. Daily calcitonin-salmon injections D. Denosumab E. Calcitriol with high-dose calcium F. No drug treatment, because his calcium is normal
Answer: A. This is symptomatic Paget disease: bone pain, skull growth, hearing loss and an isolated high ALP from bone. Bisphosphonates are recommended for pagetic bone pain, and zoledronic acid is the agent most likely to relieve it, with the most sustained response. His vitamin D, calcium and renal function are adequate, so he can be infused now, with calcium and vitamin D supplements afterward and an ALP check in 3-6 months.
- B: teriparatide stimulates bone formation, and its label says to avoid it in Paget disease of bone because of osteosarcoma concerns.
- C: calcitonin is a second-line alternative, labeled only for symptomatic disease when other treatments are not suitable; its label also carries a possible malignancy association.
- D: denosumab lacks enough data for routine use in Paget disease.
- E: calcitriol and extra calcium correct low vitamin D activity or low calcium, and he has neither; Paget disease is driven by osteoclast overactivity.
- F: normal calcium is expected in Paget disease. He has pain from active disease, which is an indication for treatment.
How USMLE tests it
- Isolated high ALP with a normal GGT in an older adult: think Paget disease (bone source), not liver disease.
- New severe pain or swelling in pagetic bone: suspect osteosarcoma and image (see osteosarcoma vs Ewing sarcoma).
- Hypercalcemia in a patient with Paget disease: immobilization (bed rest), or a second diagnosis such as primary hyperparathyroidism.
- Teriparatide: avoided in Paget disease, a favorite pharmacology trap.
- Exam lore vs current practice: review sources list calcitonin beside bisphosphonates, but its US label now limits it to patients who cannot use other treatments; zoledronic acid is first line.
Key takeaways
- Paget disease = focal, chaotic remodeling: giant osteoclasts, then disorganized osteoblast repair, leaving big, vascular, weak bone with a mosaic pattern.
- Pelvis, femur and skull are the most commonly affected bones.
- High ALP with normal calcium and phosphate is the lab signature; calcium rises only with immobilization.
- Radiographs diagnose it (cotton wool skull, cortical thickening, bowing); a bone scan maps its extent.
- Complications: osteoarthritis (up to 50%), fractures, hearing loss, spinal stenosis, rare high-output heart failure, osteosarcoma in under 1%.
- Treat pain with a bisphosphonate: single IV zoledronic acid 5 mg first line, after correcting vitamin D and calcium; avoid teriparatide.
Sources
- Paget Disease of Bone — Merck Manual Professional Edition (2026)
- Diagnosis and Management of Paget's Disease of Bone in Adults: A Clinical Guideline — Journal of Bone and Mineral Research (2019)
- Paget's Disease of Bone: An Endocrine Society Clinical Practice Guideline — Journal of Clinical Endocrinology & Metabolism (2014)
- Paget Disease of Bone for Primary Care — American Family Physician (2020)
- Paget Bone Disease — StatPearls, NCBI Bookshelf (2023)
- Reclast (zoledronic acid) injection: prescribing information — DailyMed (2026)
- Miacalcin (calcitonin salmon) injection: prescribing information — DailyMed (2024)
- Forteo (teriparatide) injection: prescribing information — DailyMed (2026)
- Vitamin D Deficiency and Dependency — Merck Manual Professional Edition (2026)
- Hypercalcemia — Merck Manual Professional Edition (2025)
- Multiple Myeloma — Merck Manual Professional Edition (2026)
- Osteoporosis — Merck Manual Professional Edition (2025)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
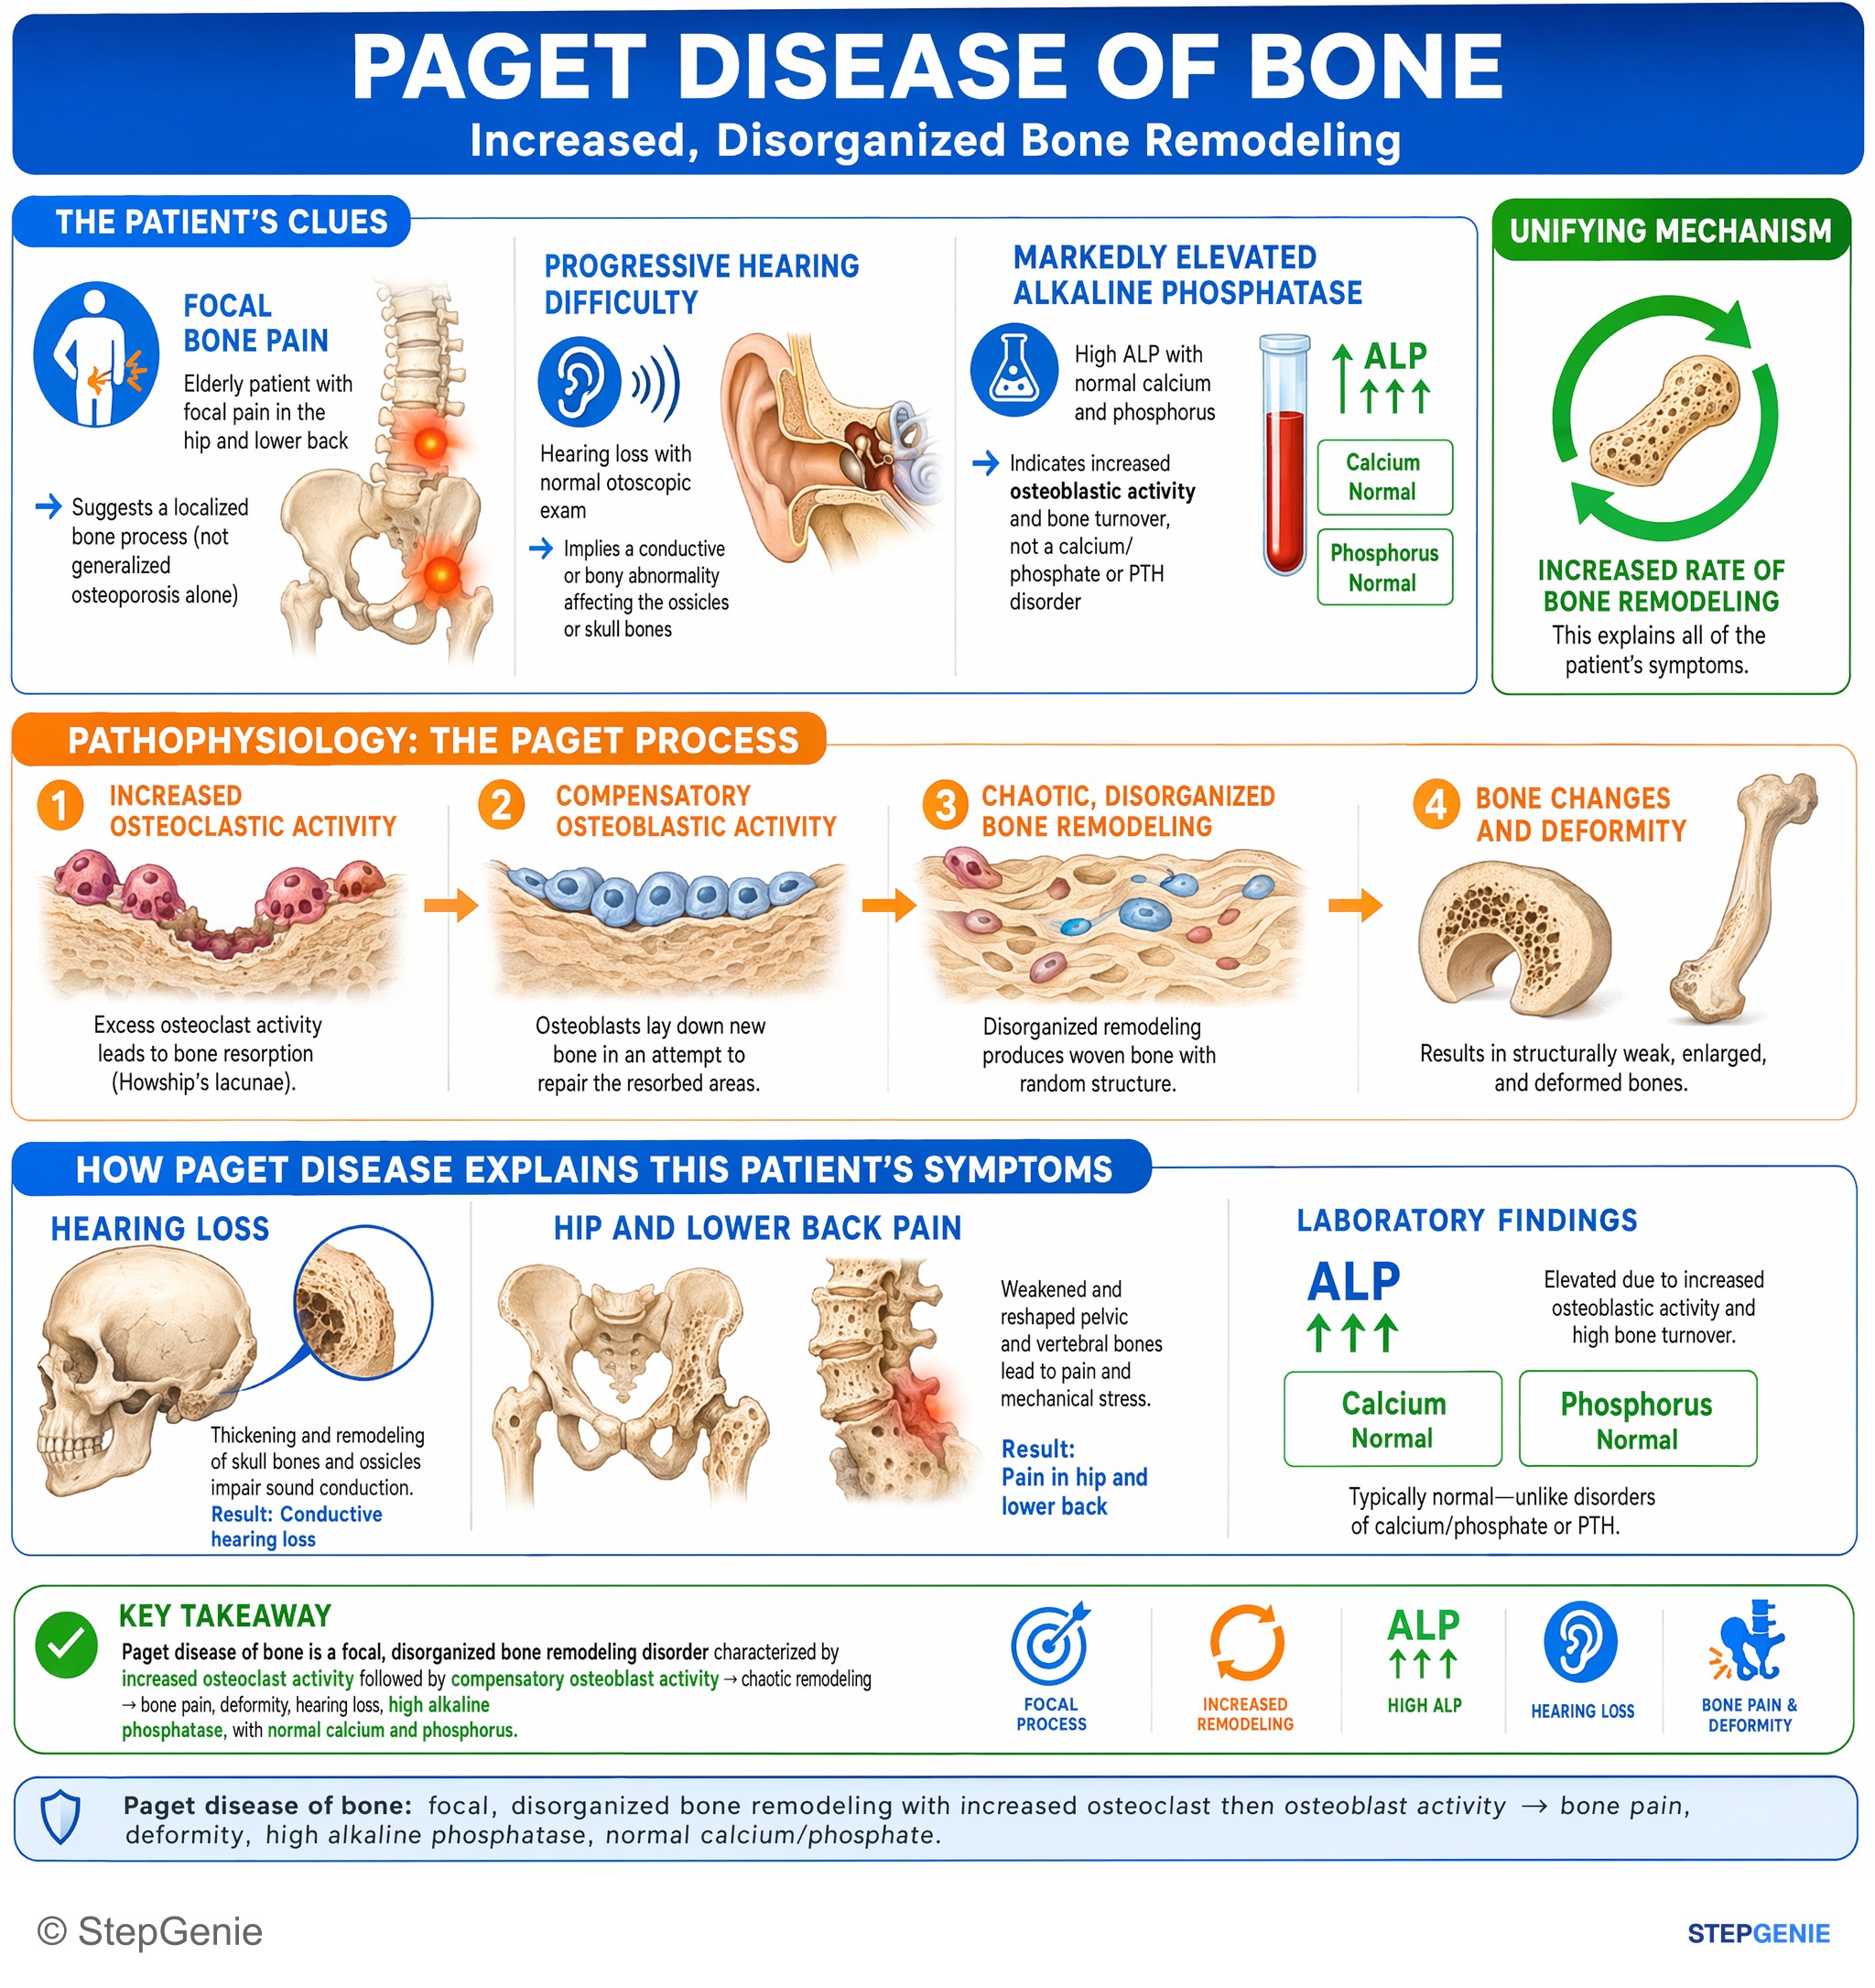
Paget disease of bone: focal, disorganized bone remodeling with increased osteoclast then osteoblast activity → bone pain, deformity, high…
USMLE Step 1
Paget disease of bone: disordered bone remodeling → bone pain, fractures, isolated high ALP with normal GGT and calcium, possible hearing…
USMLE Step 2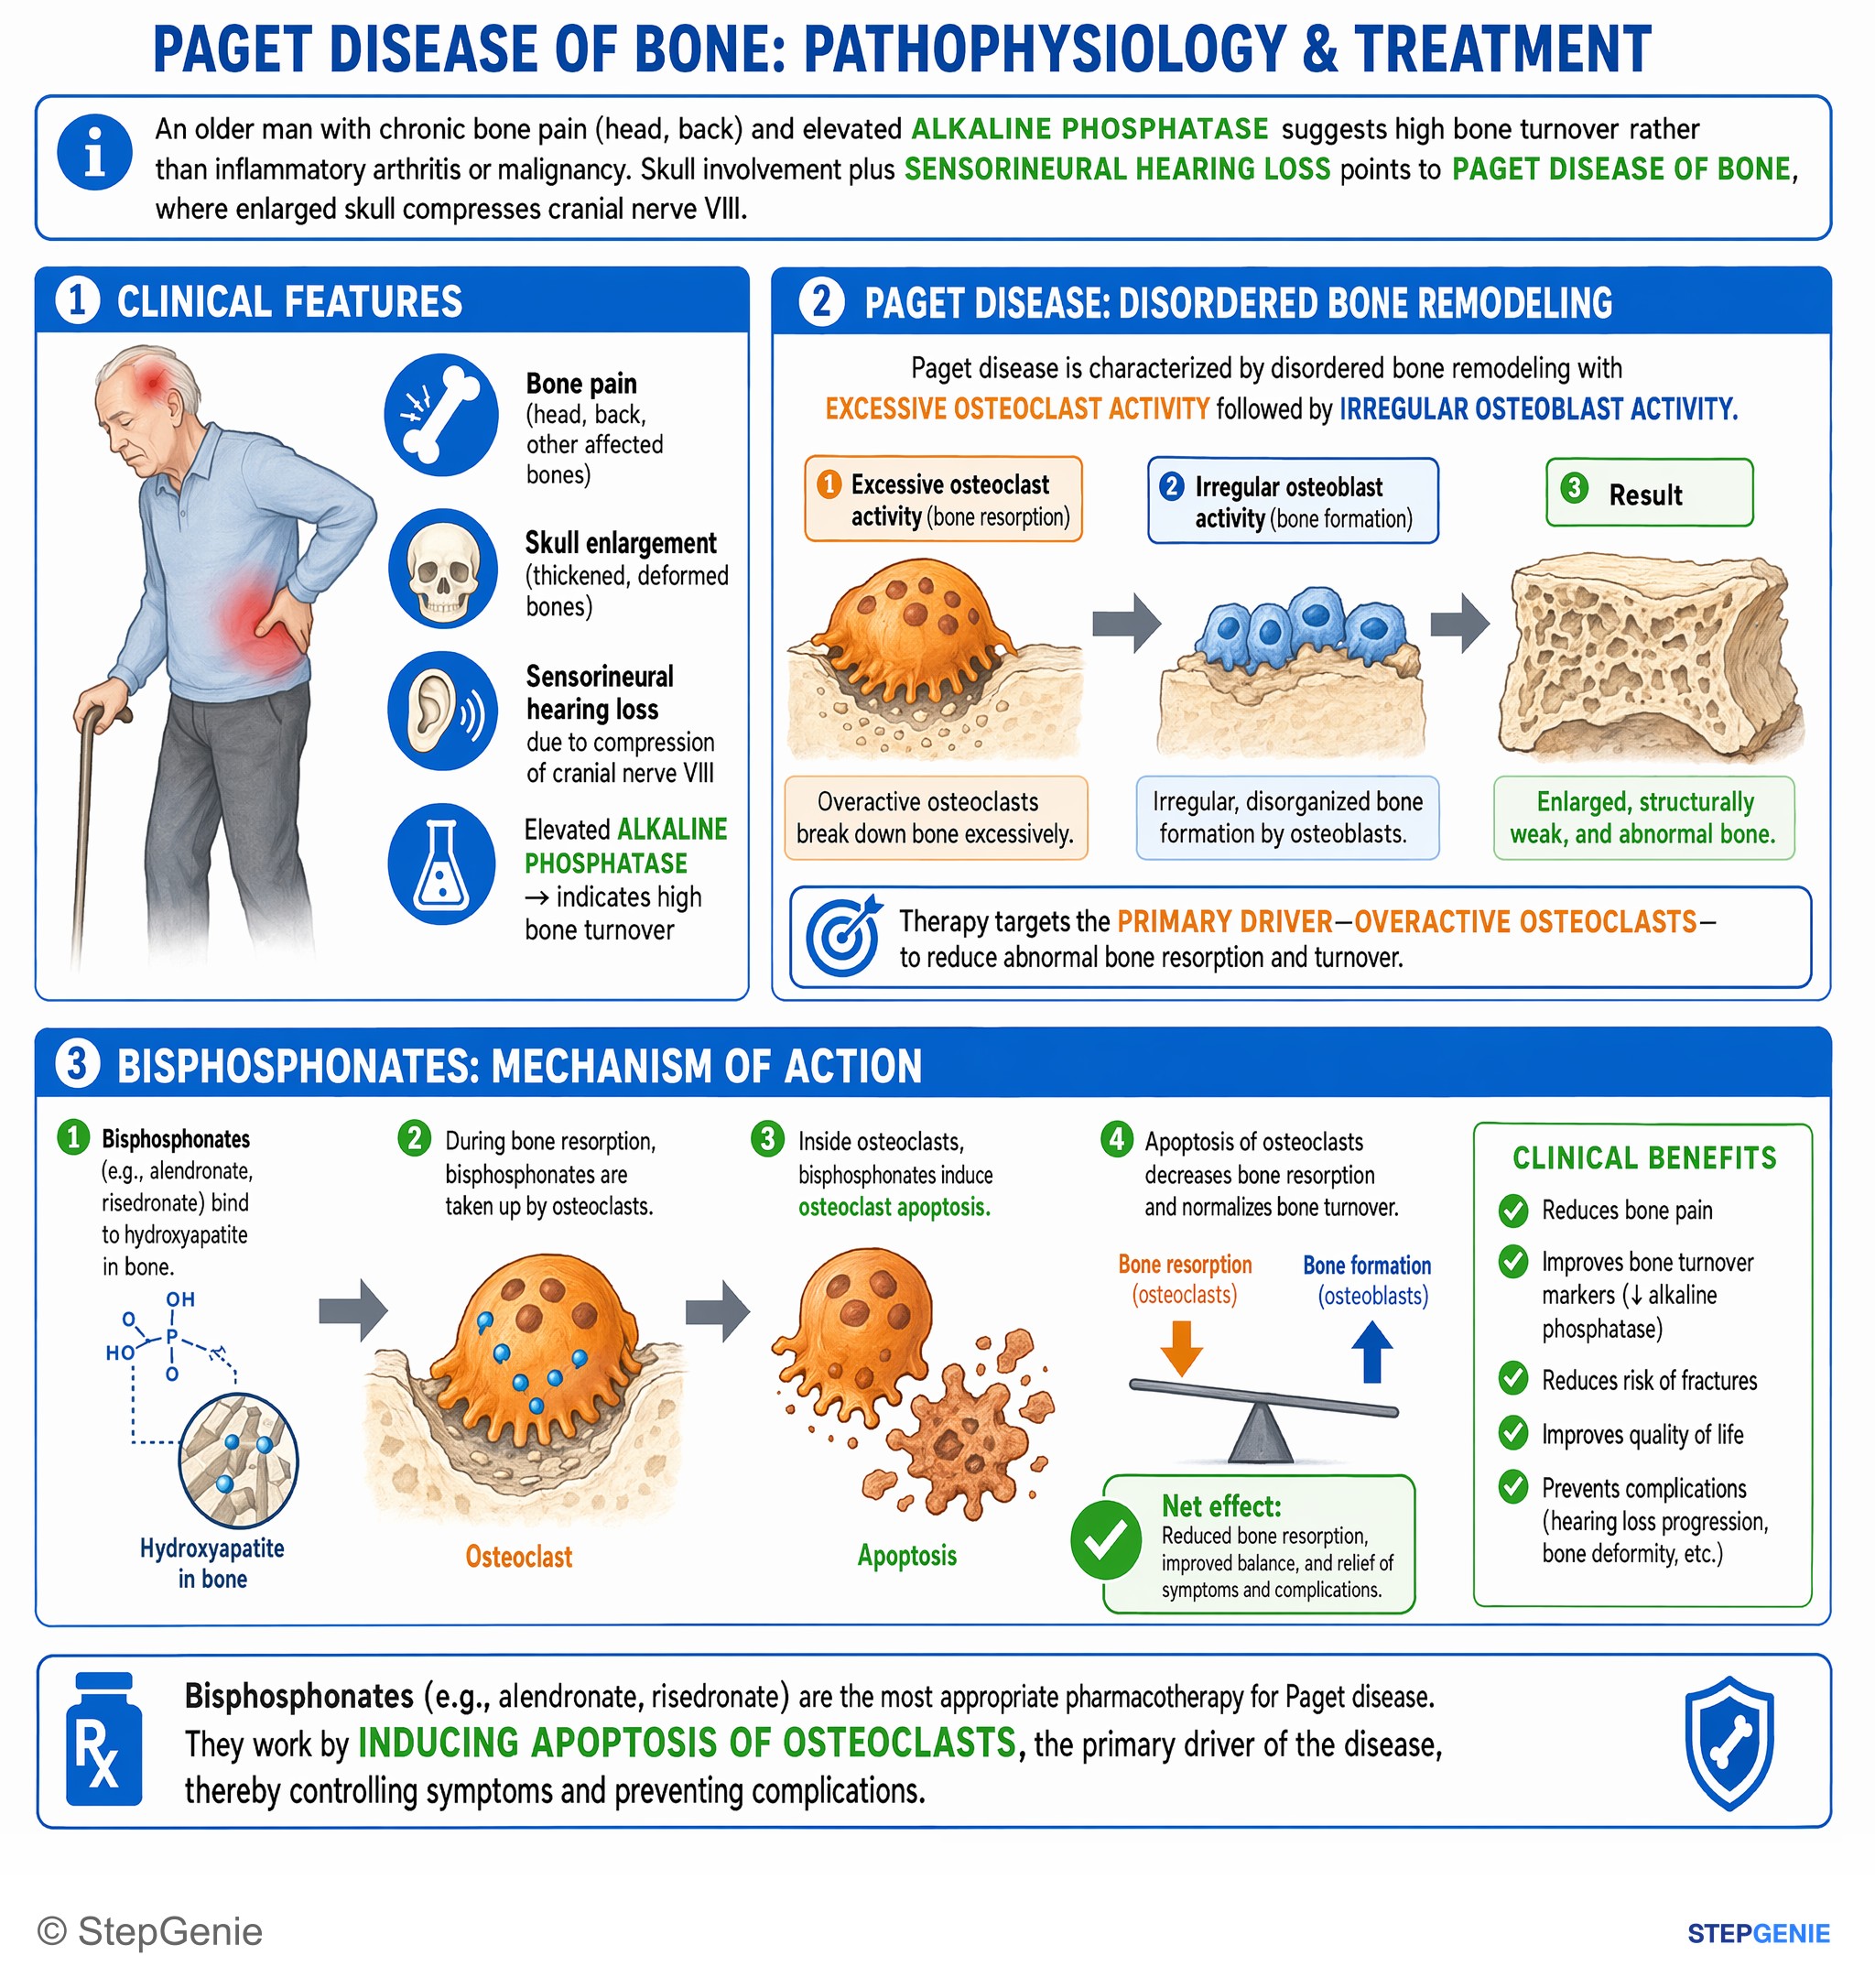
Paget disease of bone causes bone pain, skull enlargement, hearing loss; treat with bisphosphonates, which induce osteoclast apoptosis and…
USMLE Step 1Frequently Asked Questions
What lab findings are typical of Paget disease of bone?
The signature is a raised alkaline phosphatase of bone origin, with a normal GGT and 5'-nucleotidase showing that the liver is not the source, and normal serum calcium and phosphate. Calcium rises only if the patient is immobilized; hypercalcemia in a walking patient suggests coexisting hyperparathyroidism. Bone-specific ALP and turnover markers such as P1NP and CTX can help, and secondary hyperparathyroidism occurs in about 10% of patients.
What is the first-line treatment for Paget disease of bone?
Bisphosphonates are first line for bone pain from Paget disease, and a single 5 mg intravenous infusion of zoledronic acid is preferred: it normalized ALP in more patients than oral risedronate, gives a long remission after one dose and is the bisphosphonate most likely to relieve pain. Oral alternatives are alendronate 40 mg daily for 6 months and risedronate 30 mg daily for 2 months. Vitamin D and calcium must be adequate before the infusion, and zoledronic acid is contraindicated with a creatinine clearance below 35 mL/min.
Does everyone with Paget disease of bone need treatment?
No. Localized disease that causes no symptoms may not need drugs. The 2019 international guideline recommends bisphosphonates for bone pain and favors treating symptoms over chasing a normal ALP. US references, including the 2014 Endocrine Society guideline and Merck, also treat asymptomatic active disease at sites where complications could develop and patients facing elective surgery on pagetic bone, and Merck adds bone ALP above twice normal even without symptoms.
Why does Paget disease cause hearing loss and a bigger hat size?
When the skull is involved, overactive remodeling enlarges and thickens the bone, producing frontal bossing, bitemporal widening and a head that no longer fits a hat. Involvement of the petrous temporal bone and cochlea causes hearing loss, which can be sensorineural, conductive or mixed and may affect one or both ears. Treatment can relieve pain and control disease activity, but it does not reverse hearing loss that has already occurred.
What are the complications of Paget disease of bone?
Osteoarthritis in joints next to affected bone is common, affecting up to half of patients. Others include bowing deformities, pathologic fractures, hearing loss, spinal stenosis or cord compression, hypercalcemia during immobilization, excessive bleeding during orthopedic surgery and, rarely, high-output heart failure from large hypervascular lesions. Osteosarcoma develops in under 1% and should be suspected with new severe pain, swelling or bone destruction.
What does Paget disease look like on X-ray and biopsy?
Radiographs show osteolysis, coarse trabeculae, cortical thickening and sclerosis, bone enlargement and bowing of long bones such as the tibia or femur. In the skull, patchy sclerosis and lucency give the classic cotton wool appearance. A radionuclide bone scan shows the full extent of disease. Biopsy is not routine, but when done it shows the hallmark mosaic, jigsaw-puzzle pattern of bone produced by disorganized remodeling.