Osteosarcoma is a bone-forming sarcoma of teenagers (and of older adults with Paget disease or prior radiation) that arises in the metaphysis around the knee, makes malignant osteoid and classically shows a sunburst pattern and Codman triangle; RB1 and TP53 defects raise the risk. Ewing sarcoma is a small round blue cell tumor of children and teens in the diaphysis or pelvis, with an onion-skin periosteal reaction, CD99 staining and an EWSR1-FLI1 fusion from t(11;22). Both need a biopsy, both metastasize mainly to the lungs and both get chemotherapy before local treatment, but osteosarcoma relies on surgery, while Ewing sarcoma also responds well to radiation.
Osteosarcoma vs Ewing sarcoma at a glance
| Feature | Osteosarcoma | Ewing sarcoma |
|---|---|---|
| Typical patient | Teen in the growth spurt; second peak after 60 (Paget disease, bone infarcts, prior radiation) | Child or teen, peak 10–20 years; more often male and White |
| Part of the bone | Metaphysis of a long bone | Diaphysis (shaft), often extending toward the metaphysis |
| Favorite sites | Distal femur, proximal tibia, proximal humerus | Pelvis and femur are the most common sites; also ribs, tibia, fibula and spine; about 1 in 5 arise in soft tissue |
| Radiograph | Destructive lesion, lytic, sclerotic or mixed; sunburst spicules, Codman triangle | Lytic, permeative destruction, onion-skin layers, large soft-tissue mass |
| Histology | Pleomorphic malignant cells directly forming osteoid or bone | Sheets of uniform small round blue cells; clear cytoplasm with glycogen (PAS positive) |
| Helpful stains | Diagnosis rests on malignant osteoid | Membranous CD99 and nuclear NKX2.2 (neither fully specific) |
| Genetics | Somatic TP53 and RB1 loss; germline RB1, TP53, RECQL4 (Rothmund-Thomson) | t(11;22)(q24;q12) → EWSR1-FLI1 in 85–90%; t(21;22) EWSR1-ERG in about 10% |
| Symptoms | Local pain (may be worse at night), swelling, reduced joint motion, pathologic fracture | Local pain and swelling, sometimes with fever, fatigue or weight loss that mimic infection |
| Metastases at diagnosis | About 20% (NCI; about 1 in 5 per ACS), mostly lung, then bone | About 25% per NCI (about 1 in 5 per ACS): lung, bone, bone marrow |
| Chemotherapy | MAP: high-dose methotrexate, doxorubicin, cisplatin | VDC/IE: vincristine, doxorubicin, cyclophosphamide alternating with ifosfamide, etoposide |
| Local control | Wide en bloc resection; radiation only if unresectable or margins are inadequate | Surgery and/or radiation; responds well to radiation |
Why the periosteal reactions look different
The periosteum lays down new bone whenever a lesion lifts or irritates it, and the pattern depends mainly on how fast the lesion grows, not on what it is. That is why these signs mark an aggressive process rather than a specific tumor.
| Pattern | What is happening | Classic tumor | Also seen in |
|---|---|---|---|
| Onion skin (lamellated) | Growth comes in spurts; between spurts the periosteum lays down a thin shell of bone, leaving concentric layers | Ewing sarcoma | Other aggressive lesions, including osteomyelitis |
| Sunburst (hair-on-end) | Rapid, steady growth stretches Sharpey fibers perpendicular to the cortex, and they ossify as spicules | Osteosarcoma | Ewing sarcoma can show it too |
| Codman triangle | Growth outpaces the periosteum, so only the edges of the lifted periosteum ossify, forming an angle with the cortex | Osteosarcoma | Any rapidly growing lesion, including osteomyelitis |
Exam logic: the periosteal reaction tells you the lesion is fast; age, location, histology and genetics tell you what it is.
Osteosarcoma: what to know
- Definition: a malignant tumor whose cells directly form osteoid or bone. The conventional high-grade tumor starts in the medullary cavity and breaks out through the cortex; it makes up about 90% of cases as osteoblastic, chondroblastic or fibroblastic subtypes.
- Epidemiology: the most common primary malignant bone tumor (counting myeloma as a marrow tumor). Incidence peaks in adolescents during the growth spurt, with a second peak in adults 60 and older.
- Risk factors: hereditary retinoblastoma (germline RB1, 13q14), Li-Fraumeni syndrome (germline TP53, 17p13), Paget disease of bone, prior high-dose radiation, bone infarcts and rare DNA-helicase syndromes (Rothmund-Thomson, Bloom, Werner). The two-hit logic of RB1 and TP53 is reviewed in the oncogenes vs tumor suppressors cheat sheet; an older adult with worsening pain in a pagetic bone is the classic setup covered in the Paget disease of bone guide.
- Symptoms: bone pain that may come and go or be worse at night, then swelling and loss of joint motion; a pathologic fracture is more likely with the telangiectatic subtype, which can mimic an aneurysmal bone cyst.
- Labs: no blood test makes the diagnosis. A high alkaline phosphatase or LDH suggests more advanced disease, and a falling ALP during chemotherapy is a sign of response.
- Workup: radiographs, MRI of the entire bone to find skip lesions, chest CT for lung metastases, and PET-CT or bone scan. The biopsy should be done by a surgeon skilled in limb-sparing surgery, because a badly placed biopsy tract can make limb-sparing surgery impossible.
- Treatment: chemotherapy before and after surgery plus en bloc resection. In children, teens and young adults the usual regimen is MAP: high-dose methotrexate (with leucovorin rescue), doxorubicin (cardiotoxic; dexrazoxane is often given to protect the heart) and cisplatin (ototoxic, nephrotoxic); older adults more often get doxorubicin plus cisplatin. More than 80% of extremity tumors can be removed with limb-sparing surgery. At least 90% tumor necrosis after preoperative chemotherapy predicts a better outcome. Radiation has a minor role because osteosarcoma cells are not easily killed by it.
- Why chemotherapy is mandatory: micrometastases are assumed. With surgery alone at least 80% of patients develop metastases; per Merck, adjuvant chemotherapy raised 5-year survival in localized disease from under 20% to over 65%.
- Low-grade exception: parosteal osteosarcoma is a low-grade surface tumor, most often on the posterior distal femur in people aged 20–30, treated by wide excision alone, without chemotherapy.
Ewing sarcoma: what to know
- Definition: a small round blue cell sarcoma of bone or soft tissue defined by fusion of EWSR1 (rarely FUS) with an ETS-family transcription factor gene. Peripheral primitive neuroectodermal tumor (PNET) and Askin tumor of the chest wall are older names for the same tumor.
- Epidemiology: the second most common bone cancer in children and young adults; about 59% of patients are male, and in the US it is about nine times more common in White than in Black people.
- Genetics: EWSR1 on 22q12 fused to FLI1 on 11q24 in 85–90%, EWSR1-ERG in about 10%. The fusion protein acts as an aberrant transcription factor. Unlike osteosarcoma, Ewing sarcoma is rarely part of an inherited cancer syndrome; TP53 variants appear in only about 6–7% of pediatric tumors.
- Symptoms: pain and swelling near the tumor. Fever, fatigue and weight loss can occur, which is why Ewing sarcoma is sometimes mistaken for infection.
- Imaging: permeative lytic destruction is the most common finding, with onion-skin layering and a large soft-tissue mass. Radiographs underestimate the extent, so MRI defines it.
- Histology: tightly packed uniform cells with round nuclei, fine chromatin and scant clear, glycogen-rich (PAS-positive) cytoplasm. CD99 supports the diagnosis but is also positive in synovial sarcoma, non-Hodgkin lymphoma and GIST, so the fusion is confirmed by cytogenetics, FISH, RT-PCR or sequencing.
- Workup: MRI of the primary, chest CT, PET-CT (which can replace a bone scan) and bone marrow sampling in selected patients.
- Treatment: every patient gets multiagent chemotherapy, because most apparently localized tumors carry occult metastases. Standard US chemotherapy is VDC alternating with IE, given every 2 weeks (interval compression), with local control after initial chemotherapy. Surgery is used most often; radiation is an effective alternative when surgery would be too disabling and is added for positive margins. Ifosfamide and cyclophosphamide can cause hemorrhagic cystitis, which mesna helps prevent.
Prognosis
| Outcome | Osteosarcoma | Ewing sarcoma |
|---|---|---|
| Localized disease | ACS: 60–75% survival; NCI: 5-year overall survival 62–65% with surgery plus chemotherapy | NCI: about 70% 5-year event-free and overall survival; ACS (SEER 2015–2021): 81% 5-year relative survival |
| Metastatic at diagnosis | ACS: 5–30% survival | ACS (SEER distant stage): 41% |
| Worse outlook with | Metastases, axial or pelvic site, unresectable tumor, less than 90% necrosis after chemotherapy | Metastases (lung-only fares better than bone or marrow), large or pelvic tumor, age over 18, poor response to chemotherapy |
Both tumors are managed practically as localized vs metastatic. Formal AJCC and Musculoskeletal Tumor Society staging for bone sarcomas also builds in histologic grade, a clear example of grade feeding into stage; the difference between the two is covered in tumor grading vs staging.
Mimics and traps
- Osteomyelitis: fever, a warm swollen limb, a destructive lesion and periosteal new bone fit both. In children, hematogenous osteomyelitis usually strikes the metaphyses of the tibia, femur or humerus and is proven by bone biopsy and culture. A diaphyseal lesion with a big soft-tissue mass in a teen needs a biopsy for Ewing sarcoma, not another antibiotic course; compare the osteomyelitis guide.
- Sunburst does not prove osteosarcoma, and onion skin does not prove Ewing sarcoma. Both show speed of growth.
- CD99 alone is not Ewing sarcoma. The EWSR1 fusion confirms it.
- Location rule: epiphysis → giant cell tumor, metaphysis → osteosarcoma, diaphysis → Ewing sarcoma. Tumors often cross segments, so use it as a tiebreaker.
- Over 40 with a destructive bone lesion: think metastatic carcinoma first (breast, prostate, lung, kidney, thyroid); also consider myeloma, lymphoma and chondrosarcoma, a cartilage tumor of middle-aged and older adults that often arises in the pelvis, femur or humerus and shows punctate matrix calcification.
Practice question
Vignette. A 14-year-old boy has 7 weeks of worsening pain in his left thigh and has lost 3 kg. His temperature is 38.1 °C (100.6 °F), and there is a warm, tender swelling over the mid-thigh. Hemoglobin is 10.8 g/dL. A radiograph shows a permeative lytic lesion in the femoral diaphysis with layered periosteal new bone and a large soft-tissue mass. A biopsy shows sheets of uniform small round cells with PAS-positive cytoplasm and strong membranous CD99 staining. Which additional finding is most likely?
- A. Loss of both RB1 alleles at 13q14
- B. Tumor cells directly producing osteoid
- C. A germline TP53 variant
- D. A t(11;22)(q24;q12) translocation
- E. Staphylococcus aureus growing from the bone biopsy
Answer: D. Diaphyseal site, onion-skin layering, a soft-tissue mass, systemic symptoms and PAS-positive, CD99-positive small round blue cells add up to Ewing sarcoma, and 85–90% carry EWSR1-FLI1 from t(11;22).
Why not the others?
- A: RB1 loss is typical of osteosarcoma (and retinoblastoma), a metaphyseal tumor that makes osteoid.
- B: osteoid production defines osteosarcoma; Ewing cells are primitive round cells that do not make matrix.
- C: Li-Fraumeni syndrome predisposes to osteosarcoma, breast cancer, brain tumors and soft tissue sarcomas; Ewing sarcoma is rarely hereditary.
- E: fever and a warm limb suggest osteomyelitis, but pediatric hematogenous osteomyelitis favors the metaphysis, and this biopsy shows tumor, not infection.
Key takeaways
- Osteosarcoma: teens and older adults with Paget disease or prior radiation, knee metaphysis, malignant osteoid, sunburst and Codman triangle, RB1 and TP53; MAP chemotherapy plus en bloc resection.
- Ewing sarcoma: children and teens, diaphysis and pelvis, onion skin, CD99-positive small round blue cells with PAS-positive glycogen, EWSR1-FLI1 from t(11;22).
- Periosteal patterns show growth speed, not the diagnosis; biopsy with molecular testing decides.
- Both metastasize mainly to the lungs; Ewing sarcoma also commonly seeds bone and bone marrow.
- Ewing sarcoma responds well to radiation; osteosarcoma does not, so surgery is its local therapy.
- Metastasis at diagnosis is the key adverse factor for both (NCI calls it the single most powerful predictor in Ewing sarcoma), and at least 90% necrosis after chemotherapy is favorable.
Sources
- Primary Malignant Bone Tumors — Merck Manual Professional Edition (2025)
- Overview of Bone and Joint Tumors — Merck Manual Professional Edition (2025)
- Osteosarcoma and Undifferentiated Pleomorphic Sarcoma of Bone Treatment (PDQ), Health Professional Version — National Cancer Institute
- Ewing Sarcoma and Undifferentiated Small Round Cell Sarcomas of Bone and Soft Tissue Treatment (PDQ), Health Professional Version — National Cancer Institute
- Periosteal Reaction — University of Washington Online Musculoskeletal Radiology Book
- About Osteosarcoma — American Cancer Society (2025)
- Survival Rates for Osteosarcoma — American Cancer Society (2025)
- Prognostic Factors and Survival Rates for Ewing Sarcoma — American Cancer Society (2026)
- Chemotherapy for Osteosarcoma — American Cancer Society (2025)
- Radiation Therapy for Osteosarcoma — American Cancer Society (2025)
- Radiation Therapy for Ewing Sarcoma — American Cancer Society (2026)
- Osteomyelitis — Merck Manual Professional Edition (2024)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
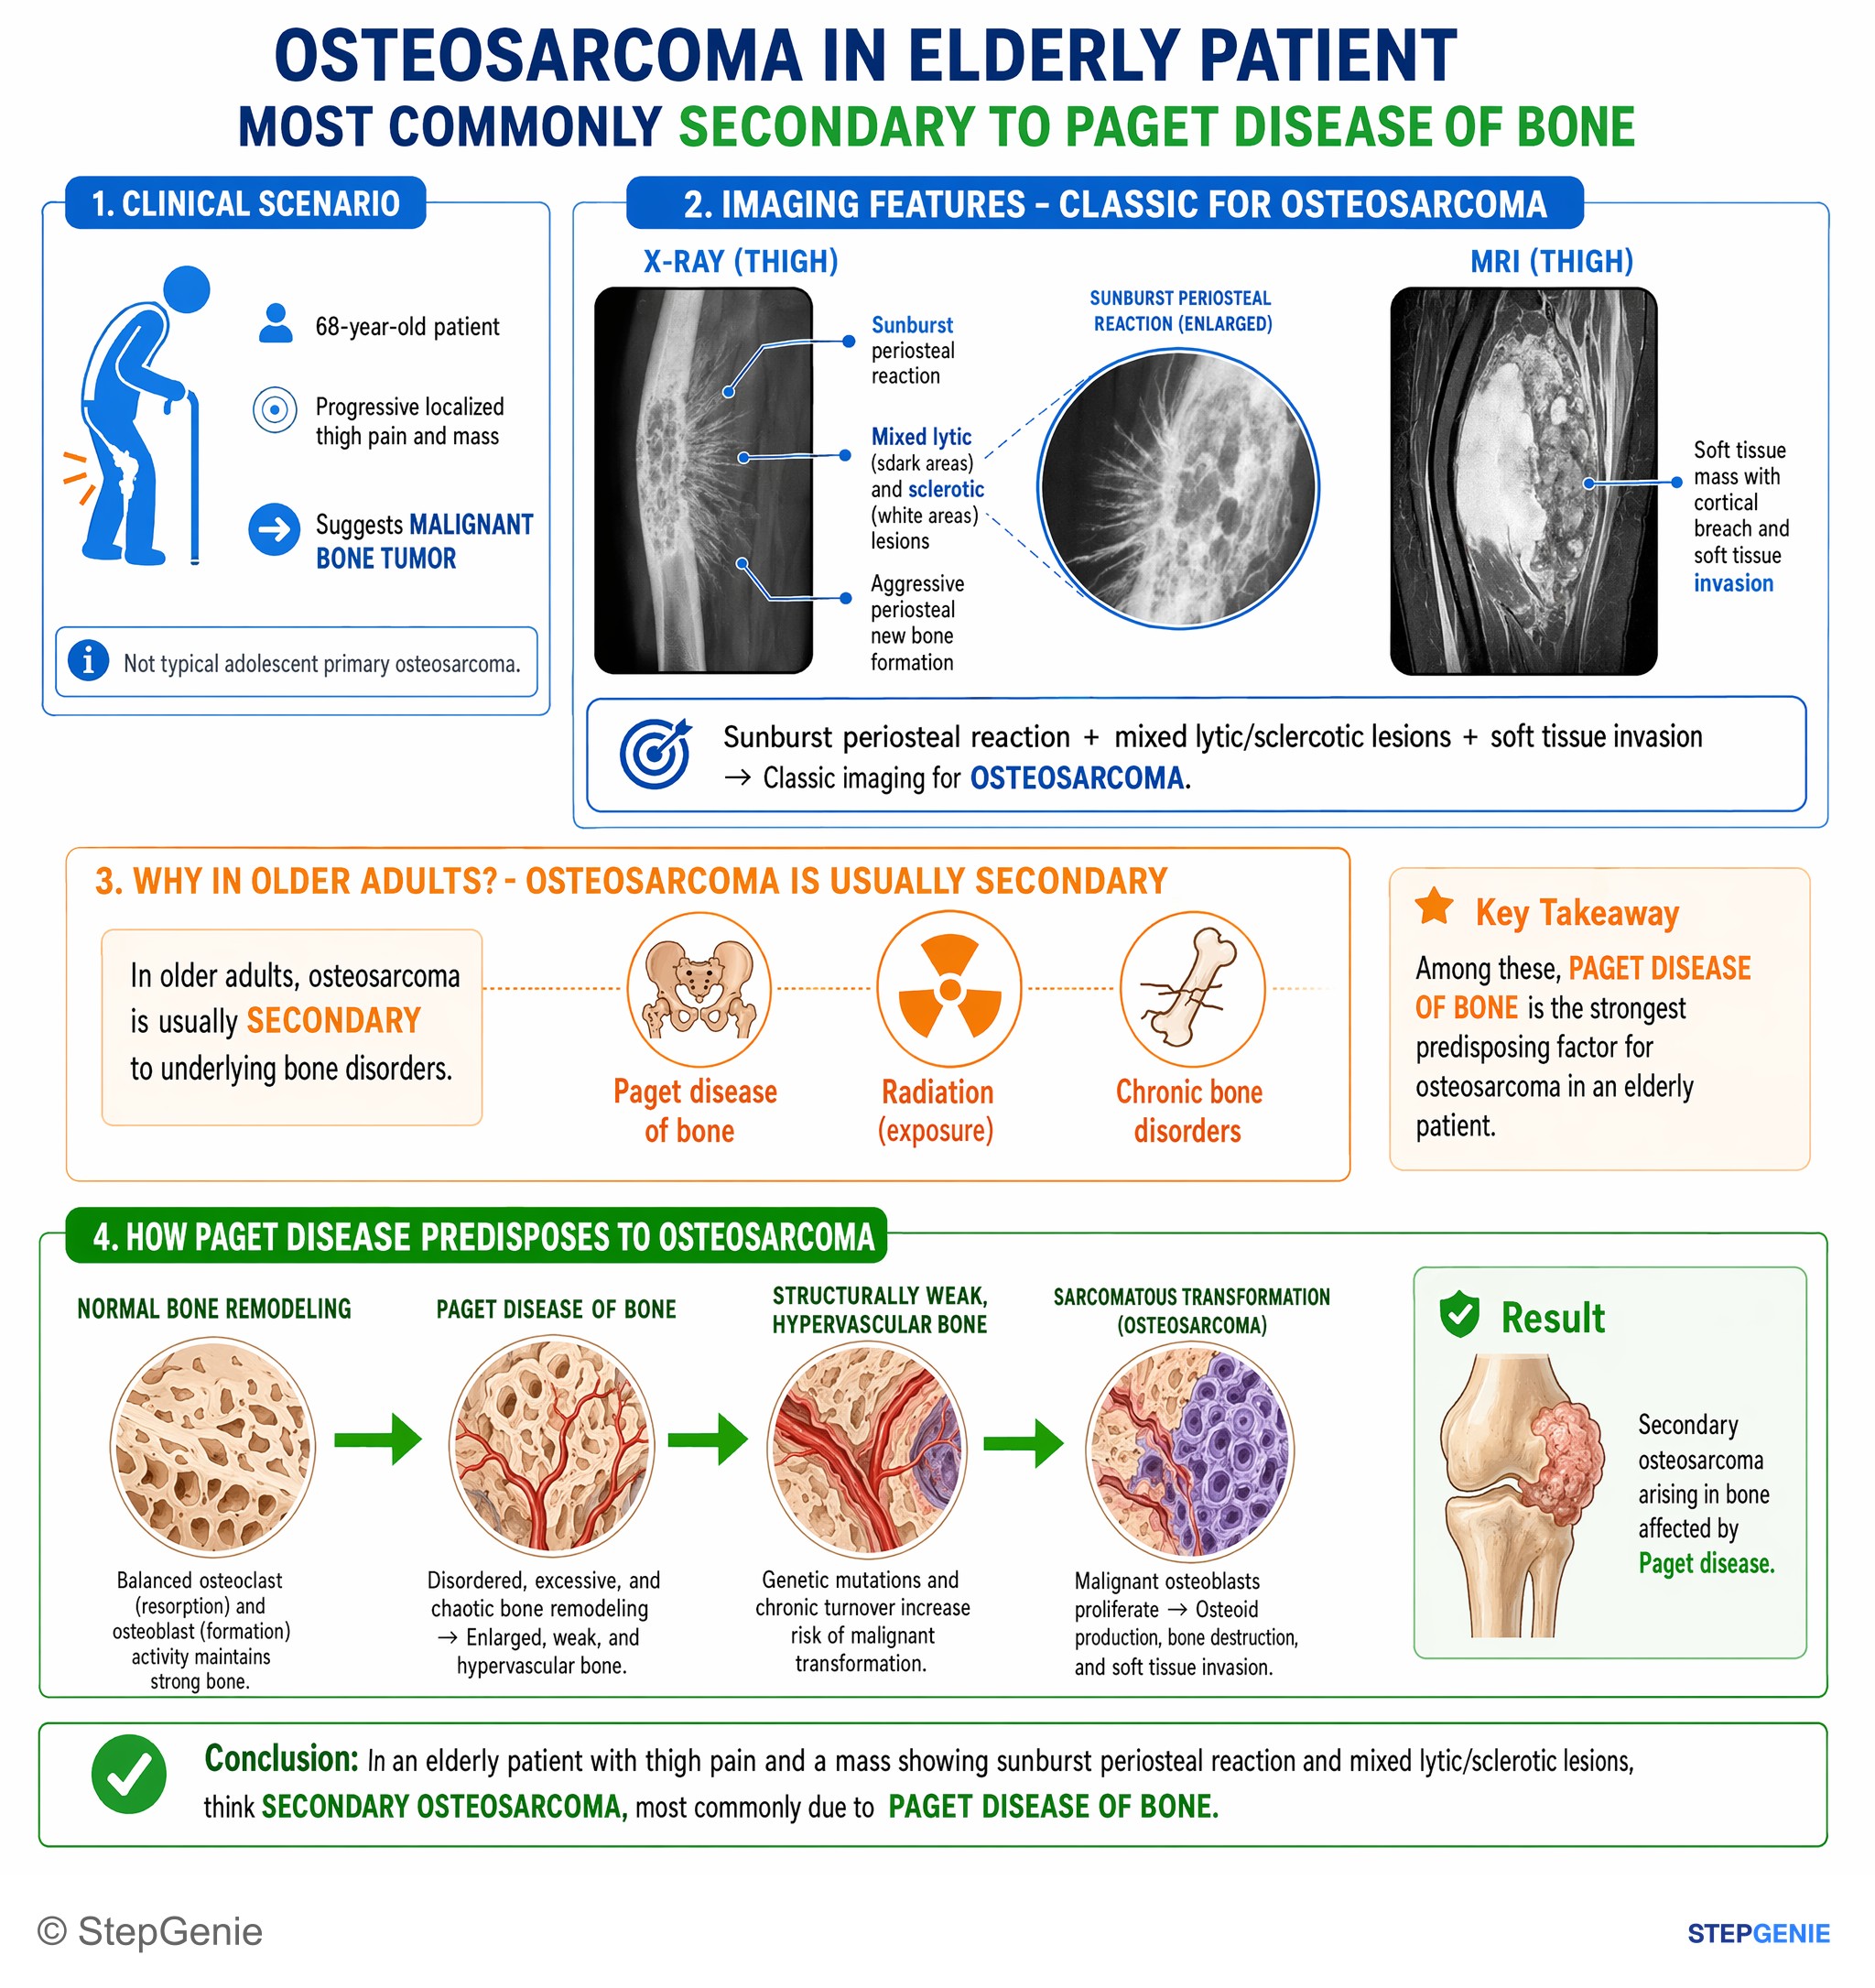
Osteosarcoma in an elderly patient often arises secondary to Paget disease of bone, showing sunburst periosteal reaction and mixed…
USMLE Step 1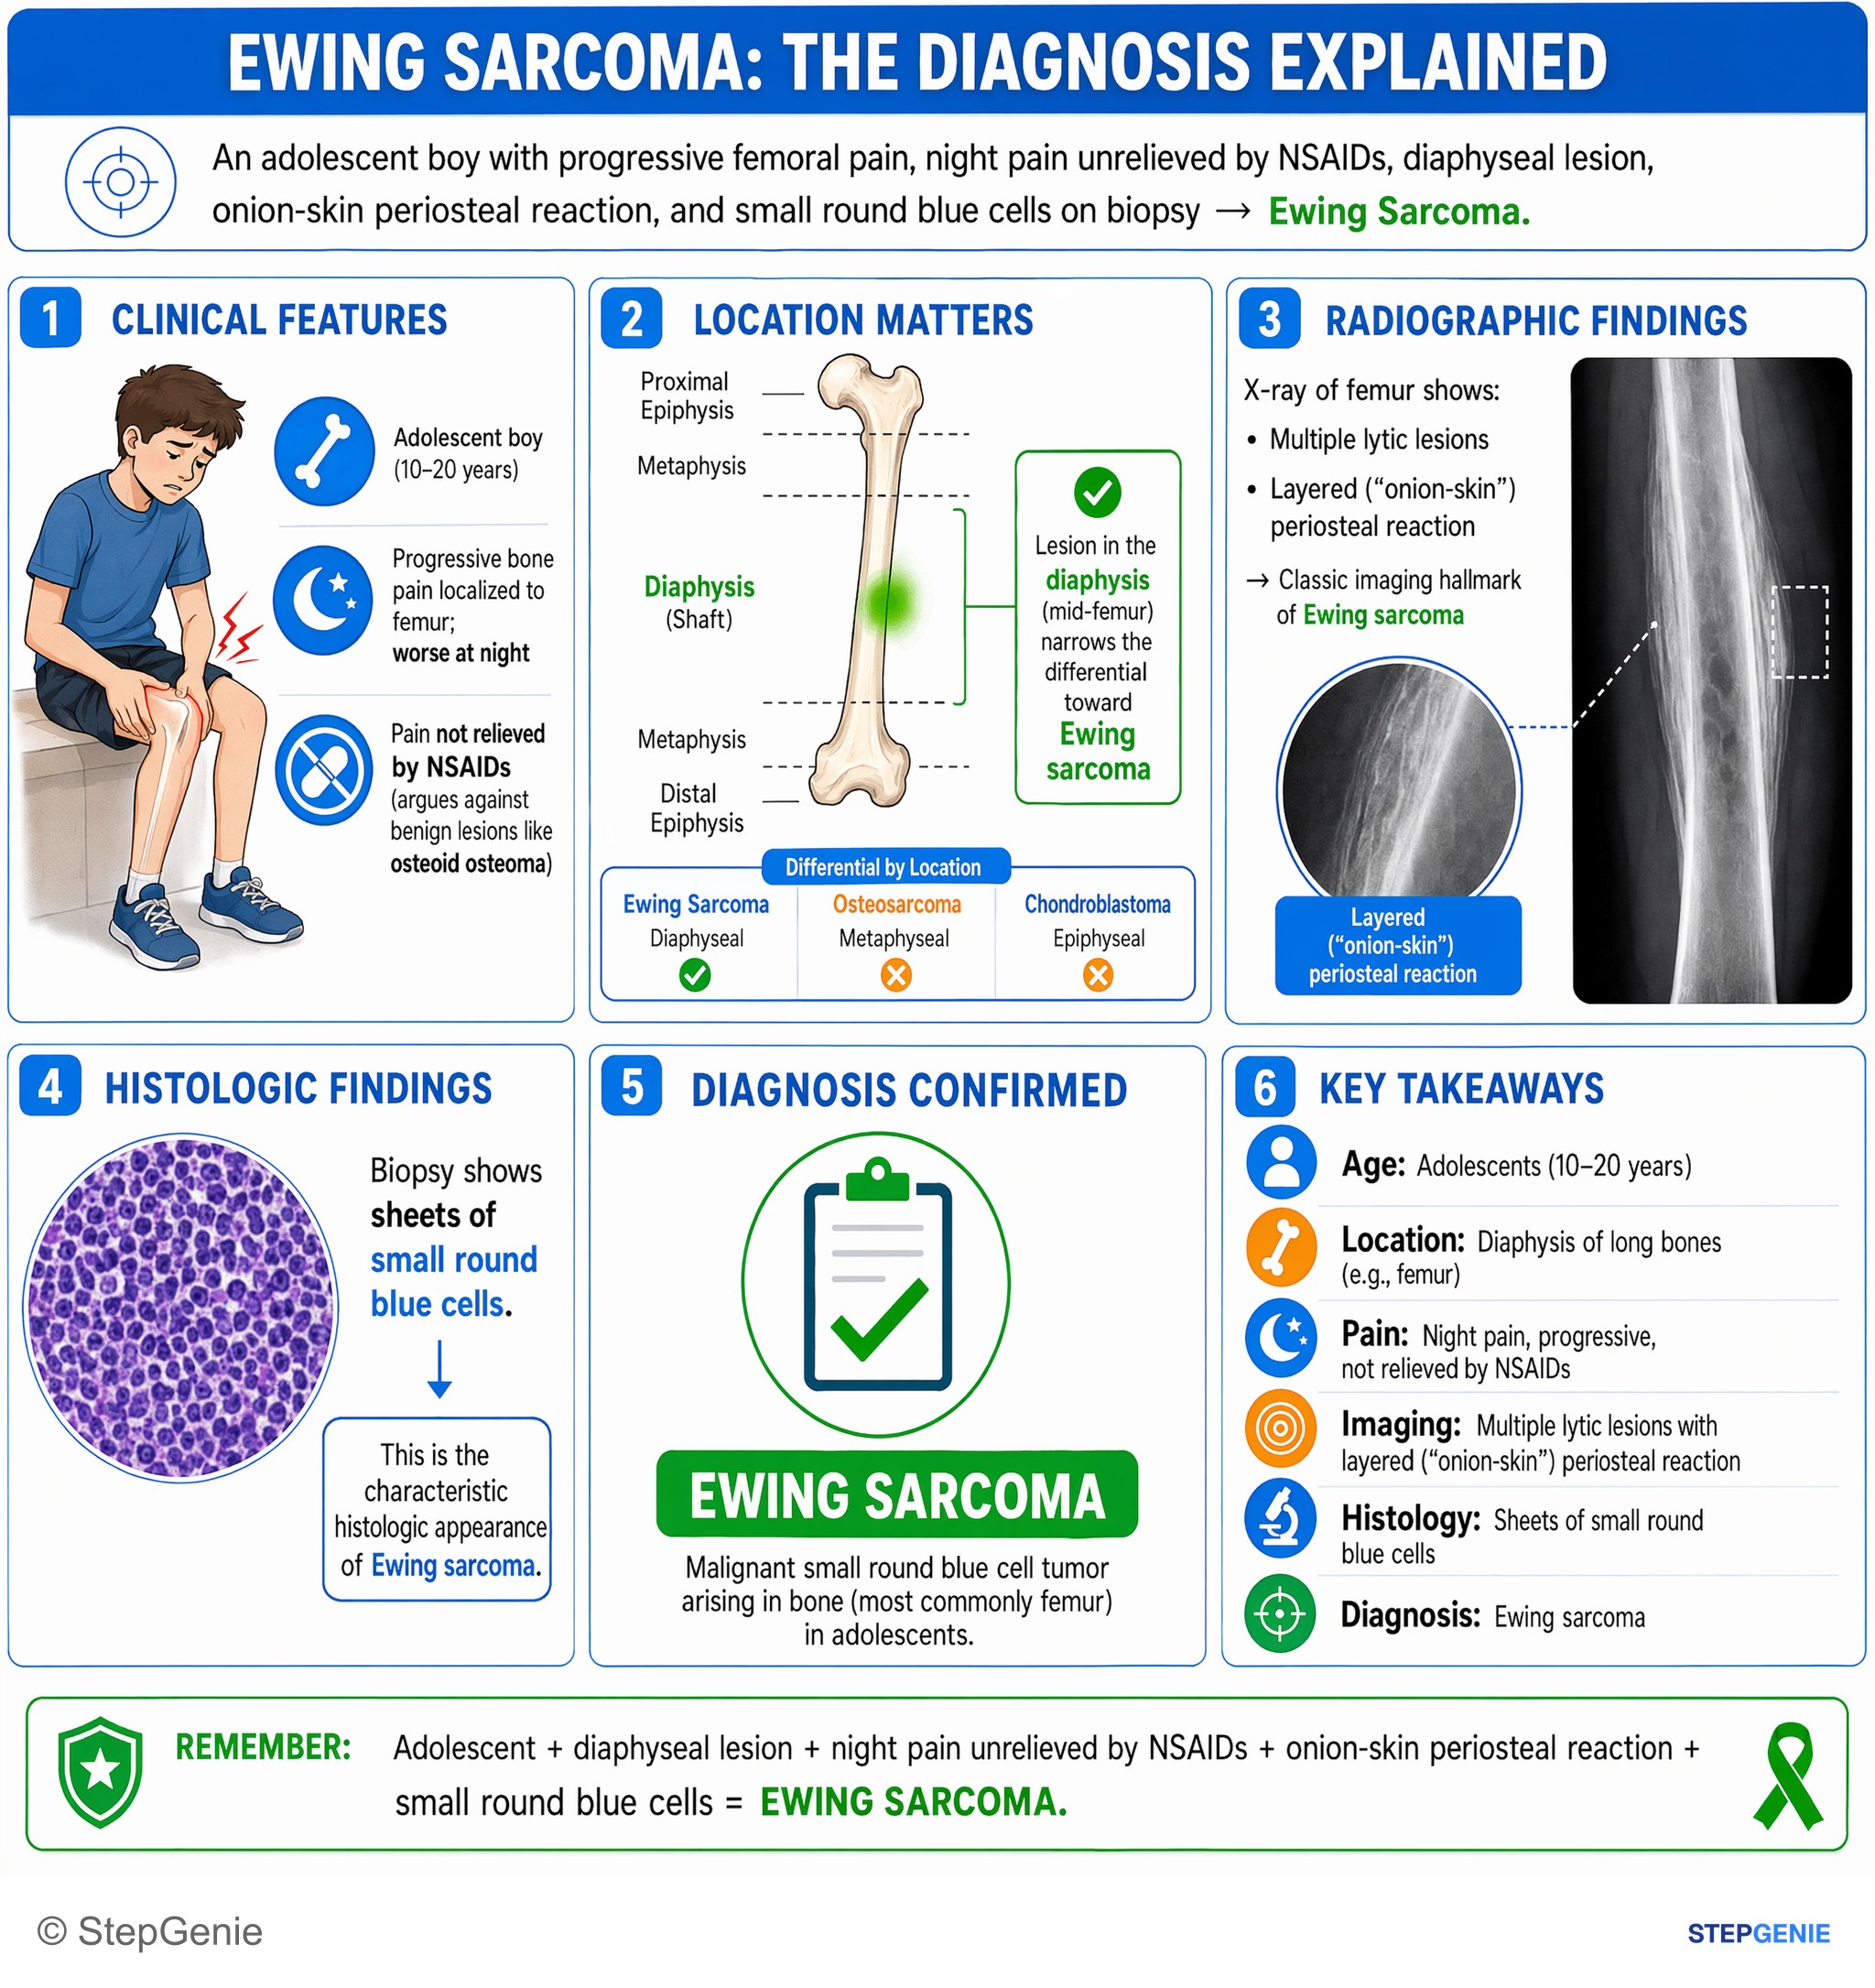
Ewing sarcoma: malignant small round blue cell tumor in adolescents, diaphyseal lesion, onion-skin periosteal reaction, night pain…
USMLE Step 1Frequently Asked Questions
What is the main difference between osteosarcoma and Ewing sarcoma?
Osteosarcoma is made of malignant cells that produce osteoid; it usually arises in the metaphysis around the knee in teenagers and classically shows a sunburst pattern or Codman triangle on x-ray. Ewing sarcoma is a small round blue cell tumor, usually in the diaphysis of a long bone or in the pelvis, with an onion-skin periosteal reaction, CD99 staining and an EWSR1-FLI1 fusion from t(11;22). A biopsy with molecular testing confirms which one it is.
Which is worse, osteosarcoma or Ewing sarcoma?
Neither is uniformly worse; the outlook depends mostly on whether the tumor has spread at diagnosis. The American Cancer Society puts survival at about 60-75% for localized osteosarcoma and 5-30% for metastatic osteosarcoma. For Ewing sarcoma, SEER 5-year relative survival is about 81% for localized and 41% for distant disease. Tumor size, site and response to chemotherapy also matter.
Where does Ewing sarcoma usually occur?
Ewing sarcoma usually involves the diaphysis, or shaft, of long bones, often extending toward the metaphysis, and flat bones such as the pelvis. The pelvis and femur are the most common sites, the ribs, tibia and fibula are also frequent, and about 1 in 5 Ewing sarcomas arise in soft tissue rather than bone. It can occur in almost any bone, including the spine and skull.
What does an onion-skin periosteal reaction mean?
An onion-skin, or lamellated, periosteal reaction is a series of thin concentric layers of new bone. It forms when a lesion grows in spurts, so the periosteum has time to lay down a shell of bone before the next spurt. It is the classic x-ray sign of Ewing sarcoma but also appears with other aggressive processes such as osteomyelitis, so it signals an aggressive lesion rather than a specific diagnosis.
What is a Codman triangle?
A Codman triangle is a small angle of new bone at the edge of a lesion where the periosteum has been lifted off the cortex. It forms when a lesion grows too fast for the periosteum to keep up, so only the edges of the raised periosteum ossify. It is classically described with osteosarcoma, but any rapidly growing process, including infection, can produce it.
What translocation is associated with Ewing sarcoma?
About 85-90% of Ewing sarcomas carry t(11;22)(q24;q12), which fuses EWSR1 on chromosome 22 to FLI1 on chromosome 11 and creates an abnormal transcription factor. About 10% instead have t(21;22), fusing EWSR1 to ERG, and rare tumors use other ETS-family partners. The fusion is detected by FISH, RT-PCR or sequencing of the biopsy.