Osteoporosis is too little bone that is normally mineralized; osteomalacia is bone whose matrix is not mineralized properly; rickets is that same mineralization failure in a growing child, where it also disrupts the growth plates. That is why the labs differ. In osteoporosis, serum calcium, phosphate, alkaline phosphatase (ALP) and PTH are normal. In vitamin D–deficiency osteomalacia and rickets, 25-hydroxyvitamin D and phosphate are low, ALP is high, PTH is usually high, and calcium is low or normal. A low bone density on DXA cannot tell them apart; the chemistry usually can, although the two can coexist.
The lab-pattern table
| Disorder | Calcium | Phosphate | ALP | PTH | Vitamin D | Clue |
|---|---|---|---|---|---|---|
| Osteoporosis | Normal | Normal | Normal | Normal | 25-OH D normal or mildly low | Fragility fracture; T-score −2.5 or lower |
| Osteomalacia (adult, vitamin D deficiency) | Low or normal | Low | High | High or normal | 25-OH D low | Bone pain, muscle weakness, Looser zones |
| Nutritional rickets (child) | Low or normal | Low | High | High | 25-OH D low | Bowed legs, rachitic rosary, swollen wrists, cupped and frayed metaphyses |
| X-linked hypophosphatemic rickets | Normal | Low (urine phosphate high) | Often high | Normal, sometimes mildly high | 25-OH D normal; calcitriol low or inappropriately normal | Rickets that does not respond to vitamin D; FGF23 excess |
| CKD mineral and bone disorder (renal osteodystrophy) | Low or normal | High | Varies with bone turnover | High | Calcitriol low | Kidney disease with secondary hyperparathyroidism |
| Primary hyperparathyroidism | High | Low | Normal or high | High | Not the key test | Hypercalcemia with an inappropriately high PTH |
| Paget disease of bone | Normal (can rise with immobilization) | Normal | High, often in isolation | Normal | Not the key test | Older adult; bone pain or deformity of the pelvis, femur or skull |
How to read it: normal chemistry plus a fracture points to osteoporosis. Low phosphate with high ALP means a mineralization defect: check 25-hydroxyvitamin D (low in nutritional disease) and PTH (high when calcium absorption is the problem, normal in phosphate-wasting XLH). High phosphate points to the kidney, high calcium to the parathyroid, and an isolated high ALP in an older adult to Paget disease, covered in the Paget disease of bone guide.
Why vitamin D deficiency produces that pattern
Low vitamin D → less calcium and phosphate absorbed from the gut → calcium starts to fall → PTH rises → bone resorption and renal calcium retention hold calcium near normal, but PTH makes the kidney waste phosphate → phosphate falls → too little mineral to harden new osteoid → osteomalacia or rickets, with a high ALP from busy osteoblasts.
So calcium can be normal while bone fails to mineralize; the low phosphate is what finally stops mineralization. The liver's 25-hydroxylation and the kidney's 1α-hydroxylation steps, which explain why liver disease and CKD can cause osteomalacia too, are laid out in the vitamin D metabolism overview; antiseizure drugs and glucocorticoids act differently, by raising vitamin D requirements.
Vitamin D status by serum 25-hydroxyvitamin D, per the 2016 Global Consensus on Nutritional Rickets (consistent with the Institute of Medicine): sufficiency above 50 nmol/L (20 ng/mL), insufficiency 30–50 nmol/L (12–20 ng/mL), deficiency below 30 nmol/L (12 ng/mL).
Osteoporosis: less bone, normal mineral
- Definition: a DXA T-score of −2.5 or lower (osteopenia is between −1.0 and −2.5), or a fragility fracture, especially of the spine, hip, humerus or distal radius, whatever the T-score.
- Mechanism: more resorption (RANKL-driven osteoclast activity, loss of estrogen or testosterone) and less formation (fewer, less active osteoblasts with age, partly through sclerostin). The mineral-to-matrix ratio stays normal.
- Fractures: a fall from standing height or less. Vertebral compression fractures are the most common, and about two-thirds cause no symptoms; the femoral neck, greater trochanter and distal radius follow. Multiple thoracic fractures cause kyphosis.
- Labs are for secondary causes: a high calcium suggests hyperparathyroidism or cancer, a low phosphate osteomalacia, and a high ALP Paget disease, liver disease or a recent fracture. Glucocorticoids, hypogonadism, hyperthyroidism, malabsorption and myeloma are other causes to exclude.
- Treatment: calcium, vitamin D, weight-bearing exercise and fall prevention, then bisphosphonates first line (alendronate, risedronate, zoledronic acid). Oral forms are taken on an empty stomach with a full glass of water, staying upright for at least 30 minutes, and can irritate the esophagus; osteonecrosis of the jaw and atypical femoral fractures are rare. Denosumab (anti-RANKL) must not simply be stopped, because rapid bone loss and multiple vertebral fractures can follow; switch to a bisphosphonate. Teriparatide and abaloparatide (PTH analogs) and romosozumab (anti-sclerostin) build bone and work best before an antiresorptive; a PTH-analog course typically lasts about 2 years and romosozumab 1 year, and an antiresorptive must follow or the gain is quickly lost. Raloxifene lowers vertebral but not hip fractures and raises clot risk. Drill the drugs with the bisphosphonates and bone drugs Q-bank.
Osteomalacia: soft adult bone
- Causes: vitamin D deficiency from little sun or poor intake; malabsorption (celiac disease, some weight-loss operations); liver disease; CKD; antiseizure drugs; and phosphate wasting, as in XLH or tumor-induced osteomalacia, where a benign mesenchymal tumor secretes FGF23.
- Symptoms: widespread bone pain (especially in the hips), muscle weakness and fractures with little trauma.
- Radiographs: demineralization and Looser zones (pseudofractures), incomplete ribbon-like lucent bands in the cortex.
- Treatment: replace vitamin D and calcium. Merck notes that vitamin D3 1,600 IU a day cures uncomplicated osteomalacia when calcium and phosphate intake is adequate; ALP falls within about 10 days. Malabsorption may need larger doses, and CKD needs calcitriol because the kidney cannot activate vitamin D.
Rickets: the growing skeleton
- Clinical signs: craniotabes (soft skull bones in the first months), delayed fontanelle closure, frontal bossing, a rachitic rosary of enlarged costochondral junctions, swollen wrists and ankles, bowed legs or knock-knees, delayed tooth eruption, and hypocalcemic tetany or seizures.
- Radiographs: widened growth plates with cupped, frayed and splayed metaphyses, best seen at the wrists and knees.
- Treatment of nutritional rickets: at least 2,000 IU of vitamin D a day for at least 3 months, plus 500 mg of calcium a day. Prevention: 400 IU a day for every infant in the first year, however the baby is fed.
- Calcium-deficiency rickets: after 12 months of age, a dietary calcium intake below 300 mg a day raises the risk of rickets even when vitamin D is adequate.
- Genetic look-alikes: XLH (X-linked dominant PHEX mutation → high FGF23 → renal phosphate wasting; treated with burosumab, an anti-FGF23 antibody, or with oral phosphate plus calcitriol); vitamin D–dependent rickets type 1 (1α-hydroxylase deficiency: normal 25-OH D, low calcitriol and calcium; treated with calcitriol); and type 2 (a defective vitamin D receptor, so calcitriol is plentiful but ineffective).
Exam traps
- Low bone density is not proof of osteoporosis. Osteomalacia also lowers density on DXA and radiographs; check calcium, phosphate, ALP, PTH and 25-hydroxyvitamin D.
- A normal calcium does not exclude vitamin D deficiency, because secondary hyperparathyroidism props it up while phosphate falls.
- A high ALP in a child can simply reflect growth; rickets is high ALP with low phosphate and growth-plate changes on radiographs.
- Rickets with very low phosphate but normal calcium and PTH that ignores vitamin D is XLH.
- Correct vitamin D deficiency and hypocalcemia before an antiresorptive; denosumab is contraindicated in hypocalcemia.
- Stopping denosumab without a bisphosphonate can trigger rebound vertebral fractures.
Worked example
Vignette. A 46-year-old woman who had a Roux-en-Y gastric bypass 6 years ago has 8 months of diffuse bone pain, aching thighs and difficulty rising from a chair. DXA shows a lumbar spine T-score of −2.6. Serum calcium is low-normal, phosphate is low, ALP and PTH are high, and 25-hydroxyvitamin D is 8 ng/mL. A pelvic radiograph shows an incomplete lucent band crossing the cortex of one bone. What is the best initial treatment?
Answer: Vitamin D and calcium repletion for osteomalacia caused by malabsorption after bariatric surgery, with doses higher than usual because absorption is impaired. A bisphosphonate is not the first step.
Why not the others?
- Osteoporosis treated with a bisphosphonate: the T-score fits, but osteoporosis has normal phosphate, ALP and PTH, and DXA cannot tell missing bone from undermineralized bone.
- Primary hyperparathyroidism: PTH is high, but calcium would be high rather than low-normal.
- Paget disease: ALP is high, but calcium and phosphate are normal and the disease is focal, usually in the pelvis, femur or skull.
- X-linked hypophosphatemia: lifelong phosphate wasting with a normal PTH and 25-hydroxyvitamin D; this patient's disease is acquired.
Key takeaways
- Osteoporosis: less bone, normal mineral, normal labs; diagnosed by a T-score of −2.5 or lower or a fragility fracture; bisphosphonates first line.
- Osteomalacia and rickets: undermineralized osteoid with low 25-OH D and phosphate, high ALP, usually high PTH, and low or normal calcium.
- Rickets adds growth-plate findings: bowing, rosary, swollen wrists, cupped and frayed metaphyses.
- Low phosphate with a normal PTH → XLH (FGF23); high phosphate → CKD; high calcium → hyperparathyroidism; isolated high ALP → Paget disease.
- Treat the cause: vitamin D and calcium (calcitriol in CKD); don't start an antiresorptive in a patient who is vitamin D deficient and hypocalcemic.
Sources
- Vitamin D Deficiency and Dependency (Rickets; Osteomalacia) — Merck Manual Professional Edition
- Osteoporosis — Merck Manual Professional Edition
- Differentiating Osteoporosis and Osteomalacia (table) — Merck Manual Professional Edition
- Munns CF, Högler W, et al. Global Consensus Recommendations on Prevention and Management of Nutritional Rickets (2016), accepted manuscript — University of Birmingham
- Hypophosphatemic Rickets — Merck Manual Professional Edition
- Paget Disease of Bone — Merck Manual Professional Edition
- Hypercalcemia — Merck Manual Professional Edition
- Chronic Kidney Disease — Merck Manual Professional Edition
- Osteoporosis: Part I. Evaluation and Assessment — American Family Physician
- Osteomalacia — MedlinePlus Medical Encyclopedia
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
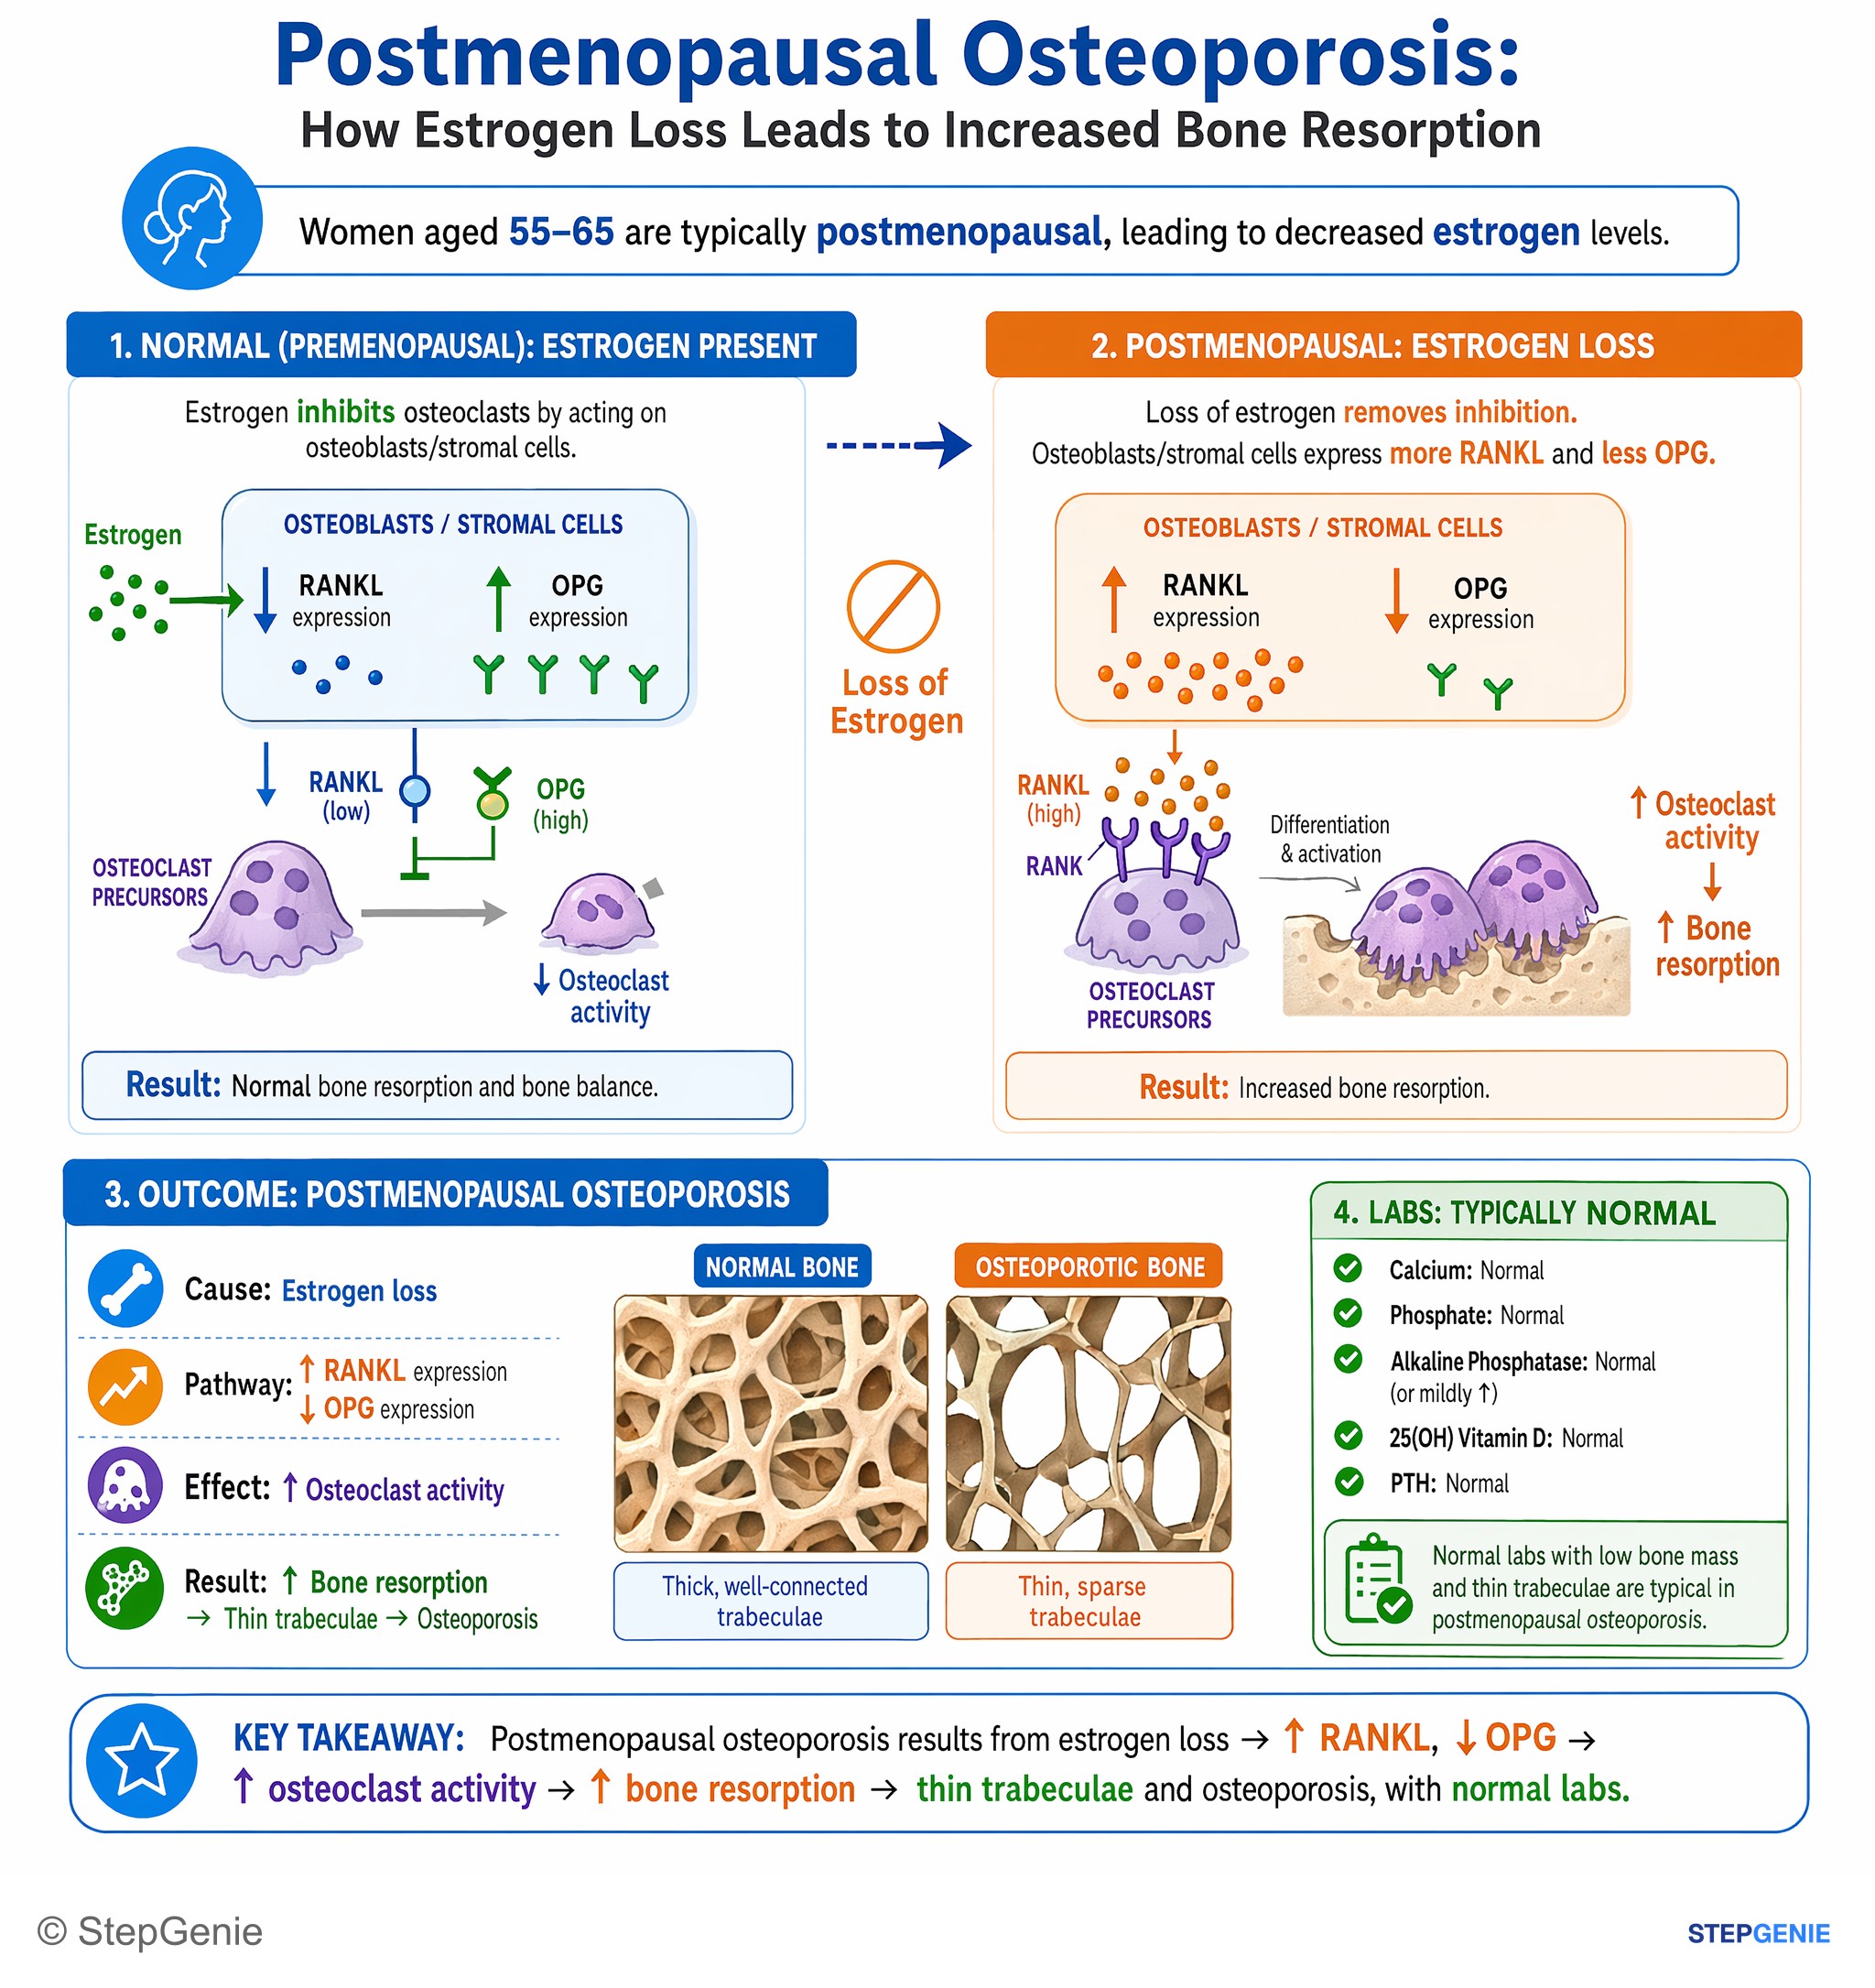
Postmenopausal osteoporosis from estrogen loss → ↑ RANKL expression → ↑ osteoclast activity → bone resorption with normal labs and thin…
USMLE Step 1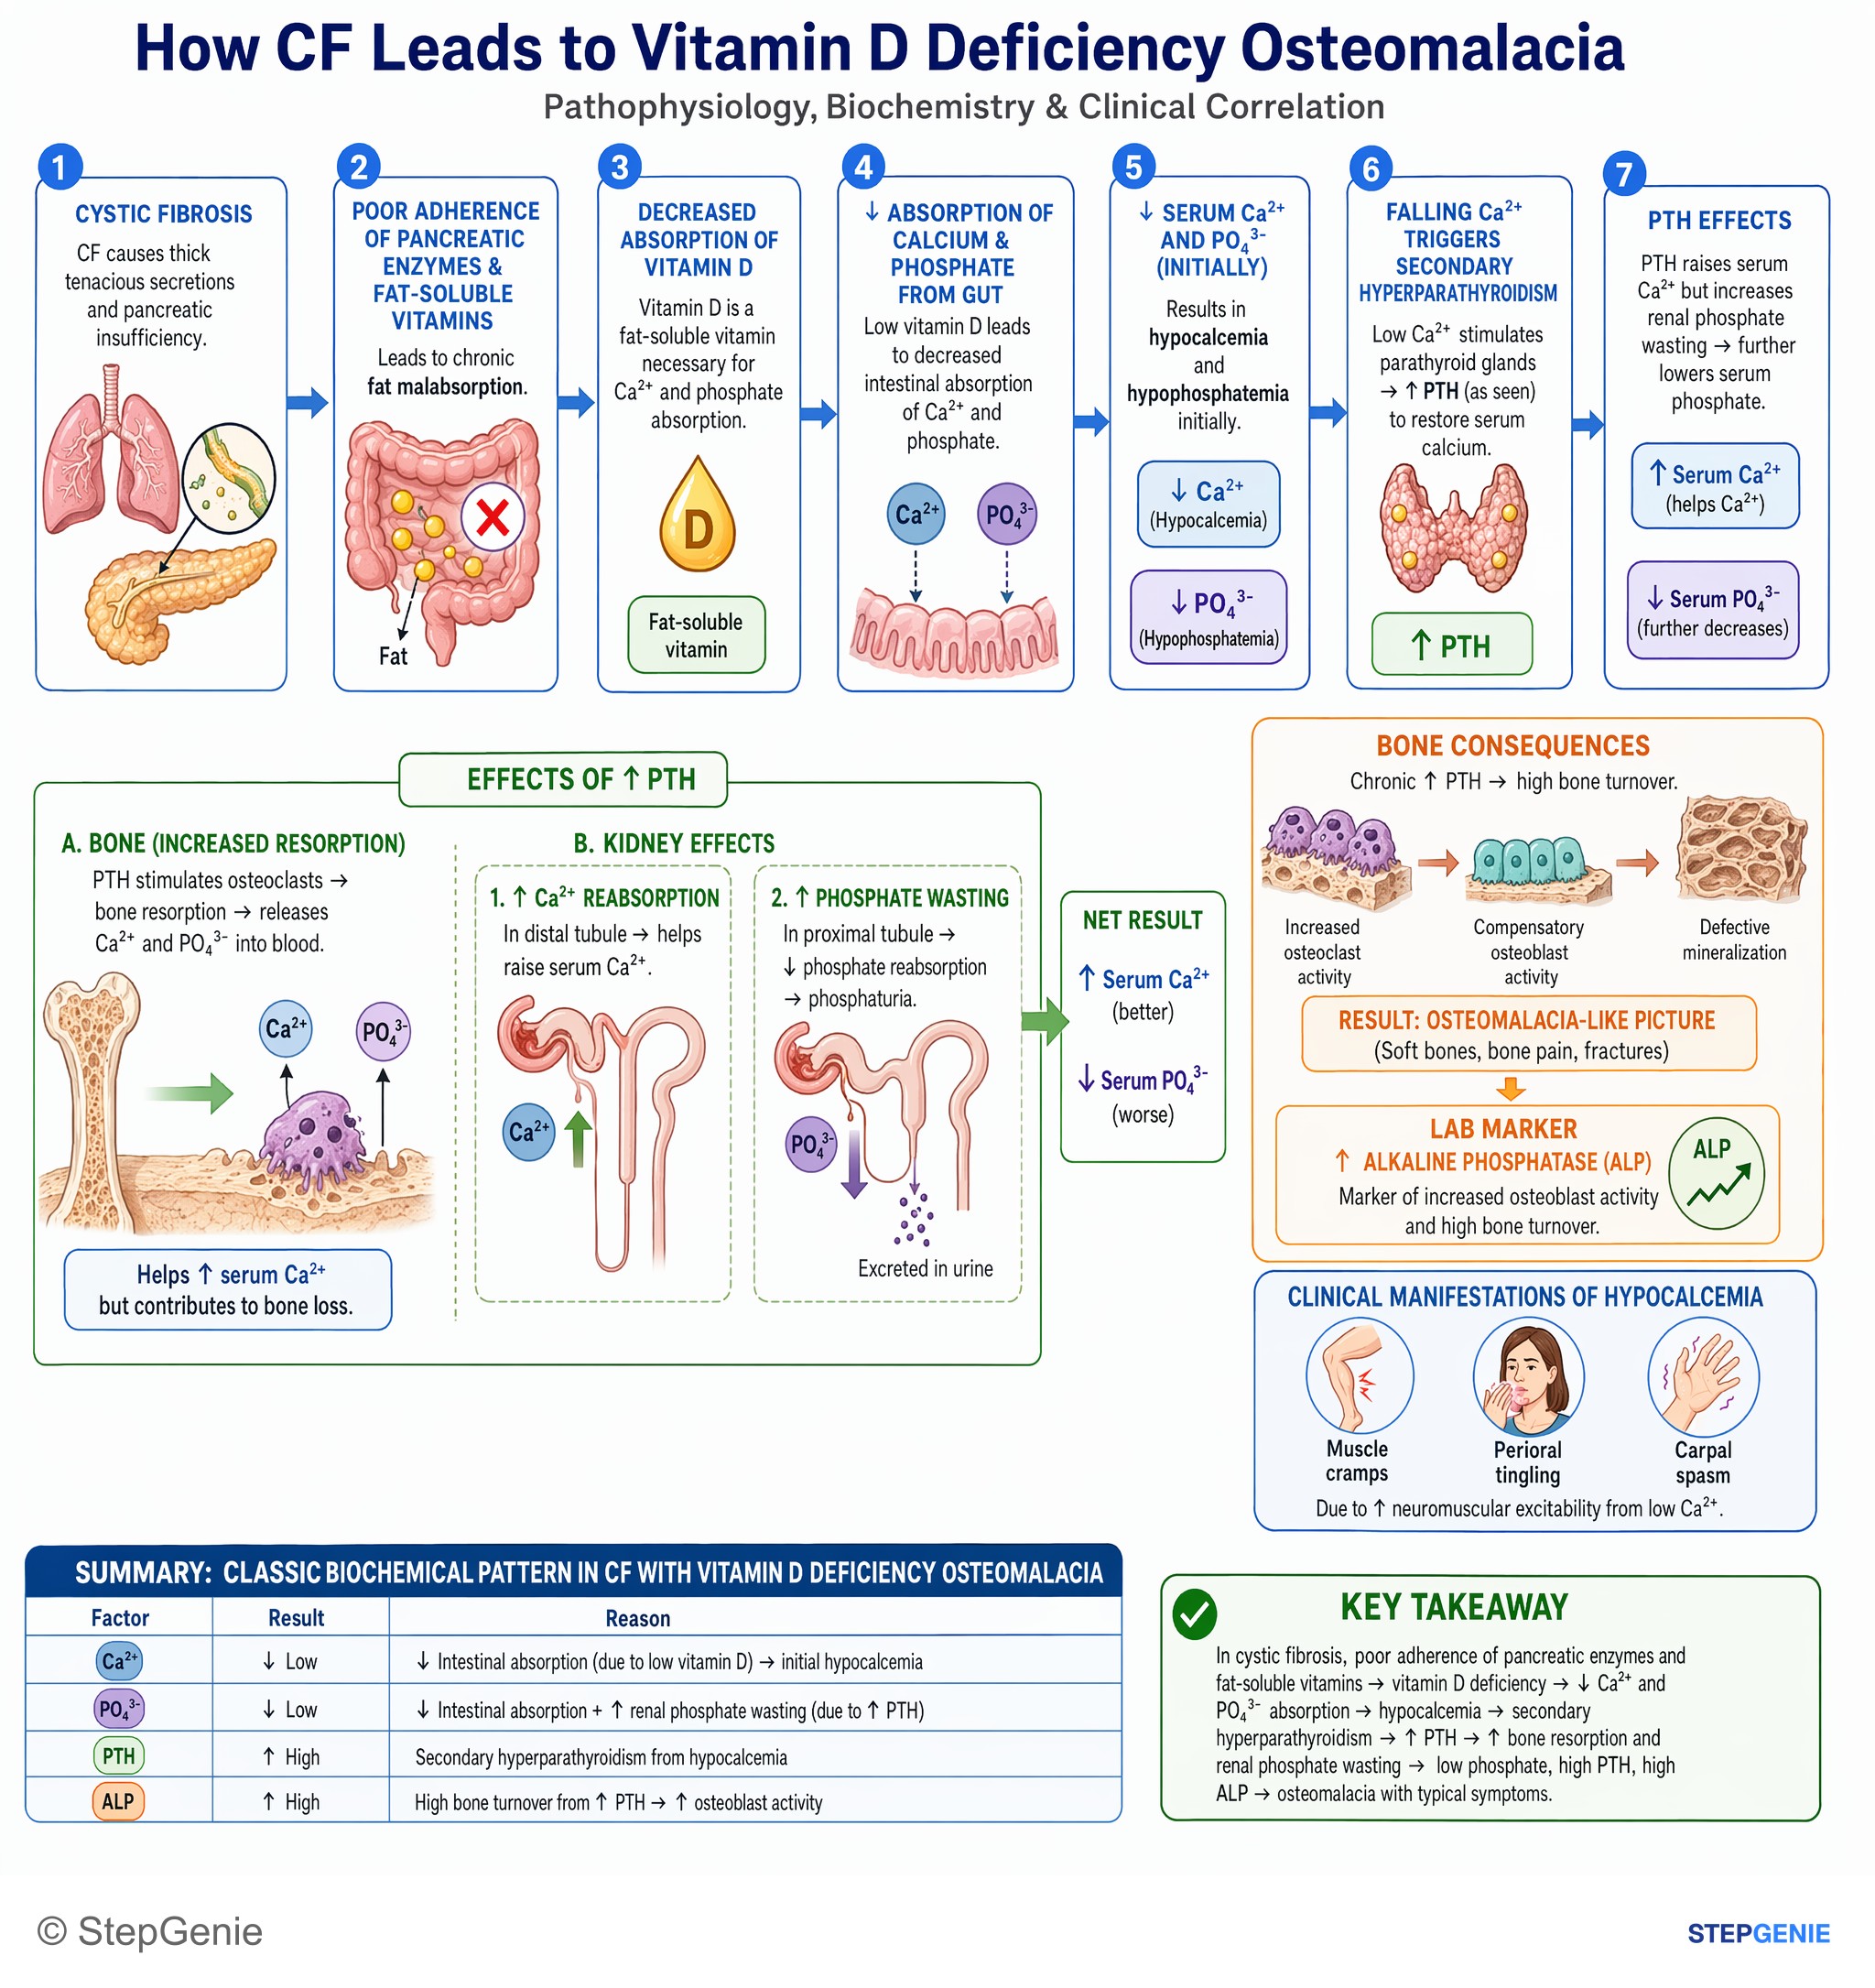
Vitamin D deficiency osteomalacia from malabsorption in cystic fibrosis → low Ca²⁺, secondary hyperparathyroidism → low phosphate, high…
USMLE Step 1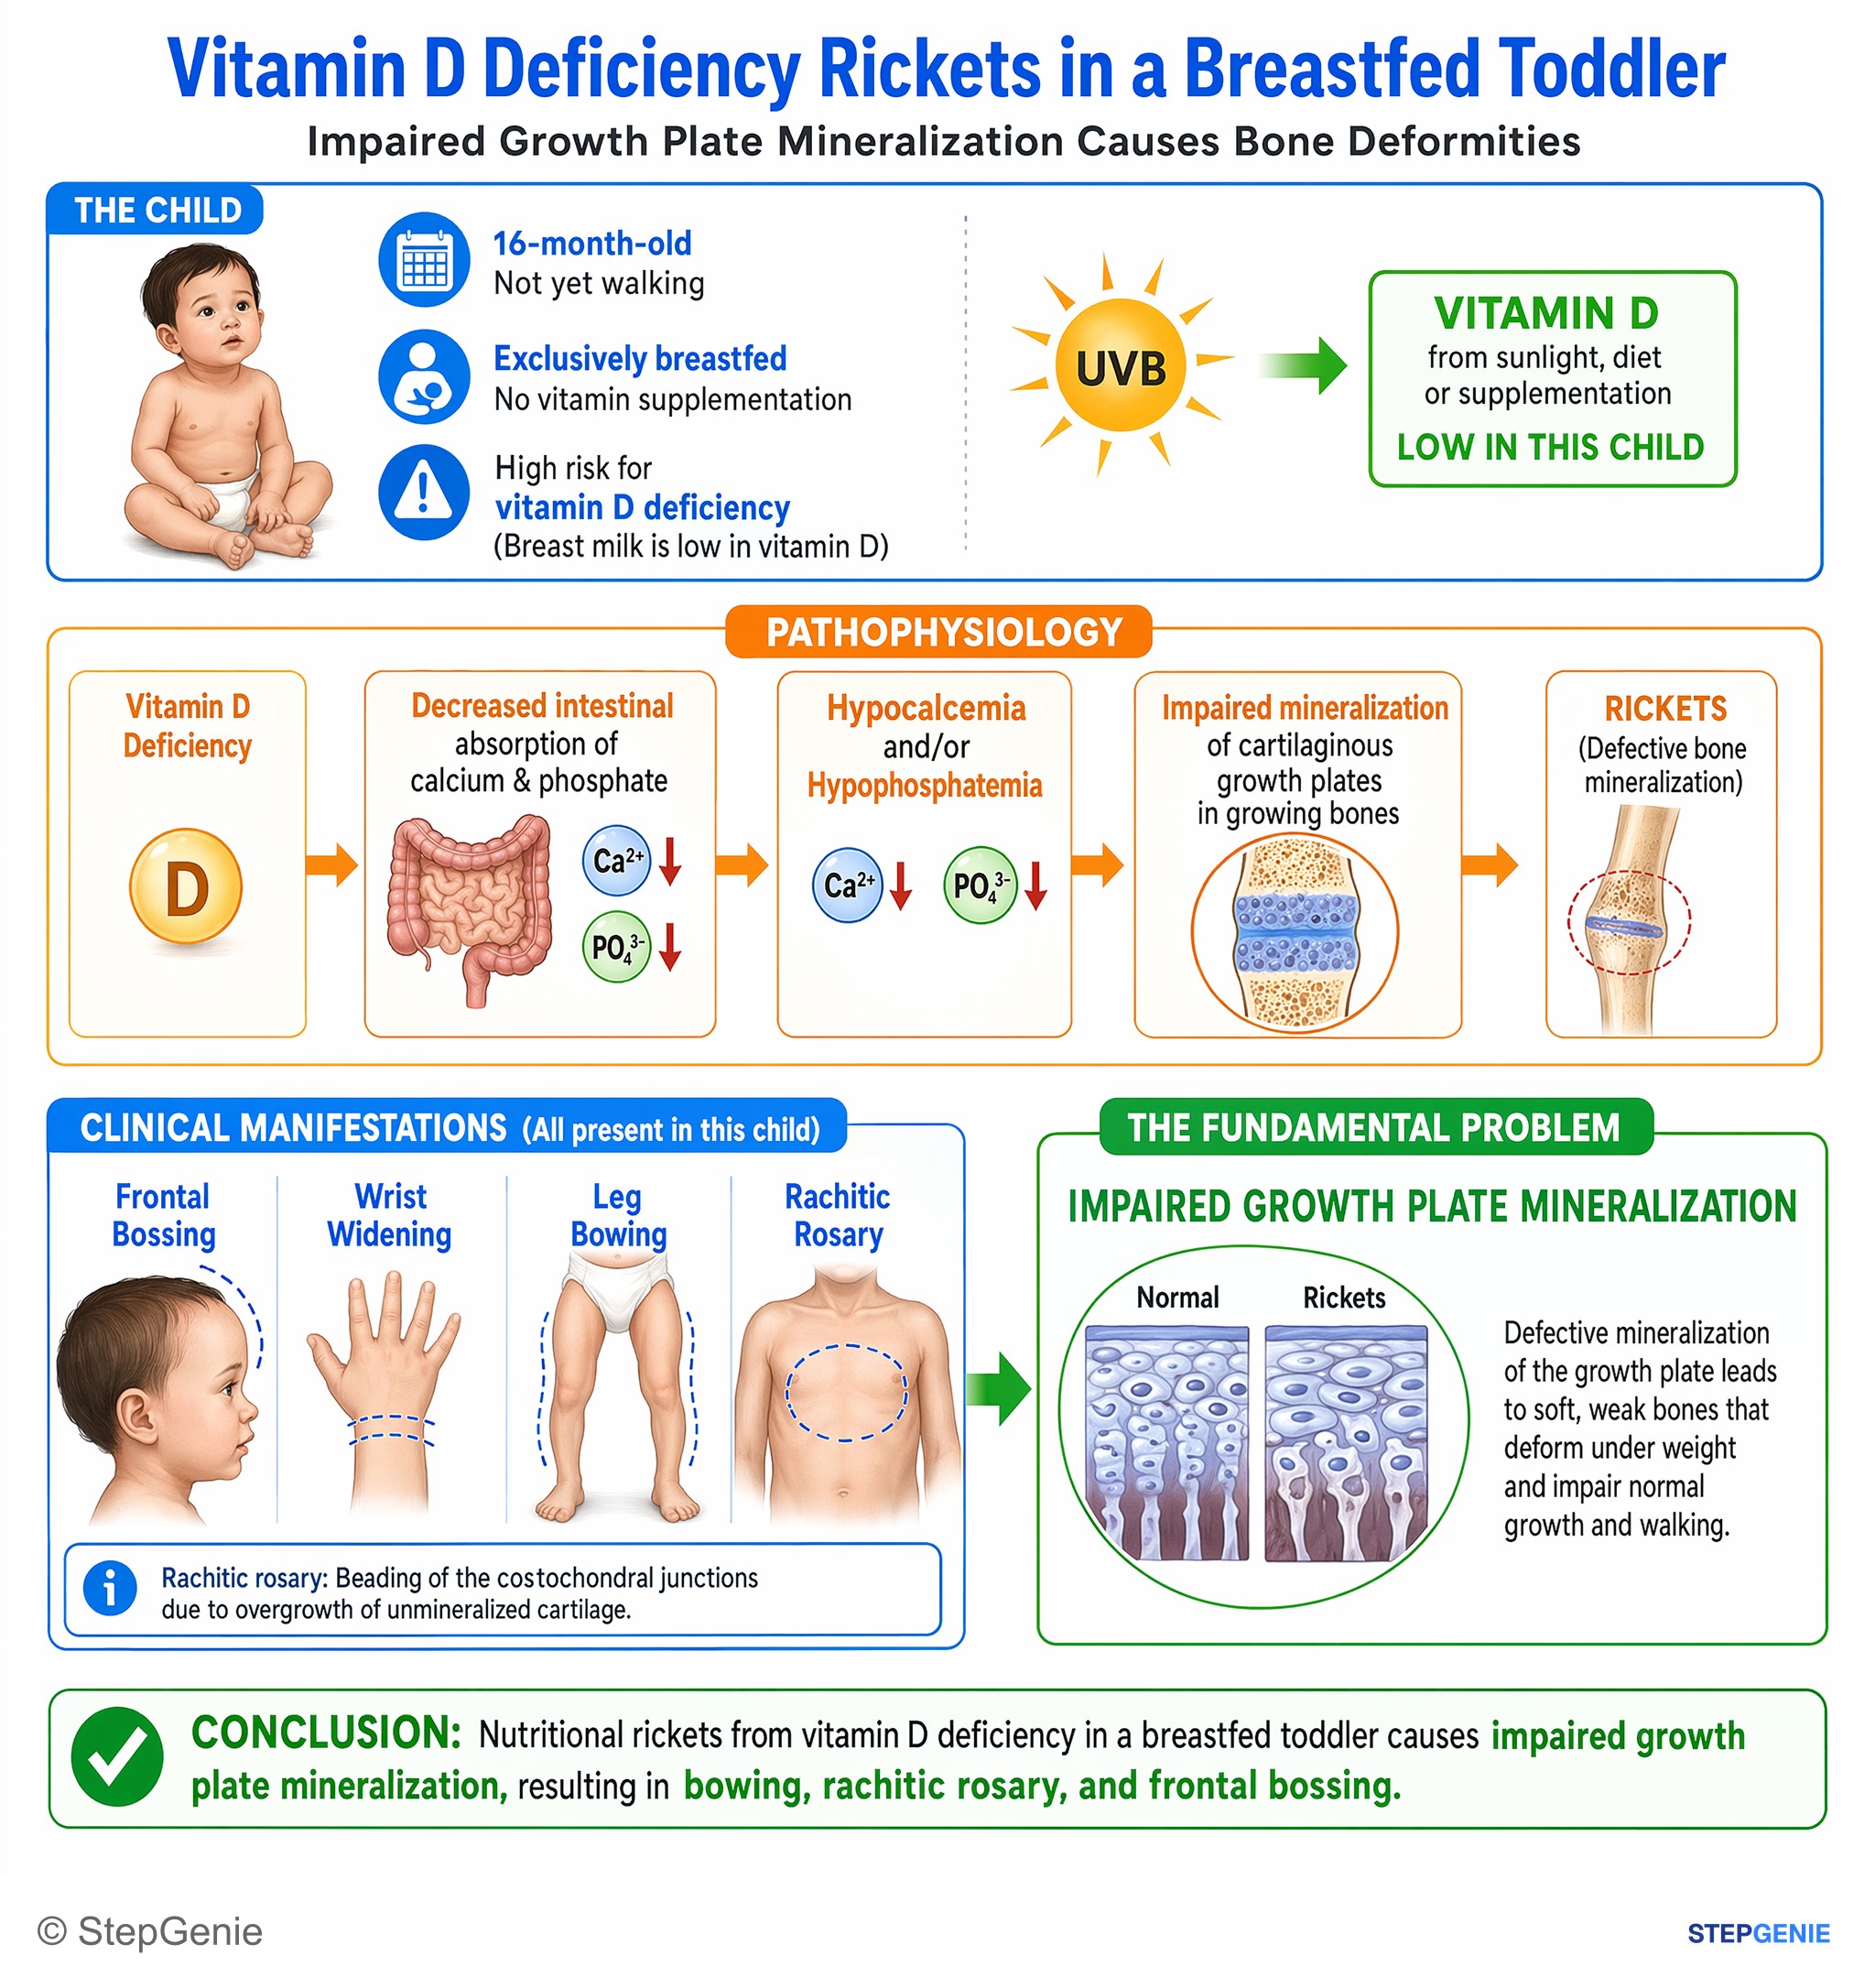
Nutritional rickets from vitamin D deficiency in a breastfed toddler causes impaired growth plate mineralization with bowing, rachitic…
USMLE Step 1Frequently Asked Questions
How do you tell osteoporosis from osteomalacia on labs?
In osteoporosis, bone mass is low but the bone that remains is normally mineralized, so serum calcium, phosphate, alkaline phosphatase and PTH are normal. In osteomalacia from vitamin D deficiency, 25-hydroxyvitamin D and phosphate are low, alkaline phosphatase is high, PTH is usually high, and calcium is low or normal. Both can lower bone density on DXA, so the chemistry, not the T-score, separates them.
Why is calcium often normal in vitamin D deficiency?
When vitamin D is low, less calcium is absorbed and serum calcium starts to fall, which stimulates PTH. PTH releases calcium from bone and helps the kidney retain it, so serum calcium is often held in the normal range. The same PTH makes the kidney waste phosphate, and the resulting low phosphate is what impairs mineralization and produces osteomalacia or rickets.
What are the classic findings of rickets?
Rickets affects the growth plates of a growing child. Clinical clues include craniotabes in young infants, delayed fontanelle closure, frontal bossing, a rachitic rosary of enlarged costochondral junctions, swollen wrists and ankles, bowed legs or knock-knees, delayed tooth eruption, and hypocalcemic tetany or seizures. Radiographs show widened growth plates with cupped, frayed metaphyses, most clearly at the wrists and knees.
How is X-linked hypophosphatemic rickets different from nutritional rickets?
X-linked hypophosphatemia is caused by PHEX mutations that raise FGF23, which makes the kidney waste phosphate and blunts calcitriol production. Serum phosphate is low while urine phosphate is high, but calcium, PTH and 25-hydroxyvitamin D are usually normal, and the rickets does not respond to ordinary vitamin D. Burosumab, an anti-FGF23 antibody, is now the treatment of choice; oral phosphate plus calcitriol is the older approach.
What is the first-line treatment for osteoporosis versus osteomalacia?
Osteomalacia is treated by restoring the mineral supply: vitamin D with calcium, phosphate if needed, calcitriol when kidney disease blocks vitamin D activation, and treatment of any malabsorption. Osteoporosis is treated with calcium, vitamin D, weight-bearing exercise and fall prevention plus drug therapy, with bisphosphonates first line; denosumab, anabolic agents such as teriparatide or romosozumab, and raloxifene suit selected patients.