Osteomyelitis is infection and destruction of bone. Bacteria reach bone through the bloodstream (hematogenous spread: the long-bone metaphyses in children, the vertebrae in adults), by spreading from nearby infected tissue such as a diabetic foot ulcer or an infected joint replacement, or through an open wound such as an open fracture, surgery or a puncture wound; contiguous spread and open wounds together cause about 80% of cases. Staphylococcus aureus is the most common cause in nearly every setting; the classic exceptions are Salmonella in sickle cell disease, Pseudomonas after a puncture wound of the foot and polymicrobial infection in the diabetic foot. X-rays lag behind the infection, MRI is the imaging test of choice, and bone culture identifies the organism so antibiotics can be targeted, usually for about 6 weeks in adults.
Three routes into bone
| Route | Who gets it | Where | Usual organisms |
|---|---|---|---|
| Hematogenous (bloodstream) | Children; adults who are older, debilitated, on hemodialysis or inject drugs | Children: metaphysis of the femur, tibia or humerus. Adults: vertebrae | S. aureus (MRSA is common); enteric gram-negative rods in older adults |
| Contiguous spread (together with open wounds, about 80% of cases) | Diabetic foot ulcers, pressure injuries, infected prosthetic joints | Foot, pressure sites, around implants | Often polymicrobial: S. aureus in at least half, plus streptococci, gram-negative enterics and anaerobes |
| Direct inoculation | Open fractures, bone surgery, puncture wounds, bites | The wound site | S. aureus; Pseudomonas after a deep foot puncture; Pasteurella or Eikenella after bites |
In children, hematogenous infection settles in the metaphysis next to the growth plate. The classic explanation: metaphyseal vessels have leaky endothelium and sluggish flow and end in capillary loops, so bacteria lodge where the physis meets the metaphysis. Long bones dominate, but 10-25% of pediatric cases involve short or non-tubular bones such as the pelvis, vertebrae, clavicle or calcaneus (PIDS/IDSA).
Match the organism to the stem
| Clue in the stem | Think | Why it fits |
|---|---|---|
| No special risk factor, child or adult | S. aureus | Most common cause overall; cover MRSA based on local rates |
| Sickle cell disease | Salmonella (the classic answer) | Splenic autoinfarction (functional asplenia) raises the risk of Salmonella infection, including osteomyelitis |
| Nail through a sneaker (deep plantar puncture) | Pseudomonas aeruginosa | Deep puncture wounds of the foot can cause draining sinuses, cellulitis and osteomyelitis |
| Injection drug use | S. aureus; also Pseudomonas and Serratia | Pseudomonas bone and joint infection favors the spine, pubic bone and sternoclavicular joint |
| Diabetic foot ulcer or pressure injury | Polymicrobial | S. aureus, streptococci, gram-negative rods, anaerobes |
| Prosthetic joint or hardware | S. aureus; coagulase-negative staphylococci (S. epidermidis) | Biofilm on foreign material; Cutibacterium acnes in shoulder implants can need up to 2 weeks of culture |
| Cat or dog bite / human bite | Pasteurella multocida / Eikenella corrodens | Hand bites, especially clenched-fist injuries, can reach joints and bone |
| Young child with bone or joint infection | Consider Kingella kingae | PIDS/IDSA lists younger age as a reason to cover it |
| Subacute back pain with TB risk, paravertebral abscess | M. tuberculosis (Pott disease) | Starts in a vertebral body and spreads to adjacent vertebrae with disc-space narrowing; untreated, vertebrae can collapse onto the cord |
More on the bugs: S. aureus toxins and MRSA, Pseudomonas clues and mimics, the infections and crises of sickle cell disease, and tuberculosis.
Why bone infection turns chronic
- Vessels occlude. Infection occludes local blood vessels, so bone dies; pus can spread under the periosteum, form subcutaneous abscesses and drain through the skin via a sinus tract.
- Sequestrum: a dead, infected bone fragment that separates from living bone. It has no blood supply, so antibiotics reach it poorly and it usually has to be excised for cure. Involucrum: a thick sheath of new periosteal bone that can encase the sequestrum.
- Acute vs chronic (PIDS/IDSA): acute is diagnosed within 4 weeks of symptom onset; chronic is marked by a sequestrum and/or relapse at the same site weeks to years after apparently successful treatment.
- Biofilm: coagulase-negative staphylococci such as S. epidermidis form biofilms on foreign material, and infected implants are often removed or exchanged; rifampin is added to antistaphylococcal regimens for prosthetic joint infection to improve biofilm penetration.
- Marjolin ulcer: squamous cell carcinoma can arise in a chronic osteomyelitic lesion or burn scar, on average about 30 years after the injury. Biopsy an old sinus or ulcer that enlarges, bleeds easily or develops raised margins.
Presentation
- Child: fever, focal bone pain and tenderness, limp or refusal to use the limb.
- Adult, vertebral: constant localized back pain and tenderness with paravertebral spasm, unresponsive to conservative care; often afebrile. Cord or root compression (for example from an epidural abscess) adds radicular pain, weakness or numbness.
- Diabetic foot: a chronic ulcer over a bony prominence, often painless because of neuropathy; exposed bone or a positive probe-to-bone test raises suspicion.
- Chronic: intermittent bone pain and draining sinuses over months to years. Labs: leukocytosis, raised ESR and CRP, often anemia and thrombocytosis; markers can be normal with indolent organisms.
Diagnosis: from X-ray to bone culture
| Test | What it adds | Exam takeaway |
|---|---|---|
| ESR, CRP | Raised but nonspecific | Diabetic foot: ESR ≥70 mm/h supports osteomyelitis (sensitivity 0.81, specificity 0.80); trend CRP to judge response |
| Blood cultures | Positive in about 31% of children with acute hematogenous osteomyelitis | Draw before antibiotics; in suspected vertebral osteomyelitis, S. aureus, S. lugdunensis or Brucella bacteremia makes a biopsy unnecessary |
| Plain X-ray | First study; later periosteal elevation, bone destruction, sequestra | Often normal early: changes may not show for 5-7 days in children or 10-14 days in adults (Merck: abnormal after 2-4 weeks); lysis appears only after a large share of bone is lost (30-50% of mineral content per Radiopaedia, 50-75% of matrix per AAFP) |
| MRI | Marrow edema, abscess, epidural and soft-tissue spread | Imaging test of choice (IDSA, PIDS/IDSA, IWGDF/IDSA) |
| CT | Cortical destruction, sequestra, involucrum | Surgical planning; PIDS/IDSA prefers MRI for diagnosis |
| Three-phase bone scan | Turns positive earlier than X-ray | Cannot tell infection from fracture or tumor |
| Labeled leukocyte scan, PET, SPECT | Localizes infection | Alternatives when MRI is not possible (IWGDF/IDSA) |
| Bone biopsy for culture and histology | Organism and susceptibilities | Definitive test; percutaneous or surgical |
- Probe-to-bone test (diabetic foot): sensitivity 0.87, specificity 0.83. A positive probe in a high-risk patient suggests osteomyelitis; a negative probe helps rule it out only in a low-risk patient.
- Vertebral osteomyelitis (IDSA 2015): two sets of blood cultures, ESR and CRP, then spine MRI; image-guided aspiration biopsy if blood cultures (or Brucella serology) do not identify a likely organism. In a stable patient with a normal neurologic exam, hold empiric antibiotics until the organism is known; start them at once for sepsis, hemodynamic instability or severe or progressive neurologic deficits. In subacute disease, test for Brucella in endemic areas and for TB in at-risk patients.
Treatment: culture, then targeted antibiotics and source control
- Empiric therapy (when it cannot wait): nafcillin or oxacillin, or vancomycin where MRSA is common, plus a third- or fourth-generation cephalosporin (ceftazidime or cefepime). Chronic contiguous infections often get ampicillin-sulbactam or piperacillin-tazobactam, adding vancomycin for severe infection or likely MRSA.
- Source control: debride dead bone, drain abscesses (including paravertebral and epidural ones), stabilize the spine, and remove or exchange infected hardware when needed.
| Setting | Usual course | Guidance |
|---|---|---|
| Child, uncomplicated acute hematogenous (S. aureus) | 3-4 weeks; switch to an oral drug rather than outpatient IV therapy when a suitable one exists | PIDS/IDSA 2021 |
| Adult native vertebral osteomyelitis | 6 weeks of IV or highly bioavailable oral therapy; 3 months for Brucella | IDSA 2015 |
| Diabetic foot osteomyelitis, no bone resected | About 6 weeks | IWGDF/IDSA 2023 |
| Diabetic foot, minor amputation with a positive bone margin | Up to 3 weeks | IWGDF/IDSA 2023 |
| Prosthetic joint infection with S. aureus | Prosthesis removal, debridement and one- or two-stage replacement, plus 6 weeks of targeted therapy with rifampin | Merck |
- IV vs oral: classic teaching is 4-6 weeks of IV antibiotics (Merck still lists 4-8 weeks of parenteral therapy for chronic contiguous-spread infection), but AAFP's 2021 review, citing the OVIVA trial, reports similar cure rates with oral antibiotics at lower risk and cost, and IWGDF/IDSA notes that oral regimens for residual diabetic foot osteomyelitis have failure rates similar to IV regimens.
- Diabetic foot: resect infected bone plus antibiotics, or antibiotics alone for selected forefoot osteomyelitis without peripheral artery disease or exposed bone; remission is judged at least 6 months after antibiotics end.
- Vertebral: operate for progressive neurologic deficits, progressive deformity or spinal instability despite adequate antibiotics; skip routine follow-up MRI when the patient is improving.
How USMLE tests it
| Look-alike | What points to it | Key test |
|---|---|---|
| Septic arthritis | Hot, swollen joint with effusion; restricted active and passive motion | Arthrocentesis: synovial WBC usually above 50,000/mcL (a lower count does not exclude it), Gram stain, culture, crystals |
| Gout | Sudden podagra (first MTP joint), recurrent flares | Needle-shaped, negatively birefringent crystals in joint fluid; serum urate is normal in at least 30% of flares |
| Pott disease | Subacute back pain, TB risk, paravertebral abscess | TB testing and biopsy; MRI shows soft-tissue spread |
See septic arthritis organisms and synovial WBC cut-offs and gout vs pseudogout for the joint side of the differential. Classic traps: a normal X-ray does not exclude early osteomyelitis; swabs of an ulcer or sinus mislead, so culture bone; in stable vertebral disease, biopsy before antibiotics.
Practice question
A 61-year-old man with type 2 diabetes and peripheral neuropathy has had an ulcer under his right first metatarsal head for 8 weeks despite dressing changes and offloading. He has no fever. The ulcer is 2 cm wide with a granulating base and minimal surrounding erythema; a sterile metal probe does not reach bone. Dorsalis pedis and posterior tibial pulses are palpable. ESR is 84 mm/h, CRP is raised and the WBC count is normal. Plain radiographs of the foot show no bone abnormality. Which is the most appropriate next step in diagnosis?
A. Arthrocentesis of the first metatarsophalangeal joint B. MRI of the right foot C. Serum uric acid level D. Superficial swab culture of the ulcer base E. Three-phase technetium-99m bone scan
Answer: B. A chronic ulcer over a bony prominence with an ESR above 70 mm/h keeps osteomyelitis likely, even though the probe did not reach bone (a negative probe only helps rule it out in low-risk patients) and the X-ray is normal (lytic change appears only after a large share of bone is lost). IWGDF/IDSA advise MRI when the diagnosis remains in doubt after clinical assessment, X-rays and labs. If MRI shows osteomyelitis, a bone specimen (percutaneous or surgical) for culture comes next so therapy can be targeted.
- A: arthrocentesis diagnoses septic or crystal arthritis, which present as an acutely hot, swollen, painful joint; this is a chronic, ulcer-centered process.
- C: serum urate is a poor test for gout (normal in at least 30% of flares), and gout does not explain a nonhealing plantar ulcer.
- D: superficial swabs grow colonizers; IWGDF/IDSA favor tissue specimens over swabs and bone over soft tissue when osteomyelitis is suspected.
- E: a bone scan turns positive early but cannot distinguish infection from fracture or tumor; when MRI is impossible, IWGDF/IDSA suggest labeled leukocyte scintigraphy, PET or SPECT instead.
Key takeaways
- S. aureus is the most common cause of osteomyelitis in nearly every group.
- Sickle cell → Salmonella; foot puncture through a shoe → Pseudomonas; injection drug use → S. aureus (also Pseudomonas, Serratia); diabetic foot → polymicrobial; hardware → S. aureus and S. epidermidis biofilm.
- Children seed the metaphysis of long bones; adults seed the vertebrae.
- X-rays lag by days to weeks; MRI is the imaging test of choice; bone biopsy and culture is definitive.
- Typical courses: 3-4 weeks for uncomplicated pediatric disease with an early oral switch; 6 weeks for vertebral or unresected diabetic foot osteomyelitis.
- Chronic disease means a sequestrum or relapse; a long-draining sinus can become squamous cell carcinoma (Marjolin ulcer).
Sources
- Osteomyelitis — Merck Manual Professional Edition (2024)
- IWGDF/IDSA Guidelines on the Diagnosis and Treatment of Diabetes-related Foot Infections — Infectious Diseases Society of America (2023)
- Clinical Practice Guidelines for the Diagnosis and Treatment of Native Vertebral Osteomyelitis in Adults — Infectious Diseases Society of America (2015)
- 2021 PIDS/IDSA Guideline on Diagnosis and Management of Acute Hematogenous Osteomyelitis in Pediatrics — Journal of the Pediatric Infectious Diseases Society (2021)
- Osteomyelitis: Diagnosis and Treatment — American Family Physician (2021)
- Hematogenous Osteomyelitis in Infants and Children: Imaging of a Changing Disease — Radiology (2017)
- Osteomyelitis — Radiopaedia
- Sequestrum — Radiopaedia
- Sickle Cell Disease — Merck Manual Professional Edition (2026)
- Pseudomonas and Related Infections — Merck Manual Professional Edition (2024)
- Prosthetic Joint Infectious Arthritis — Merck Manual Professional Edition (2025)
- Marjolin ulcer — DermNet (2024)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
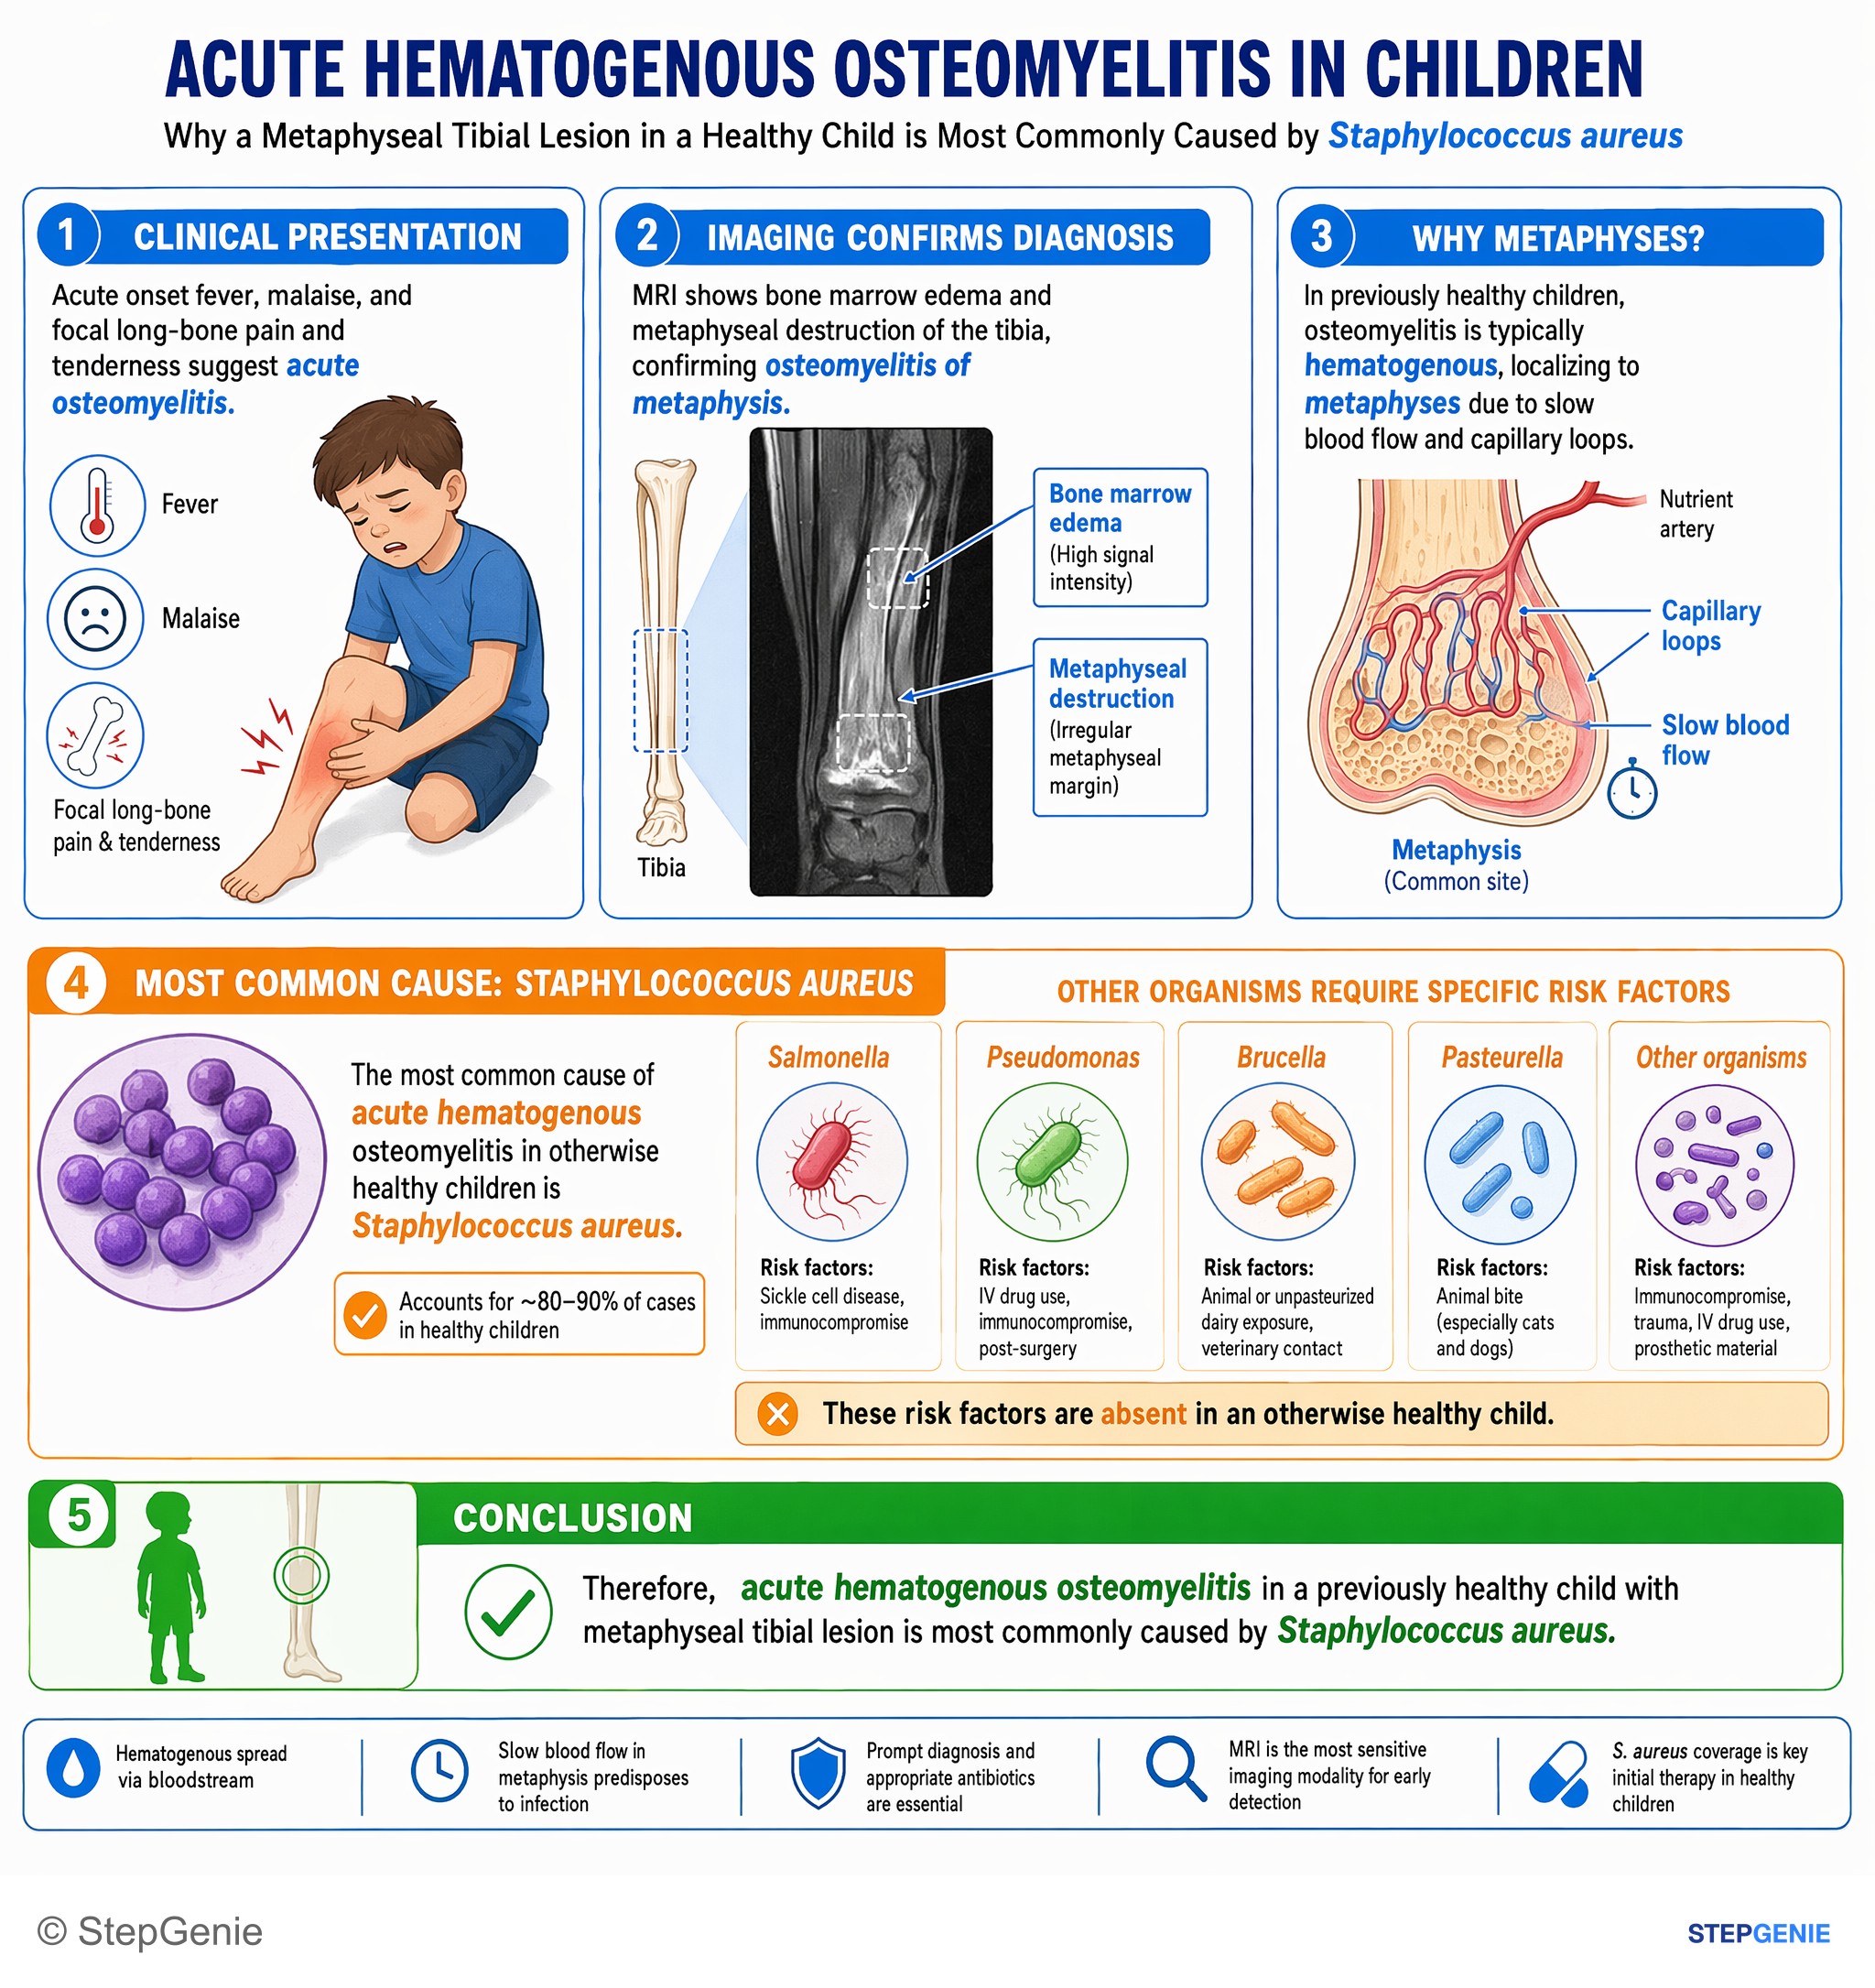
Acute hematogenous osteomyelitis in a previously healthy child with metaphyseal tibial lesion is most commonly caused by Staphylococcus…
USMLE Step 1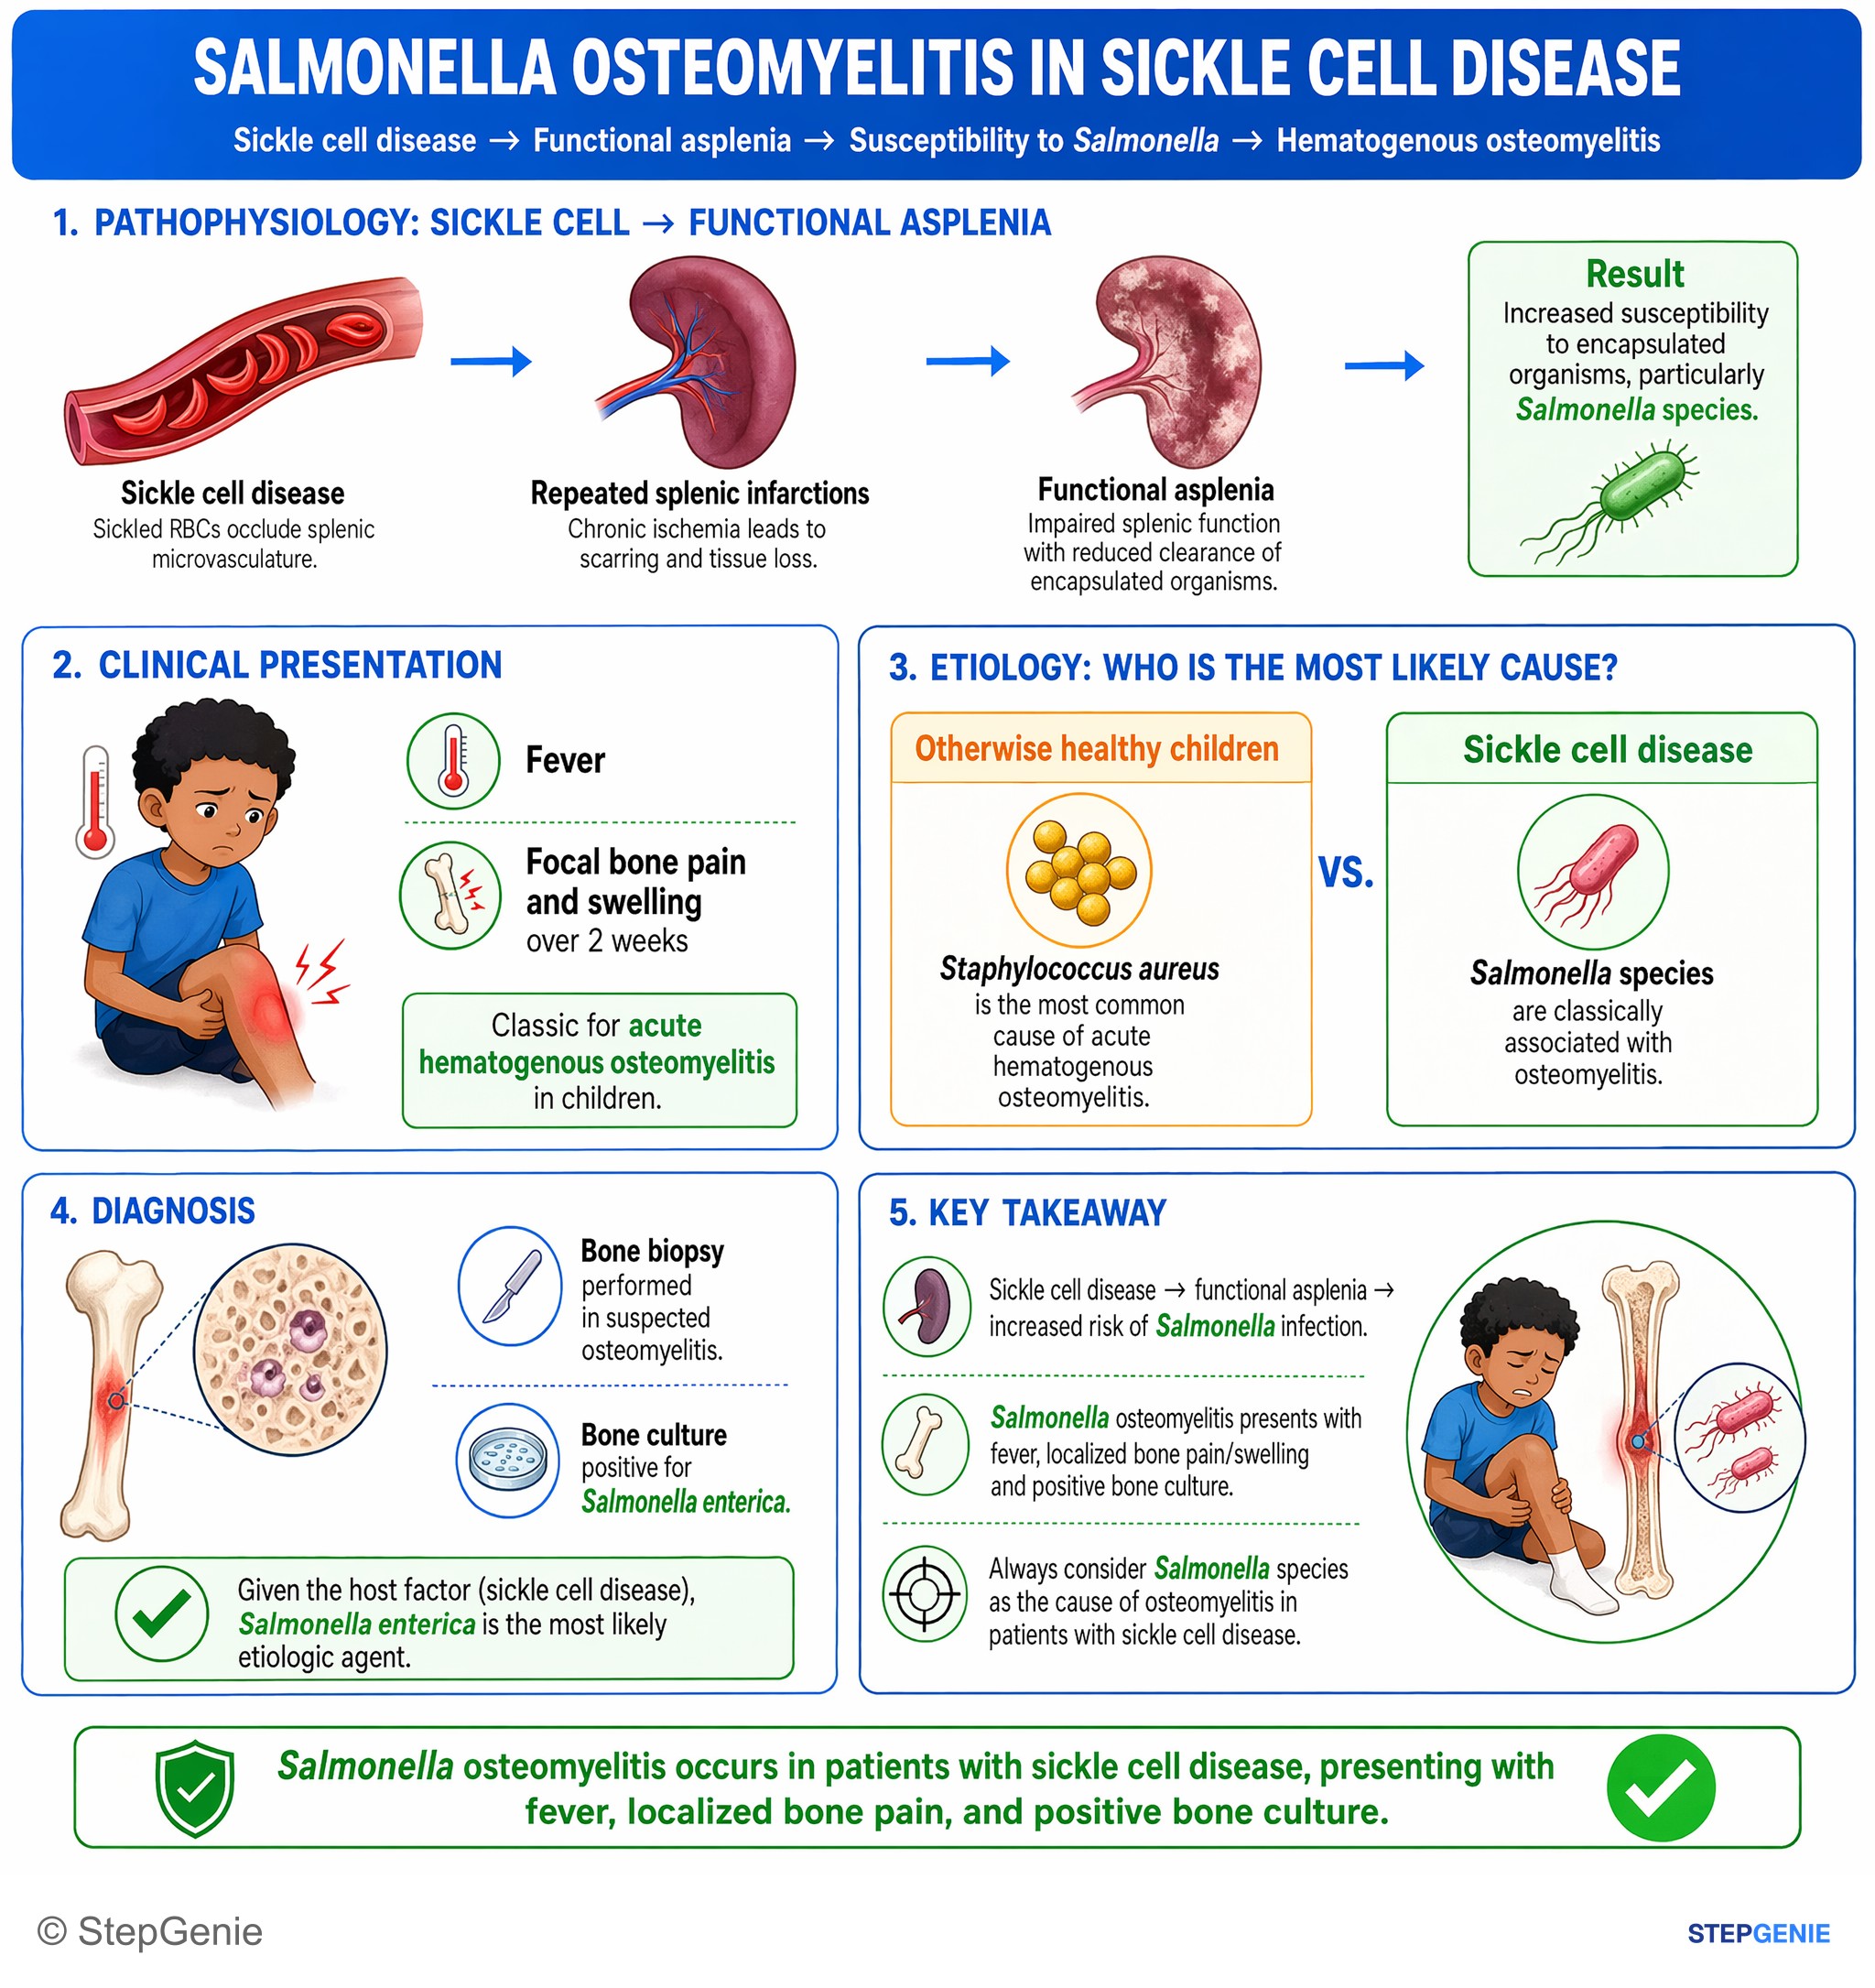
Salmonella osteomyelitis occurs in patients with sickle cell disease, presenting with fever, localized bone pain, and positive bone culture.
USMLE Step 1Frequently Asked Questions
What is the most common cause of osteomyelitis?
Staphylococcus aureus is the most common cause of osteomyelitis in children and adults, whether the infection arrives through the bloodstream or spreads from nearby tissue. Both methicillin-sensitive strains and MRSA cause it, and MRSA is common in many communities, so empiric therapy covers it where local rates are high. The classic exam exceptions are Salmonella in sickle cell disease, Pseudomonas after a puncture wound through a shoe, and polymicrobial infection in diabetic foot ulcers.
Why do people with sickle cell disease get Salmonella osteomyelitis?
Repeated sickling damages the spleen until it infarcts, leaving the patient functionally asplenic. Without a working spleen, people with sickle cell disease are more susceptible to pneumococcal and Salmonella infections, including Salmonella osteomyelitis. On exams, a child with sickle cell disease, fever and focal bone pain points to Salmonella, and pediatric guidance flags hemoglobinopathies as a reason to cover Salmonella in addition to S. aureus.
What organism causes osteomyelitis after stepping on a nail?
Pseudomonas aeruginosa is the classic answer when a nail or other sharp object punctures the sole of the foot, especially through a sneaker. Deep puncture wounds of the foot can lead to draining sinuses, cellulitis and osteomyelitis. S. aureus can still infect any wound, so bone cultures guide treatment, but in a USMLE stem a nail through a rubber-soled shoe means Pseudomonas.
What is the best imaging test for osteomyelitis?
MRI is the imaging test of choice because it shows bone marrow edema early and maps abscesses, soft-tissue spread and epidural involvement; the IDSA vertebral, PIDS/IDSA pediatric and IWGDF/IDSA diabetic foot guidelines all prefer it. Plain X-rays come first but are often normal early: changes can take 1 to 2 weeks to appear (Merck says 2 to 4 weeks) because a large share of the bone must be destroyed before lysis shows. A bone scan turns positive early but cannot distinguish infection from fracture or tumor.
How is osteomyelitis definitively diagnosed?
Bone biopsy with culture, taken percutaneously or at surgery, is the definitive test because it identifies the organism and its antibiotic susceptibilities. Swabs of ulcers or sinus tracts are unreliable because they grow colonizing bacteria. In vertebral osteomyelitis, IDSA advises an image-guided biopsy when blood cultures do not identify a likely organism and, in stable patients, holding empiric antibiotics until the organism is known.
How long is osteomyelitis treated?
Most adults need about 6 weeks of antibiotics. IDSA advises 6 weeks of IV or highly bioavailable oral therapy for native vertebral osteomyelitis, and IWGDF/IDSA suggest about 6 weeks for diabetic foot osteomyelitis when no bone is removed, or up to 3 weeks after a minor amputation with a positive bone margin. Children with uncomplicated acute hematogenous osteomyelitis usually need 3 to 4 weeks, with an early switch to oral antibiotics. Dead bone and abscesses also need surgery.