Fibromyalgia is a “diagnosis you earn,” not one you guess—because the USMLE loves to test it as chronic widespread pain with normal labs plus sleep + mood + fatigue symptoms. If you can quickly separate it from inflammatory arthritis, endocrine causes, and polymyalgia rheumatica, you’ll grab easy points on both Step 1 and Step 2.
The One-Liner (shareable)
Fibromyalgia = chronic widespread pain + fatigue + nonrestorative sleep + cognitive/mood symptoms with normal exam/labs (no objective inflammation).
Visual/Mnemonic Device: “FIBRO” Checklist
Think: FIBRO = what patients feel + what you don’t find on workup.
- F — Fatigue (often profound)
- I — “I didn’t sleep” (nonrestorative sleep; insomnia)
- B — Brain fog (“fibro fog,” concentration/memory issues)
- R — Real pain, but no Red, hot joints (no synovitis)
- O — Objective tests normal (ESR/CRP/CK typically normal)
Sticky image: A person holding a pain map (widespread pain), wearing a sleep mask (nonrestorative sleep), and carrying a clean lab report (normal inflammatory markers).
Step-by-Step Flowchart (high-yield diagnostic approach)
Step 1: Start with the symptom pattern
Chronic pain 3 months + widespread distribution (both sides, above & below waist, axial pain common).
If pain is focal → think local MSK pathology (tendinopathy, OA, radiculopathy).
If pain is widespread → go to Step 2.
Step 2: Look for the classic symptom cluster (the “fibro constellation”)
Ask targeted questions:
- Sleep: “Do you wake up unrefreshed?”
- Fatigue: “Do you feel exhausted most days?”
- Cognition/mood: brain fog, anxiety/depression
- Functional impact: headaches, IBS symptoms, pelvic pain can co-occur
If widespread pain + sleep/fatigue/cognitive symptoms → go to Step 3.
Step 3: Screen for red flags (don’t miss dangerous mimics)
If any of these are present, pause and broaden workup:
- Inflammatory features: morning stiffness hour, swollen joints, warmth/erythema
- Systemic symptoms: fever, weight loss, night sweats
- Neuro deficits: focal weakness, objective sensory loss, bowel/bladder changes
- True proximal muscle weakness (not just “pain-limited effort”)
- Older age with new severe symptoms (think PMR, malignancy)
No red flags → go to Step 4.
Step 4: Do a focused exam (what you shouldn’t find matters)
Typical findings:
- Diffuse tenderness to palpation (not necessarily in “tender point” map anymore)
- Normal joint exam: no synovitis, no effusions
- Normal strength on objective testing (may be pain-limited)
If exam suggests inflammation (swollen, warm joints) → pivot to inflammatory arthritis workup.
If exam is nonfocal and noninflammatory → go to Step 5.
Step 5: Minimal labs to exclude mimics (don’t shotgun)
Fibromyalgia is clinical, but USMLE expects you to rule out common look-alikes when appropriate:
| Concern | Clues | Suggested test(s) | What you’d see in fibro |
|---|---|---|---|
| Hypothyroidism | weight gain, constipation, cold intolerance | TSH | normal |
| Inflammatory disease (RA/PMR) | swollen joints or stiffness hr | ESR/CRP | typically normal |
| Myositis | true proximal weakness | CK | normal |
| Anemia | pallor, exertional dyspnea | CBC | usually normal |
High-yield: In fibromyalgia, ESR/CRP are normal. If stem says “elevated ESR” and dramatic morning stiffness in an older adult → think polymyalgia rheumatica, not fibro.
Step 6: Make the diagnosis (and communicate it well)
You’re there when you have:
- Widespread pain 3 months
- Associated fatigue/sleep/cognitive symptoms
- No objective inflammatory findings
- No better explanation
Test-taking tip: If the vignette includes normal labs + diffuse pain + poor sleep + mood symptoms, fibromyalgia should jump to the top.
High-Yield Differentials (USMLE favorites)
Fibromyalgia vs Polymyalgia Rheumatica (PMR)
| Feature | Fibromyalgia | PMR |
|---|---|---|
| Age | often 20–55 | (classically elderly) |
| Pain pattern | widespread, variable | shoulder/hip girdle aching |
| Morning stiffness | can occur, often less dramatic | prominent, min |
| Labs | normal ESR/CRP | elevated ESR/CRP |
| Treatment | exercise + CBT; SNRIs/TCA/gabapentinoids | low-dose steroids |
Fibromyalgia vs Rheumatoid Arthritis (RA)
- RA: symmetric inflammatory polyarthritis (MCP/PIP), synovitis, morning stiffness, possible +RF/+anti-CCP, erosions.
- Fibro: pain/tenderness without synovitis; normal inflammatory markers.
Fibromyalgia vs Hypothyroidism
- Hypothyroid can mimic fatigue, myalgias, depression → TSH is the quick screen if suggested by symptoms.
Management Flow (what Step 2 wants you to do)
First-line (most tested): Nonpharmacologic
Exercise is medicine (and it’s the best evidence-based answer on exams):
- Graded aerobic exercise (start low, go slow)
- CBT and sleep hygiene
- Stress reduction; treat comorbid depression/anxiety
Pharmacologic options (when needed)
Use meds that help pain modulation and sleep, not inflammation:
- SNRIs: duloxetine, milnacipran
- TCA: amitriptyline (often low dose at night)
- Gabapentinoids: pregabalin (sometimes gabapentin)
High-yield “NOT” list:
- NSAIDs: often minimal benefit (no inflammatory target)
- Opioids: avoid (dependency + poor long-term outcomes)
- Steroids: not indicated (think PMR if steroids dramatically help)
Rapid-Fire USMLE Pearls
- Fibromyalgia is a central sensitization pain syndrome (amplified pain processing).
- Often coexists with IBS, tension headaches/migraines, TMJ pain, and mood disorders.
- Physical exam: diffuse tenderness but no objective inflammation (no swollen joints).
- Labs/imaging: typically normal; use minimal testing to rule out mimics.
- Best next step in management on vignettes: exercise + CBT/sleep optimization.
Shareable Quick Flow (pocket version)
- Widespread pain 3 months?
- + sleep problems/fatigue/brain fog?
- No red flags + no synovitis?
- ESR/CRP normal (if checked)?
→ Fibromyalgia → exercise + CBT, consider SNRI/TCA/pregabalin.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
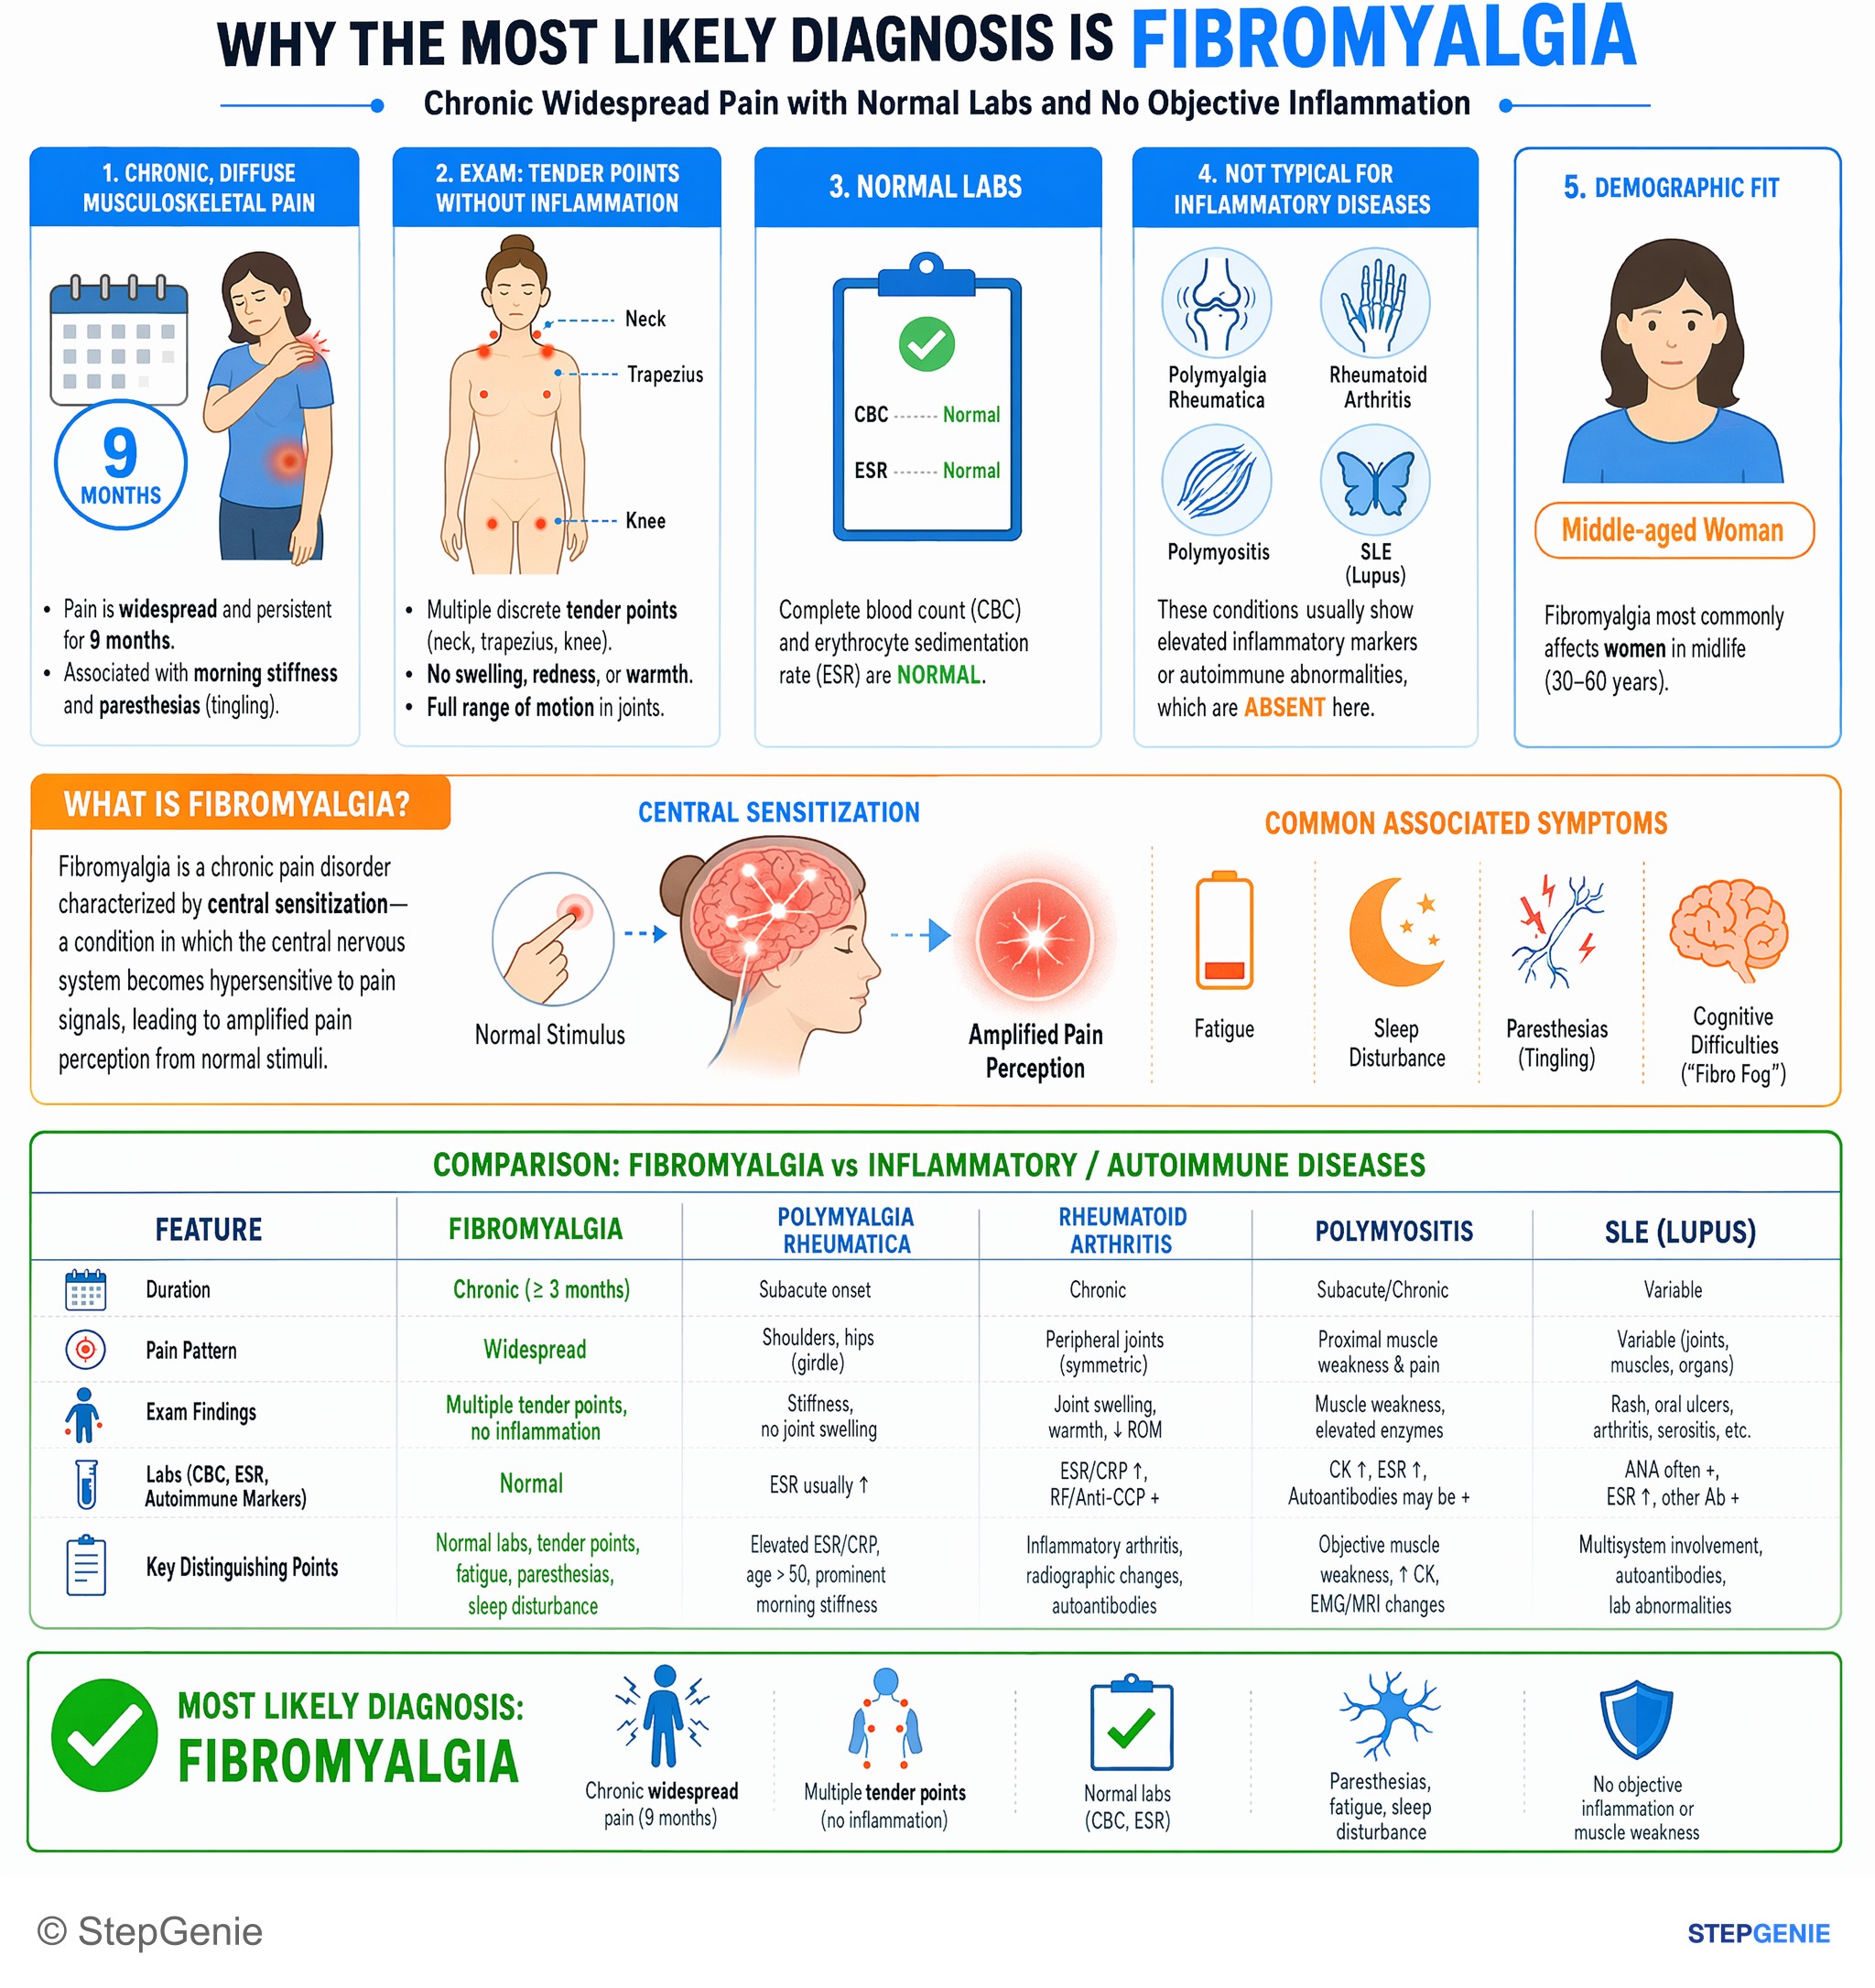
Fibromyalgia causes chronic widespread pain, tender points, and paresthesias with normal labs and no objective inflammatory or muscle…
USMLE Step 2Frequently Asked Questions
How do you recognize fibromyalgia on a USMLE-style vignette?
Fibromyalgia is recognized by chronic widespread pain lasting at least 3 months plus fatigue, nonrestorative sleep, and cognitive or mood symptoms with normal exam and labs. The key test clue is diffuse pain without objective inflammation. If a vignette gives normal inflammatory markers, poor sleep, fatigue, and mood symptoms, fibromyalgia should move high on the differential.
How do you tell fibromyalgia from polymyalgia rheumatica?
Fibromyalgia is distinguished from polymyalgia rheumatica by age, pain pattern, and inflammatory markers. Fibromyalgia often affects patients ages 20 to 55, causes widespread variable pain, and has normal ESR and CRP. Polymyalgia rheumatica classically occurs in adults older than 50, causes shoulder and hip girdle aching with prominent prolonged morning stiffness, and shows elevated ESR and CRP.
Why are ESR, CRP, and CK usually normal in fibromyalgia?
ESR, CRP, and CK are usually normal in fibromyalgia because it does not cause objective inflammation or muscle injury. Fibromyalgia is a central sensitization pain syndrome, meaning pain processing is amplified rather than driven by synovitis, inflammatory disease, or myositis. That is why the exam may show diffuse tenderness, but not swollen joints, effusions, or true inflammatory findings.
What is the first-line treatment for fibromyalgia?
The first-line treatment for fibromyalgia is nonpharmacologic therapy, especially graded aerobic exercise. Exercise is the most evidence-based exam answer, and management also includes CBT, sleep hygiene, stress reduction, and treatment of comorbid depression or anxiety. When medications are needed, options include SNRIs, low-dose amitriptyline, or pregabalin, because treatment targets pain modulation and sleep rather than inflammation.
What exam findings argue against fibromyalgia and suggest another diagnosis?
Findings that argue against fibromyalgia include objective inflammatory or neurologic abnormalities. Swollen, warm, or erythematous joints, morning stiffness lasting more than an hour, fever, weight loss, night sweats, focal weakness, objective sensory loss, bowel or bladder changes, and true proximal muscle weakness should prompt a broader workup. Fibromyalgia instead typically has diffuse tenderness with a normal joint exam and no synovitis.