Prostate cancer shows up everywhere on Step 1: it’s common, it’s high-yield, and question writers love testing how it differs from benign prostatic hyperplasia (BPH), how PSA behaves, and what you do after an abnormal screen. If you can connect androgens → peripheral gland → PSA/DRE → biopsy → staging/therapy, you’ll crush a big chunk of male reproductive pathology.
Where Prostate Cancer Fits (and Why Step 1 Loves It)
- Most common non-skin cancer in men (US); risk increases with age.
- Often asymptomatic early, so screening/diagnosis pathways are heavily tested.
- Classic board traps:
- Peripheral (posterior) prostate cancer vs transition zone BPH
- PSA pitfalls (not cancer-specific)
- Bone mets pattern and lab clues (osteoblastic lesions, ↑ ALP)
First Aid cross-reference: Reproductive → Prostate pathology; Oncology → tumor markers (PSA), metastasis patterns; Pharm → androgen deprivation therapy.
Definition (Step-Ready)
Prostate cancer is usually an adenocarcinoma arising from glandular epithelium, most commonly in the peripheral/posterior zone of the prostate.
Epidemiology & Risk Factors (High-Yield)
Big risk factors to memorize
- Age (strongest)
- Family history / genetics
- BRCA2 (particularly high-yield association with aggressive disease)
- HOXB13 (less commonly tested but real)
- African American ancestry: higher incidence and mortality
- Androgen exposure/signaling (conceptual driver; basis of therapy)
Protective-ish association (classic Step fact)
- 5-α reductase inhibitors (e.g., finasteride) reduce conversion of testosterone to DHT and can reduce prostate size; their relationship to cancer risk is nuanced, but Step questions mainly test their BPH role and sexual side effects.
Pathophysiology: What’s Happening Under the Hood?
Androgens drive growth
- Prostate tissue growth is androgen-dependent, especially DHT, formed via 5-α reductase:
- Testosterone \xrightarrow$$\text{5-}\alpha\text{ reductase}$${} DHT
- Cancer cells often remain androgen-sensitive initially → rationale for androgen deprivation therapy (ADT).
Why “peripheral zone” matters clinically
- Peripheral/posterior tumors are more likely to be felt on DRE (hard, irregular nodule).
- Transition zone enlargement is BPH → urinary symptoms early, but DRE feels “rubbery” and symmetric.
First Aid cross-reference: Prostate cancer classically in peripheral zone; BPH in transition zone.
Pathology & Histology (What They Can Show You)
Gross / location
- Typically arises in posterior peripheral prostate.
Microscopy (board-style clues)
- Adenocarcinoma: infiltrative small glands
- Prominent nucleoli can be described
- Gleason grading (pattern-based histologic grading)
- Higher Gleason score = worse prognosis (you don’t need to calculate intricate combos for Step 1, but know high score → aggressive)
Perineural invasion (common concept)
- Often mentioned in pathology reports and can be tested as a classic route of spread.
Clinical Presentation: How It Shows Up on Exams
Early disease
- Often asymptomatic
- Detected via elevated PSA or abnormal DRE
Later disease (local effects)
- Urinary symptoms can occur, but this is a trick:
- Prostate cancer is often peripheral → urinary obstruction tends to be later than in BPH.
Metastatic disease (very high-yield)
- Bone pain, especially back/hips
- Weight loss, fatigue
- Spinal cord compression signs (emergency)
- Bone metastases from prostate are classically osteoblastic.
Screening & Diagnosis (The Step 1 Core Algorithm)
Two common screening tools
- PSA
- DRE
PSA: know what it is—and what it isn’t
- PSA = serine protease produced by prostate epithelium.
- PSA is not cancer-specific.
- PSA can be elevated in:
- Prostate cancer
- BPH
- Prostatitis
- Recent ejaculation
- Recent instrumentation (e.g., catheterization, cystoscopy)
Classic Step link: BPH and prostate cancer can both elevate PSA; cancer more concerning with abnormal DRE or concerning PSA kinetics.
What confirms the diagnosis?
- Transrectal ultrasound-guided biopsy (TRUS biopsy)
- Definitive diagnosis is histology, not PSA alone.
“Free PSA” concept (high yield nuance)
- Lower % free PSA is more suggestive of cancer.
- Higher % free PSA tends to suggest BPH.
Staging & Spread (How It Travels)
Local invasion
- Seminal vesicles can be involved.
Lymphatic spread
- Typically to obturator and internal iliac nodes (pelvic nodes).
Hematogenous spread (board favorite)
- Bone metastases (especially axial skeleton: spine, pelvis)
- Produces osteoblastic (sclerotic) lesions
Lab tie-in
- Bone metastases → often ↑ alkaline phosphatase (ALP) (from osteoblastic activity)
Table: Prostate vs other bone metastasis patterns
| Primary cancer | Typical bone lesion type | Board clue |
|---|---|---|
| Prostate | Osteoblastic (sclerotic) | Bone pain + sclerotic lesions + ↑ ALP |
| Breast (often) | Mixed / osteolytic | Variable patterns |
| Renal cell, thyroid, lung | Osteolytic | “Punched-out” lesions more classic in myeloma; lytic mets common here |
Treatment (Tie Therapy to Physiology)
Management depends on risk category and stage, but Step 1 focuses on the mechanisms and the “big levers.”
Localized disease
- Active surveillance (especially low-risk)
- Radical prostatectomy
- Radiation therapy (external beam or brachytherapy)
Advanced/metastatic disease: Androgen Deprivation Therapy (ADT)
Prostate cancer is often androgen-sensitive at first.
Core pharmacology to know (very testable):
- GnRH agonists: leuprolide, goserelin
- Cause an initial testosterone flare then downregulate GnRH receptors → ↓ LH/FSH → ↓ testosterone
- Co-administer antiandrogen early to prevent flare (high-yield clinical pearl)
- GnRH antagonists: degarelix (no initial flare)
- Antiandrogens: flutamide, bicalutamide, nilutamide
- Block androgen receptor
- Androgen synthesis inhibitors: abiraterone (Step 2-ish, but may appear)
Chemo (advanced disease)
- Docetaxel and other regimens exist; less Step 1 emphasis than ADT mechanisms.
Prognosis (What Predicts Outcomes?)
High-yield predictors:
- Stage (localized vs metastatic)
- Gleason score (higher = worse)
- PSA level (trend matters; not perfectly specific)
Prostate Cancer vs BPH vs Prostatitis (Rapid Differentiation)
| Feature | Prostate cancer | BPH | Prostatitis |
|---|---|---|---|
| Typical zone | Peripheral/posterior | Transition | N/A (inflammation) |
| DRE | Hard, irregular nodule | Enlarged, rubbery, symmetric | Tender boggy prostate |
| PSA | Can be ↑ | Can be ↑ | Often ↑ |
| Symptoms | Often late urinary symptoms | Early LUTS (hesitancy, weak stream) | Dysuria, pelvic pain, systemic symptoms |
| Diagnosis | Biopsy | Clinical ± response to therapy | UA/culture; clinical |
First Aid cross-reference: Classic “peripheral zone cancer vs transition zone BPH” is a staple.
High-Yield Associations & Board Traps
1) PSA is not diagnostic
- Elevated PSA ≠ cancer.
- Definitive diagnosis requires biopsy.
2) Don’t confuse symptoms timing
- BPH causes early obstruction (transition zone).
- Prostate cancer often silent until later.
3) Bone metastasis pattern
- Prostate → osteoblastic lesions; think sclerotic on imaging and ↑ ALP.
4) DRE location clue
- Peripheral/posterior lesions are often palpable on DRE.
5) Hormone therapy logic
- ADT works because many tumors are initially androgen-dependent.
- GnRH agonists can cause a flare—pair with an antiandrogen.
Quick USMLE-Style Vignettes (Pattern Recognition)
- Older man + hard, irregular prostate nodule on DRE + elevated PSA → suspect prostate cancer → confirm with biopsy.
- Bone pain + sclerotic lesions on imaging + elevated ALP + history of prostate cancer → osteoblastic bone metastases.
- Elevated PSA after UTI-like symptoms + tender prostate → prostatitis (don’t jump to cancer without the full picture).
Rapid Review: The 10 Facts to Memorize
- Prostate cancer is typically adenocarcinoma.
- Most commonly arises in the peripheral/posterior prostate.
- BPH arises in the transition zone.
- PSA is a serine protease and is not cancer-specific.
- Diagnosis is confirmed by biopsy.
- Lower % free PSA suggests cancer (higher suggests BPH).
- Metastasis commonly goes to bone (axial skeleton).
- Bone mets are classically osteoblastic with ↑ ALP.
- Androgen dependence explains use of ADT.
- GnRH agonists can cause initial testosterone flare; prevent with antiandrogens.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
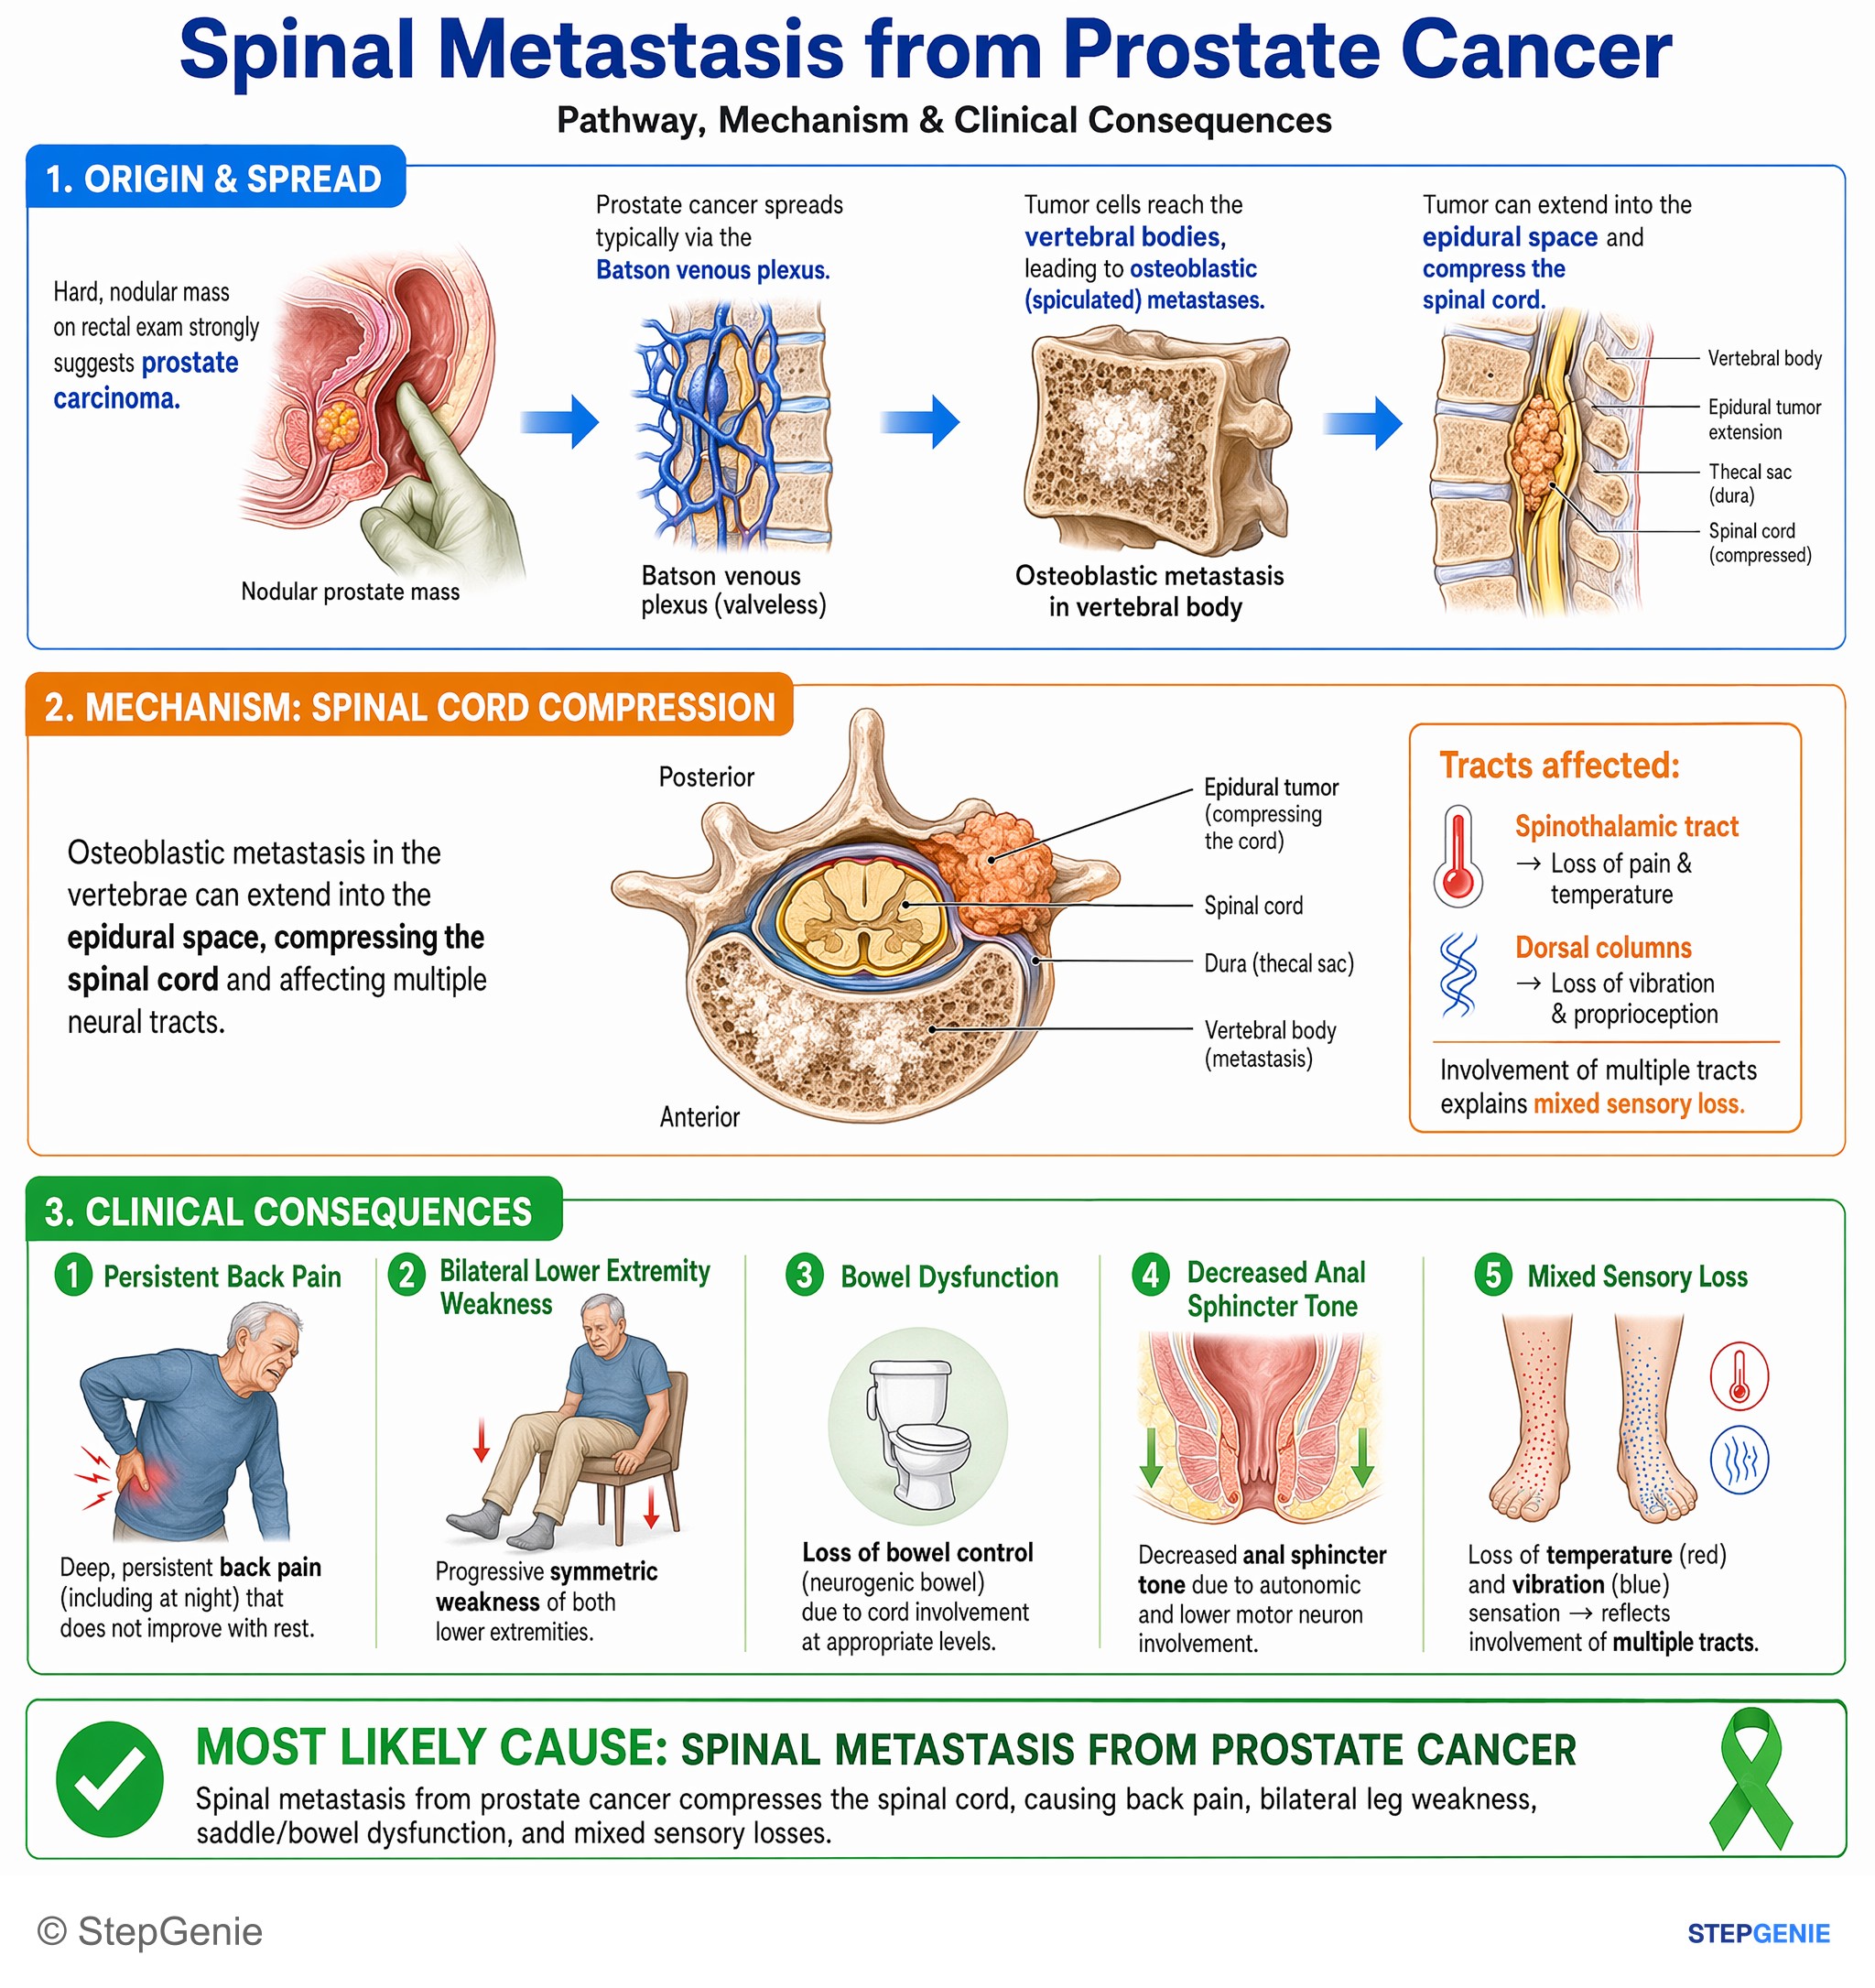
Spinal metastasis from prostate cancer compresses the spinal cord, causing back pain, bilateral leg weakness, saddle/bowel dysfunction…
USMLE Step 2Frequently Asked Questions
How do you tell prostate cancer from BPH on Step 1?
Prostate cancer usually arises in the peripheral or posterior zone, while BPH classically affects the transition zone. That difference explains the exam clues: prostate cancer may be felt as a hard, irregular nodule on digital rectal exam and often causes urinary obstruction later, whereas BPH tends to cause earlier urinary symptoms with a symmetric, rubbery enlargement on exam.
Why can PSA be elevated even if a patient does not have prostate cancer?
PSA is not cancer-specific, so an elevated PSA does not automatically mean prostate cancer. PSA is a serine protease produced by prostate epithelium and can also rise in BPH, prostatitis, recent ejaculation, and recent instrumentation such as catheterization or cystoscopy. That is why PSA alone does not confirm the diagnosis and must be interpreted with other findings.
What confirms the diagnosis of prostate cancer after an abnormal PSA or DRE?
The diagnosis is confirmed by transrectal ultrasound-guided biopsy with histology. An abnormal PSA or digital rectal exam can raise suspicion, but definitive diagnosis requires tissue showing prostate adenocarcinoma. This matters because PSA is not specific for cancer and can also be elevated in benign conditions, so biopsy is the key step that establishes the diagnosis.
What bone metastasis pattern is classic for prostate cancer?
Prostate cancer classically causes osteoblastic, or sclerotic, bone metastases, especially in the axial skeleton such as the spine and pelvis. On exams, this often appears with bone pain and an elevated alkaline phosphatase due to osteoblastic activity. Back or hip pain, weight loss, and even spinal cord compression are important clues when metastatic disease is present.
Why is androgen deprivation therapy used in prostate cancer?
Androgen deprivation therapy is used because prostate cancer is often androgen-sensitive early in its course. Prostate tissue growth is driven by androgens, especially DHT formed from testosterone by 5-alpha reductase, so lowering androgen signaling can slow tumor growth. Step 1 commonly tests this physiology along with GnRH agonists such as leuprolide and goserelin.