Benign prostatic hyperplasia (BPH) is a benign proliferation of glandular and stromal cells in the transition (periurethral) zone of the prostate, driven by dihydrotestosterone (DHT) made by 5α-reductase type 2; the enlarged gland squeezes the prostatic urethra and causes lower urinary tract symptoms (LUTS). It feels smooth, rubbery and enlarged on DRE, can raise PSA, and is not a risk factor for prostate cancer, which arises mostly in the peripheral zone. Treatment targets both parts of the obstruction: α1-blockers (the published summary of the 2026 AUA guideline names the uroselective tamsulosin, silodosin and alfuzosin) relax smooth muscle within days, while 5α-reductase inhibitors (finasteride, dutasteride) shrink an enlarged gland over months, halve PSA, and lower the risk of urinary retention and surgery.
Pathophysiology: one gland, two kinds of obstruction
- Hyperplasia, not hypertrophy: more glandular and stromal cells, forming nodules around the urethra that narrow and lengthen it.
- DHT is the driver. Stromal 5α-reductase type 2 converts testosterone to DHT, about 90% of the androgen inside the prostate. Finasteride blocks type 2 (cutting serum DHT by about 70%); dutasteride blocks types 1 and 2.
- Common with age: histologic BPH is present in 40-50% of men aged 51-60 and more than 80% of men over 80, but far fewer have symptoms.
| Component | Cause | Drug that targets it | Speed |
|---|---|---|---|
| Static (mechanical) | Bulk of the enlarged gland compressing the urethra | 5α-reductase inhibitor shrinks the gland | Months |
| Dynamic | α1-adrenergic smooth muscle tone in the prostate and bladder neck (α1A is about 70% of prostatic α1 receptors) | α1-blocker relaxes it | Days |
BPH vs prostate cancer: the zone question
| BPH | Prostate adenocarcinoma | |
|---|---|---|
| Zone | Transition (periurethral) | Mostly peripheral |
| DRE | Smooth, rubbery, enlarged, nontender | Hard nodule or induration (exam often normal) |
| Symptoms | LUTS from urethral compression | Usually silent until advanced; bone pain from osteoblastic metastases |
| PSA | Can be mildly raised | Raised |
| Premalignant? | No | — |
Deep dive: prostate cancer for Step 1.
Presentation and complications
- Voiding (obstructive): hesitancy, weak stream, straining, intermittency, incomplete emptying, terminal dribbling.
- Storage (irritative): frequency, urgency, nocturia, urge incontinence.
- AUA Symptom Index: ≤7 mild, 8-19 moderate, 20-35 severe.
- Complications: acute urinary retention (BPH is its most common cause in men), chronic retention, bladder stones, recurrent UTIs, hematuria, and hydronephrosis with postrenal kidney injury (see prerenal vs intrinsic vs postrenal AKI).
Drugs that tip an enlarged prostate into acute retention (a favorite "what precipitated this?" stem):
| Drug class | Examples | Mechanism |
|---|---|---|
| Anticholinergics | Oxybutynin, scopolamine | Weaker detrusor contraction |
| First-generation antihistamines | Diphenhydramine, chlorpheniramine | Anticholinergic |
| Tricyclic antidepressants | Amitriptyline, imipramine | Anticholinergic |
| α-agonist decongestants | Pseudoephedrine, phenylephrine | More smooth muscle tone at the bladder neck and prostate |
| Opioids | Postoperative opioids | Impaired emptying |
Acute retention is treated with immediate Foley catheter decompression, and an α-blocker is started before a voiding trial.
Evaluation (AUA 2026 and Merck)
The full 2026 AUA guideline text is open only to AUA members, so the AUA 2026 points on this page come from its published statement summary (Guideline Central).
- History with a symptom score, DRE, and urinalysis (to look for infection and blood).
- PSA may be checked after shared decision-making (AUA 2026).
- Post-void residual and uroflowmetry may be used to look for retention (a PVR over about 50 mL means incomplete emptying in younger men; up to 100 mL can be acceptable after 65).
- Counsel patients about the risk of retention and progression, and re-evaluate within 6 months of starting treatment.
Treatment ladder
- Behavioral and lifestyle measures before or alongside drugs (AUA 2026).
- α1-blocker for bothersome LUTS: AUA 2026 says to offer a uroselective drug (tamsulosin, silodosin or alfuzosin).
- Add or use a 5α-reductase inhibitor when the prostate is enlarged; the benefit is greatest in glands over 30 mL.
- Tadalafil 5 mg daily, especially with coexisting erectile dysfunction.
- Storage symptoms that persist: a β3 agonist (vibegron is labeled for men already on BPH drugs) or an antimuscarinic, watching for retention.
- Procedure when drugs fail or complications appear: recurrent UTI, bladder stones, severe bladder dysfunction or upper tract dilation.
| Class | Drugs | Mechanism | Must-know adverse effects and pearls |
|---|---|---|---|
| Uroselective α1-blockers | Tamsulosin, silodosin, alfuzosin | Relax prostate and bladder neck smooth muscle | Dizziness, orthostatic hypotension; ejaculatory dysfunction (retrograde ejaculation in 28% on silodosin); intraoperative floppy iris syndrome: tell the eye surgeon before cataract surgery |
| Nonselective α1-blockers | Doxazosin, terazosin | Same, plus vascular α1 blockade | Not among the uroselective drugs named in the 2026 AUA statement; also treat hypertension; first-dose postural hypotension and syncope, so start low (doxazosin 1 mg) and titrate |
| 5α-reductase inhibitors | Finasteride (type 2), dutasteride (types 1 and 2) | Less DHT → gland shrinks | Months to work; ↓ libido, erectile and ejaculatory dysfunction, breast enlargement; PSA falls ~50% in 6 months; label warning of more high-grade (Gleason 8-10) cancer; pregnant women should not handle crushed finasteride tablets or dutasteride capsules |
| PDE5 inhibitor | Tadalafil 5 mg daily | Raises cGMP in prostate, bladder and vascular smooth muscle (exact BPH mechanism not established) | Contraindicated with nitrates (and riociguat) |
| β3 agonist | Vibegron | Relaxes the detrusor during filling, raising bladder capacity | Labeled for men already on BPH drugs; urinary retention risk with outlet obstruction or antimuscarinics |
Combinations: what is in, what is out
- α-blocker + 5-ARI: better than either drug alone for an enlarged gland (Merck). Finasteride with doxazosin is FDA-labeled to reduce symptomatic progression, and dutasteride + tamsulosin comes as a single capsule for men with an enlarged prostate.
- Tadalafil + 5-ARI: "may be considered" for select patients (AUA 2026); the tadalafil label recommends using it with finasteride for up to 26 weeks when starting BPH treatment.
- Tadalafil + α-blocker for BPH: not recommended by the label (the combination is not adequately studied, and the vasodilation adds up to lower blood pressure).
- α-blocker + β3 agonist or antimuscarinic: for persistent storage symptoms, watching for urinary retention.
More on PDE5 inhibitors: the erectile dysfunction comparison table.
The PSA trap with 5-ARIs
A man on finasteride or dutasteride for 6 months or more has about half his true PSA: double the value before comparing it with normal ranges. A rising PSA while on a 5-ARI deserves evaluation for cancer. For men on active surveillance for prostate cancer, AUA 2026 advises counseling that a 5-ARI is not likely to increase the risk of cancer progression. 5-ARIs are not approved to prevent prostate cancer.
Procedures
TURP (transurethral resection of the prostate) is the classic operation. The 2026 AUA guideline also covers holmium laser enucleation (HoLEP), thulium laser enucleation, photoselective vaporization, robotic waterjet ablation, an intraprostatic drug-coated balloon, a temporary implantable prostate device and prostatic artery embolization for selected patients. Before any procedure, patients should be counseled on possible effects on sexual function, retreatment rates and the need for re-evaluation.
How USMLE tests it: look-alikes
| Condition | Clue | DRE |
|---|---|---|
| BPH | Older man, gradual LUTS, normal UA | Smooth, enlarged, nontender |
| Acute bacterial prostatitis | Fever, chills, dysuria, perineal pain; E. coli | Exquisitely tender, boggy; avoid prostate massage (bacteremia) |
| Chronic prostatitis / pelvic pain syndrome | Pain with voiding and ejaculation | May be tender, not boggy |
| Prostate cancer | Often silent until advanced; bone pain from metastases | Hard nodule |
| Urethral stricture | Weak stream with a normal-sized prostate | Normal prostate |
| Neurogenic bladder | Diabetes, MS, Parkinson disease | Variable; large PVR without prostate enlargement |
| Drug-induced retention | New antihistamine, decongestant, TCA or opioid | Often underlying BPH |
The BPH and urinary retention breakdown drills retention stems.
Practice question
A 66-year-old man has 8 months of hesitancy, weak stream, straining, a sense of incomplete emptying and nocturia 3-4 times a night. He has no dysuria or fever and takes no medications. Digital rectal examination shows a smooth, symmetrically enlarged, rubbery, nontender prostate estimated at 50 g. Urinalysis is normal and PSA is 2.8 ng/mL. He wants a drug that will shrink the gland and lower his long-term risk of urinary retention and surgery. Which mechanism of action does that drug have?
A. Blockade of α1A receptors in prostatic smooth muscle B. Inhibition of the conversion of testosterone to dihydrotestosterone C. Inhibition of phosphodiesterase-5 D. Antagonism of muscarinic receptors on the detrusor E. Stimulation of β3-adrenergic receptors on the detrusor
Answer: B. Finasteride or dutasteride (5α-reductase inhibitors) lower DHT, the hormone driving transition-zone hyperplasia, so an enlarged gland shrinks over months; both are labeled to reduce acute urinary retention and the need for surgery. Expect his PSA to fall by about half.
- A: tamsulosin relaxes the dynamic component and helps within days, but it does not shrink the prostate or lower the surgery risk on its own.
- C: tadalafil 5 mg daily improves LUTS (and erectile dysfunction) but does not reduce gland size.
- D: antimuscarinics such as oxybutynin treat storage symptoms and can precipitate retention in an obstructed man.
- E: vibegron treats overactive bladder symptoms in men already on BPH drugs; it does not shrink the prostate.
Key takeaways
- BPH = hyperplasia of glands and stroma in the transition zone, driven by DHT (5α-reductase type 2); not premalignant.
- DRE: smooth, rubbery, enlarged; cancer = hard nodule, mostly peripheral zone.
- α1-blockers act in days on the dynamic component; AUA 2026 names tamsulosin, silodosin and alfuzosin; warn about floppy iris before cataract surgery.
- 5-ARIs shrink an enlarged gland over months, reduce retention and surgery, and halve PSA.
- α-blocker + 5-ARI for an enlarged prostate; tadalafil for LUTS with ED (never with nitrates; not combined with α-blockers for BPH).
- Anticholinergics, antihistamines, TCAs, decongestants and opioids can trigger acute retention: catheterize, then start an α-blocker.
Sources
- American Urological Association releases the Management of LUTS Attributed to BPH Guideline — AUA (2026)
- Management of Lower Urinary Tract Symptoms Attributed to Benign Prostatic Hyperplasia: AUA Guideline — American Urological Association (2026)
- Management of Lower Urinary Tract Symptoms Guideline (AUA 2026) — Guideline Central (2026)
- Benign Prostatic Hyperplasia (BPH) — Merck Manual Professional Edition (2025)
- Benign Prostatic Hyperplasia — StatPearls, NCBI Bookshelf (2024)
- Male Urinary Retention: Acute and Chronic — StatPearls, NCBI Bookshelf (2024)
- PROSCAR (finasteride) prescribing information — DailyMed (2026)
- AVODART (dutasteride) prescribing information — DailyMed (2023)
- Dutasteride and tamsulosin capsules prescribing information — DailyMed (2023)
- CIALIS (tadalafil) prescribing information — DailyMed (2026)
- CARDURA (doxazosin) prescribing information — DailyMed (2023)
- Prostatitis — Merck Manual Professional Edition (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
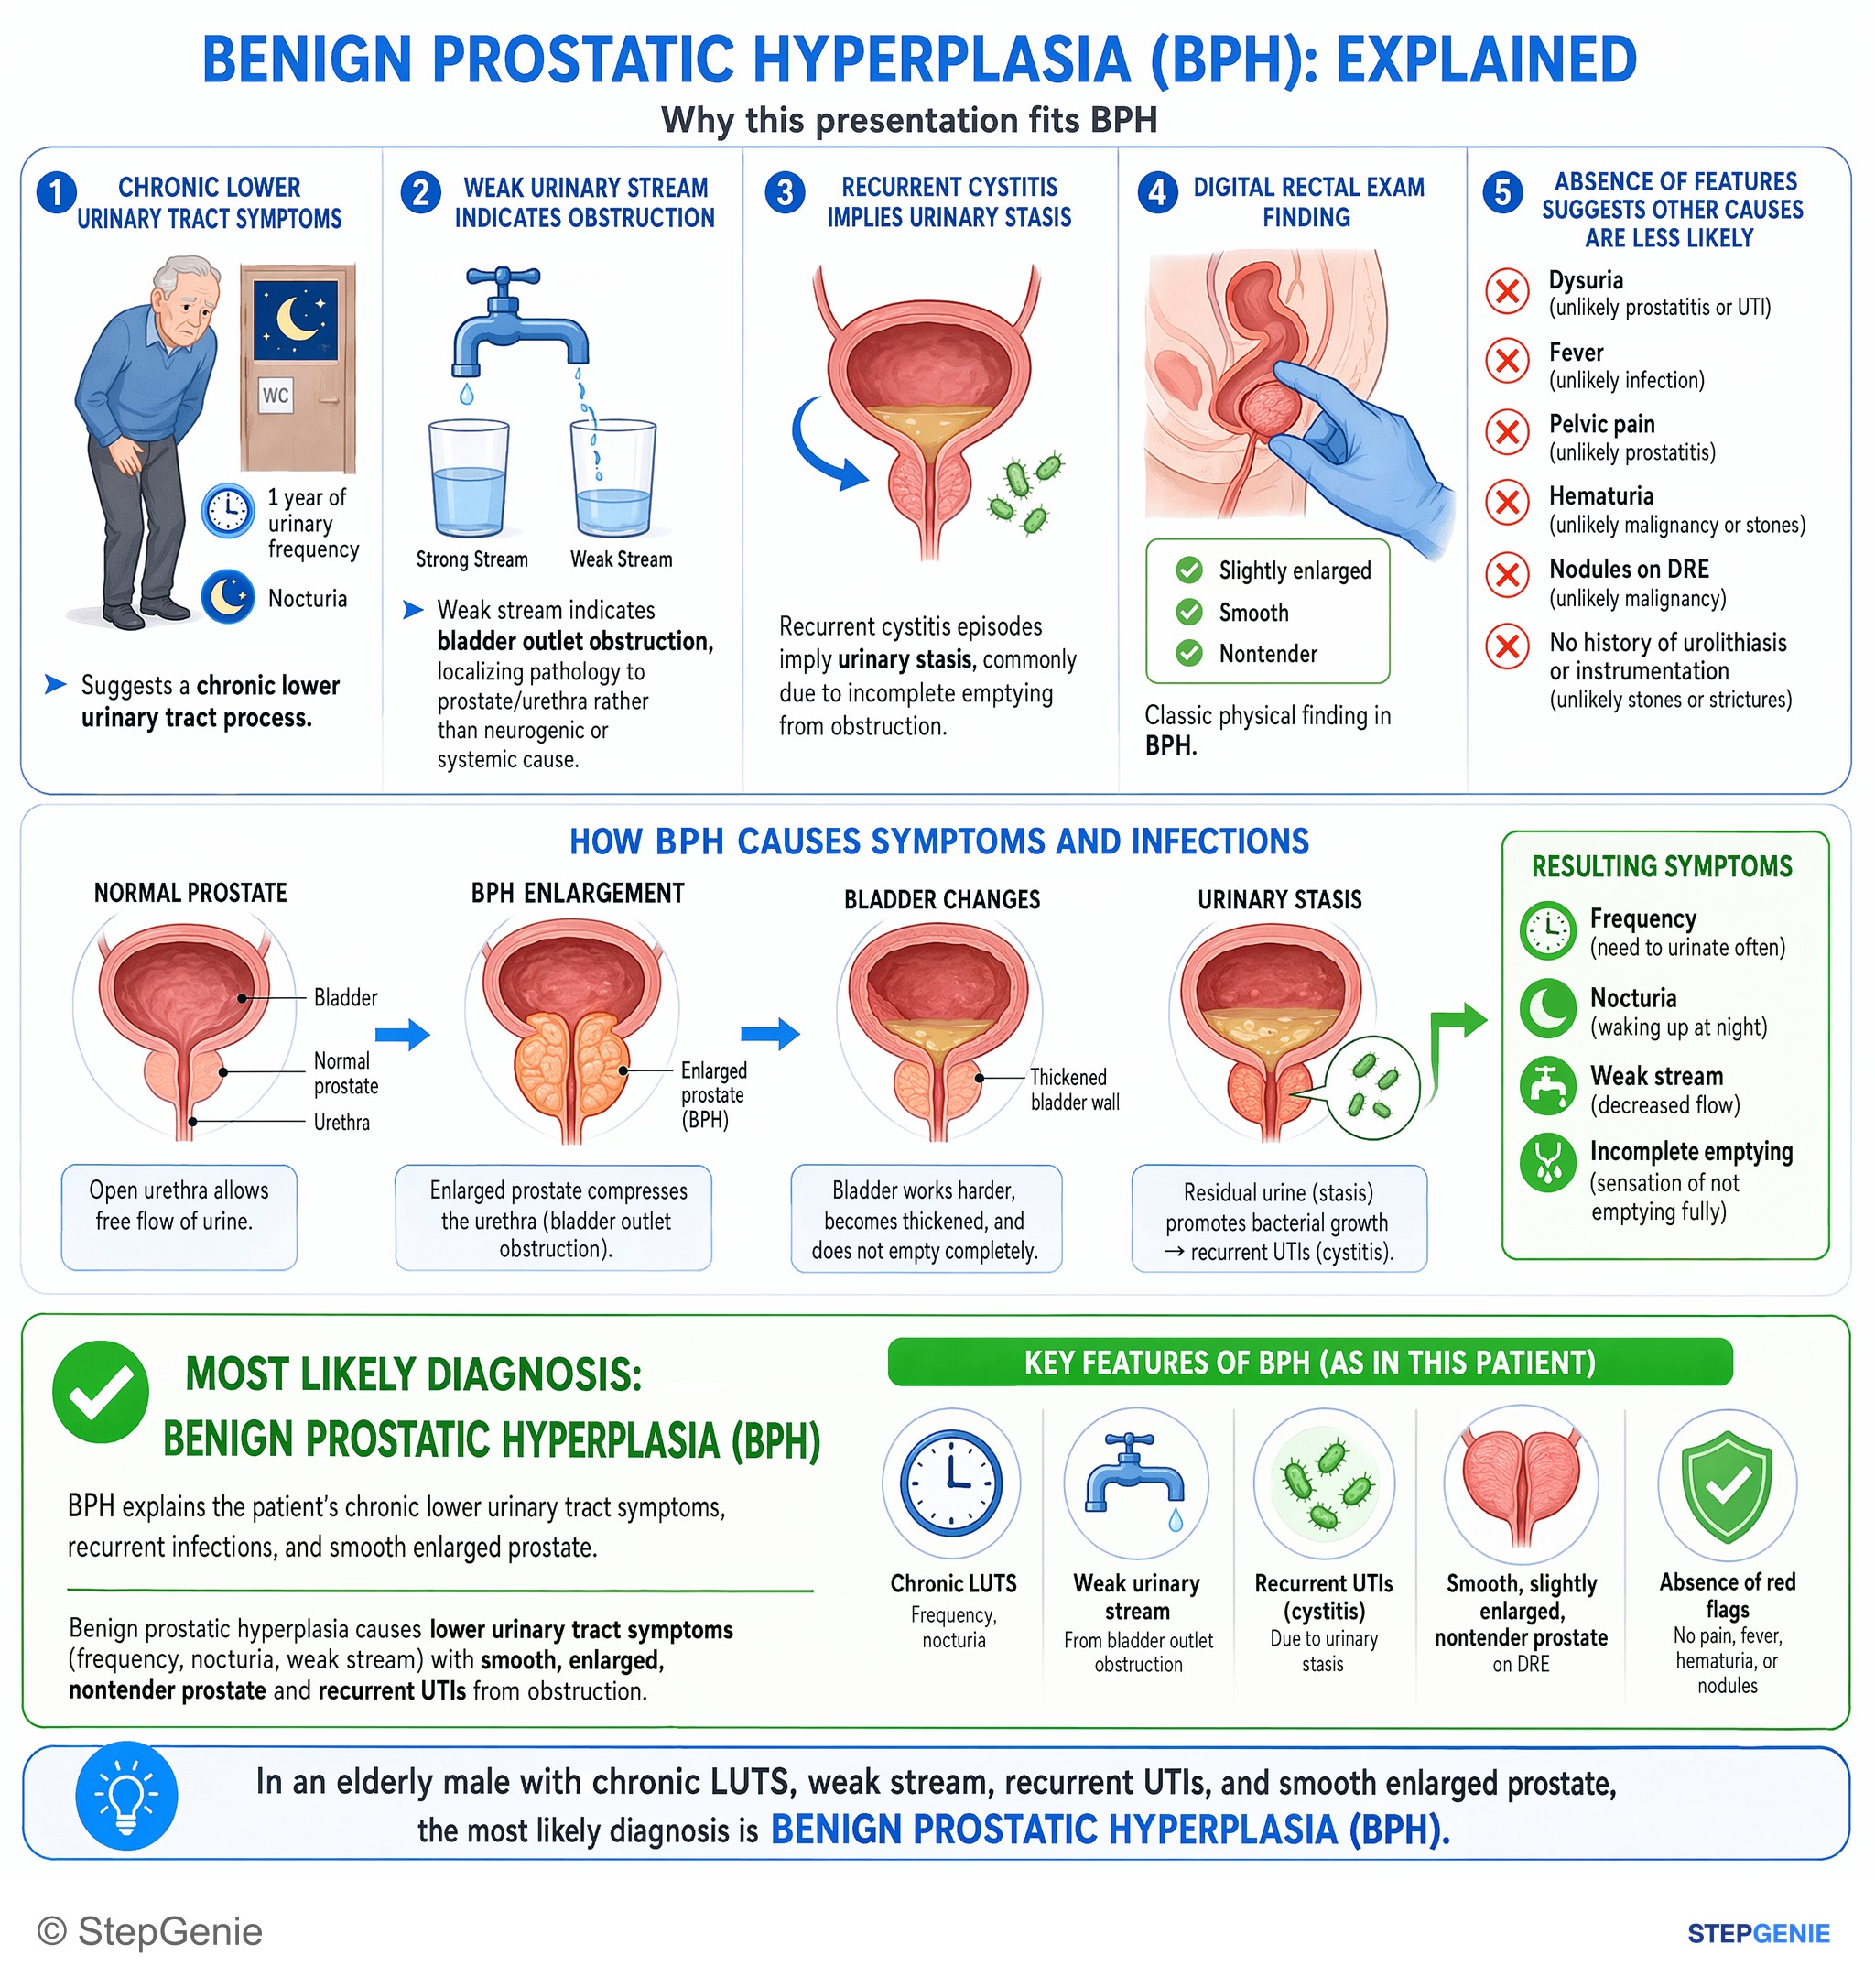
Benign prostatic hyperplasia causes lower urinary tract symptoms (frequency, nocturia, weak stream) with smooth, enlarged, nontender…
USMLE Step 2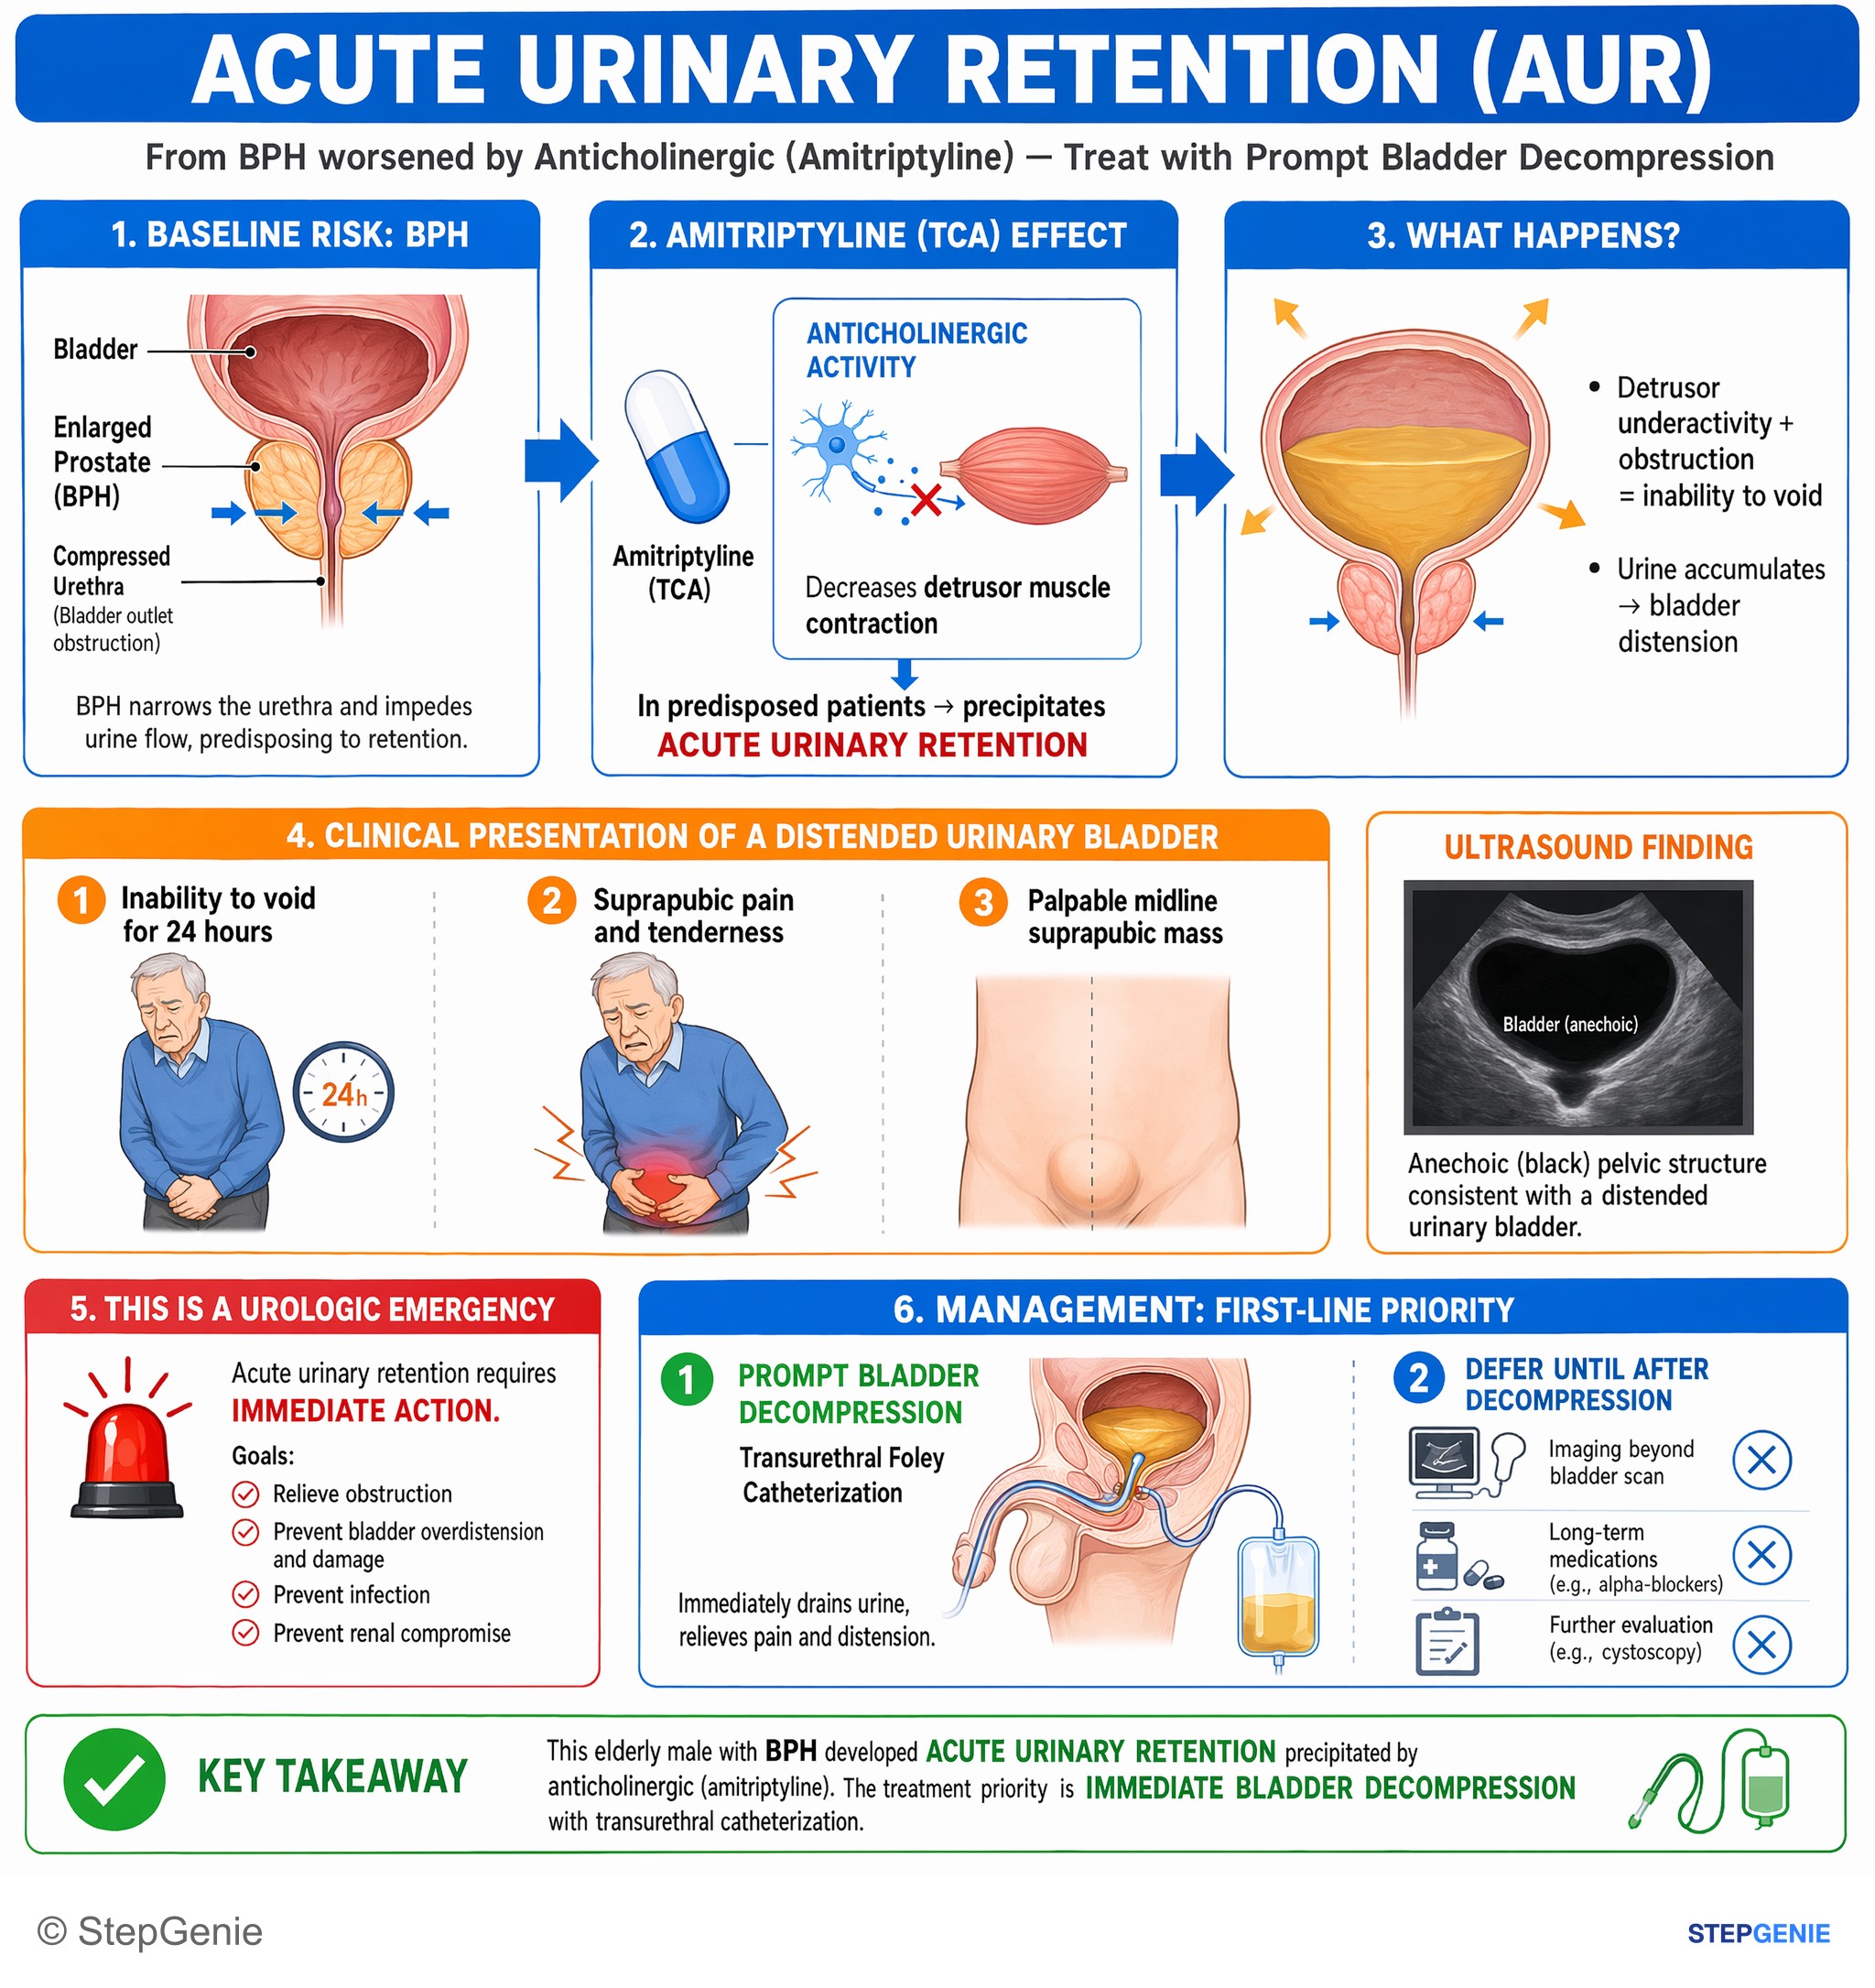
Acute urinary retention from BPH worsened by anticholinergic (amitriptyline); treat immediately with bladder decompression via…
USMLE Step 2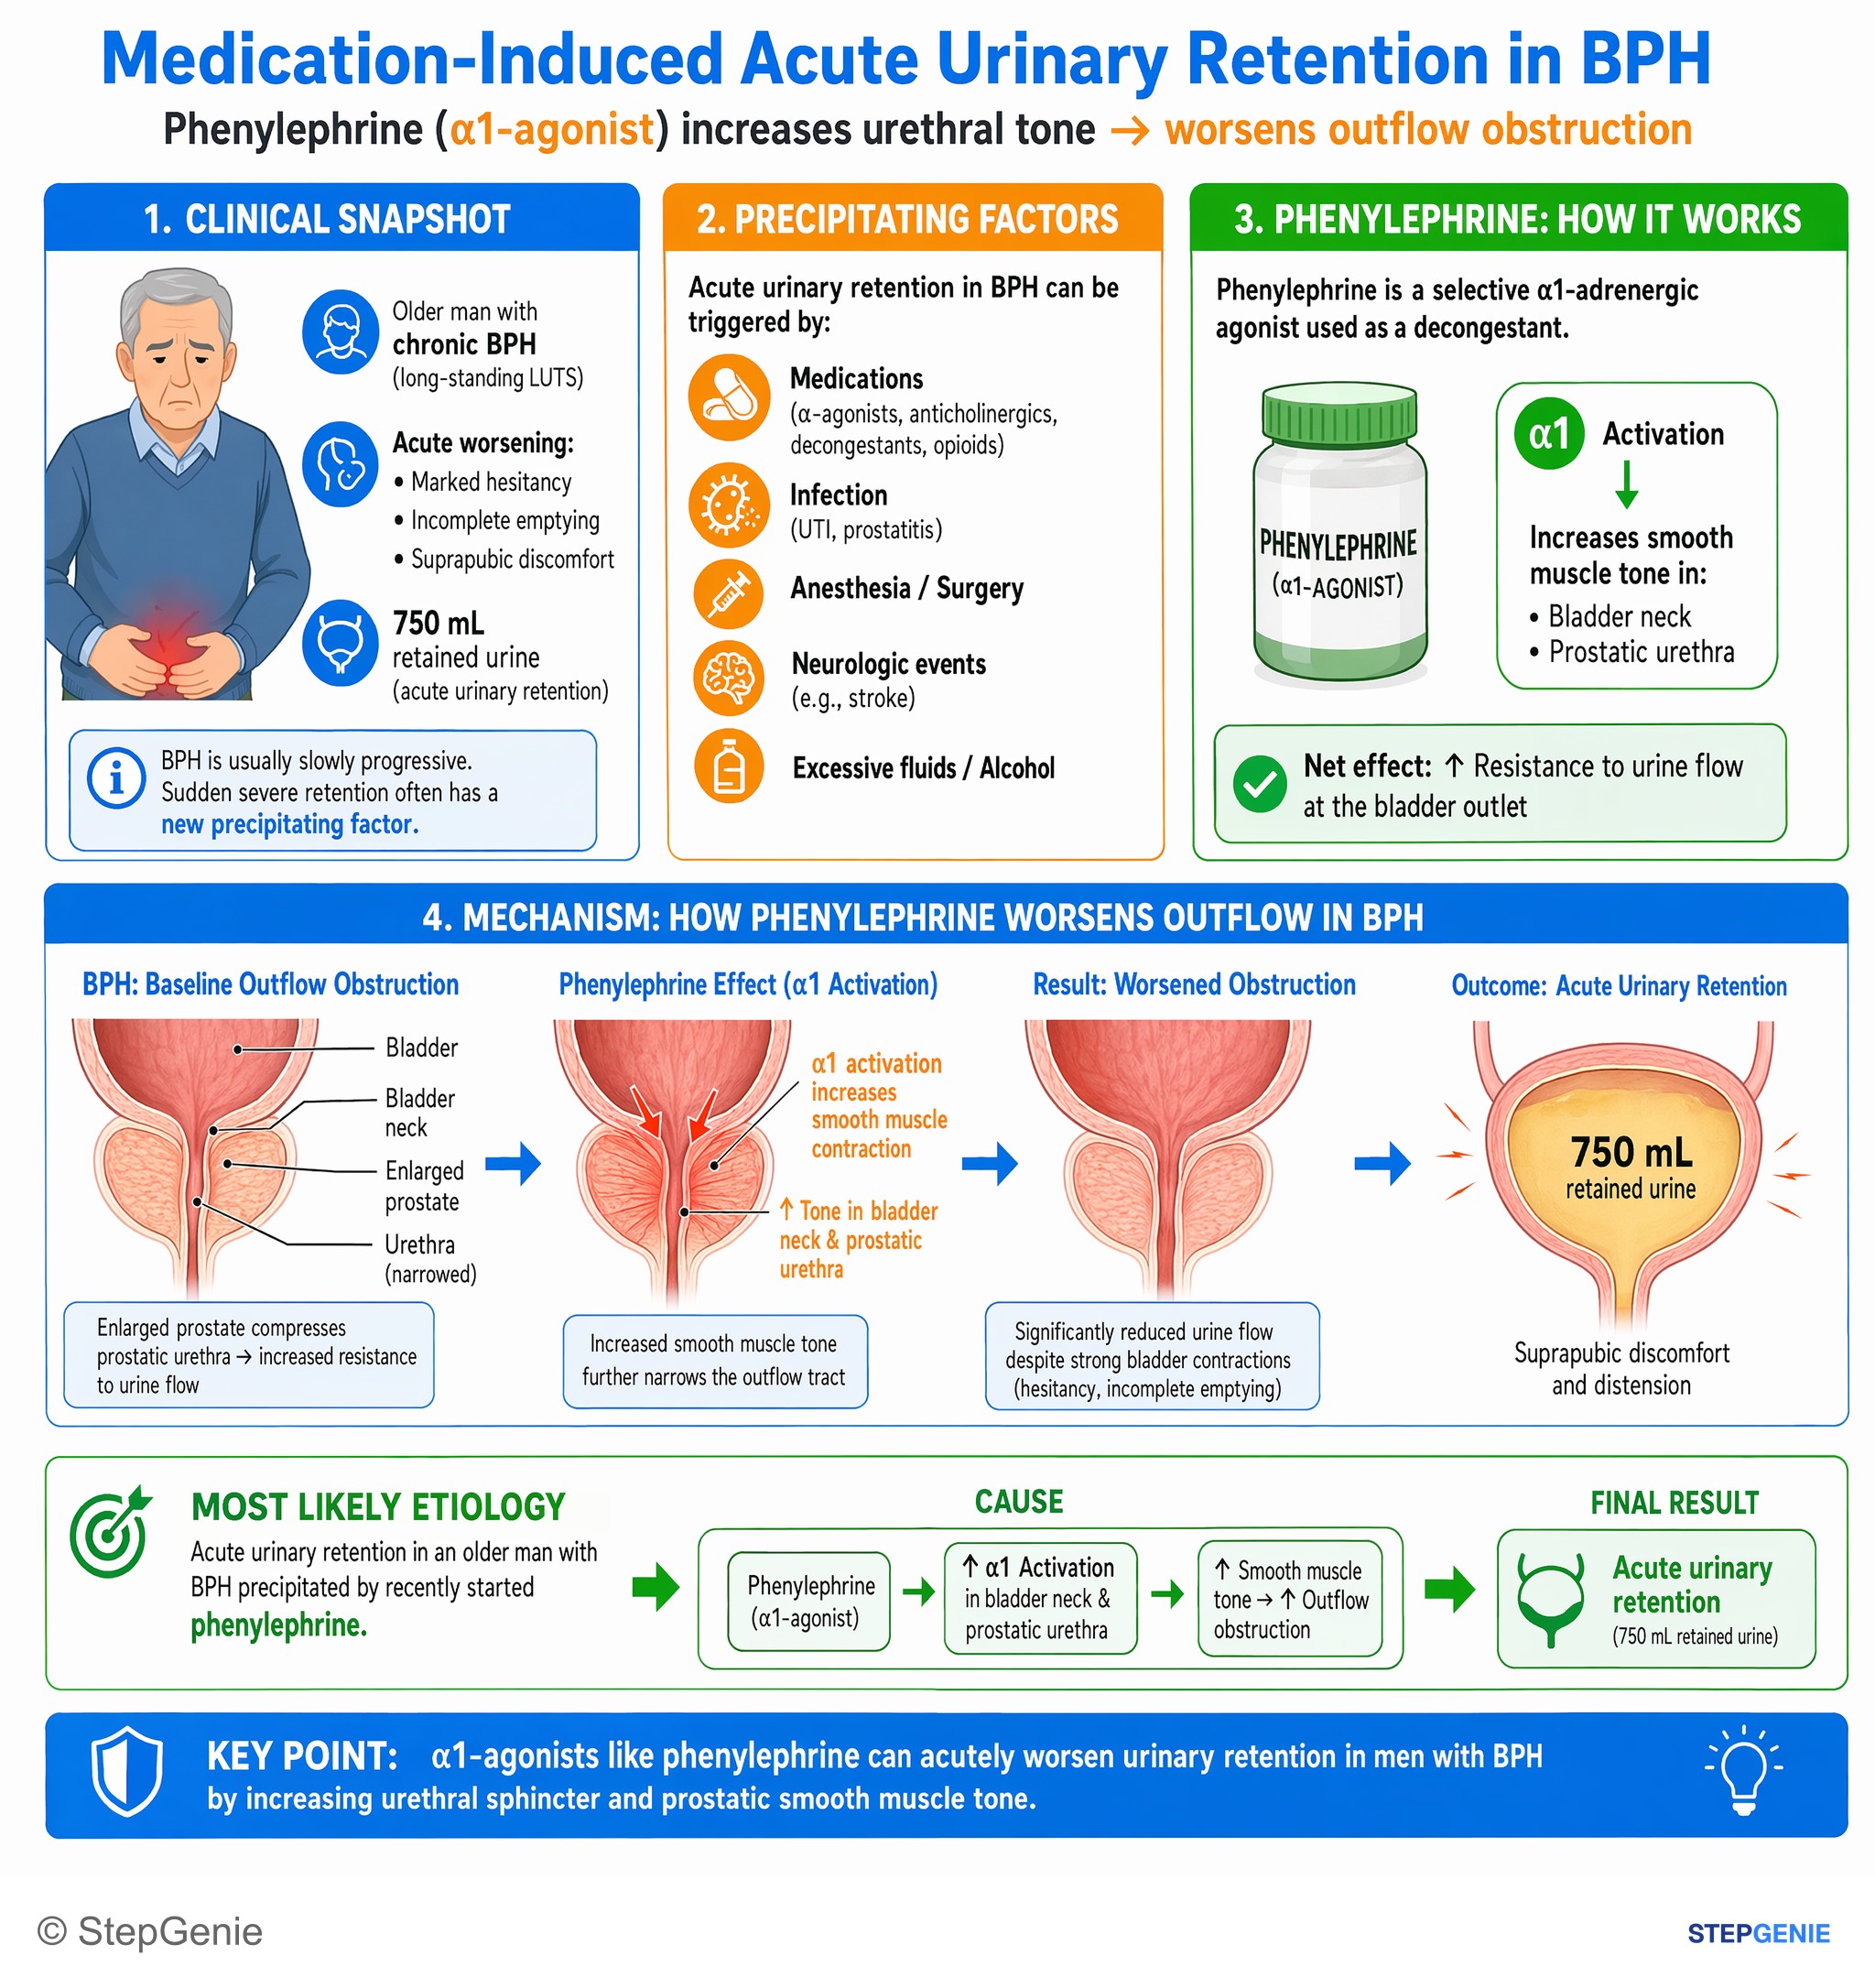
Acute urinary retention in older man with BPH precipitated by α-agonist (phenylephrine) increasing urethral sphincter tone and outflow…
USMLE Step 2Frequently Asked Questions
What causes benign prostatic hyperplasia?
BPH is a proliferation (hyperplasia, not hypertrophy) of glandular and stromal cells in the transition zone around the urethra. It is driven by dihydrotestosterone: 5-alpha-reductase type 2 in prostatic stromal cells converts testosterone to DHT, which makes up about 90% of the androgen inside the prostate. The nodules compress and lengthen the prostatic urethra, and alpha-1 adrenergic smooth muscle tone adds a dynamic component to the obstruction.
Which zone of the prostate does BPH affect compared with prostate cancer?
BPH arises in the transition (periurethral) zone, which surrounds the urethra, so even modest growth causes urinary symptoms. Prostate adenocarcinoma arises mostly in the peripheral zone, which is why it can be felt as a hard nodule on digital rectal exam and is often silent until advanced. BPH feels smooth, rubbery and enlarged. BPH can raise PSA, but it is not a premalignant lesion or a risk factor for prostate cancer.
What is the first-line medication for BPH?
For bothersome symptoms, an alpha-1 blocker is the usual first drug, alongside lifestyle measures. The published summary of the 2026 AUA guideline says to offer a uroselective agent: tamsulosin, silodosin or alfuzosin. These relax smooth muscle in the prostate and bladder neck and improve flow within days. Side effects include dizziness, orthostatic hypotension, ejaculatory dysfunction and intraoperative floppy iris syndrome, so patients should tell their eye surgeon before cataract surgery.
How do finasteride and dutasteride work, and what do they do to PSA?
Both are 5-alpha-reductase inhibitors: finasteride blocks type 2 and dutasteride blocks types 1 and 2, lowering DHT so an enlarged prostate shrinks over several months. They reduce the risk of acute urinary retention and of BPH surgery. They lower PSA by about 50% within 6 months, so the measured value should be doubled for comparison with normal ranges. Side effects include decreased libido, erectile and ejaculatory problems and breast enlargement.
Can tamsulosin and finasteride be used together for BPH?
Yes. Combining an alpha-blocker with a 5-alpha-reductase inhibitor works better than either drug alone for men with an enlarged prostate. Finasteride with doxazosin is labeled to reduce symptomatic progression, and dutasteride plus tamsulosin is sold as one capsule. Tadalafil 5 mg daily is another option, and the published summary of the 2026 AUA guideline says it may be considered with a 5-ARI for select patients, but its label does not recommend combining it with alpha-blockers for BPH.
Which drugs can cause urinary retention in men with BPH?
Drugs that weaken bladder contraction or tighten the bladder outlet can tip an enlarged prostate into acute urinary retention. Classic culprits are anticholinergics such as oxybutynin, first-generation antihistamines such as diphenhydramine, tricyclic antidepressants such as amitriptyline, alpha-agonist decongestants such as pseudoephedrine, and opioids. Acute retention is treated with immediate bladder catheterization, and an alpha-blocker is started before a trial without the catheter.