Rule out pregnancy first. Then, in primary amenorrhea, look for a uterus on exam or ultrasound (absent: karyotype and testosterone; present: FSH, plus a karyotype if FSH is high), and in secondary amenorrhea, order TSH, prolactin, FSH and estradiol and follow whichever result is abnormal.
Who needs a workup. Under the American Society for Reproductive Medicine (ASRM) 2024 committee opinion, Current evaluation of amenorrhea, primary amenorrhea needs evaluation at 15 if secondary sexual development is normal, at 13 if breasts have not started to develop, or 5 years after breast development that began before age 10. StatPearls and the 2023 PCOS guideline use 15 or 3 years after thelarche. Secondary amenorrhea means no menses for more than 3 months after regular cycles, or 6 months after irregular ones.
History, exam, FSH and estradiol identify most causes. The progestin challenge, long taught as a way to gauge estrogen, is now optional in ASRM's algorithm.
Primary amenorrhea evaluation flowchart
ASRM's 2024 algorithm branches on the exam, then the uterus, then FSH. Gonadal dysfunction (about 43%), Müllerian agenesis (10–15%) and constitutional delay (about 14%) cause most cases.
- Exclude pregnancy, even before a first period. Ovulation precedes the first menses.
- Take the history and examine. Breasts prove estrogen exposure; pubic and axillary hair proves androgen action. Note height, Turner stigmata, sense of smell, galactorrhea, headache, low BMI and cyclic pelvic pain. A blind or absent vagina means obstruction, Müllerian agenesis or androgen insensitivity; a visible cervix proves a uterus.
- Confirm the uterus with pelvic ultrasound. A transabdominal scan can miss a rudimentary or prepubertal uterus; pelvic MRI settles doubt.
- No uterus: karyotype and serum testosterone. 46,XX with female-range testosterone is Müllerian agenesis (Mayer-Rokitansky-Küster-Hauser, MRKH); 46,XY with testosterone in the normal male range or higher is complete androgen insensitivity (CAIS).
- Uterus present: FSH, with estradiol, prolactin and TSH. High FSH means gonadal failure: order a karyotype. Low or normal FSH with breasts: run the secondary workup. Low or normal FSH without breasts: constitutional delay, congenital GnRH deficiency, a CNS lesion or functional hypothalamic amenorrhea (FHA).
| Breasts | Uterus | Likely causes | Deciding test |
|---|---|---|---|
| Present | Present, outflow open | Any secondary cause: PCOS, hyperprolactinemia, thyroid disease, FHA | Secondary workup |
| Present | Present, outflow blocked | Imperforate hymen, transverse vaginal septum, vaginal agenesis | Exam, ultrasound |
| Present | Absent | MRKH (46,XX) vs CAIS (46,XY) | Karyotype, testosterone |
| Absent | Present | High FSH: Turner, 46,XX gonadal dysgenesis, Swyer. Low FSH: constitutional delay, Kallmann, CNS lesion, FHA | FSH, then karyotype or brain MRI |
| Absent | Absent | Rare: 46,XY 17α-hydroxylase deficiency, with hypertension | Karyotype |
Outflow obstruction presents with cyclic pelvic pain and trapped blood; an imperforate hymen (about 1 in 1,000 females) bulges blue at the introitus and is treated with hymenectomy.
MRKH vs complete androgen insensitivity
| Feature | MRKH (Müllerian agenesis) | Complete androgen insensitivity |
|---|---|---|
| Karyotype | 46,XX | 46,XY (X-linked AR variant) |
| Gonads | Normal ovaries | Testes, sometimes felt in the groin |
| Why no uterus | Müllerian ducts did not develop | Anti-Müllerian hormone from the testes made them regress |
| Breasts | Normal (ovarian estrogen) | Present (testosterone aromatized to estradiol) |
| Pubic and axillary hair | Normal | Sparse or absent |
| Testosterone | Female range | Normal male range or higher |
| Also check | Kidney and spine anomalies | Gonadectomy, offered after breast development and adult height |
| First-line care | Vaginal dilation, successful in 90–96% | Vaginal dilators; estrogen after gonadectomy |
No breasts, uterus present: high or low FSH
- Turner syndrome (45,X or mosaic): short stature, webbed neck and a high FSH; mean age at diagnosis is about 15. Count at least 30 cells to catch mosaicism, and look for Y material if there is virilization (gonadoblastoma risk). Start estrogen if breasts have not begun to develop by 11 to 12. See the Turner syndrome question breakdown.
- Swyer syndrome (46,XY gonadal dysgenesis): nonfunctional testes make neither anti-Müllerian hormone nor testosterone, so a uterus develops but puberty does not. Remove the streak gonads at diagnosis; tumors occur in up to 25% of women with a Y chromosome.
- Kallmann syndrome: GnRH neurons fail to migrate from the olfactory placode, giving low FSH, LH and estradiol with absent or reduced smell. Look for unilateral renal agenesis, cleft lip or palate and mirror movements.
- Constitutional delay: low FSH, delayed bone age and often a family history of late puberty; a diagnosis of exclusion.
Secondary amenorrhea flowchart
After pregnancy, PCOS and FHA are the most common causes.
- Rule out pregnancy, the most common cause. Serum hCG may be preferred if a urine test could be falsely negative. Long-term users of hormonal contraception need only a pregnancy test unless something else is wrong.
- Take a focused history and exam (table below).
- Order FSH, estradiol, prolactin and TSH; LH and AMH are optional. Add total and free testosterone, DHEAS and a morning 17-hydroxyprogesterone (17-OHP) for hirsutism, acne or virilization. Hormonal contraception should be stopped for at least 3 months before FSH and estradiol are read.
- Get a pelvic ultrasound early, transvaginal if possible: endometrial thickness reflects estrogen, and the ovaries show PCOS morphology or a hormone-secreting mass.
- Sort by pattern with the results table below.
- Use a progestin challenge only if the picture is still unclear.
The same tests fit irregular cycles: ASRM checks prolactin in any menstrual irregularity, and the Endocrine Society evaluates cycles persistently longer than 45 days.
| Clue | Suggests | Next test |
|---|---|---|
| Weight loss, low BMI, heavy training, eating disorder, stress | FHA | FSH, LH, estradiol; DXA after 6 months |
| Galactorrhea, headache, visual field loss | Prolactinoma | Prolactin, then MRI |
| Antipsychotic, metoclopramide or opioid use | Drug-induced hyperprolactinemia | Prolactin; review the drug |
| Hirsutism, acne, acanthosis nigricans, years of irregular cycles | PCOS | Testosterone, 17-OHP |
| Rapid virilization: clitoromegaly, deeper voice | Androgen-secreting ovarian or adrenal tumor | Testosterone, DHEAS |
| Hot flashes, night sweats, vaginal dryness | POI (or FHA) | FSH, estradiol |
| Curettage, hysteroscopic surgery, endometrial ablation | Intrauterine adhesions | Ultrasound, saline sonography or hysteroscopy |
| Postpartum hemorrhage, then failure to lactate | Sheehan syndrome | Free T4, cortisol, other pituitary hormones |
Amenorrhea labs: how to read each result
FSH and estradiol localize the problem: high FSH means the ovary (hypergonadotropic), low or normal FSH with low estradiol means the hypothalamus or pituitary (hypogonadotropic), and normal values mean anovulation or a uterine cause.
| Result | What it means | Next step |
|---|---|---|
| Positive hCG | Pregnancy | Stop the amenorrhea workup |
| High TSH, low free T4 | Primary hypothyroidism; raised TRH can also raise prolactin | Levothyroxine; menses usually return once euthyroid |
| Prolactin 20–40 ng/mL, no symptoms | Transient rise or macroprolactin | Repeat; macroprolactin if still mildly high |
| Prolactin persistently high | Drug, hypothyroidism, renal failure or prolactinoma | Review drugs and TSH, then pituitary MRI |
| FSH above 25 IU/L, low estradiol | POI if under 40, or gonadal dysgenesis | Karyotype, FMR1 premutation, 21-hydroxylase antibodies |
| FSH low or normal, estradiol under about 30 pg/mL | Hypogonadotropic: FHA, pituitary or hypothalamic lesion | History; brain MRI for red flags or no clear cause |
| FSH and estradiol normal, LH high relative to FSH | Anovulation, typically PCOS | Androgens; 2023 PCOS criteria |
| High testosterone | PCOS; if very high or rapid virilization, a tumor | Pelvic ultrasound; adrenal evaluation if DHEAS is very high |
| Morning 17-OHP above 2 ng/mL | Possible nonclassic congenital adrenal hyperplasia | ACTH stimulation test |
| Thin endometrium, normal hormones, prior uterine surgery | Intrauterine adhesions (Asherman syndrome) | Saline sonography or hysteroscopy |
The progestin challenge test: still taught, now optional
How it works. Medroxyprogesterone acetate 5–10 mg daily for 7–10 days; any bleeding within days of stopping is positive. Withdrawal sheds an endometrium that estrogen has already built, the same trigger as a normal period (see menstrual cycle physiology).
- Bleed: estrogen is present and the outflow tract is open, so the problem is anovulation, classically PCOS. Not reassuring: unopposed estrogen raises the risk of endometrial hyperplasia.
- No bleed: too little estrogen (FHA, POI) or a uterus that cannot respond or drain (Asherman syndrome, cervical stenosis).
- Estrogen–progestin challenge next: about 3 weeks of estrogen with a progestin at the end. A bleed means low estrogen was the problem; no bleed means the endometrium or outflow tract, so do saline sonography or hysteroscopy.
Why it is optional now.
- ASRM 2024 lists it, like LH and AMH, as optional, warns of false positives and negatives and says other approaches "may result in a more rapid and accurate diagnosis." A thin endometrium on ultrasound already predicts no bleed.
- In one survey cited by Endotext, almost half of women with premature ovarian failure bled after progestin.
- Merck warns that the trial takes weeks and can delay serious diagnoses; consider brain MRI before or during it if a pituitary lesion is suspected.
- The Endocrine Society's 2017 FHA guideline still makes a weak suggestion for it, to show chronic estrogen exposure and an intact outflow tract.
High prolactin or abnormal TSH
Prolactin. Prolactin suppresses GnRH, so LH, FSH and estradiol fall. Most labs set the upper limit at 15–20 ng/mL, and only about a third of affected women have galactorrhea, so test everyone.
- Mild rise (20–40 ng/mL): repeat it; sleep, exercise, breast stimulation, meals and drugs raise prolactin transiently. If it stays mildly high without symptoms, test for macroprolactin, an inactive antibody-bound form behind up to nearly 20% of hyperprolactinemia.
- Drugs: antipsychotics (risperidone raises it most), metoclopramide, domperidone, tricyclics, SSRIs, verapamil, methyldopa and opioids. Stop or switch the drug with the psychiatrist when possible; see typical vs atypical antipsychotics.
- Hypothyroidism: raised TRH drives both TSH and prolactin; up to 20–40% of hypothyroid patients have hyperprolactinemia, and thyroid replacement normalizes it.
- Persistently high without a drug or thyroid cause: pituitary MRI. A tumor is found in 50–60% of women with hyperprolactinemia, and its likelihood does not track the level, though values above 200 ng/mL rarely have another cause (risperidone can exceed it). A large adenoma with only a mild rise suggests the hook effect: repeat at 1:100 dilution.
- Treatment: cabergoline first; bromocriptine in pregnancy. More in prolactinoma vs acromegaly.
TSH. Check it in everyone; hypothyroidism and hyperthyroidism both cause anovulation. In central hypothyroidism, as in Sheehan syndrome, TSH is unreliable, so measure free T4 too.
High FSH: primary ovarian insufficiency
The 2024 international guideline from ESHRE, ASRM, CRE-WHiRL and the International Menopause Society simplified the diagnosis.
- Criteria: age under 40, at least 4 months of absent or irregular cycles and one FSH above 25 IU/L. Repeat FSH after 4–6 weeks only if uncertain; cycle timing does not matter. The 2015 version required two values.
- Not diagnostic alone: estradiol (a low level supports the diagnosis) or AMH (helpful if FSH is inconclusive). Exclude pregnancy, and stop hormones that can lower FSH.
- Find the cause: karyotype and FMR1 premutation testing in everyone with non-iatrogenic POI (see fragile X), 21-hydroxylase antibodies if the cause is unknown, and TSH. Chemotherapy, radiation and autoimmune oophoritis are other causes.
- Manage: DXA at diagnosis and hormone therapy until the usual age of menopause, with at least 2 mg oral or 100 µg transdermal estradiol daily for bone. About 5–10% still conceive spontaneously.
Low FSH and low estradiol: hypothalamic amenorrhea, RED-S and Sheehan syndrome
In FHA, estradiol is in the menopausal range (under about 30 pg/mL), FSH and LH are normal to low normal, and LH is often disproportionately lower than FSH.
Functional hypothalamic amenorrhea follows an energy deficit (an eating disorder, heavy exercise or stress) that slows GnRH pulses. The Endocrine Society's 2017 guideline makes it a diagnosis of exclusion:
- Labs: hCG, blood count, chemistries, TSH, free T4, prolactin, LH, FSH, estradiol and AMH; androgens and an 8 AM 17-OHP when indicated.
- Brain MRI for severe or persistent headache, persistent vomiting that is not self-induced, changes in vision, thirst or urination, lateralizing signs, or signs of another pituitary hormone problem.
- DXA after 6 months of amenorrhea, sooner with severe nutritional deficiency or skeletal fragility.
- Treatment: correct the energy balance (more calories, less exercise, often weight gain) with psychological support such as cognitive behavioral therapy. Oral contraceptives are not suggested just to restore menses or bone; if menses do not return, use short-term transdermal estradiol with cyclic oral progestin. Bisphosphonates and denosumab are not suggested. Severe bradycardia, hypotension, orthostasis or electrolyte imbalance warrants inpatient evaluation; see eating disorders.
Female athlete triad and RED-S. The triad is low energy availability (with or without an eating disorder), menstrual dysfunction and low bone density; amenorrheic athletes have more stress fractures. The International Olympic Committee's 2023 consensus describes the broader Relative Energy Deficiency in Sport (REDs), which affects female and male athletes whose energy intake is inadequate for their exercise.
Sheehan syndrome is anterior pituitary necrosis after severe postpartum hemorrhage. Failure to lactate comes first; amenorrhea, hypothyroidism and adrenal insufficiency (hyponatremia, hypoglycemia) can follow months to years later. Test free T4, cortisol and the other axes; later MRI shows an empty sella in about 70%. Replacement is lifelong, and corticosteroids start before thyroid hormone to avoid an adrenal crisis. See empty sella syndrome.
Normal FSH and estradiol: PCOS and Asherman syndrome
PCOS, renamed polyendocrine metabolic ovarian syndrome (PMOS) by a global consensus in The Lancet in May 2026, keeps its diagnostic criteria. The 2023 international guideline requires 2 of 3:
- Clinical or biochemical hyperandrogenism (total and free testosterone first; androstenedione and DHEAS only if testosterone is normal).
- Ovulatory dysfunction.
- Polycystic ovarian morphology, defined in adults as 20 or more follicles in at least one ovary, or a high AMH instead of ultrasound.
Exclude other causes with TSH, prolactin, 17-OHP and FSH. Irregular cycles plus hyperandrogenism suffice; adolescents need both, because ultrasound and AMH are not recommended at that age.
- Look-alikes: a morning 17-OHP above 2 ng/mL suggests nonclassic congenital adrenal hyperplasia (see the congenital adrenal hyperplasia chart); new, severe or worsening hyperandrogenism needs a search for an androgen-secreting tumor.
- Manage: combined oral contraceptives for irregular cycles and hirsutism, metformin mainly for metabolic features, letrozole first-line for ovulation induction. Chronic anovulation raises the risk of endometrial hyperplasia and cancer. More in the PCOS question breakdown.
Asherman syndrome is intrauterine scarring after damage to the basal endometrium, usually from curettage after a miscarriage, termination or delivery (weeks 2–4 postpartum are riskiest), and also after hysteroscopic myomectomy, ablation or genital tuberculosis. Hormones are normal and the lining is thin. Saline sonography or hysterosalpingography detects adhesions with a sensitivity of only about 75%; hysteroscopy is the gold standard and allows adhesiolysis in the same procedure. Cervical stenosis after a cone or excision procedure looks similar.
USMLE traps: classic teaching vs current guidance
| Trap | Old or tempting answer | Current guidance |
|---|---|---|
| Progestin challenge as a routine step | Bleed or no bleed sorts the cause | Optional; FSH, estradiol, prolactin, TSH and ultrasound first (ASRM 2024) |
| POI diagnosis | Two raised FSH values a month apart, often above 30–40 IU/L | One FSH above 25 IU/L plus 4 months of disordered cycles (2024) |
| FHA bone protection | Combined oral contraceptive | Fix the energy deficit; short-term transdermal estradiol with cyclic progestin if needed |
| PCOS ultrasound | 12 or more follicles of 2–9 mm | 20 or more follicles in one ovary, or AMH, in adults; neither in adolescents |
| High prolactin with high TSH | Pituitary MRI or cabergoline | Treat the hypothyroidism first |
| No uterus on ultrasound | Müllerian agenesis | A rudimentary uterus can be missed (MRI if unsure); karyotype and testosterone separate MRKH from CAIS |
| CAIS gonads | Remove at diagnosis | Usually after puberty; Swyer gonads at diagnosis |
More OB/GYN reviews are on the Obstetrics & Gynecology hub.
USMLE-style vignettes
Vignette 1: breasts but no uterus. A 16-year-old girl has never menstruated. She has Tanner 5 breasts but sparse pubic and axillary hair. The vagina is short and ends blindly, and there is a firm mass in each inguinal canal. Urine hCG is negative, and pelvic ultrasound shows no uterus. Which result is most likely?
Answer: A 46,XY karyotype with serum testosterone in the normal male range: complete androgen insensitivity.
Why not the others: 46,XX with female-range testosterone is Müllerian agenesis, but pubic hair would be normal. 45,X with high FSH is Turner syndrome, which has a uterus and no breast development. 46,XY with low testosterone fits Swyer syndrome (uterus present) or 17α-hydroxylase deficiency (no breasts, hypertension).
Vignette 2: high prolactin, high TSH. A 29-year-old woman has had no menses for 5 months after years of regular cycles. She reports fatigue, constipation and a milky nipple discharge. Urine hCG is negative. Prolactin is 48 ng/mL (reference under 20), TSH is 32 mU/L and free T4 is low. What is the best next step?
Answer: Start levothyroxine and recheck prolactin once she is euthyroid.
Why not the others: Raised TRH stimulates lactotrophs as well as thyrotrophs and can even enlarge the pituitary, so an MRI now is premature; it is for prolactin that stays high after thyroid replacement. Cabergoline treats the wrong problem, and macroprolactin testing is for mild rises without symptoms.
Vignette 3: the runner. A 19-year-old distance runner has not menstruated for 8 months; her cycles were regular until she increased her training. BMI is 17.8 kg/m². Two months ago she had a metatarsal stress fracture. Urine hCG is negative; TSH, free T4 and prolactin are normal; FSH is 3.1 IU/L, LH 0.9 IU/L and estradiol 18 pg/mL. Alongside a plan to raise her energy availability, what is the best next step?
Answer: A baseline DXA scan.
Why not the others: The Endocrine Society suggests DXA after 6 months of amenorrhea, sooner with skeletal fragility, and suggests against oral contraceptives (they mask recovery while bone loss can continue) and bisphosphonates. Brain MRI is for red flags such as persistent headache, vomiting or visual change. Low FSH excludes ovarian insufficiency, and with estradiol this low a progestin challenge is unlikely to cause a bleed.
Vignette 4: after a curettage. A 31-year-old woman has had no menses for 7 months. Her cycles were regular until a dilation and curettage (D&C) for an incomplete miscarriage, repeated 2 weeks later for retained tissue. Urine hCG is negative; TSH, prolactin, FSH and estradiol are normal. Transvaginal ultrasound shows a thin endometrium and normal ovaries. What is the best next step?
Answer: Hysteroscopy, which diagnoses and treats intrauterine adhesions (Asherman syndrome).
Why not the others: Normal hormones place the problem in the uterus, and repeated curettage after a pregnancy is the classic cause. A progestin challenge is optional and, with a thin lining, predictably negative; an estrogen–progestin challenge would only confirm that the endometrium cannot respond. Pituitary MRI and a karyotype do not fit normal prolactin and gonadotropins.
Key takeaways
- Pregnancy test first, in primary and secondary amenorrhea, even before menarche.
- Primary: confirm the uterus. No uterus: karyotype and testosterone (MRKH vs CAIS). Uterus: FSH; high FSH needs a karyotype (Turner, Swyer); low FSH without breasts suggests constitutional delay, Kallmann syndrome or a central cause.
- Secondary: FSH, estradiol, prolactin and TSH up front, pelvic ultrasound early, androgens if hirsute. The progestin challenge is optional.
- Current numbers: POI is age under 40, 4 months of disordered cycles and one FSH above 25 IU/L; PCOS (now PMOS) needs 2 of 3 criteria.
- Traps: treat hypothyroidism before blaming the pituitary; no oral contraceptives for FHA bone loss; CAIS gonadectomy after puberty, Swyer at diagnosis.
Sources
- Current evaluation of amenorrhea: a committee opinion — American Society for Reproductive Medicine, Fertil Steril (2024)
- Gordon CM, et al. Functional Hypothalamic Amenorrhea: An Endocrine Society Clinical Practice Guideline — J Clin Endocrinol Metab (2017)
- Panay N, et al. Evidence-based guideline: premature ovarian insufficiency — Human Reproduction Open (2024)
- Teede HJ, et al. Recommendations From the 2023 International Evidence-based Guideline for the Assessment and Management of Polycystic Ovary Syndrome — J Clin Endocrinol Metab (2023)
- Teede HJ, et al. Polyendocrine metabolic ovarian syndrome, the new name for polycystic ovary syndrome — The Lancet (2026)
- Bahri-Khomami M, et al. From polycystic ovary syndrome to polyendocrine metabolic ovarian syndrome — Am J Obstet Gynecol (2026)
- Mountjoy M, et al. 2023 International Olympic Committee's consensus statement on Relative Energy Deficiency in Sport (REDs) — Br J Sports Med (2023)
- Müllerian Agenesis: Diagnosis, Management, and Treatment, Committee Opinion 728 — ACOG (2018, reaffirmed 2026)
- Amenorrhea — Merck Manual Professional Edition (2026)
- Rebar R. Evaluation of Amenorrhea, Anovulation, and Abnormal Bleeding — Endotext, NCBI Bookshelf (2018)
- Primary Amenorrhea — StatPearls, NCBI Bookshelf (2023)
- Secondary Amenorrhea — StatPearls, NCBI Bookshelf (2024)
- Hyperprolactinemia — StatPearls, NCBI Bookshelf (2025)
- Turner Syndrome — StatPearls, NCBI Bookshelf (2026)
- Androgen Insensitivity Syndrome — StatPearls, NCBI Bookshelf (2026)
- Androgen Insensitivity Syndrome — GeneReviews, NCBI Bookshelf (2017)
- Kallmann Syndrome — StatPearls, NCBI Bookshelf (2024)
- Imperforate Hymen — StatPearls, NCBI Bookshelf (2023)
- Asherman Syndrome — StatPearls, NCBI Bookshelf (2023)
- Sheehan Syndrome — StatPearls, NCBI Bookshelf (2023)
- Hypopituitarism — StatPearls, NCBI Bookshelf (2023)
- Female Athlete Triad — StatPearls, NCBI Bookshelf (2023)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
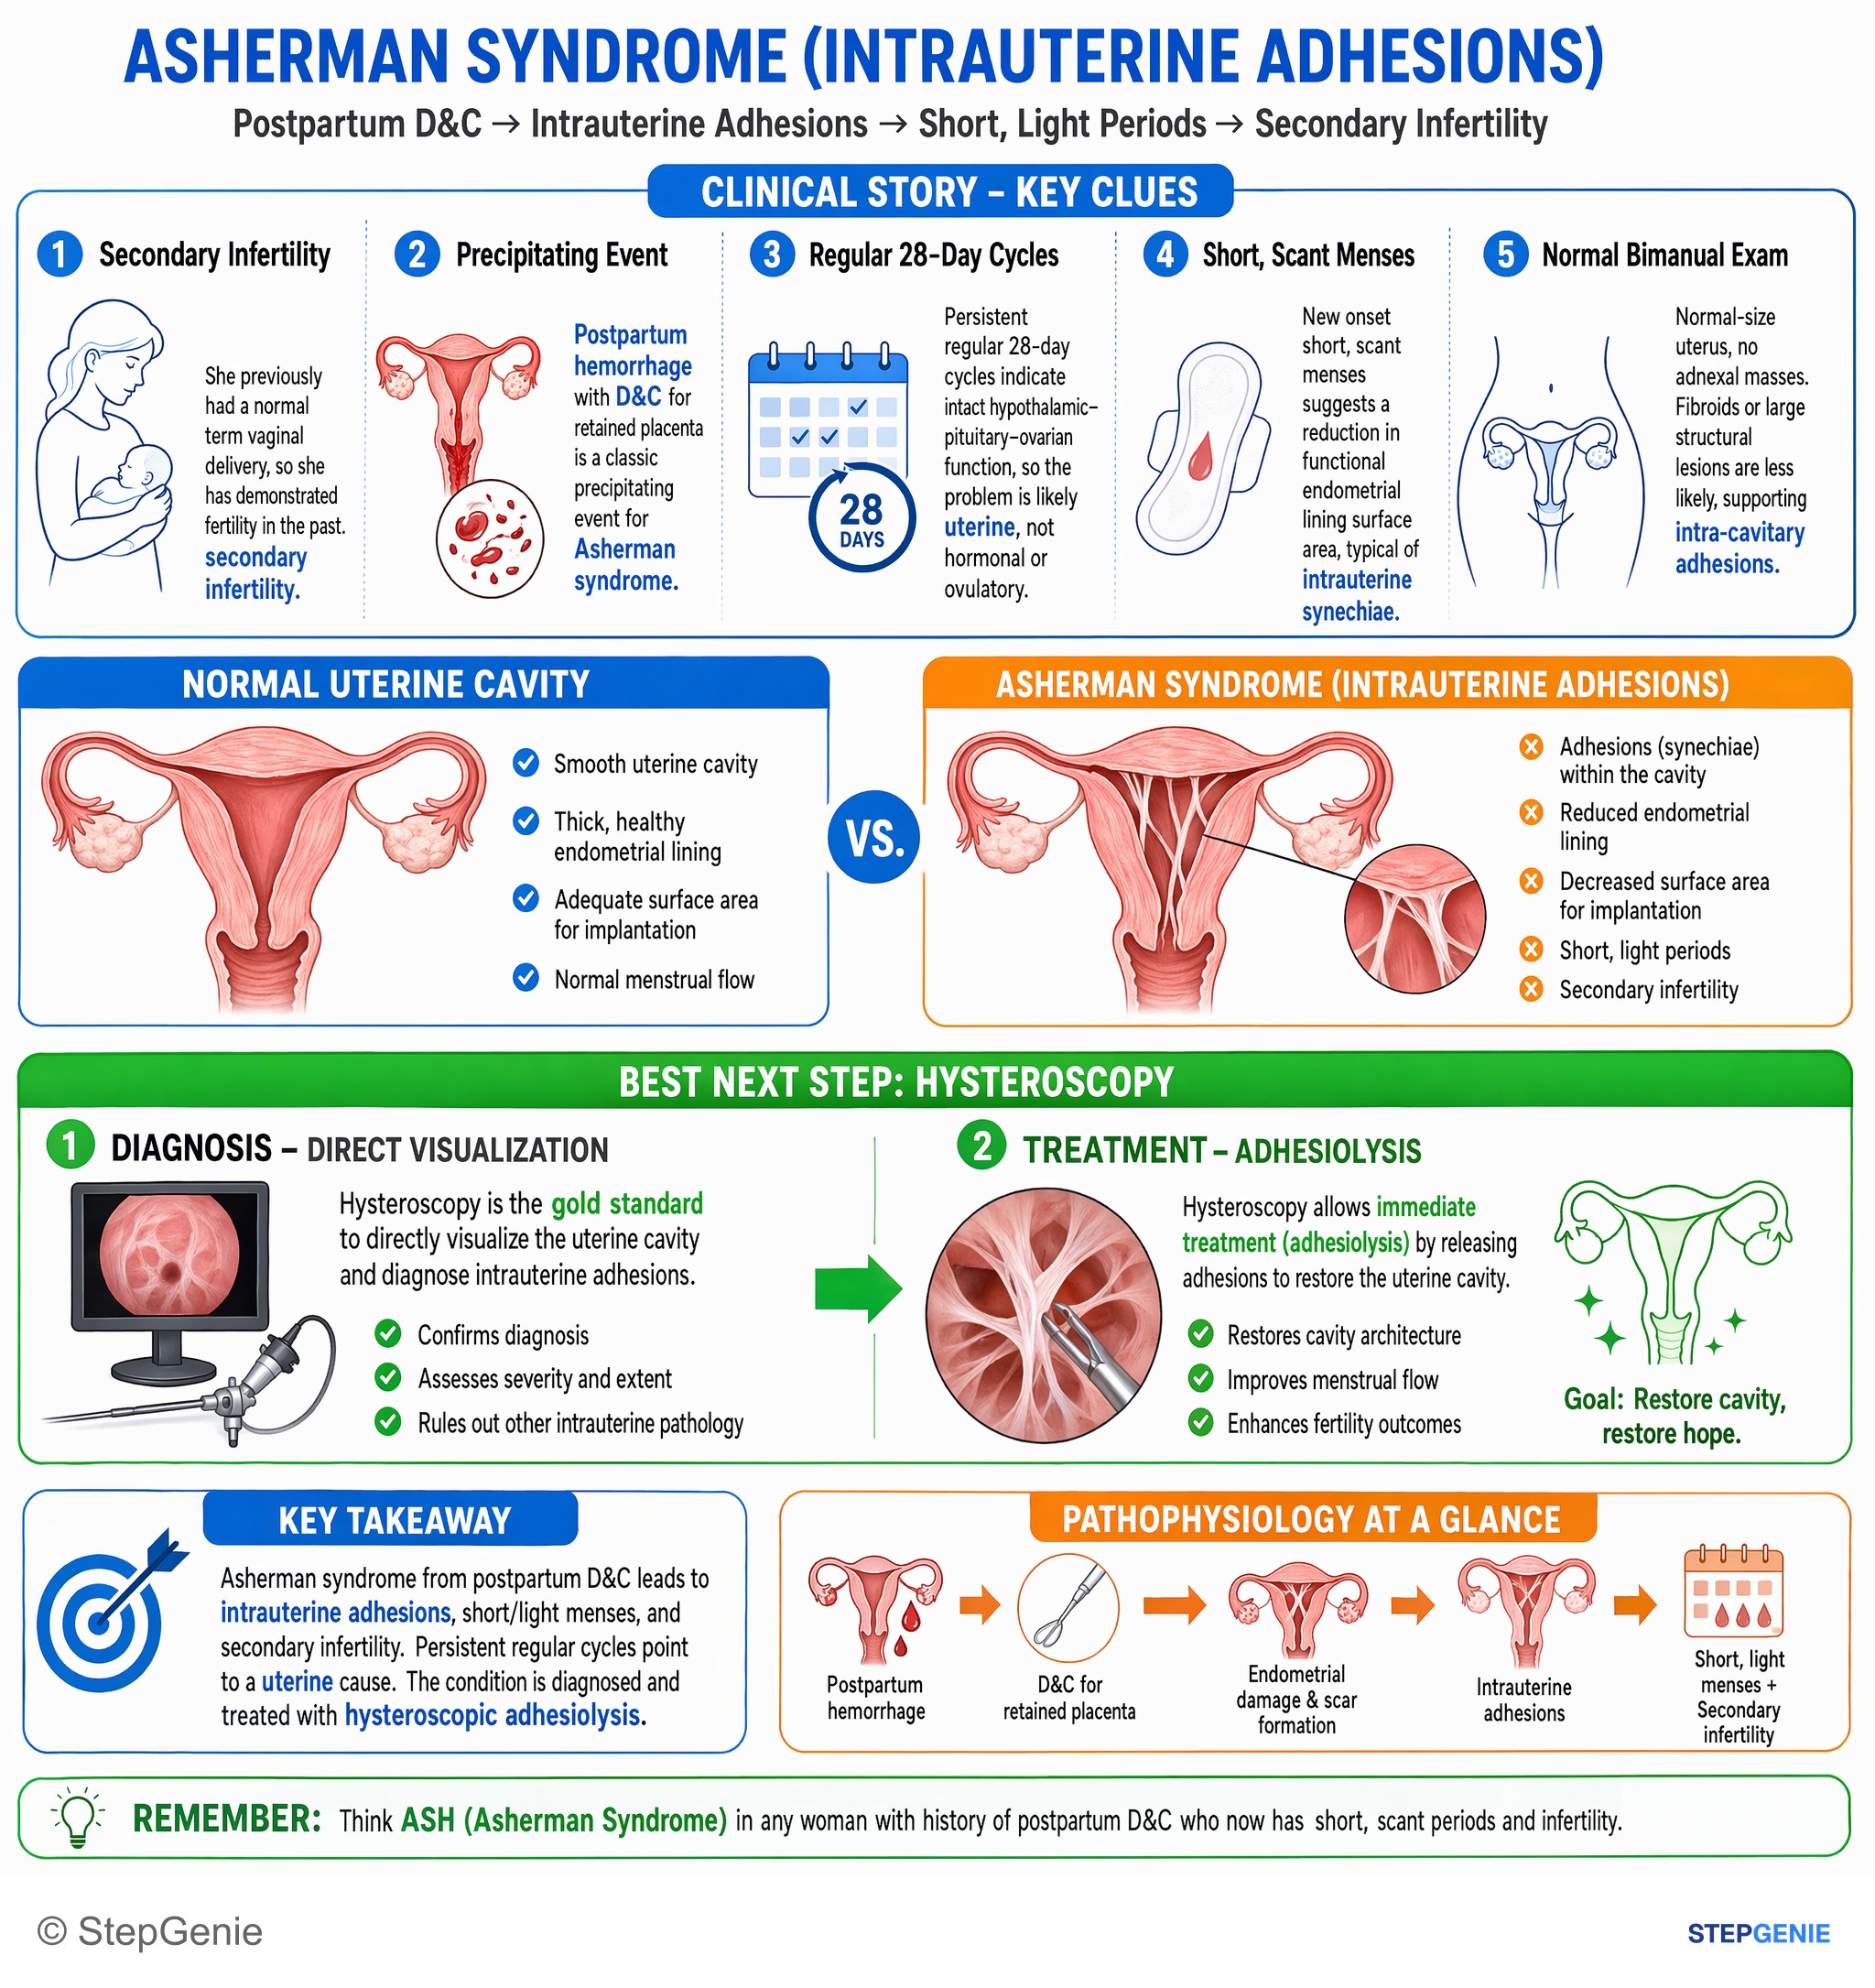
Asherman syndrome from postpartum D&C → intrauterine adhesions, short/light menses, secondary infertility; diagnose and treat with…
USMLE Step 2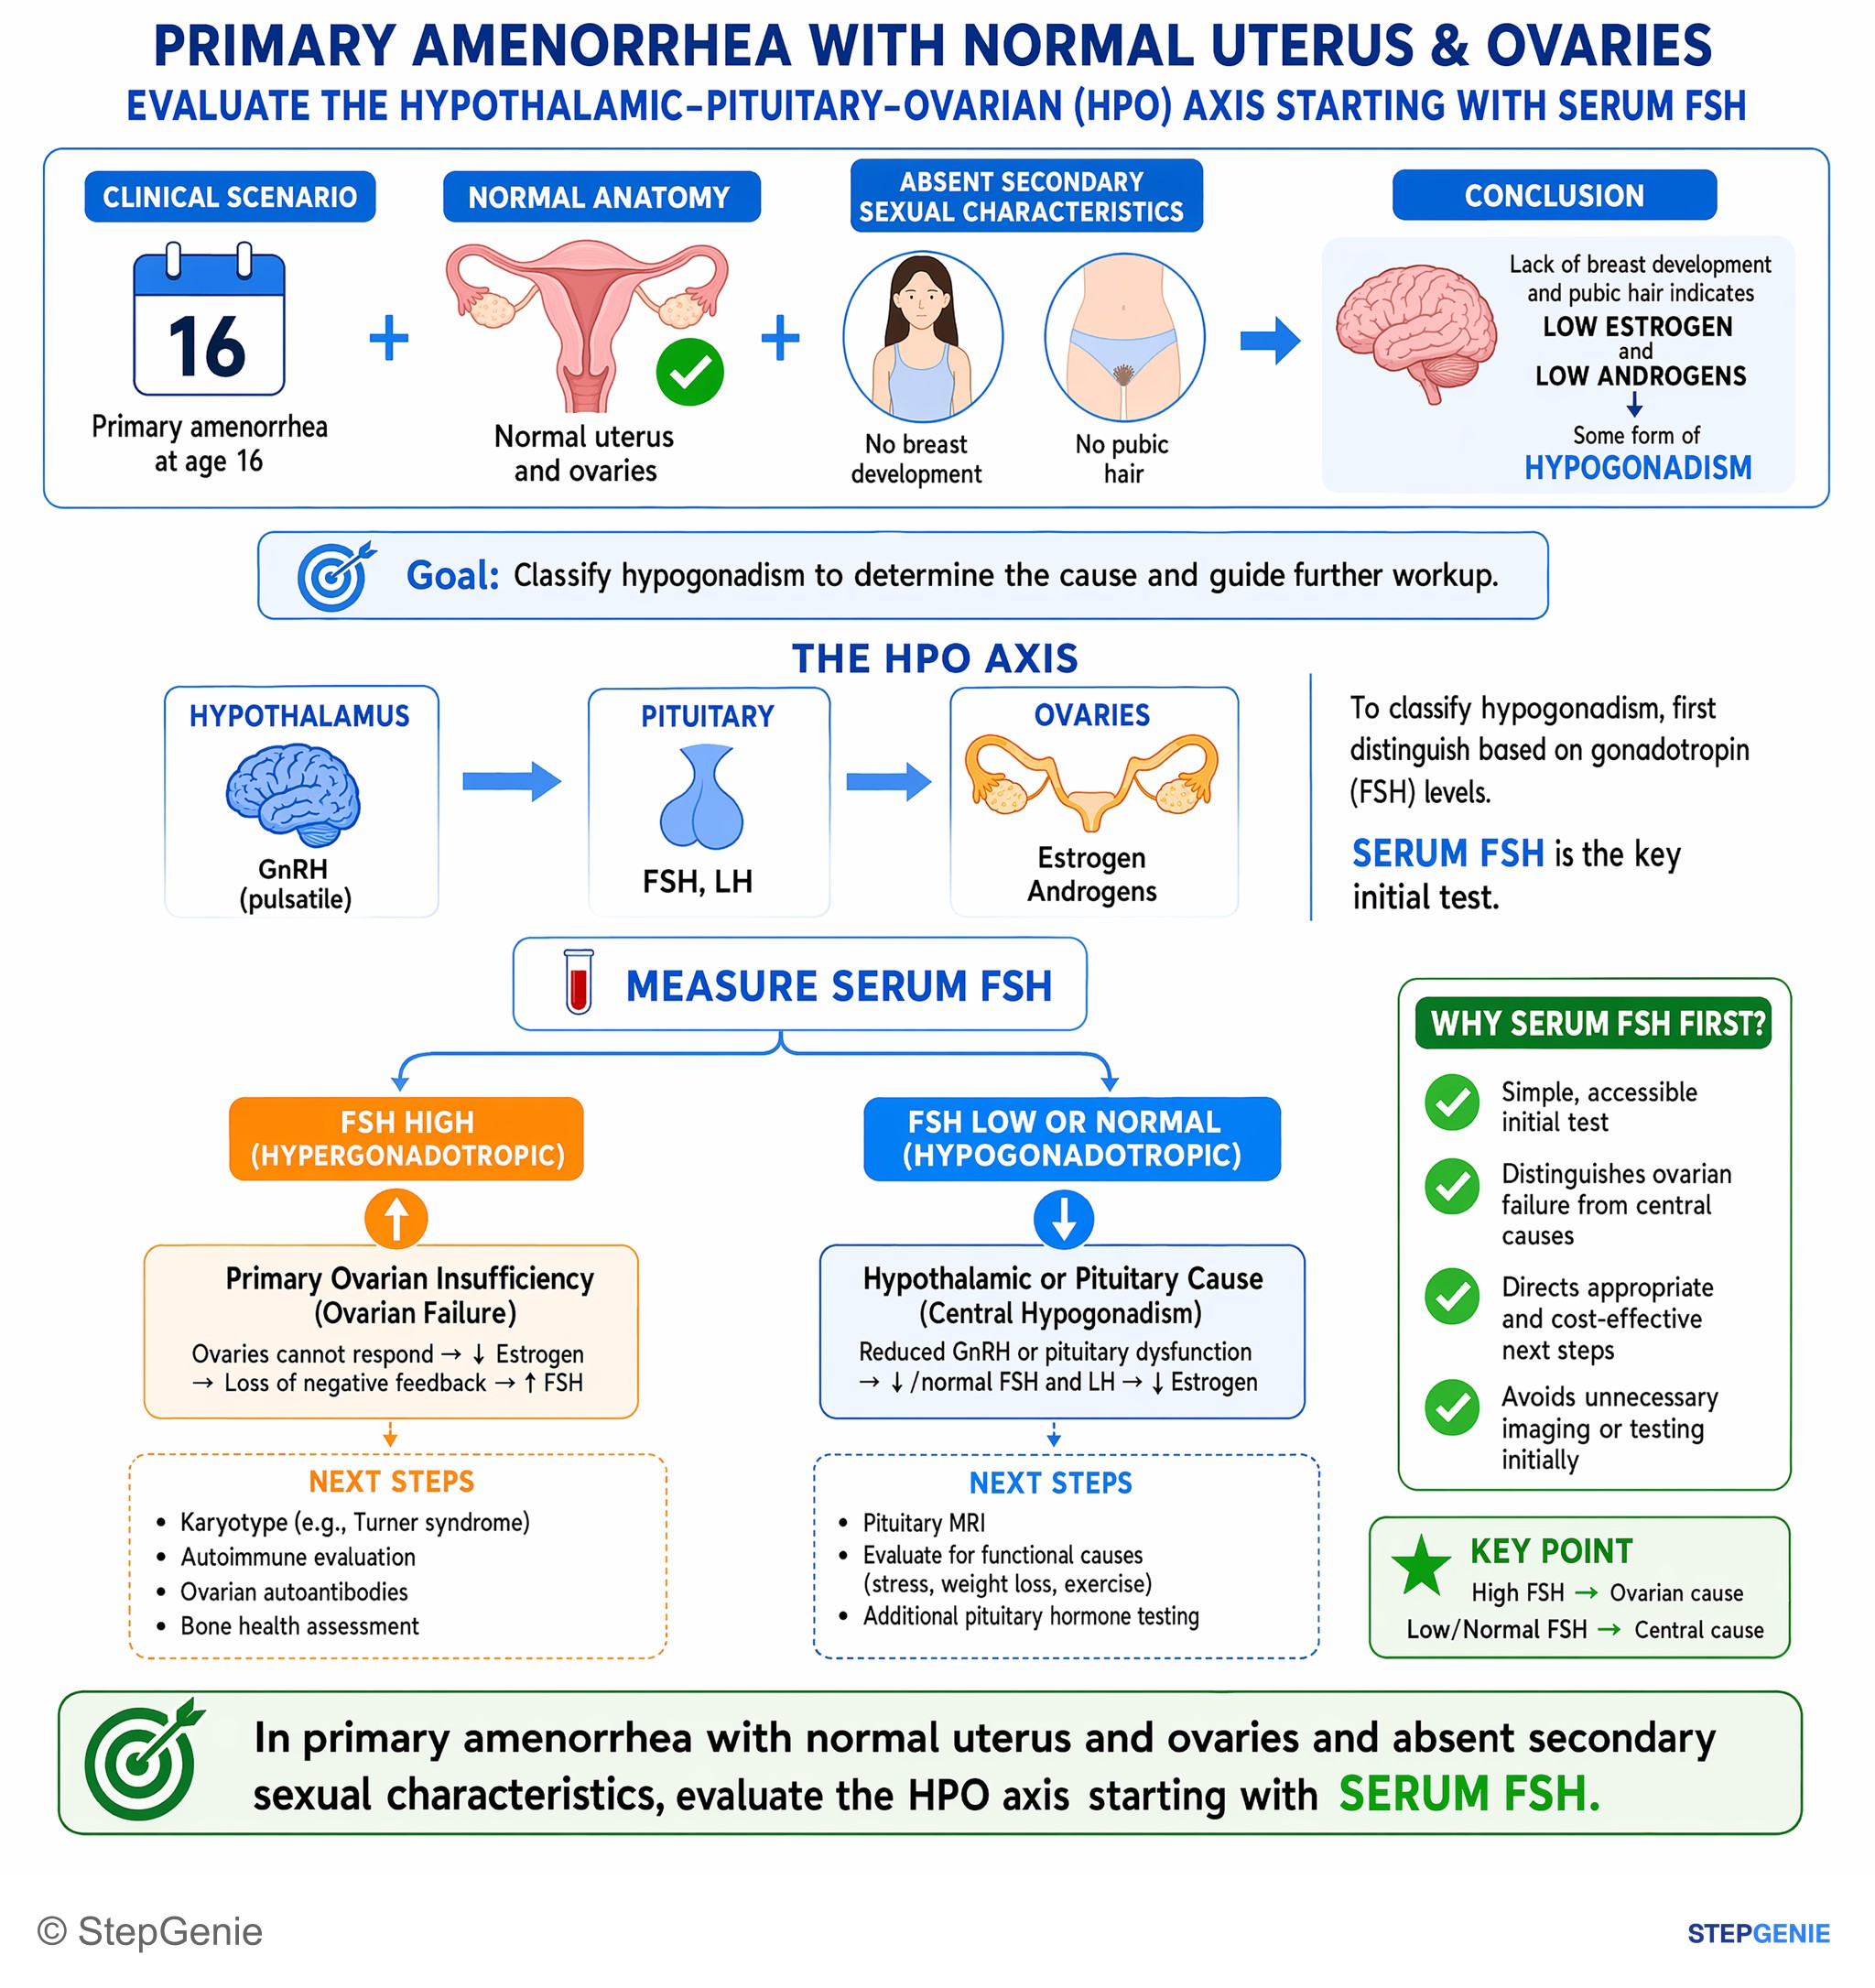
Primary amenorrhea with normal uterus/ovaries and no secondary sexual characteristics → evaluate hypothalamic–pituitary–ovarian axis…
USMLE Step 2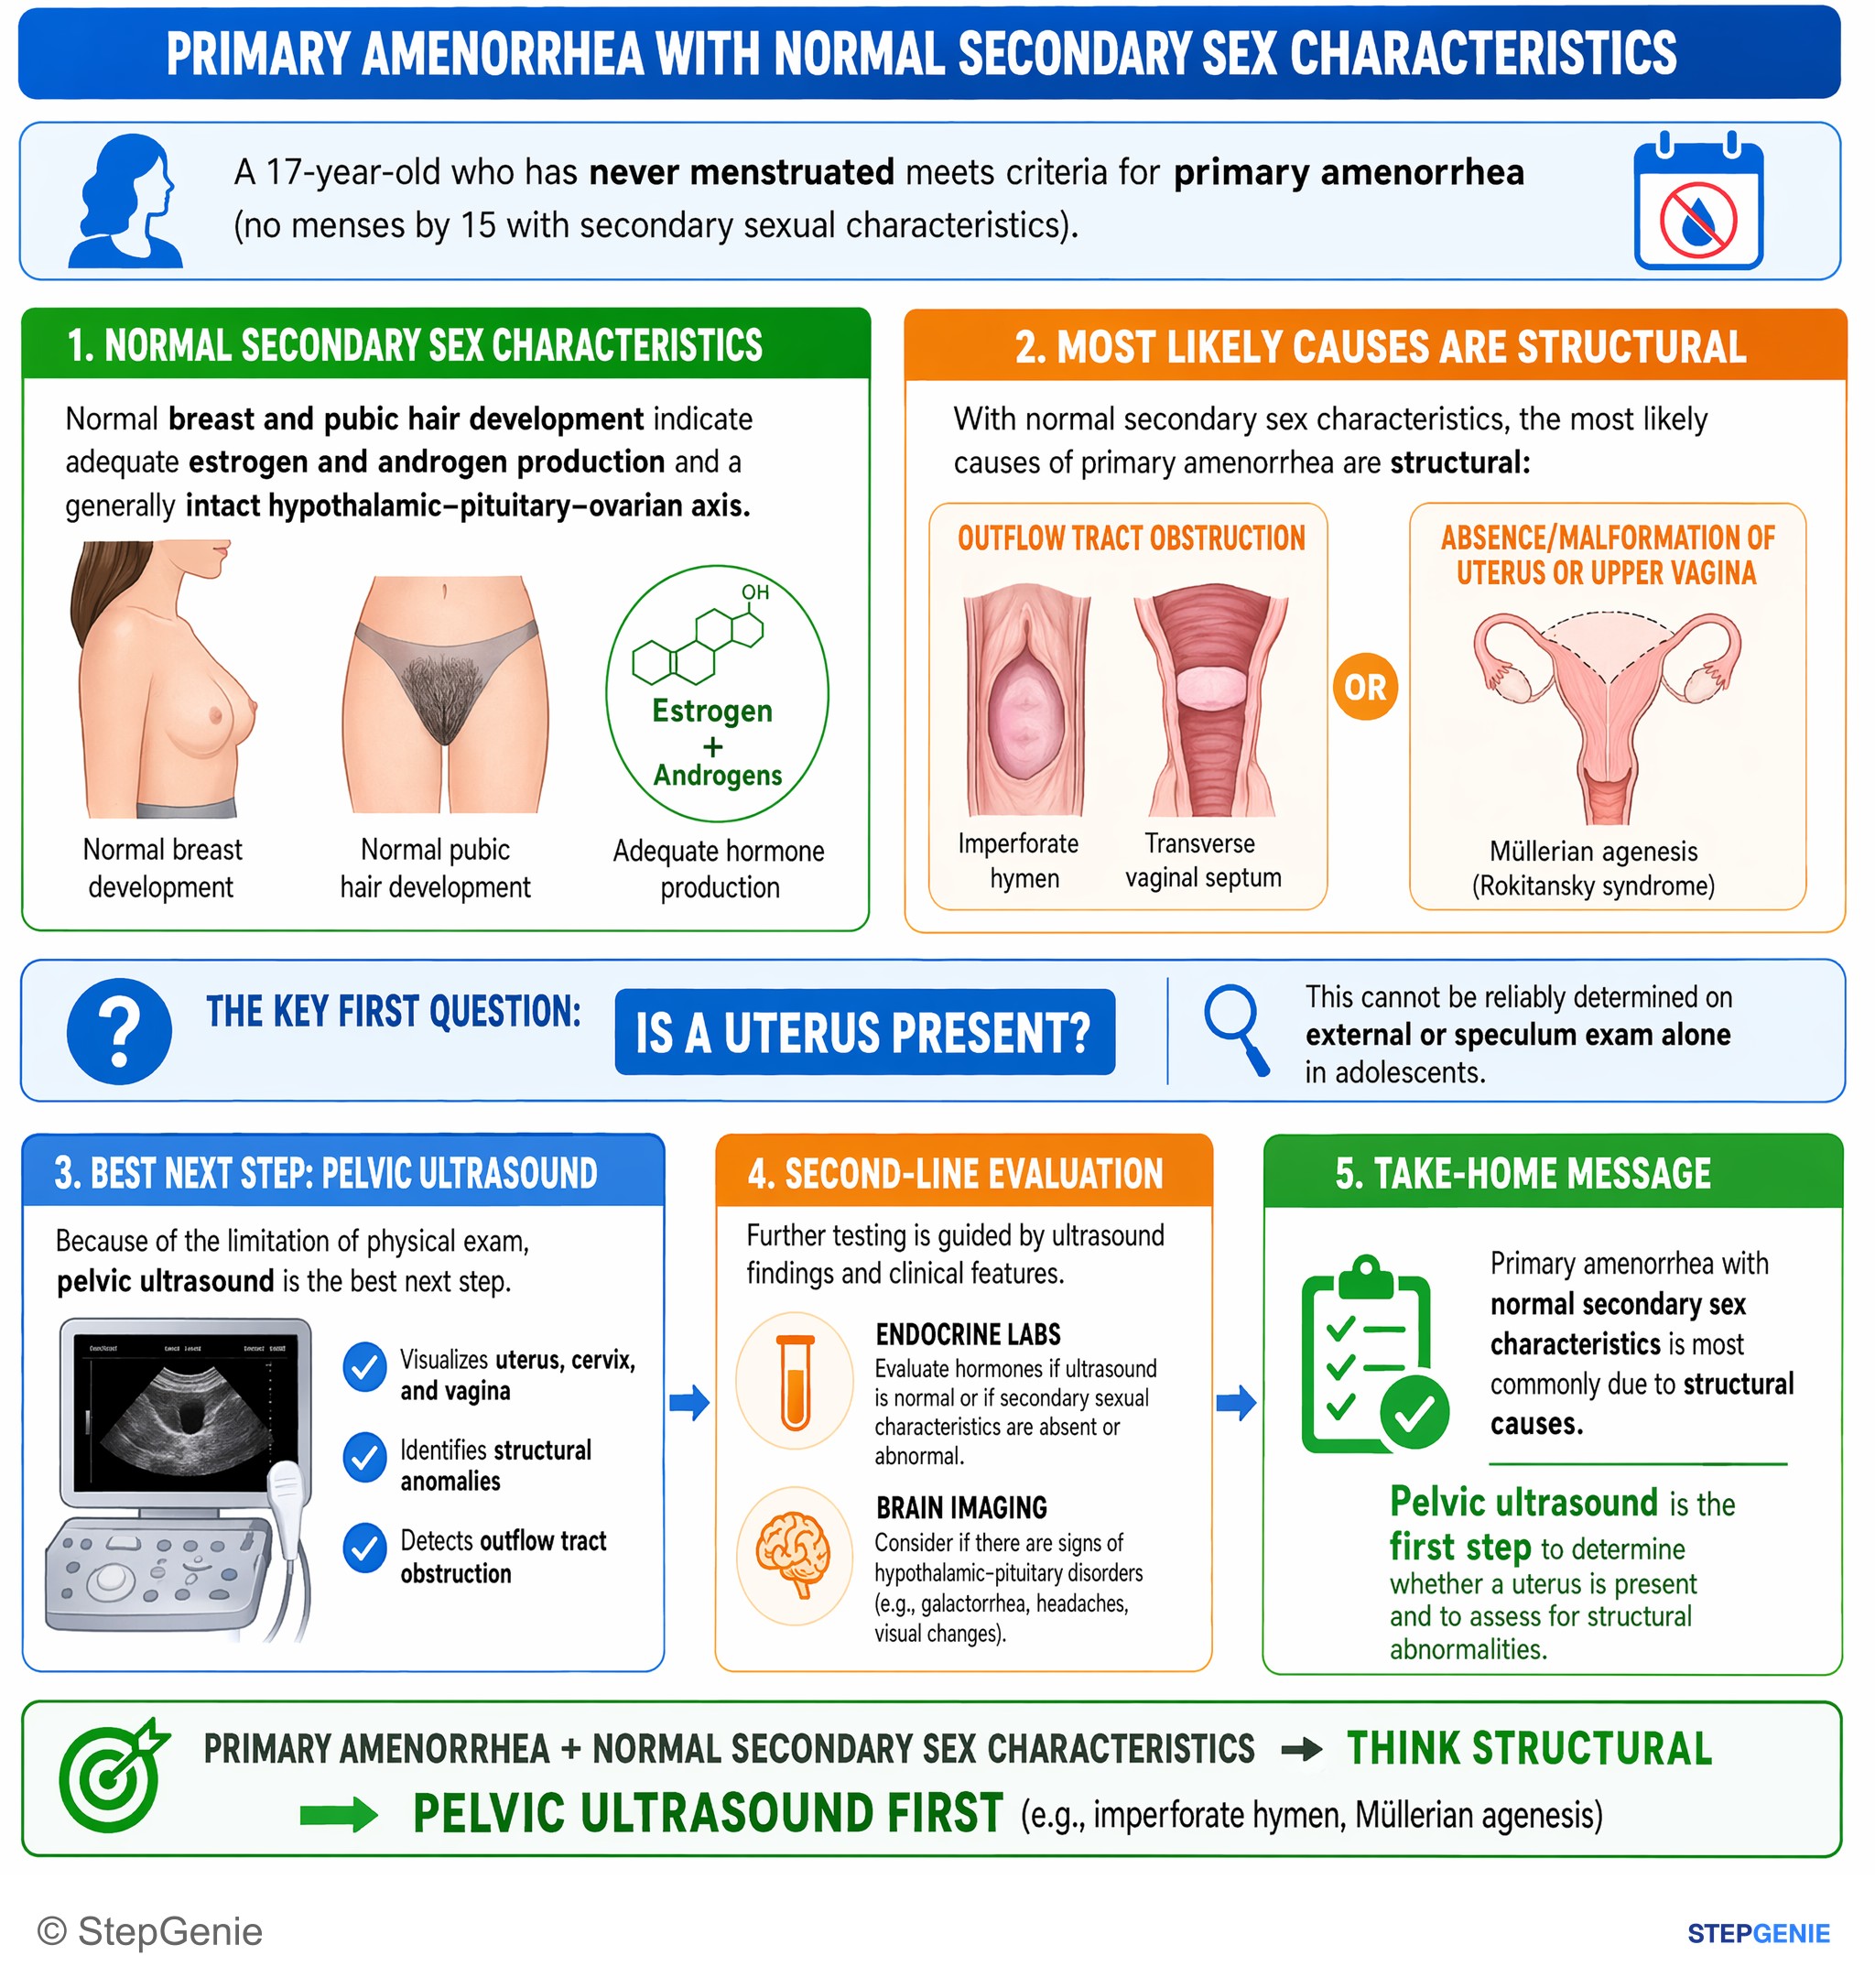
Primary amenorrhea with normal secondary sexual characteristics requires pelvic ultrasound first to assess for structural abnormalities…
USMLE Step 2Frequently Asked Questions
What is the first step in the workup of amenorrhea?
The first step is a pregnancy test, in both primary and secondary amenorrhea, because pregnancy is the most common cause and ovulation can occur before a first period. A serum hCG may be preferred if a urine test could be falsely negative. Next come a history and examination, then FSH, estradiol, prolactin and TSH, with a pelvic ultrasound to confirm the uterus and assess the endometrial lining.
What is the workup flowchart for primary amenorrhea?
Evaluate when there are no menses by 15 with normal breast development, or by 13 without breast development. After a negative pregnancy test, examine the patient and confirm the uterus with ultrasound. If it is absent, a karyotype and testosterone separate Müllerian agenesis from androgen insensitivity. If it is present, measure FSH: a high FSH needs a karyotype for Turner or Swyer syndrome, while a low FSH without breast development suggests constitutional delay, Kallmann syndrome or a central cause.
What labs should be ordered for secondary amenorrhea?
After a negative pregnancy test, order FSH, estradiol, prolactin and TSH; LH and AMH are optional. Add total and free testosterone, DHEAS and a morning 17-hydroxyprogesterone if there is hirsutism, acne or virilization. A high FSH with low estradiol suggests primary ovarian insufficiency, a low or normal FSH with low estradiol a hypothalamic or pituitary cause, and normal values with androgen excess polycystic ovary syndrome. A pelvic ultrasound early in the workup also helps.
Is the progestin challenge test still used for amenorrhea?
It is now optional. The American Society for Reproductive Medicine's 2024 committee opinion lists it among optional tests, warns that false positive and false negative results occur, and says other approaches may give a faster, more accurate diagnosis. A withdrawal bleed shows estrogen and an open outflow tract, pointing to anovulation such as PCOS. No bleed means low estrogen or a scarred or blocked uterus, which an estrogen-progestin challenge or hysteroscopy can separate.
How do you tell MRKH syndrome from complete androgen insensitivity syndrome?
Both cause primary amenorrhea with breast development and no uterus. MRKH (Müllerian agenesis) is 46,XX with normal ovaries, normal pubic and axillary hair and testosterone in the female range, and kidney anomalies are common. Complete androgen insensitivity is 46,XY with testes, sometimes felt in the groin, sparse or absent pubic and axillary hair and testosterone in the normal male range or higher. A serum testosterone and a karyotype settle the question.
What FSH level indicates primary ovarian insufficiency?
The 2024 international guideline diagnoses primary ovarian insufficiency when a woman under 40 has at least 4 months of absent or irregular cycles and an FSH above 25 IU/L. A single elevated FSH is enough; repeat it after 4 to 6 weeks only if the picture is unclear. Estradiol and AMH are not used alone for diagnosis. A karyotype and FMR1 premutation testing are recommended for every woman whose ovarian insufficiency is not iatrogenic.