Uterine fibroids (leiomyomas) are one of those Step topics that feel “obvious”… until a vignette forces you to choose between five very plausible answers. The trick isn’t just knowing what fibroids are—it’s recognizing which detail in the stem points to which diagnosis, and why every distractor is wrong for this patient.
The Vignette (Q-bank style)
A 38-year-old G2P2 presents with 6 months of heavy menstrual bleeding and increasing fatigue. Her periods are regular but very heavy, requiring changing pads every 1–2 hours on the first two days. She also reports pelvic pressure and urinary frequency. No fever or vaginal discharge. She is not using hormonal contraception.
Vitals are normal. Exam shows pale conjunctiva and an irregularly enlarged, firm uterus on bimanual exam. Pregnancy test is negative. CBC shows hemoglobin 9.2 g/dL with microcytosis.
Which is the most likely diagnosis?
A. Adenomyosis
B. Endometrial carcinoma
C. Endometriosis
D. Leiomyoma (uterine fibroids)
E. Uterine atony
The Correct Answer: D. Leiomyoma (Uterine Fibroids)
Why this is the best answer
The stem is screaming fibroids:
- Heavy menstrual bleeding (HMB) → classically due to submucosal fibroids distorting the endometrial cavity
- Pelvic pressure + urinary frequency → “bulk symptoms” from an enlarged uterus pressing on bladder
- Irregularly enlarged, firm uterus on exam → classic physical finding
- Microcytic anemia → chronic blood loss anemia from menorrhagia
High-yield fibroid facts (Step 1 + Step 2)
What they are
- Benign smooth muscle tumors of the myometrium
- Estrogen-sensitive → grow during reproductive years, may enlarge in pregnancy, often regress after menopause
Risk & associations
- More common in Black patients
- Often present with HMB, infertility, recurrent pregnancy loss (esp. submucosal)
Symptoms by location (high yield)
| Location | Key feature | What it causes |
|---|---|---|
| Submucosal | Distorts endometrial cavity | Heavy bleeding, infertility |
| Intramural | Within uterine wall | Enlarged uterus, bleeding |
| Subserosal | Projects outward | Bulk symptoms (pressure, urinary frequency, constipation) |
Diagnosis
- First-line imaging: transvaginal ultrasound
- Saline infusion sonohysterography (SIS) can better define cavity distortion if infertility/HMB is a focus
Management (board-style framework)
- Asymptomatic: observe
- HMB: NSAIDs, combined OCPs, levonorgestrel IUD, tranexamic acid
- Shrink fibroids: GnRH agonist (e.g., leuprolide) pre-op; (mechanism: downregulates GnRH receptors → ↓ LH/FSH → hypoestrogen state)
- Definitive: hysterectomy (if no fertility desire)
- Fertility-sparing: myomectomy (especially submucosal/intramural impacting cavity)
Now, Why Each Distractor Is Wrong (and how they try to trick you)
A. Adenomyosis
Why you might pick it: heavy bleeding + enlarged uterus.
Why it’s wrong here:
- Adenomyosis is endometrial glands/stroma within the myometrium → classically:
- Heavy menstrual bleeding + severe dysmenorrhea
- Uniformly enlarged, boggy uterus (not irregular/firm)
- This patient’s uterus is irregularly enlarged and firm, and the stem emphasizes pressure/urinary frequency (bulk symptoms), which fits fibroids better.
Buzzphrase contrast
- Adenomyosis: “boggy, uniformly enlarged” + dysmenorrhea
- Fibroids: “firm, irregularly enlarged” + bulk symptoms
B. Endometrial carcinoma
Why you might pick it: abnormal uterine bleeding.
Why it’s wrong here:
- The highest-yield presentation is postmenopausal bleeding (or irregular intermenstrual bleeding in older patients).
- This patient is 38 with regular cycles and a uterus exam consistent with structural masses.
When you should worry about it (Step 2 trigger list):
- Age ≥45 with abnormal uterine bleeding → endometrial biopsy (often tested)
- Any age with AUB + risk factors:
- Unopposed estrogen (obesity, chronic anovulation/PCOS, estrogen therapy)
- Tamoxifen
- Early menarche, late menopause
- Lynch syndrome
Key takeaway: In a reproductive-age patient with cyclic, regular heavy bleeding + enlarged irregular uterus, fibroids beat carcinoma.
C. Endometriosis
Why you might pick it: common female reproductive condition; students love/overuse it.
Why it’s wrong here:
- Endometriosis classically causes:
- Dysmenorrhea
- Dyspareunia
- Infertility
- Pain often cyclic and can worsen premenstrually
- Exam may show tender nodules in posterior fornix/uterosacral ligaments or fixed retroverted uterus—not an irregularly enlarged firm uterus.
Classic pathology (Step 1):
- Ectopic endometrial glands/stroma
- “Chocolate cysts” (ovarian endometriomas)
- Hemosiderin-laden macrophages
Key takeaway: Endometriosis is a pain diagnosis; fibroids are a bleeding + bulk diagnosis.
E. Uterine atony
Why you might pick it: you saw “uterus” and “bleeding.”
Why it’s wrong here:
- Uterine atony is postpartum hemorrhage due to failure of uterine contraction after delivery.
- This patient is not postpartum; she has chronic heavy menses with iron-deficiency anemia.
Postpartum hemorrhage high yield
- Uterine atony = most common cause
- “Boggy, enlarged uterus” after delivery → treat with:
- Bimanual uterine massage
- Uterotonics (oxytocin; methylergonovine contraindicated in HTN; carboprost contraindicated in asthma)
Key takeaway: If the stem isn’t postpartum (or post-abortion), uterine atony shouldn’t be on your short list.
USMLE-Style “Clue Table”: Fibroids vs Common Look-Alikes
| Condition | Bleeding pattern | Pain | Uterus on exam | Other clues |
|---|---|---|---|---|
| Leiomyoma (fibroids) | Heavy, regular menses (often) | Variable | Firm, irregularly enlarged | Bulk symptoms (urinary frequency, constipation) |
| Adenomyosis | Heavy menses | Dysmenorrhea | Boggy, uniformly enlarged | Multiparity; symptoms improve after menopause |
| Endometriosis | Usually normal flow | Dysmenorrhea, dyspareunia | Often normal; may be fixed/tender | Infertility; endometrioma |
| Endometrial cancer | Intermenstrual or postmenopausal bleeding | Usually not the main symptom | Often normal early | Unopposed estrogen risks; needs biopsy |
| Uterine atony | Acute postpartum hemorrhage | — | Boggy postpartum uterus | “4 T’s” of PPH |
Practical Test-Taking Moves (What the Q-bank wants)
-
Classify the bleeding
- Regular heavy menses → think structural (fibroids)
- Irregular bleeding/postmenopausal → think endometrial pathology (hyperplasia/cancer)
-
Respect the uterus exam
- Irregular + firm = fibroids
- Uniform + boggy = adenomyosis
-
Don’t ignore “bulk symptoms”
- Urinary frequency/constipation/pelvic pressure = fibroid mass effect until proven otherwise
-
Anemia pattern matters
- Chronic HMB → iron-deficiency anemia (microcytic)
Rapid-Fire High-Yield Pearls
- Fibroids are benign; malignant transformation to leiomyosarcoma is rare (and not reliably predicted by growth rate).
- Submucosal fibroids are most associated with heavy bleeding and infertility.
- First-line imaging: transvaginal ultrasound.
- If age ≥45 with AUB, the test often pivots to: endometrial biopsy (even if fibroids are present).
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
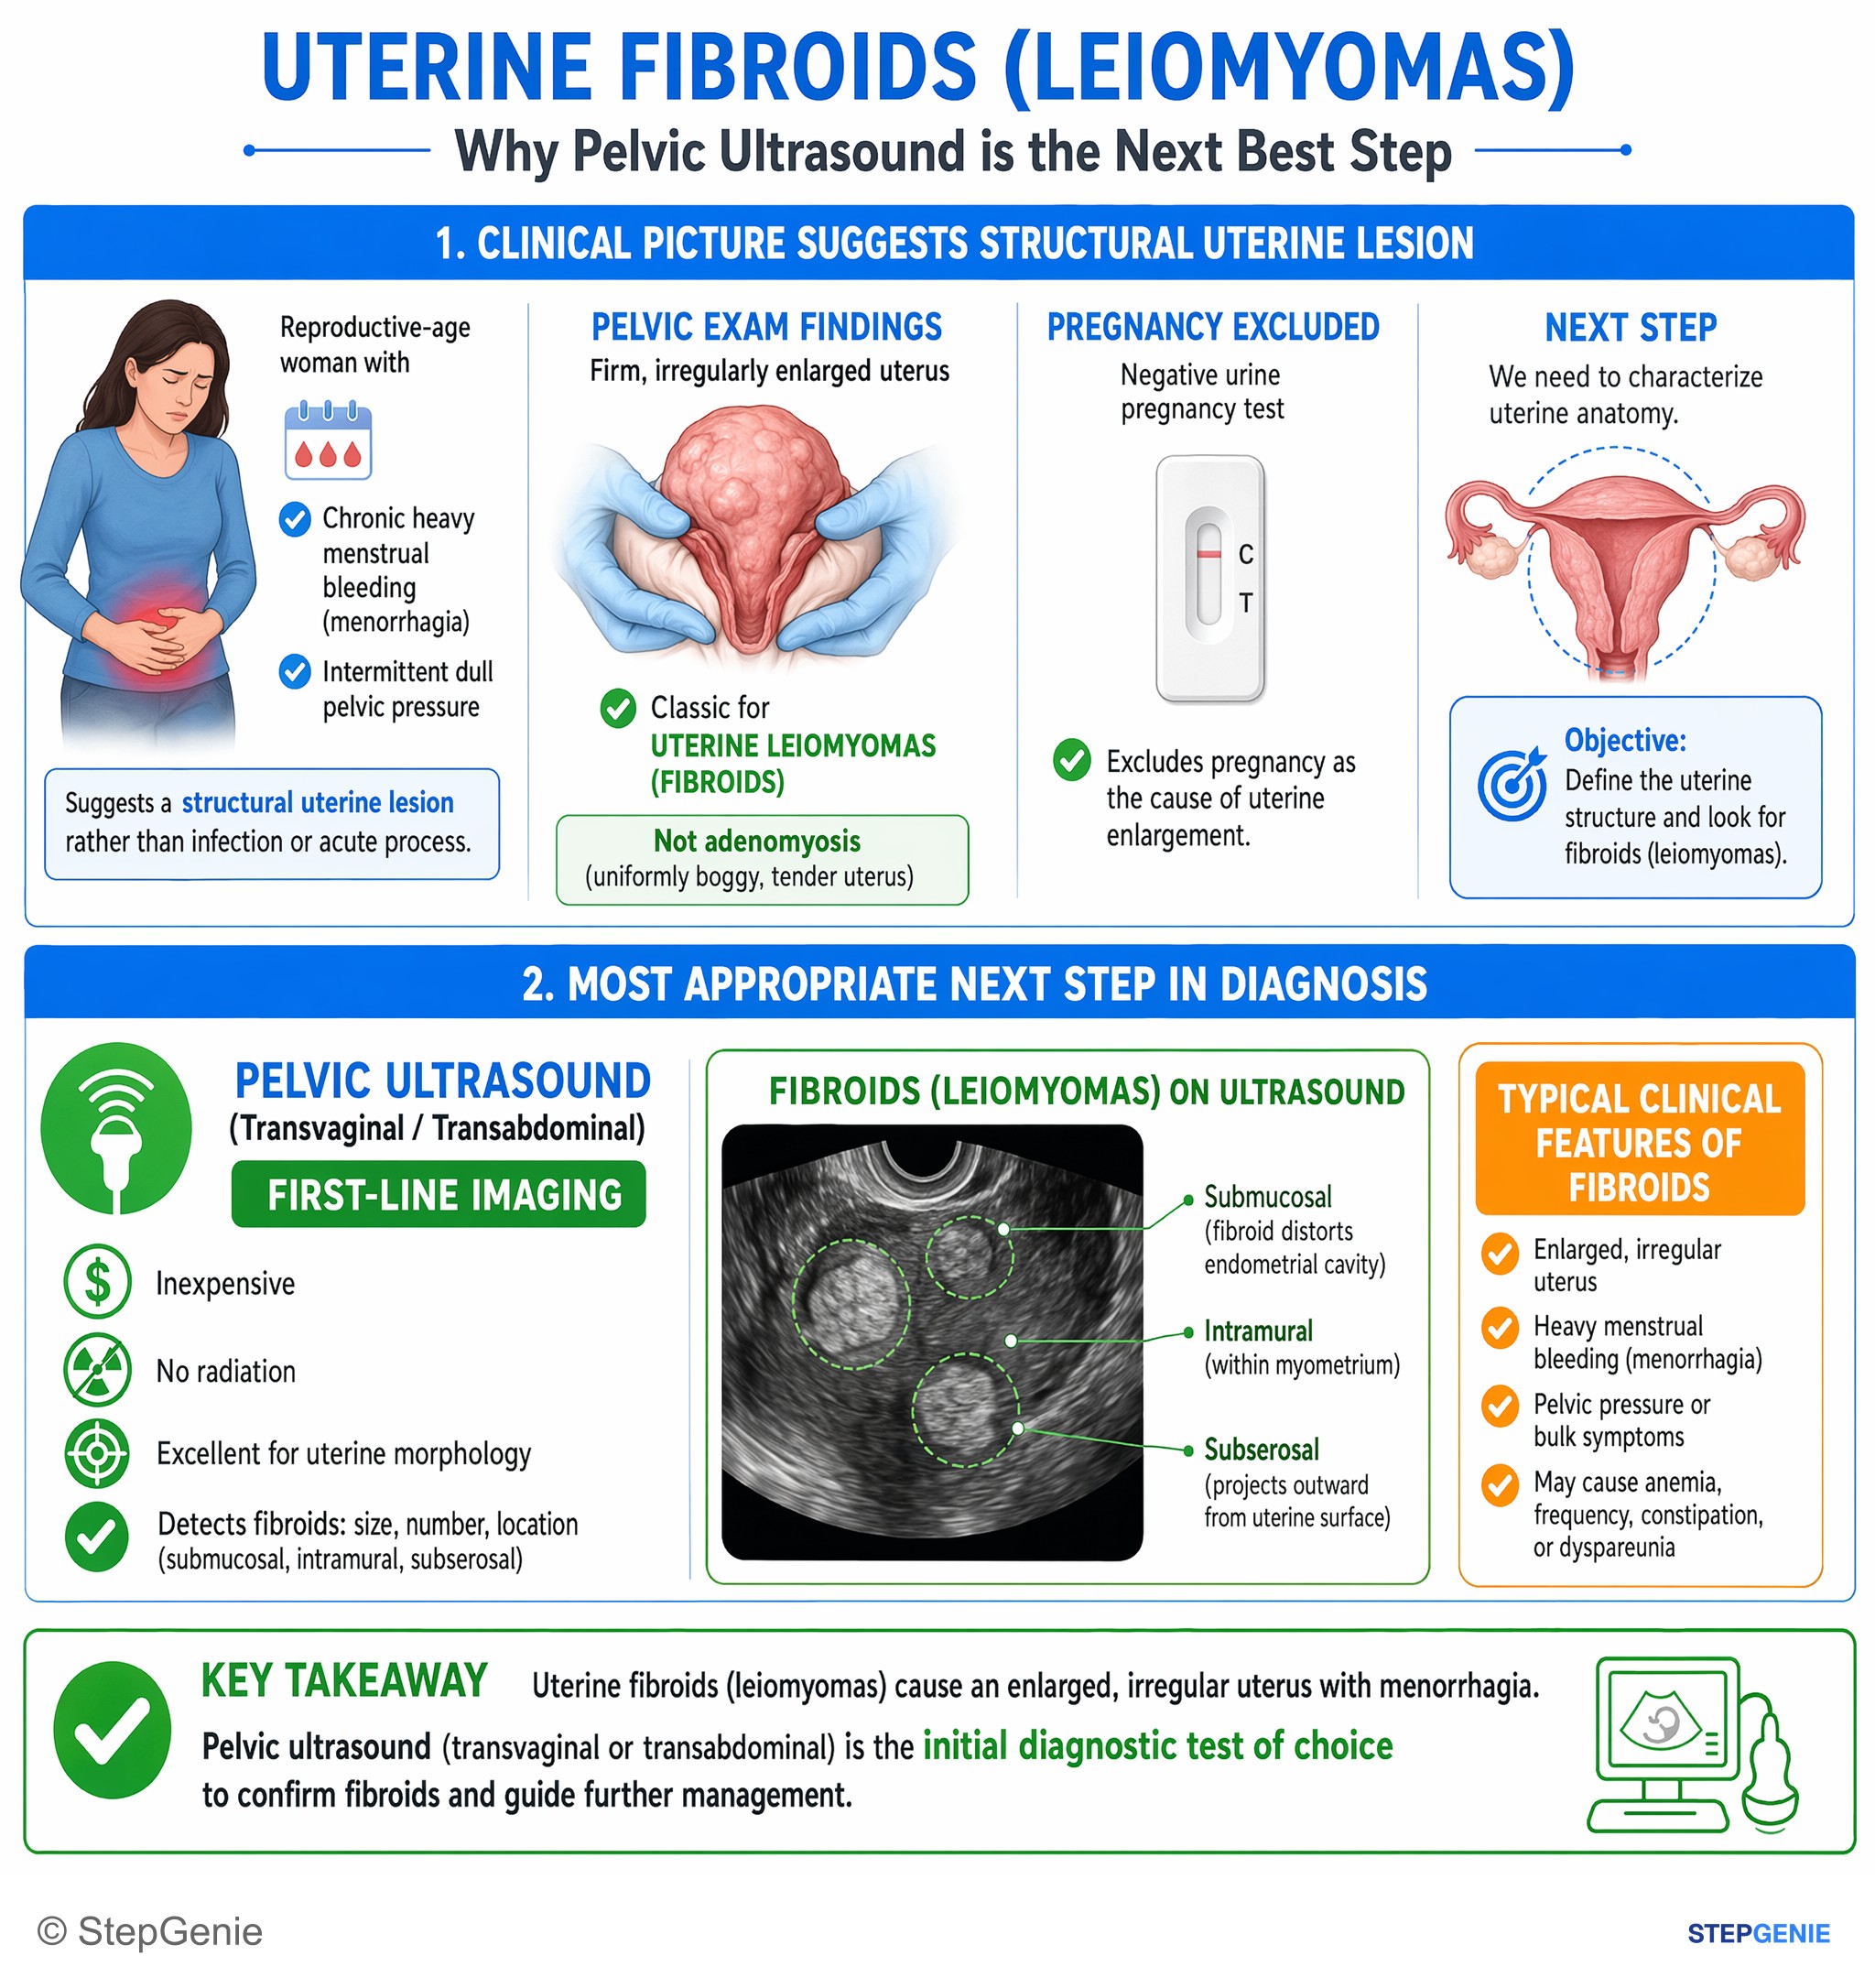
Uterine fibroids (leiomyomas) cause enlarged, irregular uterus with menorrhagia; pelvic ultrasound is the initial diagnostic test of choice.
USMLE Step 2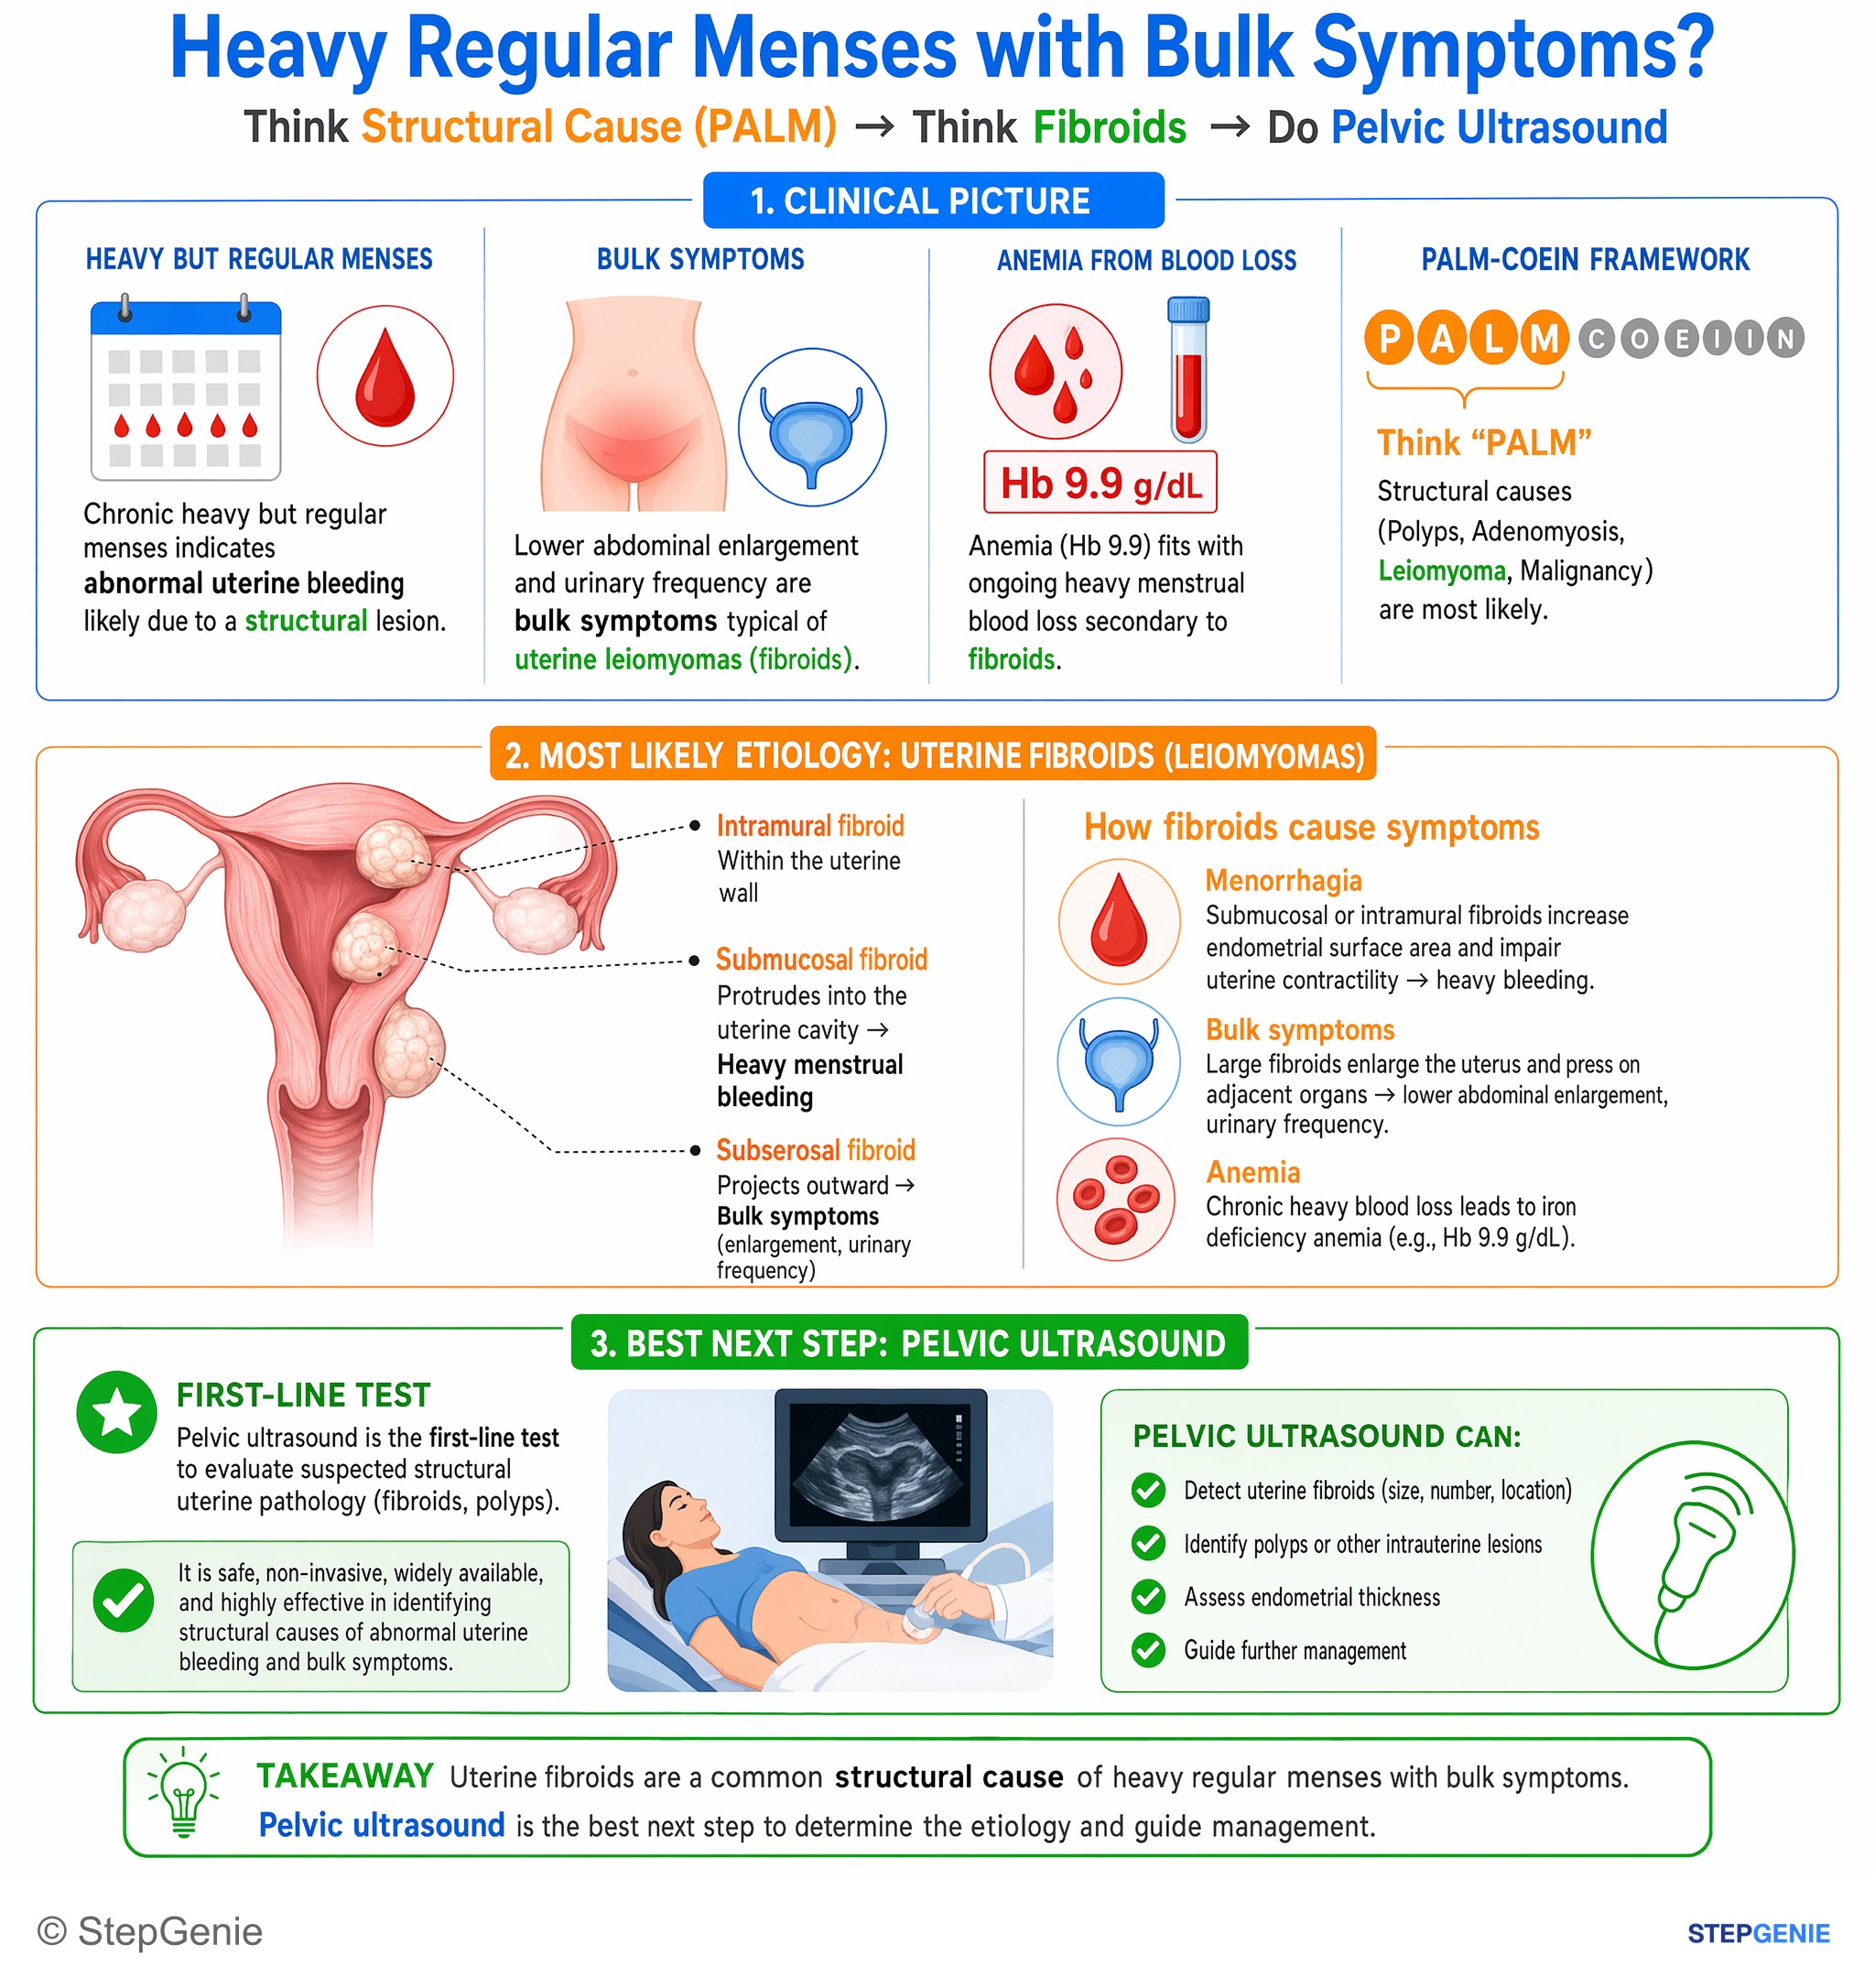
Uterine fibroids causing menorrhagia and bulk symptoms → first-line evaluation is pelvic ultrasound to identify structural uterine…
USMLE Step 2Frequently Asked Questions
How do you tell uterine fibroids from adenomyosis on exam and symptoms?
Uterine fibroids are suggested by a firm, irregularly enlarged uterus plus bulk symptoms such as pelvic pressure or urinary frequency. Adenomyosis more classically causes heavy menstrual bleeding with severe dysmenorrhea and a uniformly enlarged, boggy uterus. When the stem emphasizes pressure symptoms and an irregular firm uterine contour, fibroids fit better than adenomyosis.
Why do uterine fibroids cause heavy menstrual bleeding and urinary frequency?
Fibroids cause heavy menstrual bleeding when submucosal lesions distort the endometrial cavity, and they cause urinary frequency when the enlarged uterus creates bulk pressure on the bladder. Different fibroid locations produce different clues: submucosal fibroids are linked to bleeding and infertility, intramural fibroids enlarge the uterus and can also bleed, and subserosal fibroids mainly cause pressure symptoms.
What is the first-line imaging test for suspected uterine fibroids?
The first-line imaging test for suspected uterine fibroids is transvaginal ultrasound. It is the initial study used to evaluate a patient with heavy bleeding, an enlarged uterus, or bulk symptoms suggestive of leiomyoma. If infertility or heavy menstrual bleeding raises concern for distortion of the uterine cavity, saline infusion sonohysterography can better define that cavity distortion.
What is the first-line treatment for heavy menstrual bleeding from uterine fibroids?
For heavy menstrual bleeding from uterine fibroids, initial medical options include NSAIDs, combined oral contraceptives, a levonorgestrel IUD, and tranexamic acid. Management depends on symptoms and fertility goals. Asymptomatic fibroids can be observed, GnRH agonists such as leuprolide can shrink fibroids preoperatively, hysterectomy is definitive if fertility is not desired, and myomectomy is fertility-sparing.
Why is endometriosis less likely than fibroids with heavy menses and an irregularly enlarged uterus?
Endometriosis is less likely because it is primarily a pain diagnosis, classically causing dysmenorrhea, dyspareunia, and infertility rather than bleeding with bulk symptoms. Exam findings in endometriosis may include tender nodules or a fixed retroverted uterus, not a firm irregularly enlarged uterus. Fibroids better explain heavy regular menses, chronic blood loss anemia, pelvic pressure, and urinary frequency.