HELLP syndrome is one of those “blink and you miss it” diagnoses on a Q-bank—because the vignette often looks like just preeclampsia, just hepatitis, or just thrombocytopenia. The key move is to recognize the pattern and then prove it by eliminating distractors using one or two discriminating clues (timing, labs, symptoms, and what should be abnormal but isn’t).
The Clinical Vignette (Typical Q-bank Style)
A 29-year-old G1P0 at 33 weeks presents with severe right upper quadrant/epigastric pain, nausea, and malaise. BP is 168/112 mm Hg. She has facial/hand edema and hyperreflexia. Labs show:
- Platelets: 72,000/µL
- AST/ALT: 220/180 U/L
- Total bilirubin: 2.4 mg/dL
- Peripheral smear: schistocytes
- Urine protein: 3+
Question stem twist: “What is the most likely diagnosis?” or “Most appropriate next step in management?” or “Underlying pathophysiology?”
Correct Answer: HELLP Syndrome
What it stands for
Hemolysis
Elevated Liver enzymes
Low Platelets
Why this vignette screams HELLP
- Third trimester (or postpartum) + severe preeclampsia features
- RUQ/epigastric pain = liver capsule distention from hepatic swelling/hemorrhage
- Hemolysis evidence: schistocytes, ↑ bilirubin, ↑ LDH (often provided)
- Thrombocytopenia (often <100k)
- Transaminitis (AST/ALT often in the hundreds)
High-yield pathophysiology (Step-friendly)
HELLP is a severe variant of preeclampsia driven by abnormal placentation → systemic endothelial dysfunction:
- Placental ischemia → antiangiogenic factors (classically ↑ sFlt-1, ↓ VEGF/PlGF)
- Endothelial injury → platelet activation + microthrombi
- Microangiopathic hemolytic anemia (MAHA) → schistocytes, ↑ LDH, ↑ indirect bilirubin
- Hepatic periportal necrosis/hemorrhage → RUQ pain + ↑ AST/ALT
Management (very testable)
Definitive treatment is delivery.
Stabilize first, then deliver:
- Magnesium sulfate for seizure prophylaxis (even without seizures)
- Antihypertensives (IV labetalol, IV hydralazine, or oral nifedipine) if severe-range BP
- Delivery if:
- ≥34 weeks or
- maternal/fetal instability (often true in HELLP regardless of gestational age)
The “Why Every Answer Choice Matters” Distractor Breakdown
Below are common wrong answers and the specific clues that rule them out.
Quick Compare Table (High Yield)
| Condition (Common Distractor) | Key Clue(s) That Fit | Key Clue(s) That Don’t Fit HELLP Vignette |
|---|---|---|
| Acute fatty liver of pregnancy | 3rd trimester, nausea/vomiting, abdominal pain | Hypoglycemia, encephalopathy, ↑↑ PT/INR more prominent; hemolysis/schistocytes less classic |
| Thrombotic thrombocytopenic purpura (TTP) | MAHA + thrombocytopenia | Often no HTN/proteinuria; neuro symptoms prominent; can occur outside pregnancy; ADAMTS13 issue |
| Hemolytic uremic syndrome (HUS) | MAHA + thrombocytopenia | Renal failure predominates; often post-diarrheal (typical HUS); HTN/proteinuria not the “preeclampsia picture” |
| DIC | Low platelets, bleeding | Prolonged PT/PTT, ↓ fibrinogen, ↑ D-dimer; hemorrhage/oozing; HELLP can trigger DIC but isn’t defined by coag factor consumption |
| Viral hepatitis | RUQ pain, ↑ AST/ALT | Transaminases often very high (often >1000), platelets not necessarily low, no MAHA; BP/proteinuria not explained |
| Acute pancreatitis | Epigastric pain | Would expect ↑ lipase/amylase; not MAHA or severe HTN/proteinuria |
| ITP | Isolated thrombocytopenia | No hemolysis, normal LFTs, no severe HTN/proteinuria |
| Cholangitis/cholecystitis | RUQ pain, fever | Fever + leukocytosis, ultrasound findings; does not explain MAHA + low platelets + preeclampsia signs |
Distractor 1: Acute Fatty Liver of Pregnancy (AFLP)
Why it’s tempting: Third trimester + abdominal pain + elevated LFTs + systemic illness.
How to distinguish from HELLP (classic Step separators):
- AFLP often has hypoglycemia (think impaired hepatic metabolism)
- AFLP tends to have more prominent coagulopathy (↑ PT/INR) and encephalopathy
- Platelets can be low, but MAHA (schistocytes/LDH spike) is more HELLP-coded
Memory hook:
- AFLP = liver failure vibes (glucose down, INR up, confusion).
Distractor 2: TTP (Thrombotic Thrombocytopenic Purpura)
Why it’s tempting: MAHA + thrombocytopenia can look identical on a smear.
What pushes you away from TTP here:
- HELLP usually has severe-range HTN + proteinuria (preeclampsia umbrella)
- TTP classically emphasizes neurologic symptoms (confusion, headache, seizure) and fever
- TTP can occur in pregnancy, but the vignette’s OB context (33 weeks + preeclampsia signs) strongly favors HELLP
High-yield pearl:
- TTP = ADAMTS13 deficiency/inhibitor → large vWF multimers → platelet aggregation.
- Treatment: plasmapheresis (not delivery as the “fix,” though delivery may still be needed depending on context).
Distractor 3: HUS (Hemolytic Uremic Syndrome)
Why it’s tempting: Also MAHA + thrombocytopenia.
What should be louder in HUS:
- Acute kidney injury is front-and-center (↑ creatinine, oliguria)
- In classic (typical) HUS, history of bloody diarrhea from Shiga toxin (EHEC)
- Pregnancy-associated atypical HUS exists, but again: preeclampsia phenotype (HTN/proteinuria + RUQ pain + transaminitis) points to HELLP
Rule of thumb:
- HUS = kidneys; HELLP = liver + pregnancy HTN/proteinuria.
Distractor 4: DIC (Disseminated Intravascular Coagulation)
Why it’s tempting: Low platelets, sick pregnant patient, can happen with placental abruption/sepsis/HELLP.
How to rule out “primary DIC” as the diagnosis:
- DIC is defined by consumption of clotting factors → prolonged PT/PTT, low fibrinogen
- HELLP is primarily platelet activation + MAHA; PT/PTT can be normal unless severe/complicated
Test strategy:
If the question gives you normal PT/PTT and fibrinogen, DIC is unlikely.
Distractor 5: Viral Hepatitis
Why it’s tempting: RUQ pain + elevated liver enzymes.
Discriminators:
- Viral hepatitis often produces very high transaminases (commonly >1000 U/L)
- Doesn’t explain thrombocytopenia + schistocytes
- Doesn’t explain severe HTN + proteinuria
If they mention: sick contacts, travel, jaundice without MAHA/preeclampsia features → hepatitis climbs.
Distractor 6: ITP (Immune Thrombocytopenia)
Why it’s tempting: Pregnancy + low platelets.
What ITP should look like:
- Isolated thrombocytopenia
- Normal smear (no schistocytes)
- Normal LFTs
- No RUQ pain from hepatic injury, no severe HTN/proteinuria pattern
Step 1 immune angle:
ITP = IgG against platelet GPIIb/IIIa → splenic clearance; treat with steroids/IVIG if needed.
The Two Most Tested “Next Step” Answers
1) Seizure prophylaxis
Even without seizures, severe preeclampsia/HELLP → magnesium sulfate.
- Toxicity signs: loss of DTRs, respiratory depression
- Antidote: calcium gluconate
2) Definitive management
Delivery is definitive (especially ≥34 weeks or unstable).
Rapid-Fire High-Yield Facts (USMLE Gold)
- HELLP is a severe preeclampsia variant: expect HTN + proteinuria (though proteinuria may be variable in real life, USMLE often includes it).
- RUQ/epigastric pain is a red flag for hepatic involvement (capsular distention, hemorrhage).
- Schistocytes = MAHA, not immune thrombocytopenia.
- Complications: DIC, placental abruption, hepatic rupture, acute kidney injury, pulmonary edema.
- Can occur postpartum (don’t let delivery in the stem throw you off).
How to “Work Backward” From the Answer Choices
When you see a pregnant patient with thrombocytopenia + transaminitis, ask:
- Is there MAHA? (schistocytes, ↑ LDH, ↑ indirect bili) → HELLP/TTP/HUS
- Is there a preeclampsia phenotype? (HTN, proteinuria, edema, hyperreflexia) → HELLP
- Is there hypoglycemia/INR spike/encephalopathy? → AFLP
- Are coag factors being consumed? (PT/PTT up, fibrinogen down) → DIC
- Are transaminases in the thousands? → hepatitis/toxin/ischemic hepatitis
If you can answer those five questions, most Q-bank items become plug-and-play.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
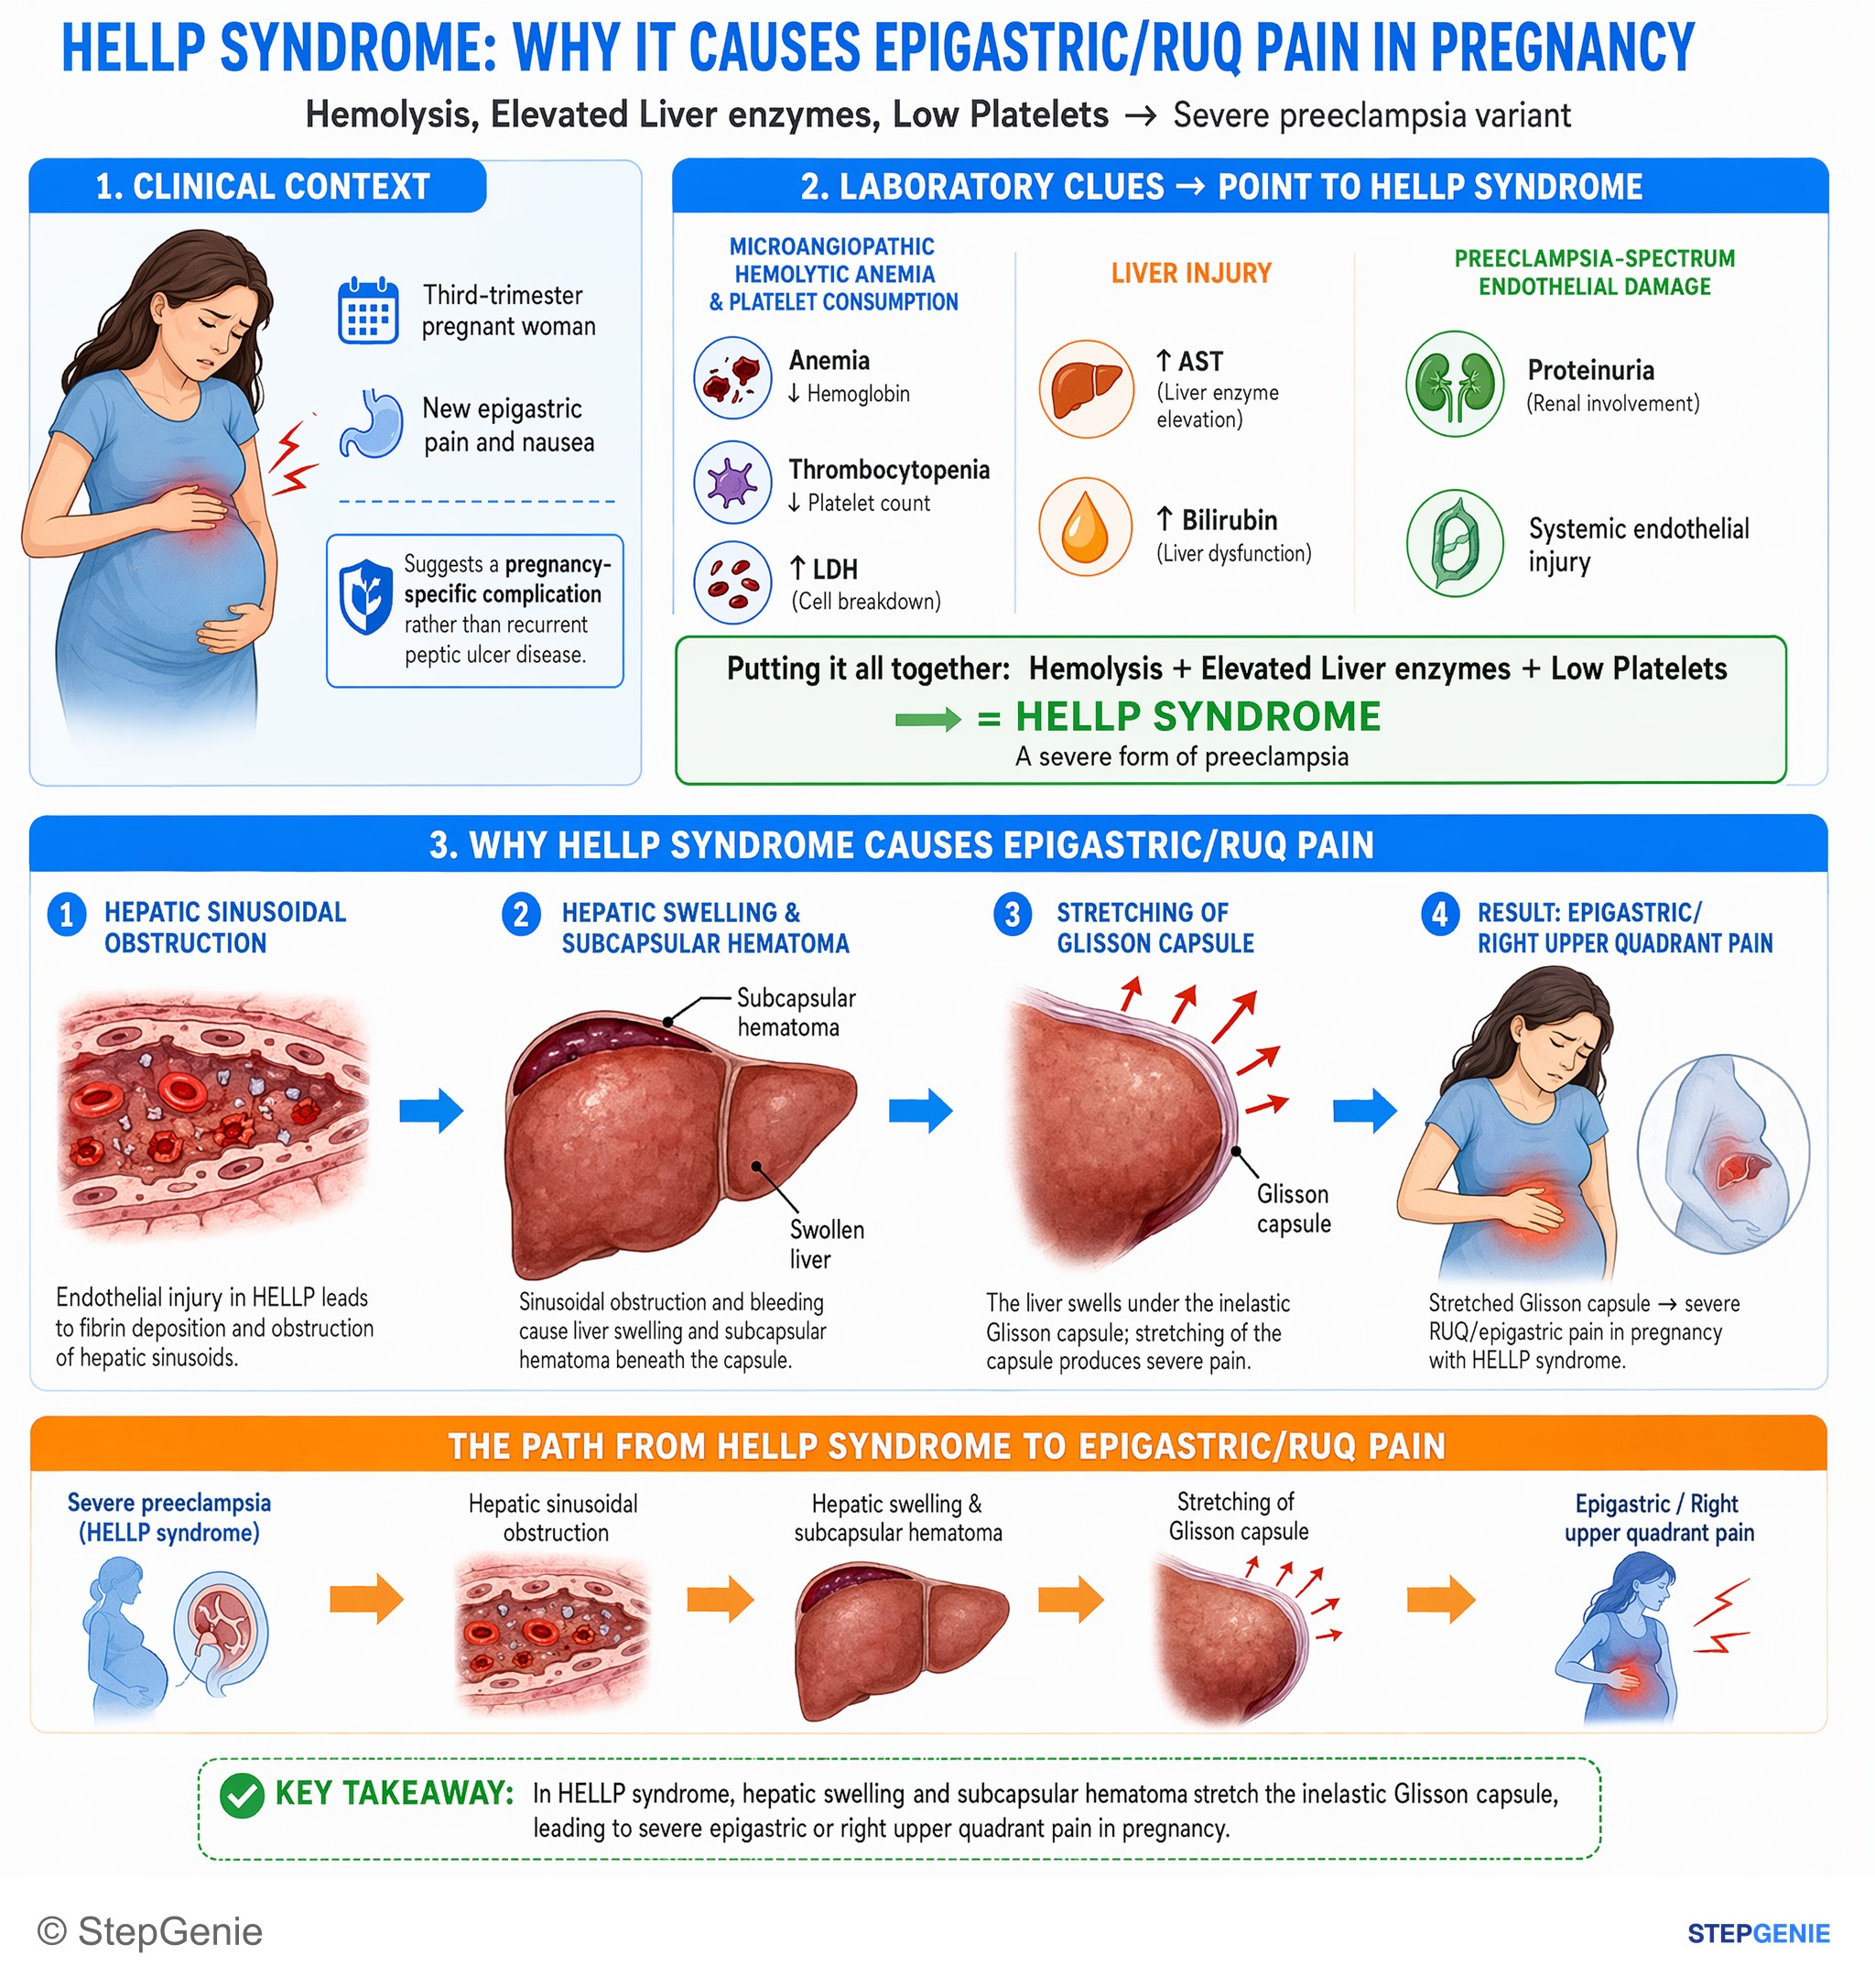
HELLP syndrome (severe preeclampsia variant) → hepatic swelling & subcapsular hematoma → stretching of Glisson capsule → epigastric/right…
USMLE Step 2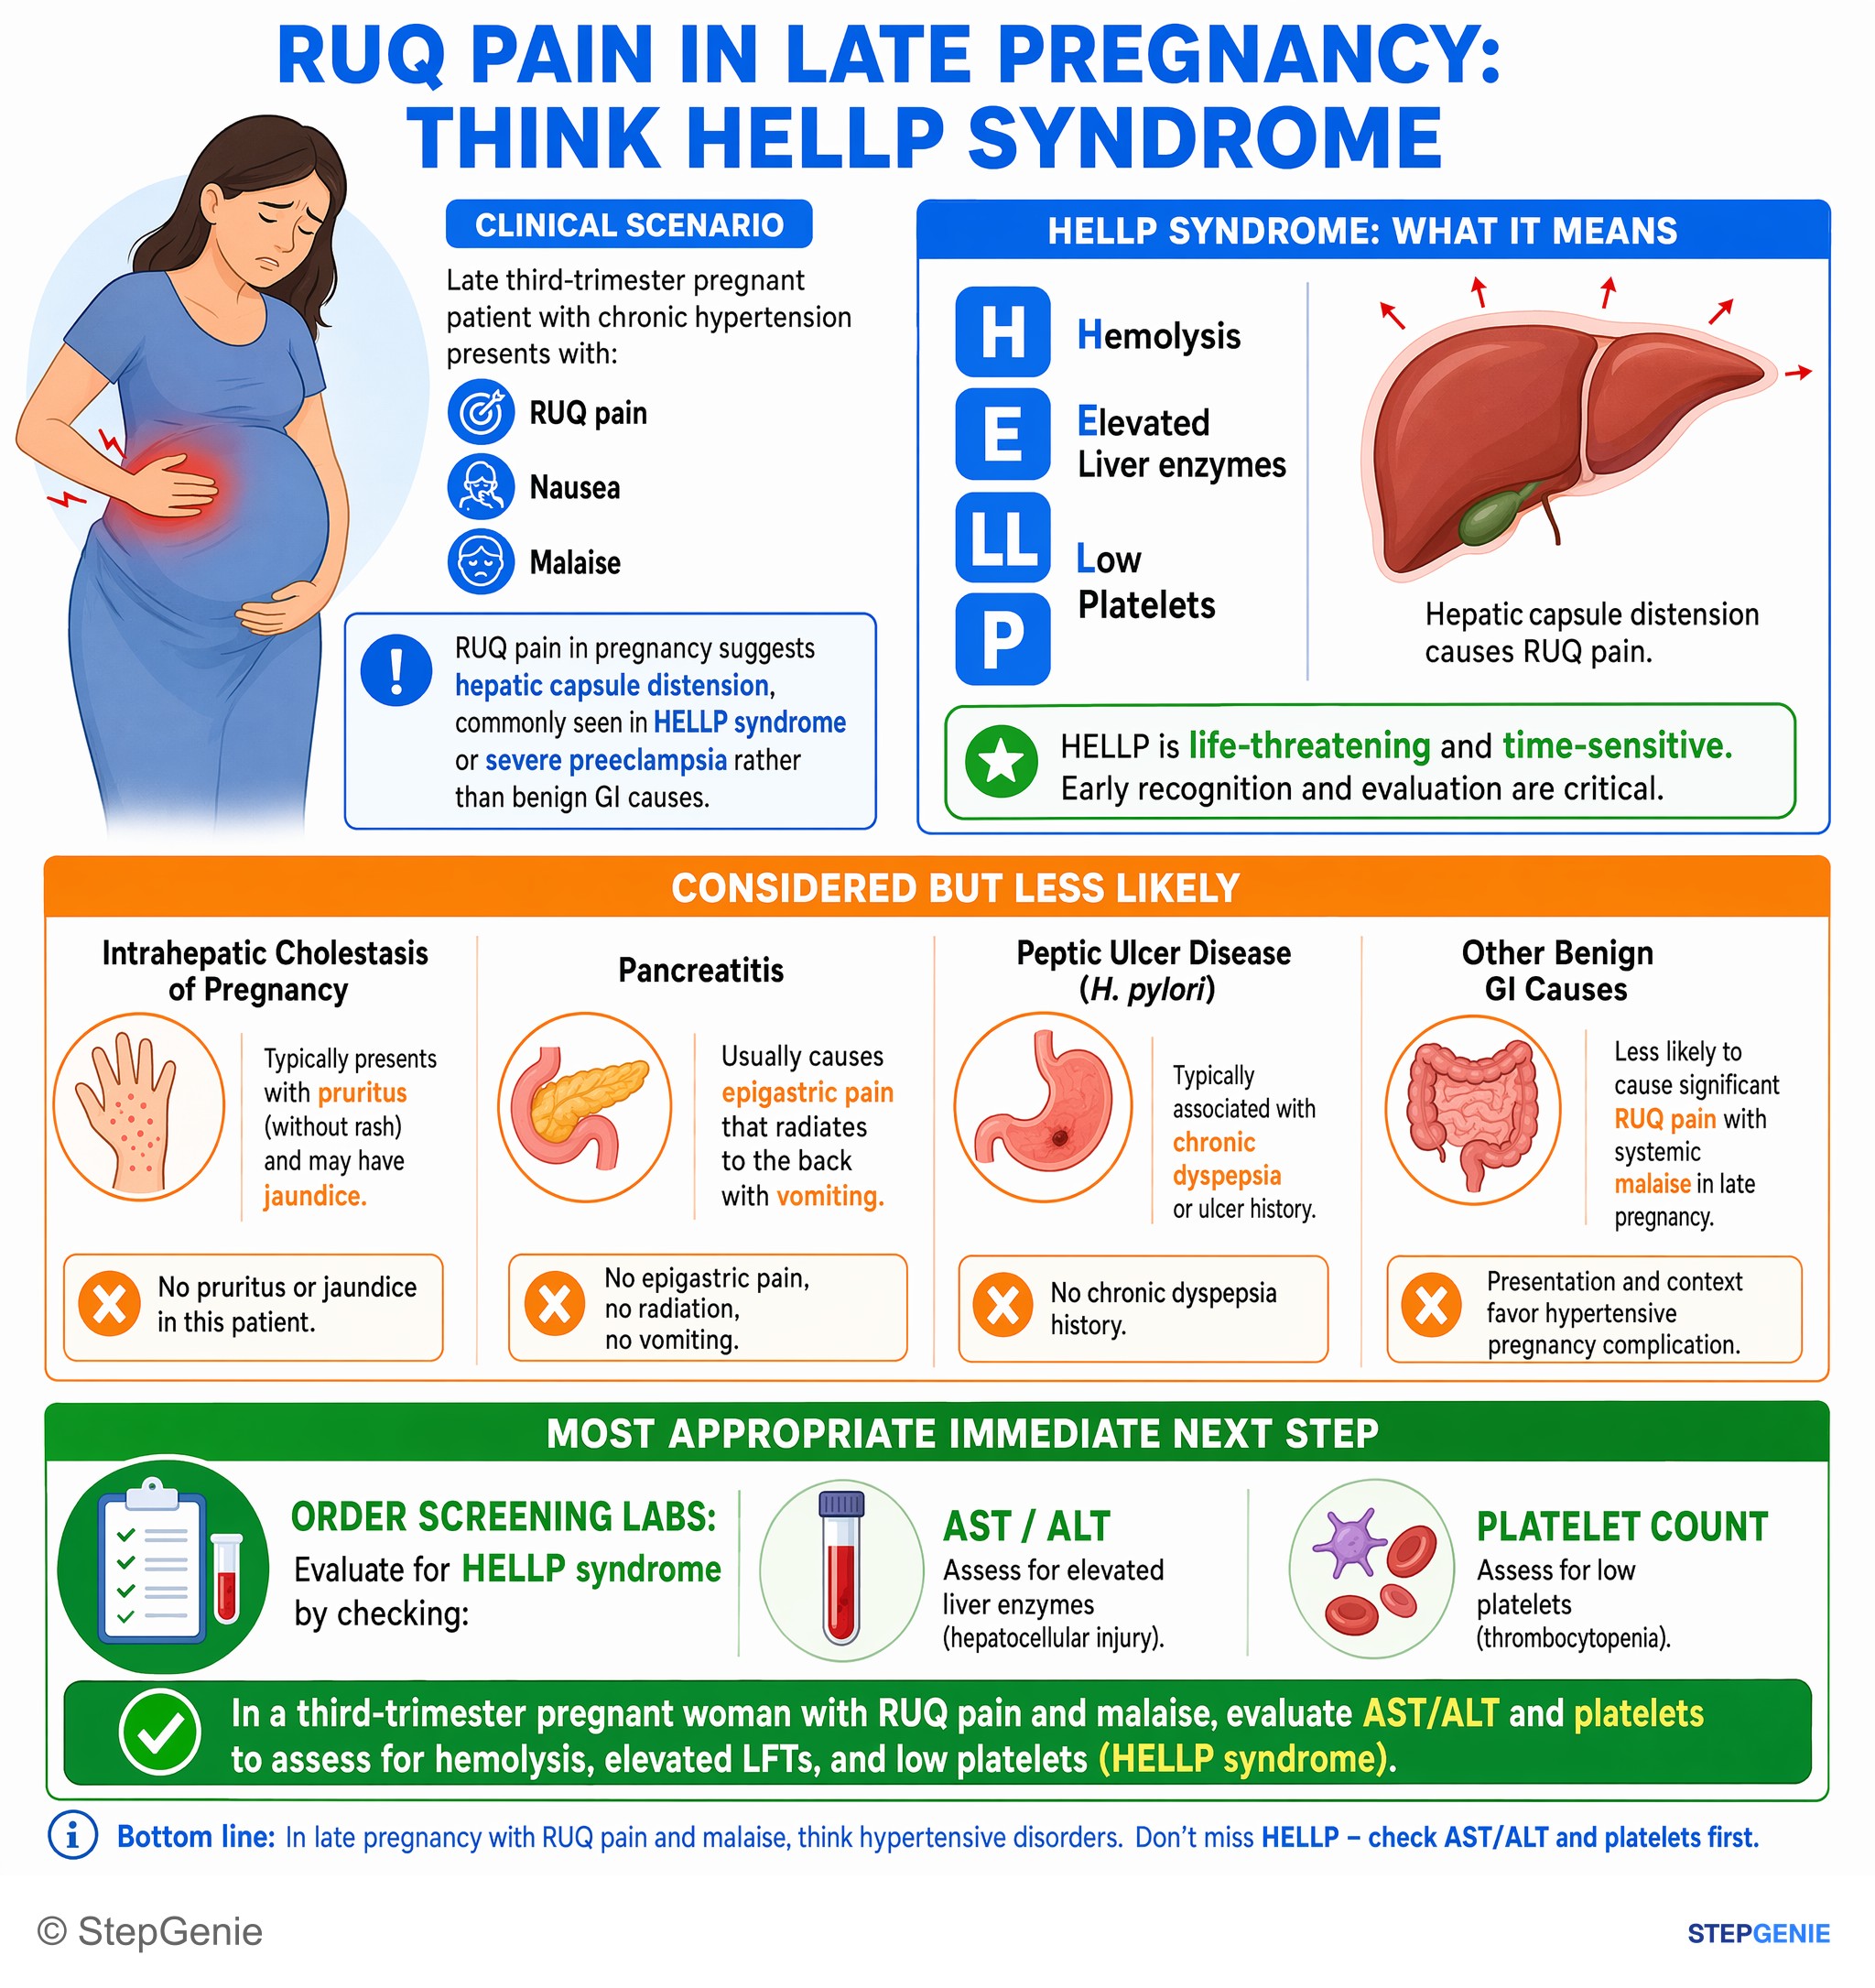
HELLP syndrome suspicion in third-trimester pregnant woman with RUQ pain and malaise → evaluate AST/ALT and platelets for hemolysis…
USMLE Step 2Frequently Asked Questions
How do you tell HELLP syndrome from severe preeclampsia on a question stem?
HELLP syndrome is identified by severe preeclampsia plus hemolysis, elevated liver enzymes, and low platelets. The clue pattern is third trimester or postpartum hypertension and proteinuria with severe right upper quadrant or epigastric pain, schistocytes on smear, bilirubin or LDH elevation, thrombocytopenia, and transaminitis. Severe preeclampsia alone does not explain the microangiopathic hemolysis and platelet drop that make HELLP distinct.
Why does HELLP syndrome cause right upper quadrant or epigastric pain?
HELLP causes right upper quadrant or epigastric pain because hepatic swelling and hemorrhage stretch the liver capsule. The underlying process is endothelial injury with microthrombi and hepatic periportal necrosis or hemorrhage. On exams, this pain becomes especially important when it appears in a pregnant patient with hypertension, proteinuria, elevated AST and ALT, and low platelets.
What is the underlying pathophysiology of HELLP syndrome?
HELLP syndrome is a severe variant of preeclampsia caused by abnormal placentation leading to systemic endothelial dysfunction. Placental ischemia promotes antiangiogenic signaling, which injures endothelium and triggers platelet activation and microthrombi. That produces microangiopathic hemolytic anemia with schistocytes and bilirubin or LDH elevation, while hepatic periportal necrosis and hemorrhage cause right upper quadrant pain and transaminitis.
What is the most appropriate management for HELLP syndrome?
The definitive treatment for HELLP syndrome is delivery after initial stabilization. Patients should first receive magnesium sulfate for seizure prophylaxis and antihypertensive therapy such as IV labetalol, IV hydralazine, or oral nifedipine if blood pressure is in the severe range. Delivery is indicated at 34 weeks or later, or earlier if there is maternal or fetal instability, which is often present in HELLP.
How do you differentiate HELLP syndrome from TTP, HUS, or acute fatty liver of pregnancy?
HELLP is favored when a third-trimester patient has the preeclampsia picture of severe hypertension, proteinuria, right upper quadrant pain, thrombocytopenia, hemolysis, and elevated liver enzymes. TTP leans toward neurologic symptoms and fever without the classic hypertension and proteinuria pattern. HUS makes renal failure more prominent, often with bloody diarrhea in typical cases. Acute fatty liver of pregnancy more often features hypoglycemia, encephalopathy, and a more prominent PT or INR elevation.