The menstrual cycle has two ovarian halves split by ovulation: a follicular phase, in which FSH grows a dominant follicle whose estradiol builds a proliferative endometrium, and a luteal phase, in which progesterone from the corpus luteum makes the endometrium secretory. Sustained high estradiol switches pituitary feedback from negative to positive and triggers the LH surge, and ovulation follows about a day and a half after the surge begins. The follicular phase varies in length while the luteal phase stays nearly constant at about 14 days, so ovulation occurs about 14 days before the next period, not always on day 14. Progesterone raises basal body temperature by about 0.5°C, and progesterone withdrawal when the corpus luteum regresses starts menses.
The 28-day cycle at a glance
| Days (28-day model) | Ovary | Endometrium | FSH | LH | Estradiol | Progesterone |
|---|---|---|---|---|---|---|
| 1–5 | Early follicular: FSH recruits a cohort of follicles | Menstrual: functional layer sheds | Slightly raised | Low; pulses every 60–90 min | Low | Low |
| 6–12 | Mid to late follicular: one dominant follicle, 18–20 mm before ovulation | Proliferative | Falling (estradiol and inhibin B feedback) | Low; pulses speed up | Rising steeply | Low |
| 13–14 | Ovulatory | Late proliferative | Smaller midcycle rise | Surge, about 10-fold | Peaks, then drops after ovulation | Starts to rise |
| 15–25 | Luteal: corpus luteum | Secretory | Low | Low; pulses slow to about every 3 h | Second, smaller mid-luteal rise | Peaks about 1 week after ovulation |
| 26–28 | Corpus luteum regresses (no hCG) | Ischemic, then shedding | Starts rising again | Low | Falls | Falls (withdrawal starts menses) |
Normal ranges (Merck): a cycle every 24–38 days (median 28), bleeding for 8 days or fewer, and blood loss under 80 mL (average about 30 mL).
Hypothalamus and pituitary: GnRH, FSH, LH and inhibin
- GnRH must be pulsatile. Rapid GnRH pulses favor LH-β transcription and slow pulses favor FSH-β. Continuous GnRH produces only a transient response and then suppression, which is why a depot GnRH agonist such as leuprolide causes an initial flare and then prolonged suppression of LH, FSH and ovarian steroids.
- Two-cell, two-gonadotropin model: LH → theca cells → androstenedione; FSH → granulosa cells → aromatase, which converts those androgens to estradiol.
- Negative feedback: through most of the cycle, estradiol stimulates LH and FSH synthesis but inhibits their secretion. Inhibin B from the growing follicles suppresses FSH but not LH. As FSH falls, the dominant follicle keeps growing while the rest of the cohort undergoes atresia.
- Inhibin A dominates the luteal phase. As the corpus luteum fails, its steroid output and inhibin A fall together, releasing FSH to recruit the next cohort (the luteal-follicular transition).
Estradiol positive feedback and the LH surge
- The dominant follicle's granulosa cells pour out estradiol.
- Once estradiol stays above about 200 pg/mL for about 50 hours (Endotext), feedback switches from negative to positive: the pituitary releases its stored LH as the LH surge, with a smaller FSH rise.
- The surge begins about 34–36 hours before ovulation (Endotext; StatPearls gives 36–44 hours), and ovulation follows about 10–12 hours after the LH peak. Home urine LH kits turn positive about 24–36 hours before ovulation (Merck).
- The LH surge:
- restarts meiosis I: the primary oocyte, arrested in prophase I since fetal life, becomes a secondary oocyte, which is ovulated and completes meiosis II only if fertilized
- activates enzymes that break down the follicle wall and release the oocyte
- starts luteinization, so progesterone begins rising around ovulation and the ruptured follicle becomes the corpus luteum
Because the follicular phase accounts for most of the variation in cycle length:
A 35-day cycle ovulates around day 21; a 24-day cycle around day 10.
Follicular vs luteal phase
| Feature | Follicular phase | Luteal phase |
|---|---|---|
| Length | Variable; explains most differences in cycle length | Nearly constant, about 14 days |
| Ovarian structure | Growing follicles, then one dominant follicle | Corpus luteum (becomes the corpus albicans if no pregnancy) |
| Main hormone | FSH early, estradiol late | Progesterone, plus estradiol and inhibin A |
| Inhibin | Inhibin B | Inhibin A |
| LH pulses | Every 60–90 min, faster before ovulation | Slower, about every 3 h mid-luteal |
| Endometrium | Proliferative | Secretory |
| Cervical mucus | Clear, copious, elastic (spinnbarkeit), ferning near ovulation | Thick, viscous, opaque; ferning minimal or absent |
| Basal body temperature | Lower | About 0.5°C higher |
Progesterone, basal body temperature and proving ovulation
- The corpus luteum secretes mainly progesterone, peaking at about 25 mg/day 6–8 days after ovulation (Merck), which is about day 21 of a 28-day cycle.
- Progesterone is thermogenic: basal body temperature rises about 0.5°C and stays up for the luteal phase. A temperature chart shows ovulation only after it happens and is often inaccurate.
- Serum progesterone ≥3 ng/mL about 1 week before the next expected period indicates that ovulation occurred (Merck). "Day 21 progesterone" is this rule applied to a 28-day cycle.
- Progesterone also thickens cervical mucus and converts the endometrium into a secretory, implantation-ready lining.
- If an embryo implants, hCG from the trophoblast keeps the corpus luteum alive, so progesterone stays high and menses do not come. After 9–10 weeks the placenta makes enough estrogen and progesterone itself.
Endometrial phases
| Phase | Timing | Driver | Histology and events |
|---|---|---|---|
| Menstrual | Days 1 to about 5 | Withdrawal of estradiol and progesterone | Spiral arterioles coil and constrict; the functional layer becomes ischemic, necroses and sheds; the basal layer stays. Endometrial prostaglandins contract the myometrium (cramps) |
| Proliferative | End of menses to ovulation (length varies) | Estradiol | Narrow, straight, tubular glands with mitoses; the basal layer regenerates the lining, and glands lengthen and become tortuous; maximal thickness late in the follicular phase |
| Secretory | Ovulation to menses (about 14 days) | Progesterone | Around day 16, glycogen collects at the base of gland cells (subnuclear vacuoles); glands then dilate, coil and secrete; stromal vascularity increases, and the stroma turns edematous late in the phase |
A secretory endometrium means progesterone, and progesterone means ovulation happened (unless a progestin was given).
Reading the hormone curves
Picture a 28-day axis with ovulation on day 14:
- LH: flat, then one tall, narrow spike at midcycle.
- FSH: a small rise at the start of the cycle, a dip through the late follicular phase, then a small spike alongside the LH surge.
- Estradiol: two humps: a tall preovulatory peak that triggers the LH surge, a dip right after ovulation, then a lower mid-luteal hump.
- Progesterone: low until ovulation, then one broad dome peaking about a week later and falling before menses.
- Basal body temperature: a step up of about 0.5°C after ovulation.
When a stem gives a cycle day, convert it to days before the next period: luteal events happen a nearly fixed number of days before menses.
When the cycle breaks
| Scenario | Hormone pattern | Result |
|---|---|---|
| Pregnancy | hCG maintains the corpus luteum; progesterone stays high | No menses; placenta takes over after 9–10 weeks |
| Anovulation (adolescence, after age 45, PCOS) | No LH surge, no corpus luteum, no progesterone; estrogen is unopposed | Endometrium outgrows its blood supply and sloughs incompletely: irregular, sometimes heavy, prolonged bleeding; repeated cycles risk endometrial hyperplasia or cancer |
| Hyperprolactinemia | Prolactin inhibits GnRH release, so LH and FSH fall | Oligo- or amenorrhea, galactorrhea; dopamine agonist (cabergoline preferred) |
| Functional hypothalamic amenorrhea | Low calorie intake, heavy exercise or stress reduce GnRH | Low FSH, LH and estradiol; amenorrhea |
| Menopause or ovarian insufficiency | Follicle depletion: inhibin and estradiol fall, feedback is lost | FSH and LH rise sharply |
| Combined oral contraceptives | Estrogen plus progestin inhibit GnRH release | No LH surge and no ovulation; thick cervical mucus; endometrium less receptive |
Work through missed periods with the amenorrhea workup flowchart, review prolactin excess in the prolactinoma vs acromegaly guide, and compare hormonal methods in the contraception methods overview.
Classic stem clues
| The stem says | Think |
|---|---|
| "Which hormone causes the LH surge?" | Estradiol, through positive feedback |
| Basal body temperature rises about 0.5°C and stays up | Progesterone from a corpus luteum: ovulation occurred |
| Clear, stretchy mucus with ferning | High estradiol, late follicular phase |
| Subnuclear glycogen vacuoles on endometrial biopsy | Early secretory phase, about 2 days after ovulation |
| Cycles lengthen from 28 to 35 days | The follicular phase got longer |
| Very high FSH with low estradiol | Menopause or primary ovarian insufficiency |
| Missed period, progesterone still high | hCG from a pregnancy rescuing the corpus luteum |
Practice question
Vignette. A 31-year-old woman is being evaluated for infertility. For years her periods have come every 35 days and last 5 days, and a pregnancy test is negative. Her physician wants a single serum progesterone level to confirm that she ovulates. On which cycle day (day 1 = first day of bleeding) should it be drawn?
- A. Day 3
- B. Day 14
- C. Day 21
- D. Day 28
- E. Day 35
Answer: D. The luteal phase is nearly constant at about 14 days, so a 35-day cycle ovulates around day 21 (35 − 14). Progesterone peaks 6–8 days after ovulation, near day 28, about 1 week before her next period. A level of at least 3 ng/mL then confirms ovulation.
Why the others are wrong:
- A (day 3): early follicular phase, when progesterone is low whether or not she ovulates. Day 3 is when FSH and estradiol are measured to screen for diminished ovarian reserve.
- B (day 14): in a 35-day cycle she is still a week away from ovulating, so a low value would wrongly suggest anovulation.
- C (day 21): "day 21 progesterone" assumes a 28-day cycle. For her, day 21 is around ovulation, before the corpus luteum's progesterone peaks.
- E (day 35): the corpus luteum has regressed and progesterone has fallen; that fall is what brings on her period.
Key takeaways
- Follicular phase = FSH and estradiol, proliferative endometrium, variable length. Luteal phase = progesterone, secretory endometrium, nearly constant at about 14 days.
- Estradiol above about 200 pg/mL for about 50 hours flips feedback to positive and triggers the LH surge; ovulation follows about 34–36 hours after the surge starts.
- Ovulation day ≈ cycle length − 14; check progesterone (≥3 ng/mL) about 1 week before the next period.
- Progesterone: secretory glands, thick mucus, basal body temperature up about 0.5°C; its withdrawal starts menses.
- LH → theca → androgens; FSH → granulosa → aromatase → estradiol. Inhibin B (follicular) and inhibin A (luteal) suppress FSH.
- Broken cycles: unopposed estrogen with anovulation, low GnRH with prolactin excess or energy deficit, high FSH in menopause, no LH surge on combined pills.
Sources
- Female Reproductive Endocrinology — Merck Manual Professional Edition
- Reed BG, Carr BR. The Normal Menstrual Cycle and the Control of Ovulation — Endotext, NCBI Bookshelf (2018)
- Thiyagarajan DK, Basit H, Jeanmonod R. Physiology, Menstrual Cycle — StatPearls, NCBI Bookshelf (2024)
- Marques P, et al. Physiology of GnRH and Gonadotrophin Secretion — Endotext, NCBI Bookshelf (2024)
- Ovulatory Dysfunction — Merck Manual Professional Edition
- Diminished Ovarian Reserve — Merck Manual Professional Edition
- Abnormal Uterine Bleeding — Merck Manual Professional Edition
- Physiology of Pregnancy — Merck Manual Professional Edition
- Prolactinoma — Merck Manual Professional Edition
- LUPRON DEPOT 3.75 mg (leuprolide acetate) prescribing information — DailyMed
- Menopause — Merck Manual Professional Edition
- Oral Contraceptives — Merck Manual Professional Edition
- 27.2 Anatomy and Physiology of the Ovarian Reproductive System — OpenStax Anatomy and Physiology 2e (2022)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
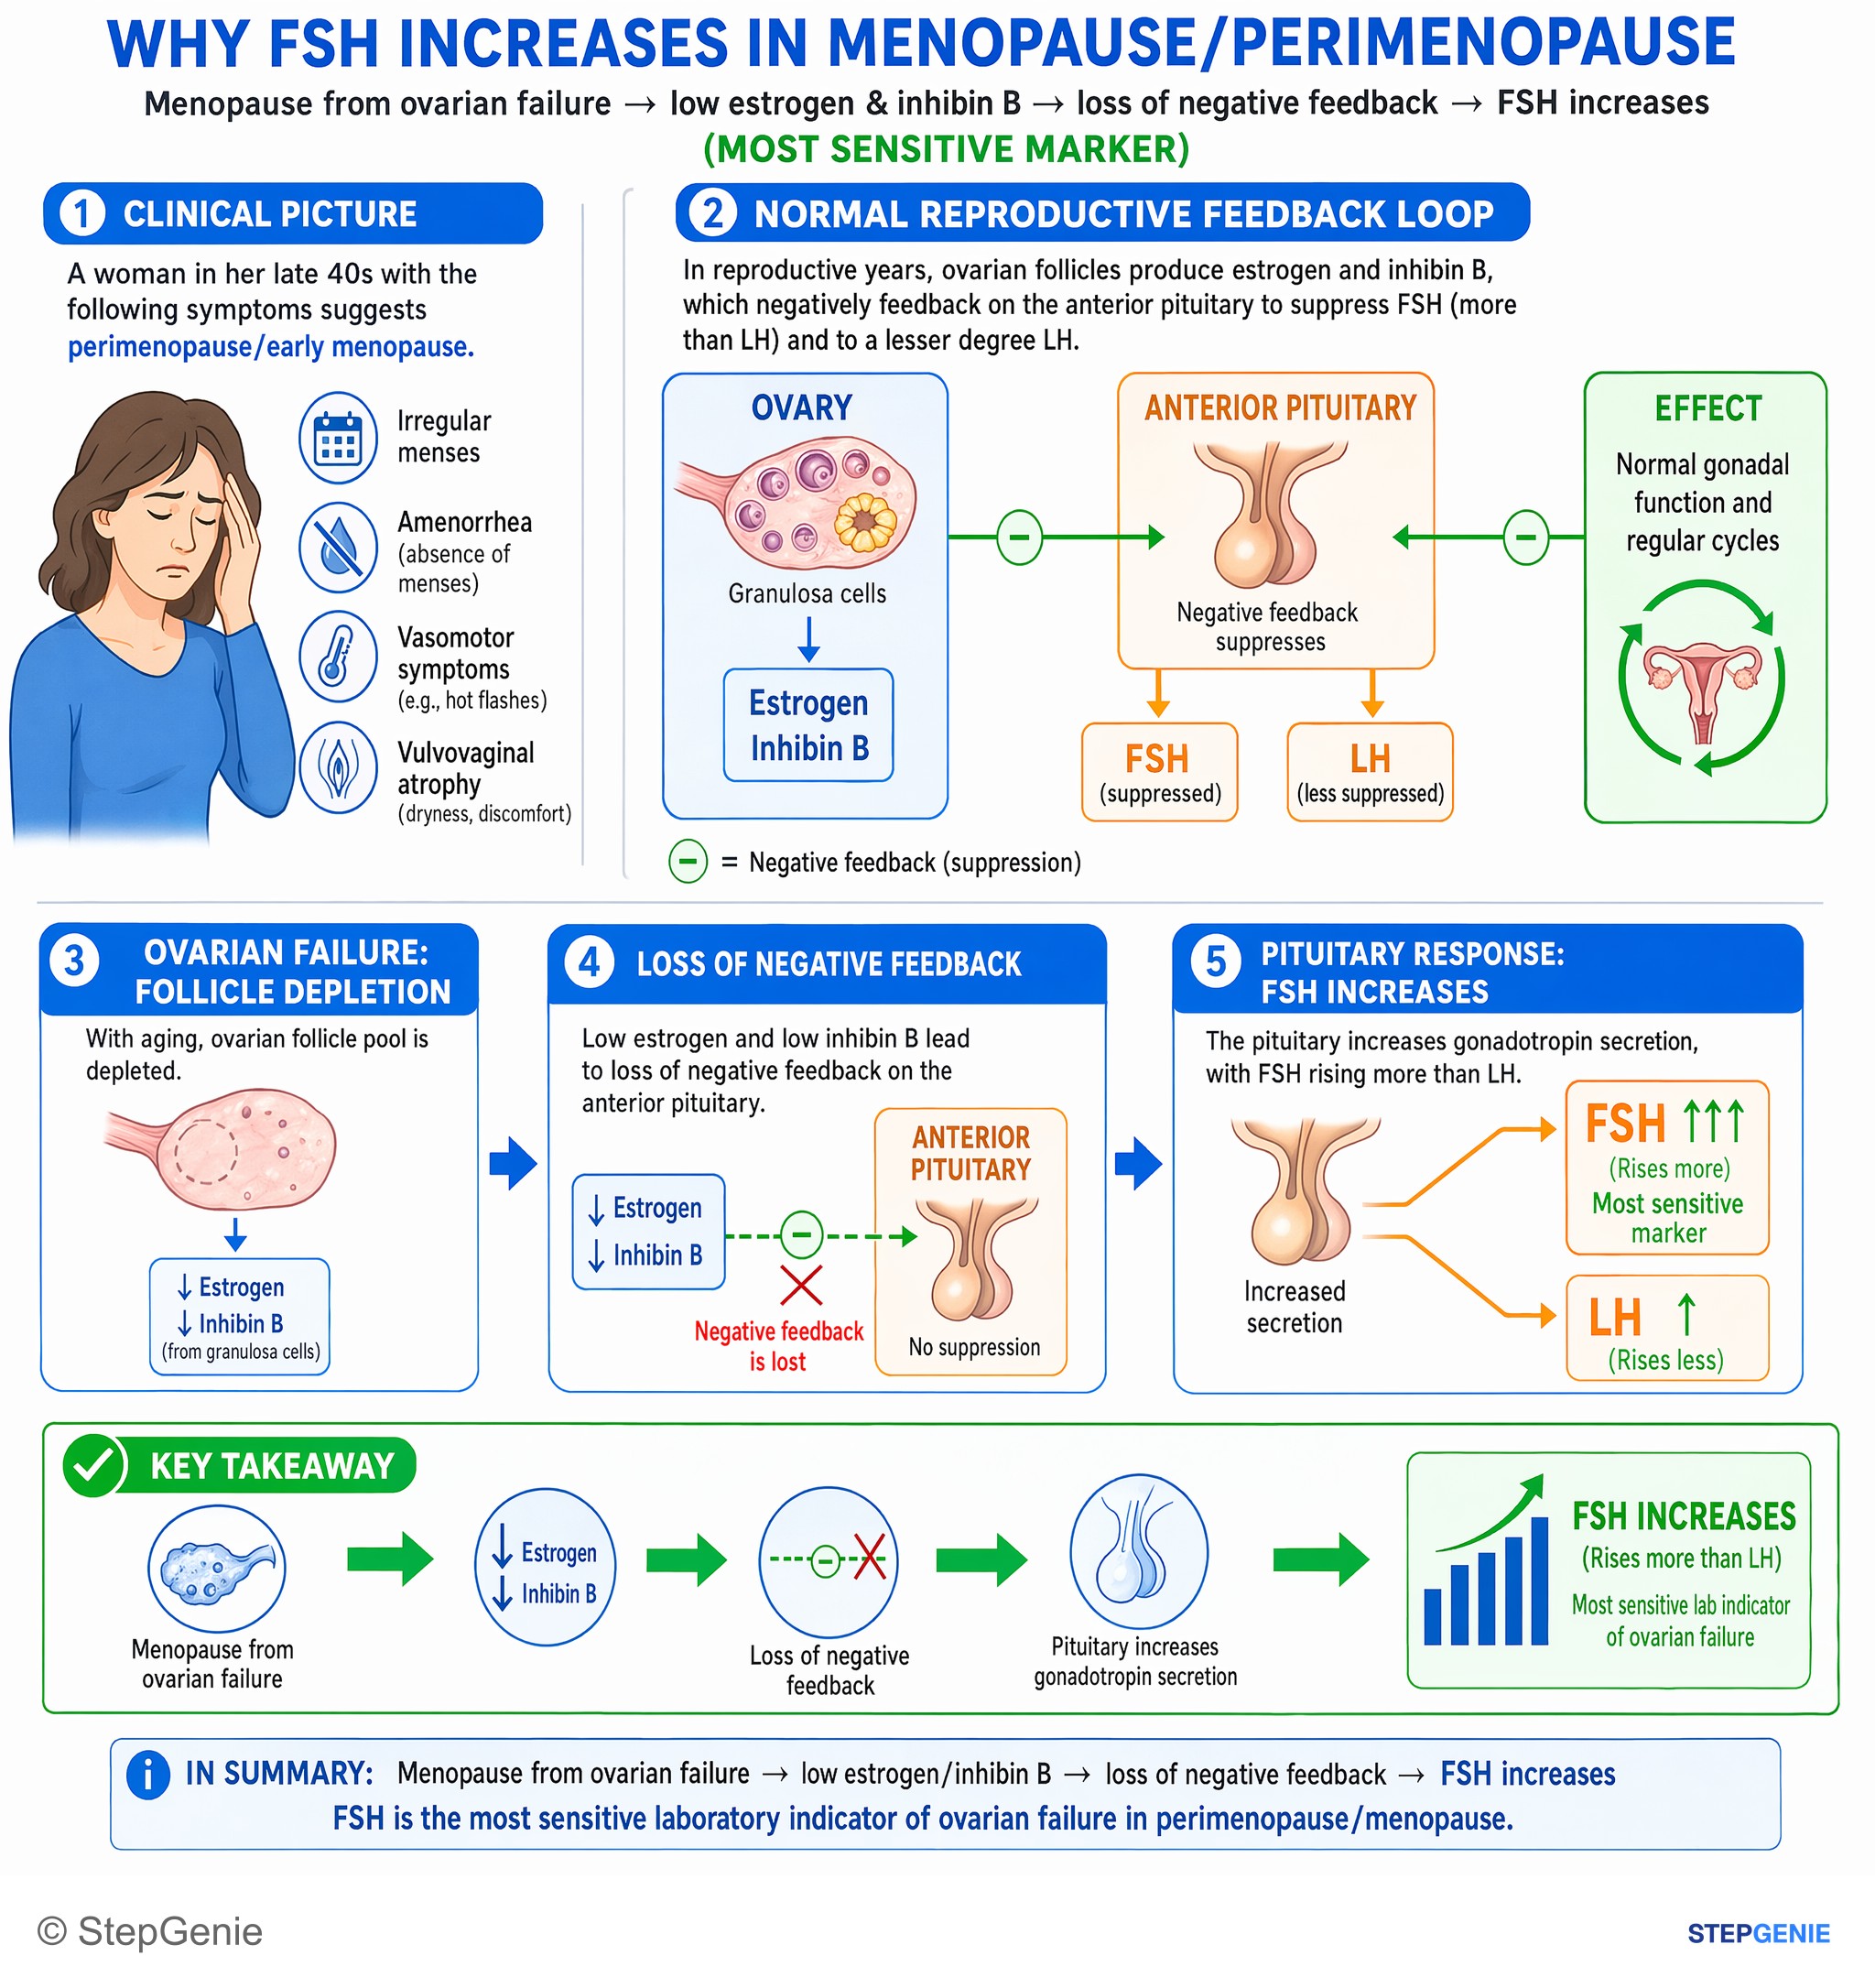
Menopause from ovarian failure → low estrogen/inhibin B → loss of negative feedback → FSH increases (most sensitive marker).
USMLE Step 1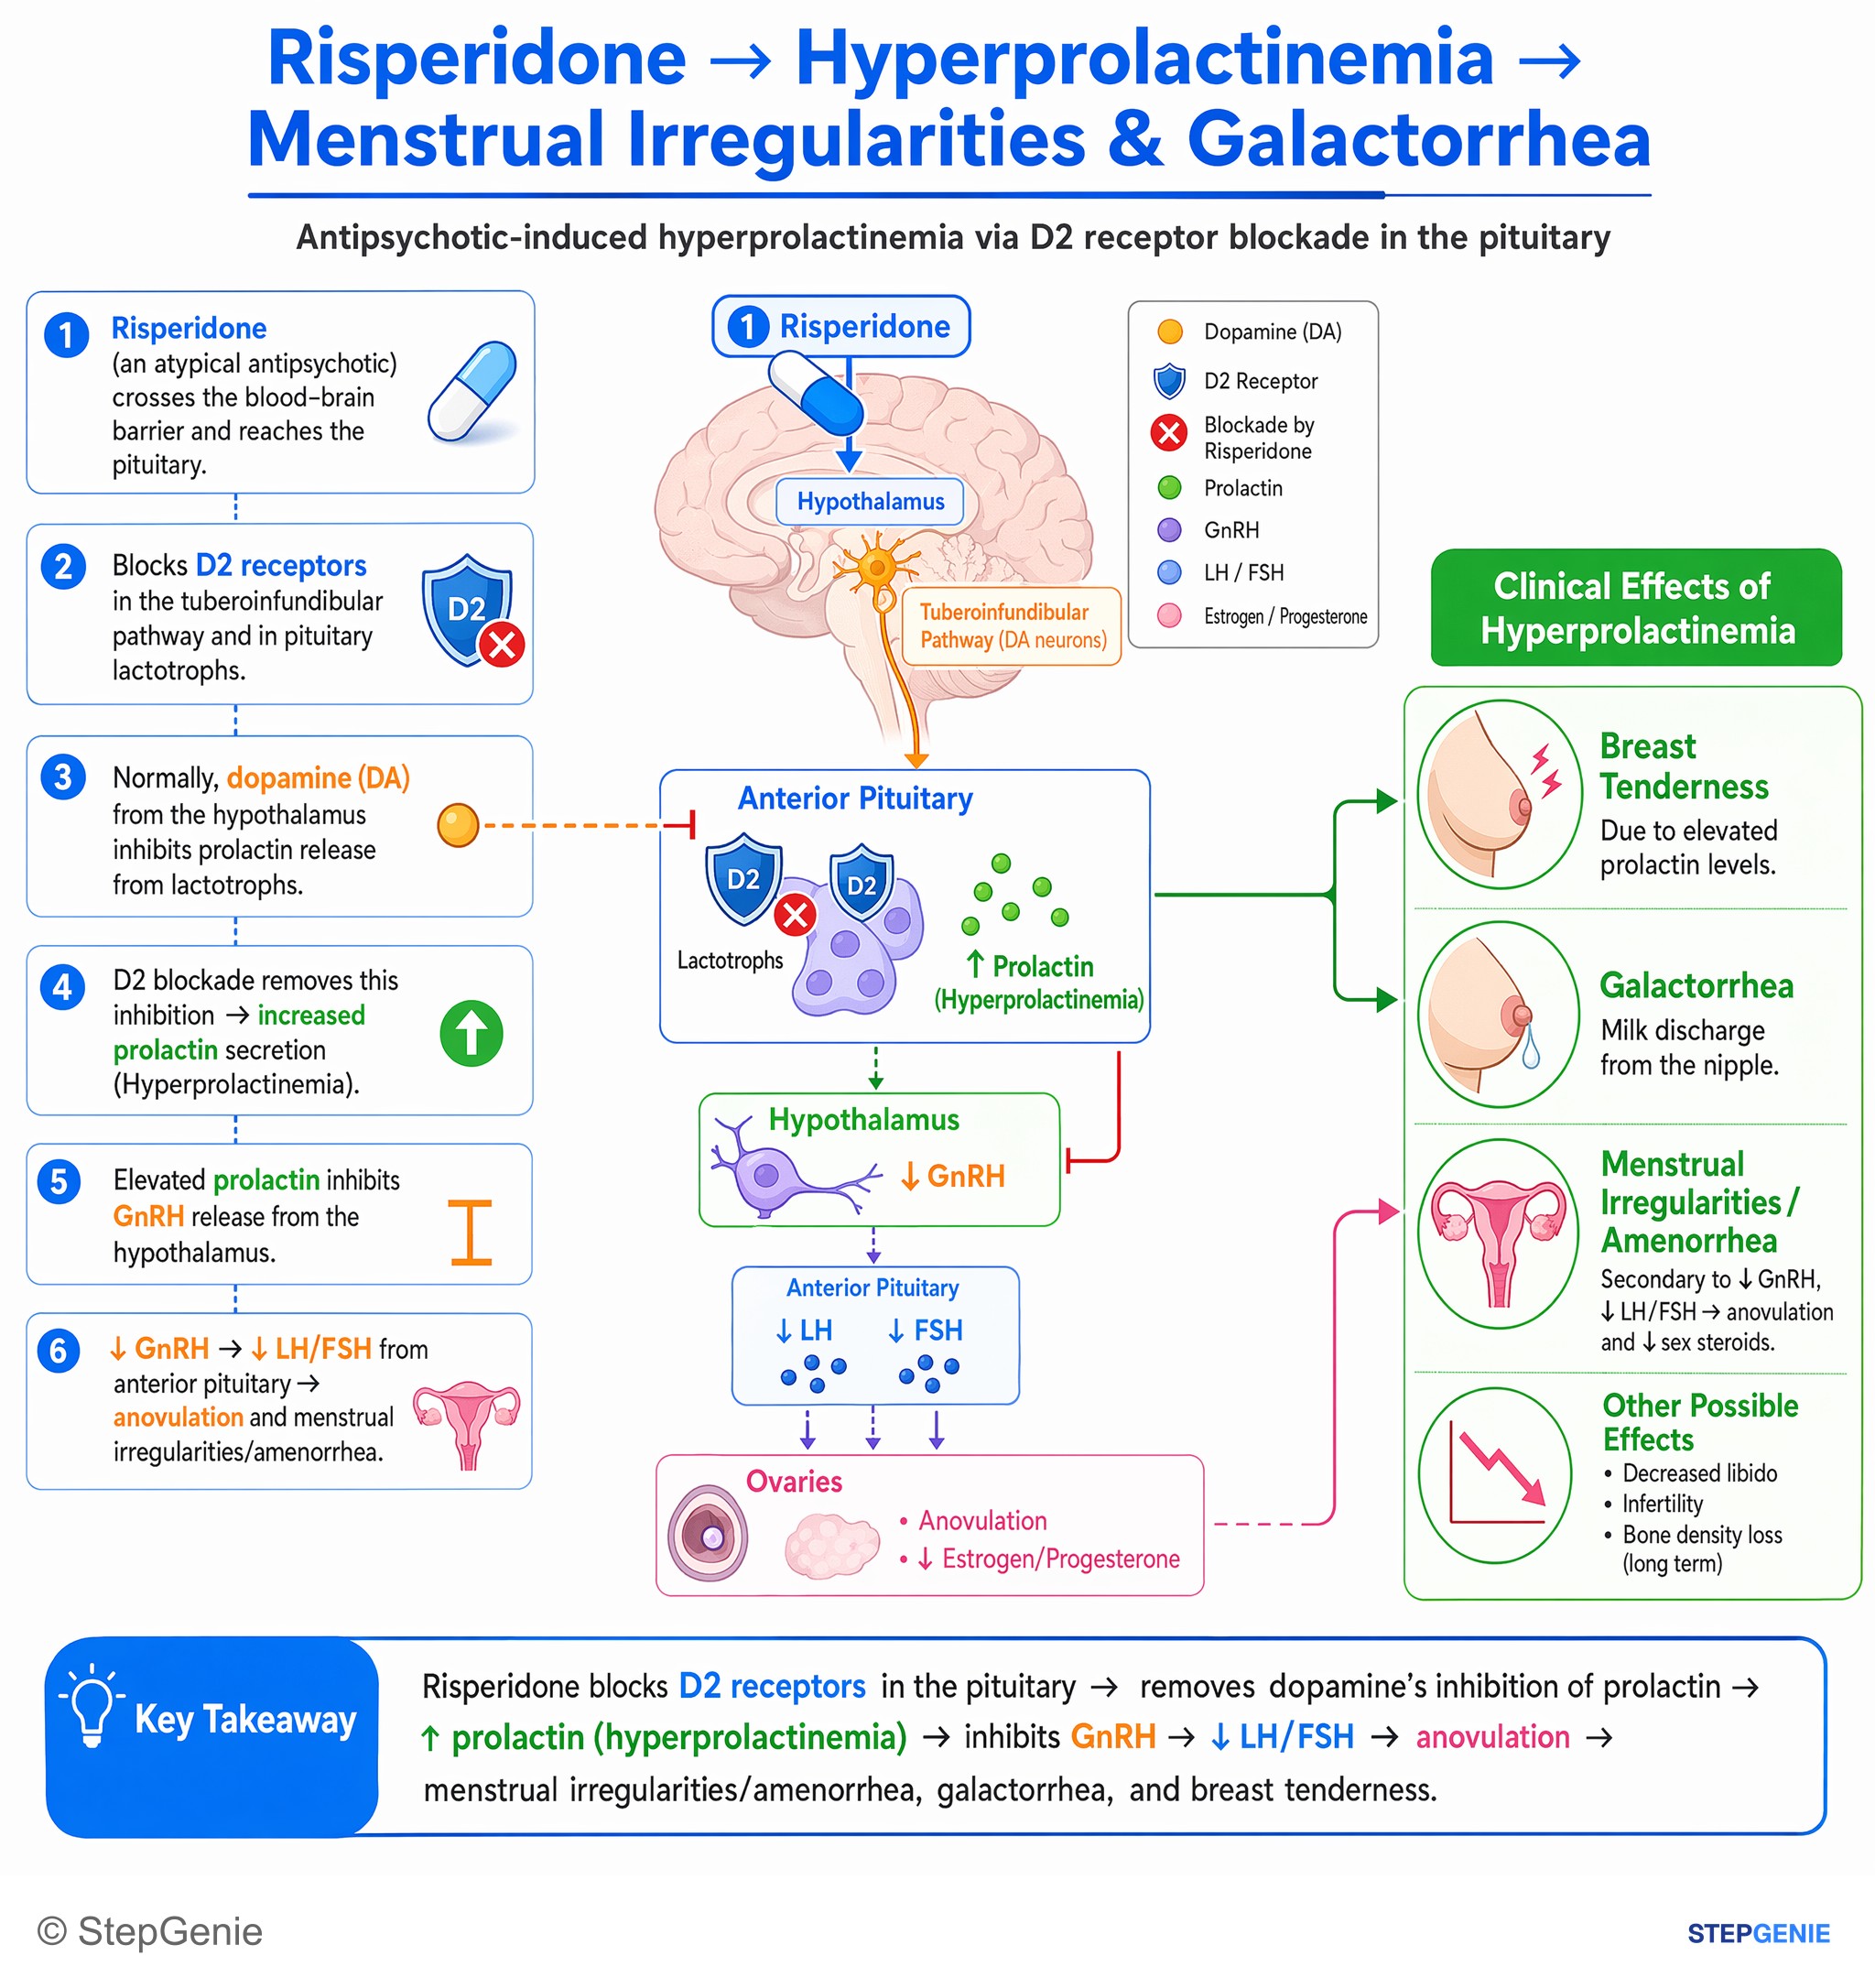
Antipsychotic-induced hyperprolactinemia (via D2 blockade in pituitary) → ↑prolactin → inhibits GnRH → oligomenorrhea/amenorrhea…
USMLE Step 2Frequently Asked Questions
What are the phases of the menstrual cycle?
The ovarian cycle has a follicular phase, ovulation and a luteal phase, while the endometrium goes through menstrual, proliferative and secretory phases. In a 28-day model, menses last about days 1 to 5, the follicular (proliferative) phase runs until ovulation around day 14, and the luteal (secretory) phase fills the final 14 days. Most of the variation in cycle length comes from the follicular phase.
What triggers the LH surge?
Estradiol positive feedback triggers the LH surge. Estradiol normally inhibits LH and FSH secretion, but once the dominant follicle keeps estradiol above about 200 pg/mL for about 50 hours, the pituitary releases its stored LH in a surge, with a smaller rise in FSH. Ovulation follows about 34 to 36 hours after the surge begins.
Why is the luteal phase about 14 days long?
The luteal phase lasts as long as the corpus luteum functions, and without pregnancy the corpus luteum degenerates after about 14 days. If an embryo implants, hCG keeps the corpus luteum making progesterone instead. Because the luteal phase is nearly constant, most differences in cycle length come from the follicular phase, and ovulation happens about 14 days before the next period.
Which hormone raises basal body temperature after ovulation?
Progesterone, which is thermogenic. After ovulation the corpus luteum secretes progesterone, and basal body temperature rises by about 0.5°C for the rest of the luteal phase. The rise shows ovulation only after it has happened and temperature charting is often inaccurate, so a mid-luteal serum progesterone level is more reliable.
When should progesterone be checked to confirm ovulation?
Serum progesterone is drawn about 1 week before the next expected period, in the mid-luteal phase. A level of at least 3 ng/mL indicates that ovulation occurred. In a 28-day cycle this is about day 21, but in a 35-day cycle it is about day 28, because the luteal phase is nearly constant at about 14 days.
What is the difference between the follicular and luteal phase?
The follicular phase is driven by FSH and estradiol, builds a proliferative endometrium, produces clear, stretchy cervical mucus and varies in length. The luteal phase is driven by progesterone from the corpus luteum, creates a secretory endometrium and thick cervical mucus, raises basal body temperature by about 0.5°C and lasts about 14 days.