Waldenström macroglobulinemia (WM) is one of those Step 1 heme/onc entities that feels “rare” until you realize how many classic vignettes it explains: older patient, IgM spike, hyperviscosity, neuropathy, and no lytic bone lesions. If you can quickly separate it from multiple myeloma, CLL, and marginal zone lymphoma—and remember what IgM does physiologically—you’ll pick up easy points.
Where Waldenström Fits (Big Picture)
Waldenström macroglobulinemia is essentially:
- A lymphoplasmacytic lymphoma (a B-cell non-Hodgkin lymphoma with plasmacytic differentiation)
- That secretes monoclonal IgM
- Causing symptoms largely from IgM-related hyperviscosity and immune effects
High-yield one-liner:
WM = lymphoplasmacytic lymphoma + IgM monoclonal gammopathy → hyperviscosity, neuropathy, bleeding, cryoglobulinemia.
Definition & Classification
What it is
Waldenström macroglobulinemia is a low-grade B-cell neoplasm characterized by:
- Bone marrow infiltration by lymphoplasmacytic cells
- A circulating monoclonal IgM paraprotein
What it’s NOT (Step 1 traps)
- Not multiple myeloma (usually IgG/IgA; lytic lesions, hypercalcemia, renal failure more prominent)
- Not MGUS (MGUS is asymptomatic and has lower M-protein burden)
- Not CLL/SLL (CD5+ CD23+ small mature lymphocytes; can have hypogammaglobulinemia)
Pathophysiology: Why IgM Causes Such Distinct Symptoms
1) IgM structure → hyperviscosity
IgM is a pentamer, so it is large and stays mainly intravascular. That makes it a prime culprit for increased plasma viscosity.
Clinical consequences of hyperviscosity:
- Neurologic: headache, dizziness, confusion, stroke-like symptoms
- Visual: blurry vision, “sausage-link” retinal veins, retinal hemorrhages
- Bleeding: mucosal bleeding (epistaxis, gingival bleeding) due to impaired platelet function and shear effects
2) IgM can behave like an autoantibody
IgM paraproteins may bind to various targets, producing:
- Peripheral neuropathy (classically demyelinating; sometimes anti–myelin-associated glycoprotein [MAG] activity)
- Cold agglutinin hemolytic anemia (IgM-mediated RBC agglutination at cold temps)
- Cryoglobulinemia (precipitation in the cold) → Raynaud, purpura, arthralgias, renal disease (more often mixed cryoglobulinemia overall, but WM can contribute)
3) Marrow infiltration → cytopenias
Bone marrow involvement can cause:
- Anemia (common)
- Thrombocytopenia and leukopenia (less common but possible)
HY genetic association
Many cases have MYD88 mutation (often MYD88 L265P), which drives NF-κB signaling and B-cell survival.
Clinical Presentation (How It Shows Up in Vignettes)
Classic symptom clusters
Hyperviscosity syndrome
- Headache, vision changes, vertigo, confusion
- Mucosal bleeding
- Retinal hemorrhages
Neuropathy
- Distal symmetric sensory symptoms (numbness/tingling)
- Can be chronic and progressive
B symptoms
- Fever, night sweats, weight loss (variable; often indolent)
Organomegaly/lymphadenopathy
- Can occur (it’s a lymphoma), but often less dramatic than aggressive NHL
Key “separate WM from multiple myeloma” clues
WM typically has:
- No punched-out lytic lesions
- No prominent hypercalcemia from bone destruction
- Hyperviscosity is more typical (because IgM is huge)
Diagnosis: What You Need to Recognize Fast
Labs you’ll see
- Monoclonal IgM spike on serum protein electrophoresis (SPEP)
- Elevated serum viscosity (if tested)
- Possible anemia, rouleaux formation may be less emphasized than in myeloma but can occur with paraproteins
Confirmatory testing (board-style)
Diagnosis is supported by:
- Bone marrow biopsy: lymphoplasmacytic infiltrate
- Immunoglobulin studies: IgM monoclonal gammopathy
- Often MYD88 mutation positivity (supportive)
Quick comparison table (high yield)
| Feature | Waldenström macroglobulinemia | Multiple myeloma |
|---|---|---|
| Cell type | Lymphoplasmacytic lymphoma | Malignant plasma cells |
| Main Ig | IgM | Usually IgG or IgA |
| Hyperviscosity | Common | Can happen, but less classic |
| Bone lesions | Absent | Lytic lesions common |
| Hypercalcemia | Uncommon | Common (CRAB) |
| Renal failure | Can occur, but less classic | Classic (light chains, cast nephropathy) |
| Organomegaly | Can occur | Less typical |
Treatment (Step 1 / Step 2 High Yield)
Immediate management: hyperviscosity = plasmapheresis
If symptomatic hyperviscosity is present (neuro/visual/bleeding symptoms), the classic move is:
- Plasmapheresis to remove circulating IgM quickly
Why it works well in WM: IgM is largely intravascular, so plasma exchange is effective.
Disease-directed therapy
Definitive treatment targets the malignant B-cell clone. Common regimens include:
- Anti-CD20 therapy (e.g., rituximab-based regimens)
- BTK inhibitors (e.g., ibrutinib, zanubrutinib) are important in contemporary management (especially with MYD88-driven signaling)
- Combination chemoimmunotherapy may be used depending on symptoms/burden
Step-level takeaway:
- Acute hyperviscosity → plasmapheresis
- Long-term control → B-cell–directed therapy (rituximab ± others; BTK inhibitors)
High-Yield Associations & “Buzzwords”
Buzzwords that should scream WM
- “Older adult with IgM monoclonal spike”
- Hyperviscosity: blurry vision + headache + mucosal bleeding
- “Peripheral neuropathy”
- “No lytic bone lesions”
Related immunology/hematology pearls
- IgM is the first antibody produced in a primary immune response and is best at complement activation
- Pentameric structure explains:
- High molecular weight
- High viscosity
- Mostly intravascular distribution
First Aid Cross-References (What to Flip To)
Use these as “anchor pages” when you review (edition page numbers vary):
- Non-Hodgkin lymphomas (indolent B-cell lymphomas; lymphoplasmacytic lymphoma)
- Plasma cell dyscrasias (compare to multiple myeloma, MGUS)
- Hyperviscosity syndrome (classically IgM-related)
- Cold agglutinin disease / autoimmune hemolysis (IgM-mediated)
How First Aid often tests it: WM appears as lymphoplasmacytic lymphoma producing IgM, associated with hyperviscosity, Raynaud/cryoglobulinemia, and neuropathy—and contrasted with myeloma’s CRAB findings and lytic lesions.
Rapid-Fire USMLE Checklist (Memorize These)
- Diagnosis core: lymphoplasmacytic lymphoma + monoclonal IgM
- Key complication: hyperviscosity (neuro + visual + mucosal bleeding)
- Key distinguishing feature: no lytic bone lesions
- Acute treatment: plasmapheresis
- Path mutation (HY): MYD88 (often L265P)
- Extra associations: neuropathy, cryoglobulinemia, cold agglutinins
Mini Vignette Pattern (Practice in Your Head)
Stem: 68-year-old with headaches, blurry vision, epistaxis, fatigue. Labs show anemia and an M-spike. Imaging shows no lytic lesions.
Answer path: Think IgM → hyperviscosity → Waldenström macroglobulinemia → treat acute symptoms with plasmapheresis, then rituximab-based therapy/BTK inhibitor.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
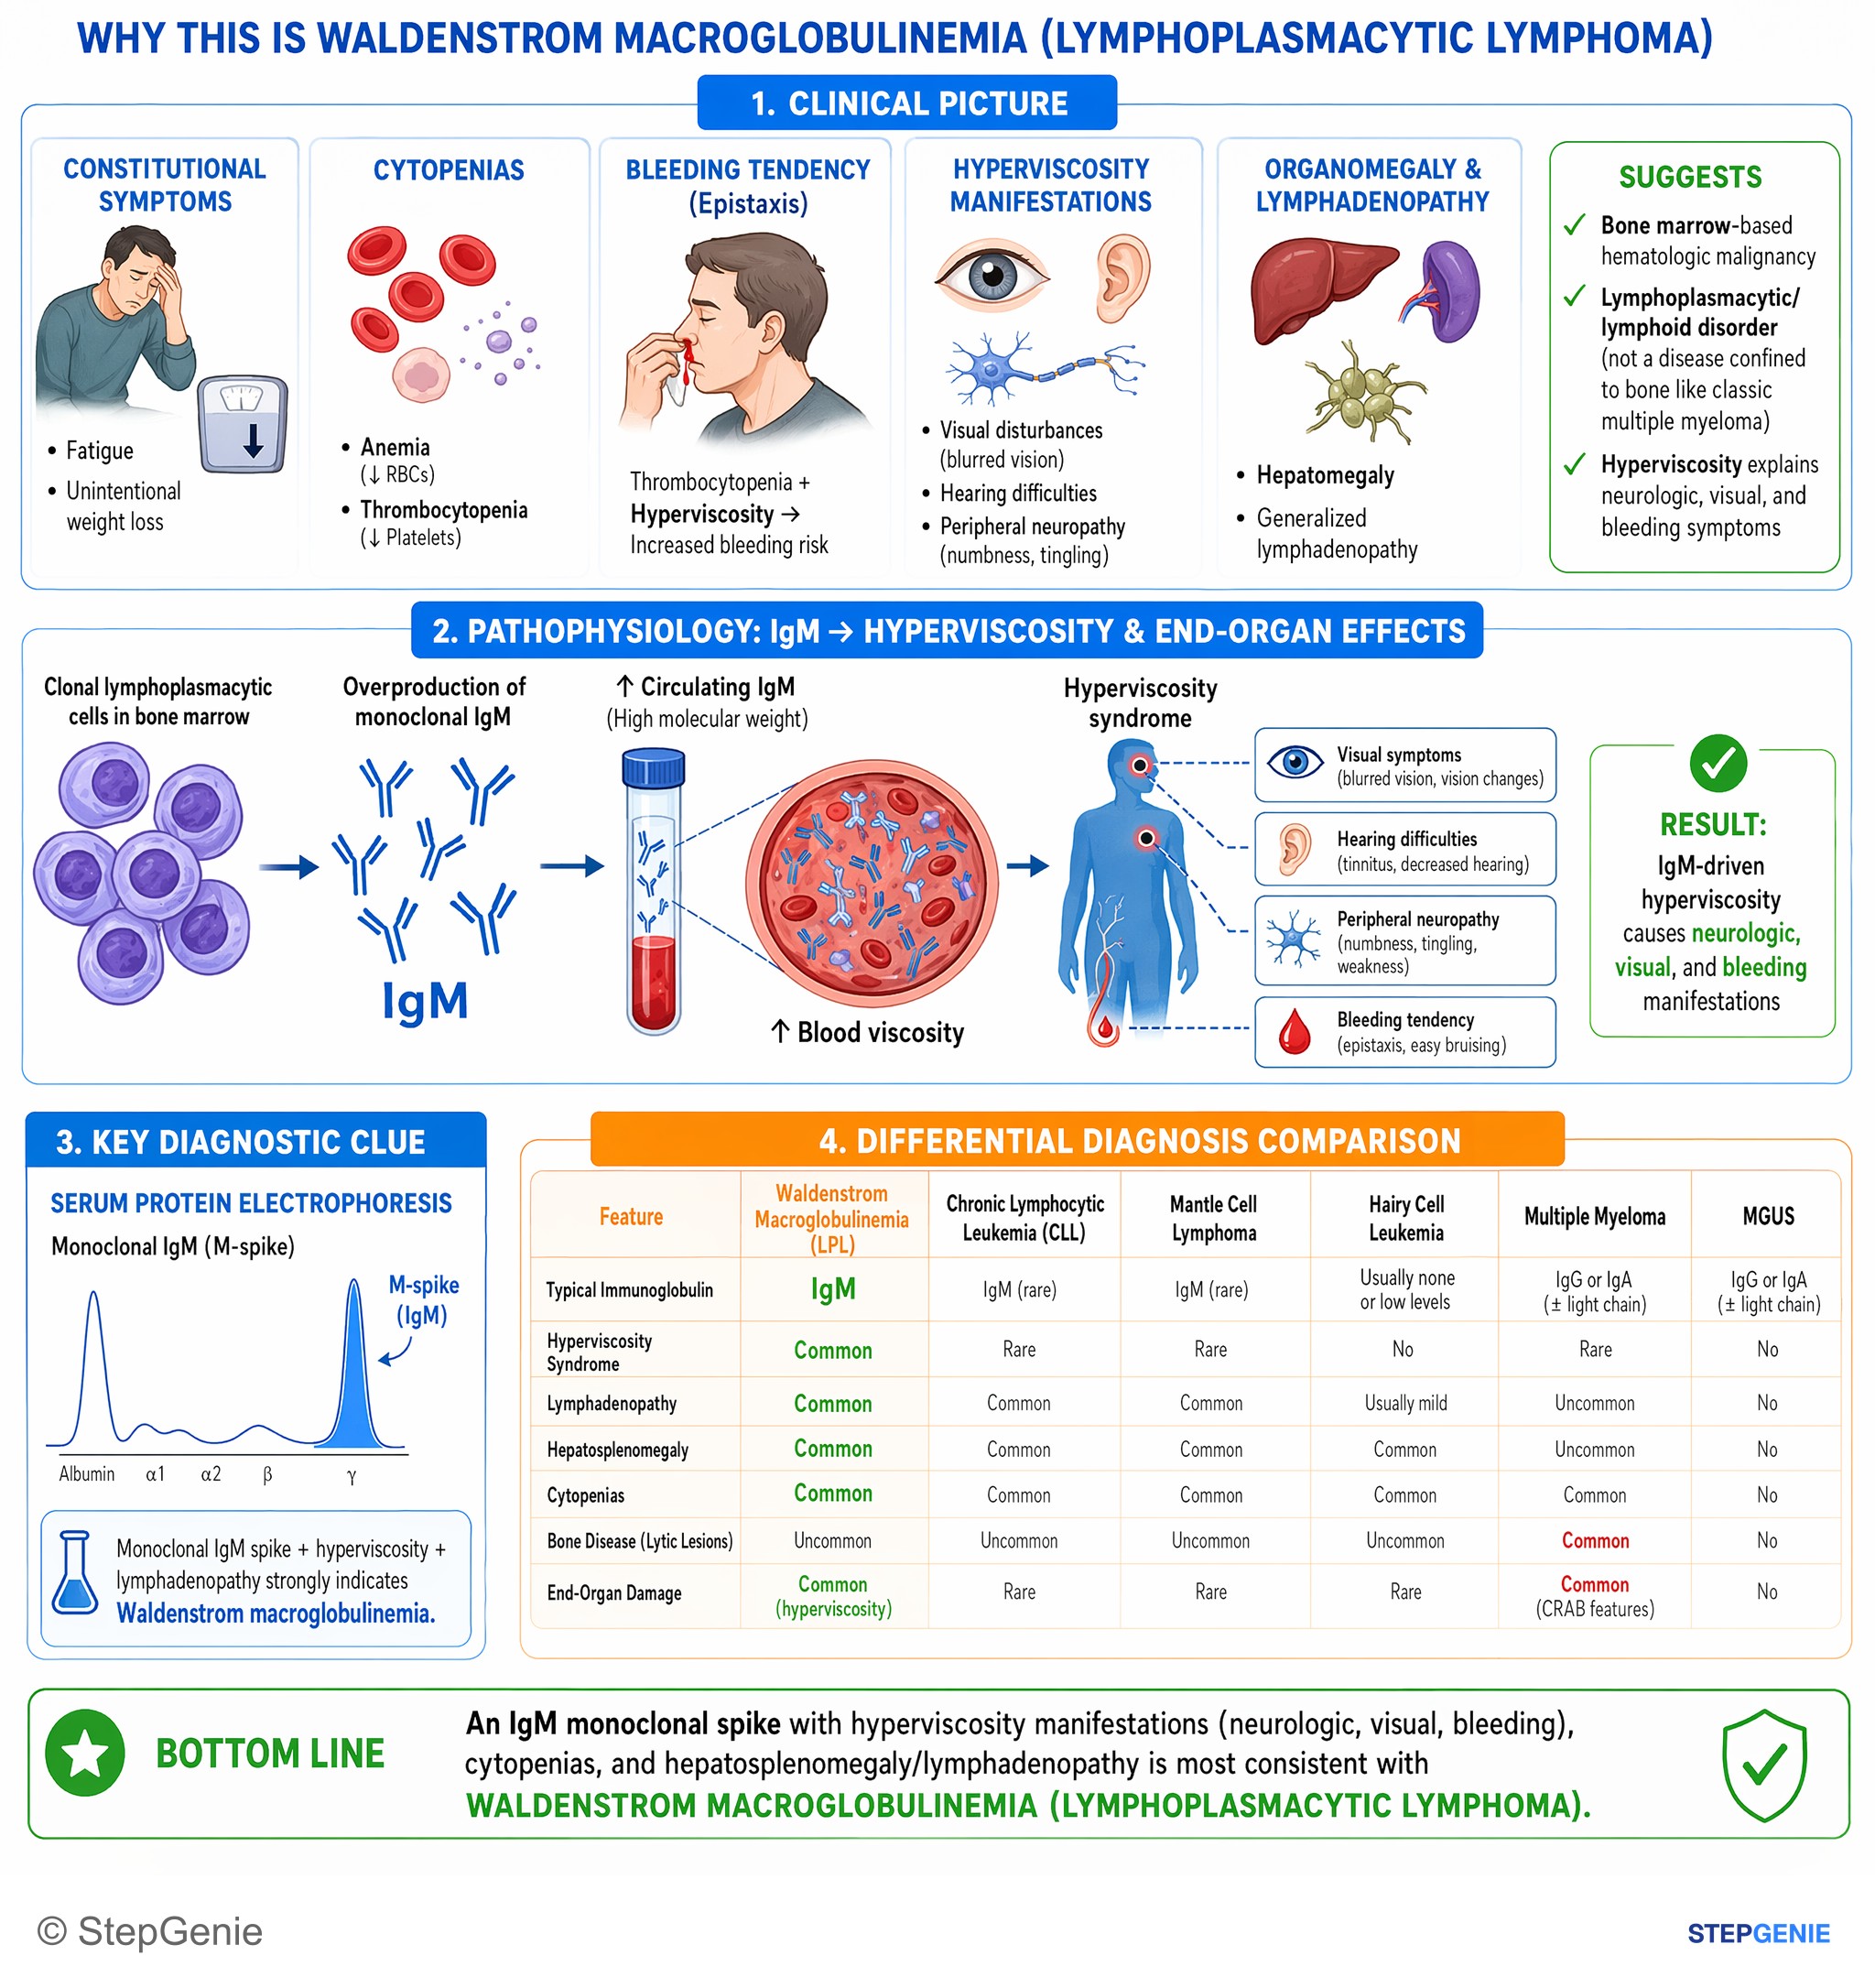
Waldenstrom macroglobulinemia: IgM monoclonal spike causing hyperviscosity (neurologic, visual, bleeding) with anemia, thrombocytopenia…
USMLE Step 1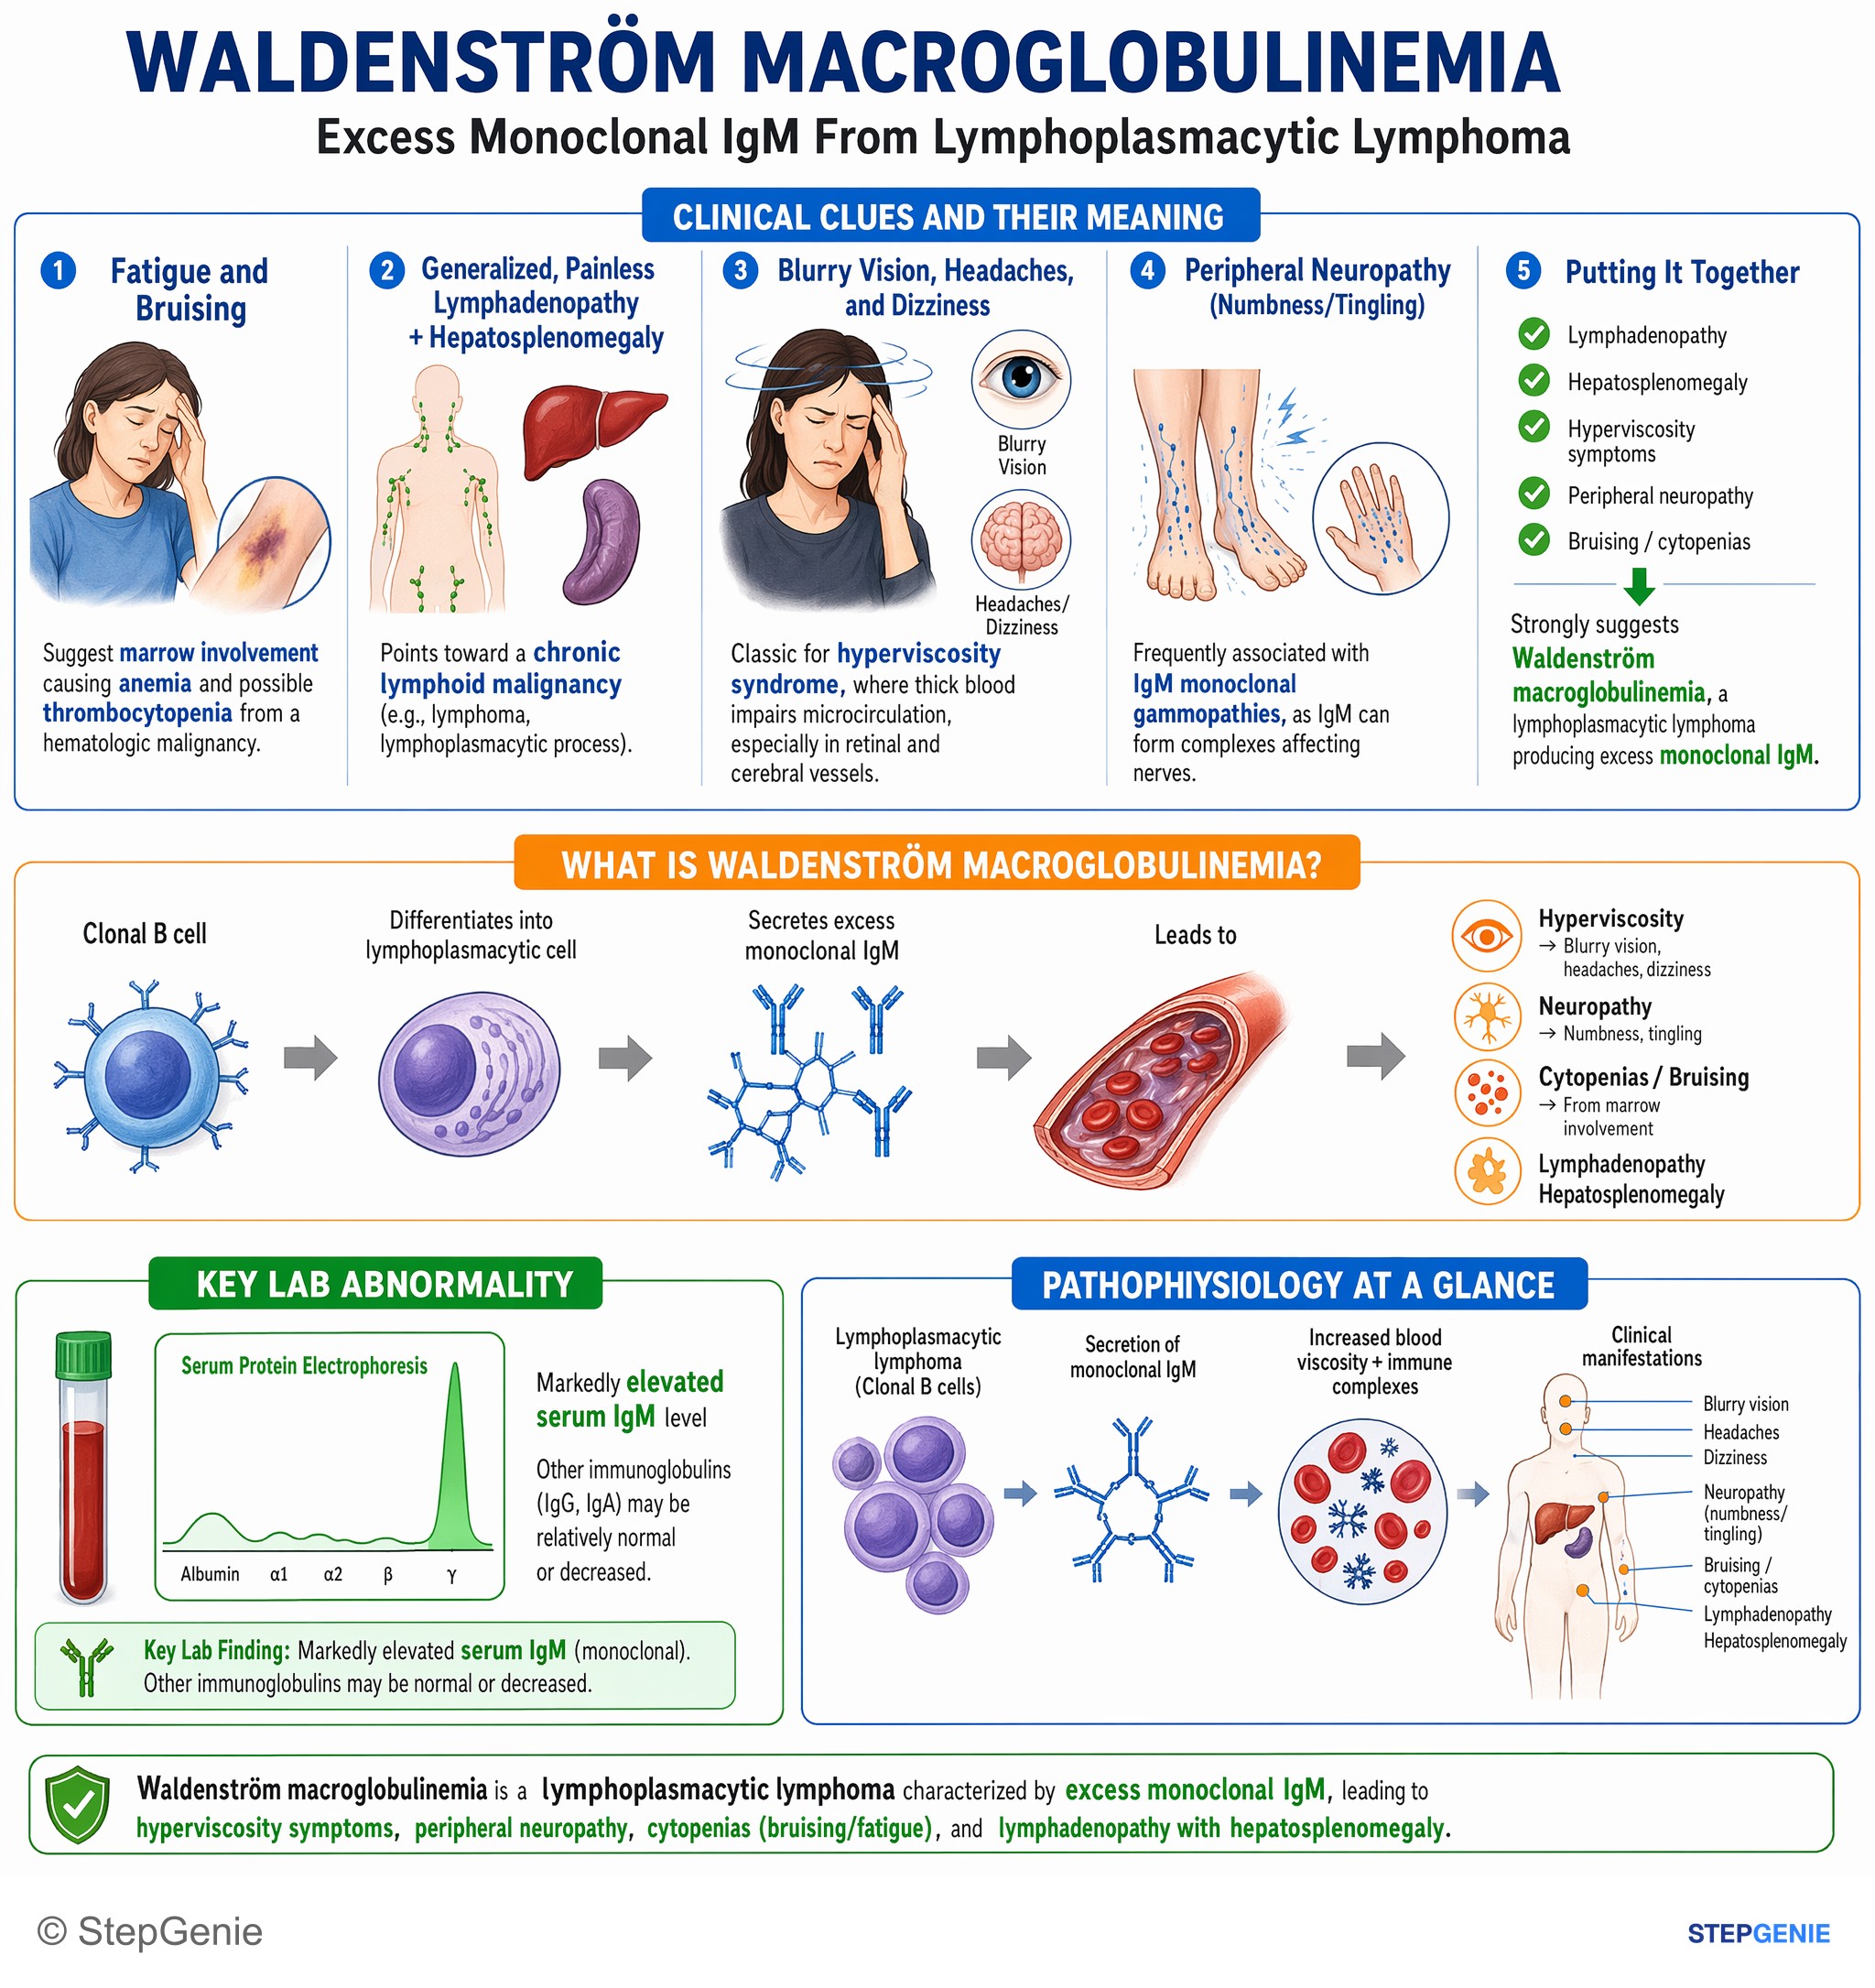
Waldenström macroglobulinemia from clonal B cells secreting excess IgM → hyperviscosity (blurry vision, headaches, dizziness, neuropathy)…
USMLE Step 1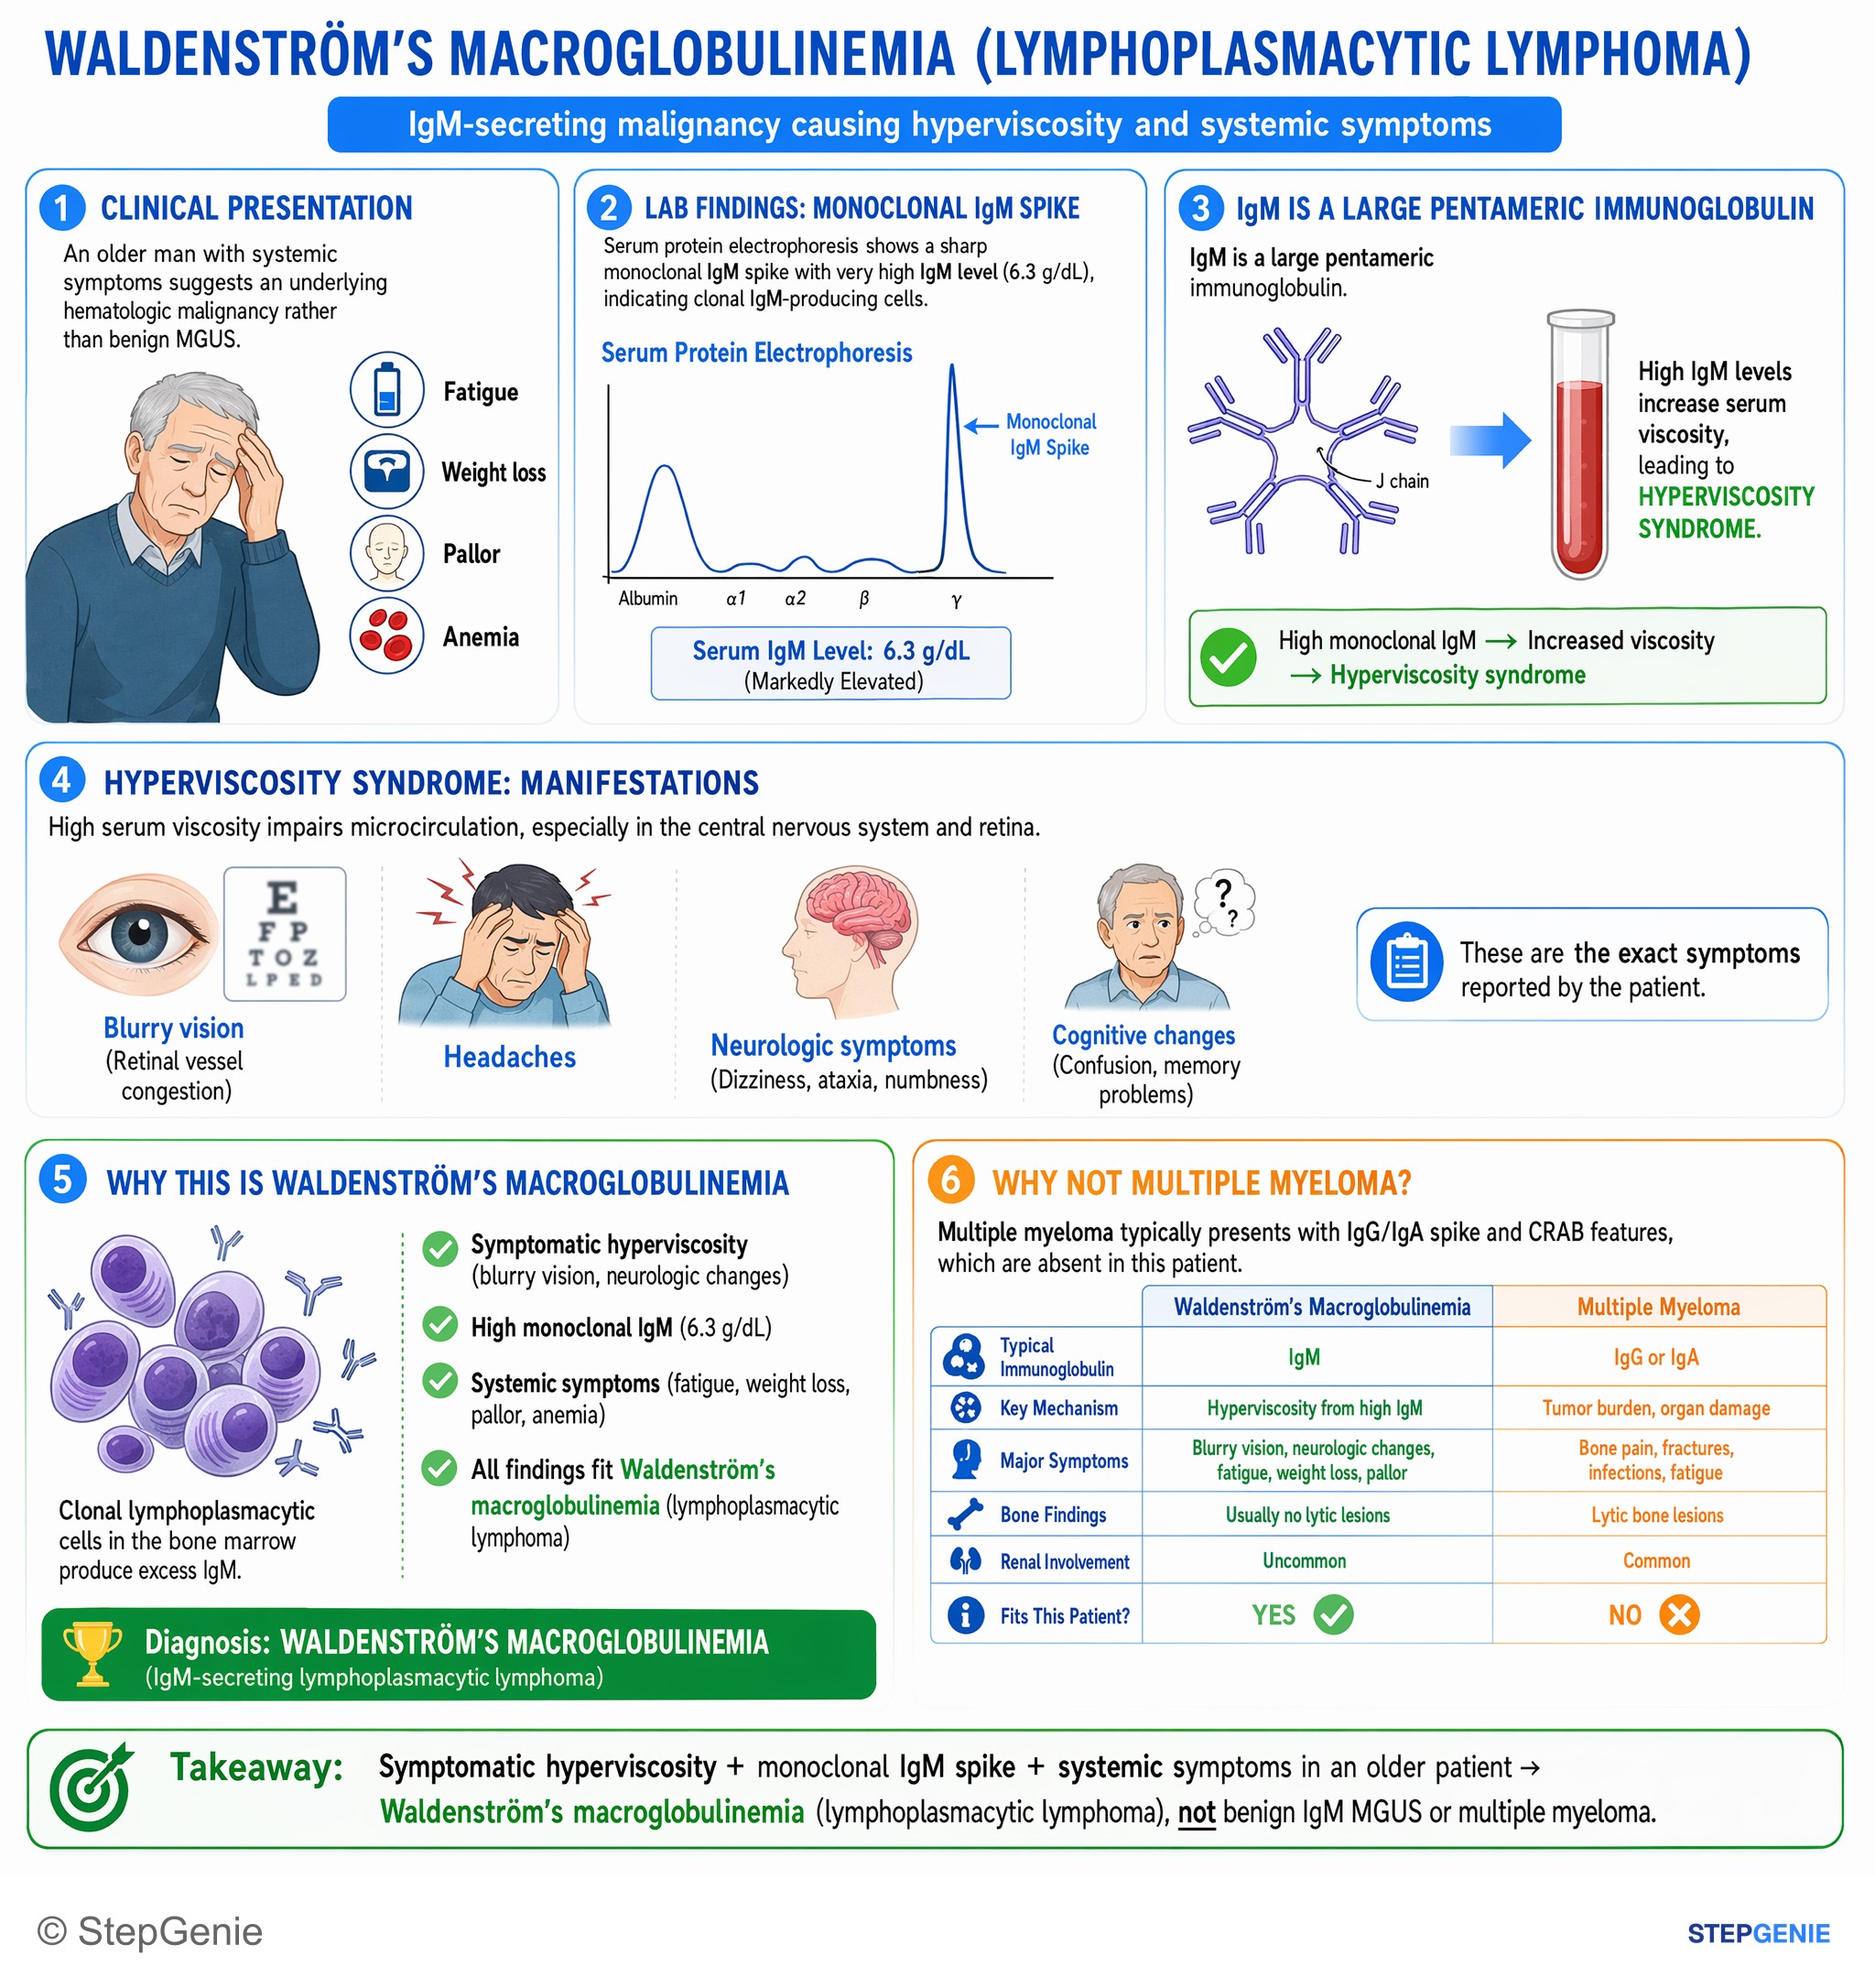
Waldenstrom’s macroglobulinemia: IgM-secreting lymphoplasmacytic lymphoma causing hyperviscosity (blurry vision, neurologic changes) with…
USMLE Step 2Frequently Asked Questions
Why does Waldenström macroglobulinemia cause hyperviscosity symptoms like blurry vision, headache, and bleeding?
Waldenström macroglobulinemia causes hyperviscosity because it produces monoclonal IgM, which is a large pentamer that stays mainly in the intravascular space. That raises plasma viscosity and leads to neurologic symptoms such as headache, dizziness, confusion, and stroke-like symptoms, visual findings like blurry vision and retinal hemorrhages, and mucosal bleeding from impaired platelet function and shear effects.
How do you tell Waldenström macroglobulinemia from multiple myeloma on Step 1?
The key distinction is that Waldenström macroglobulinemia is a lymphoplasmacytic lymphoma with an IgM monoclonal gammopathy, whereas multiple myeloma usually involves malignant plasma cells producing IgG or IgA. Waldenström classically has hyperviscosity, neuropathy, and no punched-out lytic bone lesions, while myeloma more typically has lytic lesions, hypercalcemia, and renal failure as prominent features.
What is the first-line treatment for symptomatic hyperviscosity in Waldenström macroglobulinemia?
The immediate treatment is plasmapheresis. It works especially well in Waldenström macroglobulinemia because the pathogenic IgM is largely intravascular, so plasma exchange can remove it quickly. This is the classic move when patients have symptomatic hyperviscosity, including neurologic symptoms, visual changes, or bleeding, while longer-term therapy targets the malignant B-cell clone.
Why can Waldenström macroglobulinemia cause peripheral neuropathy and cold-related immune problems?
Waldenström macroglobulinemia can cause these problems because the IgM paraprotein may act like an autoantibody. It can contribute to a demyelinating peripheral neuropathy, sometimes with anti–myelin-associated glycoprotein activity, and it can also mediate cold agglutinin hemolytic anemia and cryoglobulinemia. Those immune effects help explain findings such as numbness, tingling, Raynaud symptoms, purpura, and arthralgias.
What diagnostic findings support Waldenström macroglobulinemia?
Waldenström macroglobulinemia is supported by a monoclonal IgM spike on serum protein electrophoresis together with bone marrow infiltration by lymphoplasmacytic cells. Patients may also have elevated serum viscosity, anemia, and sometimes rouleaux formation with paraproteins. Many cases also show a MYD88 mutation, often MYD88 L265P, which is supportive of the diagnosis.