Chronic myeloid leukemia (CML) is a myeloproliferative neoplasm driven by the Philadelphia chromosome, t(9;22), which fuses BCR on chromosome 22 with ABL1 from chromosome 9 to make BCR::ABL1, a constitutively active tyrosine kinase. The classic patient is a middle-aged or older adult (average age about 66) with fatigue, night sweats and early satiety from splenomegaly, and a very high white count with granulocytes at every stage of maturation, basophilia and a low leukocyte alkaline phosphatase (LAP) score. Finding BCR::ABL1 by karyotype, FISH or RT-PCR confirms it. Oral tyrosine kinase inhibitors (TKIs) are first-line: imatinib, dasatinib, nilotinib, bosutinib and now asciminib, which binds a different site on the kinase; ponatinib and high-dose asciminib cover the resistant T315I mutation. Response is tracked with BCR::ABL1 transcript levels, and about 40-50% of patients who stop after a durable deep molecular response stay in remission off treatment.
Pathophysiology: one translocation, one kinase
- t(9;22): the ABL1 gene on chromosome 9 is joined to BCR on chromosome 22; the shortened chromosome 22 is the Philadelphia (Ph) chromosome. Karyotype shows it in 90-95% of patients, and in the rest the BCR::ABL1 fusion is still found by FISH or RT-PCR (Merck).
- What the kinase does: uncontrolled tyrosine kinase activity drives proliferation, reduces adherence of leukemic cells to the marrow stroma (so they spill into the blood) and protects them from apoptosis (Merck).
- A stem cell disease: the clone includes granulocytes, red cells, megakaryocytes, monocytes and sometimes B and T cells, which is why blast phase can be myeloid or lymphoid.
- Oncogene logic: ABL1 is a proto-oncogene activated by translocation (see oncogenes vs tumor suppressors). BCR::ABL1 also defines a subset of acute lymphoblastic leukemia, Ph+ ALL, which imatinib and ponatinib also treat.
Presentation
- Who: average age at diagnosis 66; about 9,560 new US cases were expected in 2025 (Merck). Many patients have no symptoms and are found on a routine blood count.
- Symptoms: fatigue, weakness, anorexia, weight loss, night sweats and a sense of left upper quadrant fullness or early satiety; gouty arthritis can occur.
- Signs: splenomegaly in 60-70% (Merck), from moderate to massive.
- Progression: worsening anemia, thrombocytopenia, fever, bone pain, a growing spleen and rising blasts (NCI PDQ).
Labs and smear
| Finding | Typical in chronic-phase CML |
|---|---|
| WBC | High: granulocytes usually under 50,000/µL in people without symptoms, 200,000-1,000,000/µL in symptomatic patients (Merck) |
| Differential | Neutrophilia with a left shift: myelocytes, metamyelocytes and bands, with few blasts |
| Basophils and eosinophils | Increased: absolute basophilia is a strong CML clue |
| Platelets | Normal or moderately increased |
| Hemoglobin | Usually above 10 g/dL early |
| LAP score | Low (high in a leukemoid reaction) |
Diagnosis
- Blood count and smear raise the suspicion.
- Confirm BCR::ABL1: cytogenetics (karyotype showing the Ph chromosome), FISH or RT-PCR. On exams, the most specific test is detection of BCR::ABL1.
- Bone marrow evaluates the karyotype (including extra chromosomal changes), cellularity, blast count and fibrosis.
- Baseline quantitative RT-PCR (qPCR) sets up molecular monitoring on the International Scale (IS).
Phases: chronic, accelerated, blast
| Phase | Blasts in blood or marrow (NCI PDQ) | Clues |
|---|---|---|
| Chronic | <10% | About 85% present here (Merck); indolent and highly responsive to TKIs |
| Accelerated | 10-19% | Rising basophils, worsening anemia, falling or soaring platelets, growing spleen, new chromosomal changes (extra chromosome 8, isochromosome 17q) |
| Blast | ≥20%, or blasts outside the marrow | Behaves like acute leukemia: myeloblasts in about 60%, lymphoblasts in about 30% (Merck) |
- Classification update: the WHO 5th edition (2022) dropped the accelerated phase, keeping chronic and blast phases and emphasizing high-risk features such as ABL1 kinase mutations and additional chromosomal abnormalities. Its blast phase is ≥20% myeloid blasts, an extramedullary blast proliferation, or increased lymphoblasts. The International Consensus Classification (ICC 2022) kept an accelerated phase (10-19% blasts, basophils ≥20% or specific added chromosomal abnormalities); the 2025 European LeukemiaNet (ELN) panel said it could not fully endorse either classification, and NCI PDQ and Merck still describe three phases.
- The curveball: a known CML patient who suddenly has ≥20% blasts is in blast crisis, which can look like AML or ALL.
Treatment: tyrosine kinase inhibitors
TKIs switch off the driver kinase. They are not proven to be curative but are extremely effective (Merck): 5-year survival in chronic phase now exceeds 90%, and most patients stay on treatment for years.
| Drug | How it binds | Role in CML | Signature toxicities (label) |
|---|---|---|---|
| Imatinib (1st generation) | ATP-binding site; also blocks c-KIT and PDGFR | First-line; generic | Fluid retention and edema, muscle cramps, rash, nausea |
| Dasatinib (2nd) | ATP-binding site | First-line or after imatinib | Pleural effusion (fluid retention), pulmonary arterial hypertension, bleeding |
| Nilotinib (2nd) | ATP-binding site | First-line or after imatinib | QT prolongation and sudden death (boxed), pancreatitis, arterial occlusive events; Tasigna capsules need no food 2 hours before or 1 hour after a dose |
| Bosutinib (2nd) | ATP-binding site | First-line or after prior therapy | Diarrhea, liver toxicity, fluid retention |
| Asciminib | Allosteric: binds the ABL myristoyl pocket ("STAMP" inhibitor) | Chronic phase only: first-line (accelerated approval), previously treated, and T315I at 200 mg twice daily | Myelosuppression, pancreatic toxicity, hypertension |
| Ponatinib (3rd) | ATP-binding site; active against T315I | Chronic phase after 2 or more TKIs, T315I, advanced phase; not for newly diagnosed chronic phase | Arterial occlusive events, venous thromboembolism, heart failure, hepatotoxicity (boxed) |
- First-line choice: any of imatinib, dasatinib, nilotinib, bosutinib or asciminib (NCI PDQ), chosen by comorbidities, toxicity profile, cost and risk score. Second-generation TKIs give faster, deeper molecular responses than imatinib but have not improved overall survival in randomized trials (ELN 2025). In the ASC4FIRST trial, major molecular response at 48 weeks was 67.7% with asciminib vs 49% with investigator-selected TKIs (NCI PDQ).
- Resistance: if milestones are missed, check adherence and drug interactions, test for ABL1 kinase domain mutations and switch drugs. The T315I mutation defeats imatinib, dasatinib, nilotinib and bosutinib; use ponatinib or, in chronic phase, asciminib 200 mg twice daily.
- Allogeneic stem cell transplant is the only consistently curative treatment (NCI PDQ) but is reserved for accelerated or blast phase disease or resistance to the available TKIs (Merck).
- Hydroxyurea reduces tumor burden and a distressing spleen, mainly as palliation (Merck).
Monitoring and treatment-free remission
BCR::ABL1 is measured by qPCR on the International Scale at 3, 6 and 12 months, then every 3-6 months once a major molecular response is reached (Merck).
| Time point or level | BCR::ABL1 (IS) | What it means |
|---|---|---|
| 3 months | ≤10% | Favorable (ELN 2025); early molecular response |
| 6 months | ≤1% | Favorable |
| 12 months | ≤0.1% = major molecular response (MMR, MR3) | Favorable; a 3-log reduction, then maintained |
| Deep molecular response | MR4 ≤0.01%; MR4.5 ≤0.0032% | Needed before trying to stop a TKI |
- Treatment-free remission (TFR): ELN 2025 allows a stop attempt in a motivated patient in first chronic phase with typical transcripts and access to high-quality IS testing, after more than 5 years of TKI therapy (more than 4 with a second-generation TKI) and a deep molecular response (MR4 or better) for more than 2 years. About 40-50% stay off treatment.
- After stopping: qPCR every 6-8 weeks for 6 months, every 2 months to month 12, then every 3-6 months; restart the TKI if MMR is lost. Almost all patients who relapse respond again to their previous TKI (NCI PDQ).
- TKI withdrawal syndrome: muscle and joint pain (polymyalgia or arthralgia) in 20-30% after stopping, usually mild and self-limited (ELN 2025).
CML vs leukemoid reaction vs other MPNs
| Feature | CML | Leukemoid reaction |
|---|---|---|
| Cause | Clonal BCR::ABL1 neoplasm | Reactive: severe infection, inflammation, other cancers |
| Smear | Granulocytes at every stage, basophilia, eosinophilia | Mostly mature neutrophils and bands, often with toxic changes |
| LAP score | Low | High |
| Spleen | Often enlarged | Not a feature (depends on the cause) |
| BCR::ABL1 | Present | Absent |
CML is one of four classic myeloproliferative neoplasms (MPNs). Their driver mutations are, in general, mutually exclusive (Merck):
| MPN | Driver | Hallmark | Classic clue |
|---|---|---|---|
| CML | BCR::ABL1 | Left-shifted leukocytosis | Basophilia, low LAP |
| Polycythemia vera | JAK2 V617F in about 95% (most of the rest JAK2 exon 12) | Hemoglobin above 16.5 g/dL (men) or 16.0 g/dL (women), low EPO | Itching after a warm shower, erythromelalgia |
| Essential thrombocythemia | JAK2 (about 50-70%), CALR or MPL | Platelets ≥450,000/µL | Variably sized platelets (anisocytosis) |
| Primary myelofibrosis | JAK2, CALR or MPL | Marrow fibrosis, anemia, splenomegaly | Teardrop cells, nucleated red cells and immature granulocytes (leukoerythroblastosis), dry tap |
How USMLE tests CML
- Step 1 mechanism: t(9;22) → BCR::ABL1 → constitutive tyrosine kinase → imatinib, which also blocks c-KIT (hence its use in KIT-positive GIST).
- Leukocytosis + basophilia + splenomegaly + low LAP = CML; high LAP with an obvious infection = leukemoid reaction.
- Myelocytes and metamyelocytes, not blasts: CML is a chronic leukemia; ≥20% blasts means blast crisis or acute leukemia.
- CLL is the other "C" leukemia: lymphocytes, smudge cells and CD5+/CD23+ B cells; see the CLL sketch.
- Step 2 CK and Step 3: nilotinib → QT prolongation; dasatinib → pleural effusion; bosutinib → diarrhea; ponatinib → arterial occlusion; T315I → ponatinib or asciminib; MMR = BCR::ABL1 ≤0.1% IS.
Practice question
A 52-year-old man has 3 months of fatigue, early satiety, night sweats and a 4-kg weight loss. His spleen is palpable 10 cm below the left costal margin, and there is no lymphadenopathy. WBC count is 148,000/µL with neutrophils, bands, many myelocytes and metamyelocytes, 7% basophils, 4% eosinophils and 2% blasts. Hemoglobin is 11.4 g/dL and the platelet count is 520,000/µL. The leukocyte alkaline phosphatase score is low.
Which of the following best explains his condition?
A. BCR::ABL1 fusion producing a constitutively active tyrosine kinase
B. JAK2 V617F mutation causing constitutive cytokine-receptor signaling
C. Cytokine-driven reactive neutrophilia from an occult infection
D. PML::RARA fusion from t(15;17) blocking promyelocyte maturation
E. Clonal expansion of CD5+, CD23+ mature B cells
F. BRAF V600E mutation in mature B cells
Answer: A. Splenomegaly with a left-shifted granulocytic leukocytosis, absolute basophilia and eosinophilia, few blasts and a low LAP score is chronic-phase CML, caused by t(9;22) and the BCR::ABL1 kinase.
- B: JAK2 V617F drives polycythemia vera and many cases of essential thrombocythemia and myelofibrosis, and is generally not found with BCR::ABL1. PV raises the hemoglobin, ET the platelets, and myelofibrosis gives teardrop cells and a dry tap.
- C: a leukemoid reaction usually has an evident cause and shows mostly mature neutrophils with toxic changes, no basophilia and a high LAP score.
- D: acute promyelocytic leukemia (a subtype of AML) shows abnormal promyelocytes with Auer rods and often DIC, not a spectrum of maturing granulocytes with 2% blasts.
- E: CLL is a lymphocytosis with smudge cells, not a granulocytic leukocytosis.
- F: hairy cell leukemia causes pancytopenia with splenomegaly and a dry tap, not a high white count.
What next? Confirm BCR::ABL1 (marrow karyotype or FISH, plus baseline qPCR), then start a first-line TKI. Aim for BCR::ABL1 ≤10% at 3 months, ≤1% at 6 months and ≤0.1% (MMR) by 12 months.
Key takeaways
- CML = t(9;22) → BCR::ABL1 → constitutive tyrosine kinase in a myeloid stem cell.
- Splenomegaly + left-shifted leukocytosis + basophilia + low LAP; a leukemoid reaction has a high LAP.
- Confirm with karyotype, FISH or RT-PCR; the Ph chromosome is invisible on karyotype in about 5%, but BCR::ABL1 is still there.
- Phases: chronic (<10% blasts), accelerated (10-19%; dropped by WHO 2022), blast (≥20%, myeloid or lymphoid).
- First-line TKIs: imatinib, dasatinib, nilotinib, bosutinib, asciminib (myristoyl pocket); ponatinib or asciminib for T315I.
- Monitor BCR::ABL1 (IS): ≤10% at 3 months, ≤1% at 6 months, ≤0.1% (MMR) at 12 months.
- TFR: after more than 5 years of TKI and more than 2 years in MR4, about 40-50% stay off therapy; restart if MMR is lost.
Sources
- Chronic Myeloid Leukemia (CML) — Merck Manual Professional Edition (2026)
- Chronic Myeloid Leukemia Treatment (PDQ®)–Health Professional Version — National Cancer Institute (2025)
- 2025 European LeukemiaNet recommendations for the management of chronic myeloid leukemia — Leukemia (2025)
- The 5th edition of the World Health Organization Classification of Haematolymphoid Tumours: Myeloid and Histiocytic/Dendritic Neoplasms — Leukemia (2022)
- Myeloproliferative Neoplasms — StatPearls, NCBI Bookshelf (2023)
- Chronic Myelogenous Leukemia — StatPearls, NCBI Bookshelf (2023)
- Overview of Myeloproliferative Neoplasms — Merck Manual Professional Edition (2025)
- SCEMBLIX (asciminib) prescribing information — DailyMed (2026)
- GLEEVEC (imatinib) prescribing information — DailyMed (2026)
- SPRYCEL (dasatinib) prescribing information — DailyMed (2026)
- TASIGNA (nilotinib) prescribing information — DailyMed (2025)
- ICLUSIG (ponatinib) prescribing information — DailyMed (2025)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
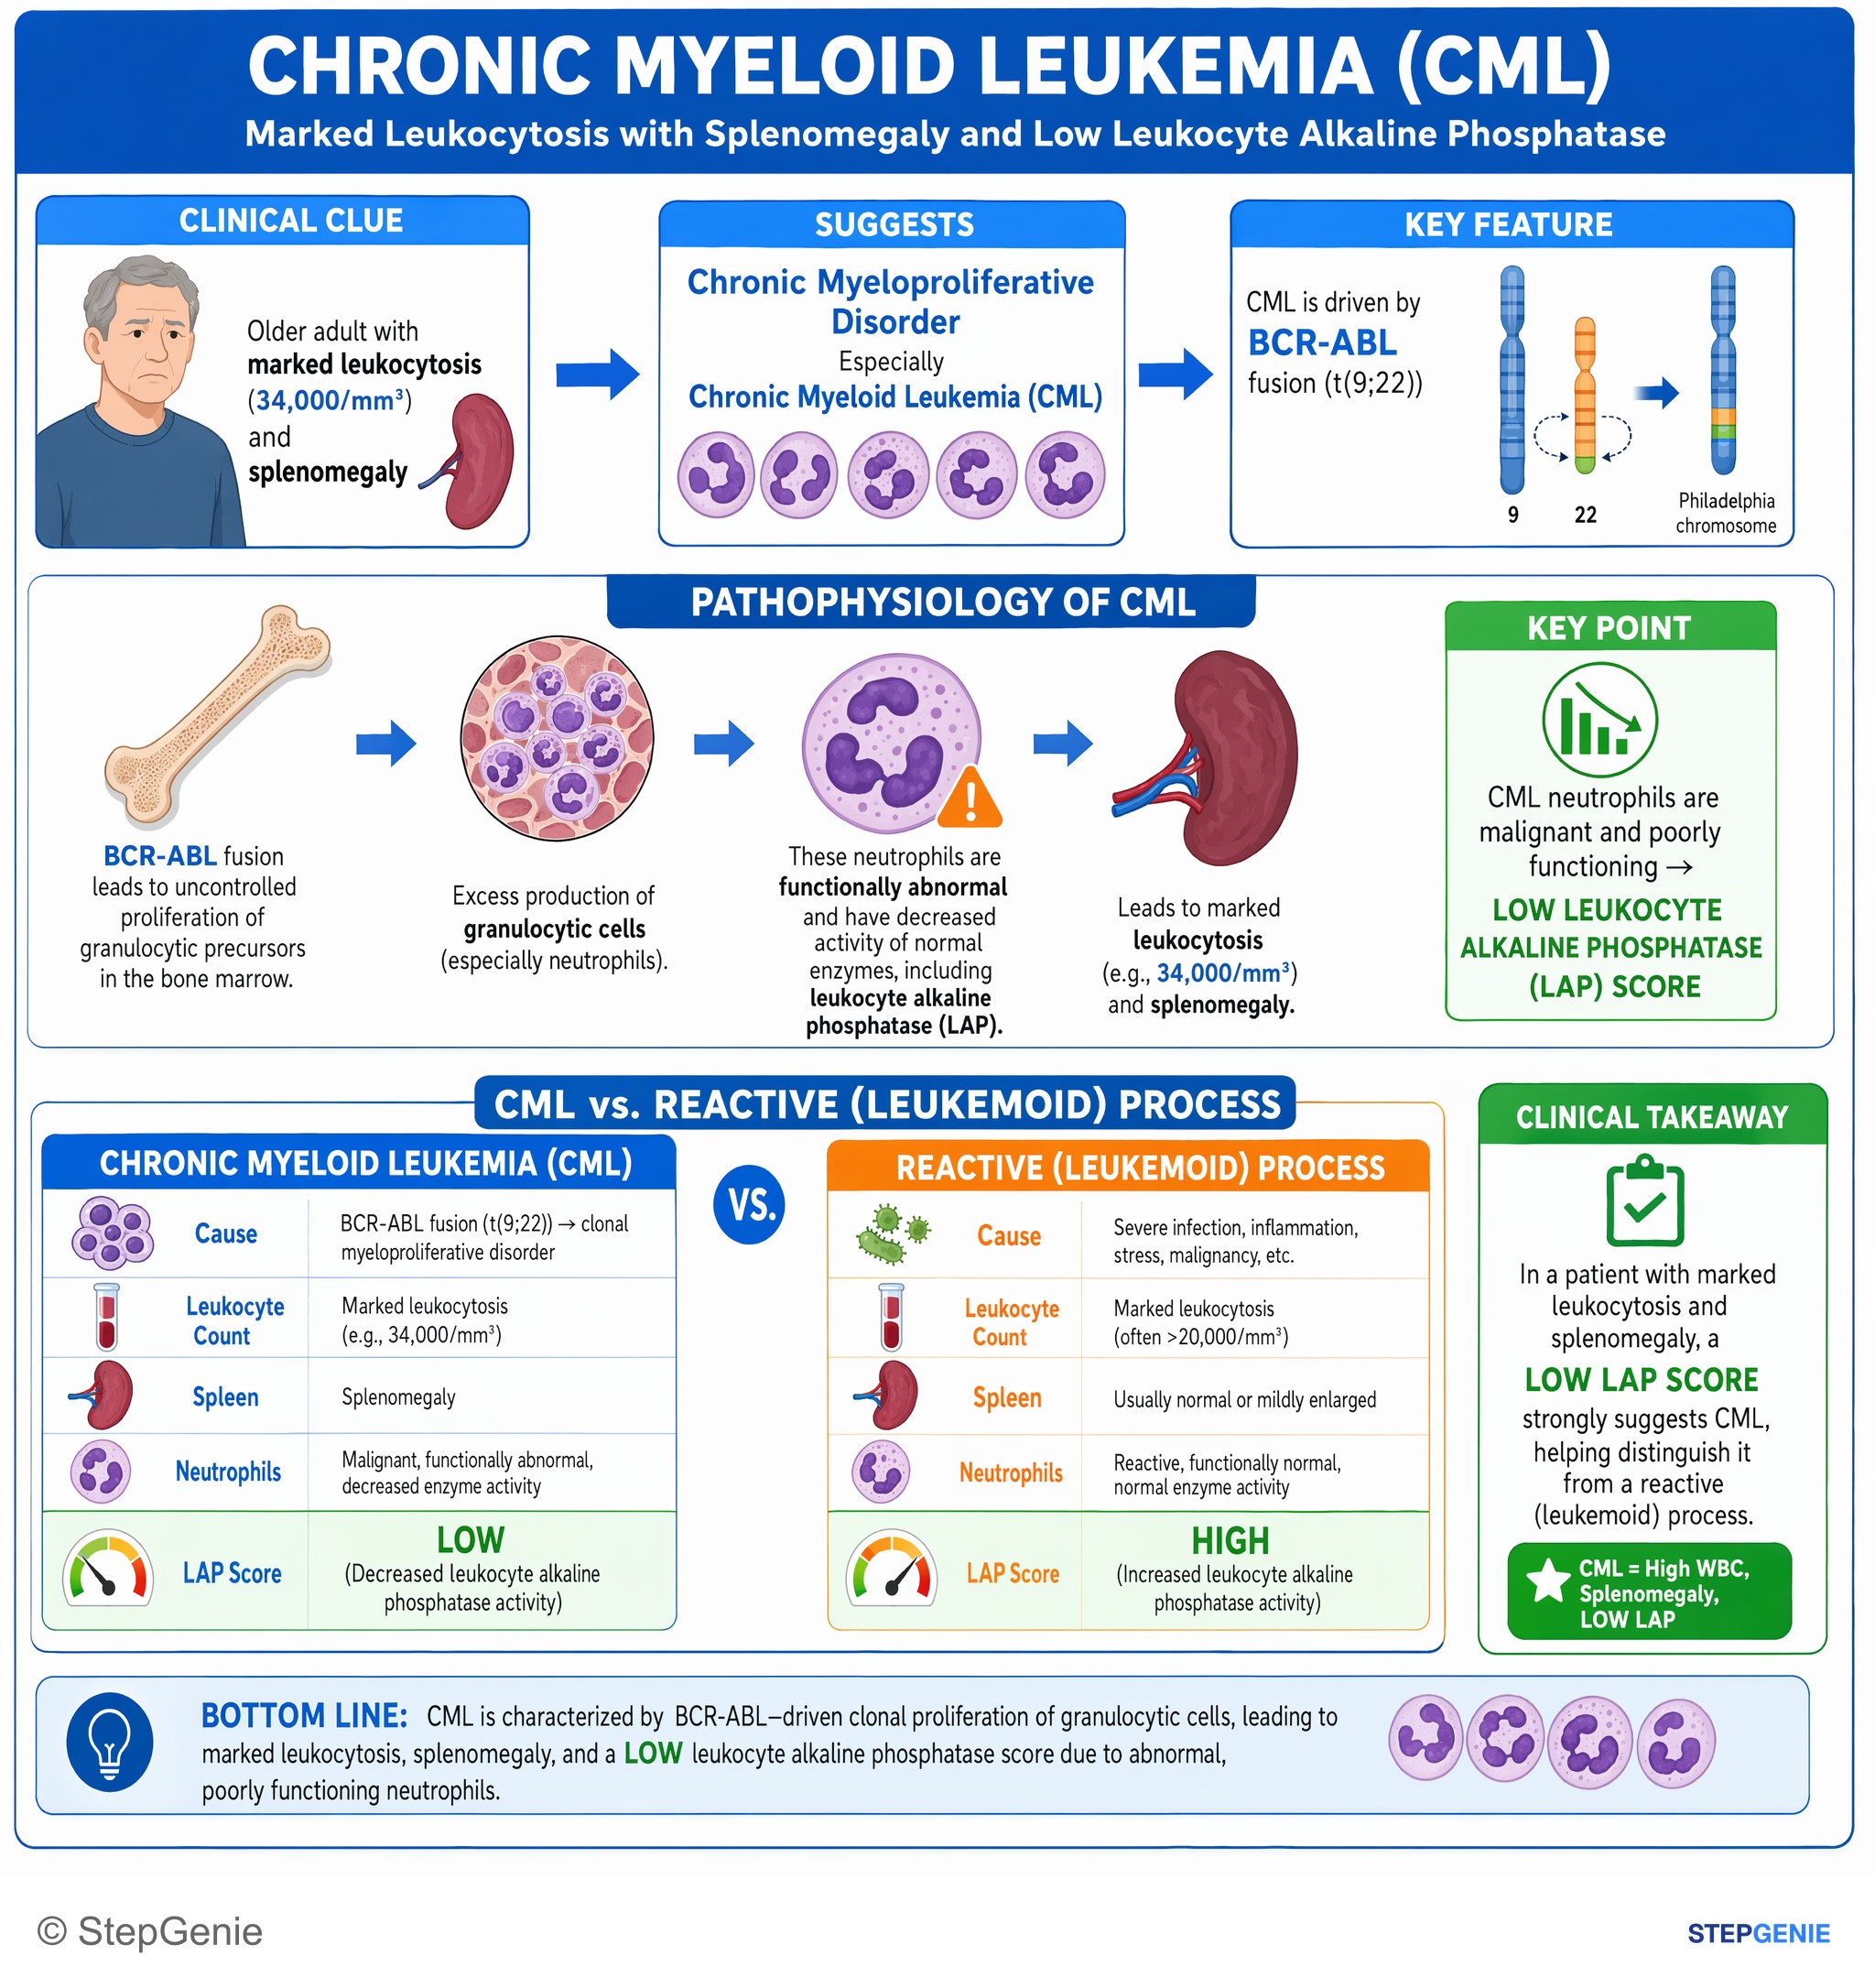
Chronic myeloid leukemia (CML): marked leukocytosis with splenomegaly and low leukocyte alkaline phosphatase due to malignant, poorly…
USMLE Step 1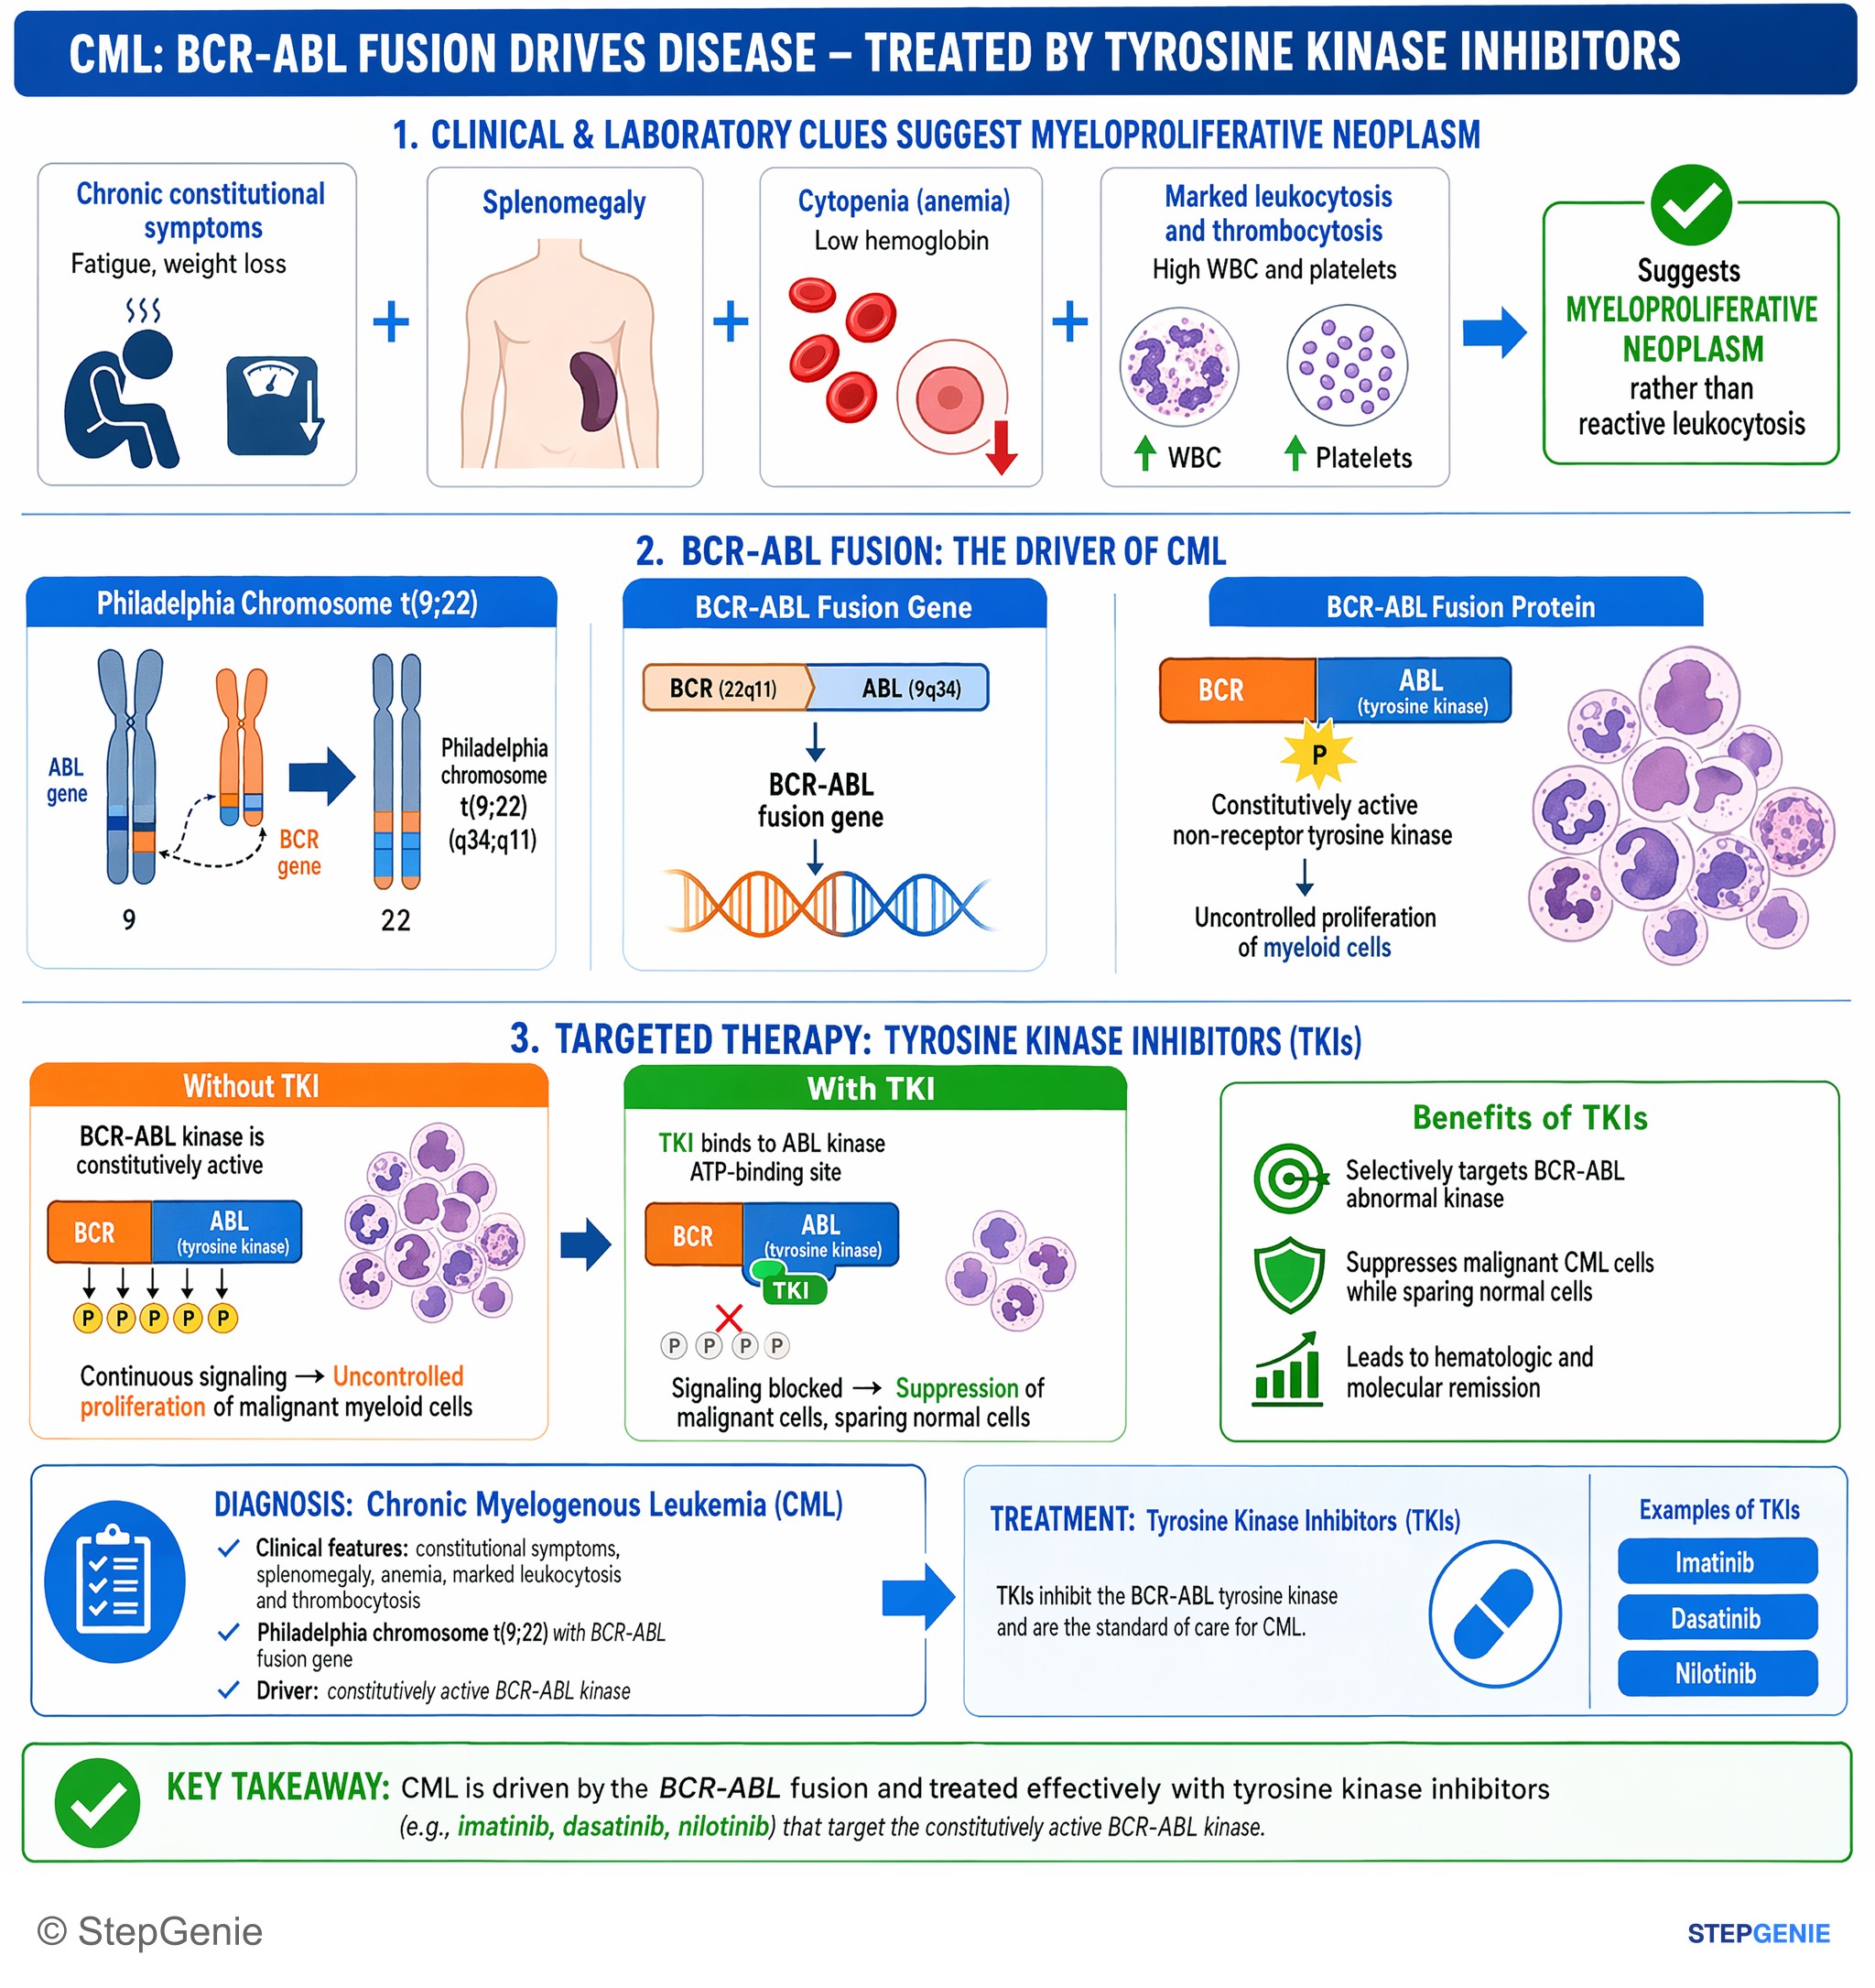
Chronic myelogenous leukemia (CML) with BCR-ABL fusion is treated with tyrosine kinase inhibitors (e.g., imatinib) targeting the…
USMLE Step 1Frequently Asked Questions
What causes chronic myeloid leukemia?
CML is caused by an acquired translocation between chromosomes 9 and 22, t(9;22), in a blood-forming stem cell. It joins the ABL1 gene from chromosome 9 to BCR on chromosome 22, creating the Philadelphia chromosome and the BCR::ABL1 fusion protein, a tyrosine kinase that is always switched on. The kinase drives myeloid proliferation, reduces adherence of leukemic cells to the marrow stroma and protects them from apoptosis, producing a very high count of granulocytes at every stage of maturation.
How do you tell CML from a leukemoid reaction?
Both can cause a very high white count with a left shift. CML is a clonal neoplasm: the smear shows granulocytes at every stage with basophilia and eosinophilia, the spleen is often enlarged, the leukocyte alkaline phosphatase (LAP) score is low and BCR::ABL1 is present. A leukemoid reaction is a reactive response to severe infection, inflammation or another cancer: the neutrophils are mostly mature, often with toxic changes, the LAP score is high and BCR::ABL1 is absent.
What is the first-line treatment for CML?
First-line treatment for chronic-phase CML is an oral BCR::ABL1 tyrosine kinase inhibitor: imatinib, dasatinib, nilotinib, bosutinib or asciminib, which has FDA accelerated approval for newly diagnosed chronic-phase disease. The choice depends on comorbidities, side effects, cost and risk score. Second-generation TKIs give faster, deeper molecular responses than imatinib, but randomized trials have not shown an overall survival advantage. Ponatinib is not recommended for newly diagnosed chronic phase.
What are the phases of CML?
CML classically has three phases. Chronic phase (fewer than 10% blasts) is where about 85% of patients are diagnosed, and it responds well to TKIs. Accelerated phase (10-19% blasts) brings rising basophils, worsening blood counts, a growing spleen and new chromosomal changes. Blast phase (20% or more blasts, or blasts outside the marrow) behaves like acute leukemia, myeloid in about 60% and lymphoid in about 30%. The WHO 2022 classification dropped the accelerated phase in favor of high-risk features.
What is the T315I mutation in CML and how is it treated?
T315I is a point mutation in the ABL1 kinase domain of BCR::ABL1, often called the gatekeeper mutation. It makes CML resistant to imatinib, dasatinib, nilotinib and bosutinib. The approved options are ponatinib, a third-generation TKI with boxed warnings for arterial occlusion, venous thromboembolism, heart failure and liver toxicity, and, in chronic phase, asciminib at a higher dose of 200 mg twice daily. Allogeneic stem cell transplant is reserved for accelerated or blast phase disease or resistance to the available TKIs.
Can patients with CML stop treatment?
Some can. The 2025 European LeukemiaNet recommendations allow a supervised attempt at treatment-free remission in motivated patients in first chronic phase who have had more than 5 years of TKI therapy (more than 4 with a second-generation TKI) and a deep molecular response (MR4, BCR::ABL1 0.01% or lower) for more than 2 years, with reliable PCR monitoring. About 40-50% stay in remission off treatment. If major molecular response is lost, the TKI is restarted, and almost all patients respond again.