Heparin-induced thrombocytopenia (HIT) is one of those “don’t miss” diagnoses: the platelet count drops, but the patient clots. If you can rapidly recognize the timing, the mechanism, and the correct next step, you’ll pick up easy points on Step—and avoid dangerous management mistakes on the wards.
Tip #1: Think “HIT = Hypercoagulable thrombocytopenia” (not a bleeding problem)
One-liner: HIT is an IgG-mediated reaction against PF4–heparin complexes that activates platelets, causing thrombosis despite thrombocytopenia.
The core mechanism (Step-friendly)
- Heparin binds platelet factor 4 (PF4) → forms a complex
- Patient makes IgG antibodies to the PF4–heparin complex
- IgG binds Fc receptors on platelets → platelet activation + consumption
- Activated platelets release procoagulant microparticles → arterial and venous thrombosis
High-yield clinical consequences
- Thrombosis is the main danger (DVT/PE, limb ischemia, stroke, MI)
- Platelets typically fall ≥ 50% from baseline
- Bleeding is uncommon (platelets usually not low enough to bleed)
Tip #2: Timing + % drop beats “absolute platelet number”
One-liner: HIT usually shows up 5–10 days after starting heparin (or within 24 hours if previously exposed).
The classic timing patterns
- Typical onset: day 5–10
- Rapid-onset HIT: within 24 hours if patient had heparin exposure in the last ~100 days (preformed antibodies)
- Delayed-onset HIT: thrombocytopenia and thrombosis can occur after stopping heparin (antibodies persist)
Quick “when to suspect” checklist
Suspect HIT if:
- Platelets drop ≥ 50%, even if nadir is still >150k
- New thrombosis occurs while on heparin
- Skin necrosis at injection sites or systemic reaction after heparin bolus
Mini-table: HIT vs DIC vs TTP/HUS (fast differentiation)
| Feature | HIT | DIC | TTP/HUS |
|---|---|---|---|
| Platelets | ↓ (often moderate; ≥50% drop) | ↓ | ↓ |
| PT/PTT | Usually normal | Prolonged | Normal |
| Fibrinogen | Normal | ↓ | Normal |
| D-dimer | May be ↑ | ↑↑ | Normal/variable |
| Smear | No schistocytes (typically) | ± schistocytes | Schistocytes |
| Key clue | Thrombosis on heparin | Sepsis/trauma/malignancy | Neuro/renal + MAHA |
Tip #3: Management is “Stop heparin + start a non-heparin anticoagulant” (and don’t give warfarin yet)
One-liner: If HIT is suspected, stop all heparin immediately and anticoagulate with a non-heparin agent—because the patient is at high risk of clotting right now.
What to do immediately (USMLE algorithm)
- Stop heparin (including heparin flushes and heparin-coated catheters)
- Start a non-heparin anticoagulant, such as:
- Argatroban (direct thrombin inhibitor; IV; hepatically cleared)
- Bivalirudin (often used in PCI/cardiac settings)
- Fondaparinux (factor Xa inhibitor; not heparin, low cross-reactivity)
- DOACs (increasingly used in practice; Step questions still love argatroban/bivalirudin)
- Order confirmatory testing:
- PF4 ELISA (sensitive)
- Serotonin release assay (SRA) (specific; classic “confirmatory”)
Two classic pitfalls to avoid
- Do NOT start warfarin during acute HIT
- Early warfarin drops protein C first → can worsen thrombosis and cause skin necrosis
- If already given, reverse with vitamin K
- Do NOT transfuse platelets unless there’s life-threatening bleeding
- You can “fuel the fire” by providing more platelets to activate
A quick mnemonic + visual to make HIT stick
Mnemonic: “HIT = Heparin → Immune → Thrombosis”
- Heparin exposure
- Immune IgG to PF4–heparin
- Thrombosis (the scary part)
Tiny visual (burn it into memory)
Heparin + PF4 → IgG → platelet activation → clots
…and the platelet count drops as a side effect of activation/consumption.
The “3-second Step takeaway”
If platelets fall 5–10 days after heparin and the patient clots, it’s HIT: stop heparin and start argatroban/bivalirudin/fondaparinux—not warfarin.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
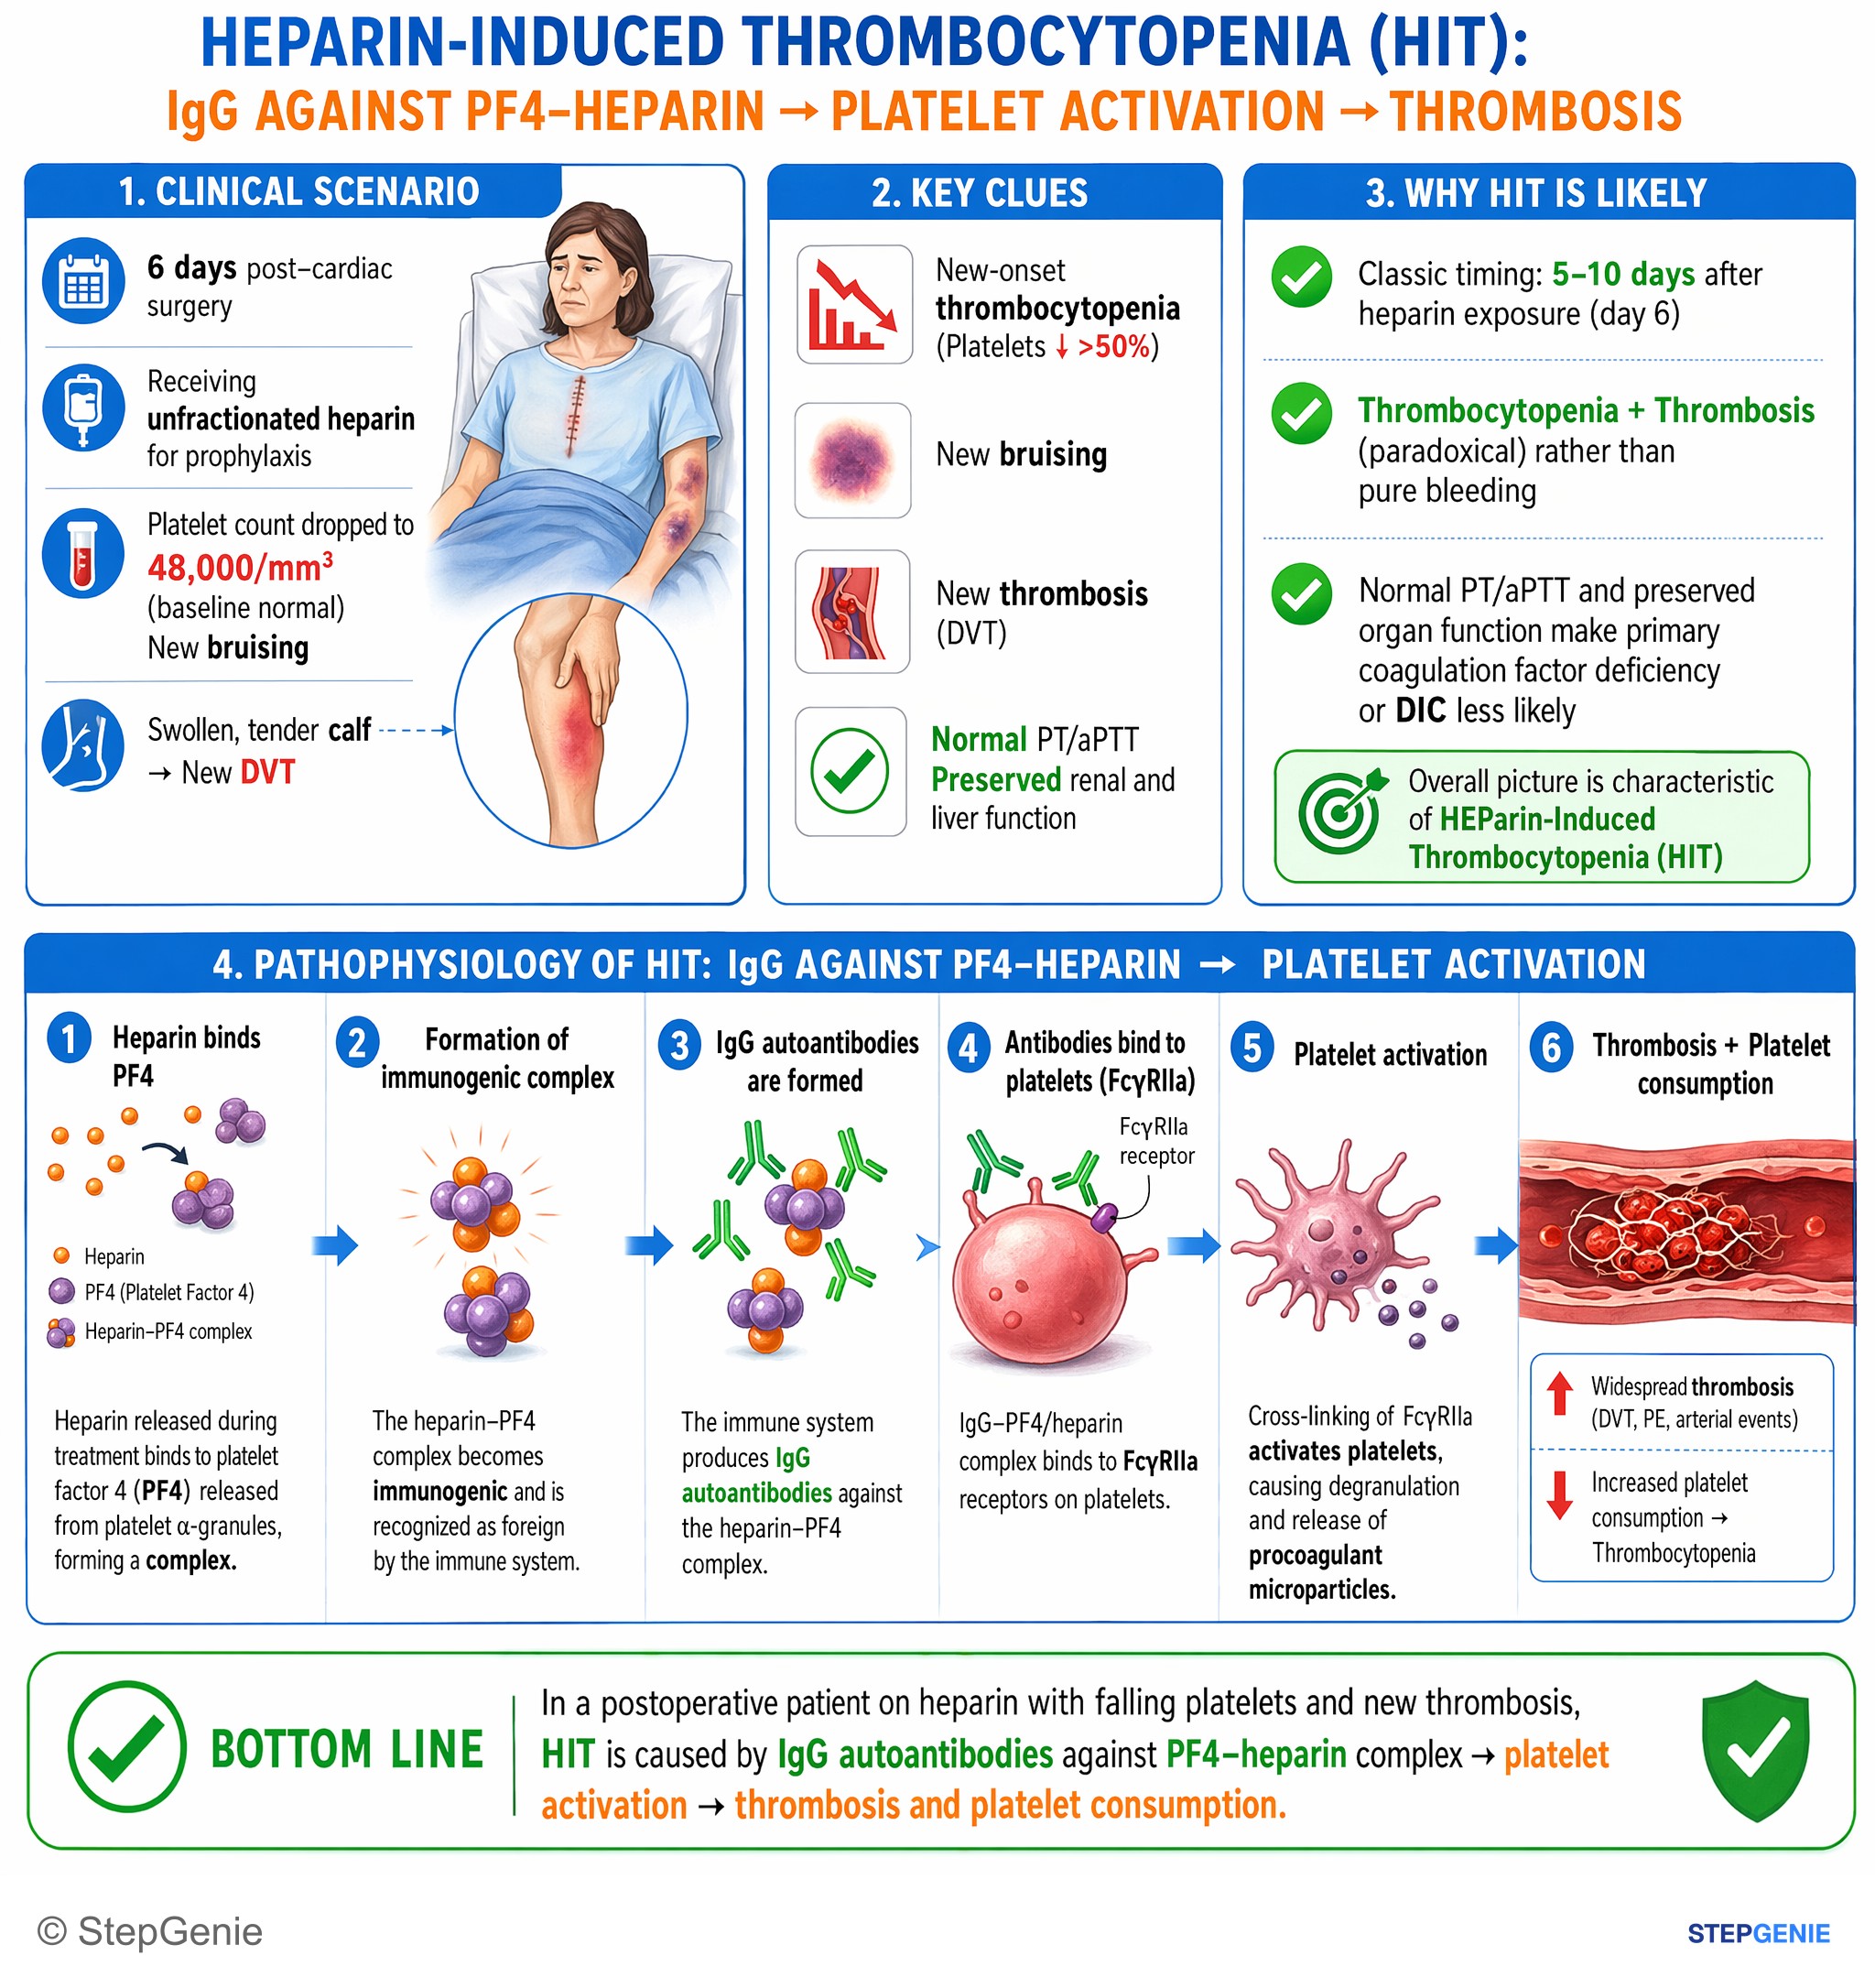
Heparin-induced thrombocytopenia (HIT): postoperative patient on heparin, falling platelets, thrombosis; due to IgG against PF4–heparin →…
USMLE Step 1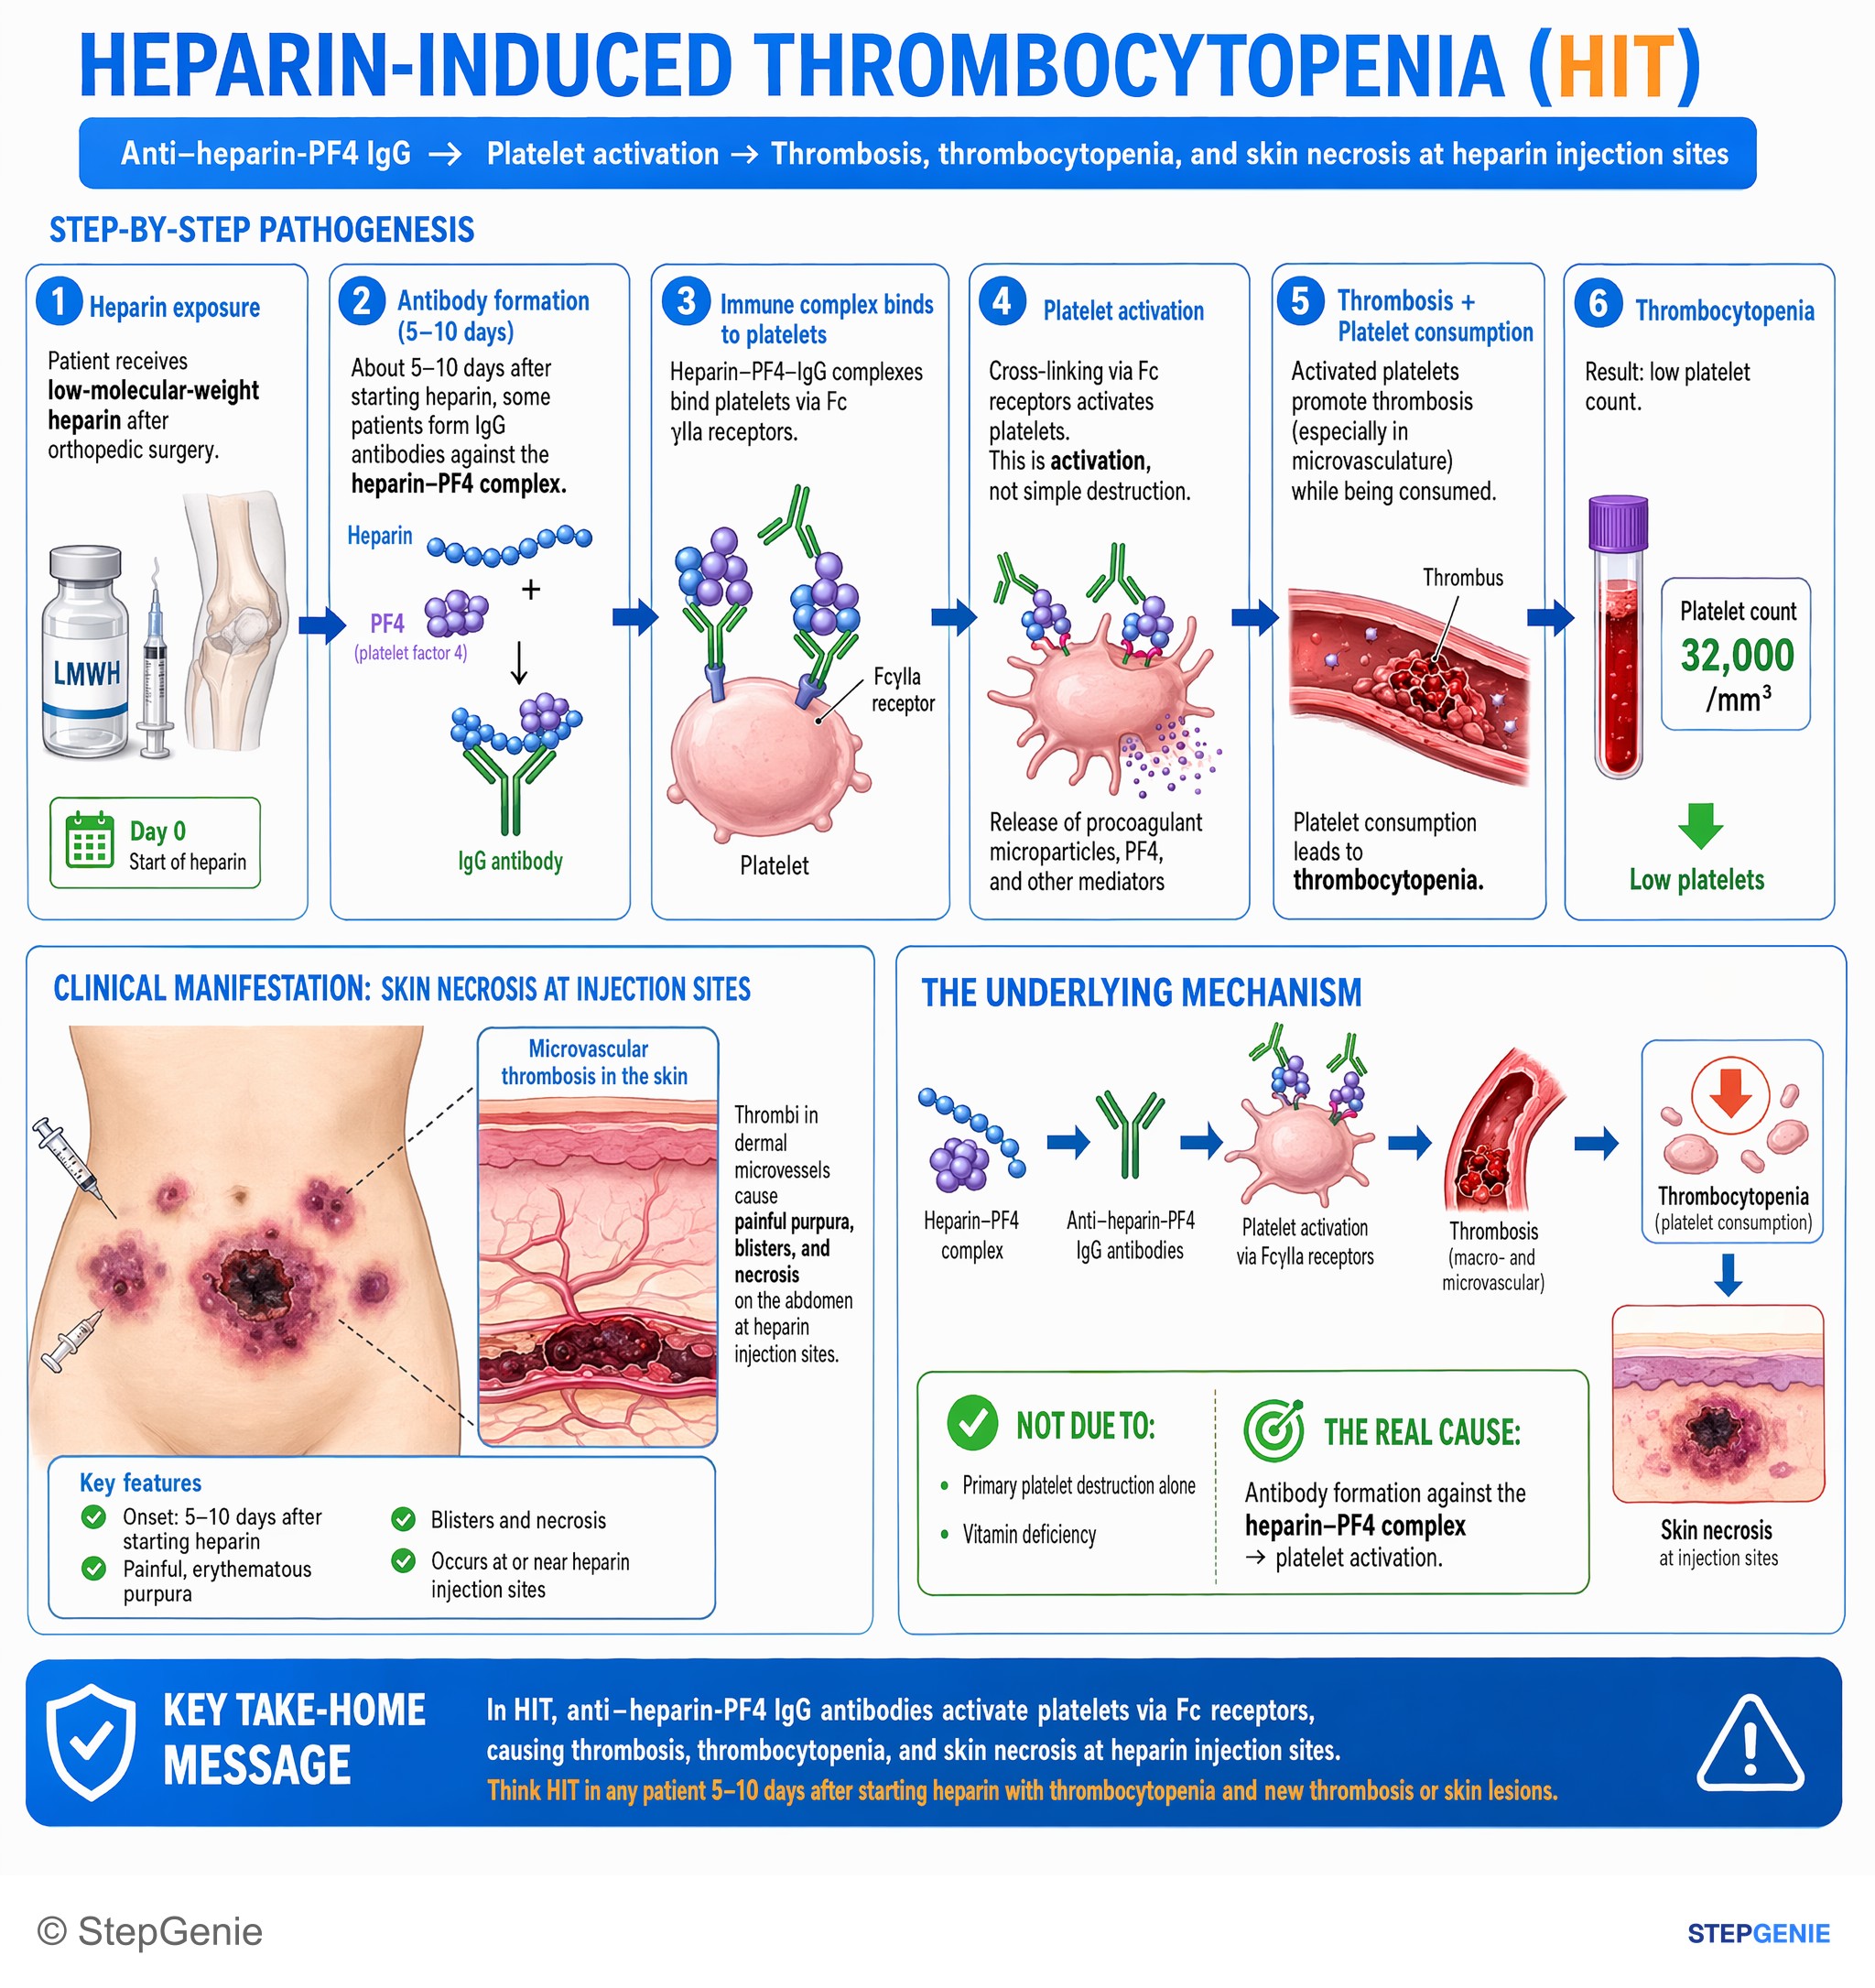
Heparin-induced thrombocytopenia (HIT): anti–heparin-PF4 IgG → platelet activation → thrombosis, thrombocytopenia, and skin necrosis at…
USMLE Step 1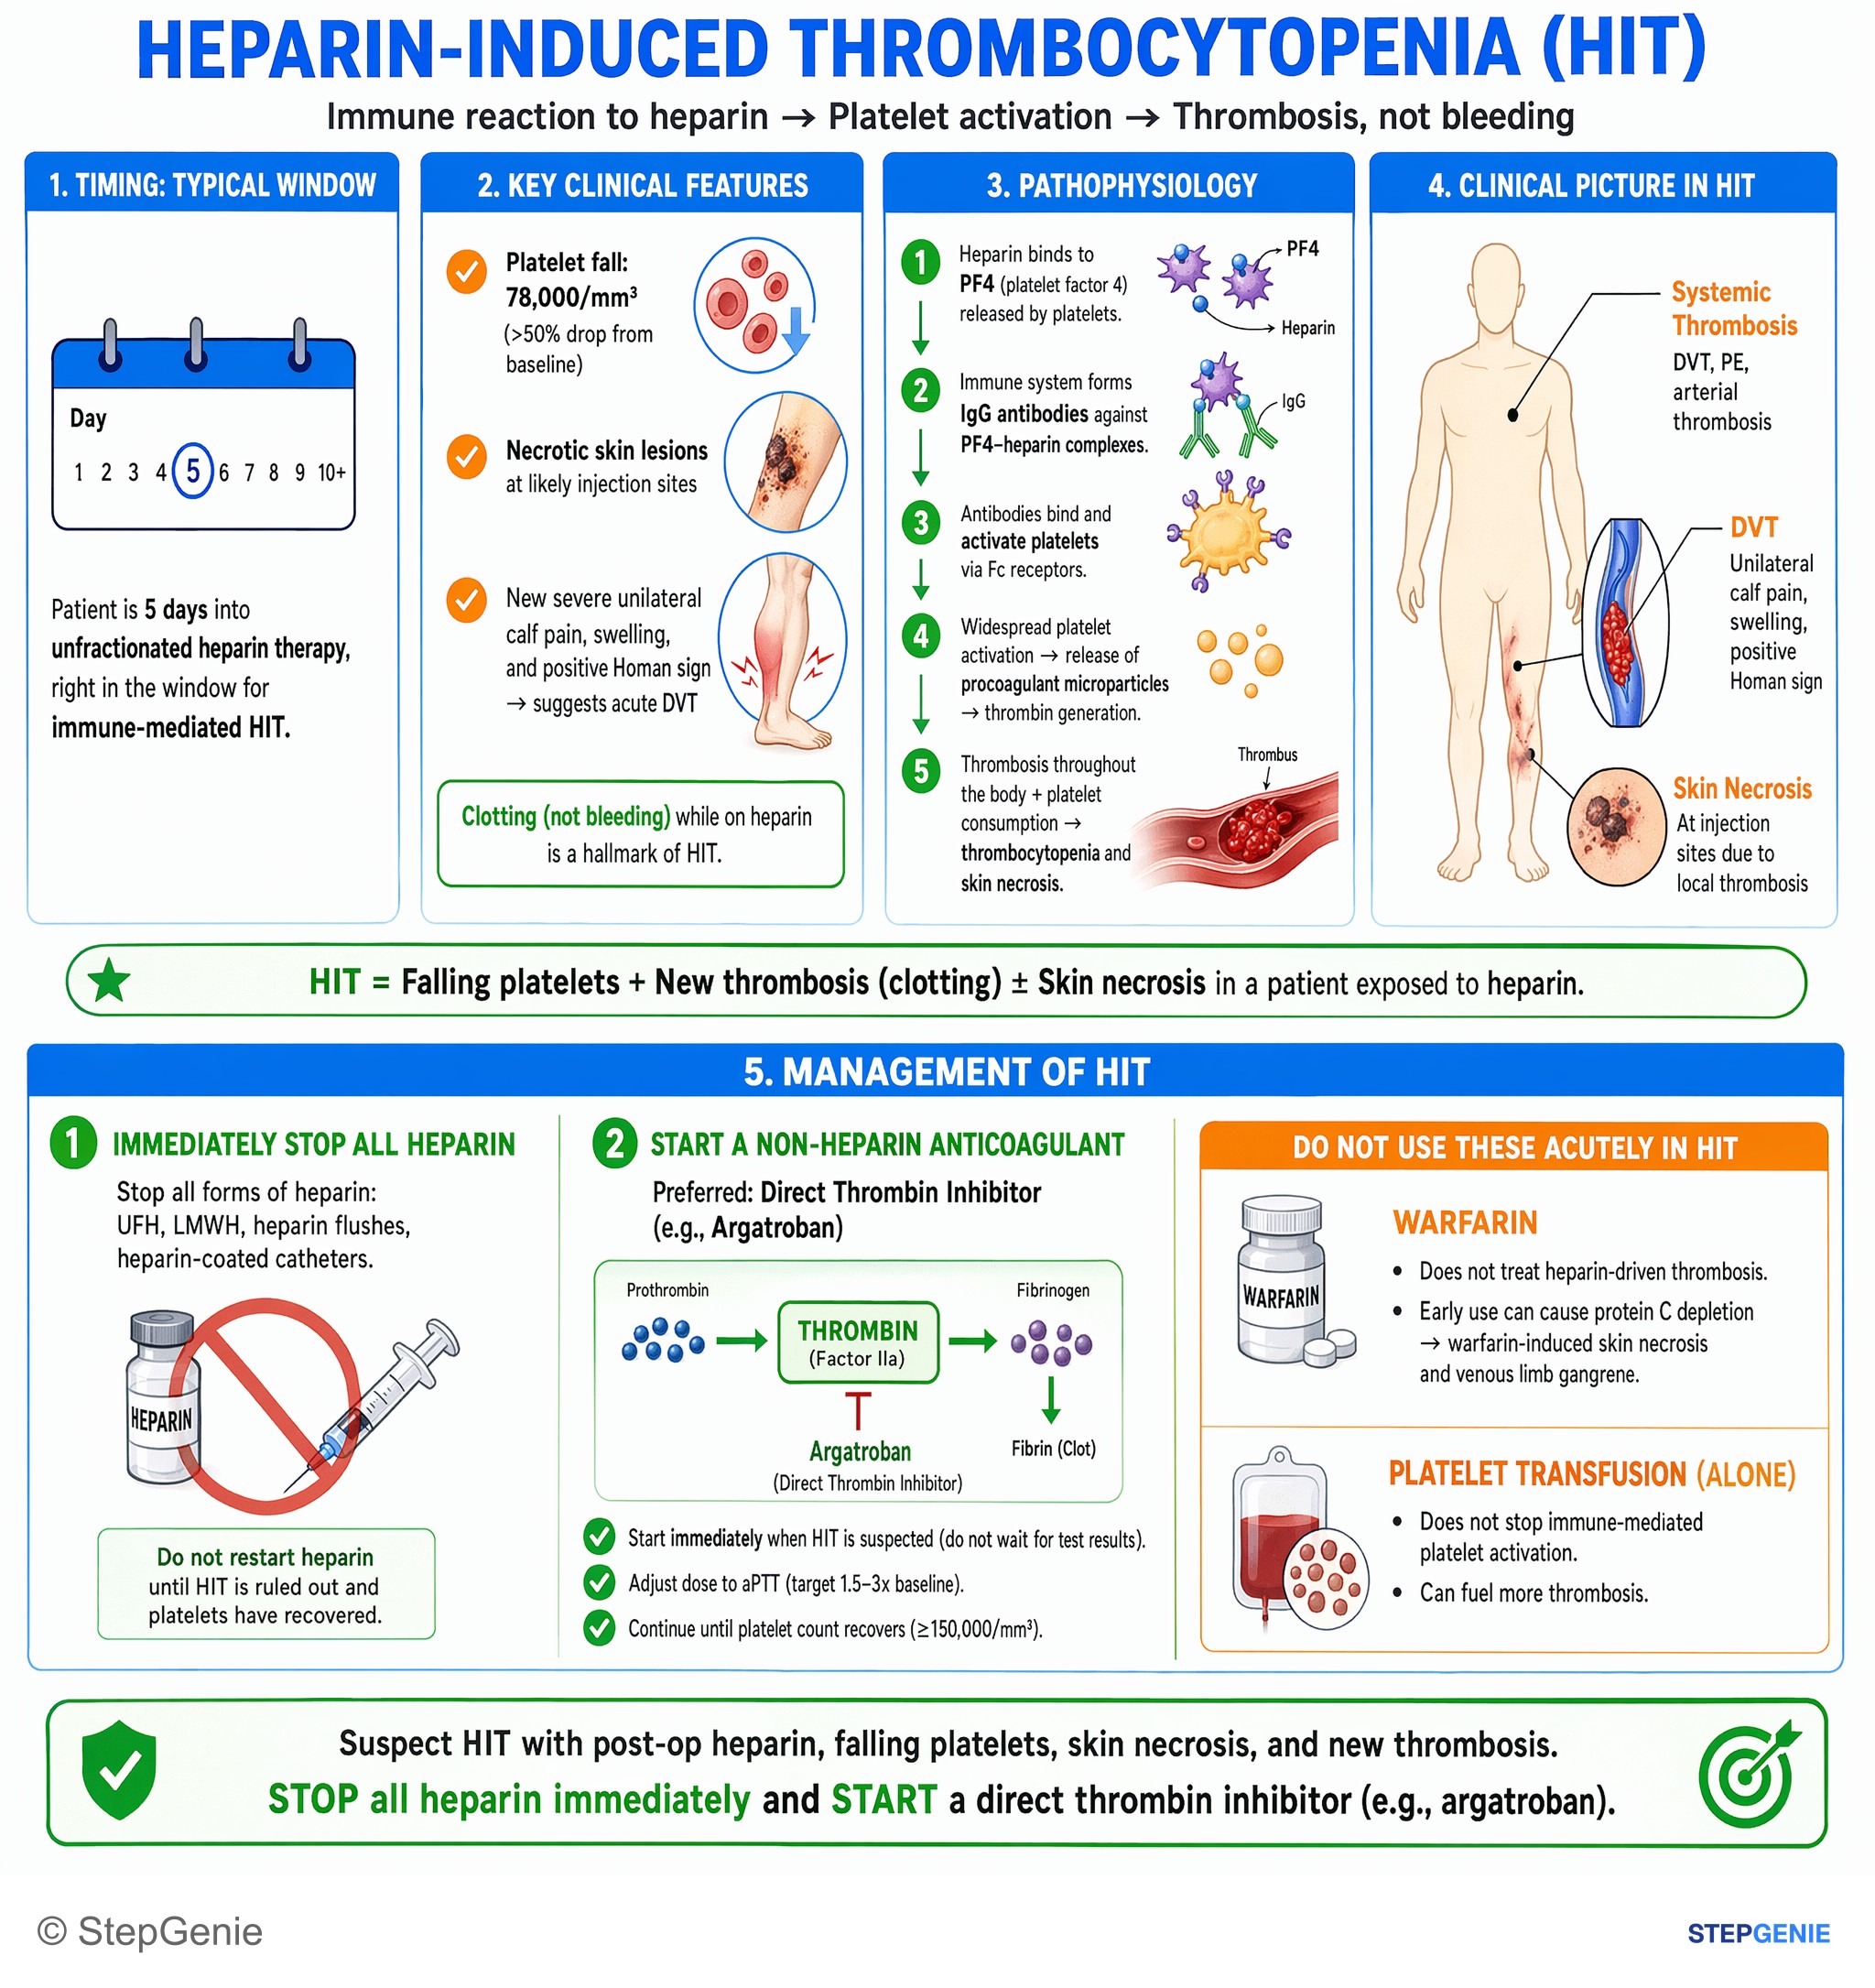
Heparin-induced thrombocytopenia: post-op heparin, falling platelets, skin necrosis, new thrombosis → stop heparin and start direct…
USMLE Step 2Frequently Asked Questions
Why does heparin-induced thrombocytopenia cause clotting instead of bleeding?
Heparin-induced thrombocytopenia causes thrombosis, not primarily bleeding, because it is an IgG-mediated reaction against PF4-heparin complexes that activates platelets. Heparin binds platelet factor 4, antibodies form against that complex, and the antibody-coated complex activates platelets through Fc receptors. Those activated platelets are consumed, so the count falls, but they also release procoagulant microparticles that drive arterial and venous thrombosis.
When should you suspect HIT after starting heparin?
You should suspect HIT when platelets fall by at least 50% about 5 to 10 days after starting heparin, even if the absolute platelet count is still above 150,000. It can also appear within 24 hours if the patient was exposed to heparin in the last roughly 100 days, and delayed-onset HIT can occur even after heparin has been stopped. New thrombosis on heparin is a major clue.
How do you tell HIT from DIC or TTP/HUS on exam questions?
HIT is suggested by thrombosis occurring on heparin with a moderate platelet fall, usually with normal PT/PTT, normal fibrinogen, and typically no schistocytes on smear. DIC instead has prolonged PT/PTT, low fibrinogen, and often a trigger like sepsis, trauma, or malignancy. TTP/HUS has thrombocytopenia too, but schistocytes are a key clue, along with neuro or renal findings and microangiopathic hemolytic anemia.
What is the first step in management when HIT is suspected?
The first step is to stop all heparin immediately and start a non-heparin anticoagulant. This includes stopping heparin flushes and heparin-coated catheters, because the patient is at high risk of clotting right now. Options listed include argatroban, bivalirudin, fondaparinux, and sometimes DOACs, while confirmatory tests such as PF4 ELISA and the serotonin release assay can be ordered.
Why should you avoid warfarin and platelet transfusions in acute HIT?
Warfarin should be avoided in acute HIT because early warfarin lowers protein C first, which can worsen thrombosis and cause skin necrosis. If warfarin has already been given, it should be reversed with vitamin K. Platelet transfusions should also be avoided unless there is life-threatening bleeding, because adding more platelets can provide more substrate for activation and worsen the prothrombotic process.