Sickle cell disease comes from a single amino acid swap in β-globin: valine replaces glutamic acid at position 6 (Glu6Val), producing hemoglobin S (HbS), which polymerizes when deoxygenated and bends red cells into rigid sickles. That one change explains the exam: chronic hemolysis (normocytic anemia, reticulocytosis, high indirect bilirubin and LDH, low haptoglobin), vaso-occlusion (pain crises, acute chest syndrome, stroke, priapism) and functional asplenia (Howell-Jolly bodies, pneumococcal sepsis, Salmonella osteomyelitis). It is autosomal recessive; on electrophoresis no HbA means disease (HbSS), while more HbA than HbS means trait (HbAS).
The question
A 17-year-old boy comes to the emergency department with severe pain in his lower back and both thighs that began two days after a cold; he has been drinking little. He has had similar admissions since early childhood. Temperature is 37.4 °C, pulse 104/min and SpO₂ 97% on room air. He has scleral icterus, and no spleen tip is palpable. Hemoglobin is 7.6 g/dL, MCV 88 fL, reticulocytes 11%, total bilirubin 3.4 mg/dL (mostly indirect), LDH high and haptoglobin undetectable; the direct antiglobulin test (DAT) is negative. The smear shows crescent-shaped cells, target cells and small round nuclear remnants inside some red cells.
Which molecular defect best explains his disease?
- A. Lysine replaces glutamic acid at position 6 of β-globin
- B. Reduced synthesis of structurally normal β-globin chains
- C. Valine replaces glutamic acid at position 6 of β-globin
- D. A spectrin or ankyrin mutation that weakens the red cell membrane
- E. IgG autoantibodies against red cell surface antigens
- F. Deficient glucose-6-phosphate dehydrogenase activity
Answer: C, hemoglobin S
Swapping a charged glutamate for a hydrophobic valine lets deoxygenated HbS molecules stick together into long, rigid polymers that distort the cell. The clues:
- Normocytic anemia with 11% reticulocytes: hemolysis with a working marrow. Reticulocytosis of 10% or more is common; microcytosis would suggest a coexisting thalassemia.
- High indirect bilirubin and LDH, absent haptoglobin, negative DAT: nonimmune hemolysis.
- No palpable spleen in a teen with severe disease: autosplenectomy. Splenomegaly is common in young children, but repeated infarction and fibrosis often leave the adult spleen atrophic.
- Nuclear remnants (Howell-Jolly bodies): functional asplenia.
- Pain after a viral illness and poor fluid intake: classic crisis triggers.
Why the other answers are wrong
| Choice | Diagnosis | Why it doesn't fit |
|---|---|---|
| A. Lysine at position 6 | Hemoglobin C | Same position, different amino acid: homozygous HbC gives mild hemolysis, mild microcytosis, splenomegaly and target cells, without sickling |
| B. Less β-globin | β-thalassemia | A quantitative defect: microcytosis, HbA2 above about 3.5% in β-thalassemia minor, often massive splenomegaly in thalassemia major (alpha vs beta thalassemia table) |
| D. Spectrin or ankyrin | Hereditary spherocytosis | Spherocytes, high MCHC, splenomegaly in almost every patient, negative DAT (hereditary spherocytosis overview) |
| E. IgG autoantibodies | Warm autoimmune hemolytic anemia | DAT positive for IgG (sometimes C3) with microspherocytes; linked to SLE, CLL, lymphoma and methyldopa |
| F. G6PD deficiency | G6PD deficiency | X-linked; episodic hemolysis after oxidants such as primaquine, dapsone, fava beans or infection, with bite cells and Heinz bodies (G6PD deficiency triggers) |
Pathophysiology in one chain
HbS + low oxygen → polymer gel → rigid sickled cell → hemolysis and vaso-occlusion.
- Hemolysis: fragile sickled cells break up in the circulation, causing anemia, jaundice and gallstones.
- Vaso-occlusion: stiff cells stick to the endothelium, provoke inflammation and vasoconstriction, and plug small vessels, causing ischemic injury to bone, lung, brain, spleen, kidney and penis.
- Triggers: low oxygen (including high altitude), dehydration, fever and infection, extreme heat or cold, and stress.
- Why young infants are spared: fetal hemoglobin (HbF, α2γ2) has no β chains, so it cannot sickle, and it wanes over the first months of life; most babies have no problems before about 5 or 6 months.
Crises and complications by age
| When | Complication | Stem clue | Management |
|---|---|---|---|
| Young children | Dactylitis (hand-foot syndrome) | Painful, swollen hands and feet | Analgesia, as for other vaso-occlusive pain |
| Young children, before the spleen fibroses | Acute splenic sequestration | Rapidly enlarging spleen, hemoglobin down at least 2 g/dL, hypovolemia | Immediate IV fluids; transfuse, avoiding over-transfusion |
| Any age, most common in childhood | Acute chest syndrome | Fever, chest pain, cough, hypoxemia and a new pulmonary infiltrate | IV cephalosporin plus oral macrolide, O₂ to SpO₂ above 95%, incentive spirometry, transfusion |
| Any age, with parvovirus B19 infection | Aplastic crisis | Hemoglobin below baseline with reticulocytes under 1% | Red cell transfusion; droplet precautions |
| Childhood (screen ages 2–16) | Ischemic stroke | Focal deficit; high transcranial Doppler velocity | Exchange transfusion, then chronic transfusion |
| Any age | Vaso-occlusive pain crisis | Bone pain after infection, dehydration or cold | Rapid opioid analgesia |
| Mostly adolescence and adulthood | Chronic organ damage | Avascular necrosis, priapism, ankle ulcers, gallstones, retinopathy, pulmonary hypertension, renal papillary necrosis | Organ-specific care |
Functional asplenia and infection
Repeated splenic infarction leaves patients functionally asplenic: Howell-Jolly bodies appear, and encapsulated bacteria (Streptococcus pneumoniae, Haemophilus influenzae, Neisseria meningitidis) are poorly cleared. Such infections are especially common in early childhood.
- Fever of 38.5 °C (101.3 °F) or higher is an emergency: blood culture, CBC and reticulocyte count, and in children prompt empiric parenteral antibiotics covering S. pneumoniae and gram-negative enteric organisms (NHLBI 2014).
- Prevention: in children with HbSS, oral penicillin 125 mg twice daily under age 3 and 250 mg twice daily from age 3, stopped at age 5 unless the child has had a splenectomy or invasive pneumococcal infection (NHLBI 2014), plus pneumococcal, H. influenzae and meningococcal vaccines.
- Salmonella osteomyelitis is the classic sickle cell association, although Staphylococcus aureus is the most common cause of osteomyelitis overall.
Sickle cell trait vs sickle cell disease
In the United States, about 8% of people with African ancestry have trait and about 0.3% have sickle cell anemia.
| Genotype | Electrophoresis | Clinical picture |
|---|---|---|
| HbAS (trait) | More HbA than HbS | Not anemic; no hemolysis, and usually no pain crises |
| HbSS (sickle cell anemia) | HbS with variable HbF, no HbA | Usually severe |
| HbS-β⁰-thalassemia | HbS, no HbA, microcytosis | Severe; counted as sickle cell anemia |
| HbSC | HbS and HbC, no HbA | Variable; can be as severe as HbSS |
| HbS-β⁺-thalassemia | HbS with some HbA | Generally milder |
Trait is usually silent; the tested exceptions:
- Kidney: hyposthenuria (poor urine concentration) is common; self-limited hematuria, usually from the left kidney; papillary necrosis, less often than in HbSS; and a higher risk of chronic kidney disease.
- Renal medullary carcinoma: rare and aggressive, linked to sickle cell trait or disease, mostly in teens, young adults and males; hematuria is the most common sign, and many cases are found after spread.
- Extreme conditions: heat illness and muscle breakdown with intense exercise, and splenic infarction; dehydration, low oxygen and high altitude raise the risk. Pulmonary embolism risk is also higher.
Labs and diagnosis
- Blood: normocytic anemia, reticulocytosis, nucleated red cells; bilirubin usually about 2–4 mg/dL.
- Smear: sickle cells, target cells, Howell-Jolly bodies and polychromatic cells.
- Confirmation: hemoglobin electrophoresis, isoelectric focusing or HPLC, also used for newborn screening; solubility testing is unreliable in the first months of life.
Management: NHLBI 2014 and ASH 2020
Hydroxyurea raises HbF, which reduces sickling; it cuts pain crises by about 45% and lowers acute chest syndrome and transfusion needs. The NHLBI 2014 expert panel recommends offering it to infants from 9 months, children and adolescents with sickle cell anemia regardless of clinical severity, and treating adults with 3 or more moderate-to-severe pain crises in 12 months, pain that interferes with daily life, severe or recurrent acute chest syndrome, or severe symptomatic anemia. Monitor for neutropenia and thrombocytopenia.
Pain crisis: analgesia within 30 minutes of triage or 60 minutes of registration, reassessed every 15–30 minutes (NHLBI 2014; ASH 2020 sets a 1-hour target, reassessing every 30–60 minutes); IV fluids no faster than maintenance if euvolemic but unable to drink; incentive spirometry while awake. Transfusion does not help an uncomplicated crisis.
Transfusion (NHLBI 2014 unless stated):
- Acute chest syndrome: simple transfusion (10 mL/kg) if hemoglobin is more than 1 g/dL below baseline; urgent exchange transfusion for rapid progression (SpO₂ below 90% despite oxygen, increasing distress, spreading infiltrates or falling hemoglobin).
- Stroke: exchange transfusion for acute stroke, then monthly transfusions to keep HbS below 30%. Screen children with sickle cell anemia by transcranial Doppler yearly from age 2 to at least 16; conditional (170–199 cm/s) or elevated (above 200 cm/s) velocities mean referral to a transfusion specialist, and elevated velocities warrant chronic transfusion.
- Surgery: in sickle cell anemia, transfuse to hemoglobin 10 g/dL before general anesthesia; ASH 2020 suggests preoperative transfusion for surgery under general anesthesia lasting over 1 hour.
- Safety: match for Rh (C, E) and K antigens (also a strong ASH 2020 recommendation), monitor iron overload, and suspect a delayed hemolytic transfusion reaction if anemia, pain or jaundice appears within 3 weeks.
Newer options: L-glutamine (age 5 and older) and the anti-P-selectin antibody crizanlizumab (16 and older) reduce pain crises; voxelotor was withdrawn in September 2024. Stem cell transplant can cure selected patients, and two gene therapies were approved in December 2023 for ages 12 and older: exagamglogene autotemcel (CRISPR editing that reactivates HbF) and lovotibeglogene autotemcel.
Exam traps
- Big spleen plus a sudden hemoglobin drop in a young child is sequestration; an absent spleen in a teen is autosplenectomy.
- Reticulocytes under 1% during an anemic crisis suggest aplastic crisis (parvovirus B19), not faster hemolysis.
- Trait carriers are not anemic; hematuria in a young adult with trait: consider renal medullary carcinoma.
- Don't transfuse for an uncomplicated pain crisis, and NHLBI 2014 advises against it as immediate treatment of priapism (lasting 4 hours or more: hydration, analgesia, urology); do use exchange transfusion for stroke and rapidly progressing acute chest syndrome.
Key takeaways
- Glu6Val → HbS polymerizes when deoxygenated → hemolysis, vaso-occlusion, functional asplenia.
- No HbA = disease; more HbA than HbS = trait.
- Asplenia: Howell-Jolly bodies, encapsulated organisms, Salmonella osteomyelitis; penicillin until age 5 plus vaccines.
- Hydroxyurea raises HbF; NHLBI 2014 offers it in sickle cell anemia from 9 months regardless of severity.
- Exchange transfusion for stroke and severe acute chest syndrome; match C, E and K.
Sources
- Sickle Cell Disease — Merck Manual Professional
- NHLBI 2014 Expert Panel Report on sickle cell disease (quick guide)
- ASH 2020 sickle cell disease guidelines: acute and chronic pain (snapshot)
- ASH 2020 sickle cell disease guidelines: transfusion support (pocket guide)
- Sickle Cell Disease: Treatment — NHLBI
- Sickle Cell Disease: Symptoms — NHLBI
- HBB gene — MedlinePlus Genetics
- What Is Sickle Cell Trait? — CDC
- Renal Medullary Carcinoma — National Cancer Institute
- Overview of Hemolytic Anemia — Merck Manual Professional
- Overview of the Spleen — Merck Manual Professional
- Osteomyelitis — Merck Manual Professional
- Hemoglobin C Disease — Merck Manual Professional
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
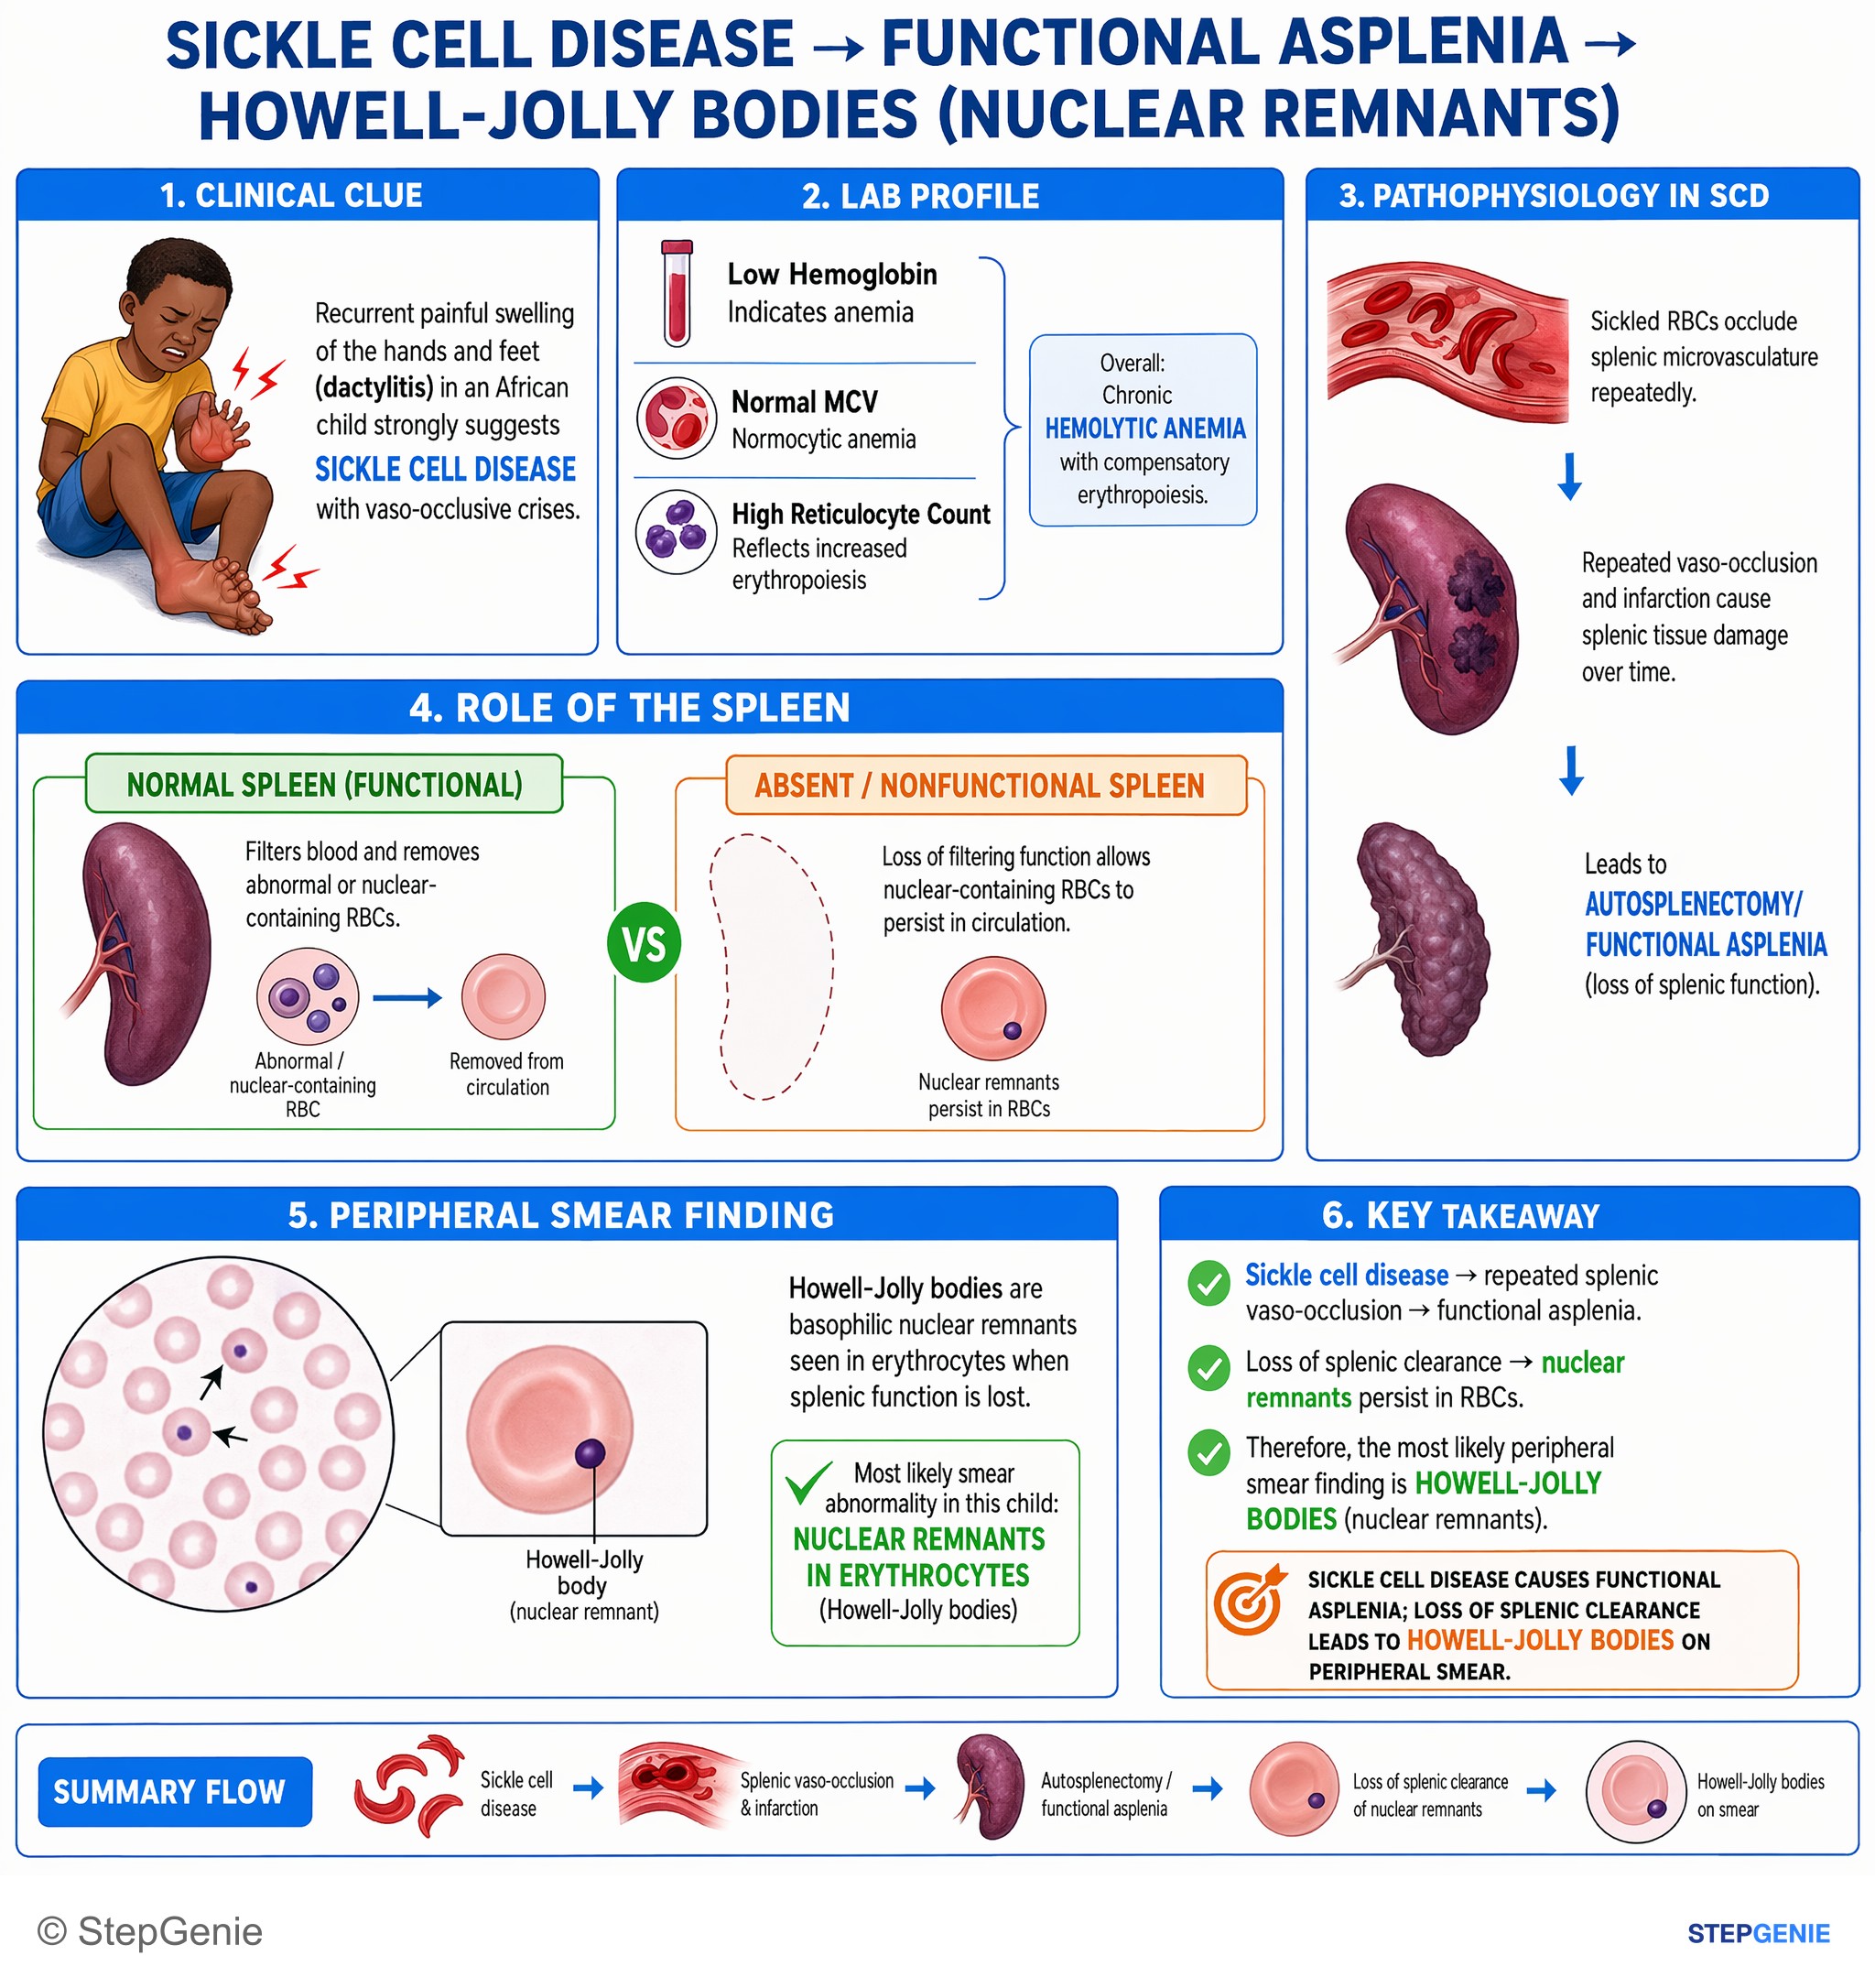
Sickle cell disease causes functional asplenia; loss of splenic clearance leads to Howell-Jolly bodies (nuclear remnants) on peripheral…
USMLE Step 1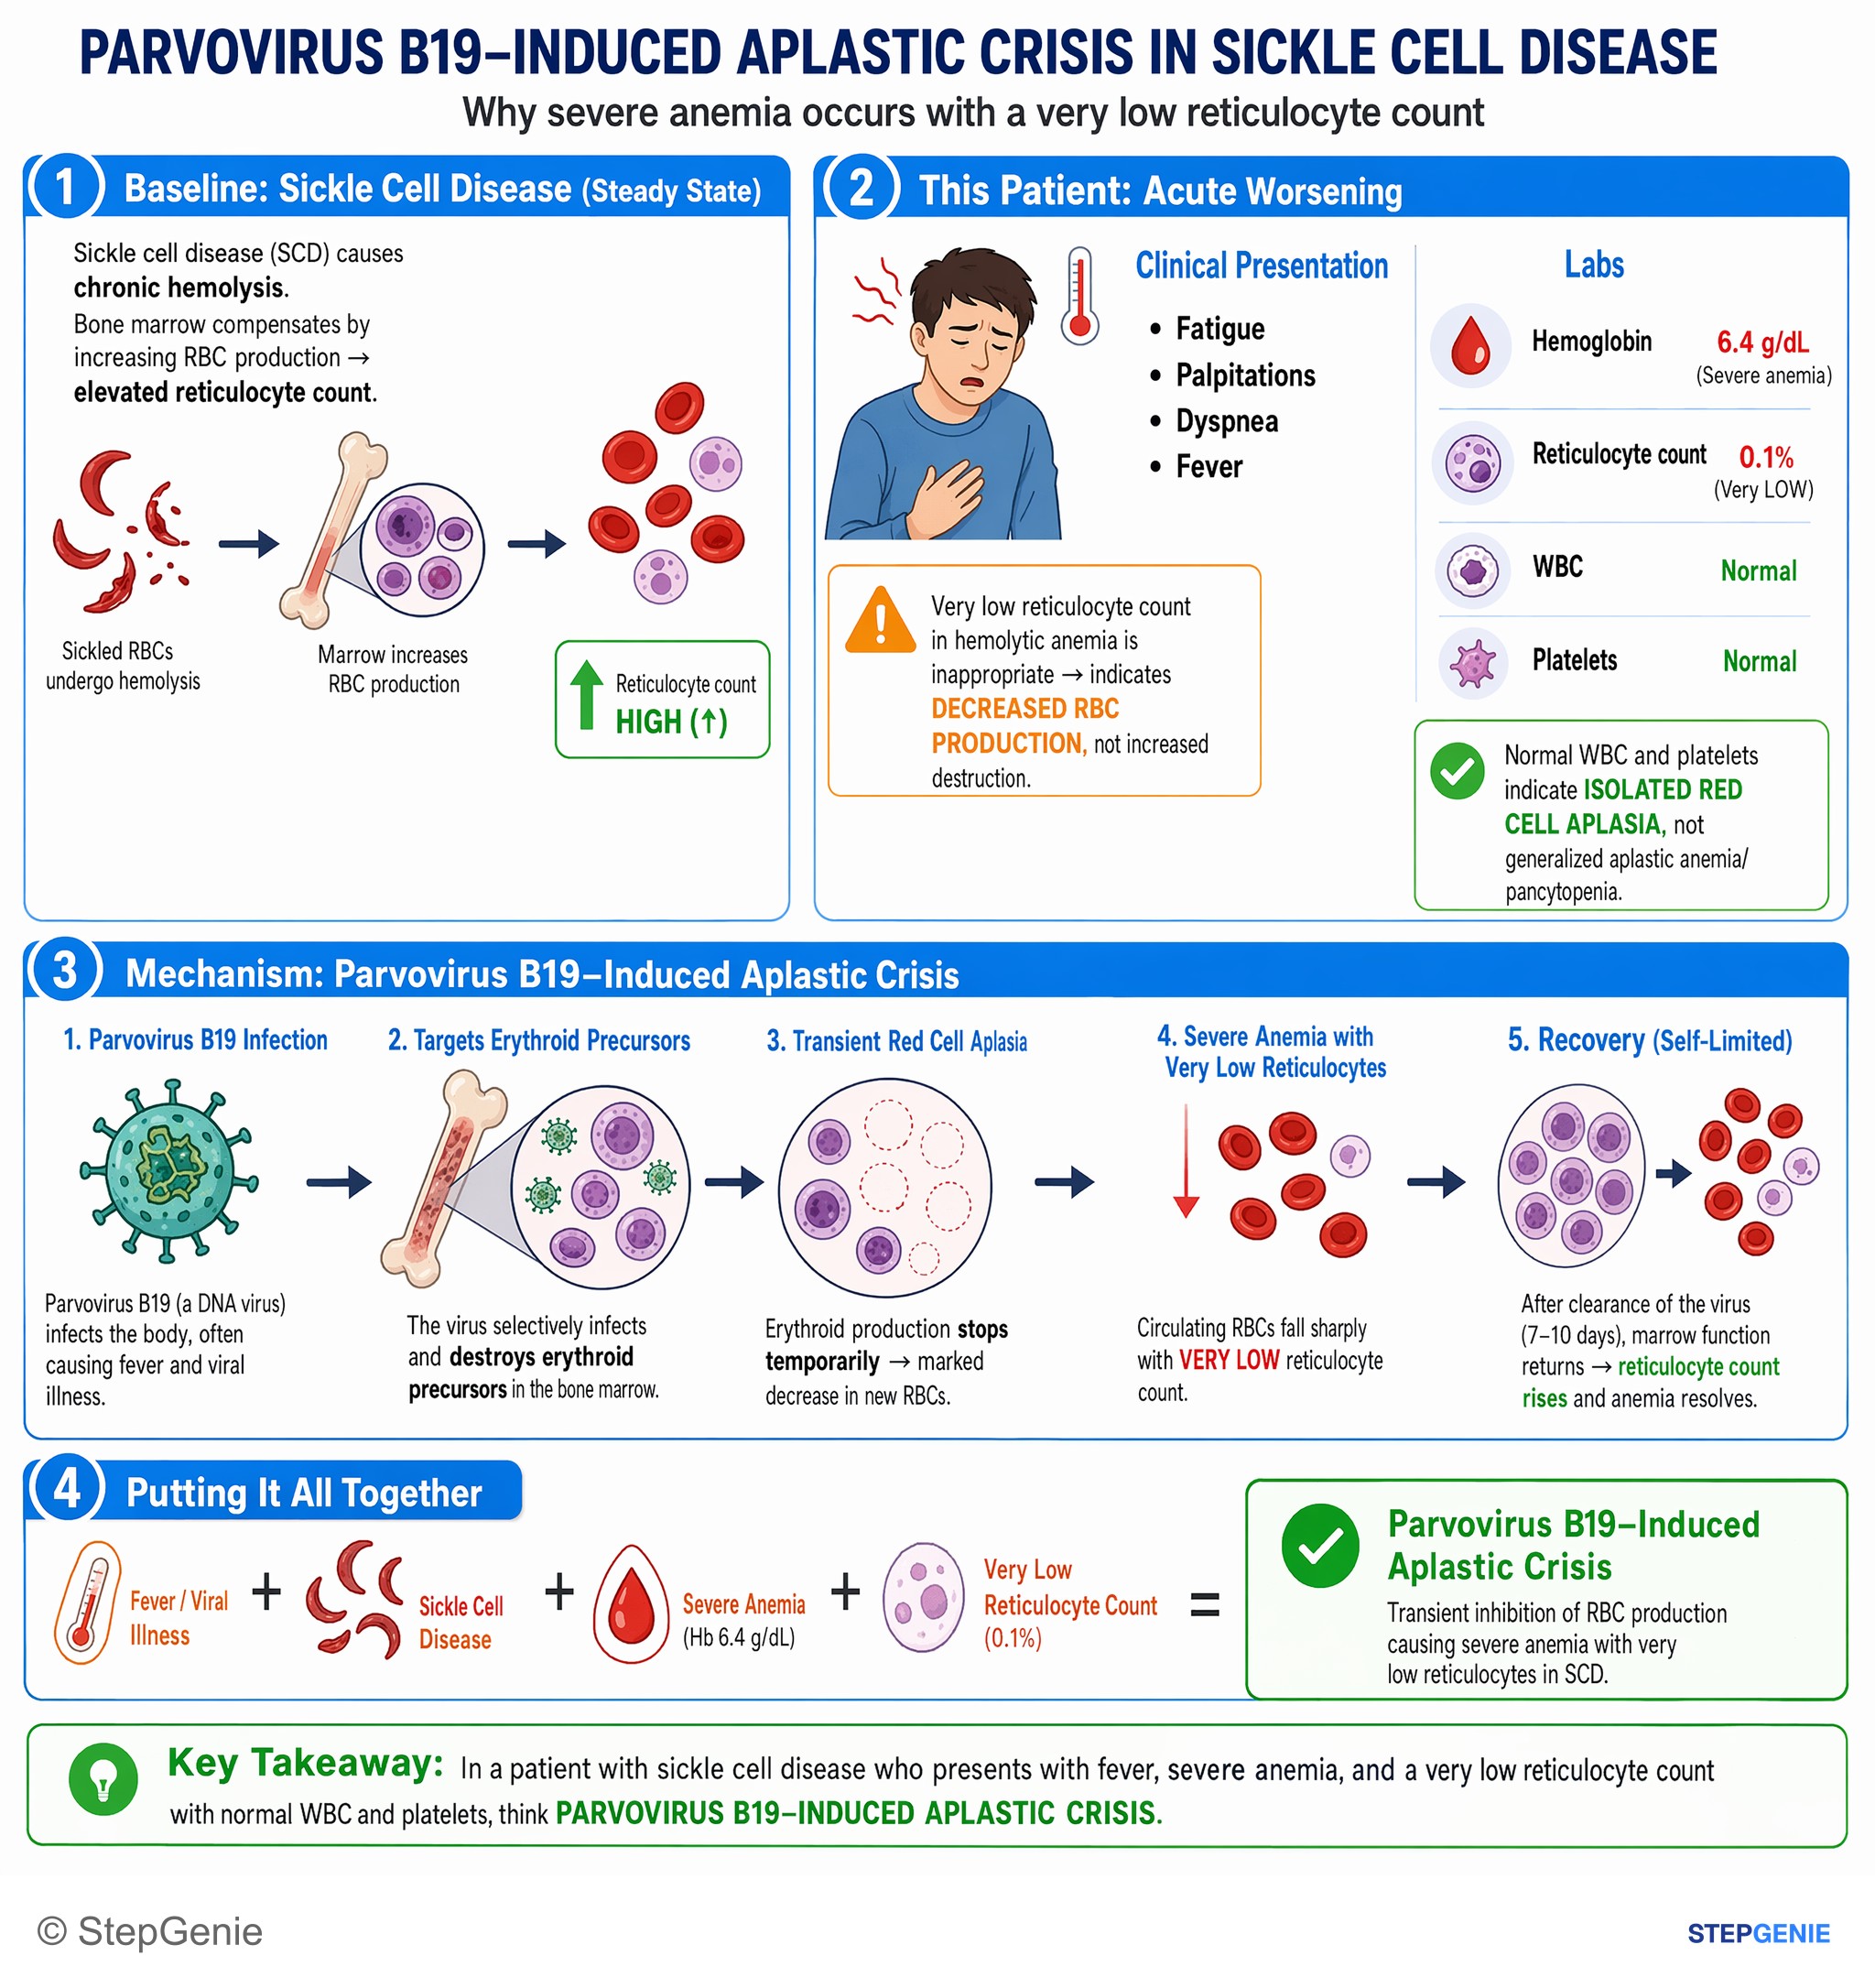
Aplastic crisis in sickle cell disease: Parvovirus B19 infects erythroid precursors → transient red cell aplasia → severe anemia with very…
USMLE Step 1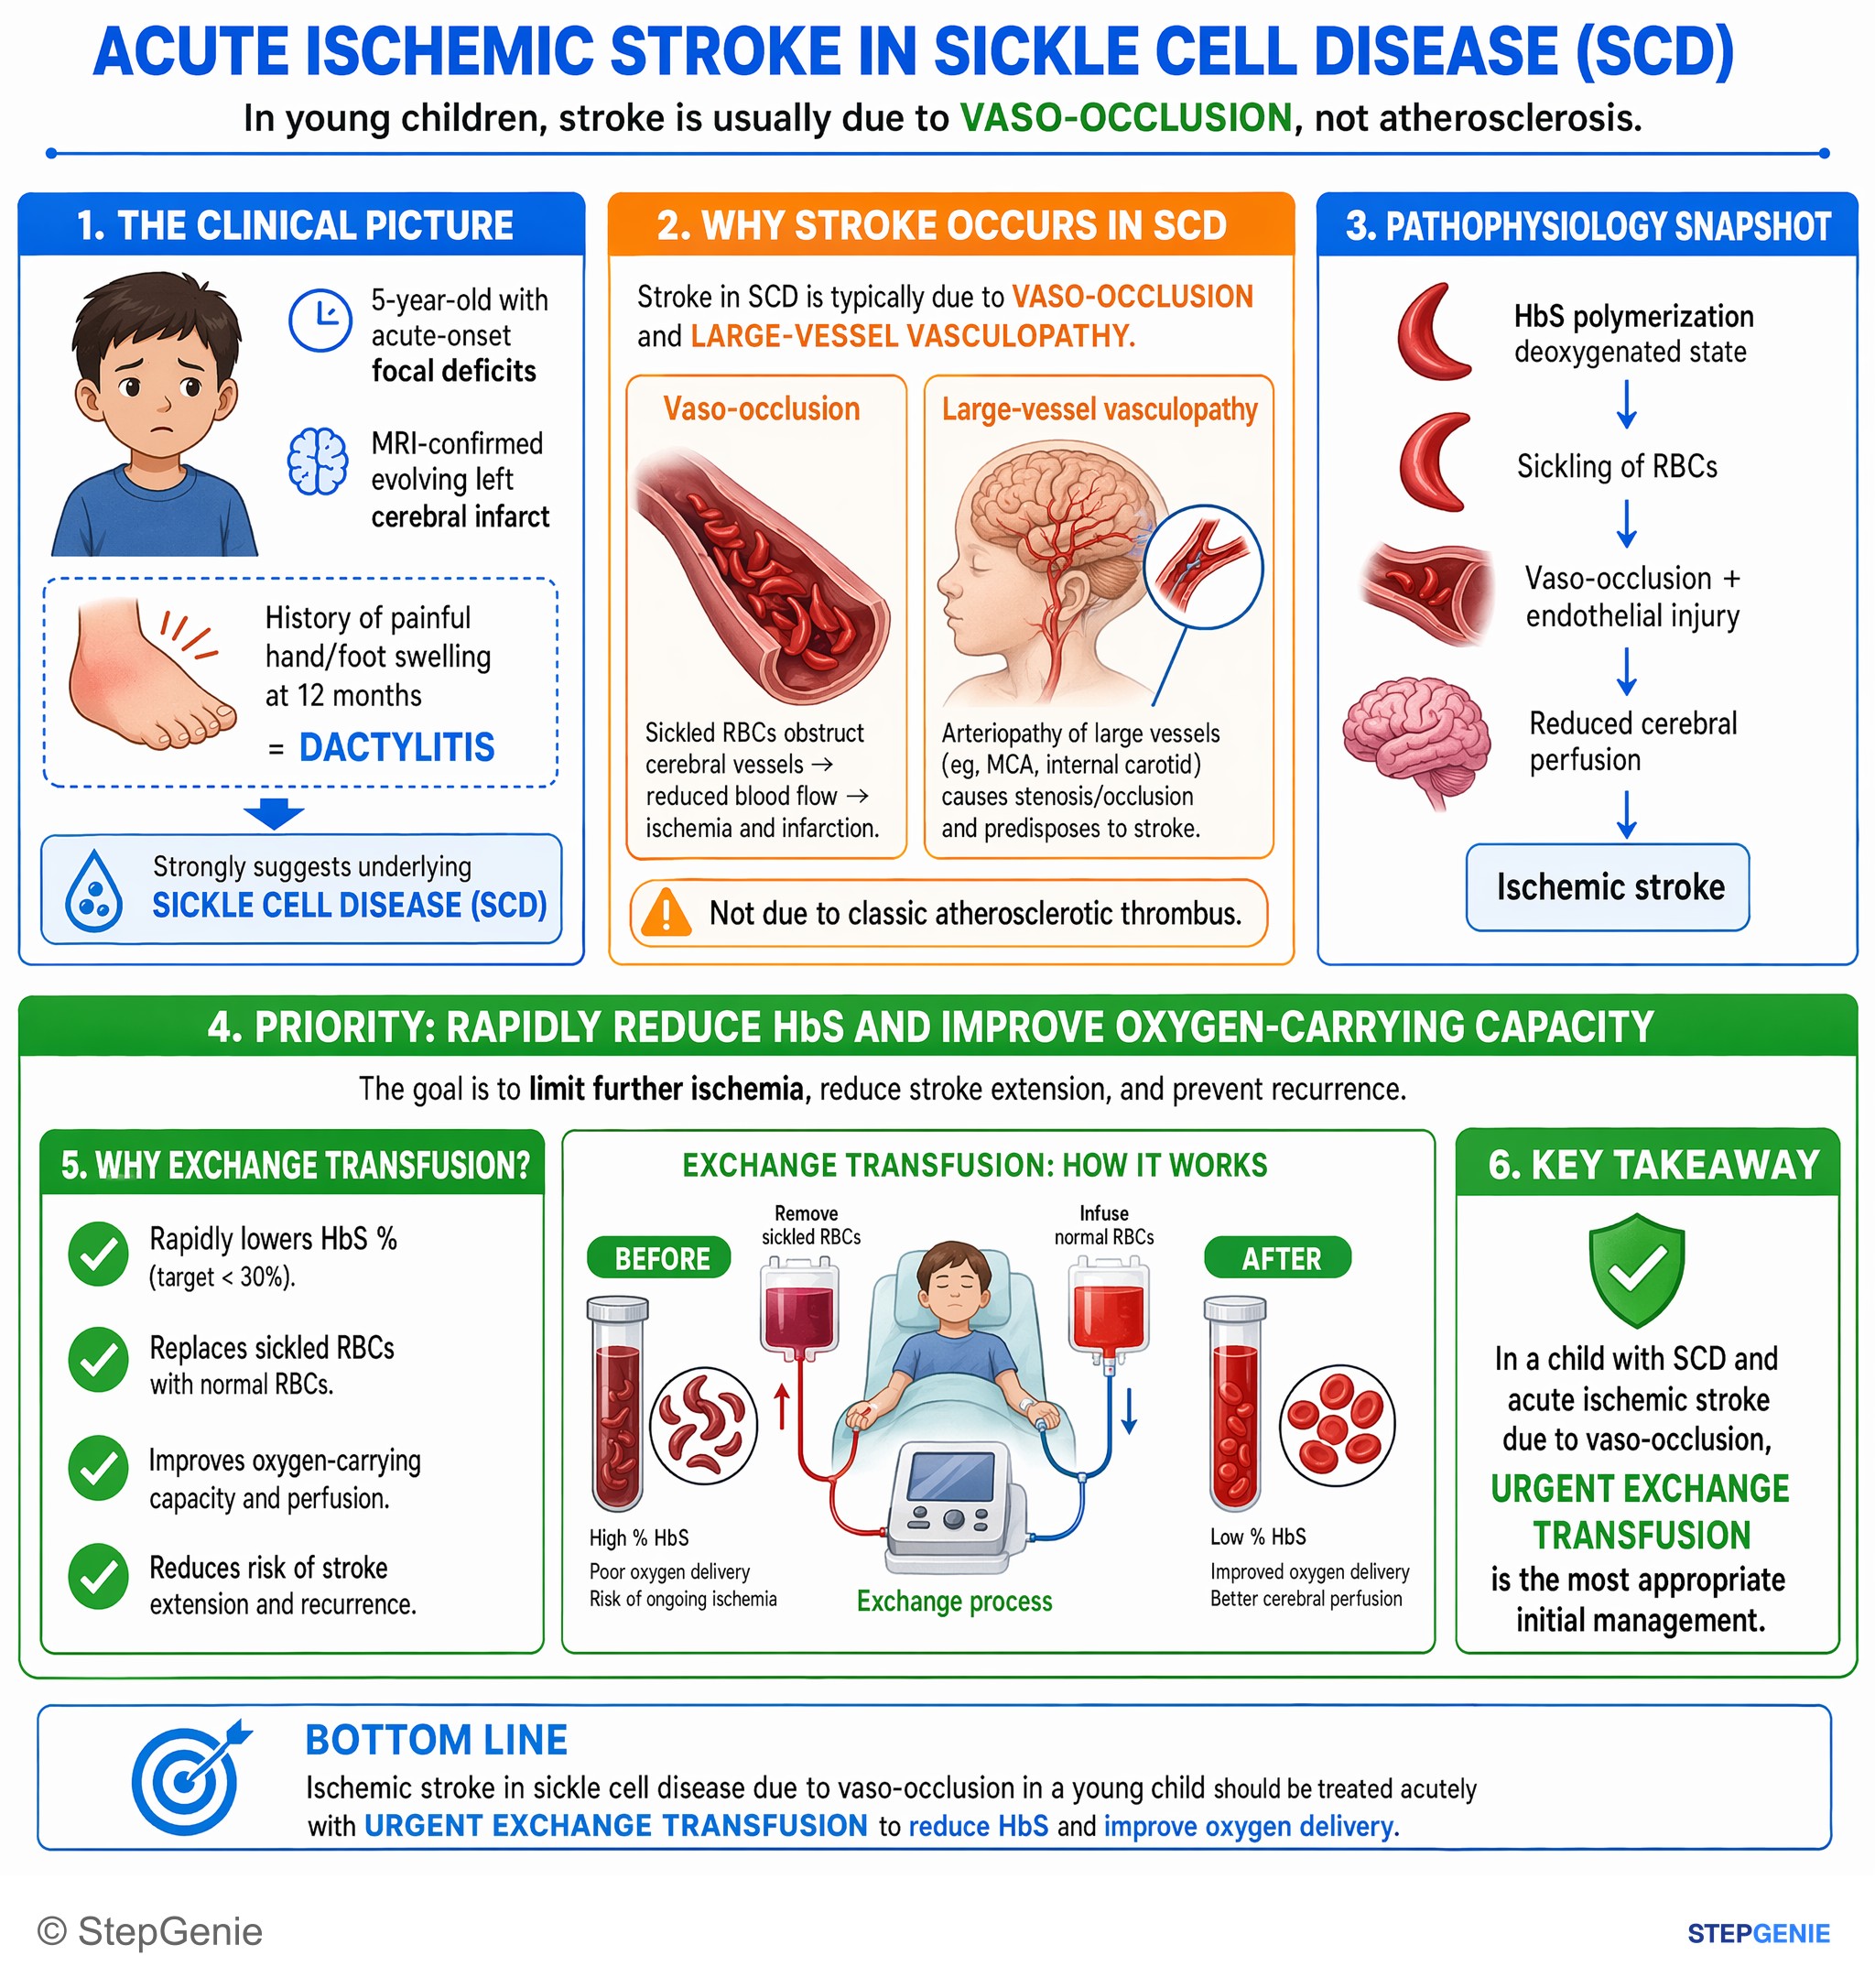
Ischemic stroke in sickle cell disease due to vaso-occlusion in a young child → treat acutely with urgent exchange transfusion to reduce…
USMLE Step 2Frequently Asked Questions
Why don't newborns with sickle cell disease have symptoms?
Newborns still carry fetal hemoglobin (HbF, alpha2 gamma2). It contains no beta chains, so the sickle mutation cannot affect it, and it wanes over the first months of life; most babies have no problems before about 5 or 6 months of age, and symptoms usually begin in early childhood. Newborn screening by hemoglobin electrophoresis, isoelectric focusing or HPLC finds the disease before symptoms appear, so penicillin prophylaxis and vaccination can start early. Raising HbF later in life is how hydroxyurea works.
What is the difference between sickle cell trait and sickle cell disease?
Trait (HbAS) means one sickle gene and one normal gene: electrophoresis shows more HbA than HbS, and carriers are not anemic, have no hemolysis and usually have no pain crises. Disease means two abnormal genes, such as HbSS, HbSC or HbS-beta-thalassemia, and HbSS shows no HbA at all. Trait still carries tested risks: hyposthenuria, self-limited hematuria, renal papillary necrosis, exertional heat illness and rhabdomyolysis, and the rare renal medullary carcinoma.
How is acute chest syndrome recognized and treated?
Suspect it when a patient with sickle cell disease has fever, chest pain, cough or hypoxemia and a new infiltrate on chest x-ray; it is a common cause of death. The NHLBI 2014 expert panel recommends an IV cephalosporin plus an oral macrolide, oxygen to keep saturation above 95%, incentive spirometry, simple transfusion when hemoglobin is more than 1 g/dL below baseline, and urgent exchange transfusion for rapid progression.
Why are people with sickle cell disease prone to pneumococcal sepsis and Salmonella osteomyelitis?
Repeated splenic infarction causes functional asplenia, so encapsulated bacteria such as Streptococcus pneumoniae, Haemophilus influenzae and Neisseria meningitidis are poorly cleared, and Howell-Jolly bodies appear on the smear. Salmonella infections, including osteomyelitis, are also more common, although Staphylococcus aureus is the most common cause of osteomyelitis overall. These infections are especially common in early childhood, so children take penicillin prophylaxis until age 5, receive vaccines, and any fever of 38.5 °C or higher is treated as an emergency.
How does hydroxyurea help in sickle cell disease?
Hydroxyurea raises fetal hemoglobin, and more HbF means less sickling. It cuts pain crises by about 45% and reduces acute chest syndrome and transfusion needs. The NHLBI 2014 panel recommends offering it to all infants from 9 months, children and adolescents with sickle cell anemia regardless of severity, and to adults with 3 or more moderate-to-severe pain crises in 12 months, recurrent acute chest syndrome or severe anemia. Blood counts are monitored for neutropenia and thrombocytopenia.