Paroxysmal nocturnal hemoglobinuria (PNH) is an acquired stem cell disorder: a somatic PIGA mutation stops the cell from building GPI anchors, so the clone's blood cells lose the complement shields CD55 and CD59 and red cells are destroyed by complement inside blood vessels. The exam picture is a triad of Coombs-negative intravascular hemolysis, thrombosis at unusual sites (hepatic, portal, cerebral veins) and bone marrow failure. Confirm it with flow cytometry (loss of CD59/CD55 on red cells, no FLAER binding on granulocytes). Treat symptomatic disease with a complement inhibitor (C5: eculizumab, ravulizumab, crovalimab; proximal: pegcetacoplan, iptacopan, add-on danicopan) after meningococcal vaccination at least 2 weeks before the first dose.
The one-line mechanism
Somatic PIGA mutation in a hematopoietic stem cell → no GPI anchor → no CD55 or CD59 on the cell surface → complement runs unchecked → membrane attack complex (C5b-9) → intravascular hemolysis.
| Missing protein | Also called | Normal job | Result of its loss |
|---|---|---|---|
| CD55 | Decay-accelerating factor (DAF) | Breaks up (dissociates) the C3 and C5 convertases | Convertases keep working; C3 fragments build up on the cell |
| CD59 | Membrane inhibitor of reactive lysis (MIRL), protectin | Binds C8 and C9 so the MAC pore cannot form | MAC pores insert → red cells lyse in the circulation |
- Acquired, not inherited. The mutation arises in one stem cell, so every lineage from that clone (red cells, granulocytes, monocytes, platelets) lacks GPI-anchored proteins.
- PIGA sits on the X chromosome. Men have one copy and women have one active copy after X-inactivation, so a single somatic hit is enough in either sex.
- Who gets it: a rare disease; Merck puts the median age at onset in the 30s, with men and women affected equally.
Why "nocturnal" is a misnomer
- Hemolysis happens throughout the day. Overnight urine is more concentrated, so the first-morning void looks darkest.
- The old theory that acidosis during sleep triggers the hemolysis was later disproved (Medscape), so don't pick it as the mechanism.
- Only about 30% of patients have overt hemoglobinuria (Merck). Clear urine does not rule PNH out.
- The paroxysms are hemolytic crises triggered by infection, transfusion, vaccination or menstruation, with abdominal, chest or back pain and dark urine.
The triad, plus the extras
| Feature | What the stem shows | Why |
|---|---|---|
| Intravascular hemolysis | Fatigue, dark urine, jaundice; high LDH, low haptoglobin, high indirect bilirubin; negative DAT | MAC lysis of GPI-deficient red cells |
| Thrombosis | Budd-Chiari (hepatic vein), portal, mesenteric or cerebral venous sinus thrombosis; arterial clots also occur | Driven by complement activation and hemolysis; the exact mechanism is not fully understood |
| Marrow failure | Leukopenia, thrombocytopenia or pancytopenia; overlap with aplastic anemia or MDS | Likely immune attack on hematopoietic stem cells (Merck) |
| Smooth muscle dystonia | Abdominal pain, esophageal spasm and dysphagia, erectile dysfunction, pulmonary hypertension | Free hemoglobin scavenges nitric oxide |
| Iron deficiency | Low iron stores after months of dark urine | Chronic urinary loss of hemoglobin and hemosiderin |
| Kidney injury | Chronic kidney disease after years of hemoglobinuria | Heme and iron injure the tubules (pigment nephropathy); renal vein thrombosis |
- Thrombosis is the leading cause of death in PNH, and Budd-Chiari syndrome is its most common thrombotic event (Perry et al., 2025). Unexplained hemolysis plus a clot in an odd vein is the classic prompt to test.
- Aplastic anemia link: Merck reports a detectable PNH clone in about half of patients with acquired aplastic anemia (a 2025 review says 40%), usually small and silent. Classic PNH can also progress to marrow failure, and PNH raises the risk of leukemia (MedlinePlus). The marrow side is mapped in the aplastic anemia flowchart.
Diagnosis: flow cytometry
Who to test (ARUP Consult): hemoglobinuria; Coombs-negative hemolytic anemia without another explanation; unexplained hemolysis with iron deficiency, abdominal pain, dysphagia, thrombosis or cytopenias; thrombosis at unusual sites; and bone marrow failure (aplastic anemia, hypoplastic anemia, MDS).
| Test | PNH result | Point to remember |
|---|---|---|
| Flow cytometry, red cells | Absent or reduced CD59 and CD55 | Underestimates the clone after transfusion of normal red cells |
| Flow cytometry, granulocytes and monocytes | No FLAER binding, plus loss of GPI-linked markers such as CD157 | FLAER (fluorescent aerolysin) binds the GPI anchor itself; white cells give the most accurate clone size |
| LDH | High | With low haptoglobin, a hallmark of intravascular hemolysis |
| Haptoglobin | Low or undetectable | Consumed by free hemoglobin |
| Direct antiglobulin (Coombs) test | Negative | Complement-driven, not antibody-driven |
| Urinalysis | Dipstick positive for blood with few or no red cells; urine hemosiderin | Hemoglobinuria, not hematuria |
| Ham test, sucrose lysis test | Historical only | Most laboratories no longer perform them |
Once diagnosed, clone size is rechecked by flow cytometry, about yearly when stable.
Treatment: complement inhibitors
Who needs treatment: symptomatic hemolysis, transfusion dependence or thrombosis. Merck notes that largely asymptomatic patients with small clones (under 30% by flow cytometry) generally do not need it.
| Drug (brand) | Target | Route and schedule | Exam-worthy detail |
|---|---|---|---|
| Eculizumab (Soliris; biosimilars eculizumab-aeeb and eculizumab-aagh) | C5 | IV every 2 weeks after induction | First PNH complement inhibitor (2007); blocks cleavage of C5 into C5a and C5b |
| Ravulizumab (Ultomiris) | C5 | IV every 8 weeks (every 4 weeks under 20 kg) | Longer half-life; approved from 1 month of age |
| Crovalimab (PiaSky) | C5 | IV loading dose, then subcutaneous (weekly for 4 doses, then every 4 weeks) | Age 13 or older and at least 40 kg; switching to or from another C5 inhibitor risks a type III (immune complex) hypersensitivity reaction |
| Pegcetacoplan (Empaveli) | C3 | Subcutaneous twice weekly | Acts upstream, so controls intravascular and extravascular hemolysis |
| Iptacopan (Fabhalta) | Factor B | Oral, twice daily | First oral monotherapy for PNH (2023) |
| Danicopan (Voydeya) | Factor D | Oral, three times daily | Add-on only to ravulizumab or eculizumab for extravascular hemolysis |
Why C5 blockers leave some patients anemic. Blocking C5 stops the MAC, so PNH red cells now survive in the circulation. Upstream, though, their surfaces collect C3 fragments (C3d), which act as opsonins: spleen and liver macrophages remove the coated cells (extravascular hemolysis), and the DAT turns positive for C3 on PNH cells (Perry et al., 2025). Proximal inhibitors work at C3 or on the alternative pathway (factor B, factor D), before this step, which is why they can control both kinds of hemolysis.
Everything else:
- Folic acid and oral iron; transfusion for crises or symptomatic anemia.
- Anticoagulate an acute thrombosis. Merck notes that long-term anticoagulation may not be needed once complement inhibition is established.
- Glucocorticoids have weak supporting evidence and long-term toxicity, so they are not a standard answer.
- Allogeneic hematopoietic stem cell transplant is the only cure (Perry et al., 2025). It is reserved for refractory disease or coexisting severe marrow failure, because complement inhibitors do not treat marrow failure.
Meningococcal vaccination and infection risk
Every complement inhibitor above carries a boxed warning for serious meningococcal infections (CDC), and each is available only through a restricted REMS program. It is the drug version of a lesson from immunology: inherited deficiency of the terminal components (C5-C9) or of factor B, factor D or properdin predisposes to Neisseria infection, as the complement deficiencies table shows.
- Before the first dose: complete or update vaccination against meningococcal serogroups A, C, W, Y (MenACWY) and B (MenB) at least 2 weeks beforehand, unless delaying treatment is the greater risk (FDA labels).
- If treatment is urgent: give antibacterial drug prophylaxis and vaccinate as soon as possible.
- Proximal inhibitors widen the net: their boxed warnings cover serious infections with encapsulated bacteria. The iptacopan label, for example, names N. meningitidis, Streptococcus pneumoniae and Haemophilus influenzae type b and requires pneumococcal as well as meningococcal (ACWY and B) vaccination at least 2 weeks before the first dose.
- Vaccination does not give full protection. CDC puts the risk of meningococcal disease at up to 2,000 times that of healthy people, and most infections identified in eculizumab users were caused by nongroupable strains, which typically do not cause invasive disease in people with normal immune systems. While on therapy, CDC advises MenACWY boosters every 5 years and MenB 1 year after the primary series, then every 2-3 years; clinicians may also consider antibiotic prophylaxis.
- Fever or meningism on a complement inhibitor: the labels say to evaluate immediately for meningococcal infection.
PNH vs other hemolytic anemias
| PNH | Warm autoimmune hemolytic anemia | G6PD deficiency | Microangiopathic (TTP, HUS, DIC) | |
|---|---|---|---|---|
| Cause | Acquired loss of GPI-anchored proteins | IgG autoantibodies | X-linked enzyme deficiency plus oxidant stress | Mechanical shearing in small vessels |
| DAT | Negative | Positive | Negative | Negative |
| Smear | No distinctive shape change | Spherocytes | Bite cells; Heinz bodies on special stain | Schistocytes |
| Main site of hemolysis | Intravascular | Extravascular | Intravascular and extravascular | Intravascular |
| Extra clue | Odd-site venous clots, cytopenias | SLE, CLL, drugs | Episodes after drugs, infection or fava beans | Thrombocytopenia |
Oxidant hemolysis is covered in the G6PD deficiency guide.
Practice question
A 34-year-old man has had 2 weeks of fatigue and 2 days of right upper quadrant pain and abdominal swelling. Several times this year he has passed cola-colored urine on waking. He has tender hepatomegaly and ascites. Hemoglobin is 8.6 g/dL, MCV 94 fL, leukocytes 3,200/µL, platelets 88,000/µL and reticulocytes 3.5%. LDH is 1,480 U/L, haptoglobin is undetectable and the direct antiglobulin test is negative. The smear shows no schistocytes or spherocytes. The urine dipstick is strongly positive for blood, with 0-2 red cells per high-power field. Doppler ultrasound shows hepatic vein thrombosis. Which test is most likely to confirm the underlying diagnosis?
A. Osmotic fragility test B. JAK2 V617F mutation analysis C. Flow cytometry for GPI-anchored proteins (CD59, FLAER) D. ADAMTS13 activity E. Bone marrow biopsy
Answer: C. Coombs-negative intravascular hemolysis (high LDH, absent haptoglobin, hemoglobinuria without red cells), cytopenias and Budd-Chiari syndrome make up the PNH triad. Flow cytometry showing loss of CD59 on red cells and absent FLAER binding on granulocytes confirms it.
- A. Osmotic fragility test: screens for hereditary spherocytosis, which gives spherocytes and extravascular hemolysis in the spleen, not hepatic vein thrombosis.
- B. JAK2 V617F: myeloproliferative neoplasms such as polycythemia vera also cause Budd-Chiari syndrome, but they raise blood counts rather than causing cytopenias with intravascular hemolysis.
- D. ADAMTS13 activity: TTP produces schistocytes and marked thrombocytopenia; the smear here has no schistocytes.
- E. Bone marrow biopsy: assesses marrow failure but cannot show GPI-anchor loss; PNH is diagnosed by flow cytometry of peripheral blood.
Next steps: anticoagulate the hepatic vein thrombosis, give MenACWY and MenB (at least 2 weeks before the first dose, or cover with antibiotics if treatment cannot wait) and start a complement inhibitor.
Key takeaways
- PNH = acquired PIGA mutation → no GPI anchor → no CD55/CD59 → complement-mediated intravascular hemolysis.
- Triad: Coombs-negative hemolysis, venous thrombosis at odd sites (Budd-Chiari most often) and cytopenias; thrombosis is the leading cause of death.
- "Nocturnal" is a misnomer: hemolysis is continuous, and only about 30% of patients have visible hemoglobinuria.
- Diagnose with flow cytometry: CD59 on red cells and FLAER on granulocytes. The Ham and sucrose lysis tests are obsolete.
- C5 inhibitors (eculizumab, ravulizumab, crovalimab) stop intravascular hemolysis; proximal inhibitors (pegcetacoplan, iptacopan, add-on danicopan) also treat C3-mediated extravascular hemolysis. Transplant is the only cure.
- Vaccinate against meningococcus (MenACWY + MenB) at least 2 weeks before starting; the risk persists despite vaccination.
Sources
- Paroxysmal Nocturnal Hemoglobinuria (PNH) — Merck Manual Professional Edition (2026)
- Paroxysmal nocturnal hemoglobinuria — MedlinePlus Genetics
- Paroxysmal Nocturnal Hemoglobinuria: Practice Essentials and Pathophysiology — Medscape Reference
- Paroxysmal Nocturnal Hemoglobinuria Workup — Medscape Reference (2023)
- Paroxysmal Nocturnal Hemoglobinuria (PNH): Choose the Right Test — ARUP Consult (2026)
- Perry C, et al. The Advancing Landscape of Paroxysmal Nocturnal Hemoglobinuria Treatment — Turkish Journal of Hematology (2025)
- Clinical Guidance for Managing Meningococcal Disease Risk in Patients Receiving Complement Inhibitor Therapy — CDC (2026)
- SOLIRIS (eculizumab) prescribing information — DailyMed (2026)
- ULTOMIRIS (ravulizumab) prescribing information — DailyMed (2025)
- FABHALTA (iptacopan) prescribing information — DailyMed (2026)
- PIASKY (crovalimab) prescribing information — DailyMed (2024)
- Biosimilar Product Information (eculizumab-aeeb, eculizumab-aagh) — FDA (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
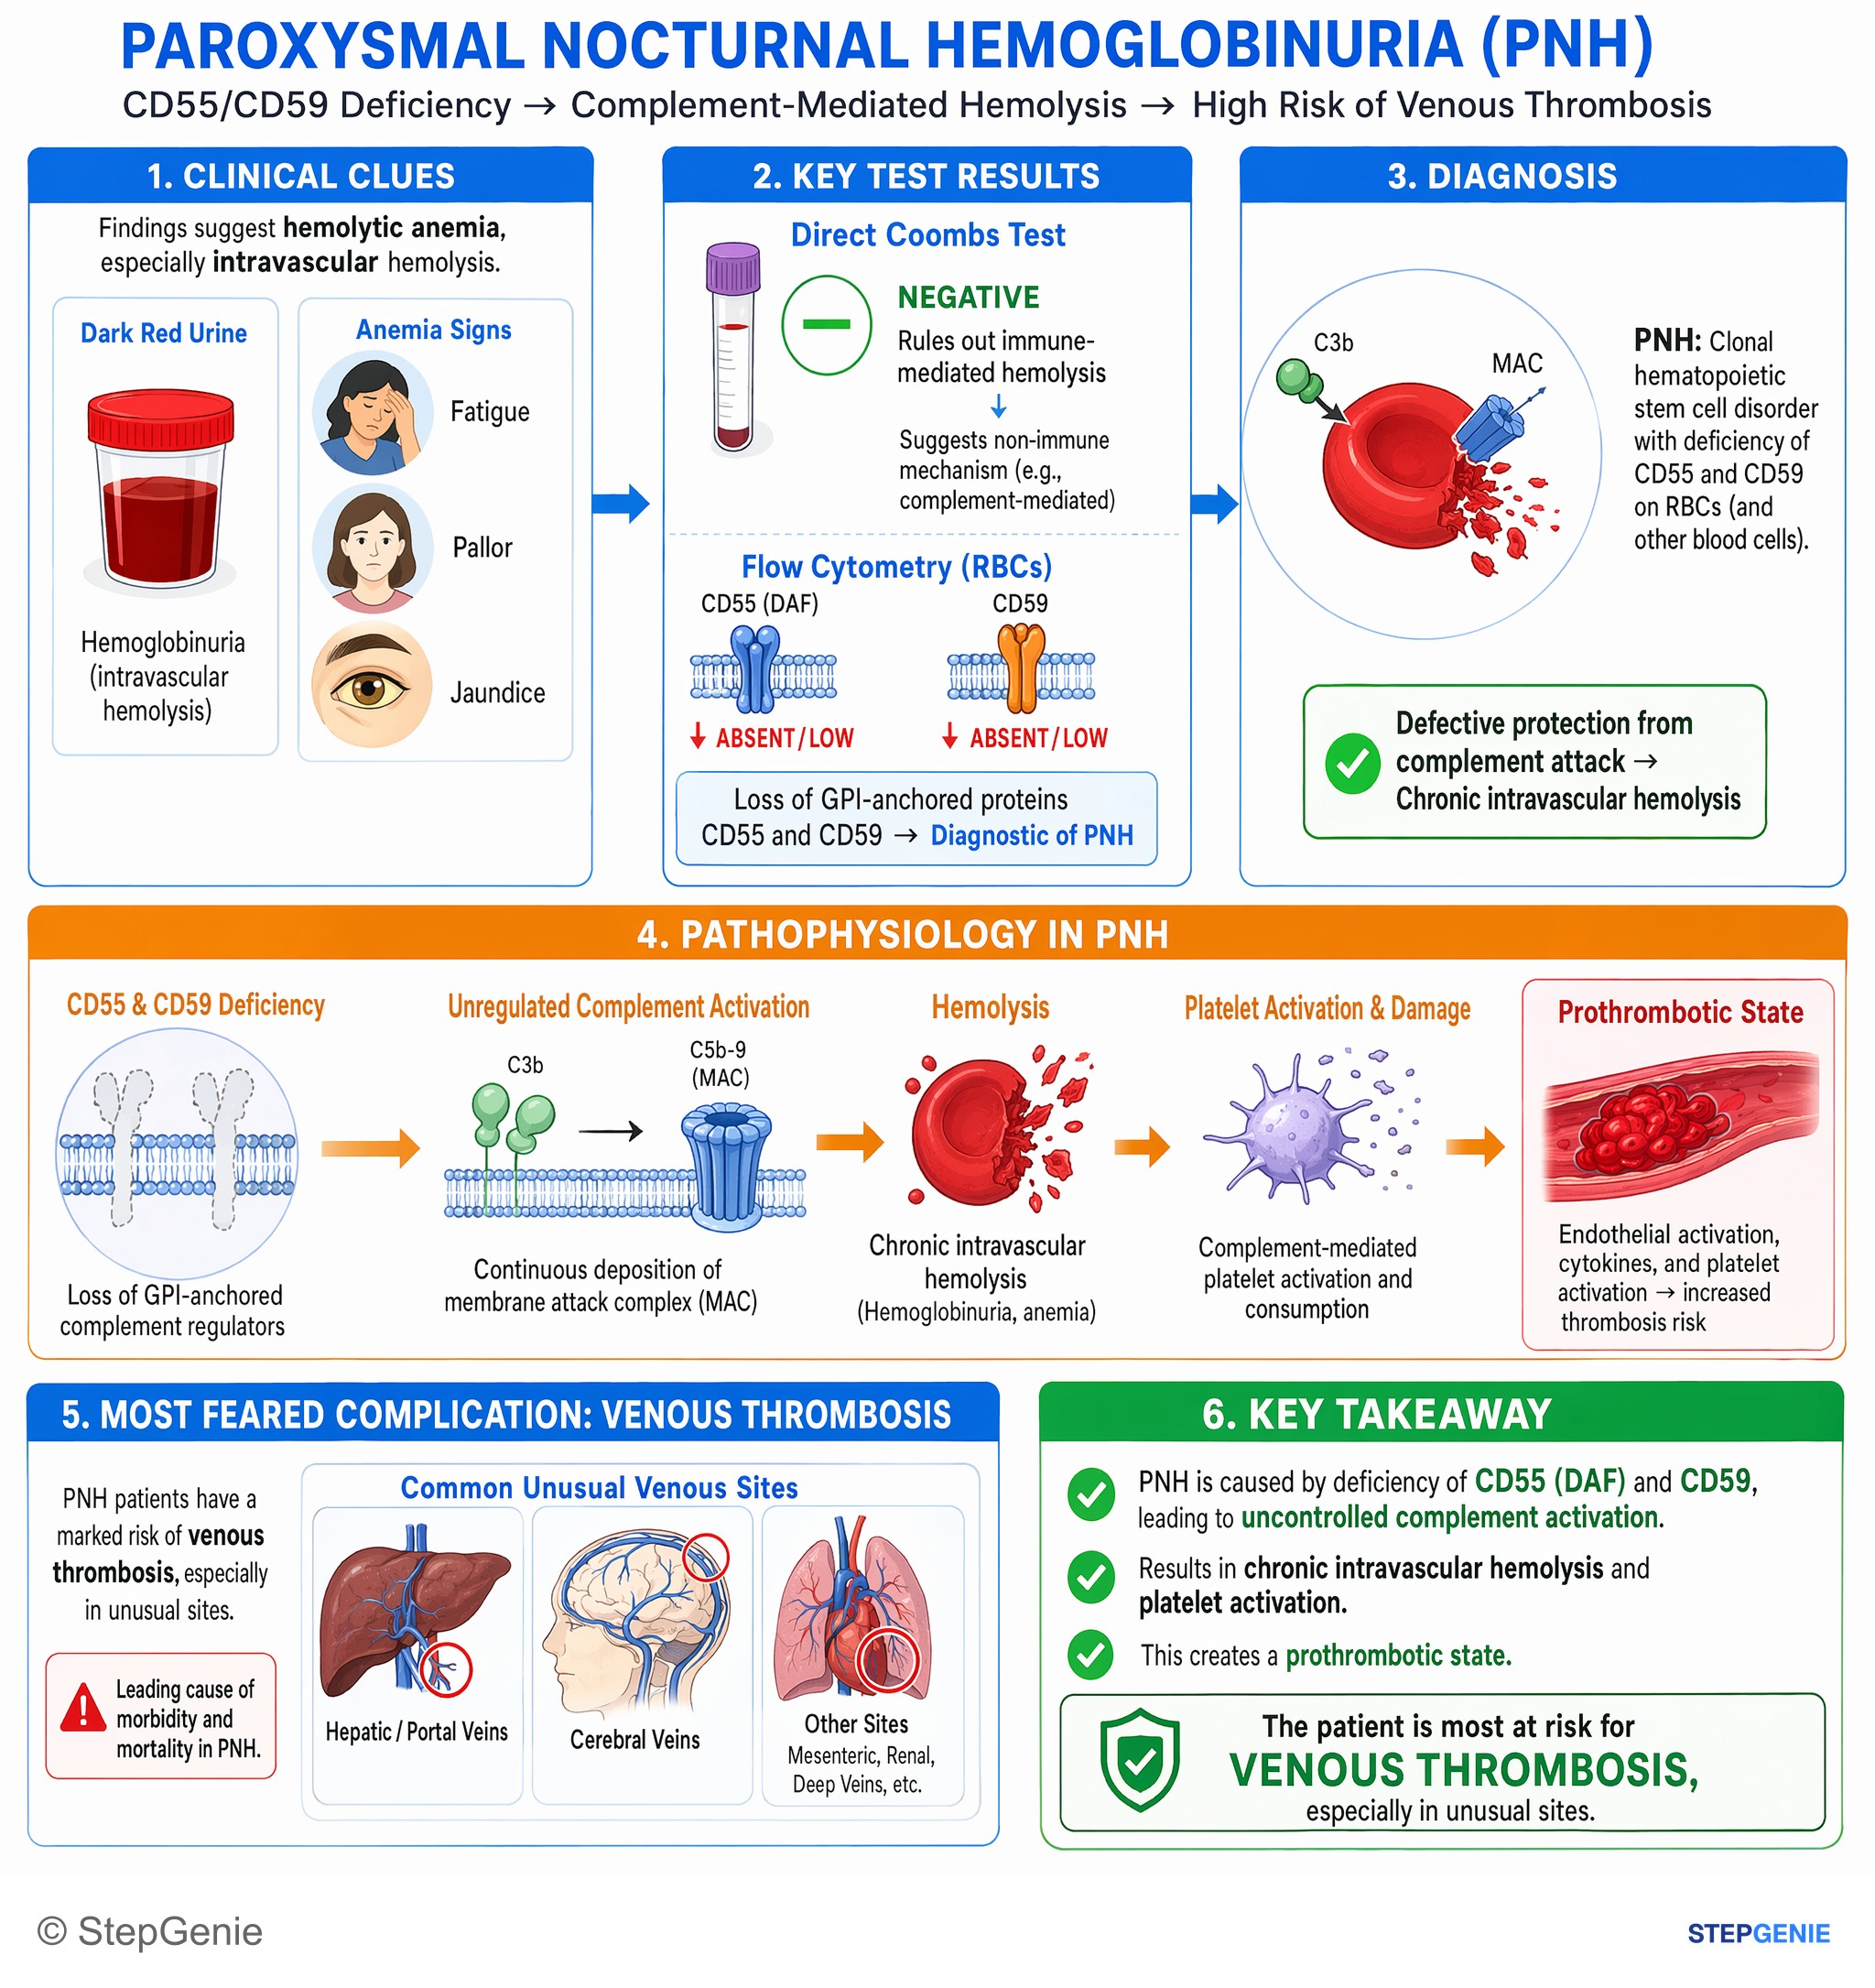
Paroxysmal nocturnal hemoglobinuria (PNH) from CD55/CD59 deficiency → complement-mediated hemolysis and marked risk of life-threatening…
USMLE Step 1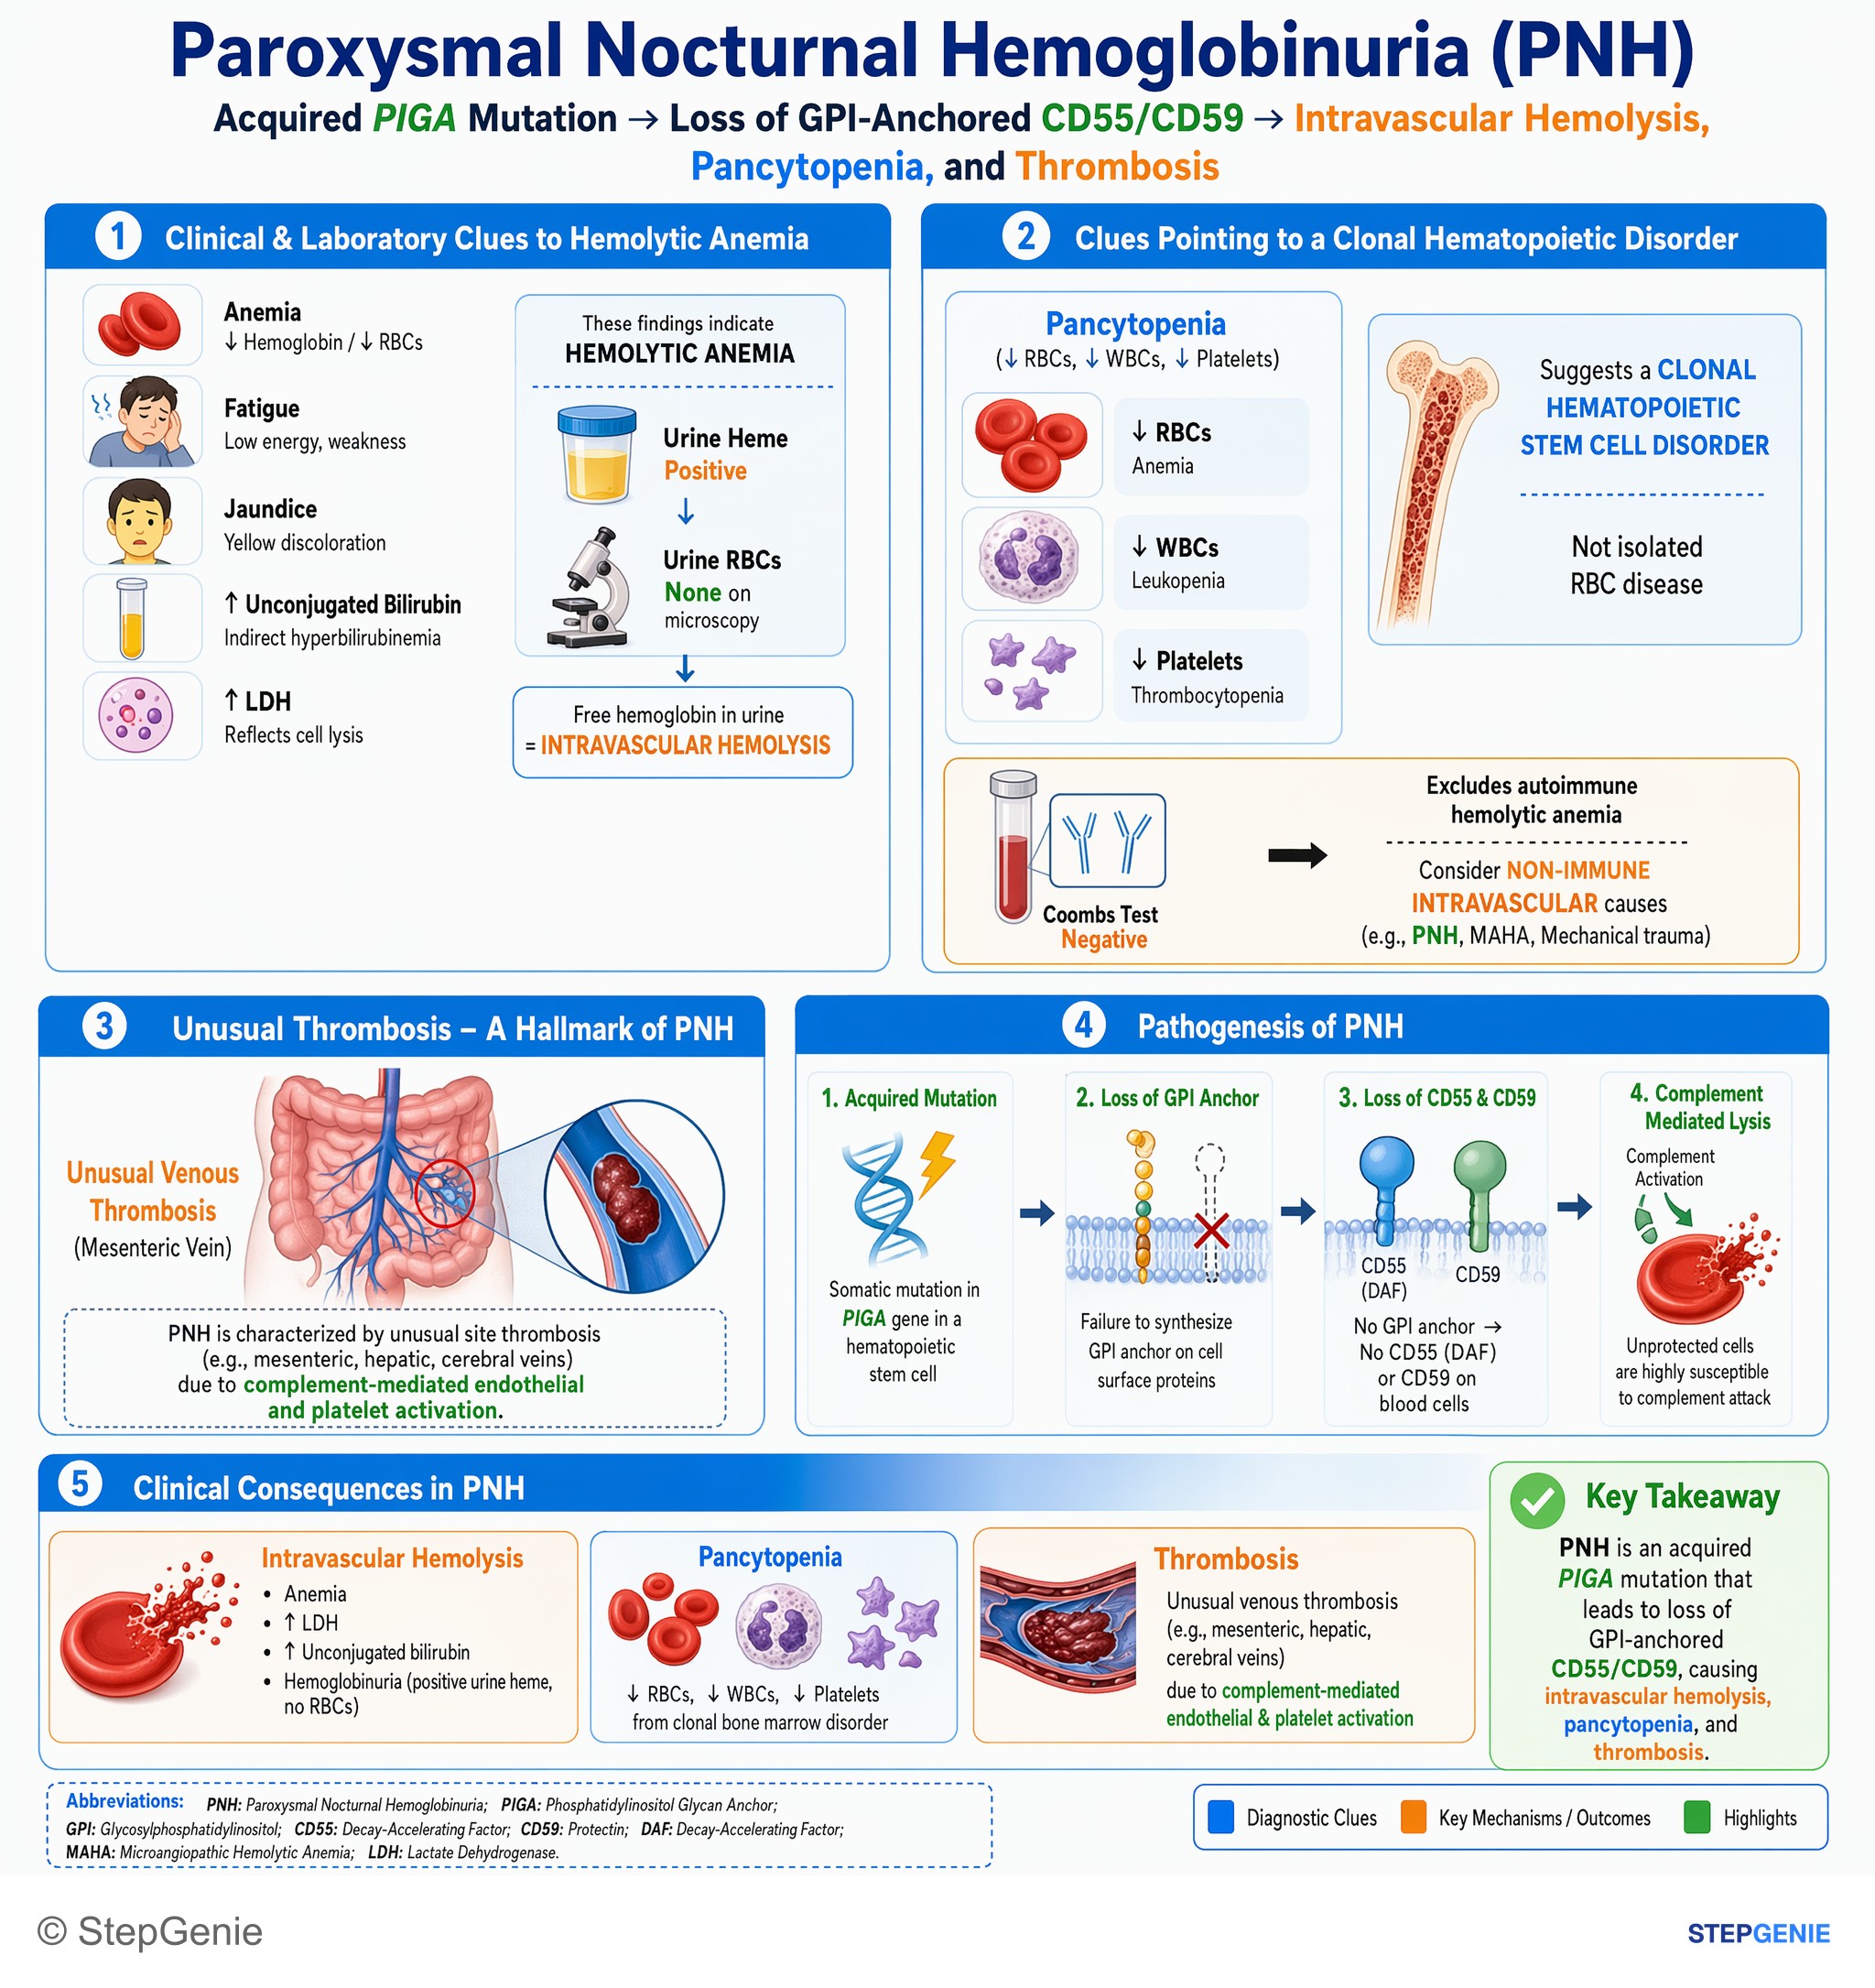
Paroxysmal nocturnal hemoglobinuria: acquired PIGA mutation → loss of GPI-anchored complement regulators (CD55/CD59) → intravascular…
USMLE Step 1Frequently Asked Questions
What causes paroxysmal nocturnal hemoglobinuria?
PNH is caused by an acquired (somatic) mutation in the PIGA gene in a single hematopoietic stem cell, not by an inherited mutation. PIGA is needed to build the GPI anchor that holds the complement regulators CD55 and CD59 on the cell surface. Blood cells from the mutant clone therefore cannot control complement, and their red cells are destroyed by the membrane attack complex inside blood vessels.
Why is PNH called nocturnal if hemolysis happens all day?
Hemolysis in PNH goes on throughout the day. Urine made overnight is more concentrated, so the first morning void looks darkest, which is where the name came from. The old idea that acidosis during sleep triggers the hemolysis was later disproved (Medscape), and only about 30% of patients have visible hemoglobinuria.
What is the best test to diagnose PNH?
Flow cytometry of peripheral blood is the diagnostic test. It shows loss of GPI-anchored proteins such as CD59 and CD55 on red cells and absent binding of FLAER, a fluorescent reagent that binds the GPI anchor itself, on granulocytes and monocytes. White cells give the most accurate clone size because transfused red cells dilute the PNH red cells. The older Ham and sucrose lysis tests are no longer performed by most laboratories.
What are the FDA-approved treatments for PNH?
Approved complement inhibitors include the C5 inhibitors eculizumab (and its biosimilars), ravulizumab and crovalimab; the C3 inhibitor pegcetacoplan; the oral factor B inhibitor iptacopan; and the oral factor D inhibitor danicopan, which is used only as an add-on to eculizumab or ravulizumab. C5 inhibitors stop intravascular hemolysis, while proximal inhibitors also control C3-mediated extravascular hemolysis. Allogeneic stem cell transplant is the only cure and is reserved for refractory disease or severe marrow failure.
Why do patients on eculizumab or ravulizumab need meningococcal vaccines?
Complement inhibitors block the terminal complement pathway that kills Neisseria, mimicking an inherited terminal complement deficiency. FDA labels require MenACWY and MenB vaccination at least 2 weeks before the first dose, or antibacterial prophylaxis if treatment cannot wait. CDC puts their risk of meningococcal disease at up to 2,000 times that of healthy people, and vaccination does not fully protect them, so boosters continue during therapy and any possible infection needs immediate evaluation.
How is PNH related to aplastic anemia?
The two conditions overlap. Merck reports a detectable PNH clone in about half of patients with acquired aplastic anemia, usually small and without much hemolysis, and classic PNH can progress to bone marrow failure. Complement inhibitors treat the hemolysis but not the marrow failure, which is why stem cell transplant is considered when severe aplastic anemia coexists.