Anemia of chronic disease (ACD), also called anemia of inflammation, is a hypoproliferative anemia in which inflammatory cytokines, above all IL-6, drive the liver to make hepcidin; hepcidin triggers degradation of the iron exporter ferroportin, so iron is trapped in macrophages and gut absorption falls. The iron panel shows low serum iron, low or low-normal TIBC (transferrin) and a normal or high ferritin (usually above 100 ng/mL), the mirror image of iron deficiency's high TIBC and ferritin below 30 ng/mL, and the soluble transferrin receptor (sTfR) stays normal. The anemia is usually mild and normocytic (sometimes microcytic) with a low reticulocyte count. Treatment is treating the underlying disease; iron helps only when true iron deficiency coexists, and erythropoiesis-stimulating agents (ESAs) are reserved for selected patients such as those with CKD.
The mechanism: three hits
Chronic infection, autoimmune disease, cancer, CKD or heart failure → IL-6 (plus IL-1, TNF-α, IFN-γ) → hepatocytes make hepcidin → hepcidin binds ferroportin, which is internalized and degraded → iron cannot leave duodenal enterocytes or macrophages → low serum iron despite full stores → iron-restricted erythropoiesis.
| Hit | Driver | Result |
|---|---|---|
| Iron sequestration | IL-6 → hepcidin → ferroportin degraded | Less duodenal absorption; macrophages keep the iron recycled from old red cells, so ferritin rises |
| Blunted erythropoietin (EPO) | IL-1 and TNF-α suppress EPO production; cytokines blunt marrow signaling | EPO too low for the degree of anemia, and a weak marrow response |
| Shorter red cell survival | Activated macrophages in the liver and spleen | Mild extra red cell destruction |
Why the body does this: withholding iron from microbes is a host defense, since pathogens need iron too. In chronic inflammation the same response starves the marrow.
Memory hook: hepcidin is the iron jailer. It locks the two exit doors (ferroportin on enterocytes and on macrophages), so the vault (ferritin) is full while the street (serum iron) is empty.
Who gets it and how it presents
- Causes: chronic infections (for example tuberculosis or HIV), autoimmune disease (especially rheumatoid arthritis, also lupus and inflammatory bowel disease), cancer, CKD and heart failure.
- How common: NIDDK calls it the second most common anemia after iron deficiency.
- Severity: mild to moderate; Merck notes the hemoglobin is usually above 8 g/dL unless another cause adds to it.
- Indices: normocytic and normochromic at first, sometimes becoming microcytic.
- Reticulocyte count: low (a production problem, not destruction).
- Symptoms: those of anemia (fatigue, weakness, dyspnea, pallor) plus the underlying disease.
Iron studies: ACD vs iron deficiency vs sideroblastic anemia
| Test | Anemia of chronic disease | Iron deficiency anemia | Sideroblastic anemia |
|---|---|---|---|
| Serum iron | ↓ (or normal) | ↓ | ↑ |
| TIBC (transferrin) | ↓ (or normal) | ↑ | Normal |
| Transferrin saturation | ↓ or normal | ↓↓ (under 10%; under 15% in mild anemia) | > 50% |
| Ferritin | Normal or ↑ (usually > 100 ng/mL) | < 30 ng/mL | > 400 ng/mL |
| Soluble transferrin receptor | Normal | ↑ | Not a key test |
| Hepcidin | ↑ | ↓ | Not a key test |
| Bone marrow | Iron present (in macrophages); no ringed sideroblasts | Iron absent | Iron ↑; ringed sideroblasts |
| Other clues | Inflammatory disease; normocytic | High RDW; microcytic | Iron-loading pattern |
Why each lab moves:
- Ferritin is both the iron storage protein and an acute-phase reactant, so inflammation raises it even when circulating iron is low.
- Transferrin (TIBC) is a negative acute-phase reactant, so it falls in inflammation; in iron deficiency it rises.
- sTfR reflects the marrow's demand for iron. Iron-starved red cell precursors raise it; in ACD alone it stays normal. Cytokines can nudge it, so read it together with ferritin.
- Thalassemia trait, the other classic microcytic mimic, shows microcytosis with a high RBC count and target cells; beta-thalassemia minor has an HbA2 above about 3.5%. See the alpha vs beta thalassemia table.
The full iron-deficiency workup is in the iron deficiency anemia guide.
The mixed picture: ACD plus true iron deficiency
Inflammation and blood loss often coexist (for example rheumatoid arthritis treated with NSAIDs, or inflammatory bowel disease). Because inflammation raises ferritin, a "normal" ferritin can hide iron deficiency.
- Ferritin below 100 ng/mL in a patient with inflammation suggests iron deficiency may be superimposed (Merck).
- A high sTfR in someone with ACD points to added absolute iron deficiency.
- The sTfR index: . In the Blood review by Weiss, Ganz and Goodnough, values below 1 fit ACD alone and above 2 fit ACD plus iron deficiency, with some overlap and a gray zone in between; Merck mentions the index without giving cutoffs.
- Hepcidin is high in ACD, suppressed in iron deficiency and in the normal range when both are present.
Treatment
| Step | What to do | Key points |
|---|---|---|
| 1. Treat the cause | Control the infection, inflammation or cancer | Curing the underlying disease usually resolves ACD |
| 2. Iron only if truly deficient | Oral iron with true deficiency and mild inflammation; IV iron if oral iron fails or active inflammation blocks absorption | High hepcidin predicts a poor response to oral iron; iron is generally avoided without deficiency or during acute, uncontrolled infection |
| 3. ESAs in selected patients | CKD, selected chemotherapy-induced anemia, some patients before elective surgery | Epoetin alfa label (CKD): start when Hb < 10 g/dL; reduce or interrupt if Hb approaches or exceeds 11 g/dL on dialysis (exceeds 10 g/dL if not on dialysis); use the lowest dose sufficient to reduce the need for transfusion; check iron first |
| 4. Transfusion | Severe, symptomatic or unstable anemia | Usually not required |
ESA safety (boxed warning): in CKD trials, targeting a hemoglobin above 11 g/dL increased death, serious cardiovascular events and stroke; in several cancers, ESAs shortened survival or increased tumor progression. The label also advises iron supplementation when ferritin is below 100 mcg/L or transferrin saturation is below 20%. In CKD, EPO deficiency adds to the inflammatory block; see the anemia of CKD guide.
Drugs that block hepcidin or protect ferroportin were only beginning human trials at the time of the 2019 Blood review and are not part of standard treatment.
Exam traps
- Low serum iron does not equal iron deficiency. Look at TIBC and ferritin before choosing iron.
- A normal ferritin does not rule out iron deficiency in inflammation; values up to 100 ng/mL remain compatible with it.
- Oral iron is not the fix for ACD: hepcidin blocks its absorption, and without true deficiency iron is generally avoided.
- A high reticulocyte count points to hemolysis (or a healthy marrow responding to blood loss), not ACD.
- Marked microcytosis with a high RBC count suggests thalassemia trait; ACD is usually normocytic or only borderline microcytic.
- High transferrin saturation, very high ferritin and ringed sideroblasts point to sideroblastic anemia, not ACD.
Practice question
A 58-year-old woman with long-standing, poorly controlled rheumatoid arthritis who takes naproxen has 3 months of fatigue. Hemoglobin is 9.6 g/dL, MCV 84 fL, and the reticulocyte count is low. Serum iron is 38 µg/dL (low), TIBC 205 µg/dL (low), transferrin saturation 18%, ferritin 340 ng/mL, and the soluble transferrin receptor is normal. Which of the following best explains her anemia?
A. Hepcidin-mediated degradation of ferroportin B. Depleted iron stores from NSAID-related gastrointestinal blood loss C. Defective heme synthesis with ringed sideroblasts D. Reduced beta-globin synthesis E. IgG autoantibodies causing extravascular hemolysis
Answer: A. Low iron with a low TIBC, a high ferritin and a normal sTfR in a patient with active inflammation is anemia of chronic disease: IL-6 raises hepcidin, ferroportin is degraded, and iron stays locked in macrophages.
- B: iron deficiency would give a high TIBC, a ferritin below 30 ng/mL (or at least below 100 with inflammation) and a high sTfR.
- C: sideroblastic anemia is an iron-loading state, with high serum iron, transferrin saturation above 50% and ringed sideroblasts in the marrow.
- D: beta-thalassemia trait causes microcytosis with a high RBC count and target cells, and an HbA2 above about 3.5%; her MCV is normal and her iron panel is inflammatory.
- E: warm autoimmune hemolysis would raise the reticulocyte count, not lower it.
Key takeaways
- ACD = inflammation → IL-6 → hepcidin → ferroportin degraded → iron trapped in macrophages and poorly absorbed.
- Cytokines also blunt EPO and shorten red cell survival; the anemia is mild, normocytic and hypoproliferative.
- Iron studies: low iron, low TIBC, ferritin normal or high (usually > 100 ng/mL), normal sTfR, marrow iron present.
- Iron deficiency is the reverse: high TIBC, ferritin < 30 ng/mL, high sTfR, absent marrow iron.
- Ferritin < 100 ng/mL with inflammation, a high sTfR or an sTfR index above 2 suggests added iron deficiency.
- Treat the underlying disease; give iron only for true deficiency; ESAs for selected patients (CKD, chemotherapy), without targeting Hb above 11 g/dL.
Sources
- Anemia of Chronic Disease — Merck Manual Professional Edition (2025)
- Weiss G, Ganz T, Goodnough LT. Anemia of inflammation — Blood (2019)
- Nairz M, Theurl I, Wolf D, Weiss G. Iron deficiency or anemia of inflammation? Differential diagnosis and mechanisms of anemia of inflammation — Wiener Medizinische Wochenschrift (2016)
- Iron Deficiency Anemia — Merck Manual Professional Edition (2025)
- Evaluation of Anemia — Merck Manual Professional Edition (2024)
- Thalassemias — Merck Manual Professional Edition (2026)
- Anemia of Inflammation or Chronic Disease — NIDDK (2018)
- EPOGEN (epoetin alfa) prescribing information — DailyMed (2024)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
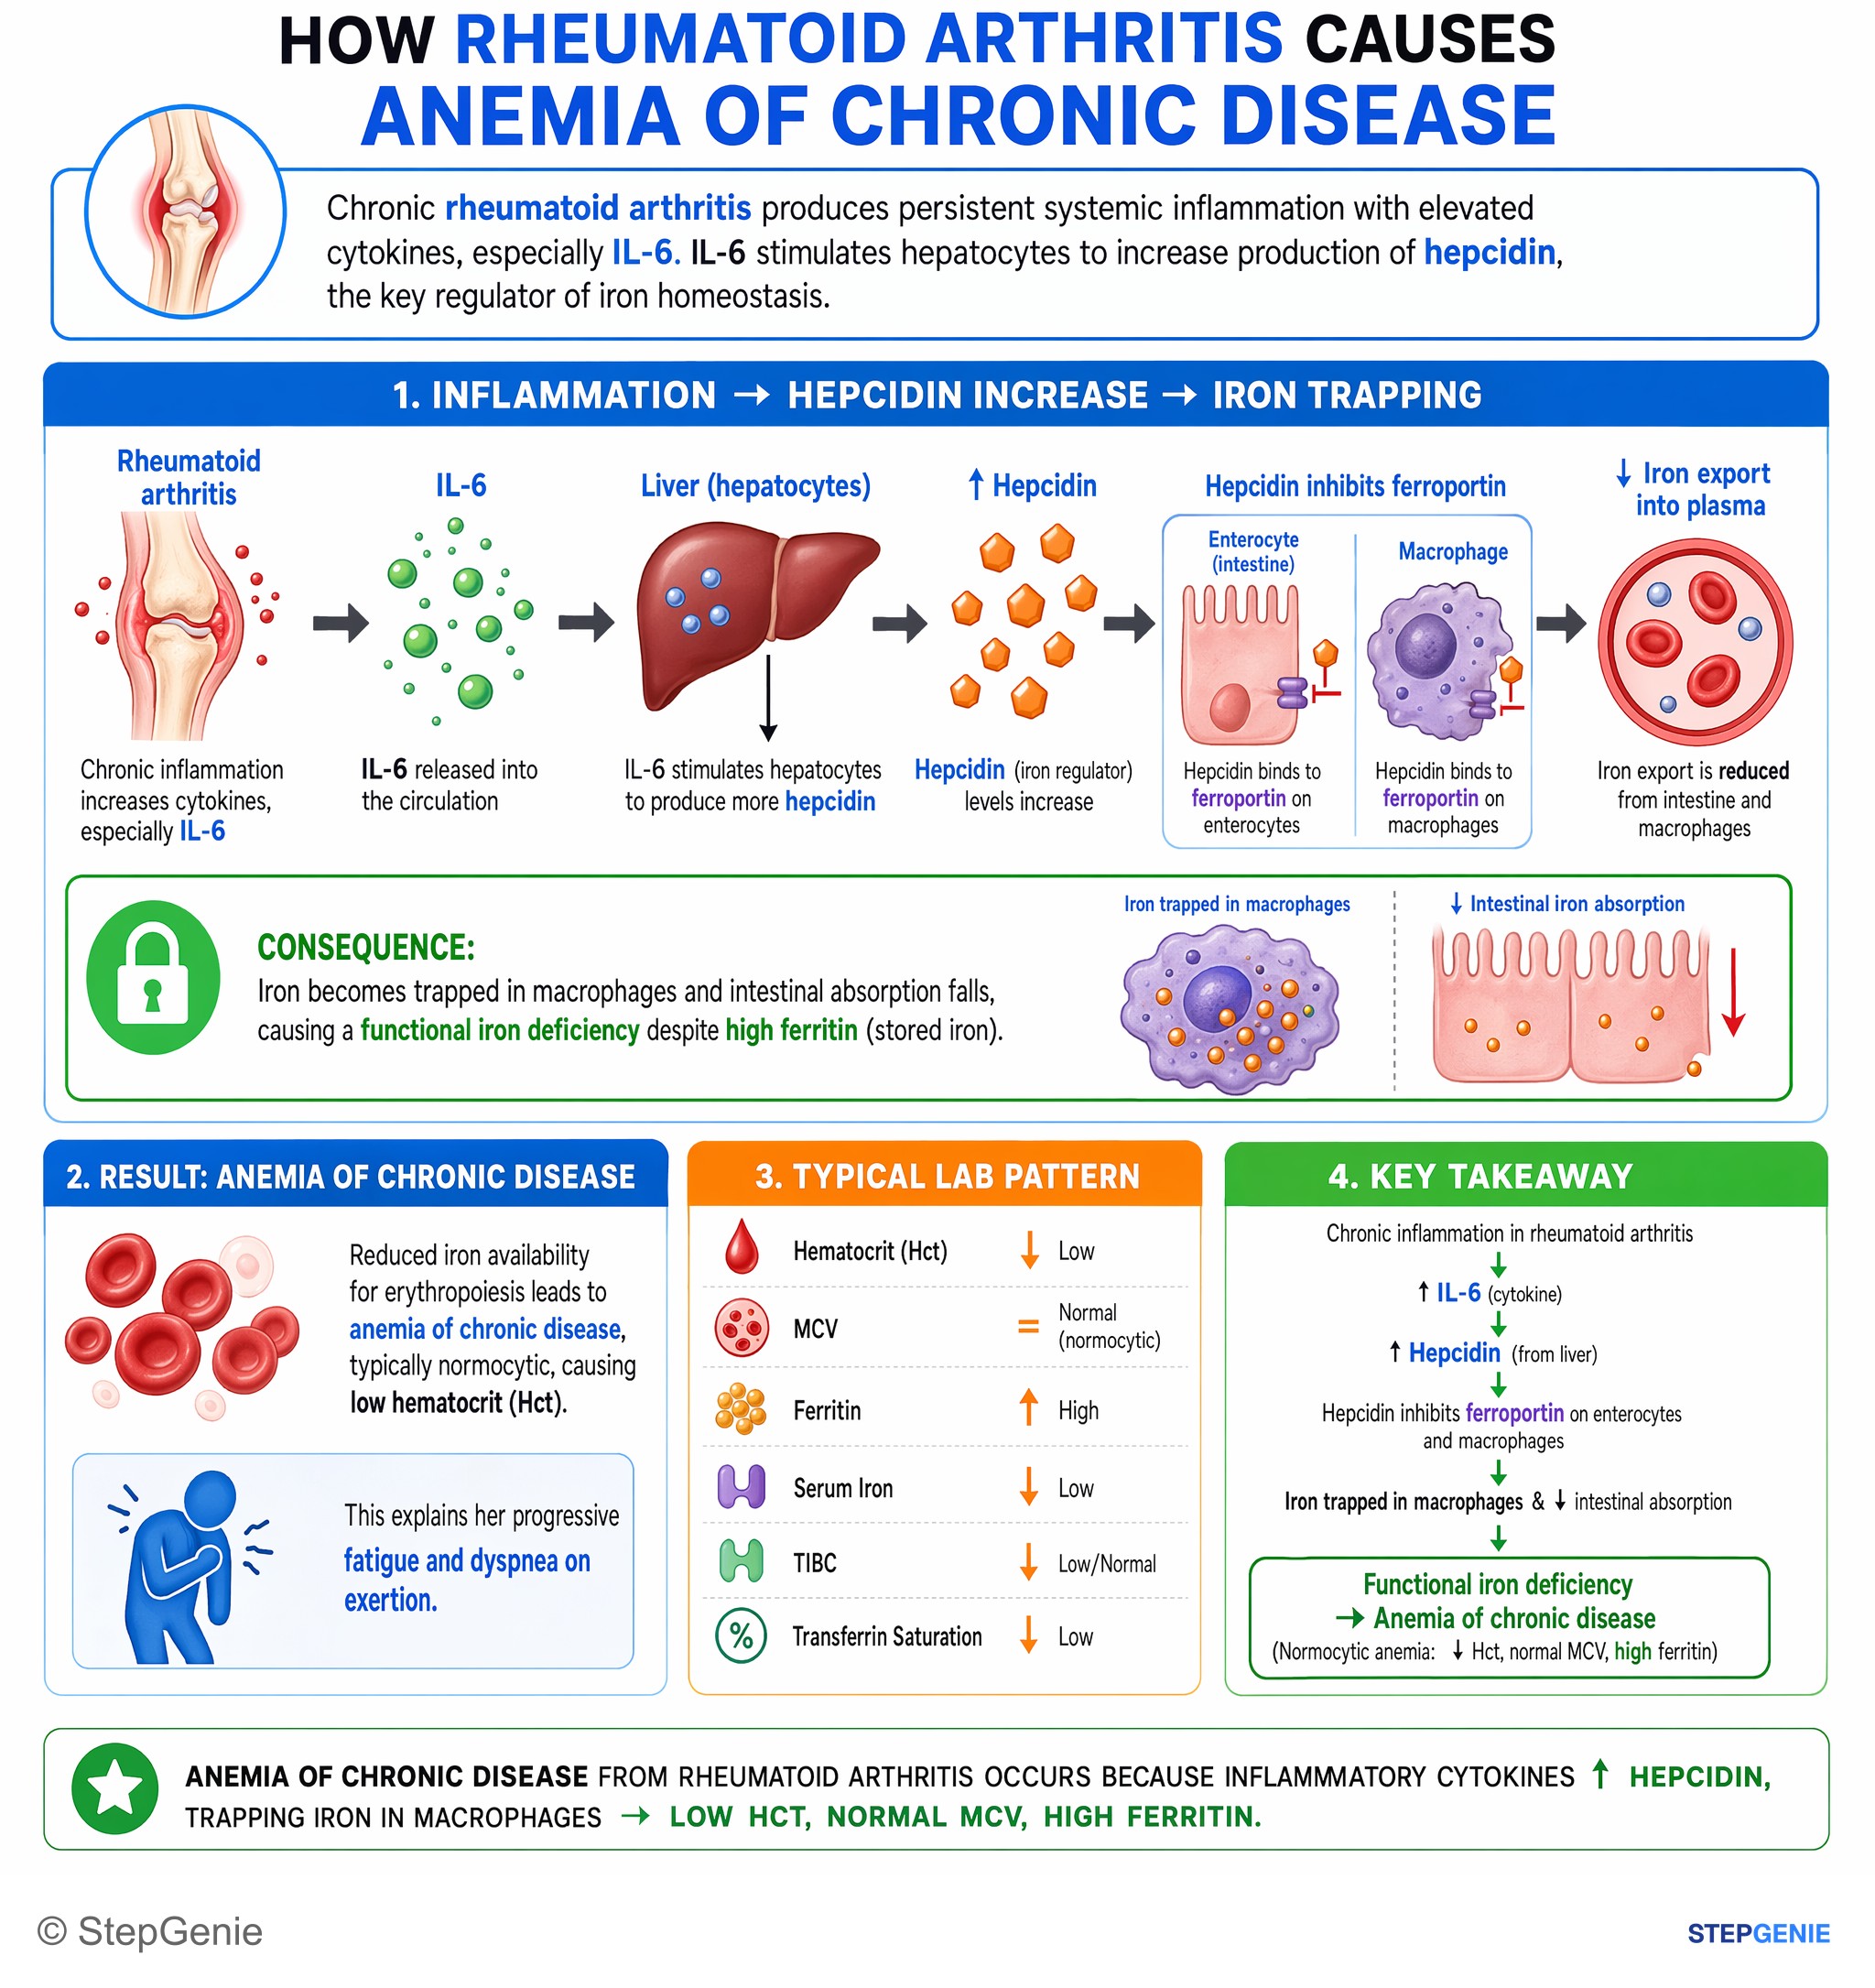
Anemia of chronic disease from rheumatoid arthritis: inflammatory cytokines ↑ hepcidin, trapping iron in macrophages → low Hct, normal…
USMLE Step 1Frequently Asked Questions
What are the iron studies in anemia of chronic disease?
Serum iron is low, TIBC (transferrin) is low or low-normal, transferrin saturation is low or normal, and ferritin is normal or high, usually above 100 ng/mL. The soluble transferrin receptor is normal and marrow iron is present. Iron deficiency is the opposite: TIBC is high, ferritin is below 30 ng/mL and the soluble transferrin receptor is high.
What does hepcidin do in anemia of chronic disease?
Inflammatory cytokines, mainly IL-6, stimulate the liver to make hepcidin. Hepcidin binds ferroportin, the only known cellular iron exporter, which is then internalized and degraded. Duodenal cells absorb less iron and macrophages keep the iron recycled from old red cells, so serum iron falls while iron stores stay full.
How do you tell anemia of chronic disease from iron deficiency anemia?
Look at TIBC and ferritin: anemia of chronic disease has a low TIBC and a normal or high ferritin, while iron deficiency has a high TIBC and a ferritin below 30 ng/mL. A normal soluble transferrin receptor favors anemia of chronic disease and a high one favors iron deficiency. In an inflamed patient, a ferritin below 100 ng/mL or an sTfR/log ferritin index above 2 (a cutoff from a 2019 Blood review, with some overlap) suggests both are present.
Is anemia of chronic disease microcytic or normocytic?
It is usually normocytic and normochromic at first and can become mildly microcytic over time. The reticulocyte count is low because red cell production is reduced. Marked microcytosis should prompt a search for iron deficiency or thalassemia trait.
Why is ferritin high in anemia of chronic disease?
Ferritin is the iron storage protein and also an acute-phase reactant. In inflammation, hepcidin traps iron inside macrophages so stores are full, and the inflammatory response raises ferritin further. For the same reason a normal ferritin does not exclude iron deficiency in an inflamed patient; values up to 100 ng/mL remain compatible with it.
What is the treatment for anemia of chronic disease?
The main treatment is controlling the underlying infection, inflammatory disease or cancer, which usually resolves the anemia. Iron is given only when true iron deficiency coexists, with IV iron used when oral iron fails or inflammation blocks absorption. Erythropoiesis-stimulating agents are reserved for selected patients such as those with CKD or chemotherapy-induced anemia, and transfusion for severe or unstable anemia.