Wernicke-Korsakoff syndrome is brain injury from thiamine (vitamin B₁) deficiency: acute Wernicke encephalopathy, with confusion, ophthalmoplegia (often with nystagmus) and ataxia, which, if untreated, often progresses to chronic Korsakoff syndrome, dominated by anterograde amnesia and confabulation. The lesions sit around the third ventricle and cerebral aqueduct, classically in the mammillary bodies and dorsomedial thalamus. The treatment rule is IV thiamine before glucose, because a carbohydrate load in a thiamine-depleted patient can precipitate or worsen the encephalopathy. The "Hotel B1" memory palace below stores the whole picture in one walk-through.
The memory palace: "Hotel B1"
Picture a run-down hotel called B1 (thiamine). A malnourished guest stumbles in off the street. Walk through it in order: front desk, lobby, upstairs suite, basement, guest book.
1. Front desk: thiamine before the sugar. The clerk offers the guest a glass of sugar water, but the manager knocks it away and hands over the B1 room key first. Rule: in anyone at risk, give IV thiamine before IV glucose.
2. The lobby (acute Wernicke): C-O-A.
- Confusion: the guest doesn't know where he is and is drowsy, inattentive and indifferent.
- Ophthalmoplegia: his eyes are stuck like a broken elevator (lateral rectus weakness, gaze palsies), and nystagmus makes them bounce.
- Ataxia: he crosses the lobby with slow, short, wide-based steps, as if the floor were tilting.
3. Upstairs suite (chronic Korsakoff): the confabulation suite. The guest book has blank pages for everything since check-in (anterograde amnesia) and a few torn-out older pages (retrograde amnesia; remote memories are spared more than recent ones). He fills the gaps with confident invented stories (confabulation), not to deceive: he believes them. He seems apathetic and unconcerned.
4. Basement (the lesions): the shrunken mammoth statues. Two small statues, the mammillary bodies, have shriveled, and the dorsomedial thalamus lamp beside them flickers. The damage wraps symmetrically around the central corridors: the third ventricle, the aqueduct and the fourth ventricle.
5. Guest book (who gets it): alcohol use disorder, hyperemesis gravidarum, bariatric surgery, starvation and refeeding, anorexia nervosa, cancer, AIDS and dialysis.
Why thiamine, and why glucose makes it worse
Thiamine pyrophosphate is the cofactor for pyruvate dehydrogenase, α-ketoglutarate dehydrogenase and branched-chain α-ketoacid dehydrogenase, and for transketolase in the pentose phosphate pathway (the enzyme cofactors are drilled in the pyruvate dehydrogenase cofactors mnemonic). Glucose metabolism depends on it, so a carbohydrate load, whether IV dextrose or refeeding after starvation, raises the demand for what little thiamine is left and can trigger Wernicke encephalopathy.
Alcohol makes deficiency likely in several ways at once: poor intake, impaired absorption from the gut, poor storage in the liver and increased demand. The wider spectrum of thiamine deficiency (dry and wet beriberi) is covered in the thiamine (beriberi and Wernicke) overview.
Wernicke vs Korsakoff side by side
| Feature | Wernicke encephalopathy | Korsakoff syndrome |
|---|---|---|
| Onset | Acute and sudden | Chronic; a late complication of untreated or repeated Wernicke encephalopathy |
| Core findings | Confusion, ophthalmoplegia (lateral rectus palsy, gaze palsies), horizontal and vertical nystagmus, wide-based ataxia | Anterograde amnesia, retrograde amnesia of varying degree, confabulation |
| Other findings | Sluggish or unequal pupils, vestibular dysfunction, hypothermia or postural hypotension; stupor can progress to coma | Disorientation to time, apathy or mild euphoria, reduced initiative |
| Lesions | Around the third ventricle, aqueduct and fourth ventricle: mammillary bodies, dorsomedial thalamus, periaqueductal gray, ocular motor and vestibular nuclei | Same circuitry, with degeneration of the thalamus and mammillary bodies |
| Response to thiamine | Eye signs start to improve within 24 hours; ataxia and confusion over days to months | Memory often doesn't recover fully |
| If untreated | Mortality 10–20%; about 80% of survivors develop Korsakoff syndrome | Severe cases often need residential care |
The memory circuit these lesions interrupt is mapped in the limbic system overview.
Diagnosis and treatment
- Diagnosis is clinical. There is no specific test. Serum thiamine is not routinely measured, because a normal level doesn't exclude the disorder, and imaging, spinal fluid and EEG show no characteristic changes, although MRI can support the diagnosis. Labs such as glucose, electrolytes and liver tests help rule out other causes.
- Treat on suspicion. Eye signs are common and confusion is often present, but not every patient has all three findings, and Wernicke encephalopathy is thought to be underdiagnosed, partly because its symptoms overlap with alcohol-related delirium.
- Thiamine first, and parenterally. No single dosing regimen has been proven best. Merck's Wernicke chapter lists 100 mg IV or IM immediately, then daily for at least 3–5 days; its thiamine-deficiency chapter describes a common higher-dose regimen of 500 mg IV three times a day for 2 days, then 250 mg IV or IM daily for 5 more days, with other B vitamins. Either way, give it before IV glucose, not after.
- Correct magnesium. Magnesium is a cofactor in thiamine-dependent metabolism, so hypomagnesemia should be corrected. Add fluids, electrolytes and multivitamins; alcohol cessation is essential.
- Prevent it. Undernourished patients should get parenteral thiamine, particularly when IV dextrose is needed, and thiamine is prudent before treatment in anyone with a reduced level of consciousness.
- Korsakoff syndrome is treated with thiamine, magnesium and hydration, abstinence from alcohol and memory rehabilitation; severe cases often need residential care.
Don't confuse it with
| Condition | Key clue | How to tell it apart |
|---|---|---|
| Wernicke encephalopathy | Confusion, eye signs and ataxia in a malnourished patient | Eye signs start improving within a day of IV thiamine |
| Alcohol withdrawal and delirium tremens | Tremor, sweating, tachycardia; delirium tremens usually starts 48–72 hours after the last drink, with hallucinations and autonomic instability | Treated with benzodiazepines (plus thiamine); see the alcohol withdrawal and delirium tremens memory palace |
| Portosystemic (hepatic) encephalopathy | Liver disease, asterixis, fetor hepaticus | Treated with lactulose, often with rifaximin |
| Hypoglycemia | Low fingerstick glucose | Needs dextrose now; in anyone at risk, give IV thiamine before or with it |
Exam traps
- Glucose before thiamine is the classic wrong answer.
- Waiting for the full triad, an MRI or a thiamine level delays treatment of a medical emergency.
- Confabulation isn't lying or malingering; the patient unconsciously fills memory gaps and believes the story.
- Korsakoff syndrome can follow severe or repeated delirium tremens, even without a typical Wernicke episode first.
- Low magnesium should be corrected alongside thiamine.
- Not only alcohol: hyperemesis gravidarum, bariatric surgery, anorexia nervosa and parenteral nutrition without vitamins all cause it.
Worked example
Vignette. A 26-year-old woman at 12 weeks' gestation is admitted for hyperemesis gravidarum after 3 weeks of vomiting and is started on dextrose-containing IV fluids. On day 2 she is confused and unsteady. She has horizontal nystagmus, bilateral lateral rectus weakness and a wide-based gait. Fingerstick glucose is 110 mg/dL. What is the most appropriate next step?
Answer: Give IV thiamine immediately, correct magnesium if low, and give no further dextrose until thiamine is on board.
Why not the alternatives:
- Brain MRI first: it can support the diagnosis, but imaging may show no characteristic abnormality and must not delay treatment.
- Serum thiamine level: not routinely used, and a normal value doesn't exclude deficiency.
- Increase the dextrose infusion: more carbohydrate without thiamine can worsen the encephalopathy.
- Lorazepam: treats alcohol withdrawal, which doesn't fit this picture.
- Lactulose: treats hepatic encephalopathy; nothing here suggests liver disease.
Key takeaways
- Wernicke = acute C-O-A (confusion, ophthalmoplegia with nystagmus, ataxia); Korsakoff = chronic amnesia with confabulation.
- Lesions: mammillary bodies and dorsomedial thalamus, around the third ventricle and aqueduct.
- IV thiamine before glucose; correct magnesium; treat on suspicion.
- Untreated: 10–20% mortality, and about 80% of survivors develop Korsakoff syndrome.
- Risk groups: alcohol use disorder, hyperemesis gravidarum, bariatric surgery, starvation and refeeding, anorexia nervosa, cancer, AIDS, dialysis.
- Recovery: eye signs improve within a day; memory often doesn't fully return.
Sources
- Wernicke Encephalopathy — Merck Manual Professional Edition
- Korsakoff Psychosis — Merck Manual Professional Edition
- Thiamine Deficiency — Merck Manual Professional Edition
- Alcohol Toxicity and Withdrawal — Merck Manual Professional Edition
- Portosystemic Encephalopathy — Merck Manual Professional Edition
- Wernicke-Korsakoff Syndrome — National Institute on Alcohol Abuse and Alcoholism (NIAAA)
- Thiamin — Linus Pauling Institute Micronutrient Information Center, Oregon State University
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
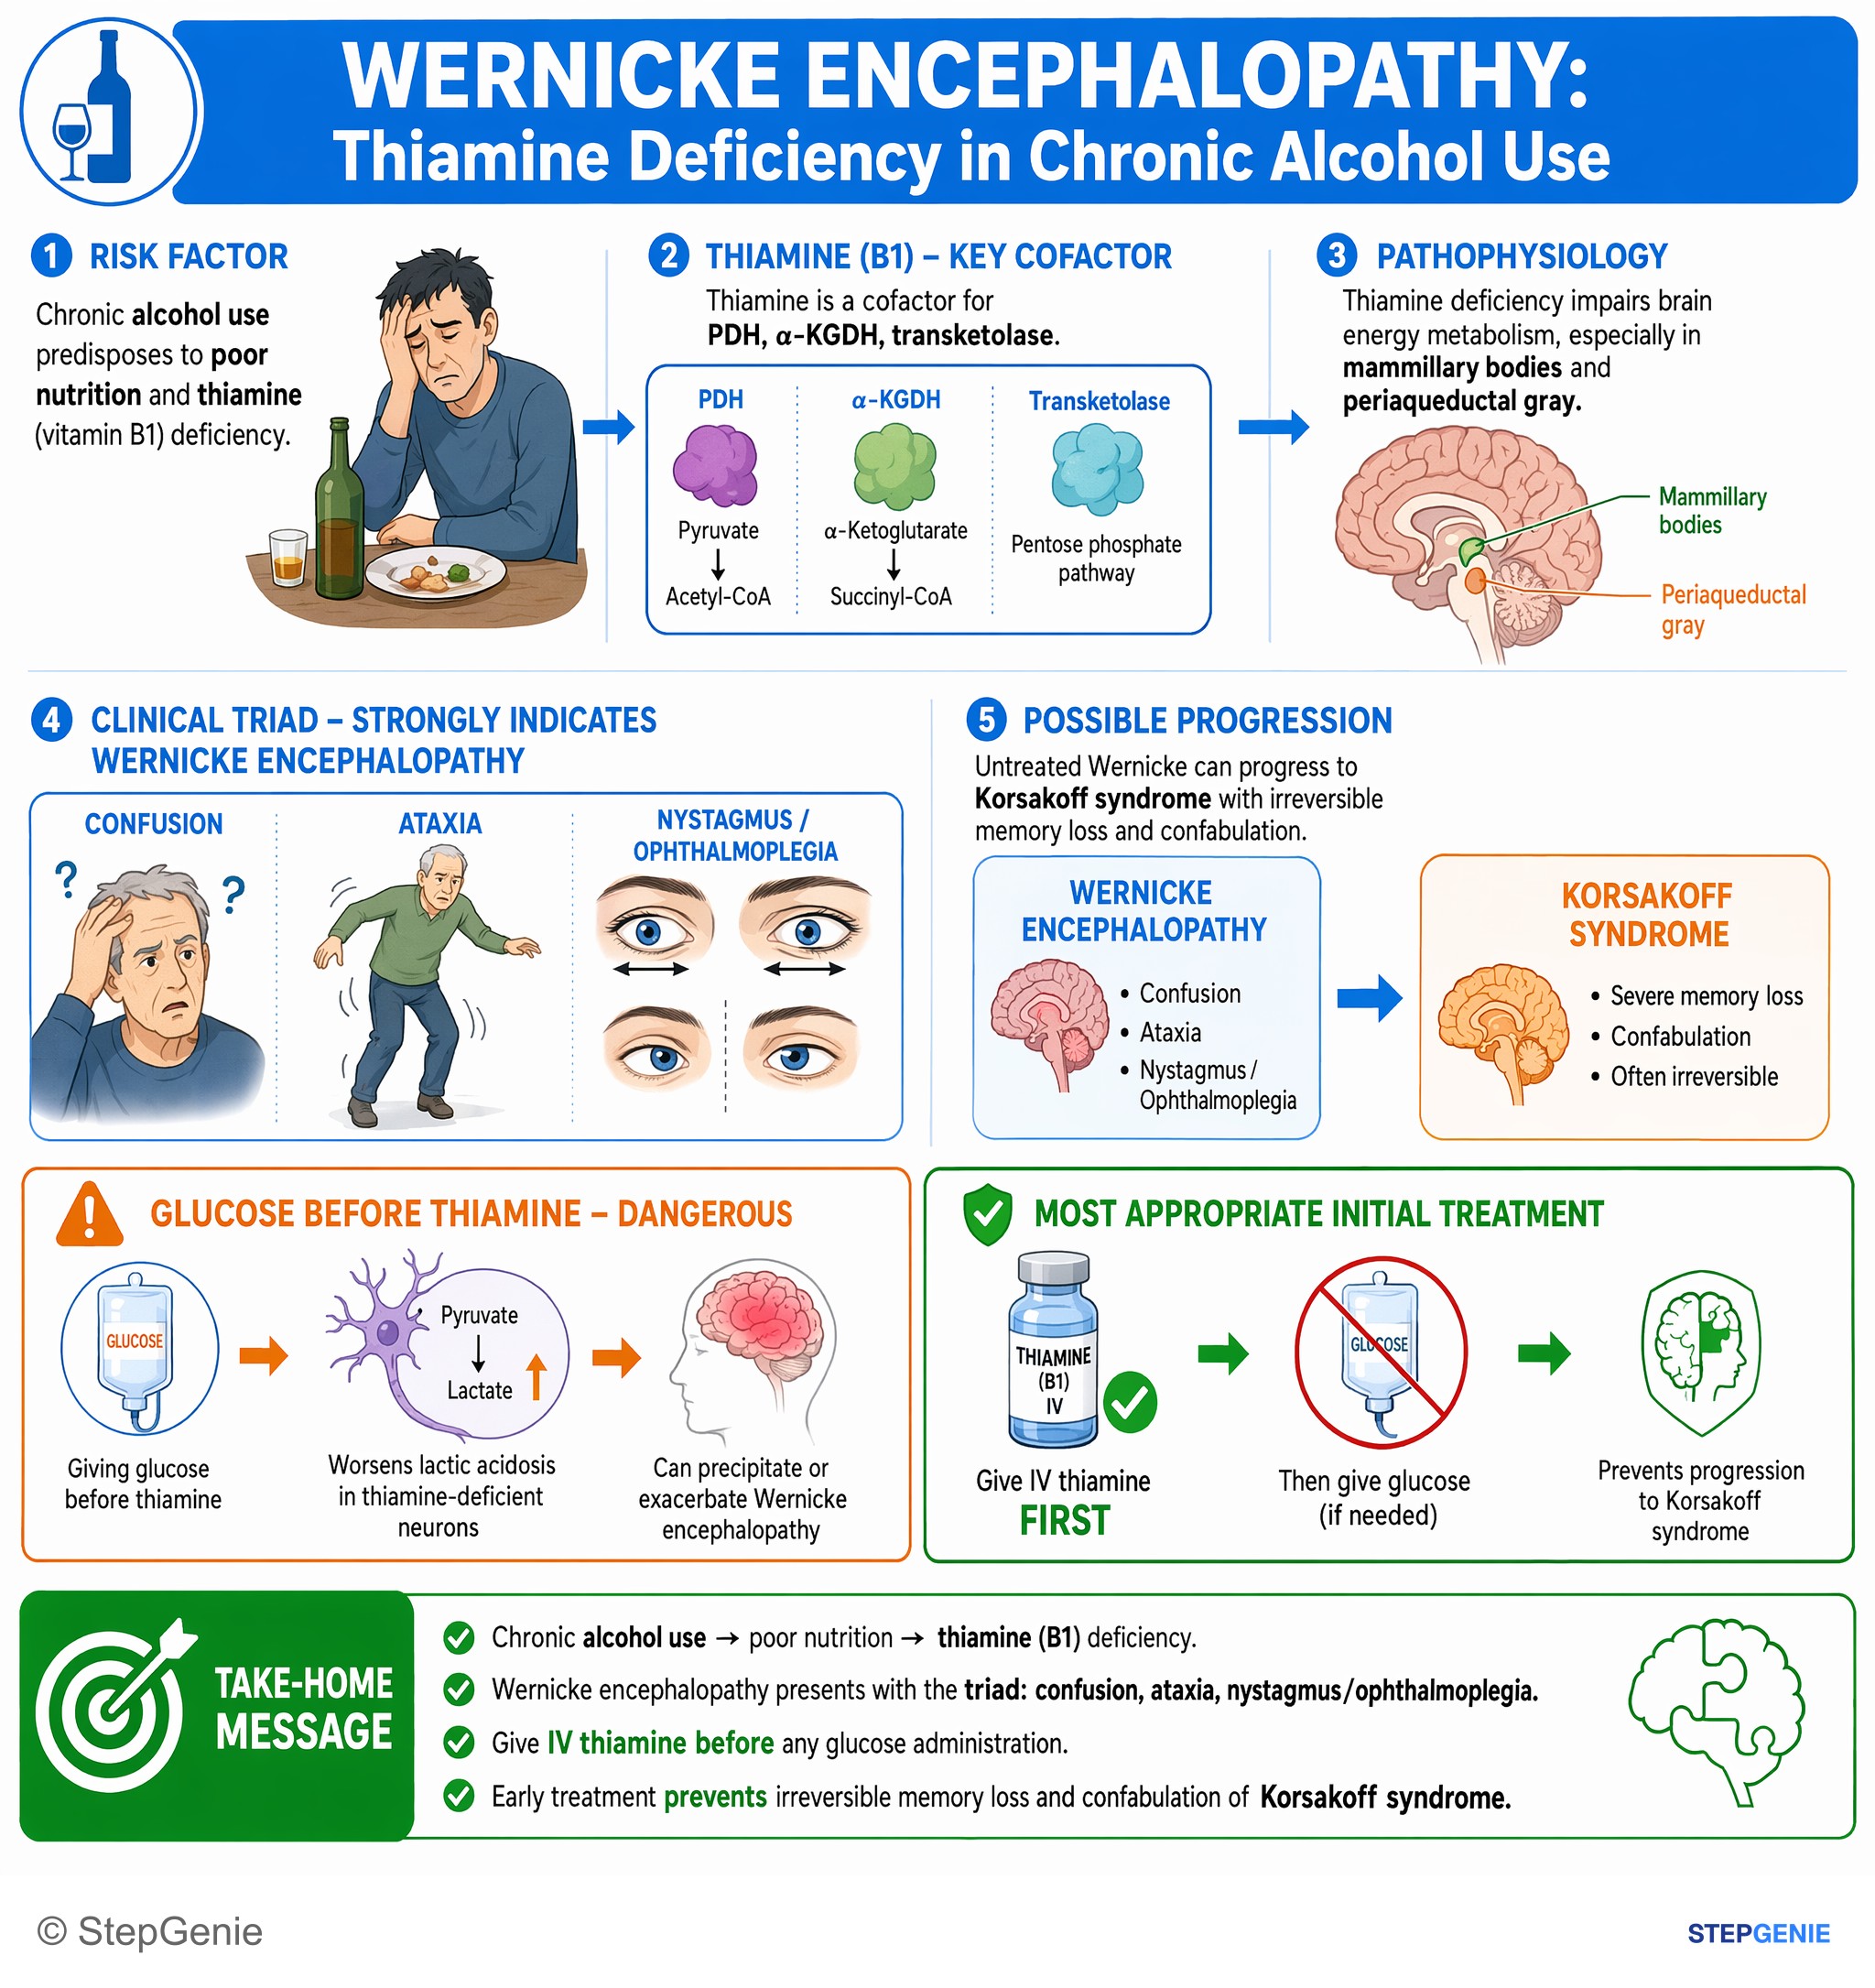
Wernicke encephalopathy from thiamine deficiency in an alcoholic: confusion, ataxia, nystagmus/ophthalmoplegia. Give IV thiamine before…
USMLE Step 2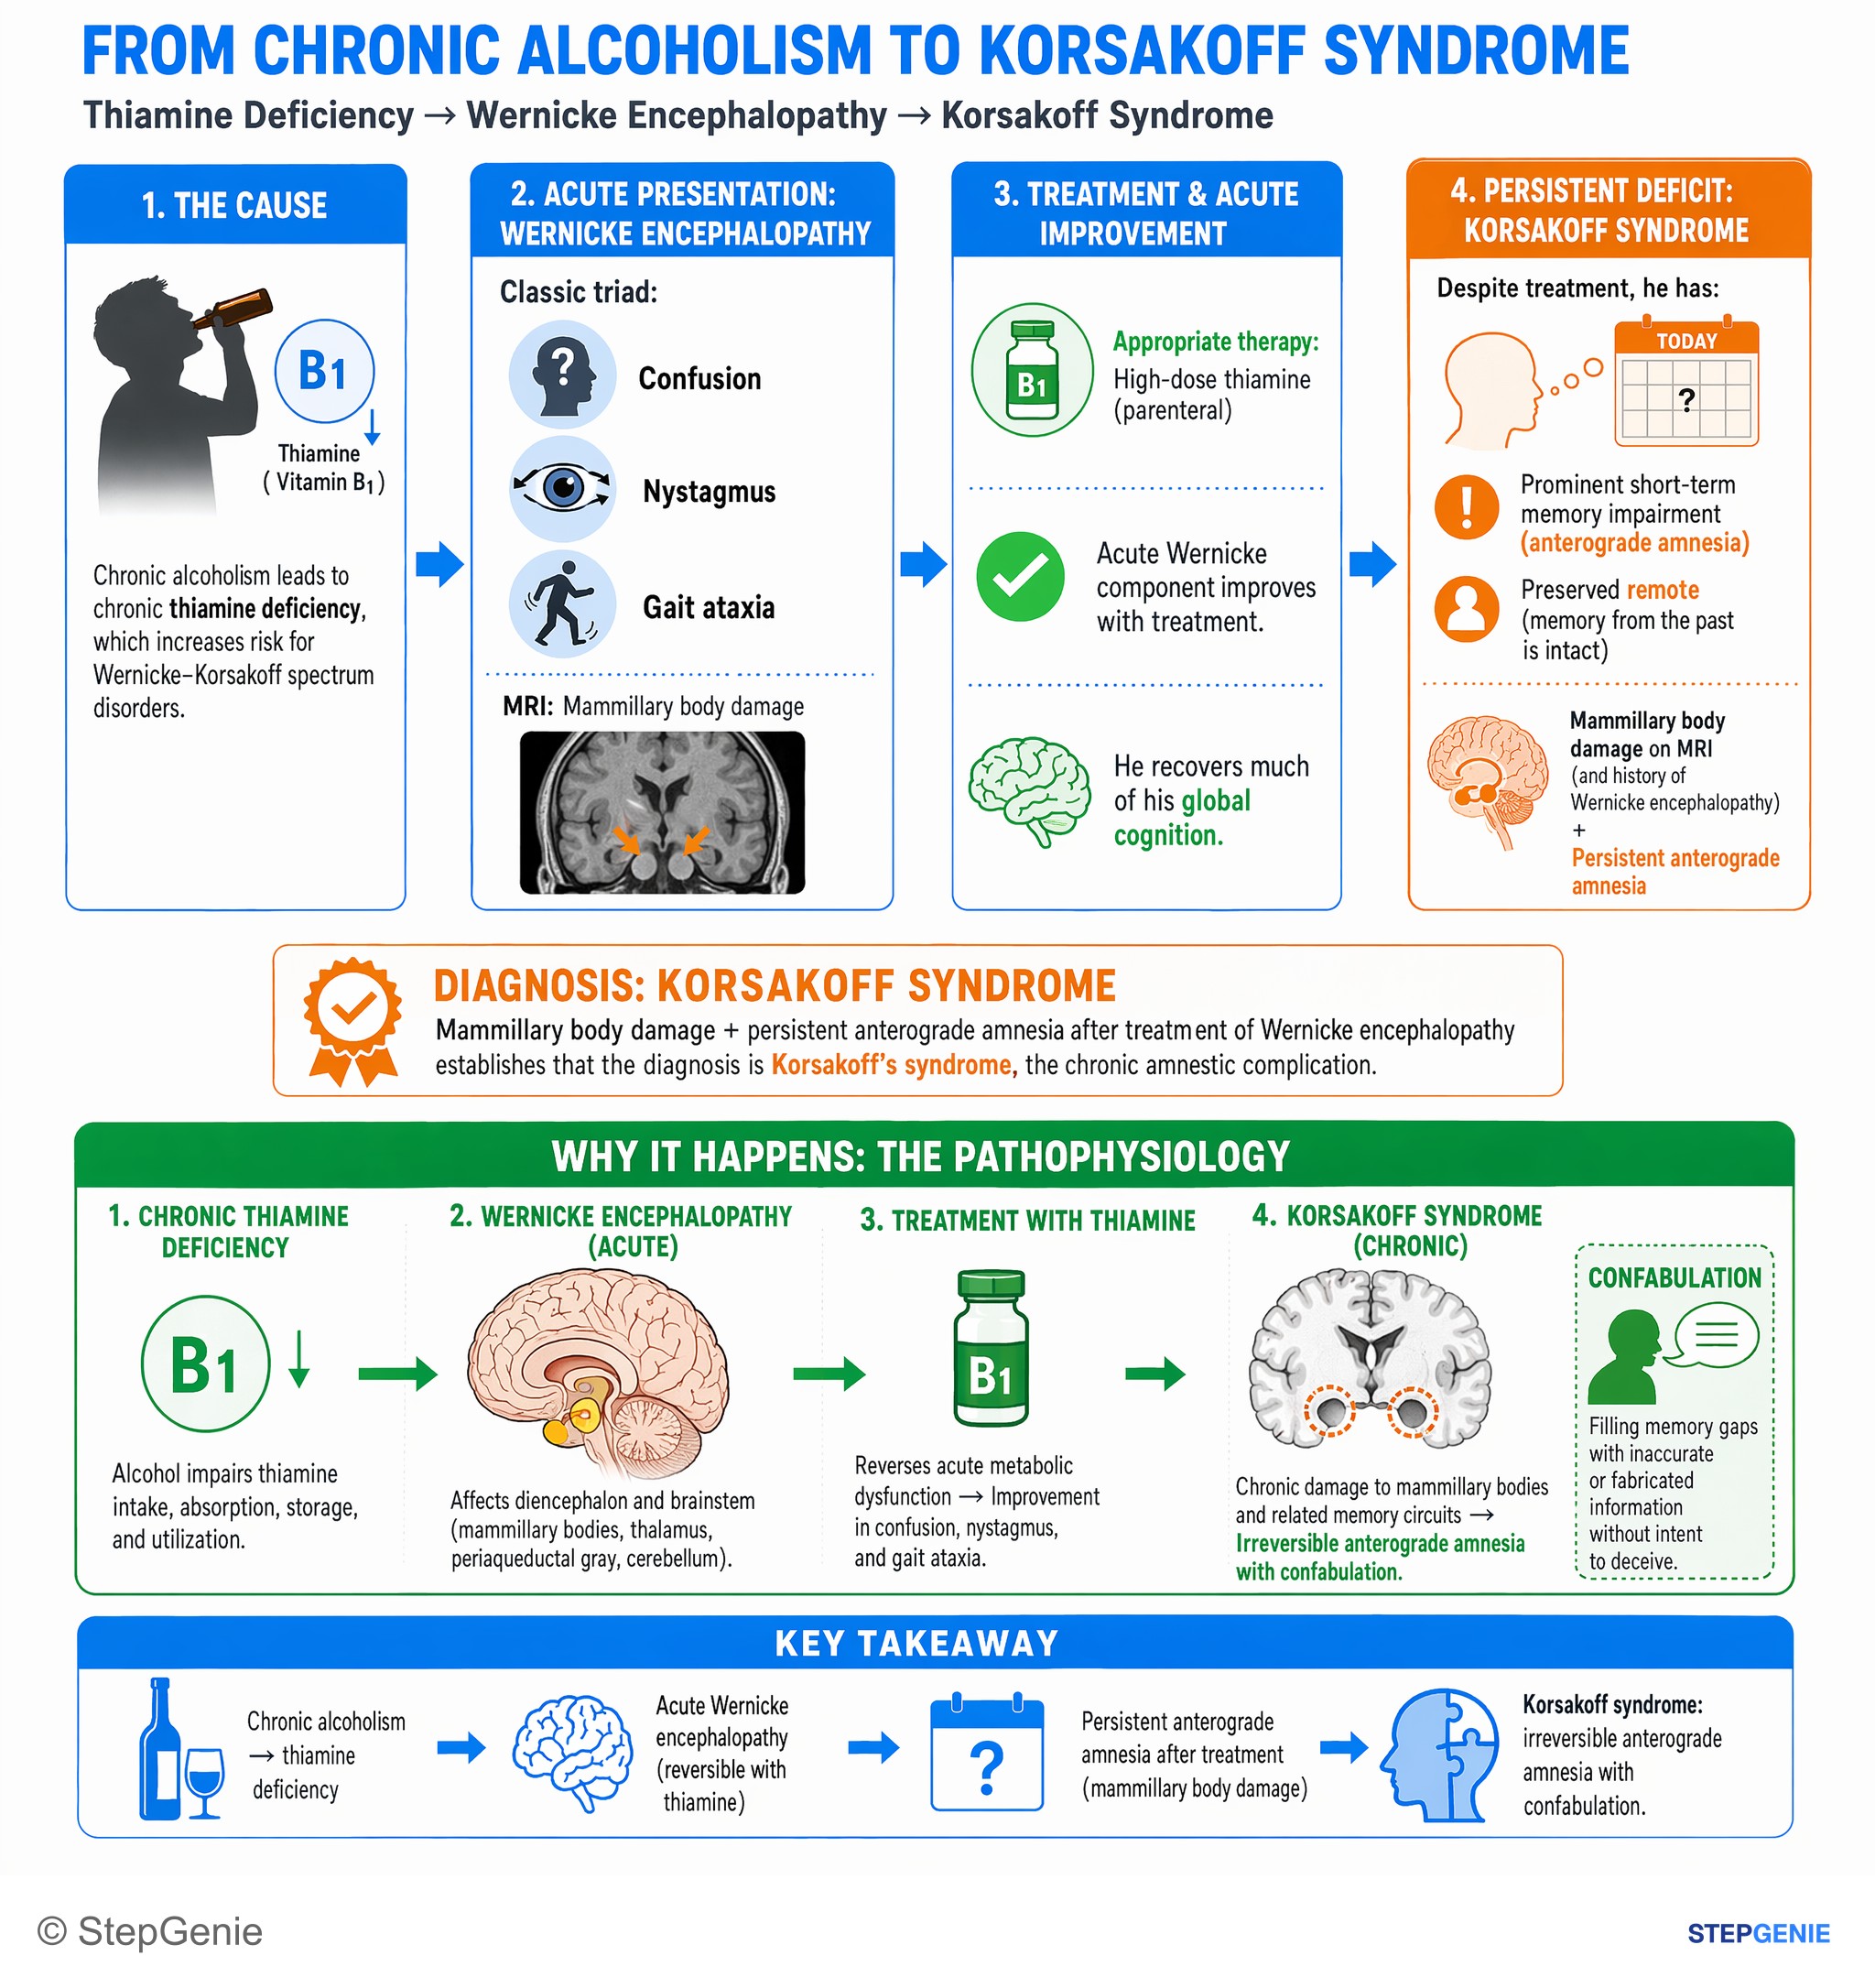
Korsakoff syndrome: chronic thiamine deficiency → mammillary body damage → irreversible anterograde amnesia with confabulation after acute…
USMLE Step 1Frequently Asked Questions
What is the mnemonic for the Wernicke encephalopathy triad?
COA: confusion, ophthalmoplegia and ataxia. Picture a confused hotel guest whose eyes are stuck like a broken elevator, bouncing with nystagmus, who staggers across a tilting lobby on a wide-based gait. Not every patient shows all three signs, so clinical suspicion alone, especially in someone malnourished or drinking heavily, is enough to give IV thiamine.
Why is thiamine given before glucose?
Thiamine pyrophosphate is a cofactor for pyruvate dehydrogenase, α-ketoglutarate dehydrogenase and transketolase, so a glucose load raises the demand for it. Giving IV dextrose or refeeding a thiamine-depleted patient can therefore precipitate or worsen Wernicke encephalopathy. People with alcohol use disorder and others at risk should get IV thiamine before glucose-containing fluids; glucose can follow once thiamine is on board.
What part of the brain is damaged in Wernicke-Korsakoff syndrome?
Lesions are symmetric around the third ventricle, cerebral aqueduct and fourth ventricle. The classic sites are the mammillary bodies and the dorsomedial thalamus, with involvement of the periaqueductal gray, locus ceruleus and the ocular motor and vestibular nuclei, which explain the eye signs and imbalance. Degeneration of the thalamus and mammillary bodies underlies the memory loss of Korsakoff syndrome.
Is Korsakoff syndrome reversible?
Usually not completely. Wernicke encephalopathy responds quickly if treated early: eye signs begin to improve within a day, although ataxia and confusion can take days to months to settle. Once Korsakoff syndrome develops, memory impairment often persists. Treatment is still thiamine, magnesium, hydration, alcohol abstinence and memory rehabilitation, and severe cases often need residential care.
Who gets Wernicke encephalopathy besides heavy drinkers?
Anyone who is thiamine-depleted, especially when given carbohydrate. Recognized settings include hyperemesis gravidarum, bariatric or other gastric surgery, anorexia nervosa, starvation and refeeding, cancer, AIDS, recurrent dialysis and parenteral nutrition without added vitamins. The same rule applies in every case: give parenteral thiamine before dextrose-containing fluids or refeeding.