Viral meningitis is inflammation of the meninges (fever, headache, neck stiffness) with a lymphocytic CSF and normal glucose; enteroviruses are the most common cause, and it usually resolves with supportive care. Viral encephalitis is inflammation of the brain itself, so it adds altered mental status, seizures or focal deficits; herpes simplex virus (HSV) is the most common cause of sporadic encephalitis in the US. Any suspected encephalitis gets IV acyclovir immediately, before PCR or MRI results, because untreated HSV encephalitis is often fatal. Confirm with CSF HSV PCR (repeat it in 48-72 hours if the first test is negative but suspicion stays high) and MRI, which shows temporal and orbitofrontal involvement; treatment lasts 14-21 days.
Meningitis vs encephalitis: where the line is
The clinical line is brain dysfunction. Confusion, personality change, seizures, aphasia or other focal deficits mean the parenchyma is involved (encephalitis, or meningoencephalitis when the meninges are inflamed too).
| Viral meningitis | Viral encephalitis | |
|---|---|---|
| What is inflamed | Meninges and subarachnoid space | Brain parenchyma |
| Symptoms | Fever, headache, nuchal rigidity, usually milder than bacterial meningitis | Fever and headache plus altered mental status, often with seizures and focal deficits; personality change, speech or memory problems |
| Usual causes | Enteroviruses (most common), HSV-2, VZV, HIV at seroconversion, arboviruses, lymphocytic choriomeningitis virus (LCMV), mumps | HSV (most common sporadic cause), arboviruses such as West Nile (epidemic), VZV, enteroviruses; autoimmune anti-NMDA receptor encephalitis is a mimic |
| Imaging | Not the key test | Contrast MRI; CT is much less sensitive for HSV |
| Treatment | Supportive; mild cases usually improve within 7-10 days; acyclovir for HSV or VZV; antiretrovirals for HIV | Empiric IV acyclovir until HSV and VZV are excluded, plus supportive care |
| Outcome | Usually resolves on its own over weeks | HSV encephalitis is often fatal untreated; survivors of severe disease often keep permanent deficits |
CSF findings: viral vs bacterial vs TB vs fungal
| CSF | Normal | Viral (meningitis or encephalitis) | Bacterial | Tuberculous | Fungal |
|---|---|---|---|---|---|
| Cells | 0-5/µL, lymphocytes | Raised, lymphocytes (neutrophils and lymphocytes may mix in the first 24-48 hours) | Often greatly raised, neutrophils | Raised, usually mixed | Raised, usually lymphocytes |
| Protein | Under 40 mg/dL | Mildly raised, usually under 150 mg/dL | Raised, typically 100-500 mg/dL | Raised | Raised |
| Glucose | Over 50% of blood glucose | Normal or only slightly low | Low (under 50% of blood; may be extremely low) | Low (may be extremely low) | Low (may be extremely low) |
| Other clues | Clear | RBCs and higher protein in HSV encephalitis (hemorrhagic necrosis) | Turbid; high opening pressure | ||
| Best tests | PCR (HSV, VZV, enterovirus); IgM for West Nile | Gram stain, culture, multiplex PCR | Acid-fast stain, PCR, culture, Xpert MTB/RIF | Cryptococcal antigen, India ink, fungal culture |
- A CSF glucose of 18 mg/dL or less, or a CSF-to-blood glucose ratio under 0.23, strongly suggests bacterial meningitis.
- Lymphocytes with a low glucose should make you think TB or fungus, not a virus. The full four-way comparison is in bacterial vs viral vs fungal meningitis.
- If a patient looks seriously ill and bacterial meningitis is possible, even with a "viral" CSF, start antibiotics and glucocorticoids and continue them until CSF cultures are negative.
CT before LP? When signs suggest raised intracranial pressure or a mass, image first: papilledema, focal deficits, focal seizures, a known CNS mass, a large acute stroke, or a suspected focal infection such as an abscess. If imaging will delay the tap, take blood cultures and start empiric treatment first; never let the scan delay therapy. CT can rule out a dangerous LP, but it is much less sensitive than MRI for HSV encephalitis.
The viruses and their clues
| Virus | Classic clue | Key point |
|---|---|---|
| Enteroviruses (coxsackievirus, echovirus) | Summer to early autumn; the most common viral meningitis | Supportive care |
| HSV-1 | Encephalitis at any time of year, mostly in people under 20 or over 40; olfactory aura (smell of rotten eggs or burnt meat), aphasia, personality change, early seizures | IV acyclovir for 14-21 days; see the herpesviruses overview |
| HSV-2 | Meningitis that recurs (Mollaret meningitis); HSV-2 may be the more common encephalitis strain in immunocompromised patients | IV acyclovir, then oral valacyclovir to finish 10-14 days |
| VZV | Meningitis or encephalitis | Acyclovir |
| West Nile virus | Summer outbreaks; worse in older and immunocompromised adults; tremor, myoclonus, parkinsonism, ataxia; acute flaccid paralysis from anterior horn cell damage, identical to poliomyelitis | Serum or CSF IgM; no drug treats it (supportive care); about 10% of neuroinvasive cases are fatal. More in arboviral encephalitis |
| Rabies | Bite (bats cause most US cases); agitation, hallucinations, hypersalivation and hydrophobia from laryngeal spasm, or an ascending paralytic form | Nearly always fatal once symptoms start; post-exposure prophylaxis prevents it. See the rabies case |
| HIV | Meningitis at seroconversion, early in infection | Antiretroviral therapy |
| LCMV | Contact with infected wild mice; autumn to winter | Supportive |
Only under 1% of West Nile infections become neuroinvasive, and about 80% cause no symptoms at all.
HSV encephalitis: management that matches current guidance
- Start IV acyclovir immediately in anyone with suspected encephalitis, and continue it until HSV and VZV encephalitis are excluded. Give empiric antibiotics too when bacterial infection can't be excluded.
- Dose (adults): 10 mg/kg IV every 8 hours, each dose infused at a constant rate over 1 hour (never as a bolus), with adequate hydration.
- Duration: 14-21 days of IV therapy (CDC 2021 STI guideline; Merck). The FDA label lists 10 days; current guidance prefers the longer course to prevent relapse.
- Confirm: CSF HSV PCR is sensitive and specific, but it can be falsely negative early; repeat it in 48-72 hours if suspicion remains, and keep acyclovir running meanwhile.
- Image: MRI shows edema in the temporal and orbitofrontal lobes; hemorrhagic necrosis explains RBCs and higher protein in the CSF.
- Neonates are different: acyclovir 20 mg/kg IV every 8 hours for 21 days when the CNS is involved or disease is disseminated (14 days if limited to skin and mucous membranes).
- HSV meningitis is not HSV encephalitis: HSV-2 meningitis gets IV acyclovir 5-10 mg/kg every 8 hours until improvement, then valacyclovir 1 g three times daily to complete 10-14 days; in patients with previously documented HSV-2 meningitis, a recurrence can be treated with oral valacyclovir for the whole course.
Acyclovir toxicity (Step 1 favorite): acyclovir can precipitate as crystals in the renal tubules and cause renal failure, which is why it is infused slowly with hydration. About 1% of patients get neurotoxicity (lethargy, confusion, tremor, hallucinations, seizures, coma), which can be mistaken for worsening encephalitis; the label advises caution in patients with renal impairment or underlying neurologic problems.
Late twist: anti-NMDA receptor encephalitis can follow HSV encephalitis, with a new decline within weeks. It is autoimmune, so it is treated with immunotherapy (glucocorticoids, plasma exchange or IV immune globulin), not more antivirals.
How USMLE tests it: traps
- Confusion, seizure or aphasia plus fever means encephalitis: the answer is IV acyclovir now, not "wait for the PCR" or "get an MRI first."
- Early neutrophils (first 24-48 hours) can appear in viral meningitis; a normal glucose and a well-looking patient keep you on the viral side.
- RBCs in the CSF of a patient with encephalitis fit HSV's hemorrhagic necrosis (a traumatic tap is the other explanation, so read them with the clinical picture).
- A normal CT or one negative PCR does not exclude HSV. MRI is far more sensitive, and early PCR can be falsely negative.
- Temporal lobe signs, such as memory loss, olfactory aura and behavior change, fit the limbic system anatomy HSV favors.
- Recurrent benign lymphocytic meningitis is HSV-2 (Mollaret).
- Older adult, summer, tremor or flaccid weakness points to West Nile; wild mice point to LCMV; seroconversion illness points to HIV.
Practice question
A 46-year-old woman is brought to the emergency department after a focal seizure. For 3 days she has had fever and headache, and since yesterday she has been confused and keeps smelling "burning rubber." Temperature is 38.9°C. She is disoriented and has difficulty naming objects; there is no papilledema or rash. CT of the head is normal. CSF shows 140 white cells/µL (85% lymphocytes), 350 red cells/µL, protein 85 mg/dL, glucose 64 mg/dL (serum 98 mg/dL), and a negative Gram stain. MRI is scheduled for the next morning, and CSF PCR results will take 2 days. Which of the following is the most appropriate next step?
A. Start IV acyclovir now B. Give supportive care only, as for enteroviral meningitis C. Wait for the CSF HSV PCR result before starting treatment D. Start high-dose IV methylprednisolone for autoimmune encephalitis E. Start IV ceftriaxone and vancomycin alone
Answer: A. Fever, confusion, an olfactory aura, aphasia and a focal seizure mean encephalitis with temporal lobe involvement, and lymphocytes, normal glucose, mildly raised protein and RBCs fit HSV encephalitis. Acyclovir is started at once, before MRI or PCR results, and continued for 14-21 days if HSV is confirmed.
- B: enteroviral meningitis is managed supportively, but this patient has brain dysfunction, and untreated HSV encephalitis is often fatal.
- C: HSV PCR can be falsely negative early; waiting 2 days for a test that may need repeating loses brain tissue.
- D: anti-NMDA receptor encephalitis can mimic viral encephalitis, and it also follows HSV encephalitis, but immunotherapy is not the first move in an acute febrile illness with an HSV-pattern CSF; the virus must be treated first.
- E: ceftriaxone plus vancomycin covers bacterial meningitis, which this CSF (lymphocytes, normal glucose) does not suggest; antibiotics may be added while bacterial infection is excluded, but alone they leave HSV untreated.
Key takeaways
- Meningitis: fever, headache, stiff neck without brain dysfunction; encephalitis adds altered mental status, seizures or focal deficits.
- Viral CSF: lymphocytes (early neutrophils possible), mildly raised protein, normal glucose; low glucose suggests bacteria, TB or fungus.
- Enteroviruses are the most common cause of viral meningitis (summer to early autumn), treated supportively; HSV-2 causes recurrent Mollaret meningitis.
- HSV is the top cause of sporadic encephalitis: temporal and orbitofrontal lobes, olfactory aura, seizures, RBCs in CSF.
- Empiric IV acyclovir now, 10 mg/kg every 8 hours for 14-21 days; repeat a negative early PCR in 48-72 hours; MRI beats CT.
- Acyclovir: crystal nephropathy (infuse slowly, hydrate) and neurotoxicity.
- West Nile: movement disorders and polio-like flaccid paralysis, diagnosed by IgM, treated supportively; rabies: hydrophobia, nearly always fatal once symptomatic.
Sources
- Encephalitis — Merck Manual Professional Edition (2026)
- Viral Meningitis — Merck Manual Professional Edition (2026)
- Acute Bacterial Meningitis (CSF findings table) — Merck Manual Professional Edition (2026)
- Herpes Simplex Virus (HSV) Infections — Merck Manual Professional Edition (2026)
- Viral Meningitis — CDC (2025)
- Genital Herpes: STI Treatment Guidelines, 2021 — CDC
- Acyclovir Injection Prescribing Information — DailyMed (2024)
- Clinical Signs and Symptoms of West Nile Virus Disease — CDC (2025)
- Clinical Testing and Diagnosis for West Nile Virus Disease — CDC (2025)
- Rabies — Merck Manual Professional Edition (2026)
- Encephalitis — National Institute of Neurological Disorders and Stroke (2026)
- Treatment and Prevention of West Nile Virus Disease — CDC (2025)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
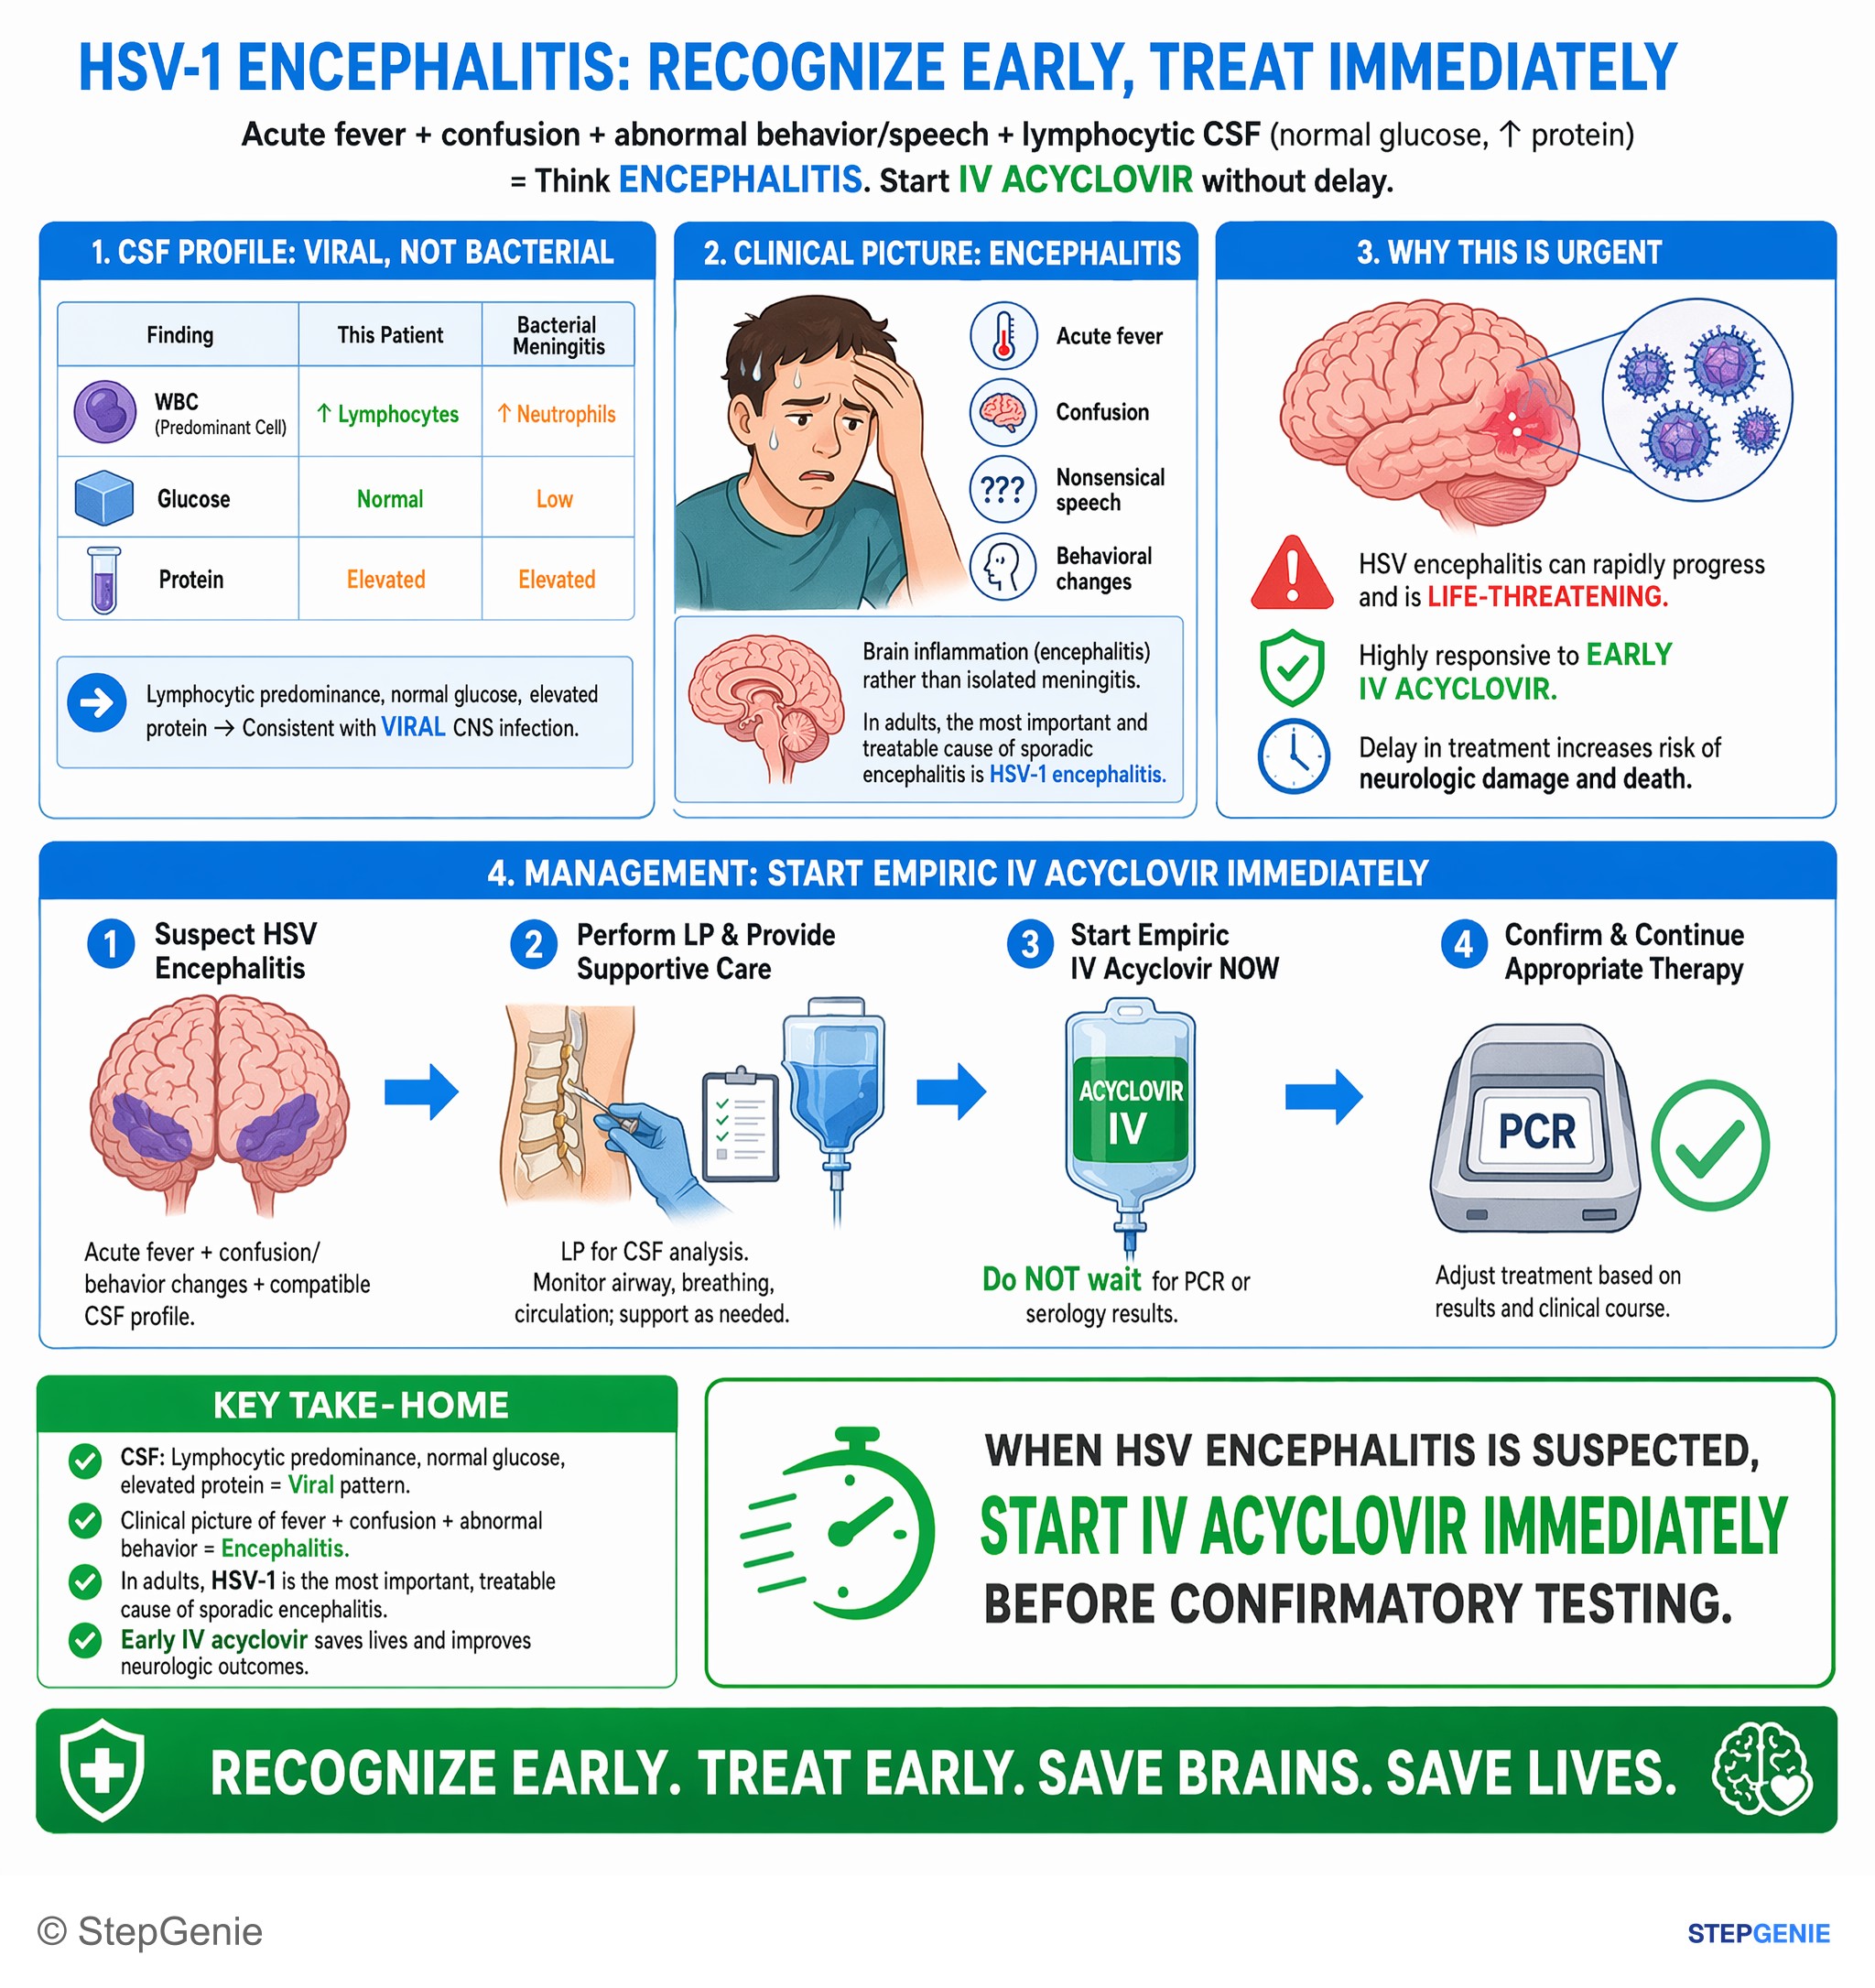
HSV encephalitis: acute fever, confusion, lymphocytic CSF with normal glucose → treat urgently with IV acyclovir before confirmatory…
USMLE Step 2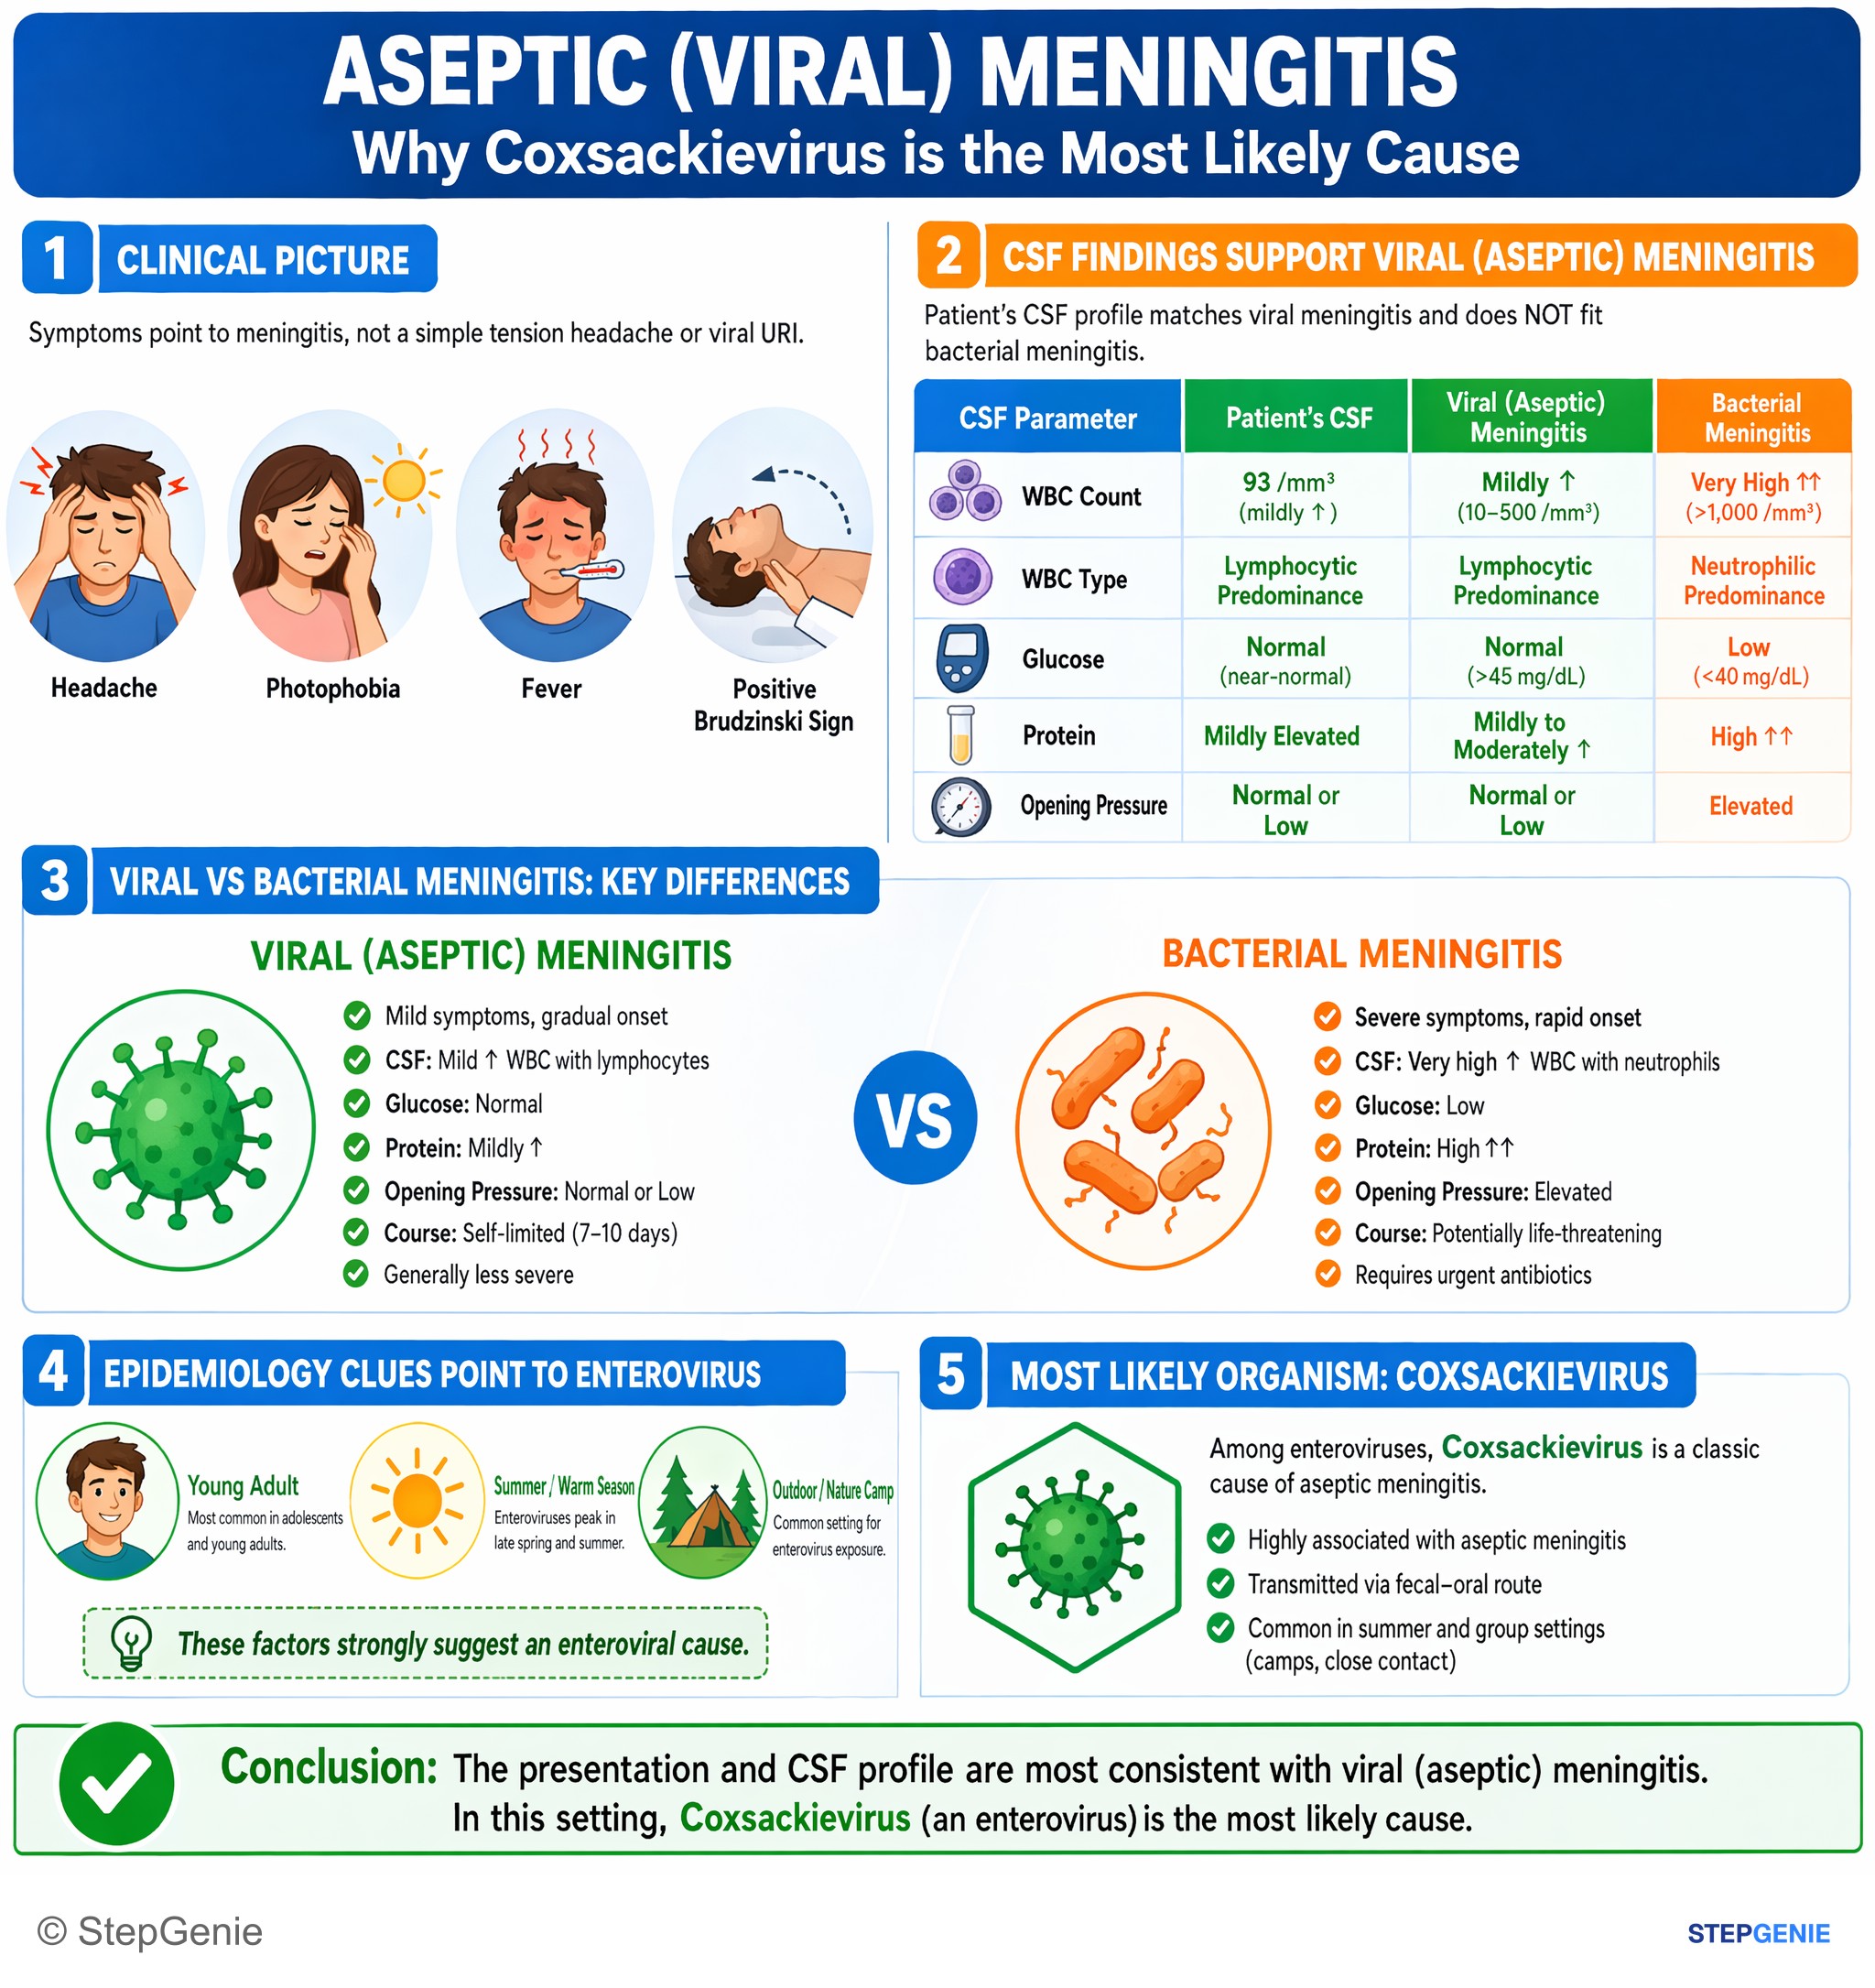
Viral meningitis (aseptic): lymphocytic CSF, near-normal glucose, mildly ↑ protein, low/normal opening pressure; young adult…
USMLE Step 1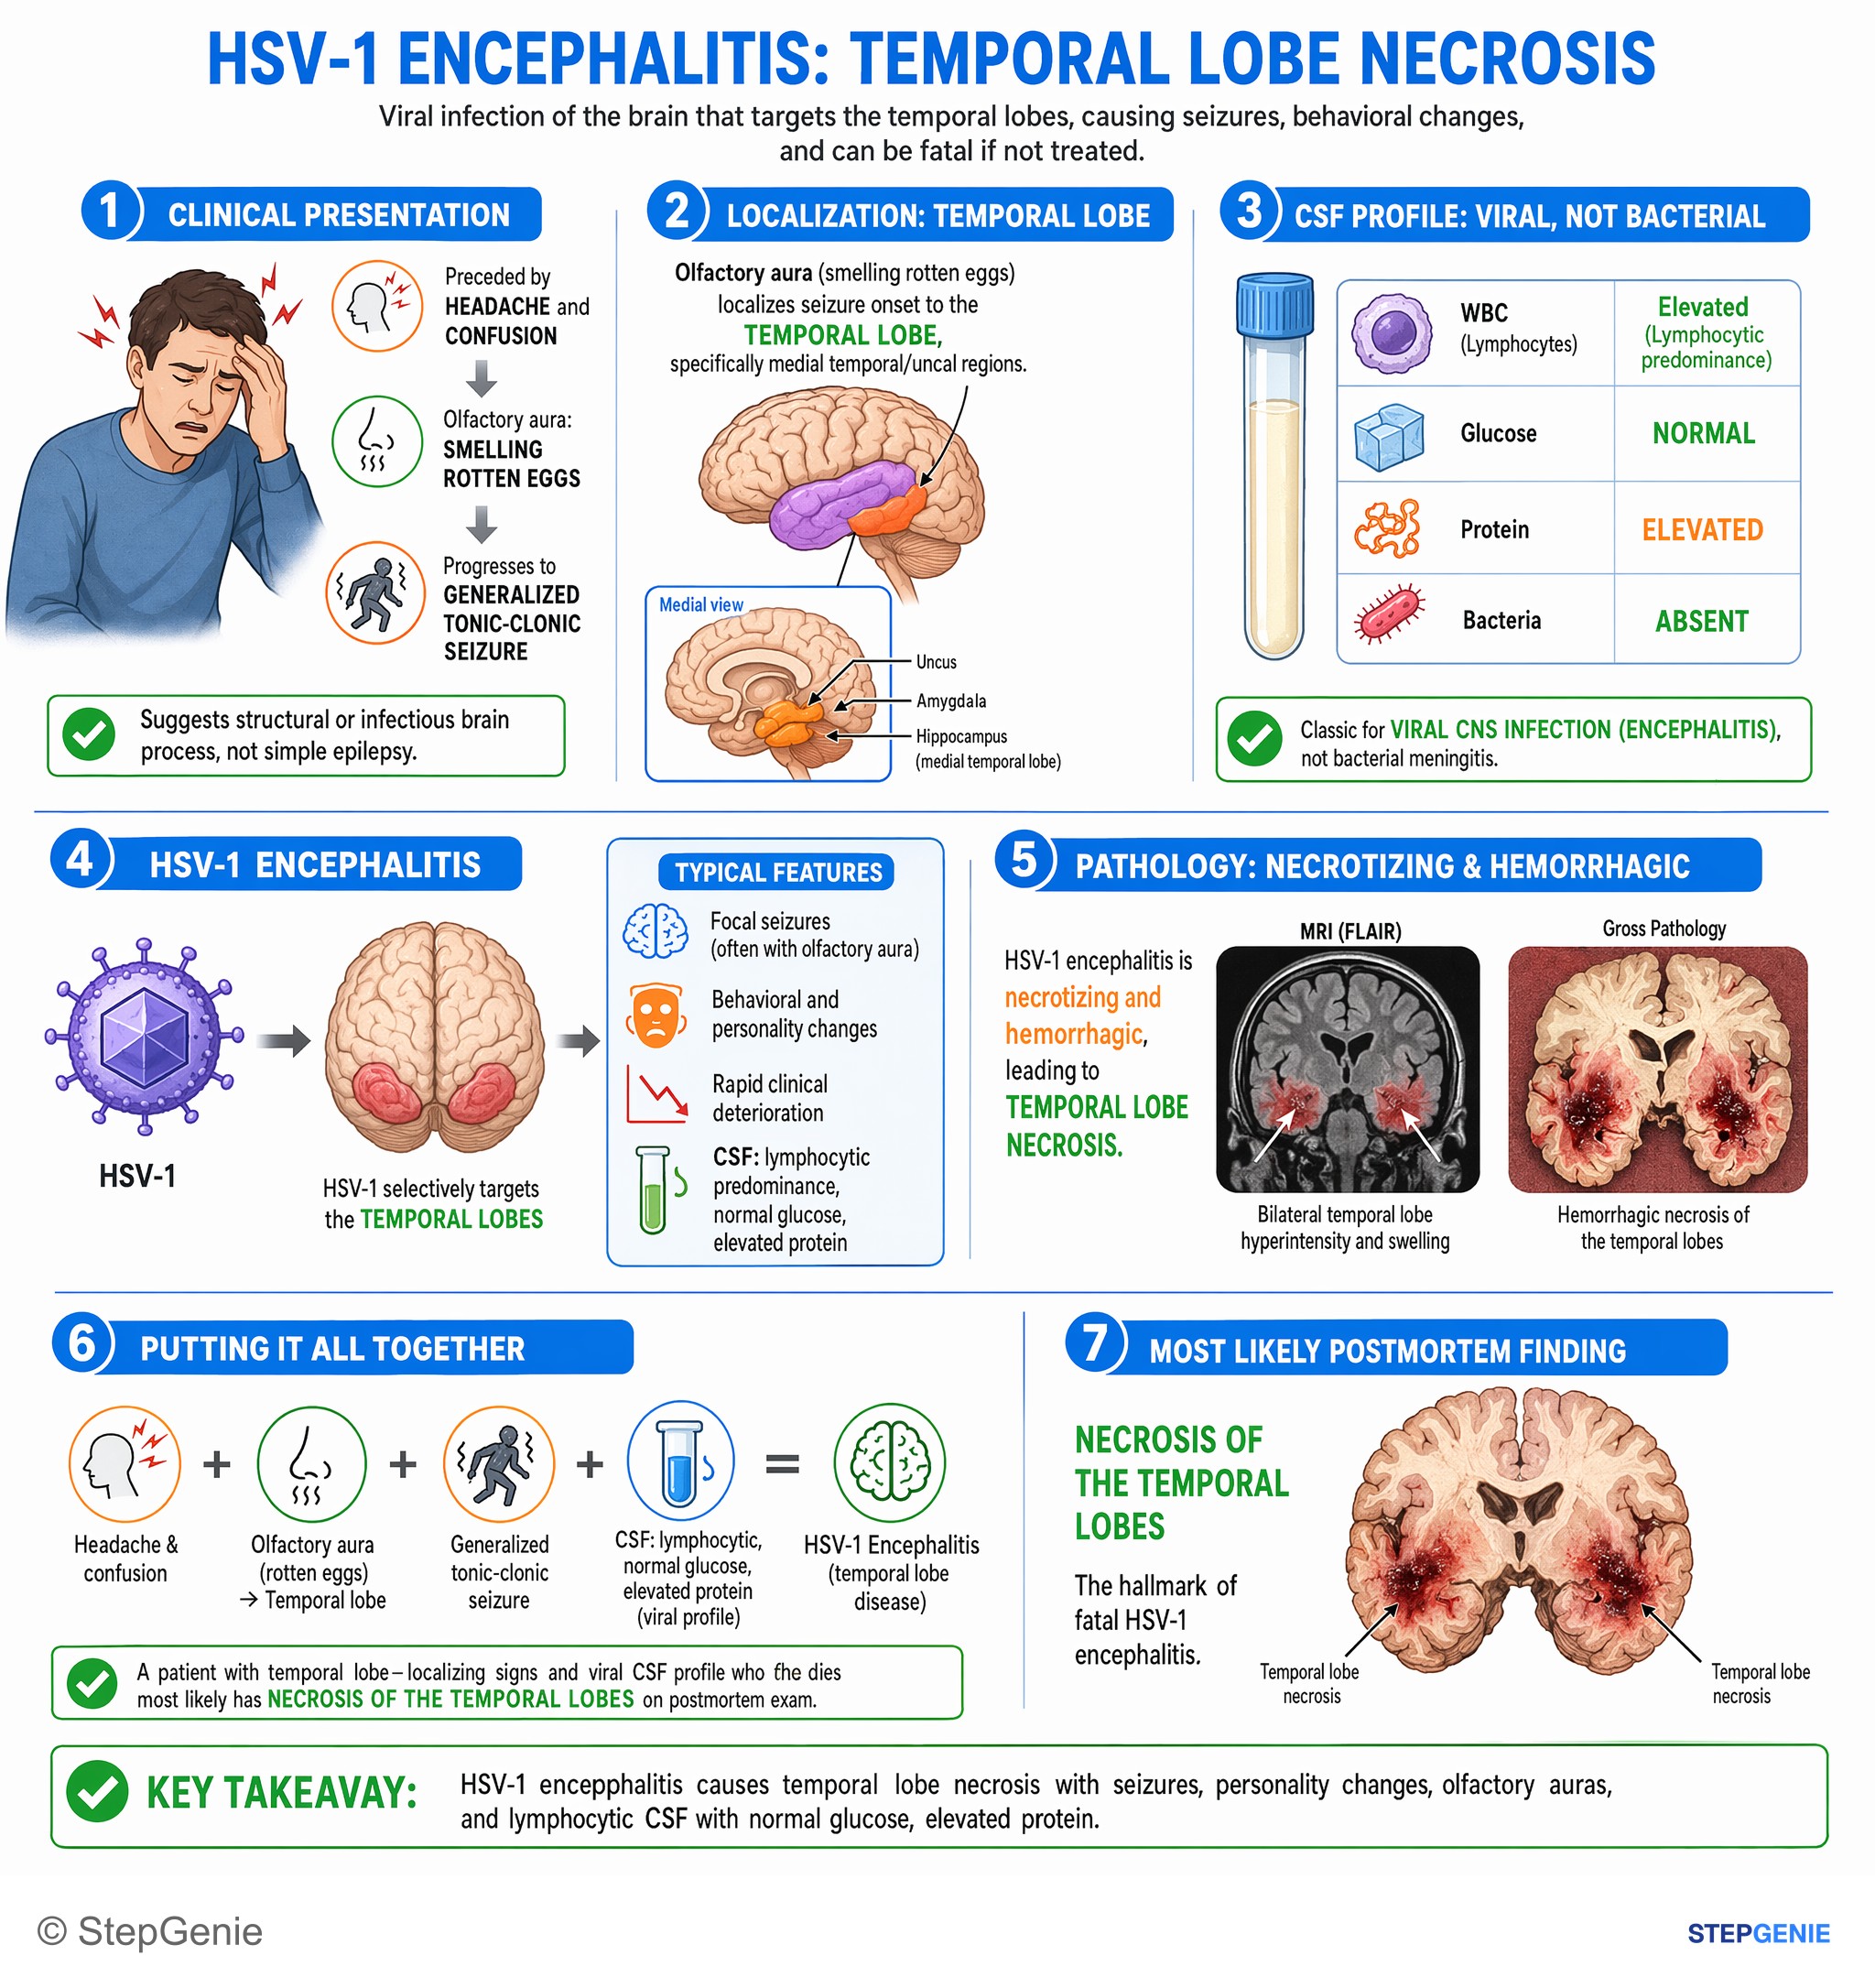
HSV-1 encephalitis causes temporal lobe necrosis with seizures, personality changes, olfactory auras, and lymphocytic CSF with normal…
USMLE Step 1Frequently Asked Questions
What is the difference between viral meningitis and encephalitis?
Viral meningitis is inflammation of the meninges and subarachnoid space, causing fever, headache and neck stiffness, and it usually resolves with supportive care. Viral encephalitis is inflammation of the brain tissue itself, so it adds altered mental status, often with seizures, focal deficits, personality change or speech problems. Encephalitis is more dangerous: HSV, its most common sporadic cause in the US, is often fatal without treatment, so suspected encephalitis gets IV acyclovir right away.
What are the CSF findings in viral meningitis?
Viral meningitis typically shows a raised white cell count with lymphocyte predominance, although neutrophils and lymphocytes can be mixed in the first 24 to 48 hours. Protein is mildly raised, usually under 150 mg/dL, and glucose is normal or only slightly low. The Gram stain is negative, and PCR can identify enteroviruses, HSV, varicella-zoster virus or West Nile virus. A low glucose with lymphocytes suggests tuberculous or fungal meningitis instead.
What is the most common cause of viral meningitis?
Non-polio enteroviruses, such as coxsackieviruses and echoviruses, are the most common cause of viral meningitis in the US, with most cases in summer and early autumn. Other causes include HSV-2 (which can cause recurrent Mollaret meningitis), varicella-zoster virus, HIV at seroconversion, arboviruses such as West Nile virus, lymphocytic choriomeningitis virus from wild mice, and mumps. Most people with mild viral meningitis recover on their own within 7 to 10 days.
How is HSV encephalitis treated?
IV acyclovir is started immediately in anyone with suspected encephalitis, without waiting for PCR or MRI results, and continued until HSV and varicella-zoster encephalitis are excluded. The usual adult dose is 10 mg/kg every 8 hours, each dose infused over 1 hour with good hydration to avoid crystal nephropathy. For confirmed HSV encephalitis, CDC and Merck recommend 14 to 21 days of IV therapy; neonates with CNS disease receive 20 mg/kg every 8 hours for 21 days.
Can the CSF HSV PCR be negative in HSV encephalitis?
Yes. CSF HSV PCR is sensitive and specific, but it can be falsely negative early in the illness. If clinical suspicion remains high, the test should be repeated in 48 to 72 hours, and acyclovir should be continued in the meantime. MRI also helps, because it is far more sensitive than CT and typically shows edema in the temporal and orbitofrontal lobes, so a normal CT does not exclude HSV encephalitis.
Why are there red blood cells in the CSF in HSV encephalitis?
HSV encephalitis causes hemorrhagic necrosis, mainly in the temporal and orbitofrontal lobes, which can release red blood cells into the CSF and raise the protein. Together with a lymphocytic pleocytosis and normal glucose, red cells in a patient with fever, confusion, seizures or aphasia point toward HSV encephalitis. A traumatic lumbar puncture can also add red cells, so the finding has to be read alongside the clinical picture and MRI.