A meningioma is a usually benign, slow-growing, extra-axial tumor that arises from arachnoid cap cells and is attached to the dura. It is the most common primary brain and other CNS tumor: 42.6% of all primary tumors in the 2025 CBTRUS report (US diagnoses 2018-2022). The classic patient is a middle-aged or older woman with slowly progressive headache, focal seizures or a focal deficit; contrast MRI shows a well-circumscribed, homogeneously enhancing dural-based mass, often with a dural tail, and histology shows whorls and psammoma bodies. Most are CNS WHO grade 1: small asymptomatic tumors can be watched with serial MRI, symptomatic or growing ones are removed, and radiosurgery or radiotherapy treats residual, inaccessible or higher-grade disease. The risk factors to know are female sex, prior ionizing radiation and NF2-related schwannomatosis (multiple meningiomas).
The Q-bank vignette
A 52-year-old woman has 6 months of progressive headaches and intermittent focal seizures involving her right hand. Her family has noticed a gradual change in her personality, and she has trouble planning at work. Examination shows mild weakness of the right arm. MRI of the brain with contrast shows a well-circumscribed, extra-axial mass along the left frontal convexity with homogeneous enhancement and a "dural tail." There is surrounding vasogenic edema with mild midline shift.
Which of the following is the most likely diagnosis?
A. Glioblastoma B. Meningioma C. Metastatic brain tumor D. Oligodendroglioma E. Vestibular schwannoma
Read the stem in three passes
- Where is it? Extra-axial and dural-based. Meningiomas usually compress the brain from outside rather than invading it.
- What does it look like? Well circumscribed, homogeneous enhancement and a dural tail: the textbook meningioma.
- What does it do? A left frontal convexity mass irritates the cortex (focal seizures of the right hand) and presses on the motor strip (right arm weakness) and the frontal lobe (personality and planning change). Merck lists focal seizures and cognitive deficits as the typical convexity findings, followed later by raised intracranial pressure.
Answer: B. Meningioma
A course of months in a middle-aged woman, plus a dural-based, homogeneously enhancing mass with a dural tail, is a meningioma until proven otherwise; it is the only brain tumor that is more common in women (Merck). Vasogenic edema and mass effect explain the symptoms even though the tumor is usually benign. Dexamethasone reduces the edema, antiseizure medication controls the seizures, and a symptomatic convexity tumor like this one is usually resected.
Why every other choice is wrong
- A. Glioblastoma: an intra-axial, infiltrative astrocytic tumor (glioblastoma, IDH-wildtype, CNS WHO grade 4). MRI shows ring enhancement around central necrosis with marked edema, and it can cross the corpus callosum ("butterfly glioma"). Histology shows pseudopalisading necrosis and microvascular proliferation. It is the most common primary malignant brain tumor (13.7% of all primary tumors and 52.2% of malignant ones), with a median observed survival of about 8 months (CBTRUS). Review the glioblastoma Q-bank breakdown.
- C. Metastatic brain tumor: brain metastases are about 10 times more common than primary brain tumors (Merck). They classically sit intra-axially at the gray-white junction, are often multiple and enhance with edema out of proportion to their size, in a patient with lung, breast, kidney or colon cancer or melanoma. Imaging can mislead, so an atypical mass may need a biopsy (Merck).
- D. Oligodendroglioma: an intra-axial, usually frontal tumor of adults that often presents with seizures and calcifies. It is defined by an IDH mutation with 1p/19q codeletion and shows "fried egg" cells and "chicken-wire" capillaries, with no dural attachment.
- E. Vestibular schwannoma: a Schwann cell tumor of the vestibular division of cranial nerve VIII that grows from the internal auditory canal into the cerebellopontine angle (CPA), causing unilateral sensorineural hearing loss, tinnitus and imbalance. Histology shows Antoni A and B areas, Verocay bodies and S-100 staining; bilateral tumors mean NF2-related schwannomatosis. See the vestibular schwannoma review.
Meningioma at a glance
| Feature | High-yield fact |
|---|---|
| Cell of origin | Arachnoid cap (meningothelial) cells |
| Frequency | Most common primary brain and CNS tumor: 42.6% of all primary tumors and 57.4% of non-malignant ones (CBTRUS 2018-2022); the most common histology in adults aged 40 and older |
| Patient | Median age 67; more common in women; grade 1 tumors are more common in women, grades 2 and 3 in men |
| Risk factors | Ionizing radiation (especially in childhood), NF2-related schwannomatosis, repeated long-term medroxyprogesterone acetate (FDA label warning since December 2025) |
| Location | Anywhere there is dura: convexities near the venous sinuses, parasagittal and falx, skull base, posterior fossa and CPA, spine; rarely intraventricular |
| Imaging | Extra-axial, dural-based, homogeneous enhancement, dural tail (suggestive, not pathognomonic), calcification, hyperostosis of adjacent bone |
| Histology | Whorls of meningothelial cells, psammoma bodies (laminated calcifications), vimentin-positive; may express progesterone and estrogen receptors |
| Genetics | Loss of NF2 (chromosome 22q12, merlin); chromosome 22 deletions in more than half of meningiomas |
| Grade | CNS WHO grade 1, 2 or 3; most are grade 1 |
| Treatment | Observe small asymptomatic tumors; resect symptomatic or growing ones; radiosurgery or radiotherapy for residual, inaccessible, recurrent or higher-grade tumors |
Location decides the symptoms
| Site | Typical findings |
|---|---|
| Cerebral convexity | Focal seizures, cognitive deficits, later raised intracranial pressure |
| Parasagittal or falx | Spastic weakness or numbness starting in the contralateral leg, which can mimic anterior cerebral artery syndrome |
| Olfactory groove | Anosmia; sometimes papilledema and visual loss |
| Sphenoid wing | Medial: oculomotor palsies and facial numbness (cavernous sinus); middle: visual loss and exophthalmos; lateral: seizures and headache |
| Tuberculum sellae | Visual loss; chiasmal compression gives a bitemporal hemianopia, the same field cut as a pituitary adenoma |
| Clivus, petrous apex or cerebellopontine angle | Gait disturbance, limb ataxia and deficits of cranial nerves V, VII and VIII; a CPA meningioma can mimic a vestibular schwannoma |
| Foramen magnum | Ipsilateral suboccipital pain, weakness that starts in the ipsilateral arm and spreads to the leg and then the opposite side, cranial nerve deficits |
Midline tumors in older adults can cause dementia with few focal signs.
Imaging: proving it is extra-axial
- MRI with gadolinium is the test of choice; CT is better for calcification and bone changes such as hyperostosis.
- Extra-axial clues: a broad dural base, brain that is displaced rather than infiltrated, homogeneous enhancement and a dural tail of thickened, enhancing dura. The dural tail is helpful but not pathognomonic.
- A small, calcified, dural-based mass found by chance in an asymptomatic older adult is the classic incidental meningioma.
Pathology, genetics and risk factors
- Whorls and psammoma bodies: psammoma bodies are calcified whorls. They also occur in papillary thyroid carcinoma, serous ovarian carcinoma and mesothelioma, so they support the diagnosis without proving it.
- NF2-related schwannomatosis (the 2022 name for neurofibromatosis type 2) is autosomal dominant and caused by loss of the NF2 tumor suppressor, merlin, on chromosome 22q12. It brings bilateral vestibular schwannomas, meningiomas and ependymomas, and two or more meningiomas count as a major diagnostic criterion. Compare ependymoma.
- Radiation: cranial irradiation can cause meningiomas decades later (latency about 10-40 years), especially after childhood exposure; radiation-induced meningiomas are the most common radiation-induced brain tumors and tend to be multiple and aggressive.
- Hormones: progesterone and estrogen receptors may explain growth during pregnancy. Since December 2025 the Depo-Provera label (medroxyprogesterone acetate) warns that meningiomas have been reported after repeated, mainly long-term use; the drug is stopped if a meningioma is diagnosed.
- Other WHO CNS5 drivers: AKT1, TRAF7, SMO and PIK3CA, plus KLF4, SMARCE1 or BAP1 in particular subtypes.
WHO CNS5 grading (2021) at a high level
- Meningioma is one tumor type with many histologic subtypes, graded 1, 2 or 3; CNS5 uses Arabic numerals and grades within each tumor type.
- Grade 1 is the most common (about 80% of meningiomas), grows slowly and is usually curable when it can be completely removed.
- Grade 2 (atypical) is more likely to recur after removal and can invade nearby tissue, including bone. Under current WHO criteria, brain invasion by itself makes a meningioma at least grade 2.
- Grade 3 (anaplastic or malignant) grows fast and is likely to invade the brain. Besides anaplastic histology or a very high mitotic count, WHO CNS5 uses TERT promoter mutation or homozygous CDKN2A/B deletion to assign grade 3.
- Grades 2 and 3 are more common in men; NCI reports a 5-year relative survival of about 63.5% for high-grade meningioma.
Management
- Small, asymptomatic, incidental tumor (especially in older adults): active surveillance with serial MRI, because most grow minimally.
- Symptomatic or growing tumor: surgical resection when it is safe. Surgery may be deferred when the tumor is very large, encases vessels or sits beside critical structures such as the brainstem.
- Stereotactic radiosurgery: for surgically inaccessible tumors, residual tumor after surgery, older patients and tumors smaller than about 3 cm.
- Fractionated radiotherapy: for unresectable or recurrent tumors. Grades 2 and 3: surgery plus radiation.
- Supportive care: dexamethasone for symptomatic vasogenic edema or raised intracranial pressure, and antiseizure medication for seizures.
Meningioma vs schwannoma vs glioblastoma vs metastasis
| Feature | Meningioma | Vestibular schwannoma | Glioblastoma | Metastasis |
|---|---|---|---|---|
| Origin | Arachnoid cap cells | Schwann cells of CN VIII (vestibular division) | Astrocytic glioma, IDH-wildtype, grade 4 | Systemic cancer: lung, breast, melanoma, kidney, colon |
| Position | Extra-axial, dural-based | Extra-axial, internal auditory canal into the CPA | Intra-axial, infiltrating white matter | Intra-axial, gray-white junction |
| Number | Usually single; multiple in NF2 | Single; bilateral in NF2 | Usually single; may cross the corpus callosum | Often multiple |
| MRI | Homogeneous enhancement, dural tail, calcification, hyperostosis | Enhancing canal and CPA mass | Ring enhancement around necrosis, marked edema | Ring or solid enhancement, edema out of proportion |
| Histology | Whorls, psammoma bodies | Antoni A and B, Verocay bodies, S-100 | Pseudopalisading necrosis, microvascular proliferation, GFAP | Resembles the primary tumor |
| Story | Slow headache, seizures, focal deficit | Unilateral sensorineural hearing loss, tinnitus | Rapidly progressive deficits, raised intracranial pressure | Known cancer |
How USMLE tests it
- Most common primary brain tumor = meningioma; most common primary malignant brain tumor = glioblastoma; most common brain tumor in adults overall = metastasis.
- Extra-axial + dural tail + whorls or psammoma bodies = meningioma.
- CPA mass with unilateral hearing loss: vestibular schwannoma is the usual answer and meningioma the main alternative.
- Slowly progressive leg weakness from a parasagittal mass mimics an ACA stroke.
- Bilateral vestibular schwannomas plus meningiomas = NF2-related schwannomatosis (chromosome 22).
- Incidental, small, asymptomatic meningioma = observation with serial MRI, not surgery.
Key takeaways
- Meningioma = arachnoid cap cells, extra-axial and dural-based; the most common primary brain and CNS tumor (42.6%, CBTRUS 2018-2022).
- Older woman, slowly progressive headache, seizures or a focal deficit set by location; MRI shows homogeneous enhancement and a dural tail, CT shows calcification and hyperostosis.
- Histology: whorls and psammoma bodies; progesterone receptors may be present.
- Risk: female sex, ionizing radiation, NF2-related schwannomatosis (22q12, merlin); long-term medroxyprogesterone now carries a label warning.
- WHO CNS5 grades 1-3; most are grade 1; brain invasion means at least grade 2, and TERT promoter mutation or homozygous CDKN2A/B deletion means grade 3.
- Watch small asymptomatic tumors, resect symptomatic or growing ones, and use radiosurgery or radiotherapy for residual, inaccessible or high-grade disease.
Sources
- Meningiomas — Merck Manual Professional Edition (2026)
- Overview of Central Nervous System Tumors — Merck Manual Professional Edition (2026)
- Meningioma — StatPearls, NCBI Bookshelf (2026)
- CBTRUS Statistical Report: Primary Brain and Other CNS Tumors Diagnosed in the United States in 2018-2022 — Neuro-Oncology (2025)
- CBTRUS Fact Sheet — Central Brain Tumor Registry of the United States (2025)
- Meningioma: Diagnosis and Treatment — National Cancer Institute, NCI-CONNECT
- Central Nervous System Tumors Treatment (PDQ), Health Professional Version — National Cancer Institute (2025)
- The 2021 WHO Classification of Tumors of the Central Nervous System: A Summary — Neuro-Oncology (2021)
- Neurofibromatosis — Merck Manual Professional Edition (2026)
- Vestibular Schwannoma — Merck Manual Professional Edition (2026)
- Orbital Meningiomas — EyeWiki, American Academy of Ophthalmology
- Depo-Provera CI (medroxyprogesterone acetate) Prescribing Information — DailyMed (2025)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
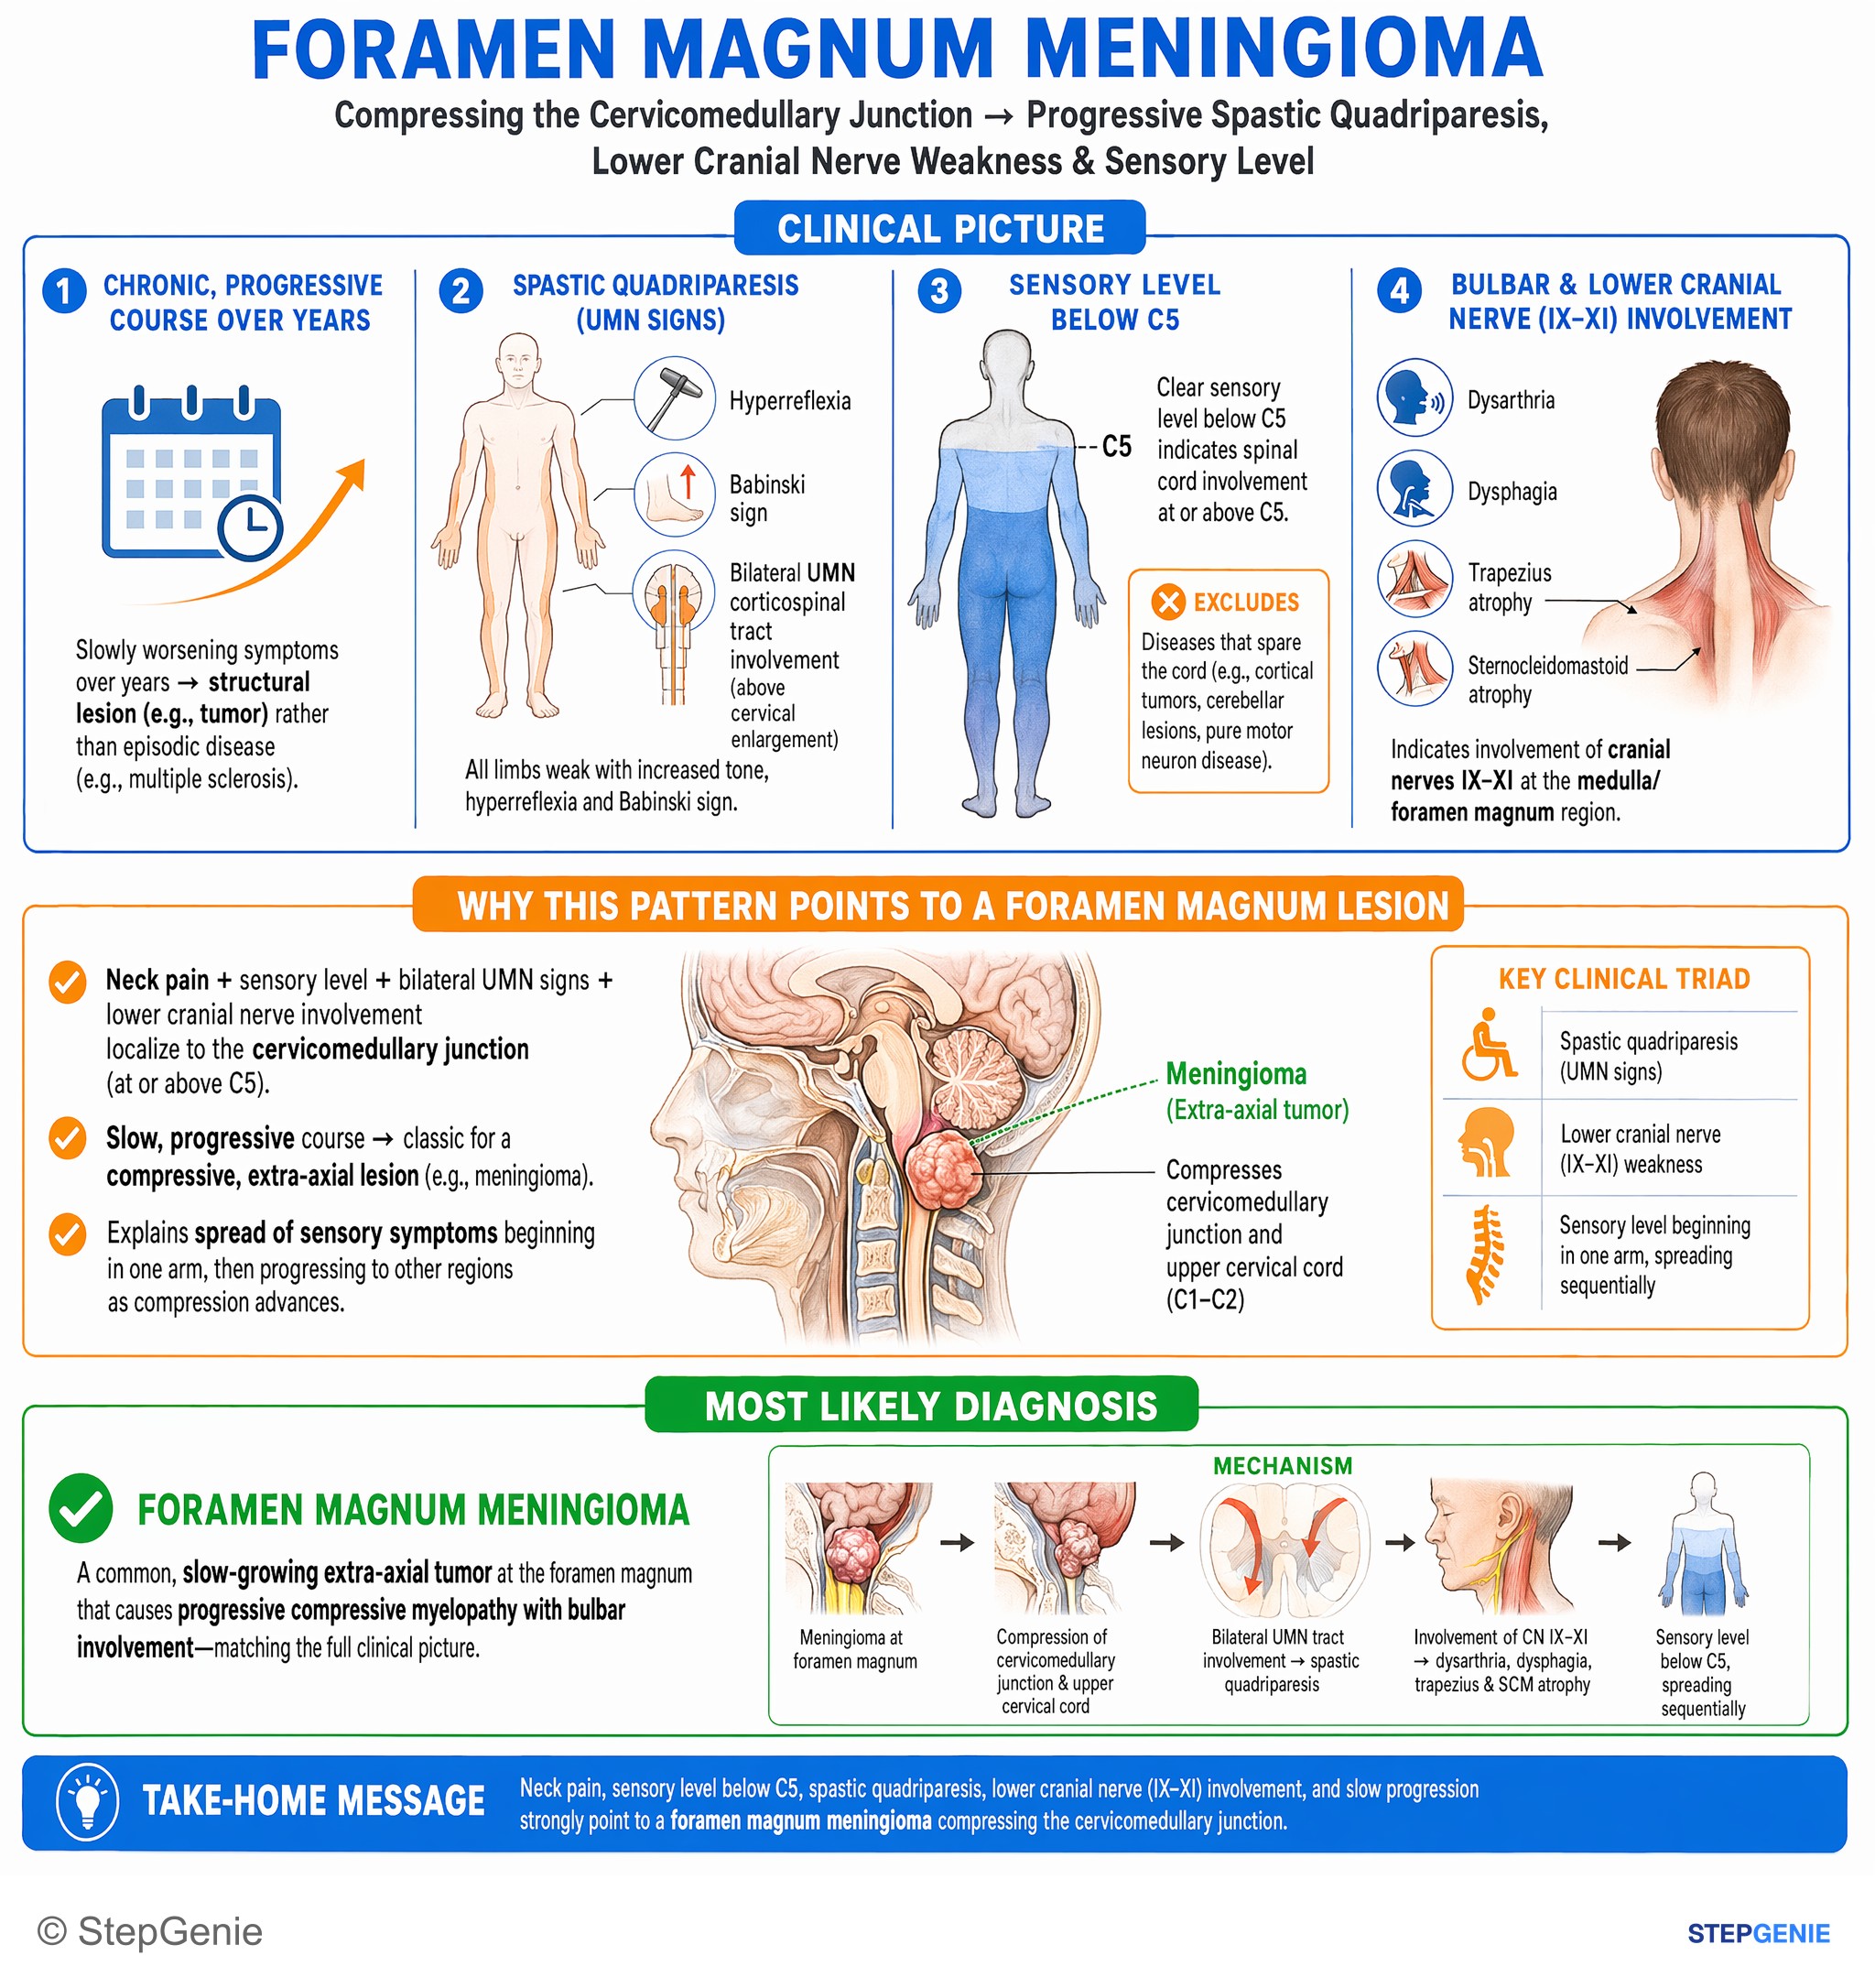
Foramen magnum meningioma compresses cervicomedullary junction causing progressive spastic quadriparesis, lower cranial nerve weakness…
USMLE Step 1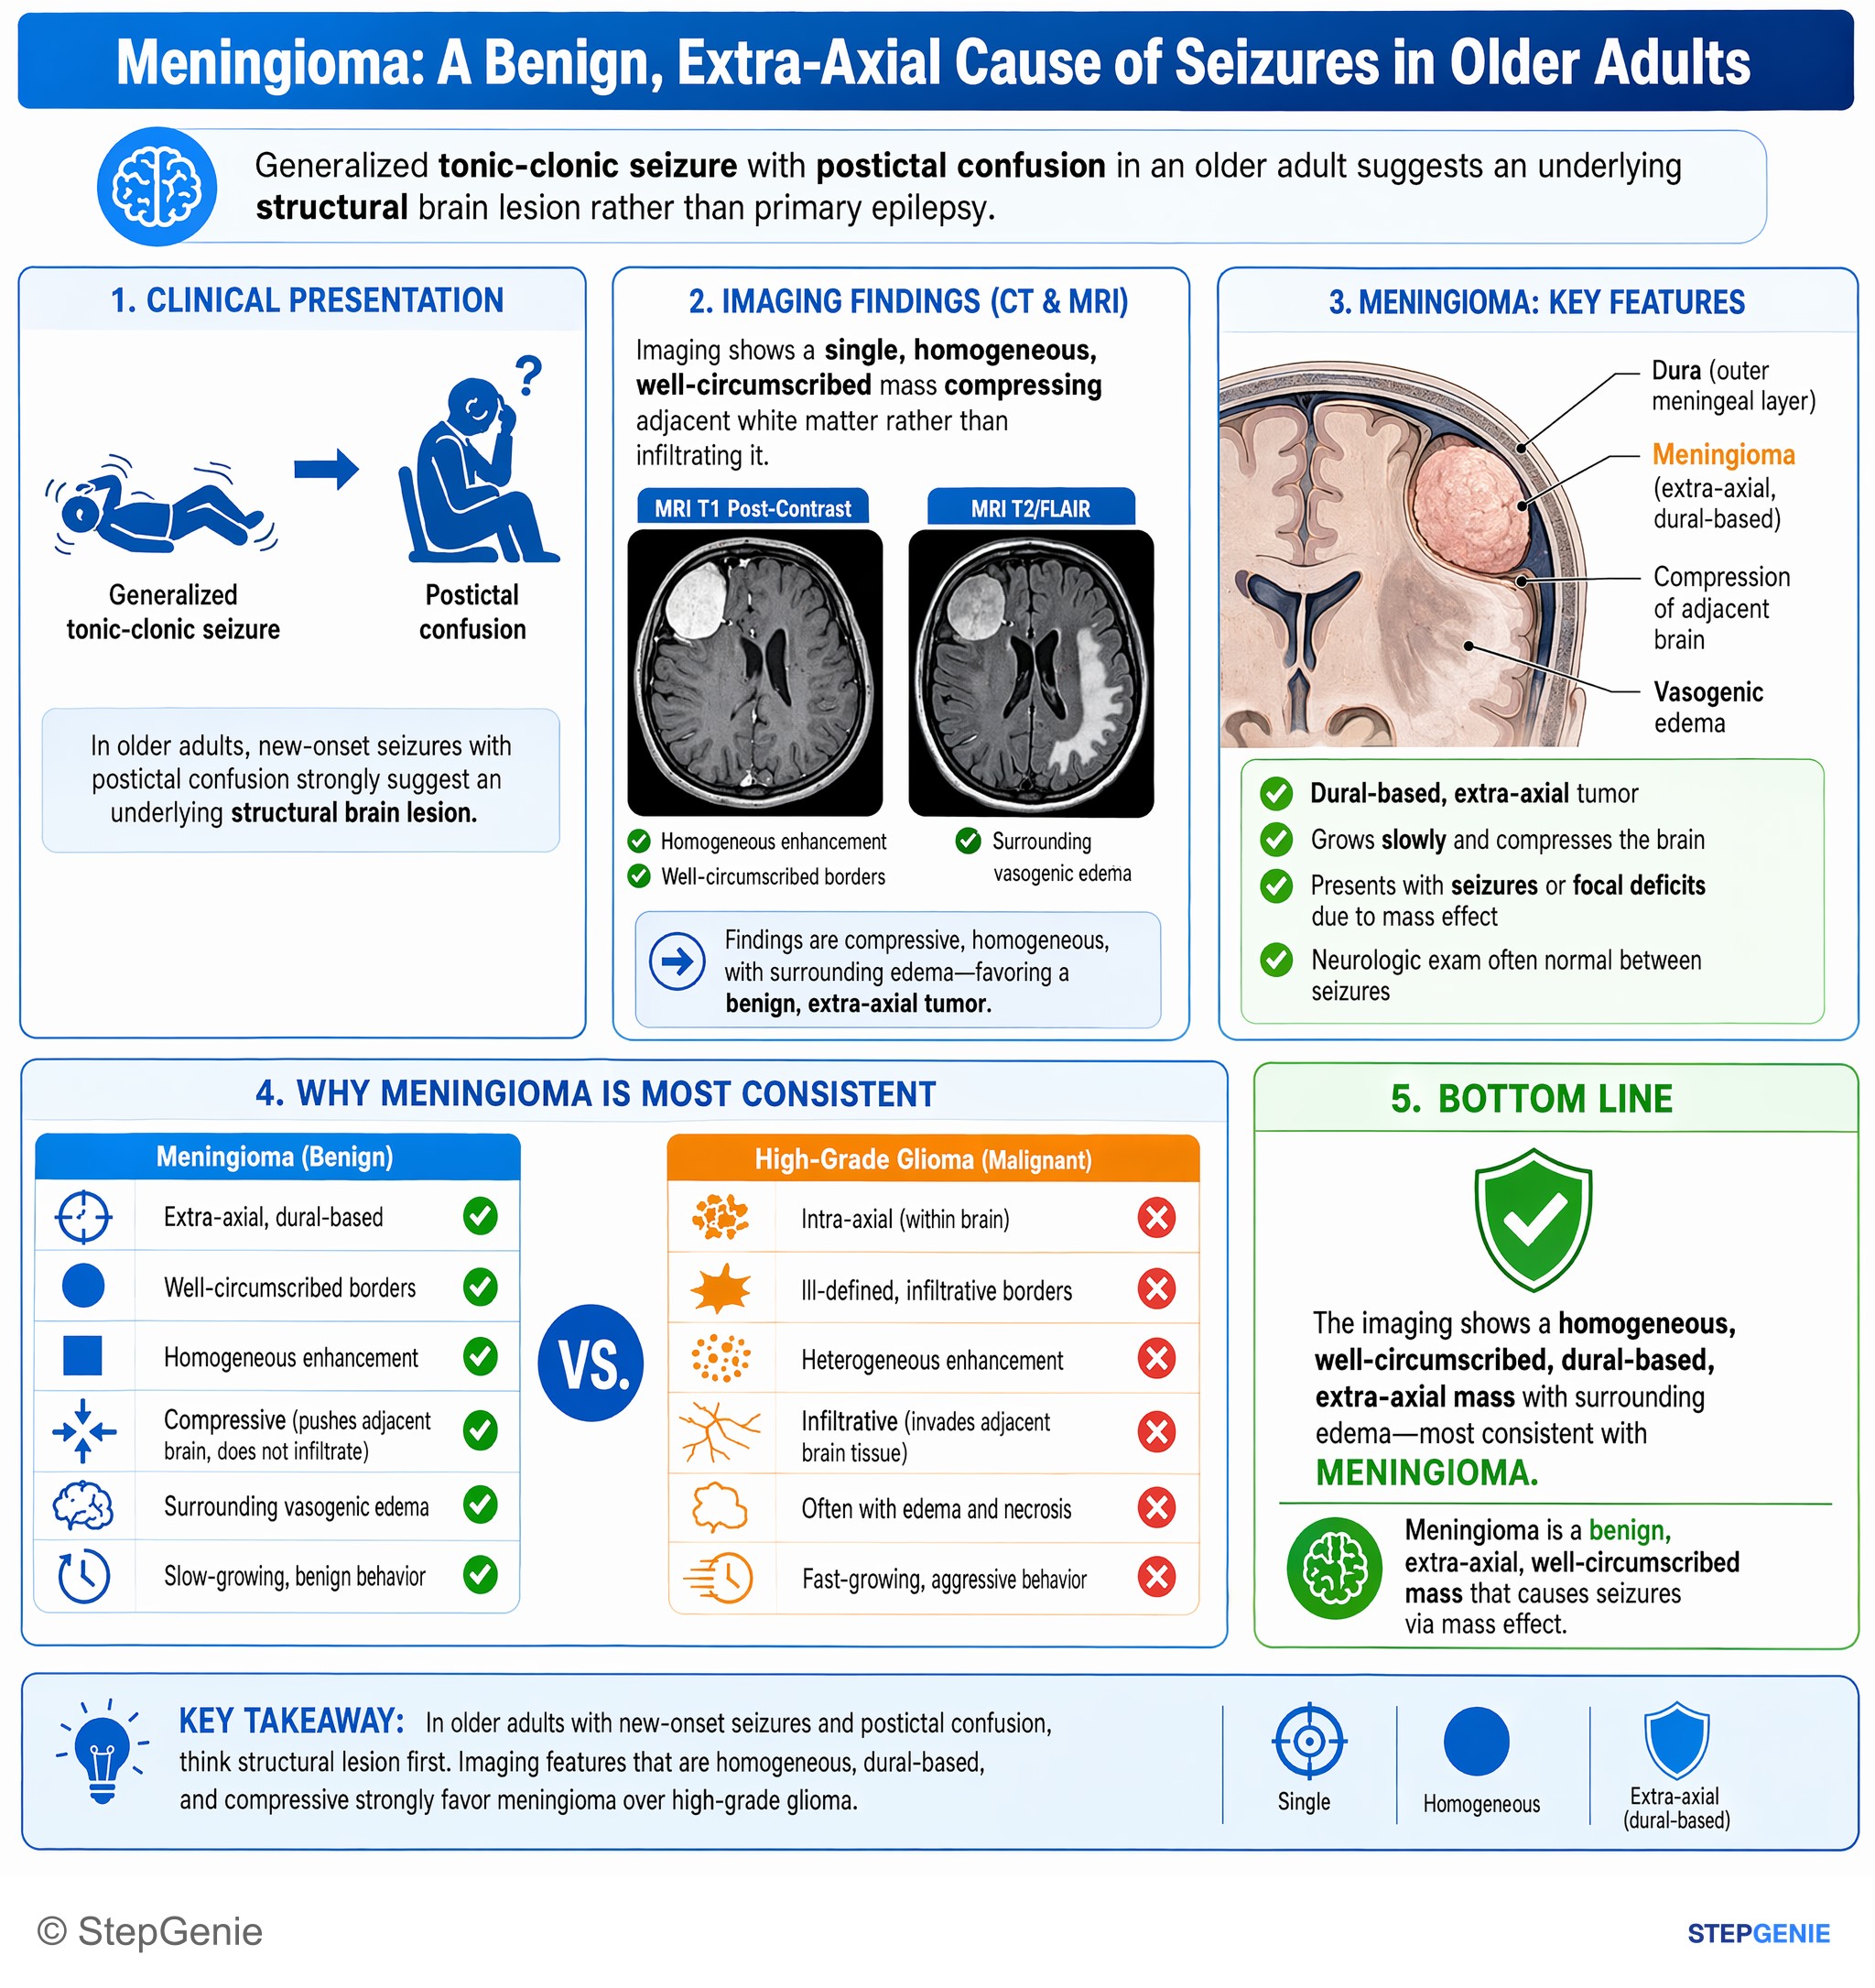
Meningioma is a benign, extra-axial, well-circumscribed mass causing seizures via mass effect; homogeneous, dural-based lesion with…
USMLE Step 2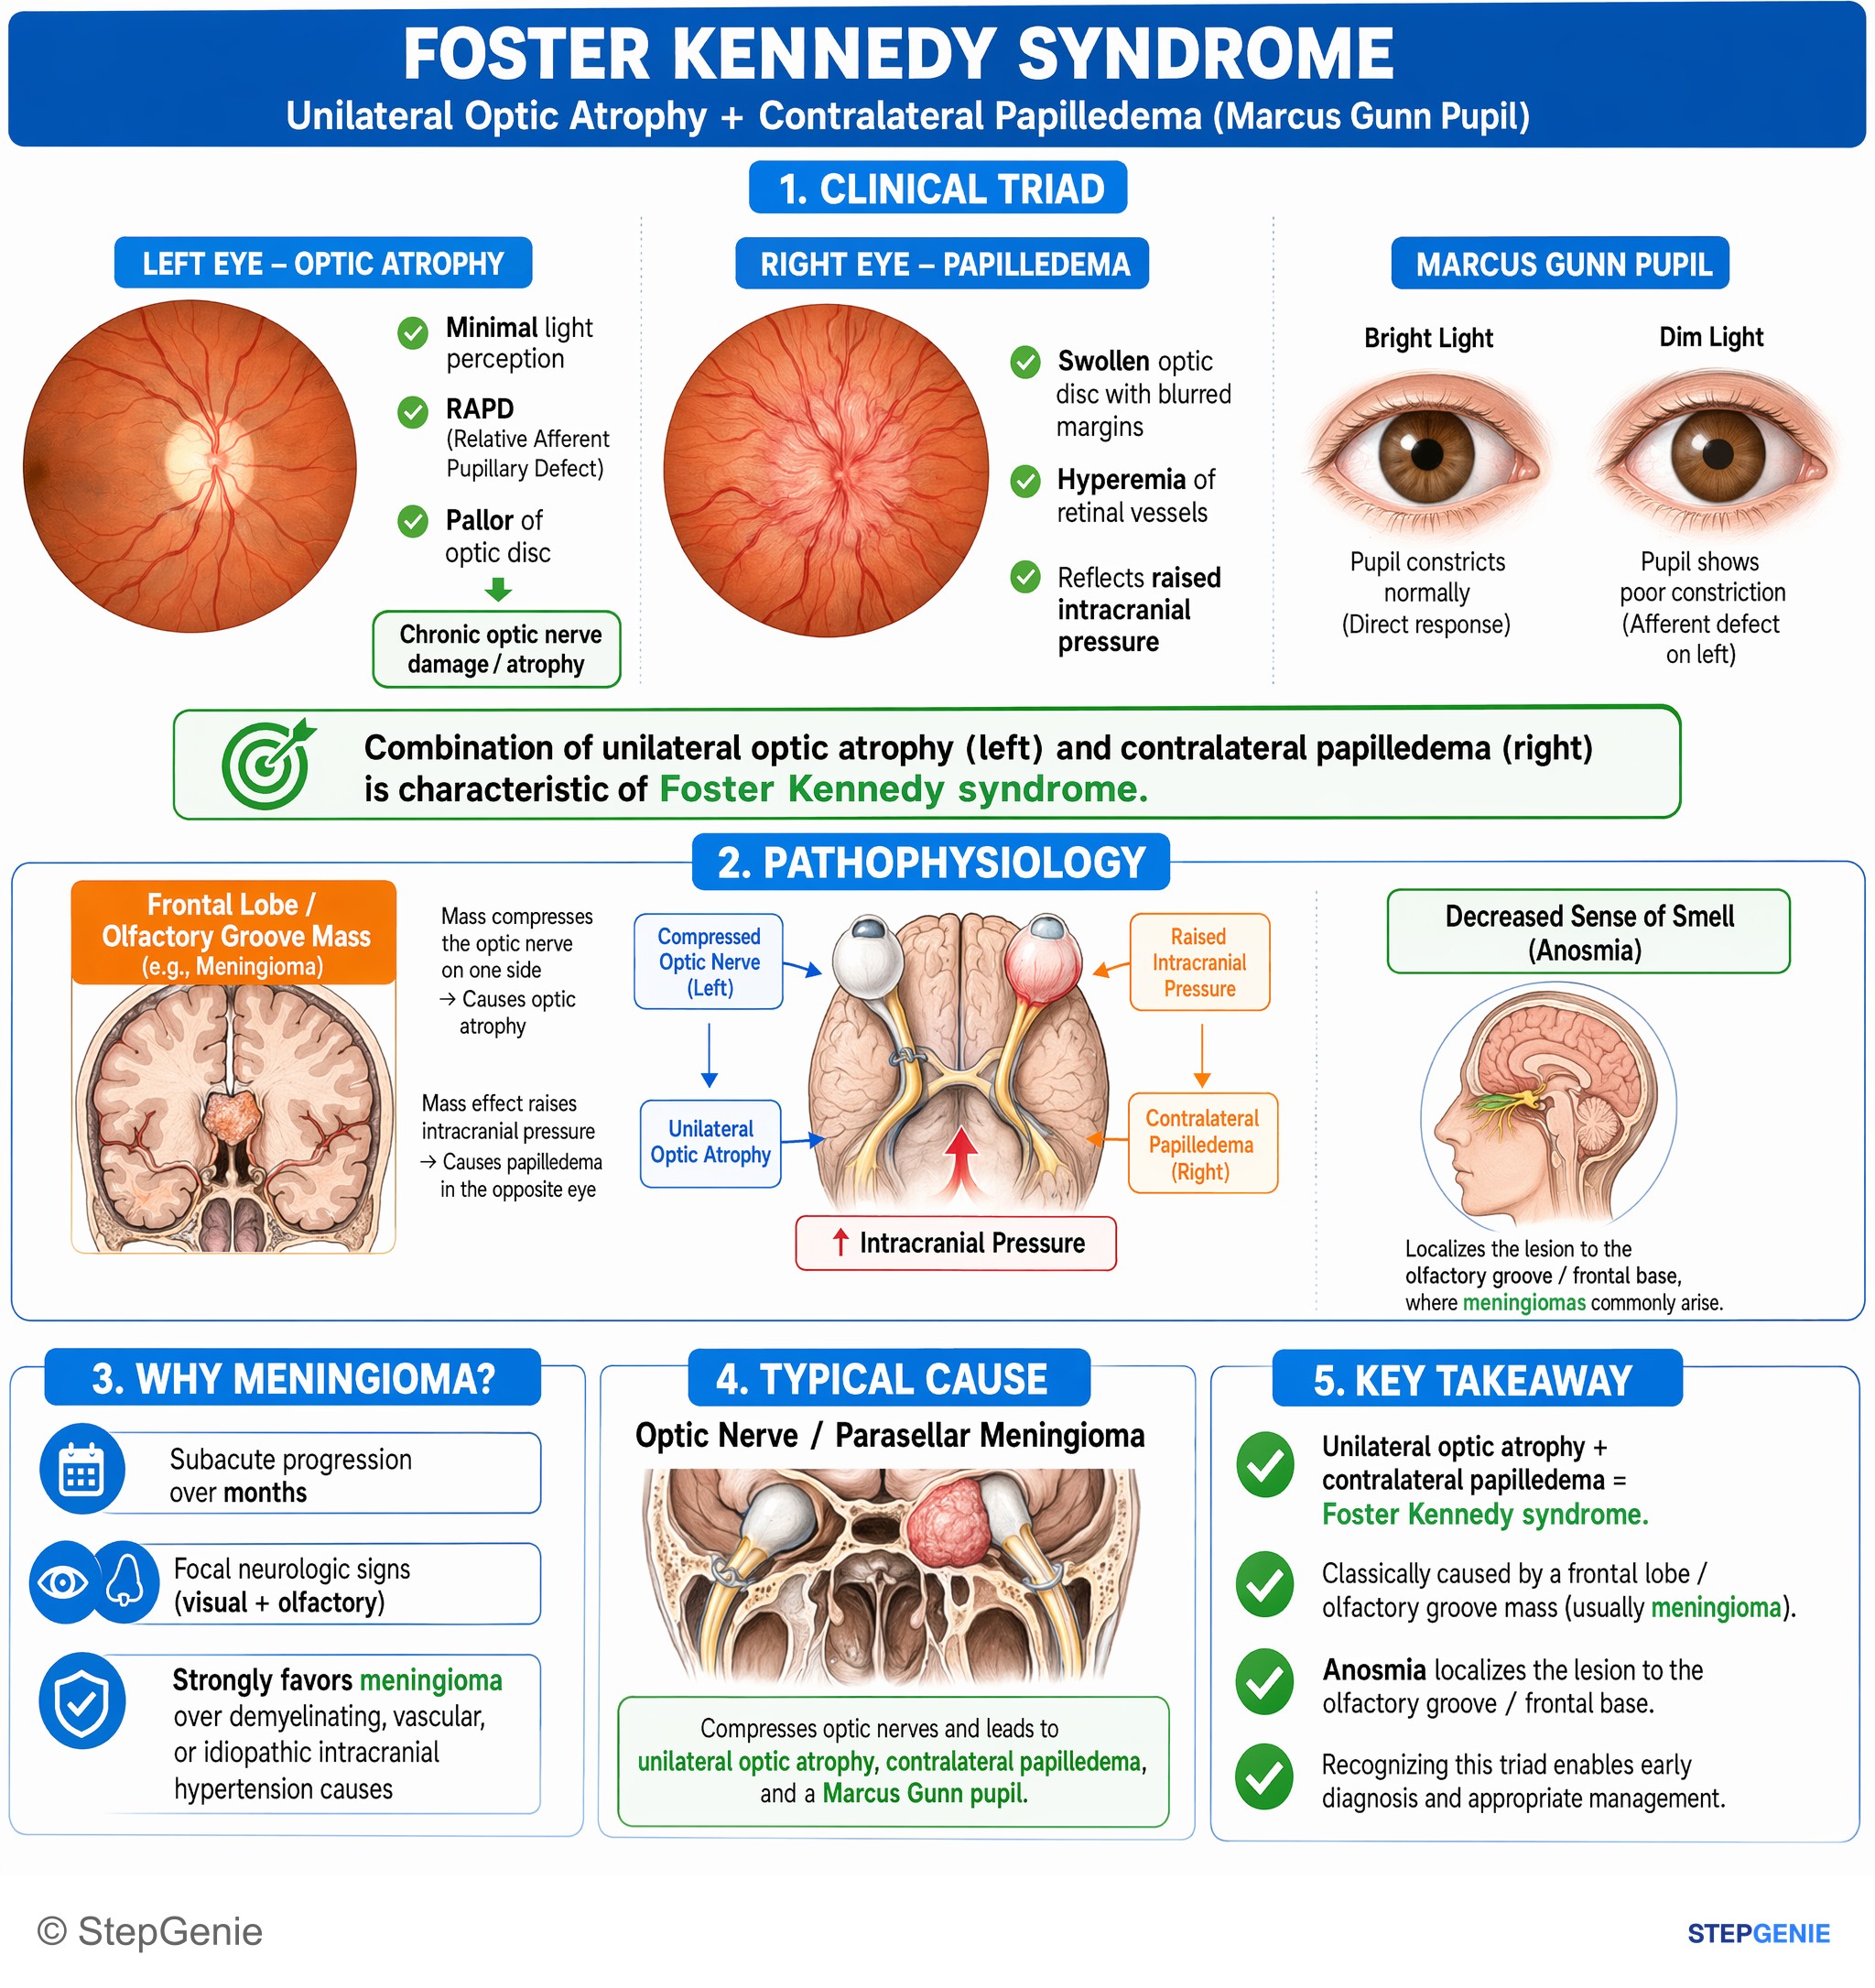
Optic nerve/parasellar meningioma compresses optic nerves → unilateral optic atrophy, contralateral papilledema, and Marcus Gunn pupil…
USMLE Step 2Frequently Asked Questions
What is a meningioma?
A meningioma is a tumor of the meninges that arises from arachnoid cap cells and attaches to the dura. It is extra-axial, meaning it usually compresses the brain from outside rather than invading it. Most meningiomas are slow-growing CNS WHO grade 1 tumors, but grade 2 (atypical) and grade 3 (anaplastic) tumors recur more often and can invade bone or brain. Symptoms depend on location and include headache, focal seizures and focal neurologic deficits.
Is meningioma the most common primary brain tumor?
Yes. In the CBTRUS report covering US diagnoses from 2018 to 2022, meningioma made up 42.6 percent of all primary brain and other central nervous system tumors and 57.4 percent of non-malignant ones, and it was the most common tumor type in adults aged 40 and older. Glioblastoma is the most common primary malignant brain tumor. Brain metastases, however, are about 10 times more common than primary brain tumors.
What does a dural tail sign mean on MRI?
A dural tail is a thickened, enhancing strip of dura extending away from the edge of a dural-based mass on contrast MRI. It is a classic sign of meningioma and, together with a broad dural base, homogeneous enhancement and displacement rather than infiltration of the brain, helps show that the mass is extra-axial. It is helpful but not pathognomonic, because other dural-based lesions can also produce it.
What are psammoma bodies and which tumors have them?
Psammoma bodies are round, concentrically laminated calcifications. In meningioma they form from calcified whorls of meningothelial cells and sit alongside the characteristic whorled pattern. They are also classic in papillary thyroid carcinoma, serous ovarian carcinoma and mesothelioma, so in a dural-based mass they support a diagnosis of meningioma but do not prove it on their own.
What genetic syndrome causes multiple meningiomas?
NF2-related schwannomatosis, the 2022 name for neurofibromatosis type 2, is the classic cause. It is autosomal dominant and results from loss of the NF2 tumor suppressor gene on chromosome 22q12, which encodes merlin. Patients develop bilateral vestibular schwannomas, meningiomas and ependymomas, and two or more meningiomas count as a major diagnostic criterion. Prior cranial radiation is the other major risk factor for meningioma.
How is a meningioma treated?
Small, asymptomatic meningiomas, especially in older adults, are usually watched with serial MRI because most grow little. Symptomatic or growing tumors are removed surgically when this is safe, and complete resection usually cures grade 1 tumors. Stereotactic radiosurgery treats small, inaccessible or residual tumors, fractionated radiotherapy treats unresectable or recurrent ones, and grade 2 or 3 tumors usually receive surgery plus radiation. Dexamethasone treats symptomatic edema and antiseizure drugs treat seizures.