You’ve probably seen it: an older adult with a new, progressive neuro deficit and a ring-enhancing brain lesion. The “easy” move is to click glioblastoma and move on. But USMLE questions are built so that every distractor teaches something—especially in CNS tumors, where imaging patterns and patient context are everything.
The Vignette (Classic Q-Bank Style)
A 62-year-old man presents with 2 months of worsening headaches and new personality changes. His wife notes increasing forgetfulness and irritability. Neuro exam shows mild right-sided weakness. MRI of the brain with contrast reveals a heterogeneously ring-enhancing mass in the left frontal lobe with central necrosis, surrounding vasogenic edema, and extension across the corpus callosum.
Most likely diagnosis?
A. Oligodendroglioma
B. Primary CNS lymphoma
C. Glioblastoma
D. Metastatic carcinoma
E. Toxoplasma gondii encephalitis
Correct answer: C. Glioblastoma
Why the Correct Answer Is Glioblastoma
This is the prototypical presentation of glioblastoma (WHO grade 4 astrocytoma):
The high-yield “anchors”
- Age: typically older adults (often >50)
- Location: cerebral hemispheres (frontal/temporal common)
- Imaging:
- Ring enhancement due to necrosis and breakdown of the BBB
- Heterogeneous appearance (“multiforme”)
- Crosses the corpus callosum → the famous “butterfly glioma”
- Significant vasogenic edema (mass effect symptoms: headache, nausea, focal deficits)
- Clinical: progressive headaches, cognitive/personality changes, focal deficits, seizures
Pathology & molecular facts worth memorizing (USMLE gold)
- Pseudopalisading necrosis (tumor cells lining up around necrotic areas)
- Microvascular proliferation (glomeruloid vessels)
- Can arise:
- Primary (de novo; older patients; often EGFR amplification, PTEN loss)
- Secondary (from lower-grade astrocytoma; younger patients; often IDH mutation)
- Prognosis: poor even with treatment (resection + radiation + temozolomide)
The “Why Not” Section: Each Distractor Matters
A. Oligodendroglioma
Why it’s tempting: It’s an adult glioma and often presents with seizures.
Why it’s wrong here:
- Calcifications and a more cortical-based lesion are common.
- Classically frontal lobe, but it’s usually more homogeneous and less necrotic than glioblastoma.
- Not famous for crossing the corpus callosum.
High-yield identifiers
- “Fried egg” cells (perinuclear halos) and chicken-wire capillaries
- 1p/19q codeletion (strong association; better prognosis and chemo sensitivity)
B. Primary CNS lymphoma
Why it’s tempting: Can enhance with contrast and occurs in older adults.
Why it’s wrong here:
- In immunocompetent patients, lesions are often solidly enhancing, not classically necrotic ring-enhancing.
- In immunocompromised (e.g., AIDS, transplant), it can ring-enhance—but a key clue would be immune status and often EBV association.
High-yield identifiers
- Strong association with EBV in immunocompromised patients
- Periventricular location is common
- Steroids can dramatically shrink lesions (can obscure biopsy—classic test pearl)
Quick compare
- CNS lymphoma: more homogeneous enhancement, often deep/periventricular
- Glioblastoma: heterogeneous ring enhancement + necrosis + “butterfly” spread
C. Glioblastoma (Correct)
To lock it in, remember the trio:
Older adult + ring enhancement with necrosis + crosses corpus callosum.
D. Metastatic carcinoma
Why it’s tempting: Metastases often produce ring-enhancing lesions with edema.
Why it’s wrong here:
- Metastases are often multiple lesions at the gray-white junction (watershed of blood flow).
- They typically do not cross the corpus callosum as a single infiltrative mass.
- You’d expect a cancer history or systemic symptoms (though not always provided).
High-yield identifiers
- Common primaries: lung, breast, melanoma, kidney, colon
- Imaging: multiple ring-enhancing masses + lots of edema
- Location: gray-white matter junction
E. Toxoplasma gondii encephalitis
Why it’s tempting: Ring-enhancing brain lesions is the buzzphrase.
Why it’s wrong here:
- Toxo is a classic opportunistic infection in advanced HIV/AIDS (typically CD4 < 100), or other severe immunosuppression.
- Usually multiple ring-enhancing lesions, often in basal ganglia.
- This vignette points hard toward an infiltrative primary brain tumor (corpus callosum involvement).
High-yield identifiers
- HIV + multiple ring-enhancing lesions + seizures/focal deficits
- Serology: often Toxoplasma IgG positive (reactivation)
- Treatment: pyrimethamine + sulfadiazine + leucovorin (folinic acid rescue)
One Table to Rule Them All (Ring-Enhancing Lesions)
| Condition | Typical Patient | Number/Location | Enhancement Pattern | Key Clues |
|---|---|---|---|---|
| Glioblastoma | Older adult | Often single; hemispheres; can cross corpus callosum | Heterogeneous ring + necrosis | “Butterfly” glioma; pseudopalisading necrosis |
| Metastases | Known malignancy (or occult) | Multiple, gray-white junction | Ring-enhancing with edema | Lung/breast/melanoma/kidney/colon |
| Toxoplasmosis | AIDS (CD4 < 100) | Multiple, basal ganglia | Ring-enhancing | Opportunistic infection; treat empirically in HIV |
| Primary CNS lymphoma | Immunocompromised (or older immunocompetent) | Deep/periventricular | Often homogeneous (ring if immunocompromised) | EBV association; steroid response |
| Oligodendroglioma | Adult | Frontal; cortical | Often more calcified, less necrotic | 1p/19q codeletion; “fried egg” |
USMLE-Style Takeaways (What to Click Under Pressure)
- Crosses corpus callosum = glioblastoma until proven otherwise.
- Multiple lesions at gray-white junction = metastases.
- HIV + multiple ring-enhancing basal ganglia lesions = toxoplasmosis.
- Periventricular + homogeneous enhancement + immunosuppression/EBV = primary CNS lymphoma.
- Calcifications + “fried egg” + 1p/19q = oligodendroglioma.
Quick Self-Check (1-Minute Drill)
If a vignette says:
- “Heterogeneous ring enhancement + central necrosis” → think high-grade tumor
- “Butterfly lesion” → think glioblastoma
- “CD4 50” + ring lesions → think toxoplasma, don’t overthink
- “Deep periventricular mass” + immunosuppression → think CNS lymphoma
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
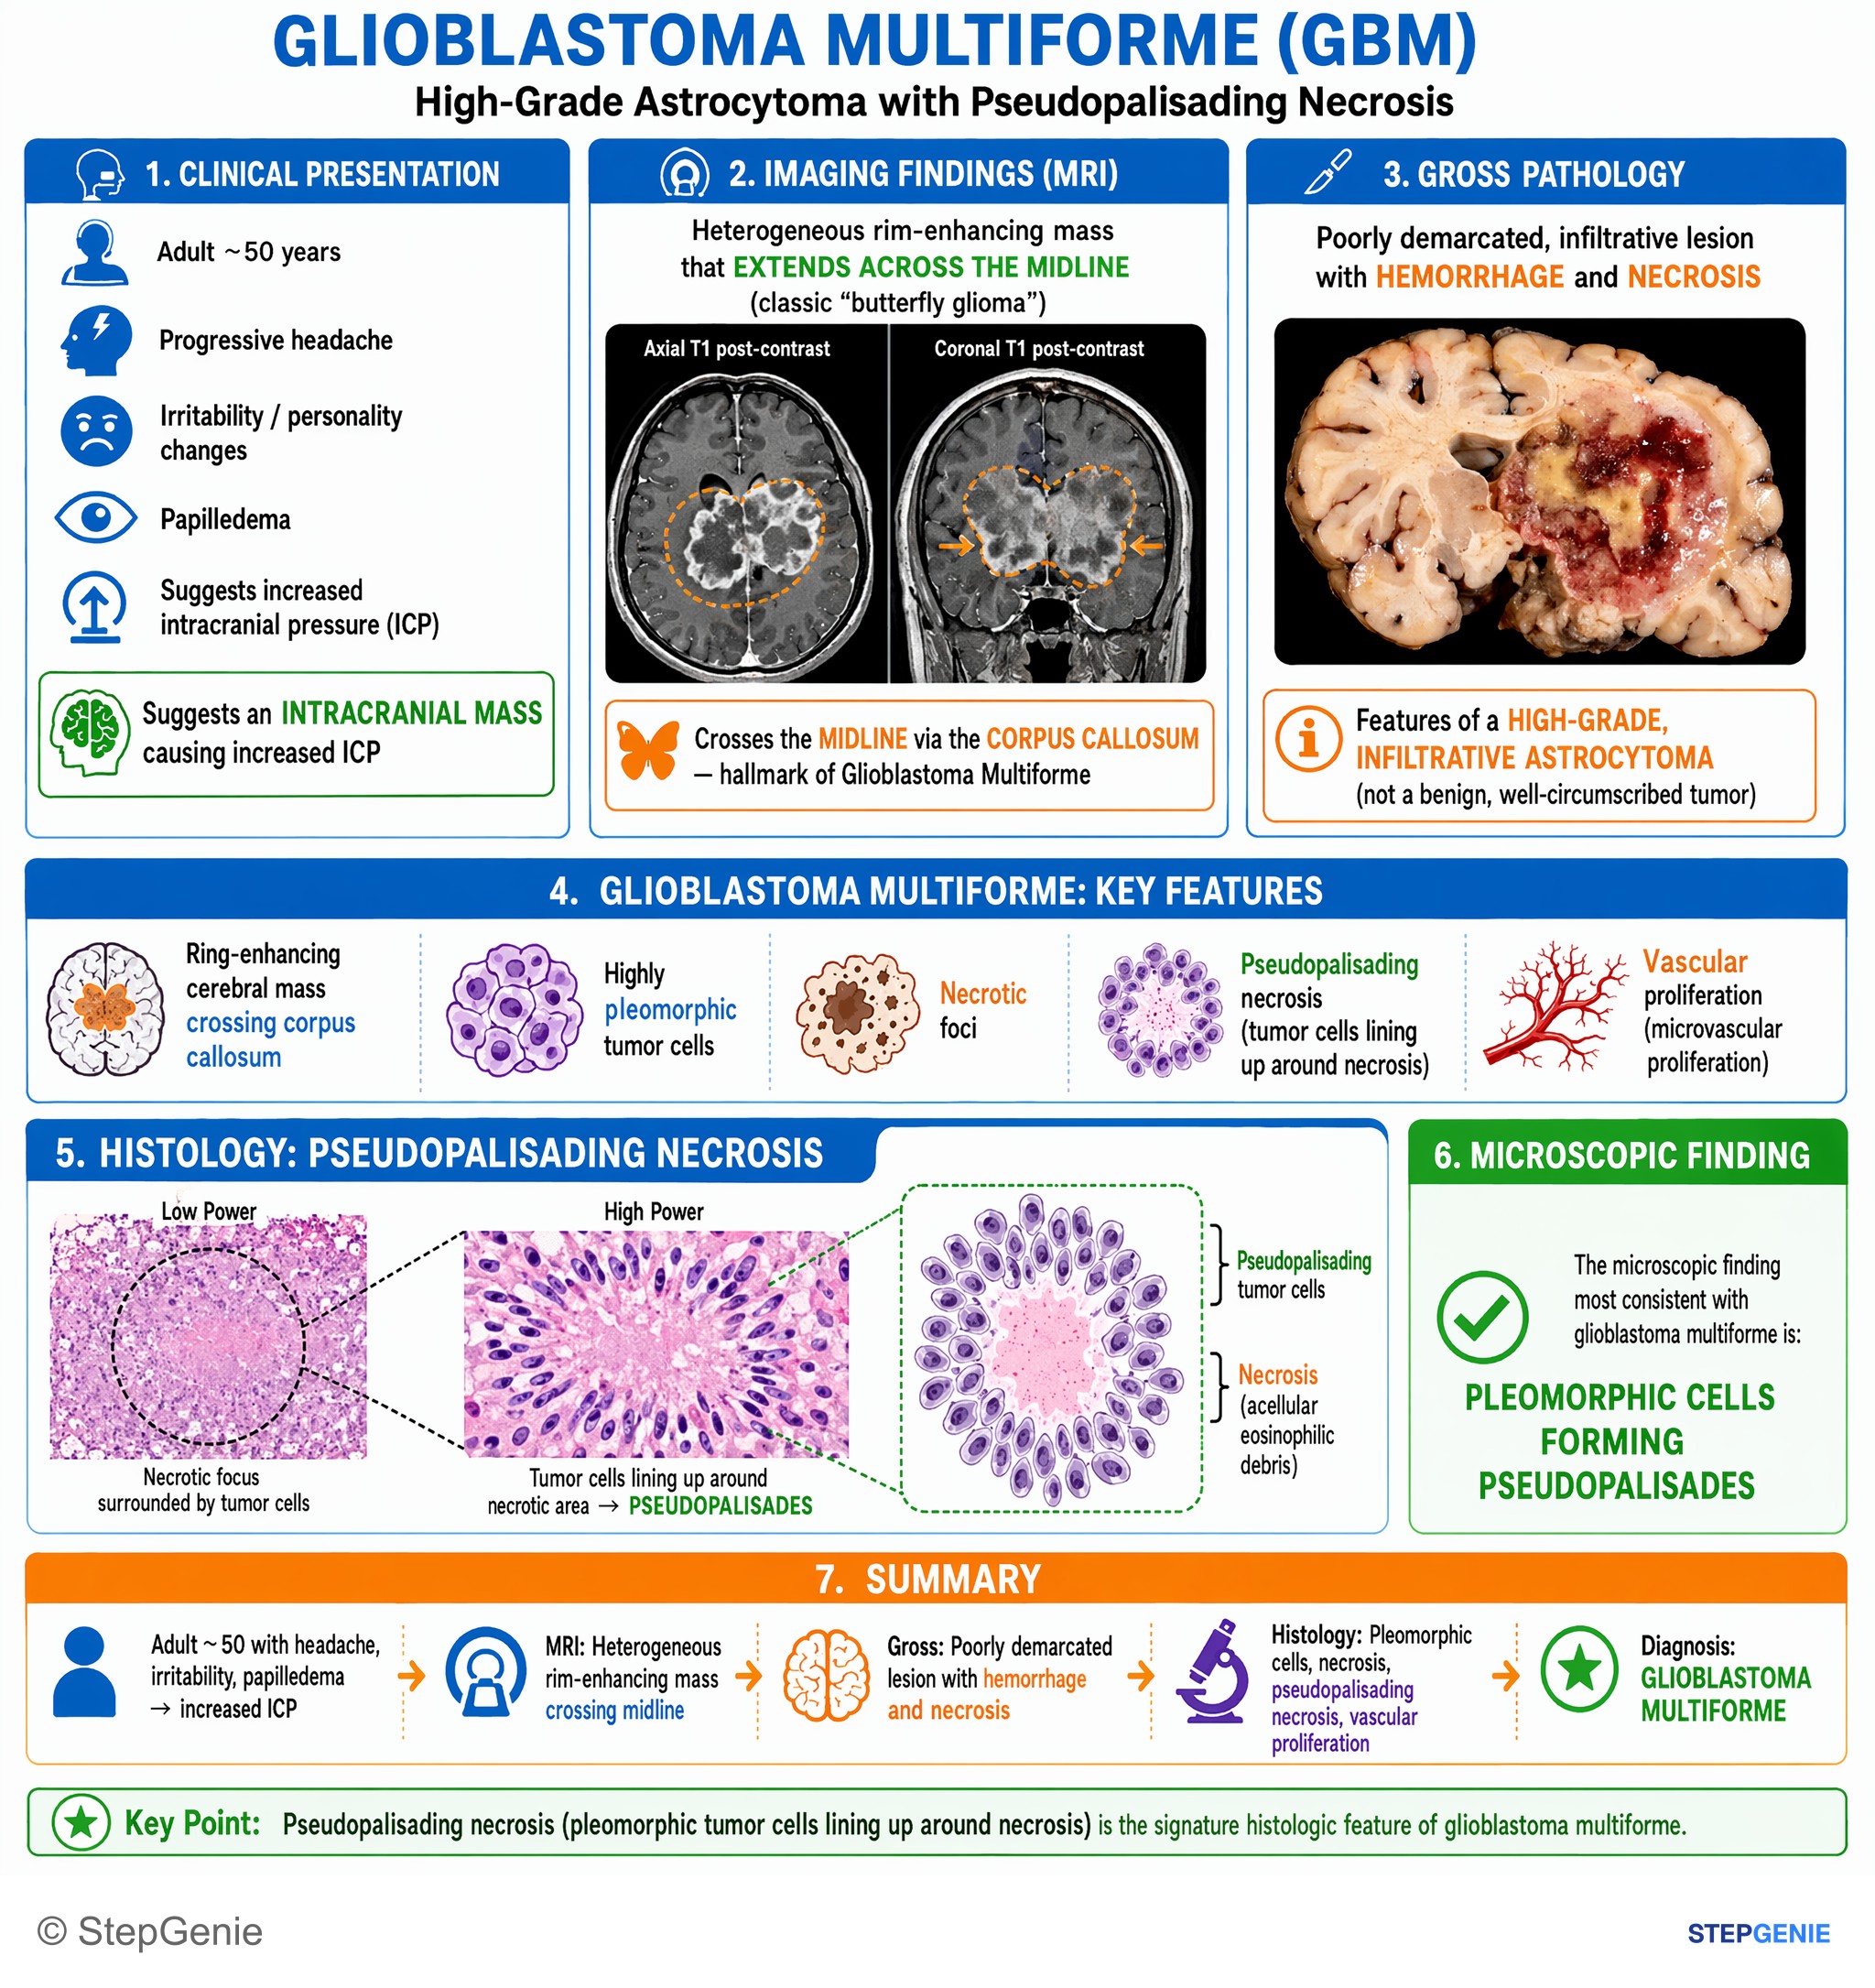
Glioblastoma multiforme presents with ring-enhancing cerebral mass crossing corpus callosum; histology shows pleomorphic tumor cells with…
USMLE Step 1Frequently Asked Questions
How do you recognize glioblastoma on a brain MRI question stem?
Glioblastoma is suggested by an older adult with a heterogeneously ring-enhancing brain mass that has central necrosis, marked vasogenic edema, and extension across the corpus callosum. This classic butterfly glioma pattern, especially in the cerebral hemispheres such as the frontal or temporal lobes, fits a WHO grade 4 astrocytoma and commonly presents with headaches, personality or cognitive changes, focal deficits, and sometimes seizures.
Why does crossing the corpus callosum point to glioblastoma?
Crossing the corpus callosum strongly points to glioblastoma because this tumor is classically infiltrative and can spread between the cerebral hemispheres, creating the famous butterfly glioma appearance. In contrast, oligodendroglioma is not famous for crossing the corpus callosum, and metastases typically do not cross it as a single infiltrative mass, making this imaging clue especially high-yield.
How do you tell glioblastoma from primary CNS lymphoma on imaging?
Glioblastoma is more likely when the lesion shows heterogeneous ring enhancement with central necrosis and corpus callosum involvement. Primary CNS lymphoma, by contrast, is often deep or periventricular and tends to enhance more homogeneously in immunocompetent patients. Lymphoma can ring-enhance in immunocompromised patients, but then immune status and the strong EBV association become important clues rather than the classic glioblastoma butterfly pattern.
How do you distinguish glioblastoma from brain metastases in a vignette?
Glioblastoma is usually a single infiltrative hemispheric mass that may cross the corpus callosum and contains necrosis with heterogeneous ring enhancement. Metastatic carcinoma more often causes multiple ring-enhancing lesions with lots of edema at the gray-white junction. A history of systemic cancer or symptoms from a primary malignancy can also support metastases, whereas the corpus callosum clue pushes more strongly toward glioblastoma.
How do you tell glioblastoma from toxoplasma encephalitis in a ring-enhancing lesion question?
Glioblastoma is favored when an older adult has a single infiltrative mass with necrosis, vasogenic edema, and corpus callosum involvement. Toxoplasma gondii encephalitis is classically seen in advanced HIV/AIDS or severe immunosuppression and usually causes multiple ring-enhancing lesions, often in the basal ganglia. The patient’s immune status and the number and location of lesions are the main clues separating these two answer choices.