Febrile seizures are one of those topics that show up everywhere: pediatrics shelves, Step 1 neuro questions, ED vignettes, and anxious-parent counseling scenarios. The good news is they’re very pattern-recognizable—and when you know the rules (age range, fever timing, simple vs complex, and what not to do), you can bank easy points.
What is a Febrile Seizure?
A febrile seizure is a seizure that occurs in a child with fever without evidence of:
- CNS infection (eg, meningitis, encephalitis)
- Acute metabolic derangement (eg, hypoglycemia, hyponatremia)
- Prior afebrile seizures (ie, not epilepsy)
The classic age range (Step-defining)
- 6 months to 5 years (most commonly 6–18 months)
If the vignette is outside this age window, your suspicion should pivot toward other causes (CNS infection, epilepsy, toxic ingestion, etc.).
Pathophysiology (Why Fever Triggers Seizures)
Febrile seizures are thought to occur because fever increases neuronal excitability in an immature brain. Key ideas:
- Immature inhibitory pathways (relative GABAergic immaturity) in young children
- Rapid rise in temperature is often more important than the absolute peak temperature
- Genetic predisposition plays a role (family history is common)
High-yield association: febrile seizures often occur early in the febrile illness—sometimes as the first sign of infection.
Types: Simple vs Complex (Memorize This Table)
| Feature | Simple Febrile Seizure | Complex Febrile Seizure |
|---|---|---|
| Duration | < 15 minutes | ≥ 15 minutes |
| Focality | Generalized | Focal features possible |
| Recurrence in 24 hr | No | Yes (≥2 in 24 hours) |
| Neuro status after | Returns to baseline quickly | May have prolonged postictal state or deficits |
| Workup | Minimal (if well-appearing) | More consideration for further eval |
| Prognosis | Excellent | Still usually good, but higher epilepsy risk |
Rule of thumb: Complex = Long, Focal, or Multiple in 24 hours.
Clinical Presentation (What the Vignette Looks Like)
Typical vignette:
- Previously healthy toddler (eg, 18 months)
- Fever from viral illness (URI, roseola, otitis media, etc.)
- Generalized tonic-clonic seizure
- Seizure lasts 1–3 minutes
- Child is sleepy after, then returns to baseline
- Normal neuro exam afterward
Common fever sources to mention/recognize
- Viral infections (most common)
- Roseola (HHV-6): high fever → febrile seizure risk → then rash appears after fever breaks
- Otitis media, influenza, URI pathogens
Diagnosis: Mainly Clinical
Febrile seizures are a clinical diagnosis after you rule out red flags for CNS infection or other causes.
What you should (and shouldn’t) do
Simple febrile seizure + well-appearing child:
- Usually no labs, no imaging, no EEG
- Focus on identifying the source of fever clinically
Complex febrile seizure or concerning features may prompt more evaluation depending on context.
When to Do a Lumbar Puncture (LP): High-Yield Decision Point
You do LP when you suspect meningitis/encephalitis, not just because there was a seizure.
Red flags suggesting CNS infection
- Nuchal rigidity, photophobia, persistent altered mental status
- Toxic appearance, inconsolability, bulging fontanelle (infants)
- Petechiae/purpura, persistent lethargy
- Seizure with signs not explained by brief postictal state
Step-friendly nuance (commonly tested)
Consider LP more strongly in:
- Infants (especially if < 12 months) where meningitis signs can be subtle
- Children not fully immunized against Hib or Strep pneumoniae
- Children pretreated with antibiotics (can partially treat meningitis and blunt classic signs)
Differential Diagnosis (Step 1/2 Must-Not-Miss)
If it’s not a straightforward simple febrile seizure, think:
- Meningitis/encephalitis (HSV encephalitis, bacterial meningitis)
- Epilepsy (prior afebrile seizures, recurrent unprovoked seizures)
- Electrolyte abnormalities (hyponatremia, hypocalcemia)
- Hypoglycemia
- Toxic ingestion (eg, isoniazid → refractory seizures unless treated with pyridoxine)
- Trauma / intracranial hemorrhage (esp with focal deficits)
Treatment (Acute + Aftercare)
Acute management (ABCs first)
- Airway, breathing, circulation
- If actively seizing and prolonged: benzodiazepine (eg, lorazepam)
Most simple febrile seizures stop spontaneously within a few minutes.
Antipyretics: what they do and don’t do
- Acetaminophen/ibuprofen can improve comfort
- But they do not reliably prevent recurrence of febrile seizures (high-yield counseling point)
Long-term therapy
- No chronic antiseizure medication for simple febrile seizures
(risks outweigh benefits)
Some complex cases may warrant neurology follow-up, but routine daily prophylaxis is generally avoided.
Prognosis and Recurrence
Recurrence risk (common counseling + testable)
- Recurrence is common (roughly 1/3 of kids have another febrile seizure)
- Risk factors for recurrence:
- Young age at first seizure (< 18 months)
- Family history of febrile seizures
- Low-grade fever at time of seizure (suggests seizure threshold is lower)
- Short duration of fever before seizure (seizure early in illness)
Risk of future epilepsy (important nuance)
- Slightly increased vs general population, but still low overall
- Higher risk with complex febrile seizures, abnormal neurodevelopment, or family history of epilepsy
Key Step line: Simple febrile seizures are benign and do not cause brain damage, intellectual disability, or death.
High-Yield USMLE Associations & “Buzz Phrases”
HY clues pointing to febrile seizure
- 6 months–5 years
- Fever early in illness (often first sign)
- Generalized seizure lasting < 15 minutes
- Returns to baseline with normal neuro exam
- No prior afebrile seizures
HY clues pointing away (think CNS infection/other)
- Persistent altered mental status, neck stiffness
- Focal deficits after the seizure (Todd paralysis can occur, but still treat as complex and evaluate carefully)
- Repeated seizures in 24 hours
- Age outside typical range
Commonly tested “don’t do this”
- Don’t order routine EEG for a simple febrile seizure
- Don’t get routine head CT/MRI if exam is normal and presentation is classic
- Don’t start chronic antiepileptics for simple febrile seizures
First Aid Cross-References (Where This Lives in FA)
In First Aid (Neurology → Seizures) you’ll typically see febrile seizures listed alongside:
- Seizure classifications and causes in pediatrics
- Key distinction: simple vs complex, benign nature, age range
When reviewing FA, annotate these extra Step-ready pearls next to the febrile seizure line:
- 6 months–5 years
- <15 min, generalized, no recurrence in 24 hours = simple
- LP only if meningitis suspected or special circumstances (very young, unimmunized, antibiotics)
- Antipyretics improve comfort but don’t prevent recurrence
Rapid Review Checklist (What to Memorize)
- Definition: seizure with fever in child 6 months–5 years, no CNS infection/metabolic cause
- Simple: generalized, <15 min, single in 24 hr, normal baseline after
- Complex: ≥15 min, focal, or recurrent in 24 hr
- Workup: minimal if simple + well-appearing; consider LP if meningitis concerns
- Tx: supportive; benzo if prolonged; no long-term AEDs for simple
- Prognosis: excellent; recurrence common; epilepsy risk slightly ↑ (more with complex)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
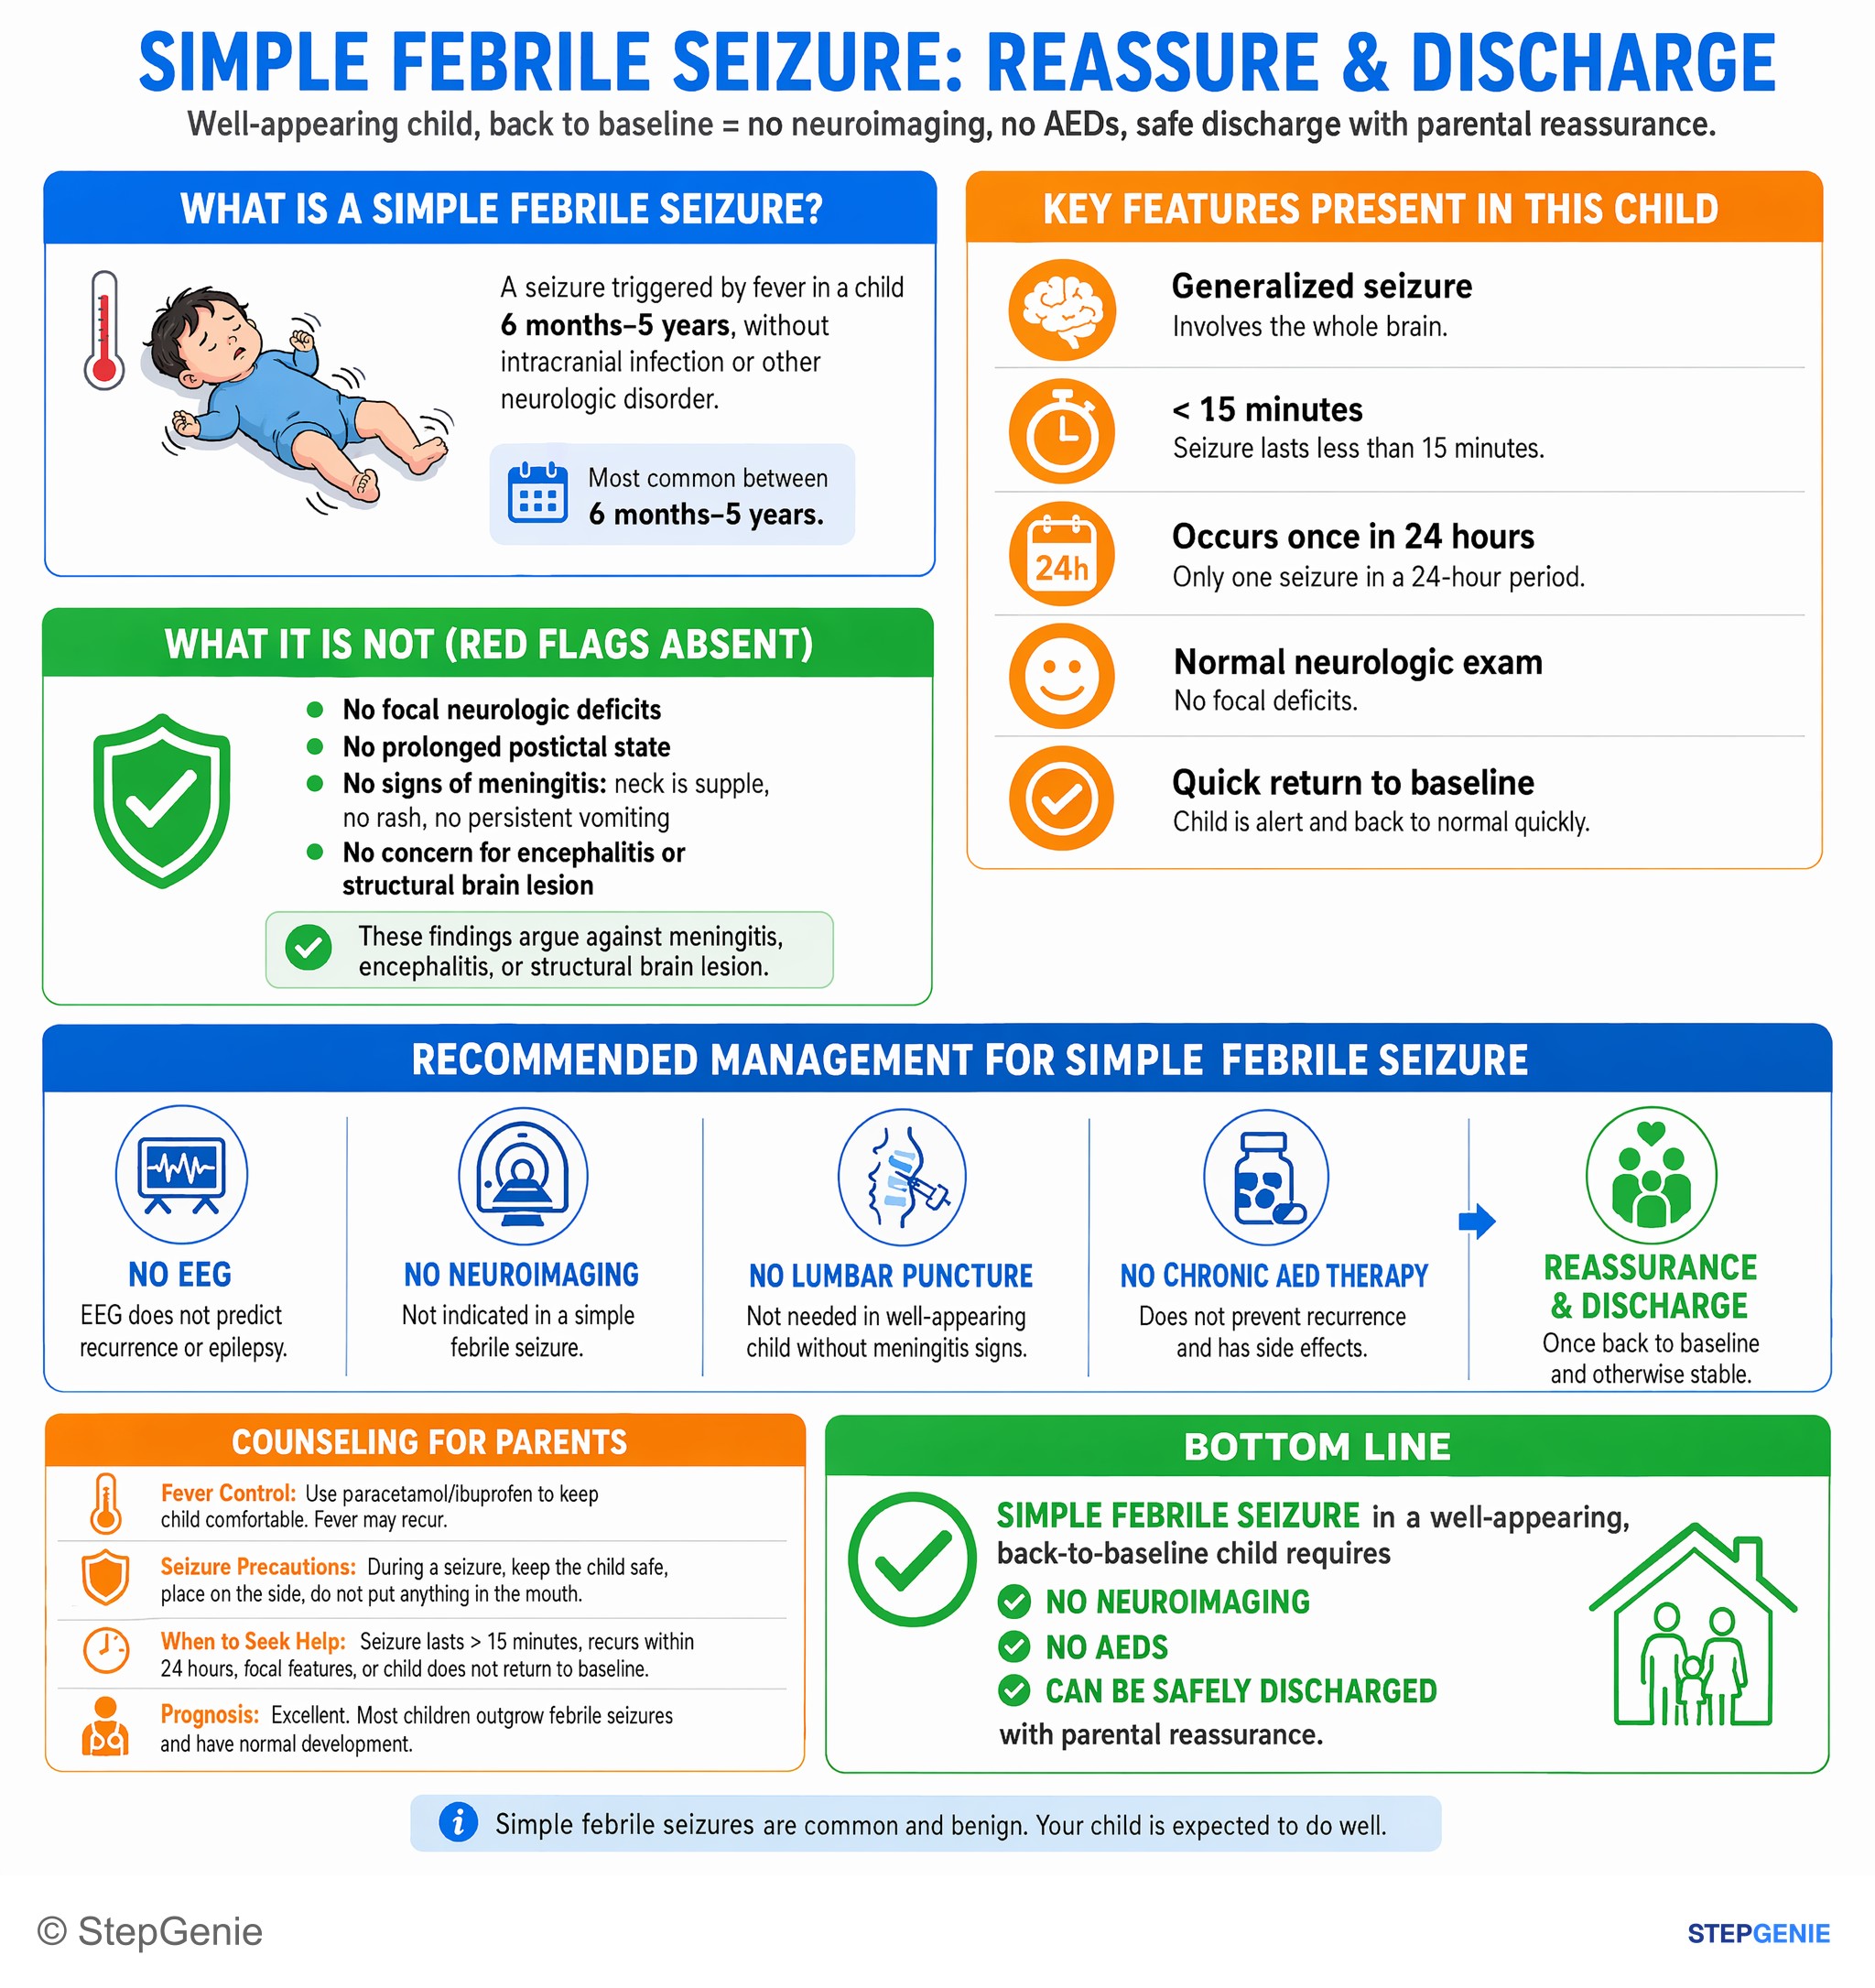
Simple febrile seizure in a well-appearing, back-to-baseline child requires **no neuroimaging, no AEDs, and can be safely discharged with…
USMLE Step 2Frequently Asked Questions
What is the classic age range for a febrile seizure, and when should you think of something else?
The classic age range is 6 months to 5 years, with most cases occurring between 6 and 18 months. A seizure with fever outside that window should push you to consider other causes such as CNS infection, epilepsy, toxic ingestion, or another non-febrile seizure etiology rather than assuming it is a febrile seizure.
Why does fever trigger seizures in young children?
Fever is thought to trigger seizures because it increases neuronal excitability in an immature brain. Young children have relatively immature inhibitory pathways, including GABAergic inhibition, which makes them more susceptible. A rapid rise in temperature is often more important than the absolute peak fever, and genetic predisposition also contributes, so family history is common.
How do you tell a simple febrile seizure from a complex febrile seizure?
A simple febrile seizure is generalized, lasts less than 15 minutes, does not recur within 24 hours, and the child returns to baseline quickly. A complex febrile seizure is long, focal, or multiple within 24 hours. Complex seizures may also have a prolonged postictal state or neurologic deficits and usually prompt more consideration for further evaluation.
Do you need labs, imaging, EEG, or a lumbar puncture for every febrile seizure?
No, a simple febrile seizure in a well-appearing child usually does not need labs, imaging, or EEG. Lumbar puncture is not done just because a seizure occurred; it is used when meningitis or encephalitis is suspected. Red flags include nuchal rigidity, photophobia, persistent altered mental status, toxic appearance, bulging fontanelle, petechiae or purpura, and persistent lethargy.
What is the treatment for a simple febrile seizure, and do antipyretics prevent recurrence?
Treatment is supportive, starting with airway, breathing, and circulation, and prolonged active seizures are treated with a benzodiazepine such as lorazepam. Most simple febrile seizures stop on their own within minutes. Acetaminophen or ibuprofen can improve comfort, but they do not reliably prevent recurrence, and chronic antiseizure medication is not recommended for simple febrile seizures.