Myasthenia gravis (MG) is one of those USMLE-friendly diagnoses you can spot in 5 seconds if you train your brain to look for the right pattern: fatigable weakness that gets worse with use and better with rest, especially in the eyes and bulbar muscles.
The 5-Second Rule (What you should think immediately)
If the stem says:
- Ptosis and/or diplopia
- Weakness worsens over the day or with repeated use
- Normal sensation
- Normal reflexes
- Improves with rest
→ Think Myasthenia gravis until proven otherwise.
One-liner: Autoantibodies against postsynaptic ACh receptors (or MuSK) → fewer functional receptors → fatigable weakness.
“MG = Muscle Gets tired” Mnemonic + Visual
The sticky-note mental image
Picture a neuromuscular junction where the muscle-side receptors are missing:
Nerve releases ACh → muscle has “empty parking spots” → each repeated signal finds fewer spots → muscle response fades.
Mini-mnemonic (shareable)
Myasthenia Gravis = Muscle Gives out
- Use it → lose it (temporarily)
- Rest it → best it
High-Yield Clinical Pattern (Step-style)
What’s weak?
- Extraocular: ptosis, diplopia (often first)
- Bulbar: dysphagia, dysarthria (nasal speech)
- Proximal limb weakness
- Respiratory involvement in severe cases (myasthenic crisis)
What’s not affected (classic clue)
- Sensation: intact
- Pupils: normal (helps separate from botulism)
- Reflexes: typically normal
Step 1 Pathophys in 20 Seconds
| Feature | Myasthenia gravis |
|---|---|
| Problem location | Postsynaptic neuromuscular junction |
| Antibody target | ACh receptor (most common) or MuSK |
| Mechanism | Receptor blockade + complement-mediated damage → ↓ endplate potentials |
| Result | Weakness that worsens with repeated activity |
| Key association | Thymic hyperplasia or thymoma |
Thymoma association is exam gold: MG can be a paraneoplastic clue—get chest imaging when suspected.
How to Diagnose (USMLE-High Yield)
Bedside / rapid testing concepts
- Ice pack test: improves ptosis (cold inhibits acetylcholinesterase → ↑ ACh in cleft)
Confirmatory testing
- AChR antibodies (binding/blocking/modulating)
- MuSK antibodies (esp if AChR Ab negative and bulbar prominent)
- Electrophysiology:
- Repetitive nerve stimulation: decremental response
- Single-fiber EMG: increased jitter (most sensitive)
Older “edrophonium test” is classic historically but less used clinically—still shows up on exams.
Treatment Framework (Quick + Testable)
Symptomatic
- Pyridostigmine (acetylcholinesterase inhibitor)
Disease-modifying / immunotherapy
- Corticosteroids
- Steroid-sparing agents: azathioprine, mycophenolate
- Thymectomy: especially with thymoma (and often beneficial even without thymoma in AChR+ generalized MG)
Myasthenic crisis (respiratory failure risk)
- IVIG or plasmapheresis (fastest immunologic improvement)
- Plus airway/ventilation support as needed
Clinical trigger clue: infection, surgery, pregnancy/postpartum, certain meds can precipitate crisis.
Medications That Worsen MG (Classic Step Trap)
Common “don’t do it” culprits:
- Aminoglycosides
- Fluoroquinolones
- Macrolides
- Magnesium
- Beta-blockers
- Neuromuscular blockers (esp peri-op)
MG vs Lambert-Eaton vs Botulism (5-second differentiator table)
| Feature | Myasthenia gravis | Lambert-Eaton (LEMS) | Botulism |
|---|---|---|---|
| Lesion | Postsynaptic AChR/MuSK | Presynaptic Ca channels | Presynaptic ACh release blocked |
| Weakness pattern | Worse with use | Improves with use (facilitation) | Descending paralysis |
| Reflexes | Normal | Decreased | Variable, often decreased |
| Pupils/autonomics | Usually normal | Autonomic symptoms common | Dilated pupils, autonomic symptoms |
| Cancer link | Thymoma | Small cell lung cancer | Foodborne/infant/wound source |
The 5-Second Takeaway (Ultra-shareable)
Myasthenia gravis = fatigable weakness (eyes/bulbar first) + normal pupils/sensation/reflexes + improves with rest → AChR (or MuSK) antibodies; treat with pyridostigmine + immunotherapy; crisis = IVIG/plasmapheresis.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
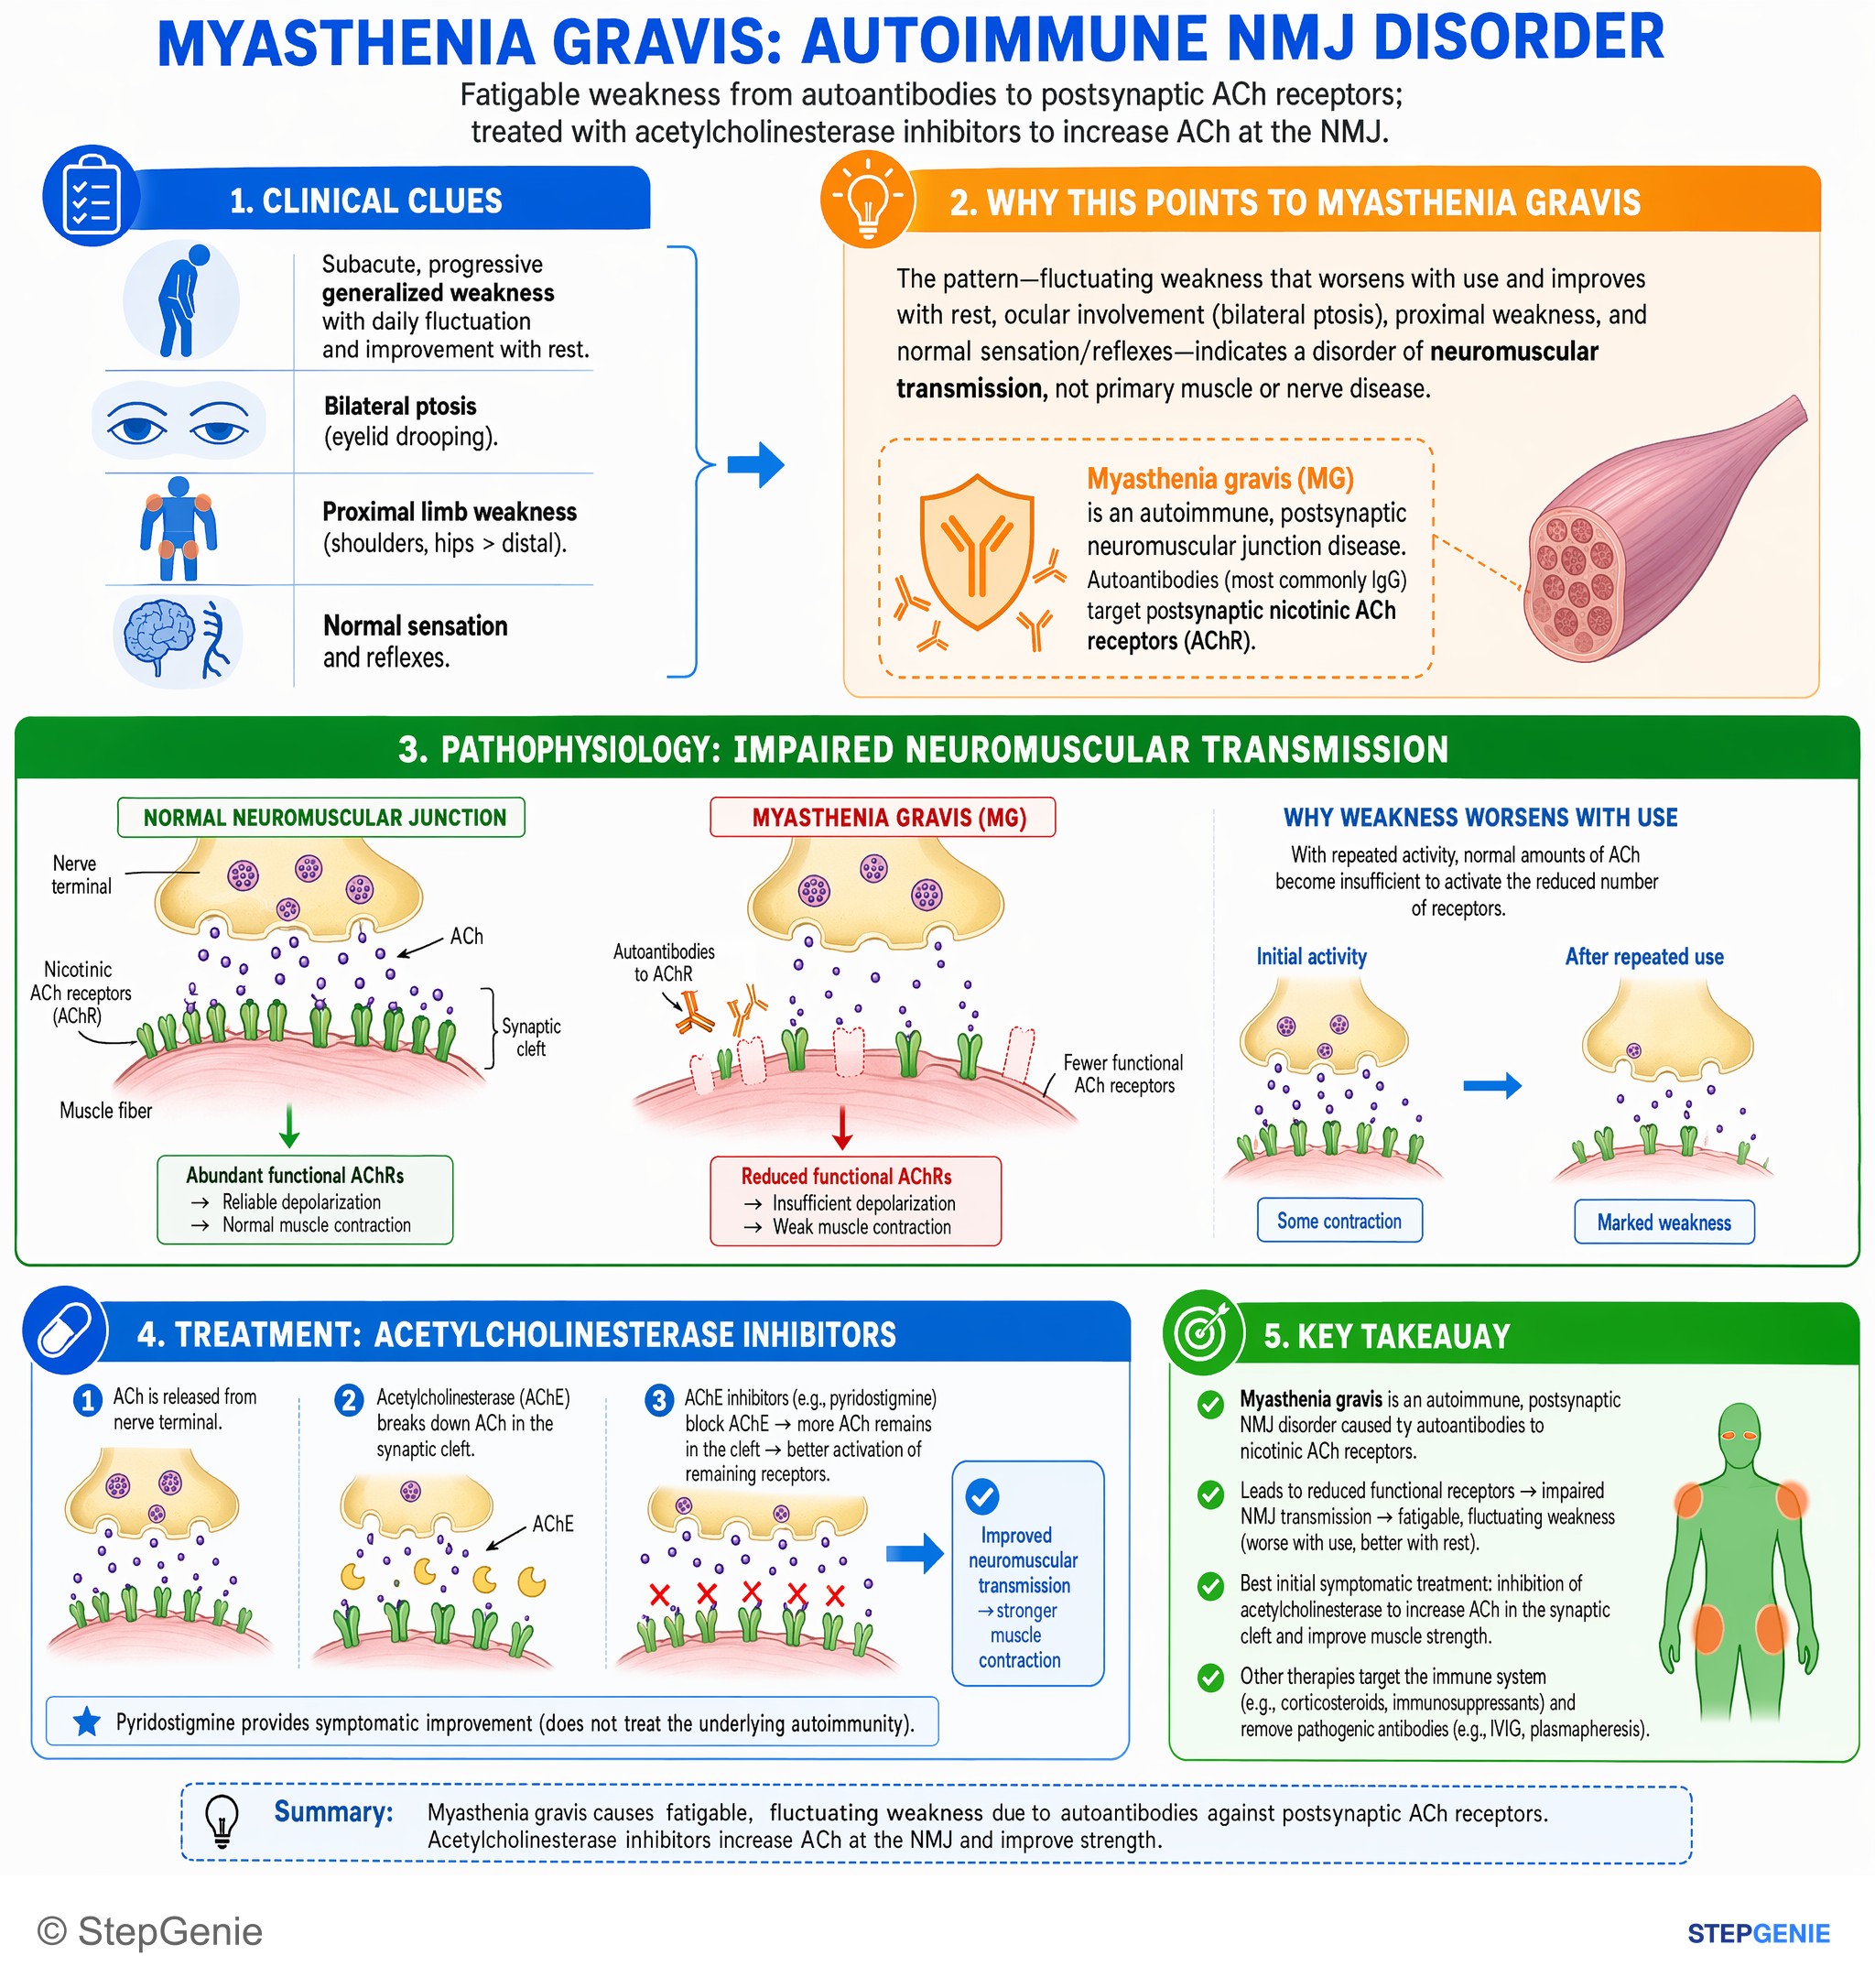
Myasthenia gravis causes fatigable weakness from autoantibodies to postsynaptic ACh receptors; treated with acetylcholinesterase…
USMLE Step 1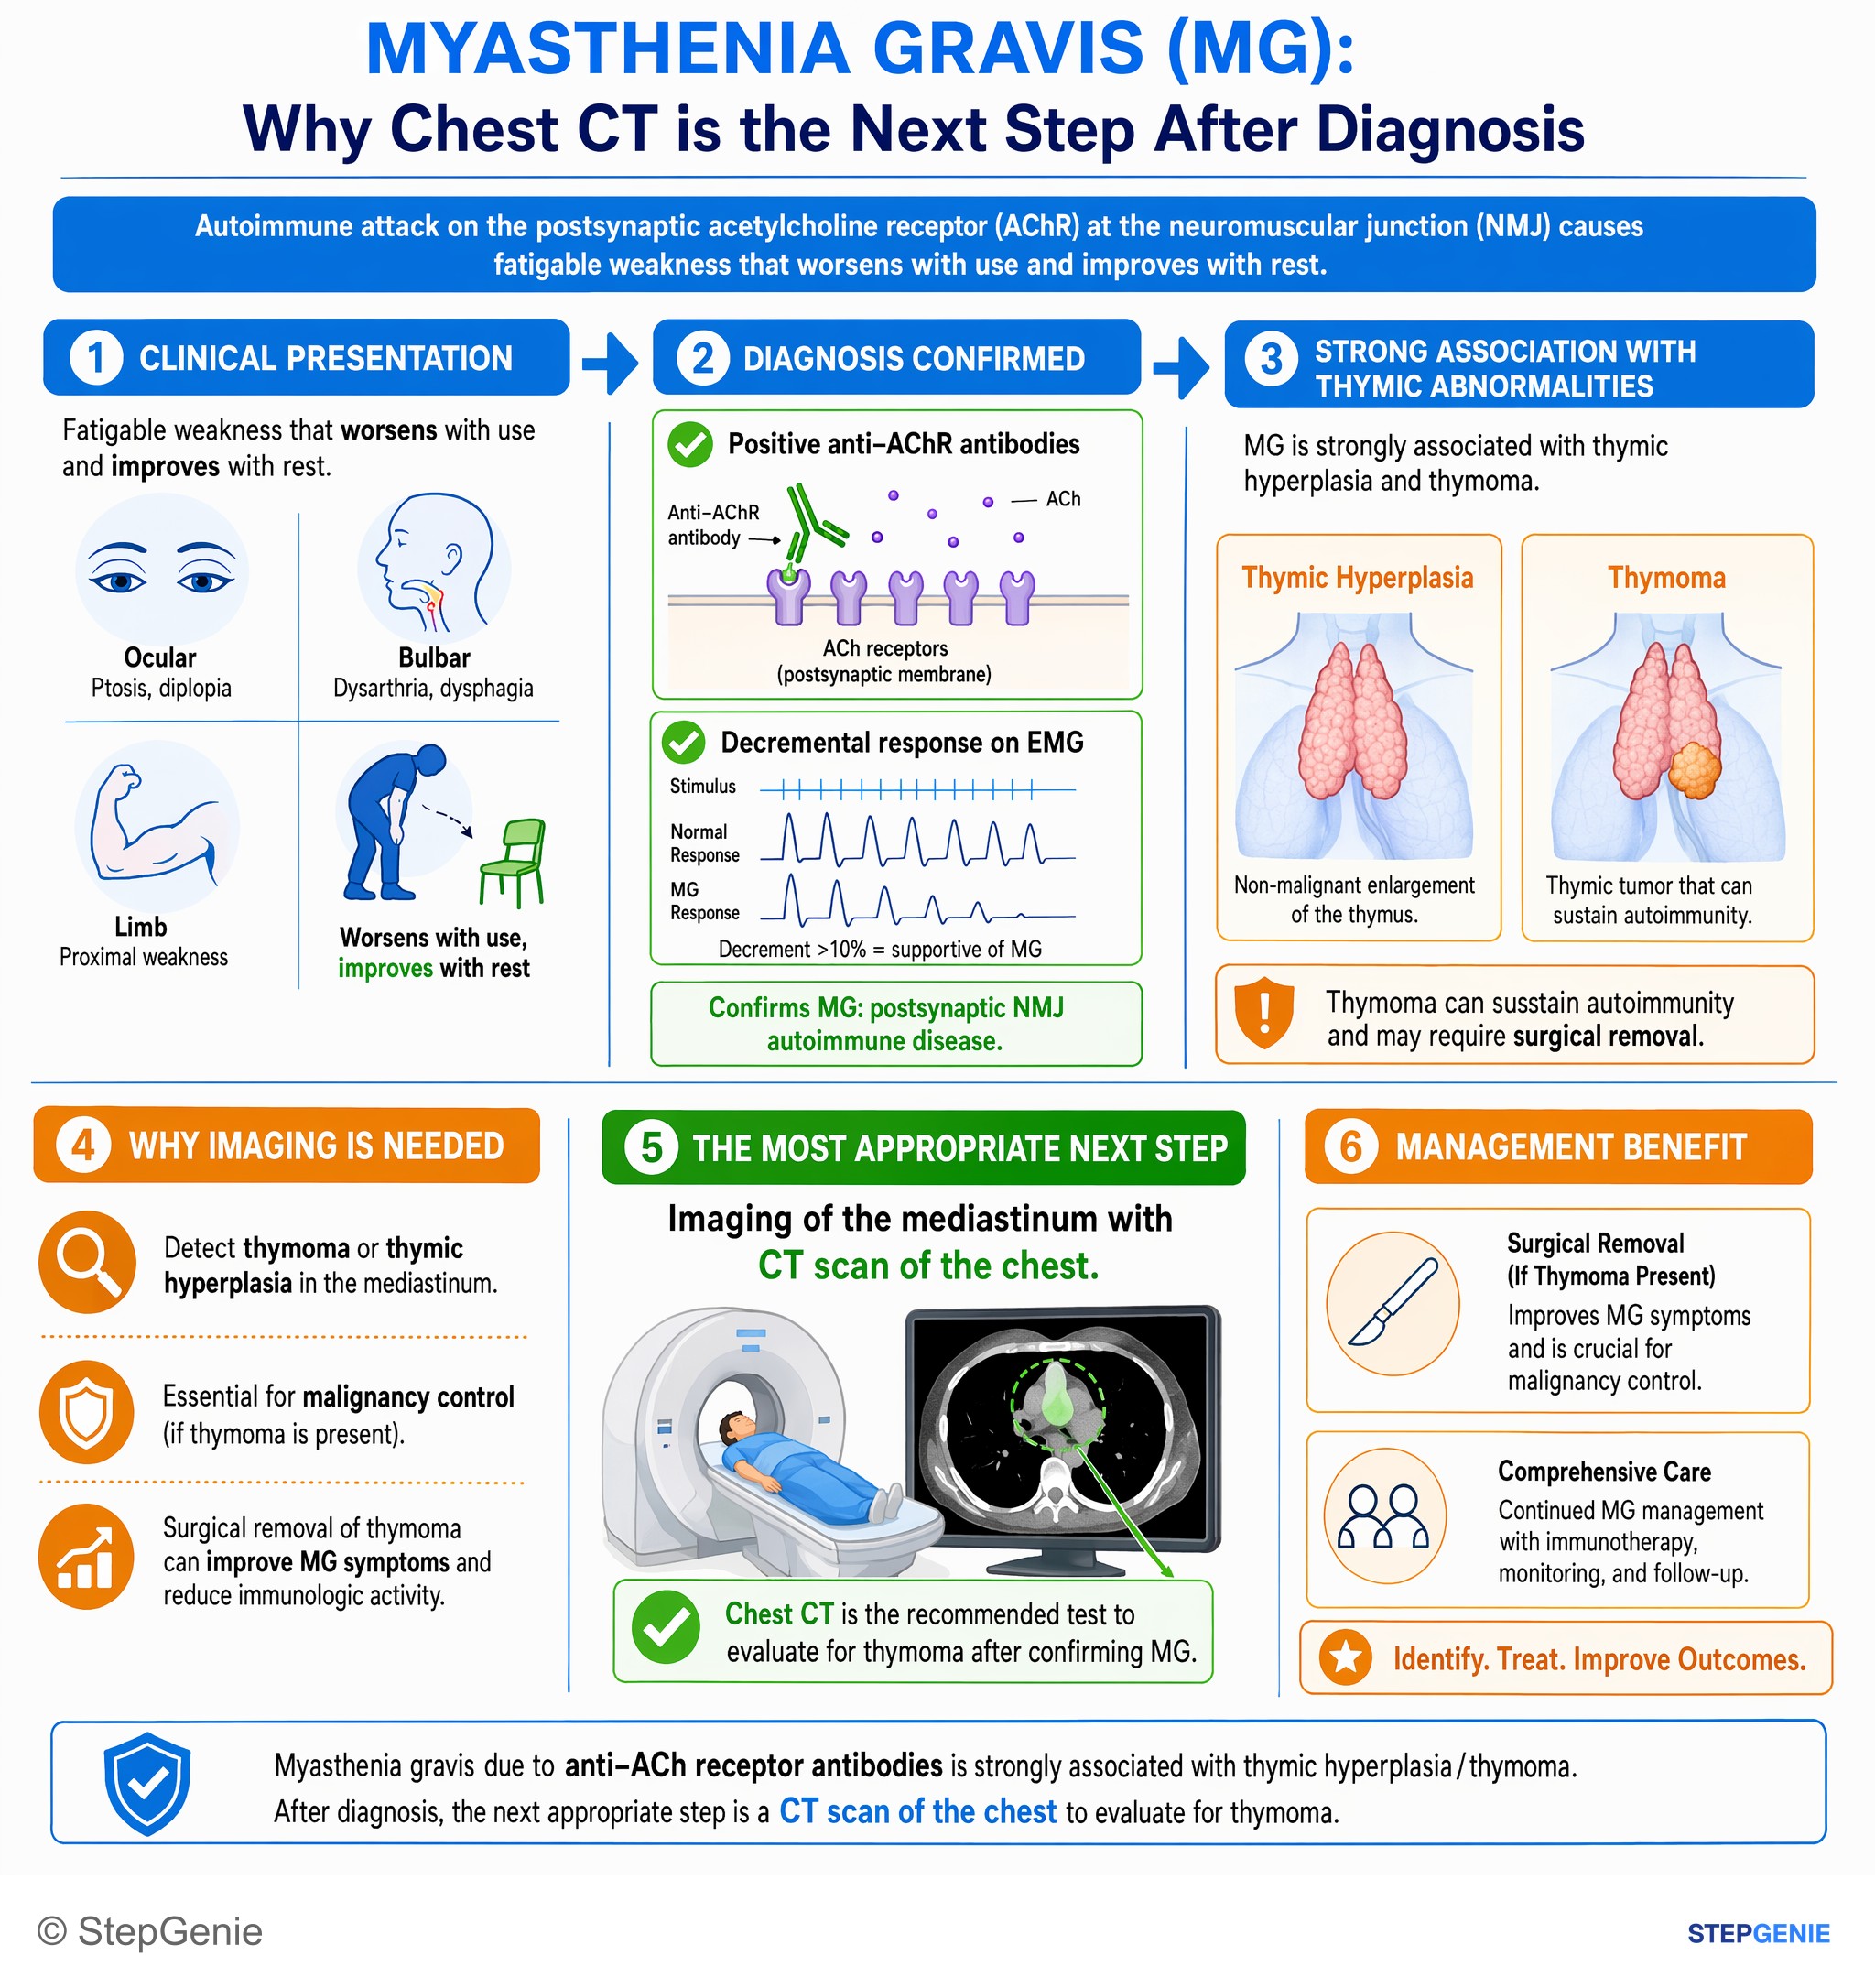
Myasthenia gravis from anti–ACh receptor antibodies is strongly associated with thymic hyperplasia/thymoma → evaluate with chest CT after…
USMLE Step 2Frequently Asked Questions
How do you recognize myasthenia gravis in a question stem quickly?
Think myasthenia gravis when the stem shows fatigable weakness that worsens with repeated use and improves with rest, especially with ptosis, diplopia, or bulbar symptoms. The classic supporting clues are normal sensation, normal reflexes, and normal pupils. This pattern points to a neuromuscular junction problem affecting strength without affecting sensory pathways or pupillary function.
Why does myasthenia gravis cause weakness that gets worse with use?
Myasthenia gravis causes fatigable weakness because autoantibodies target postsynaptic acetylcholine receptors, or MuSK, at the neuromuscular junction. That leaves fewer functional receptors available, so with repeated signaling the muscle response fades. The nerve releases acetylcholine, but the muscle has too many missing receptor “parking spots,” causing strength to drop temporarily with use and improve with rest.
How do you tell myasthenia gravis from Lambert-Eaton syndrome or botulism?
Myasthenia gravis is distinguished by weakness that worsens with use, normal reflexes, and usually normal pupils and sensation. Lambert-Eaton syndrome instead improves with use and typically has decreased reflexes with autonomic symptoms. Botulism causes presynaptic blockade of acetylcholine release, often presents with descending paralysis, and commonly has dilated pupils and autonomic findings, which helps separate it from myasthenia gravis.
What tests help confirm myasthenia gravis?
Useful confirmatory tests for myasthenia gravis include acetylcholine receptor antibodies, MuSK antibodies, and electrophysiologic studies. Repetitive nerve stimulation shows a decremental response, while single-fiber EMG shows increased jitter and is the most sensitive test mentioned. A bedside ice pack test can improve ptosis because cooling inhibits acetylcholinesterase, increasing acetylcholine in the synaptic cleft.
What is the treatment for myasthenia gravis and myasthenic crisis?
Symptomatic treatment for myasthenia gravis is pyridostigmine, and disease-modifying therapy includes corticosteroids, azathioprine, mycophenolate, and thymectomy in appropriate patients. Myasthenic crisis requires rapid immunologic therapy with IVIG or plasmapheresis, along with airway or ventilatory support if needed. Infection, surgery, pregnancy or postpartum state, and certain medications can precipitate crisis.