Insulin questions are USMLE catnip: they’re fast, pattern-based, and loaded with high-yield traps (timing, onset/peak/duration, and which ones you can mix). If you can “see” an insulin curve in your head and match it to the patient’s story, you’ll pick up easy points on Step 1 and Step 2—especially on diabetes treatment vignettes and hypoglycemia scenarios.
Big Picture: What Insulin Is and Why We Use It
Insulin is a peptide hormone made by pancreatic -cells (islets of Langerhans). Its job is to promote the fed/anabolic state by:
- Increasing glucose uptake in muscle and adipose via GLUT4 translocation
- Increasing glycogen synthesis (liver, muscle)
- Increasing lipogenesis and decreasing lipolysis
- Increasing protein synthesis and decreasing proteolysis
- Driving potassium into cells (clinically important!)
USMLE framing: Insulin is the “storage hormone.” When insulin is absent (Type 1) or ineffective (Type 2), the body behaves like it’s starving—even when glucose is high.
First Aid cross-reference: Endocrine → Diabetes mellitus pharmacology; insulin preparations; DKA/HHS.
Pathophysiology Refresher (Because Insulin Types Show Up in Context)
Type 1 Diabetes Mellitus (T1DM)
- Autoimmune destruction of -cells → absolute insulin deficiency
- Associated with HLA-DR3, HLA-DR4
- Autoantibodies: anti-GAD, anti-islet cell
- Leads to:
- DKA risk (ketogenesis from uninhibited lipolysis)
- Weight loss, polyuria, polydipsia
HY Step clue: young patient + weight loss + ketosis + needs insulin.
Type 2 Diabetes Mellitus (T2DM)
- Insulin resistance + eventual -cell dysfunction
- Associated with obesity, metabolic syndrome
- Leads to:
- HHS risk (severe hyperglycemia, dehydration, minimal ketosis)
- Often initially managed without insulin; insulin later as -cells fail
HY Step clue: older/obese + very high glucose + high serum osmolality + no acidosis = HHS.
Clinical Presentation & Diagnosis (Fast USMLE Checklist)
Classic symptoms
- Polyuria, polydipsia, polyphagia
- Blurry vision, fatigue
- Recurrent infections (e.g., Candida), poor wound healing (more T2)
Diagnostic criteria (any one, confirmed if asymptomatic)
- A1c
- Fasting plasma glucose mg/dL
- 2-hour OGTT mg/dL
- Random plasma glucose mg/dL + symptoms
First Aid cross-reference: Endocrine → Diabetes diagnosis; A1c.
Treatment Overview (Where Insulin Types Actually Matter)
When insulin is required/strongly indicated
- All T1DM (lifelong)
- DKA (IV regular insulin)
- HHS (IV insulin after fluids, depending on protocol)
- T2DM with:
- Marked hyperglycemia (e.g., A1c , glucose )
- Symptoms/catabolic state (weight loss)
- Pregnancy (insulin preferred; some oral agents used selectively)
- Failure of non-insulin therapy
Step-ready principle: insulin is the most powerful glucose-lowering therapy and the most testable for acute complications.
The Core of This Post: Insulin Types You Must Know
Why timing matters
USMLE loves “What insulin caused the 3 AM hypoglycemia?” or “Which insulin covers post-meal spikes?” That’s all about onset, peak, duration.
Insulin types at a glance (high-yield table)
| Class | Insulins | Onset | Peak | Duration | Common use | HY notes |
|---|---|---|---|---|---|---|
| Rapid-acting | Lispro, Aspart, Glulisine | ~15 min | ~1 hr | ~3–4 hr | Meals/corrections | “LAG” for rapid. Give right before eating. Less late hypoglycemia. |
| Short-acting | Regular | ~30–60 min | ~2–4 hr | ~5–8 hr | Meals; IV in DKA | Only one commonly used IV. Risk of hypoglycemia if meal delayed. |
| Intermediate-acting | NPH | ~1–2 hr | ~4–12 hr | ~12–18 hr | Basal (older regimens), BID dosing | Not Peakless, Has peak → nocturnal hypoglycemia. Cloudy. |
| Long-acting | Glargine, Detemir | ~1–2 hr | minimal | ~24 hr | Basal insulin | “Peakless.” Glargine can precipitate if mixed. |
| Ultra–long-acting | Degludec | ~1 hr | minimal | > 24–42 hr | Basal with flexible dosing | Very long half-life; stable basal coverage. |
First Aid cross-reference: Endocrine pharm → insulin preparations; onset/peak/duration; mixing rules.
High-Yield Memory Anchors (Fast Recall on Test Day)
Rapid vs Regular (classic USMLE compare/contrast)
-
Rapid-acting (lispro/aspart/glulisine)
- Better for postprandial control
- Can dose immediately before meals
- Lower risk of “late” post-meal hypoglycemia
-
Regular insulin
- Must be dosed 30 minutes before meals
- IV option for emergencies (DKA, severe hyperkalemia adjunct)
- Used in some older sliding-scale regimens (less ideal)
NPH is the “peaky basal”
- Peaks significantly → hypoglycemia risk, especially overnight
- Often used BID (morning + evening)
- “Cloudy” insulin (because it’s a suspension)
Glargine/Detemir/Degludec = basal backbone
- Minimal peak → steadier basal coverage
- Common in basal-bolus therapy with rapid-acting mealtime insulin
Mixing Insulins: A Favorite Step 1 Trap
What you can mix
- Regular + NPH: yes
- Rapid-acting + NPH: yes (commonly in practice)
What you should not mix (classic)
- Glargine: do not mix with other insulins
- It’s formulated to precipitate in subcutaneous tissue; mixing can alter absorption.
Technique pearl: “Clear before cloudy”
When drawing up from vials:
- Draw up clear (Regular/rapid) before cloudy (NPH)
This prevents contaminating the clear vial with NPH.
First Aid cross-reference: insulin mixing rules; NPH cloudy.
Clinical Scenarios (How Insulin Types Show Up in Vignettes)
Scenario 1: “Woke up shaky at 3 AM”
- Patient on evening NPH → nocturnal hypoglycemia due to NPH peak
- Management strategies:
- Adjust evening NPH dose
- Add bedtime snack
- Consider switching basal regimen (e.g., glargine)
HY association: NPH peak = night lows.
Scenario 2: “Meal is delayed after insulin was given”
- Patient took regular insulin 30–45 minutes before food, then meal delayed → hypoglycemia risk
Rapid-acting would have allowed tighter timing.
Scenario 3: “DKA management in the ED”
- Treat with:
- IV fluids
- IV regular insulin
- Potassium monitoring/repletion
Insulin drives into cells → can unmask/worsen hypokalemia.
HY warning: If potassium is very low, correct before insulin to avoid arrhythmias.
Scenario 4: Hyperkalemia treatment
- Insulin (often regular IV) + glucose shifts into cells (temporary fix)
- Mechanism: stimulates Na⁺/K⁺-ATPase → intracellular shift
Insulin Pharmacology: Mechanism + Adverse Effects (USMLE-Ready)
Mechanism of action
Insulin binds a receptor tyrosine kinase → autophosphorylation → downstream signaling → GLUT4 insertion in adipose/muscle.
First Aid cross-reference: receptor types; RTKs (insulin, IGF-1).
Adverse effects (high yield)
- Hypoglycemia (most important)
- Symptoms: sweating, tremor, palpitations, anxiety (adrenergic) → confusion, seizures (neuroglycopenic)
- Weight gain
- Lipodystrophy at injection sites (rotate sites)
- Allergic reactions (rare)
- Hypokalemia (insulin shifts into cells)
Insulin Regimens You Should Recognize
Basal–bolus (common modern physiology-based regimen)
- Basal: glargine/detemir/degludec (or NPH)
- Bolus: rapid-acting with meals + correction doses
USMLE phrasing: “Tight control with long-acting plus rapid-acting at meals.”
Sliding scale (common in questions, less ideal outpatient)
- Reactive dosing based on glucose readings; can cause swings
- Step 2 may test “it’s not great alone,” but you still must understand it.
High-Yield Rapid Review: “Which insulin is it?”
| Clue in question | Most likely answer |
|---|---|
| IV insulin in DKA | Regular insulin |
| “LAG” rapid onset for meals | Lispro, Aspart, Glulisine |
| “Cloudy” insulin with a peak | NPH |
| “Peakless” basal, 24-hour coverage | Glargine (or Detemir) |
| Ultra-long basal, very long duration | Degludec |
| Nocturnal hypoglycemia in older regimen | NPH |
First Aid-Style Pearls to Lock In Points
- Insulin receptor = receptor tyrosine kinase (Step 1 classic).
- Regular insulin is IV-usable (DKA, hyperkalemia shift).
- NPH is intermediate + peaks → hypoglycemia.
- Glargine is long-acting + cannot be mixed (common exam line).
- Hypoglycemia is the key toxicity—think autonomic symptoms first, then neuro symptoms.
Quick Self-Quiz (Check Your Pattern Recognition)
- Patient with T1DM has morning headaches and night sweats on NPH: what happened?
- Which insulin do you start in the ED for DKA?
- Which insulin is best to cover the glucose spike from dinner?
- Why can insulin lower potassium?
(If you can answer these quickly, your insulin pharmacology is in great shape.)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
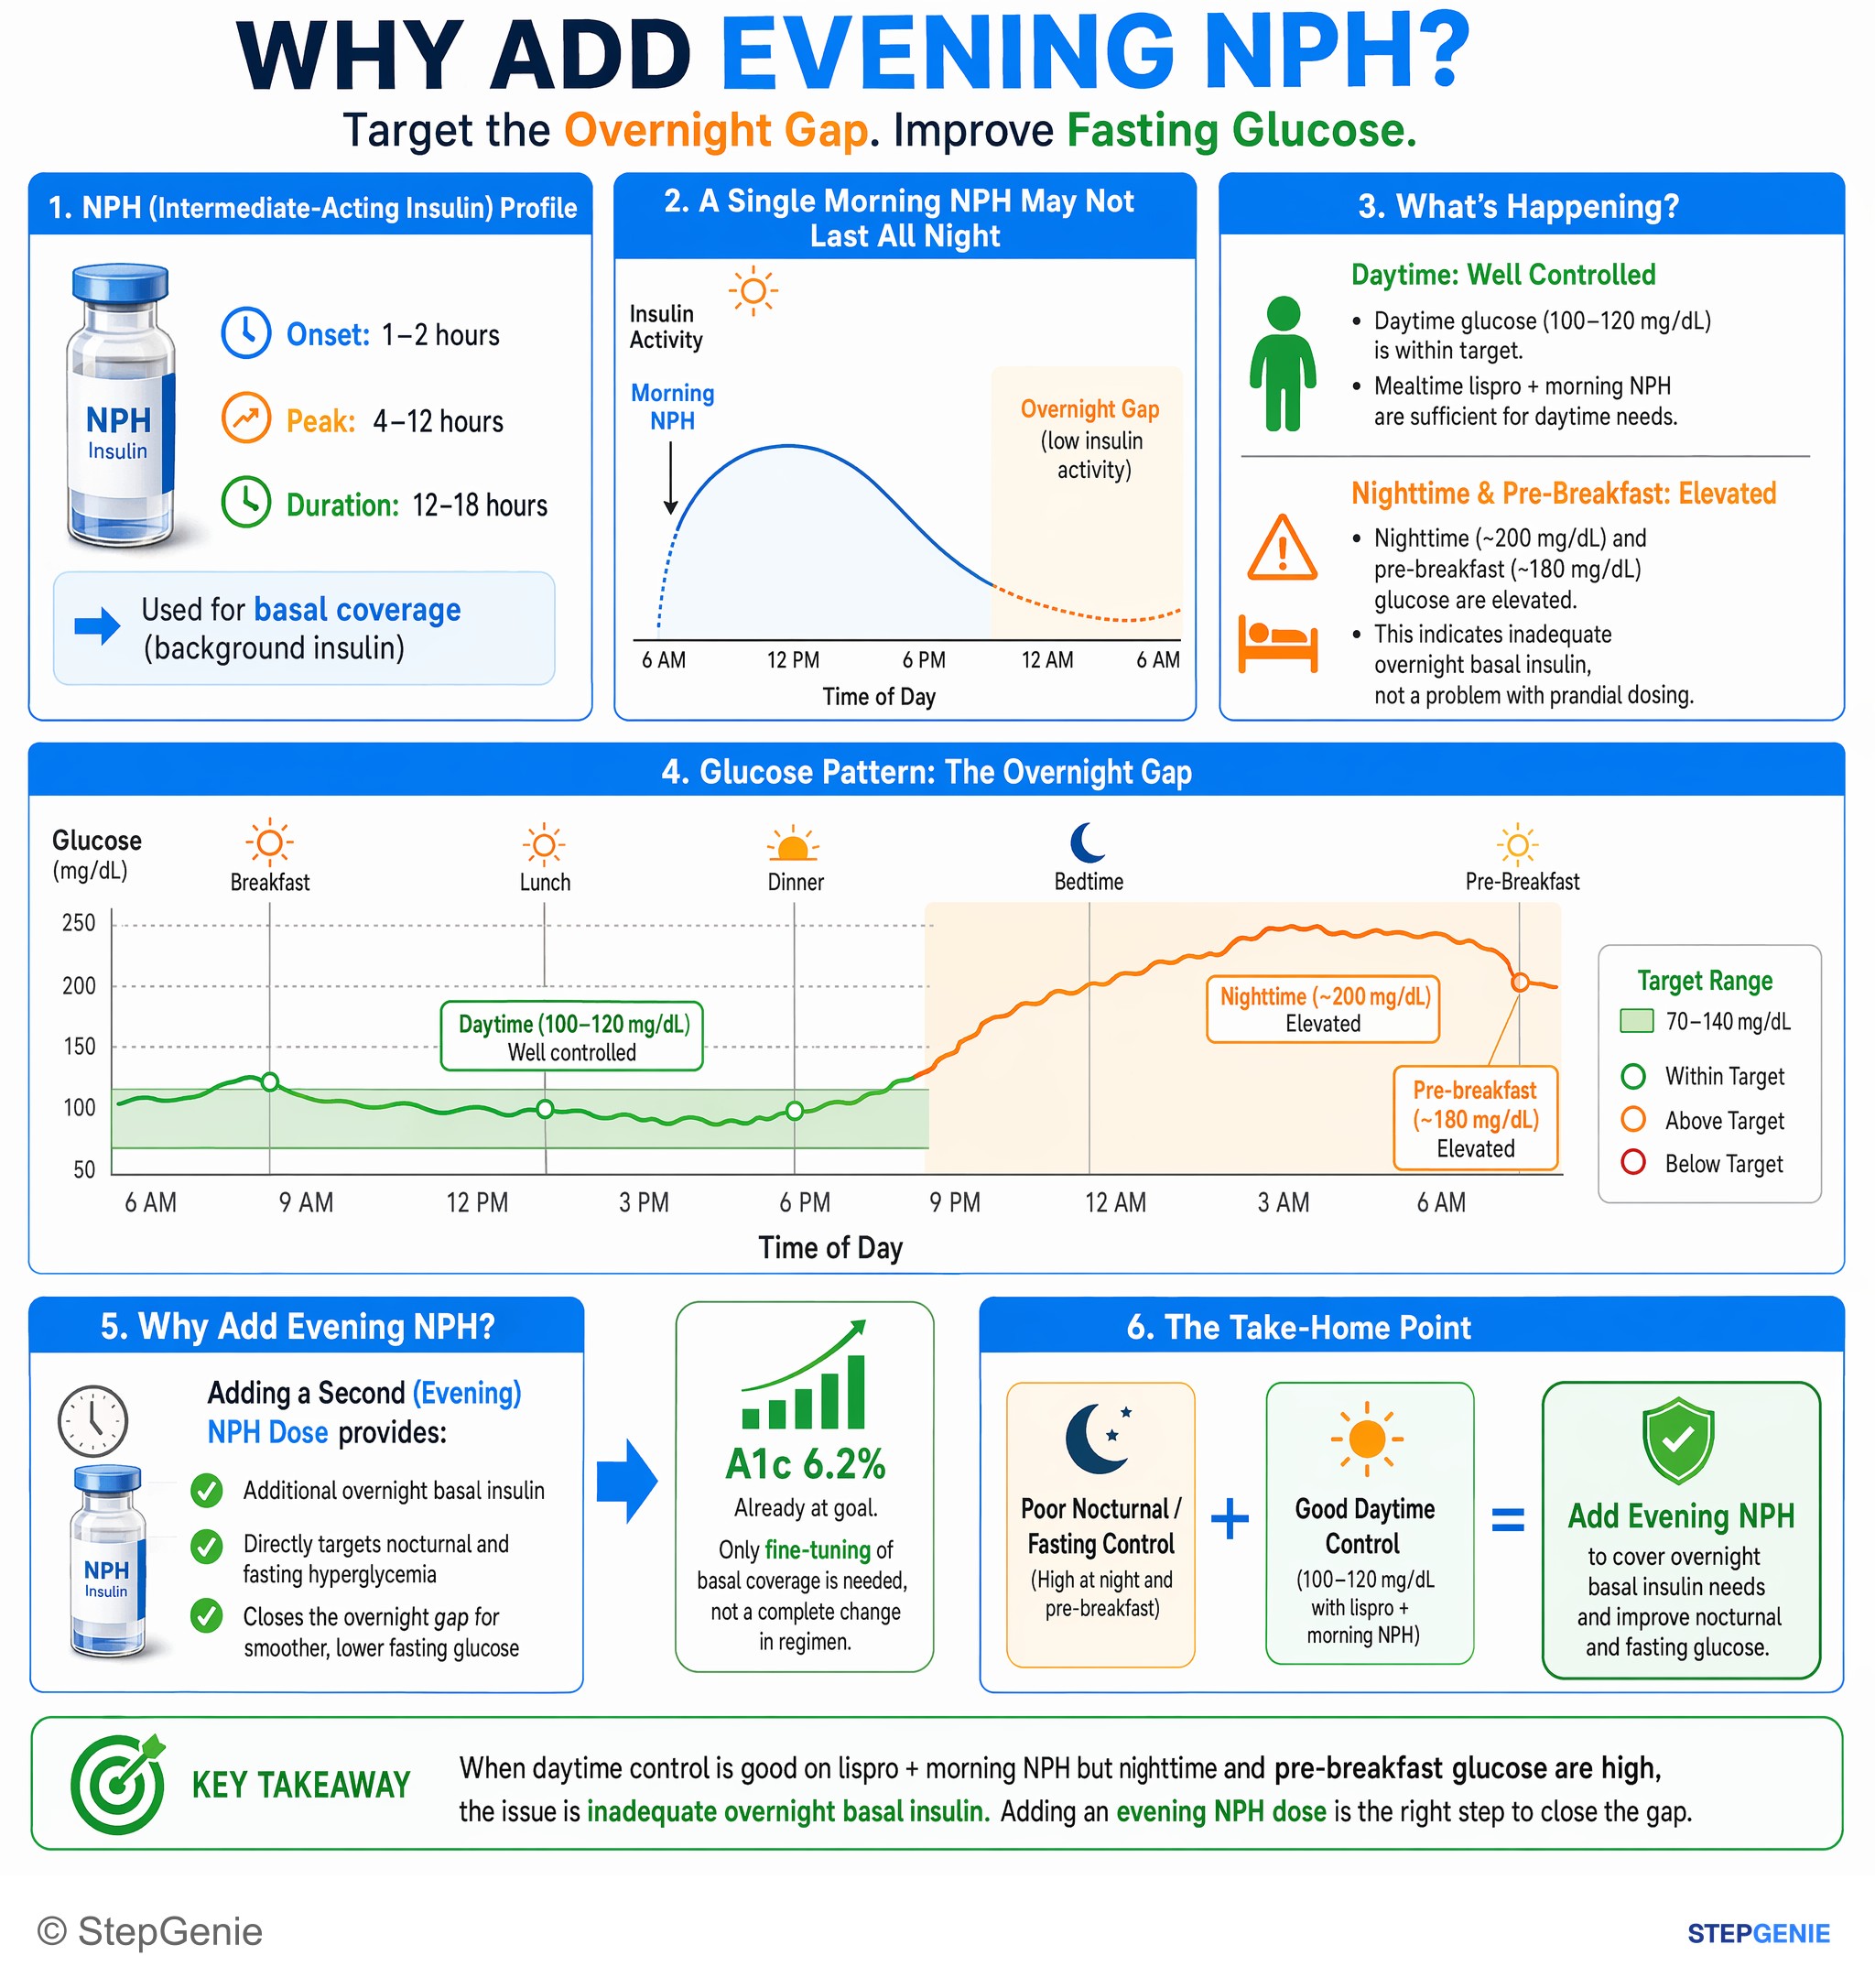
Poor nocturnal/fasting control with good daytime control on lispro + morning NPH → add evening NPH to cover overnight basal insulin needs.
USMLE Step 2Frequently Asked Questions
Which insulin is used IV in DKA?
Regular insulin is the commonly used IV insulin in DKA. It is a short-acting insulin with an onset of about 30 to 60 minutes, a peak at 2 to 4 hours, and a duration of about 5 to 8 hours. It is specifically highlighted as the insulin used IV for emergencies, making it the key answer for DKA treatment questions.
How do you tell rapid-acting insulin from regular insulin on Step 1?
Rapid-acting insulin is given right before meals and is best for postprandial glucose spikes, while regular insulin must be given about 30 minutes before meals. Rapid-acting agents are lispro, aspart, and glulisine, with faster onset and less late hypoglycemia. Regular insulin has a slower onset and is also the one commonly used IV in emergencies like DKA.
Why does NPH cause nocturnal hypoglycemia?
NPH causes nocturnal hypoglycemia because it has a real peak rather than flat basal activity. Its onset is about 1 to 2 hours, its peak is about 4 to 12 hours, and its duration is about 12 to 18 hours. When given in the evening, that peak can occur overnight, which is why a patient may wake up shaky at 3 AM.
Which insulins should not be mixed, and what is the classic mixing rule?
Glargine should not be mixed with other insulins because it is formulated to precipitate in subcutaneous tissue and mixing can alter its absorption. In contrast, regular plus NPH and rapid-acting plus NPH can be mixed. The classic vial technique is clear before cloudy, meaning draw up clear insulin like regular or rapid before cloudy NPH.
Which insulin types provide basal coverage versus mealtime coverage?
Basal coverage comes from NPH, glargine, detemir, and degludec, while mealtime coverage comes from rapid-acting insulin and sometimes regular insulin. Rapid-acting lispro, aspart, and glulisine are used for meals and corrections. Glargine and detemir are long-acting with minimal peak, and degludec is ultra-long-acting, giving stable basal coverage over more than 24 to 42 hours.