MEN2A and MEN2B both come from activating RET mutations and cause medullary thyroid carcinoma (MTC) and pheochromocytoma; MEN2A adds primary hyperparathyroidism, while MEN2B adds mucosal neuromas, a marfanoid habitus and intestinal ganglioneuromatosis. MEN2B, usually RET M918T, brings the earliest and most aggressive MTC and almost never hyperparathyroidism.
MEN1 is the third syndrome: loss of the menin tumor suppressor causes the 3 P's (parathyroid, pituitary, and pancreatic or duodenal neuroendocrine tumors), and primary hyperparathyroidism is the most common and usually the first sign. All three are autosomal dominant.
Calcium sorts them on the exam: hypercalcemia is expected in MEN1, appears in a minority with MEN2A and is essentially absent in MEN2B. Before thyroid surgery for MTC in MEN2, pheochromocytoma must be excluded.
MEN1 vs MEN2A vs MEN2B at a glance
| Feature | MEN1 | MEN2A | MEN2B |
|---|---|---|---|
| Gene | MEN1 (menin), 11q13: tumor suppressor, loss of function | RET, 10q11.21: proto-oncogene, gain of function | RET, M918T in about 95% |
| Parathyroid | Usually the first sign; nearly all by age 50; multigland | 20-30%, mild | Under 1% |
| Thyroid | No MTC | MTC in about 95% | MTC in about 100%, from infancy |
| Adrenal | Adrenocortical lesions (20-73%), mostly nonfunctioning; pheochromocytoma under 1% | Pheochromocytoma about 50% | Pheochromocytoma about 50% |
| Pancreas, duodenum, pituitary | Nonfunctioning NETs (about 55%), gastrinoma (about 40%), insulinoma (about 10%); pituitary adenoma, most often prolactinoma | No | No |
| Skin and build | Facial angiofibromas, collagenomas, lipomas | Lichen amyloidosis (codon 634) | Mucosal neuromas, marfanoid habitus |
| Prevention | Lifelong surveillance from childhood; thymectomy with parathyroid surgery | Thyroidectomy timed by genotype | Thyroidectomy in the first year of life (M918T) |
| Hypercalcemia? | Yes, usually first | Sometimes | No |
Count the P's: 3, 2, 1. MEN1 has 3 P's (parathyroid, pituitary, pancreas), the label Endotext uses; MEN2A has 2 (pheochromocytoma, parathyroid) plus MTC; MEN2B has 1 (pheochromocytoma) plus MTC, mucosal neuromas and a marfanoid habitus. The P that MEN2B loses is the parathyroid, which is why its calcium is normal.
Where MEN4 fits. MEN4 is caused by CDKN1B (12p13.1), a tumor suppressor that encodes the cyclin-dependent kinase inhibitor p27, and it mimics MEN1: primary hyperparathyroidism (usually a single adenoma, diagnosed around age 50), pituitary adenomas and, less often, pancreatic NETs, with no MEN1-type skin lesions reported (GeneReviews; StatPearls). Fewer than 100 genetically confirmed cases are known. Test CDKN1B when a patient looks like MEN1 but has no MEN1 variant.
MEN2A vs MEN2B: the key differences
| MEN2A | MEN2B | |
|---|---|---|
| Share of MEN2 | About 95% (includes familial MTC) | About 5% |
| Usual RET variant | Cysteine codons in exons 10 and 11 (609, 611, 618, 620, 630, 634) | M918T in about 95%; A883F in under 5% |
| ATA risk group | High (codon 634) or moderate (the rest) | Highest (M918T); high (A883F) |
| MTC | About 95%; usually the first tumor; childhood (codon 634) to early adulthood | About 100%; infancy or early childhood; most aggressive |
| Pheochromocytoma | About 50% (varies by codon), often bilateral | About 50%, often bilateral |
| Primary hyperparathyroidism | 20-30%, usually mild | Under 1% |
| Signature extras | Cutaneous lichen amyloidosis (codon 634); Hirschsprung disease (exon 10) | Mucosal neuromas of lips and tongue, thick everted eyelids, prominent corneal nerves, no tears in infancy, marfanoid habitus, intestinal ganglioneuromatosis |
| New (de novo) variant | 5-9% | 50-75% |
| Preventive thyroidectomy | At or before age 5 for codon 634; timed by calcitonin for moderate-risk variants | In the first year of life for M918T; at or before age 5 for A883F |
| Other name | Sipple syndrome | Mucosal neuroma syndrome |
- Calcium is the quickest split. Primary hyperparathyroidism in a patient with MEN2 means MEN2A; MEN2B "is not associated with an increased risk for clinically significant parathyroid disease" (GeneReviews).
- The face is the other split. MEN2B features are almost always visible before the thyroid nodule (ATA): thick "blubbery" lips, bumps on the tongue, everted eyelids, a long, thin build. Children diagnosed from these features were younger and more often cured.
Tip 1: MEN1 = the 3 P's, and calcium usually comes first
MEN1 follows the two-hit model: a germline loss-of-function MEN1 variant plus an acquired second hit in the gland inactivates menin, a nuclear scaffold protein that restrains cell proliferation (GeneReviews; Endotext). About 10% of cases are de novo, so a negative family history does not rule it out. Penetrance passes 50% by age 20 and 95% by age 40-70, depending on the series.
- Parathyroid, the first and most common P. Primary hyperparathyroidism is usually the first clinical feature, typically begins between ages 20 and 25, and is present in essentially everyone by 50. It is multigland disease, not a single adenoma, so the operation is a subtotal (3.5-gland) parathyroidectomy or total parathyroidectomy with forearm autotransplantation, usually with transcervical thymectomy; about half recur within 10 years of a subtotal operation (Endotext). The physiology is drawn out in primary hyperparathyroidism.
- Pancreas and duodenum. Nonfunctioning NETs are the most common (about 55%), and malignant pancreatic and duodenal NETs are now the leading cause of MEN1-related death (Endotext). Gastrinomas (about 40%) cause Zollinger-Ellison syndrome: refractory or multiple ulcers, reflux and diarrhea. More than 90% arise in the duodenum, typically as multiple tumors under 1 cm (GeneReviews), and 20-25% of all gastrinoma patients have MEN1 (Endotext); see Zollinger-Ellison syndrome. Insulinomas (about 10%) cause fasting hypoglycemia about a decade earlier than sporadic ones.
- Pituitary. Adenomas occur in about 35-60%, mostly prolactinomas, then nonfunctioning adenomas; GH-secreting tumors are under 10% (Endotext; 2025 guideline). Compare prolactinoma vs acromegaly.
- Extras: thymic carcinoids (aggressive, mostly in men, worst in smokers), bronchial and gastric carcinoids, adrenocortical lesions, meningiomas, a higher breast cancer risk in women, and skin lesions (facial angiofibromas in about 85%, collagenomas in about 70%, lipomas in about 30%).
Diagnosis needs two of the three main tumors (clinical), one of them plus a first-degree relative with MEN1 (familial), or a germline MEN1 variant (genetic), per the Thakker 2012 guideline and GeneReviews.
Tip 2: MEN2A = MTC + pheo + parathyroid (RET switched on)
RET (10q11.21) encodes a receptor tyrosine kinase for GDNF-family ligands. MEN2 variants are gain-of-function: in MEN2A, cysteine changes in the extracellular domain let two receptors bond and signal without ligand (GeneReviews). That makes RET a proto-oncogene, the opposite of menin (oncogenes vs tumor suppressors); loss-of-function RET variants cause Hirschsprung disease instead.
- Medullary thyroid carcinoma (about 95%) is usually the first tumor. It arises from calcitonin-secreting parafollicular C cells, classically taught as neural crest-derived (lineage tracing in mice points to endoderm), through a precursor stage of C-cell hyperplasia, and in MEN2 it is often multifocal and bilateral. More than half contain calcitonin-derived amyloid with apple-green birefringence on Congo red (StatPearls). Calcitonin and CEA are the markers; diarrhea appears when calcitonin is very high and signals a poor prognosis. Compare the thyroid cancer types.
- Pheochromocytoma (about 50%): often bilateral, almost always benign, and it makes epinephrine; a tumor that makes only normetanephrine argues against MEN2 (GeneReviews). It is the first tumor in 13-27% (GeneReviews), and before biochemical and genetic screening it, not MTC, was the most common cause of death in classical MEN2A (ATA).
- Primary hyperparathyroidism (20-30%, mostly codon 634): milder than in MEN1 and often asymptomatic, with one to four enlarged glands; surgeons remove only the visibly enlarged ones (ATA and NCCN, per StatPearls).
- The four MEN2A variants (ATA): classical MEN2A; MEN2A with cutaneous lichen amyloidosis, an intensely itchy, later pigmented patch over the upper back (dermatomes T2-T6), seen almost only with codon 634 variants and sometimes before MTC; MEN2A with Hirschsprung disease (about 7% of MEN2A, all exon 10: codons 609, 611, 618, 620); and familial MTC, families with MTC but no pheochromocytoma or hyperparathyroidism, still screened like MEN2A.
Tip 3: MEN2B = MTC + pheo + neuromas + marfanoid body, no parathyroid
MEN2B is only about 5% of MEN2, and about 95% of patients carry the same variant in the tyrosine kinase domain, RET p.Met918Thr (M918T); A883F accounts for under 5% and seems less aggressive (ATA). Half to three-quarters of cases are de novo (50% in GeneReviews, about 75% in the ATA guideline), so the parents are often healthy.
- MTC in essentially 100%, starting in infancy or early childhood. Before early thyroidectomy, the median age at death was 25 years (GeneReviews).
- Pheochromocytoma in about 50%; about half are multiple and often bilateral.
- No hyperparathyroidism (under 1%), so calcium screening is not needed.
- Mucosal neuromas of the tongue, lips, palate or pharynx (lips become thick and "blubbery"), eyelid neuromas that thicken and evert the upper lids, mild ptosis, prominent corneal nerves on slit lamp, and inability to make tears in infancy (ATA).
- Marfanoid habitus in about 75%, often with kyphoscoliosis, joint laxity and little subcutaneous fat (GeneReviews); other skeletal clues are a long, narrow face, high-arched palate, pectus excavatum, pes cavus and slipped capital femoral epiphyses (ATA). This is the body shape only; the cause is RET, not true Marfan syndrome.
- Intestinal ganglioneuromatosis (about 40% in GeneReviews), with bloating, constipation, diarrhea or megacolon, often from infancy. Obstruction can occur, but not from Hirschsprung disease (StatPearls).
How USMLE vignettes give each syndrome away
| Clue in the stem | Think |
|---|---|
| Kidney stones or hypercalcemia plus peptic ulcers, diarrhea or a prolactinoma | MEN1 |
| Multiple or refractory duodenal ulcers with diarrhea and a high gastrin | Gastrinoma (Zollinger-Ellison syndrome); check calcium for MEN1 |
| Facial angiofibromas, collagenomas or lipomas with hypercalcemia | MEN1 |
| Thyroid nodule with high calcitonin; amyloid that is apple-green on Congo red | MTC: send germline RET testing (20-30% are hereditary) |
| Episodic headache, sweating and palpitations; a relative who died during anesthesia | Pheochromocytoma; with MTC, think MEN2 |
| Itchy, pigmented patch between the shoulder blades with MTC | MEN2A with lichen amyloidosis (codon 634) |
| Newborn with bowel obstruction or severe constipation in a family with MTC | MEN2A with Hirschsprung disease (exon 10) |
| Bumpy lips and tongue, everted eyelids, no tears as a baby, long thin limbs | MEN2B |
| Hypercalcemia plus a jaw mass | Hyperparathyroidism-jaw tumor syndrome (CDC73), not MEN |
Hypercalcemia in the stem: sort it in three moves.
- Confirm it. Primary hyperparathyroidism and malignancy cause about 90% of cases (StatPearls).
- Check PTH. A high or inappropriately normal PTH means PTH-mediated disease: primary or tertiary hyperparathyroidism, lithium, or familial hypocalciuric hypercalcemia, which a low 24-hour urine calcium separates out (FHH breakdown). A suppressed PTH points elsewhere: PTHrP or bone metastases, granulomatous disease or lymphoma making 1,25-dihydroxyvitamin D, vitamin D toxicity, hyperthyroidism, immobilization or thiazides.
- Young age, multigland disease or a family history means a syndrome until proven otherwise: MEN1 with pancreatic or pituitary clues, MEN2A with a thyroid nodule or adrenergic spells.
Workup order: pheochromocytoma first, then the thyroid
- Confirm and stage the MTC: neck ultrasound, fine-needle aspiration and serum calcitonin and CEA (StatPearls); a calcitonin above 500 pg/mL calls for imaging for distant metastases (ATA).
- Send germline RET testing for every MTC, even with no family history: 1-7% of apparently sporadic MTC is hereditary (ATA).
- Exclude pheochromocytoma before any procedure: plasma free or 24-hour urine fractionated metanephrines, with adrenal imaging only if they are high (Endotext exempts very young children having prophylactic thyroidectomy: none has been described before age 8). Women with MEN2 are screened before a planned pregnancy.
- If a pheochromocytoma is found, it comes out first, before thyroid or parathyroid surgery (ATA), after an alpha-blocker (phenoxybenzamine or doxazosin) with salt and fluids, then a beta-blocker (StatPearls). Never give a beta-blocker alone: GeneReviews lists beta-blockers and D2 antagonists such as metoclopramide as high-risk drugs. Cortical-sparing adrenalectomy can avoid lifelong steroids when both glands are involved, at some risk of recurrence. More in the pheochromocytoma mnemonic.
- Check calcium (and PTH) for MEN2A hyperparathyroidism, which can be treated at the same operation.
- Thyroid surgery: total thyroidectomy with central (level VI) neck dissection when ultrasound shows no nodal or distant disease, plus dissection of any involved lateral compartments (ATA). C cells do not concentrate iodine, so radioiodine has no role and levothyroxine is replacement only, not TSH suppression (StatPearls).
- Follow the markers. Check calcitonin and CEA 3 months after surgery; a calcitonin above 150 pg/mL prompts imaging for distant disease. In one study, a calcitonin doubling time under 6 months carried a 5-year survival of 25%, versus 92% at 6-24 months (ATA). A rising CEA with flat or falling calcitonin suggests poorly differentiated MTC. For advanced RET-mutant MTC, the selective RET inhibitor selpercatinib is approved from age 2 (FDA label), alongside vandetanib and cabozantinib.
Prophylactic thyroidectomy by ATA RET risk category
The 2015 revised ATA guideline groups RET variants by how early and aggressively MTC develops, and the group sets the timing. GeneReviews (2023) and StatPearls (2026) still use these categories; the ATA's 2025 guideline covers differentiated thyroid cancer, not MTC.
| ATA category | Variants | Thyroidectomy | Yearly exam, ultrasound and calcitonin from | Pheochromocytoma screening from | Parathyroid screening from |
|---|---|---|---|---|---|
| Highest (HST) | M918T (MEN2B) | In the first year of life, perhaps in the first months | Calcitonin is of little help in infancy (normally very high) | Age 11 | Not needed |
| High (H) | Any codon 634 variant; A883F | At age 5, or earlier if calcitonin rises | Age 3 | Age 11 | Age 11 (MEN2A) |
| Moderate (MOD) | All others (for example 609, 611, 618, 620, 630, 768, 790, 804) | When calcitonin rises; parents may choose surgery around age 5 instead of years of checks | Age 5 | Age 16 | Age 16 |
- Why so early in MEN2B: in one series, all 9 children operated on before age 4 were cured biochemically, versus 1 of 35 operated on after age 5 (ATA).
- Neck dissection: in ATA-high children it is added when calcitonin is above 40 pg/mL or nodes are seen; with a preoperative calcitonin under 40 pg/mL, thyroidectomy alone is adequate.
Genetic testing and family screening
All are autosomal dominant: each child of a carrier has a 50% risk, and once the family variant is known, relatives can be tested; prenatal and preimplantation testing are possible (GeneReviews).
- Who gets RET testing (ATA): every patient with MTC, first-degree relatives in hereditary MTC families, parents of a baby or child with MEN2B features, patients with cutaneous lichen amyloidosis, and children with Hirschsprung disease who carry an exon 10 variant. StatPearls adds every pheochromocytoma and paraganglioma (a gene panel can reveal MEN2 before MTC).
- When children are tested: as soon as possible after birth in MEN2B families, and by age 5 at the latest in MEN2A and familial MTC families (GeneReviews), earlier in codon 634 families, whose checks start at 3; MTC has been found at 12 months.
- MEN1: first-degree relatives should be offered testing at the earliest opportunity, because tumors can appear by age 5 (Thakker 2012). The 2025 international MEN1 guideline (Brandi et al.) also suggests testing patients with primary hyperparathyroidism before 30 or multigland disease, and recommends it for anyone with a gastrinoma or multiple pancreatic NETs.
- Surveillance: MEN1 carriers are screened for life from childhood (calcium and PTH, prolactin and IGF-1, fasting glucose and insulin, pituitary and pancreatic imaging, gastrin from adulthood; GeneReviews); the 2025 guideline found no consensus on a start age and suggests considering age 10. MEN2 carriers follow the ATA ages above.
- Negative test, typical picture: some patients who meet clinical MEN1 criteria have no detectable MEN1 variant (5-10% in Endotext, more in simplex cases per GeneReviews); CDKN1B (MEN4) is one alternative cause.
USMLE traps
| Trap | What is actually true |
|---|---|
| "Hypercalcemia fits any MEN2" | Only MEN2A (20-30%); MEN2B has no hyperparathyroidism |
| "Calcitonin lowers calcium, so MTC causes hypocalcemia" | Calcitonin has only a minor role in human calcium balance (Mayo Clinic Laboratories), and most patients with MTC and high calcitonin are normocalcemic (Deftos 1974). Hypercalcemia in MEN2 usually means parathyroid disease |
| "MTC is the cancer, so operate on the thyroid first" | Exclude, and remove, a pheochromocytoma first |
| "Start a beta-blocker for the palpitations" | Alpha-blocker first; beta-blocker only after alpha blockade |
| "The MEN1 gastrinoma is a pancreatic mass to resect" | Usually multiple, small and duodenal; PPIs, and parathyroidectomy to lower acid output |
| "MEN1 hyperparathyroidism is a single adenoma" | Multigland disease; subtotal or total parathyroidectomy, and recurrence is common (MEN4 and CDC73 disease usually do have single adenomas) |
| "RET is a tumor suppressor, like menin" | Proto-oncogene with gain-of-function variants; loss-of-function RET causes Hirschsprung disease |
| "No family history, so not MEN2B" | Half to three-quarters of MEN2B cases are de novo |
| "Constipation in MEN2B is Hirschsprung disease" | Ganglioneuromatosis; Hirschsprung disease goes with MEN2A exon 10 variants |
| "Hypercalcemia plus a jaw tumor is MEN1" | Hyperparathyroidism-jaw tumor syndrome (CDC73): ossifying fibromas, parathyroid carcinoma in at least 10-15% |
Three practice vignettes
Vignette 1: the family with "pancreatic tumors." A 34-year-old man has recurrent kidney stones, constipation and fatigue. Serum calcium is 11.6 mg/dL, PTH is elevated and phosphate is low. His father had "pancreatic tumors" and his sister has a "pituitary mass." Which additional finding is most likely?
A. Medullary thyroid carcinoma. B. Pheochromocytoma. C. A duodenal gastrinoma or another pancreaticoduodenal NET. D. Mucosal neuromas. E. Ossifying fibroma of the jaw.
Answer: C. PTH-dependent hypercalcemia plus relatives with pancreatic and pituitary tumors completes the 3 P's of MEN1; gastrinomas affect about 40% and nonfunctioning NETs about 55%. A and B belong to MEN2. D marks MEN2B, which lacks hyperparathyroidism. E suggests CDC73 disease. Hypercalcemia of malignancy would suppress PTH.
Vignette 2: the teenager with bumpy lips. A 13-year-old girl has a firm 2-cm thyroid nodule. She has thick, nodular lips, small bumps on her tongue, long thin limbs and lifelong constipation; her parents are healthy. Calcitonin is markedly elevated and serum calcium is normal. Fine-needle aspiration shows medullary carcinoma. What is the next step?
A. Total thyroidectomy with central neck dissection now. B. Radioactive iodine uptake scan. C. Plasma free metanephrines. D. Propranolol, then surgery. E. Sestamibi scan for a parathyroid adenoma.
Answer: C. This is MEN2B, probably a de novo RET M918T variant. About half of patients develop pheochromocytoma, and an undiagnosed one can cause a fatal hypertensive crisis during surgery, so metanephrines come before any operation. A is the right operation, but only after pheochromocytoma is excluded or removed. B: MTC does not take up iodine. D: never a beta-blocker without prior alpha blockade. E: MEN2B does not cause hyperparathyroidism. Her parents should still be examined and offered testing.
Vignette 3: the carrier toddler. A 3-year-old boy is tested because his mother has MEN2A with a RET C634R variant, and he carries it. He is well, his neck ultrasound is normal and his calcitonin is within the reference range for his age. What is the recommended plan?
A. Thyroidectomy now, as for M918T. B. Yearly exam, neck ultrasound and calcitonin, with thyroidectomy at age 5 or earlier if calcitonin rises. C. Watch until a nodule is palpable. D. Begin yearly pheochromocytoma screening now.
Answer: B. Codon 634 is ATA high risk: yearly checks from age 3 and thyroidectomy at age 5, sooner if calcitonin climbs, with a central neck dissection if calcitonin exceeds 40 pg/mL. A is the M918T rule. C waits for MTC to spread. D: routine pheochromocytoma screening starts at 11 for ATA-high carriers. More practice is on the Endocrinology hub.
Key takeaways
- MEN2A vs MEN2B: both are RET gain of function with MTC and pheochromocytoma; MEN2A adds hyperparathyroidism (20-30%), and MEN2B adds mucosal neuromas, a marfanoid habitus and ganglioneuromatosis, with no hyperparathyroidism.
- MEN1 = 3 P's (parathyroid, pituitary, pancreas and duodenum): menin tumor suppressor on 11q13; hyperparathyroidism usually first; gastrinomas small, multiple and duodenal.
- Before any MEN2 operation: metanephrines; remove a pheochromocytoma first, with an alpha-blocker before any beta-blocker.
- Thyroidectomy by ATA risk: M918T in the first year of life; codon 634 or A883F at or before age 5; moderate risk when calcitonin rises.
- Test the family: RET testing for every MTC and soon after birth in MEN2B families; early MEN1 testing for relatives; CDKN1B (MEN4) when an MEN1-like patient tests negative.
Sources
- Multiple Endocrine Neoplasia Type 2 — GeneReviews, NCBI Bookshelf (2023)
- Multiple Endocrine Neoplasia Type 1 — GeneReviews, NCBI Bookshelf (2022)
- Multiple Endocrine Neoplasia Type 4 — GeneReviews, NCBI Bookshelf (2023)
- CDC73-Related Disorders — GeneReviews, NCBI Bookshelf (2023)
- Wells SA Jr, et al. Revised American Thyroid Association Guidelines for the Management of Medullary Thyroid Carcinoma — Thyroid (2015)
- Ringel MD, et al. 2025 American Thyroid Association Management Guidelines for Adult Patients with Differentiated Thyroid Cancer — Thyroid (2025)
- Thakker RV, et al. Clinical Practice Guidelines for Multiple Endocrine Neoplasia Type 1 (MEN1) — J Clin Endocrinol Metab (2012)
- Brandi ML, et al. Multiple Endocrine Neoplasia Type 1 (MEN1): Recommendations and Guidelines for Best Practice — Lancet Diabetes Endocrinol (2025)
- Multiple Endocrine Neoplasia Type I — Endotext, NCBI Bookshelf (2026)
- Multiple Endocrine Neoplasia Type 2 — Endotext, NCBI Bookshelf (2022)
- Multiple Endocrine Neoplasia Type 2 — StatPearls, NCBI Bookshelf (2026)
- Multiple Endocrine Neoplasia Type 4 — StatPearls, NCBI Bookshelf (2026)
- Gastrinoma — StatPearls, NCBI Bookshelf (2025)
- Hypercalcemia — StatPearls, NCBI Bookshelf (2024)
- Retevmo (Selpercatinib) Prescribing Information — DailyMed, NLM (2026)
- Deftos LJ, Parthemore JG. Secretion of Parathyroid Hormone in Patients with Medullary Thyroid Carcinoma — J Clin Invest (1974)
- Calcitonin, Serum — Mayo Clinic Laboratories
- Johansson E, et al. Revising the Embryonic Origin of Thyroid C Cells in Mice and Humans — Development (2015)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
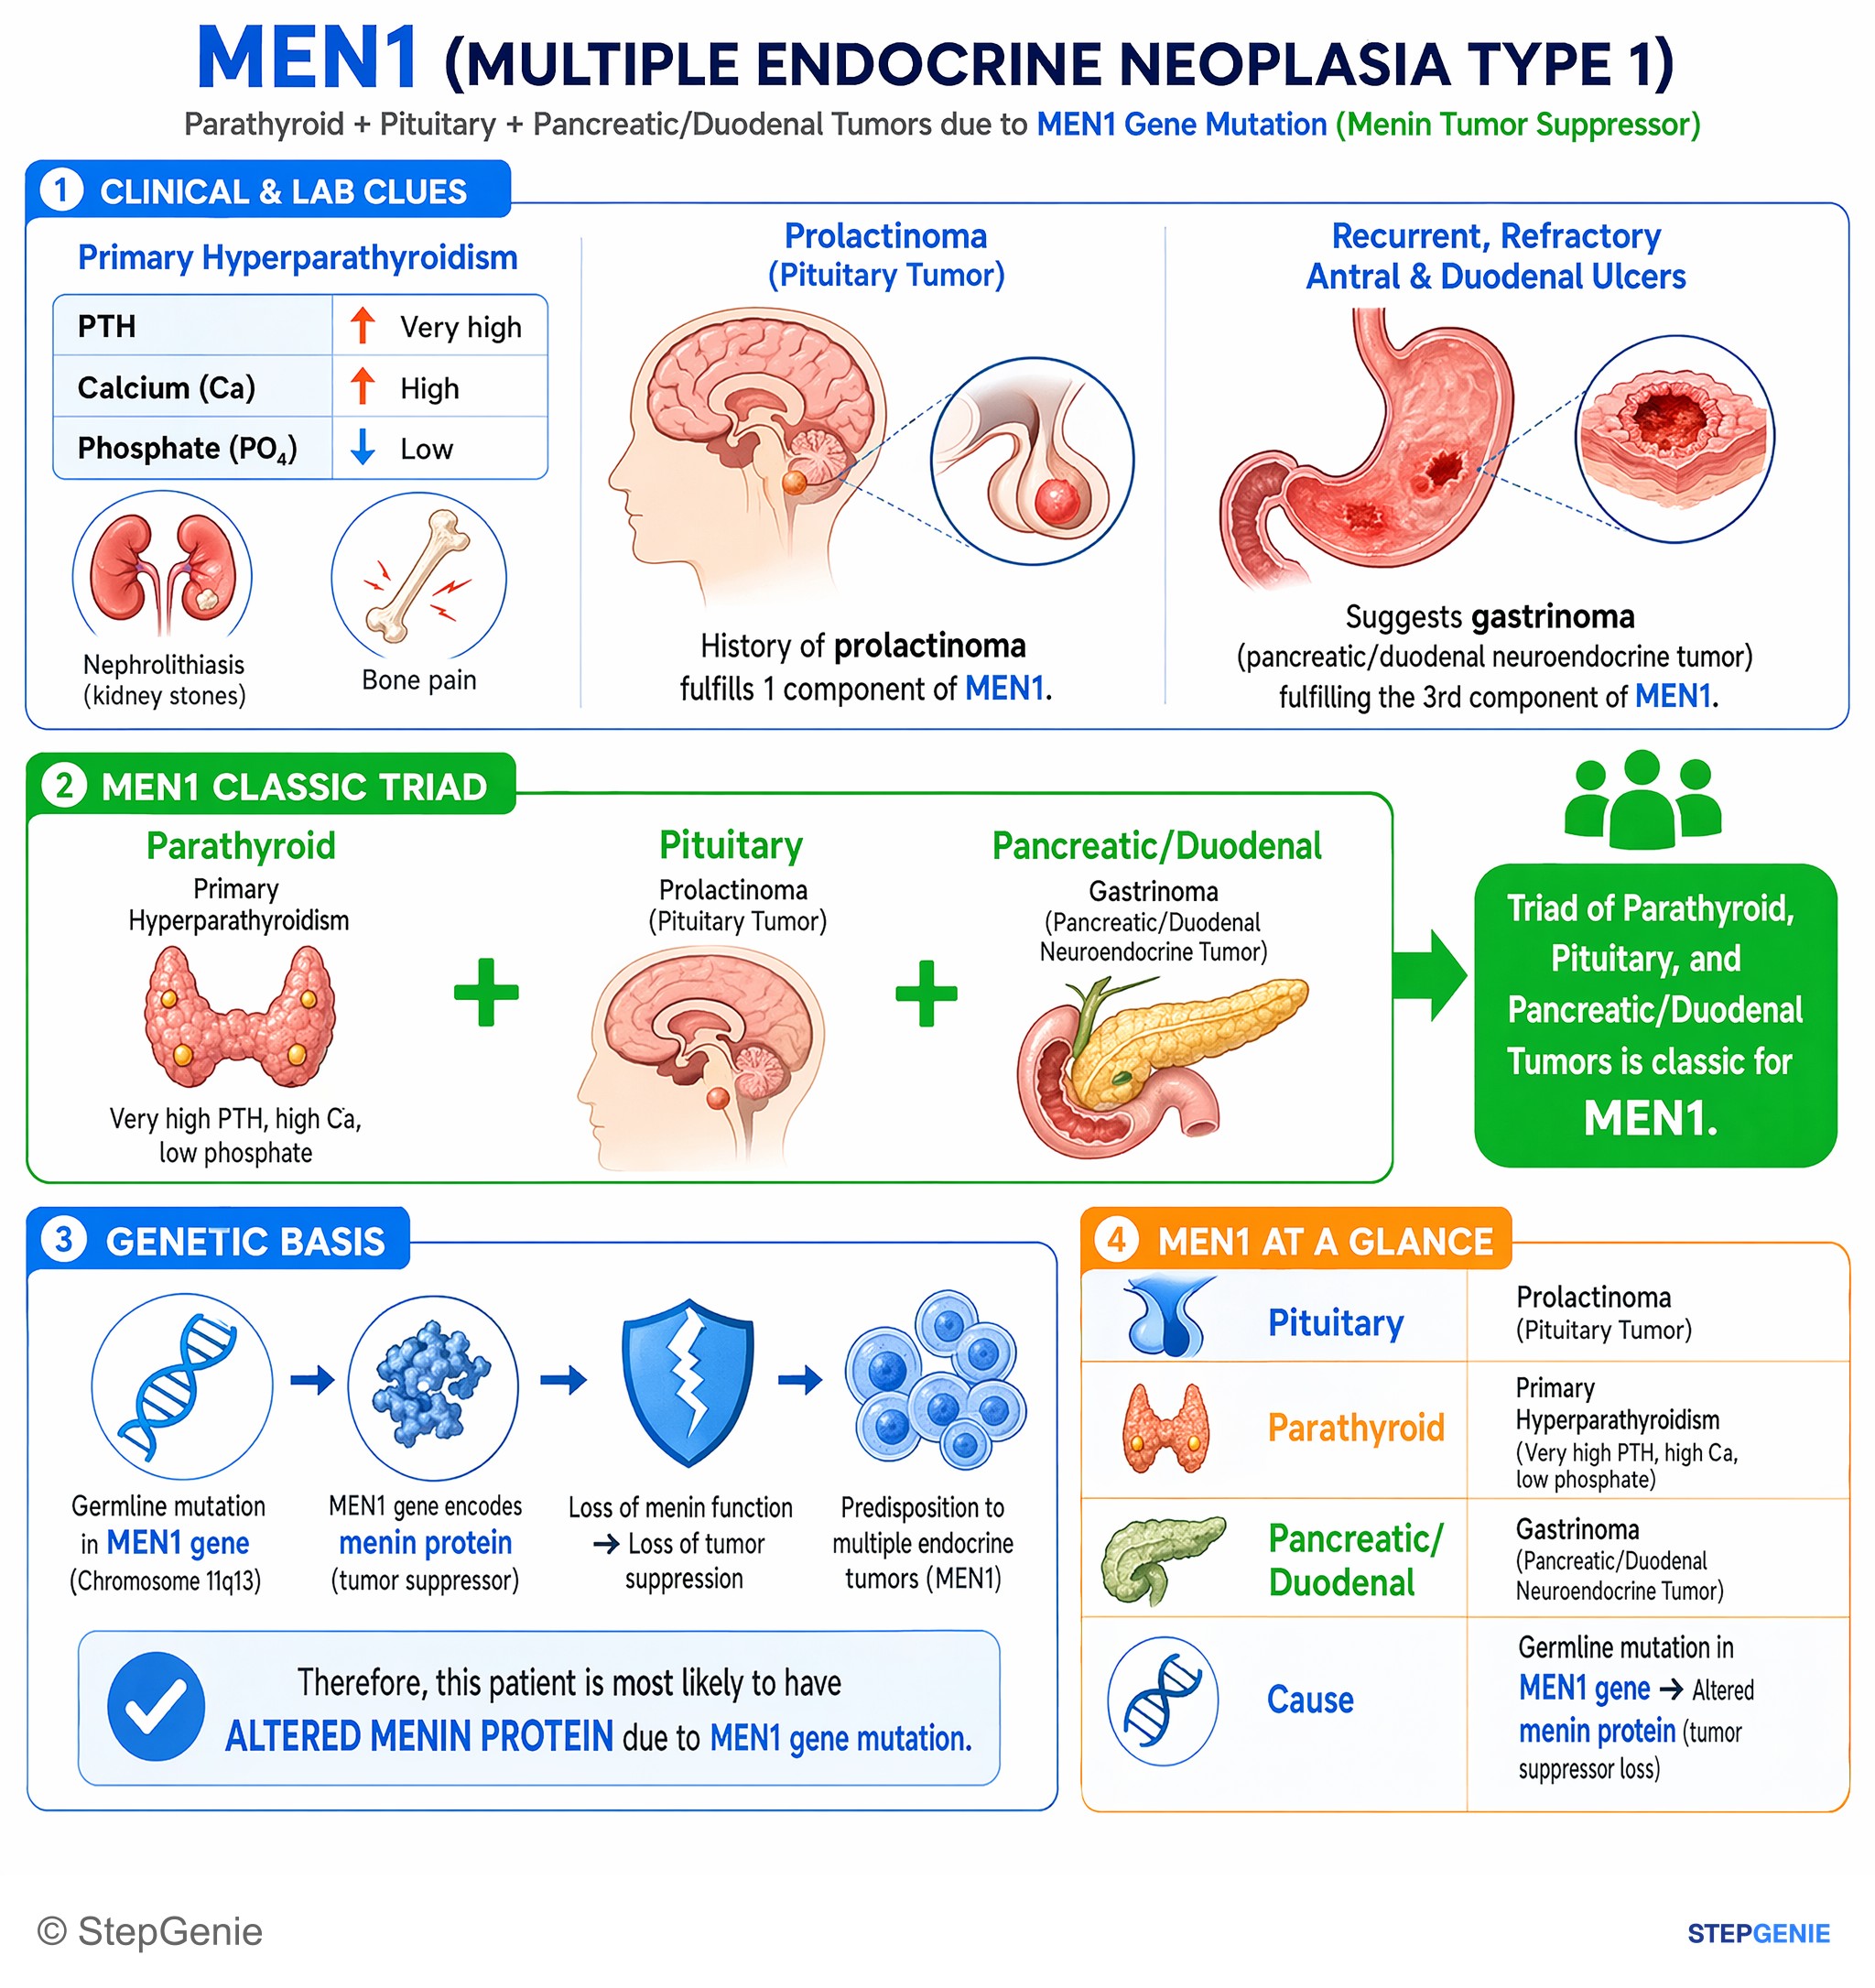
MEN1: pituitary (prolactinoma) + parathyroid (primary hyperparathyroidism) + pancreatic/duodenal tumors; due to menin tumor suppressor…
USMLE Step 1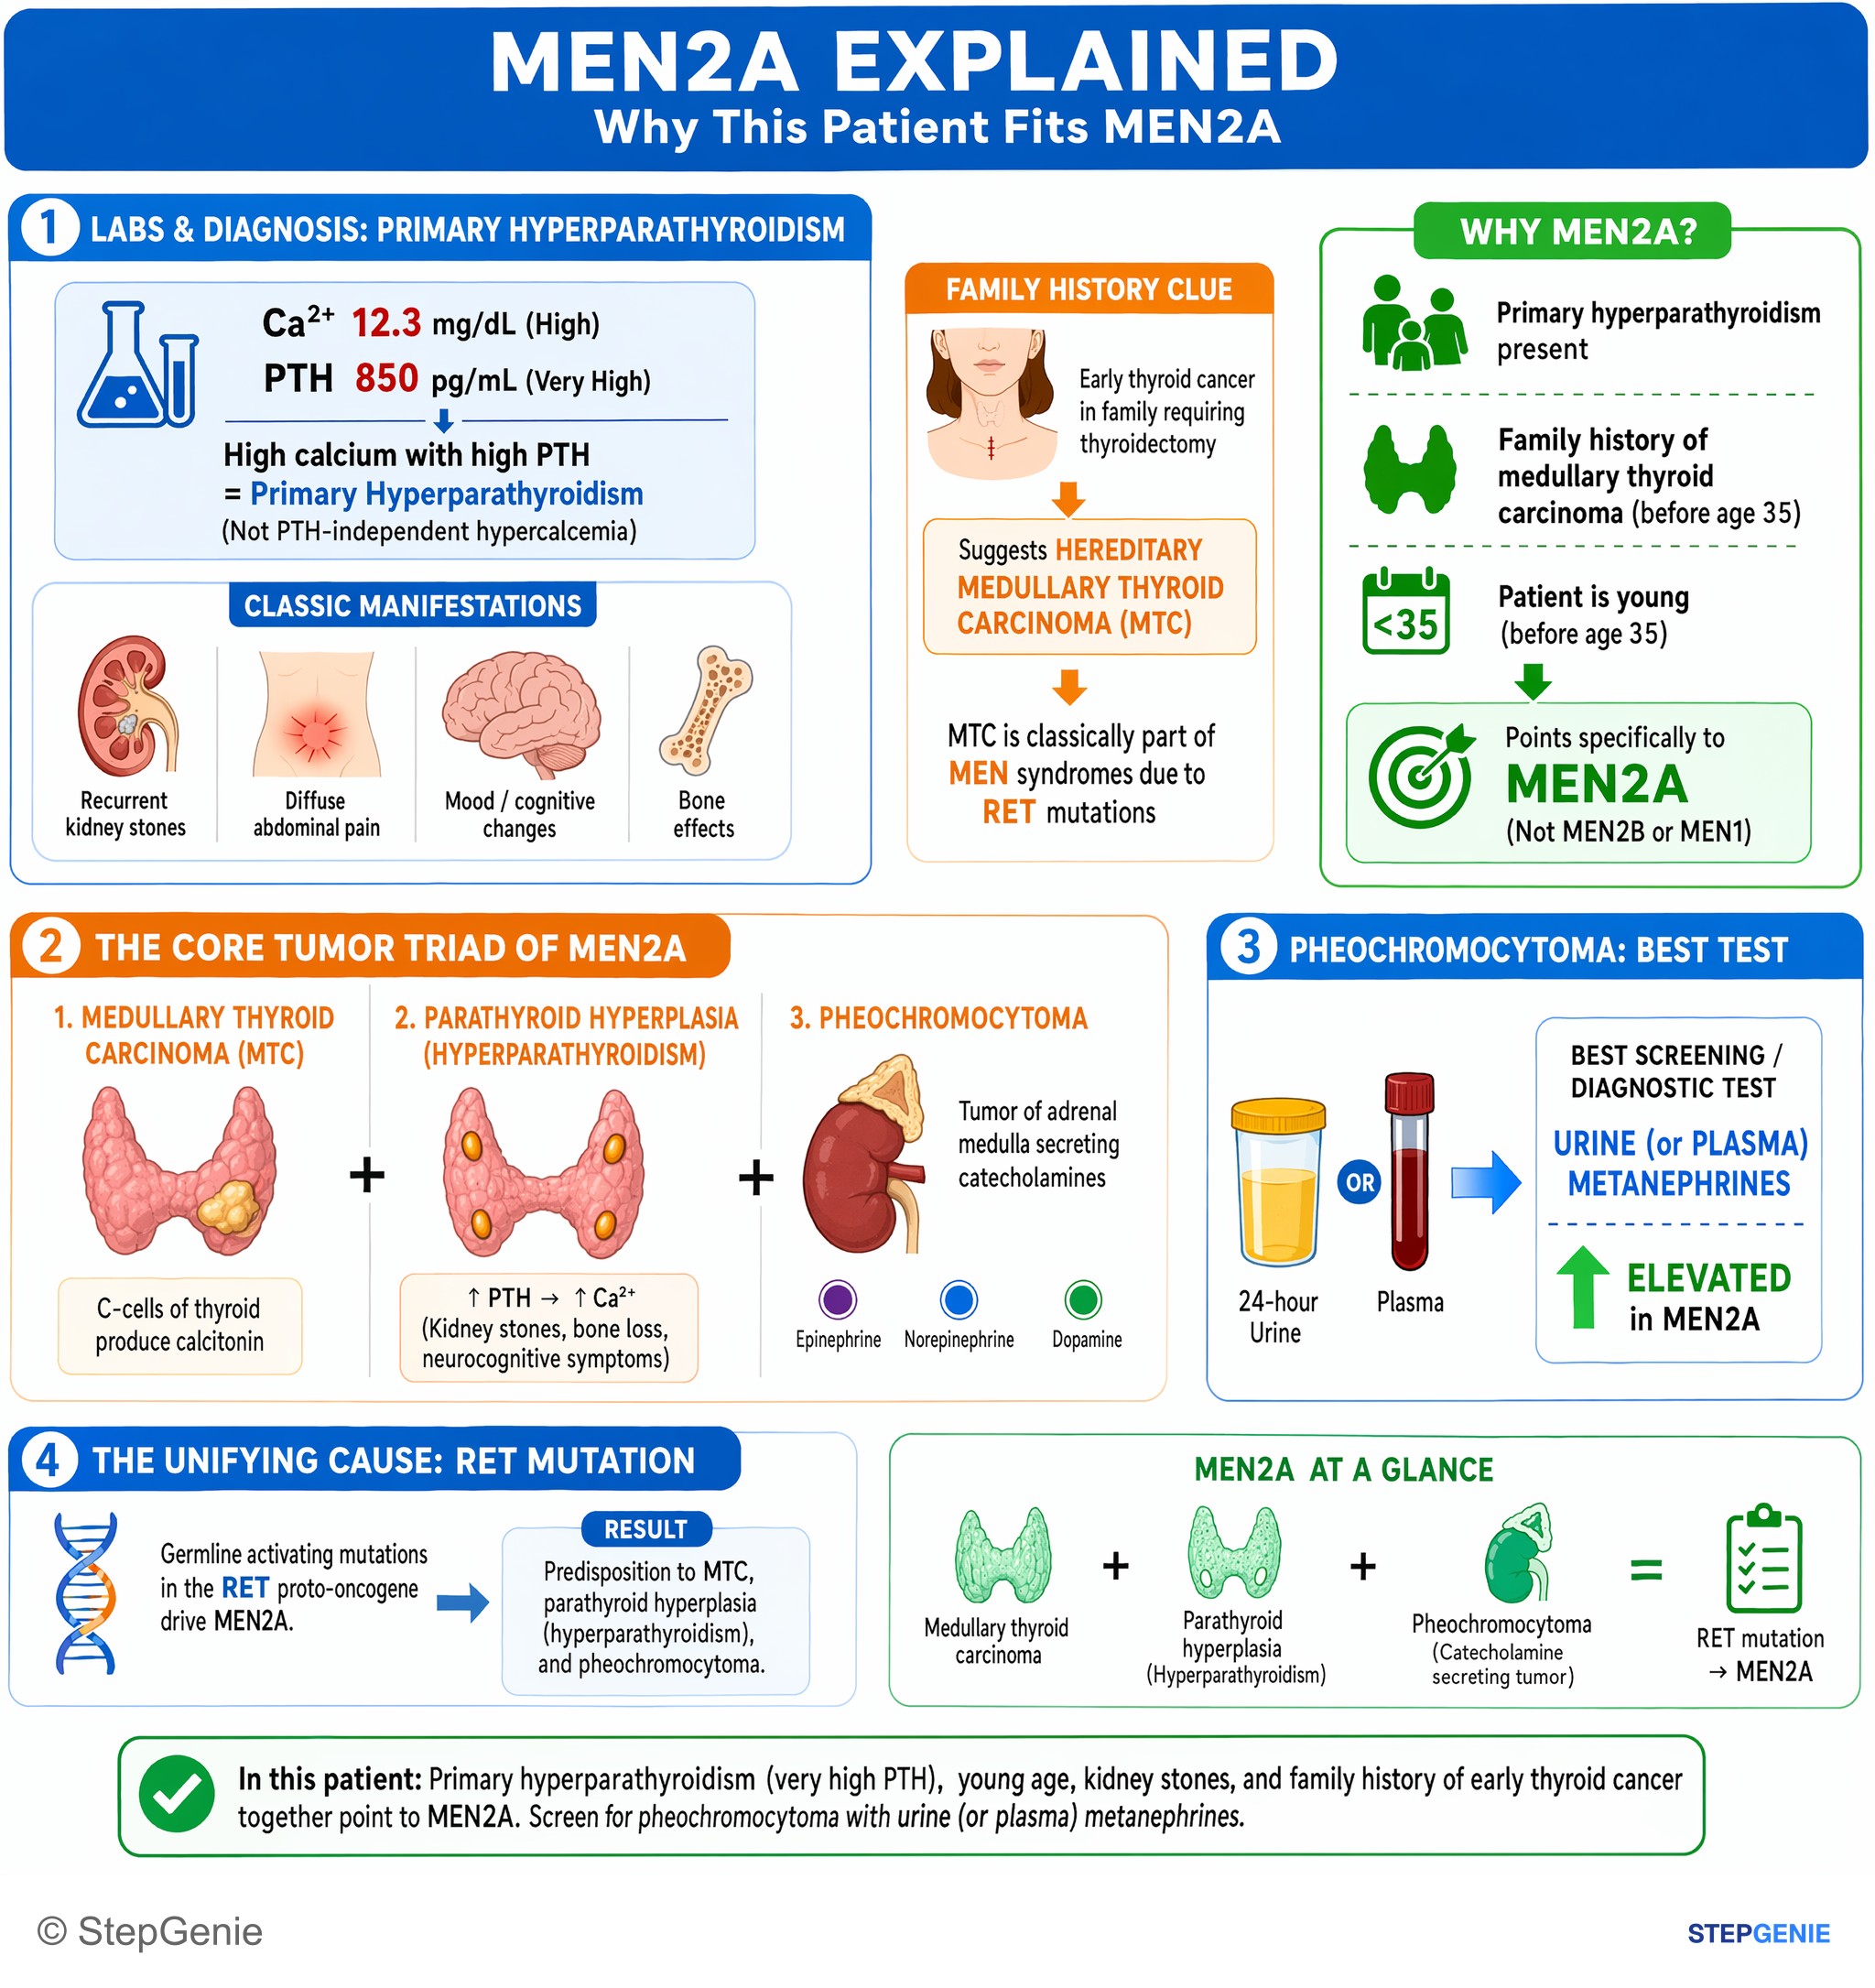
MEN2A: RET mutation → medullary thyroid carcinoma + hyperparathyroidism + pheochromocytoma → elevated urine metanephrines.
USMLE Step 1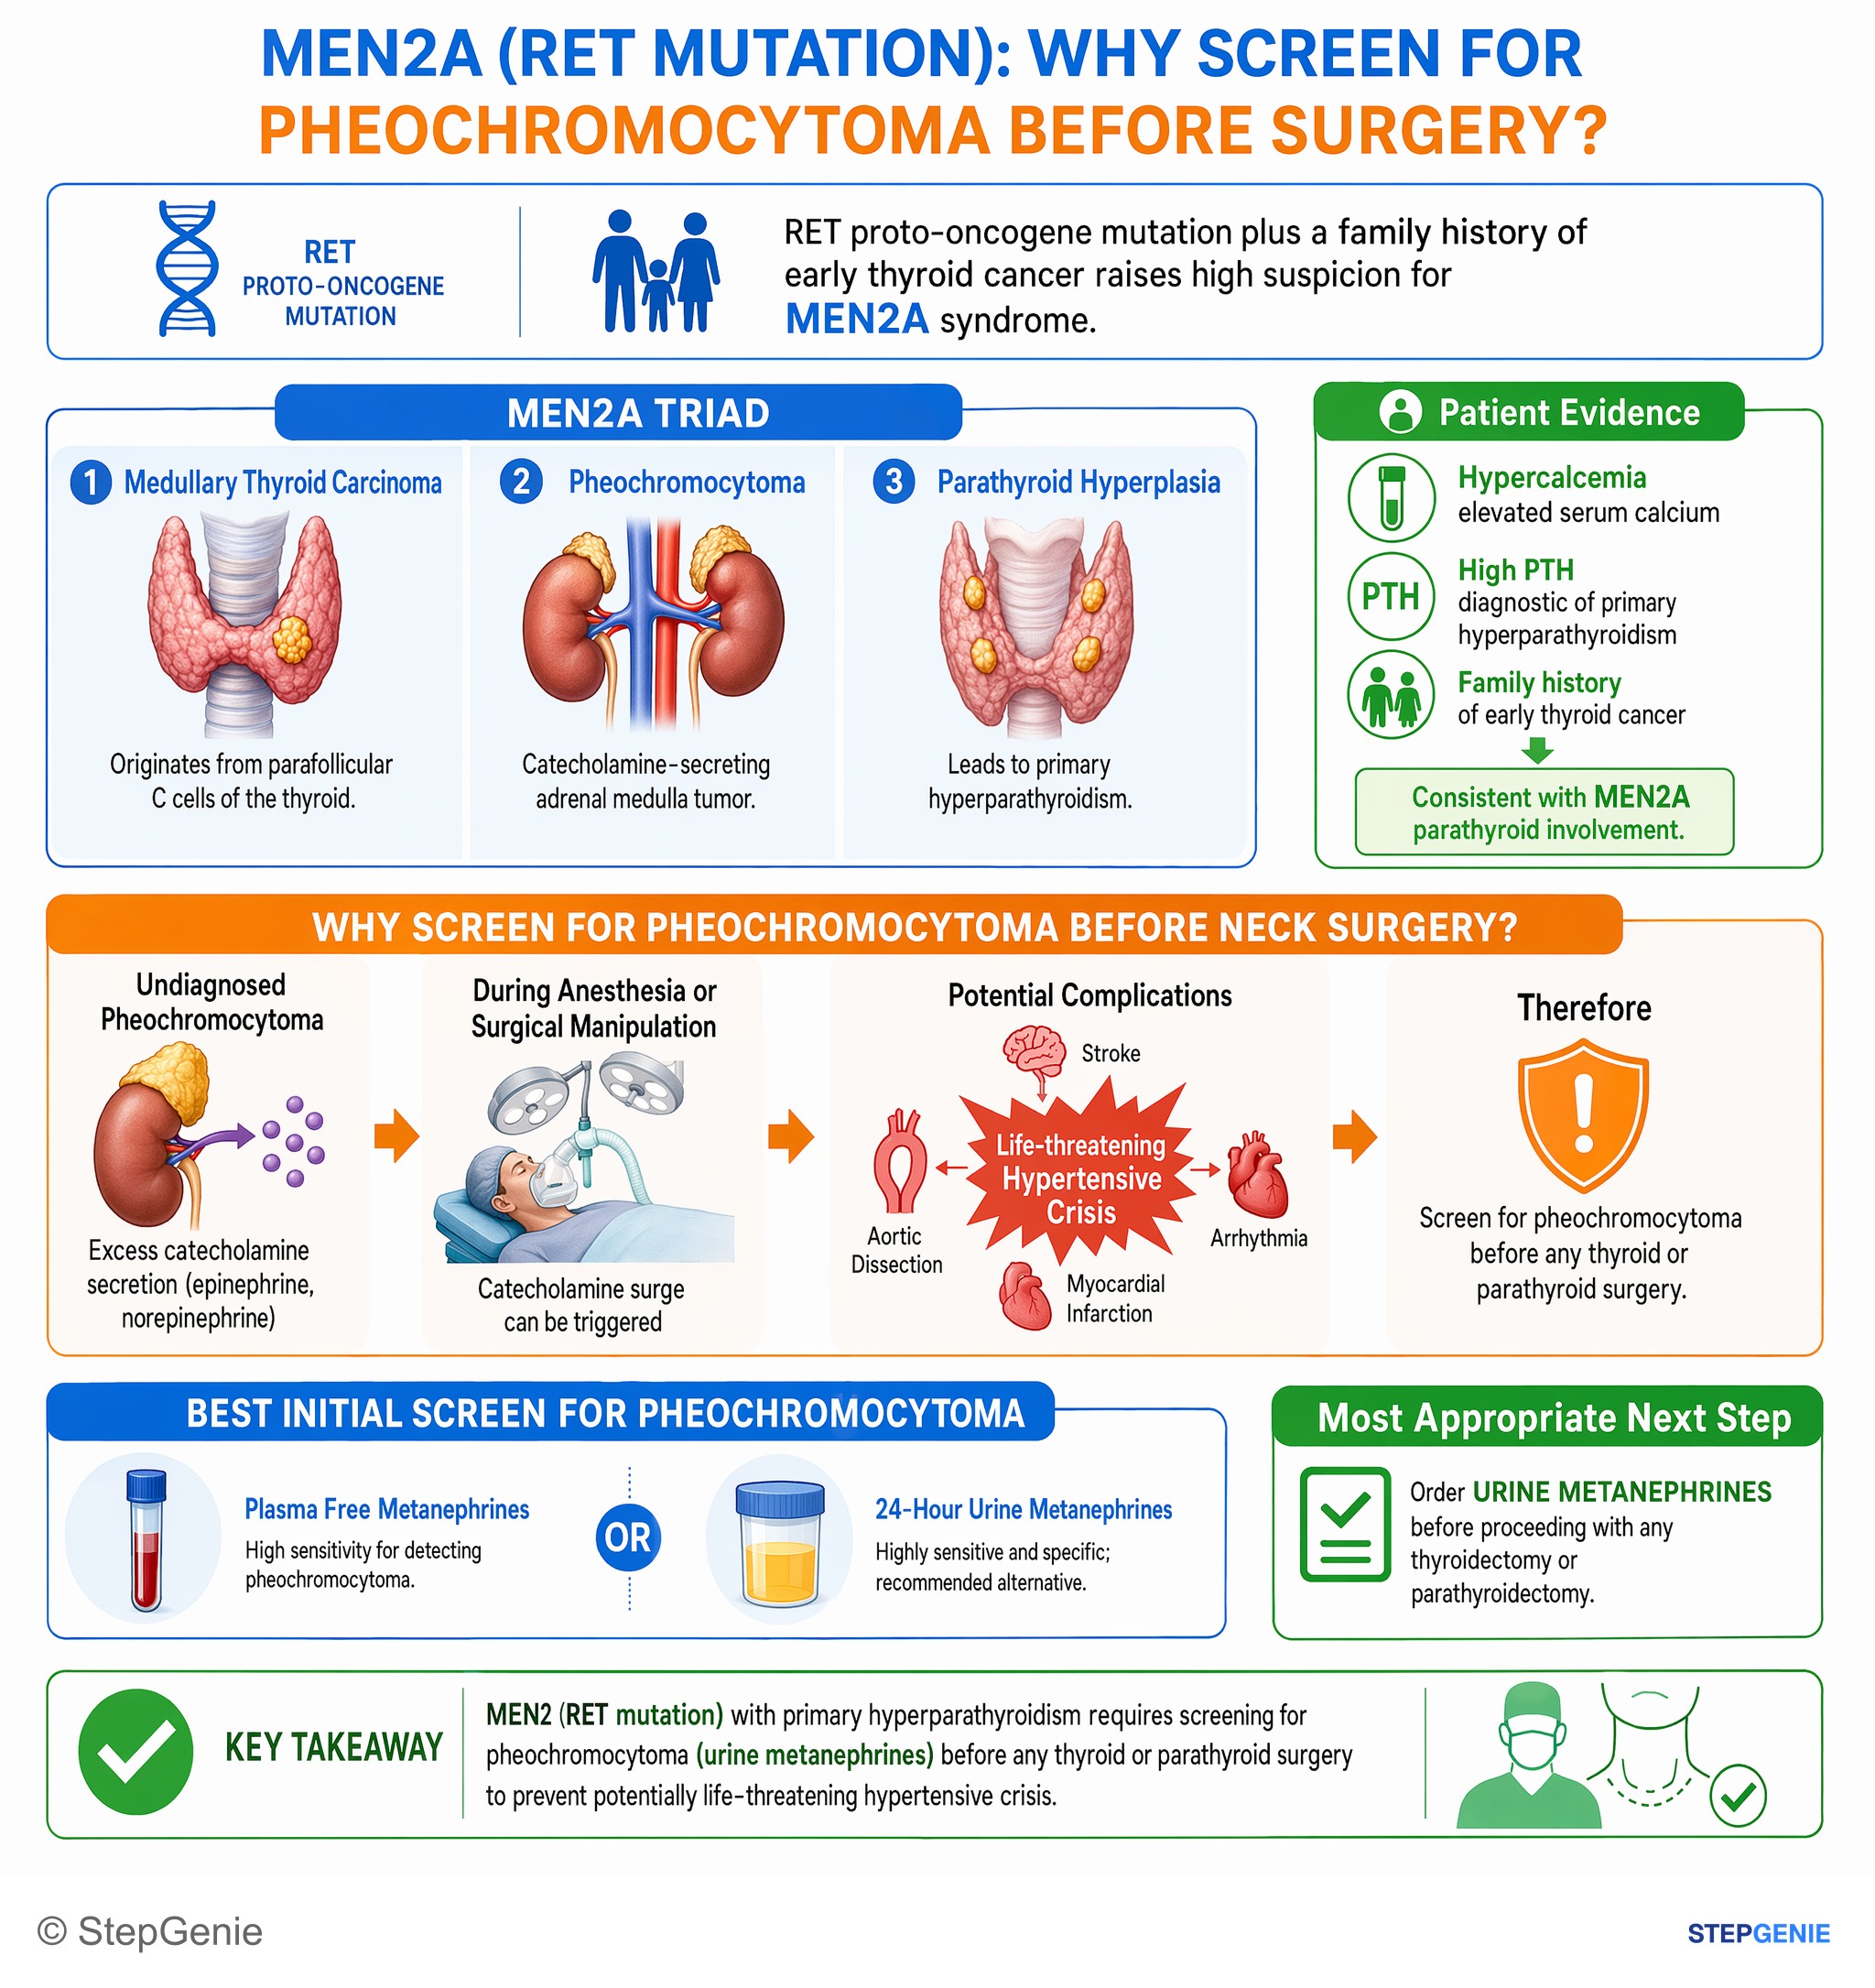
MEN2 (RET mutation) with primary hyperparathyroidism requires screening for pheochromocytoma (urine metanephrines) before any thyroid or…
USMLE Step 2Frequently Asked Questions
What is the difference between MEN1, MEN2A and MEN2B?
MEN1 is caused by loss of menin, a tumor suppressor, and produces the 3 P's: parathyroid hyperplasia, pituitary adenomas and pancreatic or duodenal neuroendocrine tumors such as gastrinomas. MEN2A and MEN2B are caused by activating RET mutations and share medullary thyroid carcinoma and pheochromocytoma. MEN2A adds primary hyperparathyroidism in 20 to 30%, while MEN2B adds mucosal neuromas, a marfanoid habitus and intestinal ganglioneuromatosis. All three are autosomal dominant.
What is the difference between MEN2A and MEN2B?
Both come from gain-of-function RET mutations, and both cause medullary thyroid carcinoma and, in about half of patients, pheochromocytoma. MEN2A, about 95% of MEN2, adds primary hyperparathyroidism in 20 to 30% and can include lichen amyloidosis or Hirschsprung disease. MEN2B, about 5%, is usually caused by RET M918T, almost never has hyperparathyroidism, and adds mucosal neuromas, a marfanoid habitus and intestinal ganglioneuromatosis, with the earliest and most aggressive thyroid cancer.
What is a mnemonic for MEN1, MEN2A and MEN2B?
Count the P's: 3, 2, 1. MEN1 has three P's: parathyroid, pituitary and pancreas. MEN2A has two P's, pheochromocytoma and parathyroid, plus medullary thyroid carcinoma. MEN2B has one P, pheochromocytoma, plus medullary thyroid carcinoma, mucosal neuromas and a marfanoid habitus. The P that drops out in MEN2B is the parathyroid, which is why hypercalcemia points to MEN1 or MEN2A but not to MEN2B.
Which MEN syndrome does not cause hypercalcemia?
MEN2B. Hyperparathyroidism occurs in under 1% of people with MEN2B, compared with 20 to 30% in MEN2A and nearly everyone with MEN1 by age 50. Medullary thyroid carcinoma secretes calcitonin, but calcitonin has only a minor role in human calcium balance, and most patients with very high levels keep a normal calcium. Hypercalcemia in a patient with MEN2 therefore usually points to parathyroid disease, and so to MEN2A.
When is prophylactic thyroidectomy done in MEN2?
The timing follows the RET risk category in the 2015 American Thyroid Association guideline. Children with the highest-risk M918T variant, the usual cause of MEN2B, should have thyroidectomy in the first year of life. Those with high-risk codon 634 or A883F variants should have it at age 5, or earlier if calcitonin rises. Moderate-risk carriers start yearly calcitonin and ultrasound around age 5 and have surgery when calcitonin rises.
Why must pheochromocytoma be ruled out before thyroid surgery in MEN2?
About half of people with MEN2A or MEN2B develop pheochromocytoma, often in both adrenal glands, and an undiagnosed tumor can cause a fatal hypertensive crisis during anesthesia. Plasma free or 24-hour urine fractionated metanephrines are therefore checked before any operation. If a pheochromocytoma is found, it is removed first, after an alpha-blocker such as phenoxybenzamine or doxazosin followed by a beta-blocker, and the thyroid or parathyroid surgery comes afterward.