Sigmoid volvulus is the classic USMLE volvulus: an elderly, often institutionalized patient with chronic constipation develops abdominal pain, massive distension and obstipation, and the plain film shows a "coffee bean" loop projecting toward the upper abdomen (a bird's beak on contrast enema, a whirl sign on CT). With no peritonitis, ischemia or perforation, the first step is endoscopic detorsion and decompression (ASCRS 2021), followed by sigmoid colectomy, ideally during the same admission (WSES 2023). Cecal volvulus is treated by resection, not endoscopy, and midgut volvulus is a neonatal emergency that announces itself with bilious vomiting and is fixed with the Ladd procedure.
The Q-bank vignette
A 78-year-old man who lives in a nursing facility and has long-standing constipation and Parkinson disease develops abdominal pain and progressive distension. He has passed no stool or flatus for 36 hours and vomited once. Temperature is 37.4°C (99.3°F), pulse 96/min and blood pressure 138/82 mm Hg. The abdomen is tense, tympanitic and mildly tender without guarding or rebound; the rectum is empty. Lactate is normal. An abdominal radiograph shows a massively dilated loop of colon rising out of the pelvis in a "coffee bean" shape that points to the upper abdomen.
Most likely diagnosis and next step? Sigmoid volvulus. He has no peritonitis, instability or signs of perforation, so the next step is flexible endoscopic detorsion and decompression, leaving a decompression tube in place, then sigmoid colectomy during the same admission.
Why it's sigmoid volvulus
- Mechanism: a long, redundant sigmoid colon on a narrow mesenteric base twists on itself. Twisting beyond 180° can cause a closed-loop obstruction; venous outflow is blocked first, then arterial inflow, leading to ischemia, gangrene and perforation. In large-bowel obstruction, strangulation is rare except with volvulus.
- Who gets it: in Western countries, mainly men older than 70, especially those with neuropsychiatric disease leading to reduced autonomy, institutional care or prolonged bed rest, chronic constipation or frequent laxative use. In the endemic "volvulus belt" (which includes Africa, South America, Russia, Eastern Europe, the Middle East and India), patients are younger men, and a high-fiber diet is among the listed risk factors. In younger patients, megacolon from Hirschsprung disease or Chagas disease can also predispose.
- How it presents: abrupt, continuous pain (sometimes with colicky waves), marked distension and obstipation, with vomiting as a late sign and often an empty rectum.
- Numbers to know: the sigmoid accounts for 60–75% of colonic volvulus, the cecum 25–40% and the transverse colon 1–4%.
Sigmoid vs cecal vs midgut volvulus
| Feature | Sigmoid volvulus | Cecal volvulus | Midgut volvulus (malrotation) |
|---|---|---|---|
| Typical patient | Elderly man, institutionalized, chronically constipated | Somewhat younger woman (60 or younger) | Neonate: about 40% of patients with malrotation present in the first month of life and more than 80% by age 5 |
| What twists | Redundant sigmoid on a narrow mesentery | Cecum around its mesentery | Small bowel on a narrow, stalk-like mesentery after incomplete rotation |
| Lead symptom | Pain, massive distension, obstipation | Pain and distension (obstruction) | Bilious vomiting in an infant |
| Plain film | "Coffee bean" projecting toward the upper abdomen | Large gas-filled cecum in the mid-abdomen or left upper quadrant | Dilated stomach and proximal duodenum (double bubble) with little distal gas, when obstructed |
| Confirming study | CT whirl sign; bird's beak on contrast enema | CT; bird's beak on contrast enema | Upper GI series: duodenojejunal junction right of the spine; ultrasound whirlpool sign |
| Treatment | Endoscopic detorsion, then sigmoid colectomy; urgent resection if detorsion fails or the colon is nonviable or perforated | Segmental resection; endoscopic reduction not recommended | Emergency Ladd procedure |
Imaging signs that decide the question
- Coffee bean sign: the dilated sigmoid loop projects toward the upper abdomen, sometimes above the transverse colon (the "northern exposure" sign).
- Bird's beak: on contrast enema, the column of contrast tapers to a beak at the point of the twist, in both sigmoid and cecal volvulus. An enema can even reduce a sigmoid volvulus, but it is contraindicated if perforation is suspected.
- Whirl sign: on CT, the twisted colon and mesentery form a swirl. CT is used when the diagnosis is uncertain or ischemia or perforation is suspected; WSES reports a diagnostic yield of 89% for sigmoid volvulus.
- Midgut volvulus: an upper GI series is the preferred test for malrotation. On ultrasound, a reversed position of the mesenteric vessels suggests malrotation, and a whirlpool sign suggests volvulus.
Management (ASCRS 2021 and WSES 2023)
- Resuscitate: nasogastric suction, IV fluids, correction of electrolytes, and antibiotics if bowel ischemia is suspected.
- Sigmoid, stable, no peritonitis or perforation: lower endoscopy to assess colonic viability, detorse and decompress (strong recommendation, low-quality evidence). Detorsion works in 60–95% of patients; a decompression tube is left to maintain the reduction.
- Then resect: after successful decompression, sigmoid colectomy should be offered as early as possible, even during the index admission, because the recurrence rate after detorsion alone is 45–71%. Operations without resection (detorsion alone, sigmoidopexy, mesosigmoidoplasty) are inferior; endoscopic fixation is reserved for patients too high-risk for surgery.
- Urgent sigmoid resection: failed detorsion, nonviable or perforated colon, peritonitis or septic shock. Whether to form an anastomosis or an end colostomy (Hartmann procedure) is individualized.
- Cecal volvulus: endoscopic reduction is generally not recommended; segmental resection is preferred, and nonresectional procedures are limited to patients unfit for resection.
- Midgut volvulus: the Ladd procedure detorses the bowel, divides Ladd bands, widens the mesentery, places the small bowel on the right and the colon on the left, and removes the appendix.
Why every other answer choice is wrong
Cecal volvulus. Also a twisted colon with a bird's beak, but the patient is typically a younger woman, and the dilated cecum sits in the mid-abdomen or left upper quadrant. Colonoscopy rarely reduces it, so the answer is resection.
Small bowel obstruction (adhesions). Adhesions, hernias and tumors are the most common causes of mechanical obstruction. Small bowel obstruction causes periumbilical cramps and vomiting early, with high-pitched rushes and a ladder-like series of dilated small-bowel loops with air-fluid levels, rather than one giant colonic loop. Review it in the small bowel obstruction Q-bank breakdown.
Ogilvie syndrome (acute colonic pseudo-obstruction). Massive colonic dilation without a mechanical cause, so there is no twist, no whirl and no bird's beak. Treatment is supportive care (correct the predisposing conditions), then neostigmine with cardiac monitoring, then colonoscopic decompression if neostigmine fails or is contraindicated.
Obstructing colon cancer. Large-bowel obstruction from a tumor, usually in the left colon, develops more gradually, with increasing constipation before obstipation, and a mass may be palpable. Volvulus starts abruptly.
Acute mesenteric ischemia. Pain out of proportion to the examination in a patient with atrial fibrillation, heart failure or atherosclerosis. CT angiography or mesenteric angiography makes the diagnosis; lactate rises only late.
Worked example: the newborn version
Vignette. A 6-day-old boy born at term, who has been feeding well and passed meconium on day 1, suddenly vomits bright green fluid three times. He is fussy; the abdomen is soft and not distended. An abdominal radiograph shows a dilated stomach and proximal duodenum with little gas beyond. What is the most likely diagnosis?
Answer: Malrotation with midgut volvulus. Bilious vomiting in an infant is an emergency; after stabilization, an upper GI series (if the infant is stable enough) and an emergency Ladd procedure follow, because untreated volvulus can infarct the midgut and lead to short bowel syndrome or death.
Why the distractors fail:
- Hypertrophic pyloric stenosis: projectile nonbilious vomiting at 3–6 weeks in a hungry infant, sometimes with an olive-shaped mass and hypochloremic, hypokalemic metabolic alkalosis; diagnosed by ultrasound.
- Duodenal atresia: also a double bubble, but symptoms start in the first days of life, and it is often associated with Down syndrome.
- Hirschsprung disease: most affected newborns fail to pass meconium in the first 48 hours, with distension and obstipation; diagnosed by rectal biopsy. See the Hirschsprung disease overview.
- Intussusception: a different pediatric obstruction, compared in the intussusception Q-bank breakdown.
Exam traps
- Endoscopy is for the stable sigmoid only. Peritonitis, perforation or a nonviable colon means surgery now.
- Don't stop at detorsion: without resection, recurrence is common, so plan sigmoid colectomy during the same admission.
- Cecal volvulus is a surgical disease; endoscopic reduction is not recommended.
- Bilious vomiting in a newborn is malrotation with volvulus until proven otherwise, and it needs immediate evaluation.
- Pseudo-obstruction has no twist; treat with supportive care and neostigmine, not detorsion.
- Contrast enema is contraindicated when perforation is suspected.
Key takeaways
- Sigmoid volvulus: elderly, institutionalized, constipated; coffee bean sign, bird's beak, whirl sign; detorsion, then colectomy.
- Cecal volvulus: younger patients, dilated cecum in the mid-abdomen or left upper quadrant; resection.
- Midgut volvulus: neonate with bilious vomiting; upper GI series; Ladd procedure.
- Volvulus strangulates: it is the exception to the rule that large-bowel obstruction rarely compromises blood supply.
- Guidelines: ASCRS 2021 and WSES 2023 both endorse endoscopic detorsion first for uncomplicated sigmoid volvulus and resection to prevent recurrence.
Sources
- Tian BWCA, et al. WSES consensus guidelines on sigmoid volvulus management — World Journal of Emergency Surgery (2023)
- ASCRS Clinical Practice Guidelines for the Management of Colonic Volvulus and Acute Colonic Pseudo-Obstruction (2021) — Guideline Central summary
- Intestinal Obstruction — Merck Manual Professional Edition
- Malrotation of the Bowel — Merck Manual Professional Edition
- Ileus — Merck Manual Professional Edition
- Acute Mesenteric Ischemia — Merck Manual Professional Edition
- Hypertrophic Pyloric Stenosis — Merck Manual Professional Edition
- Duodenal Obstruction — Merck Manual Professional Edition
- Hirschsprung Disease — Merck Manual Professional Edition
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
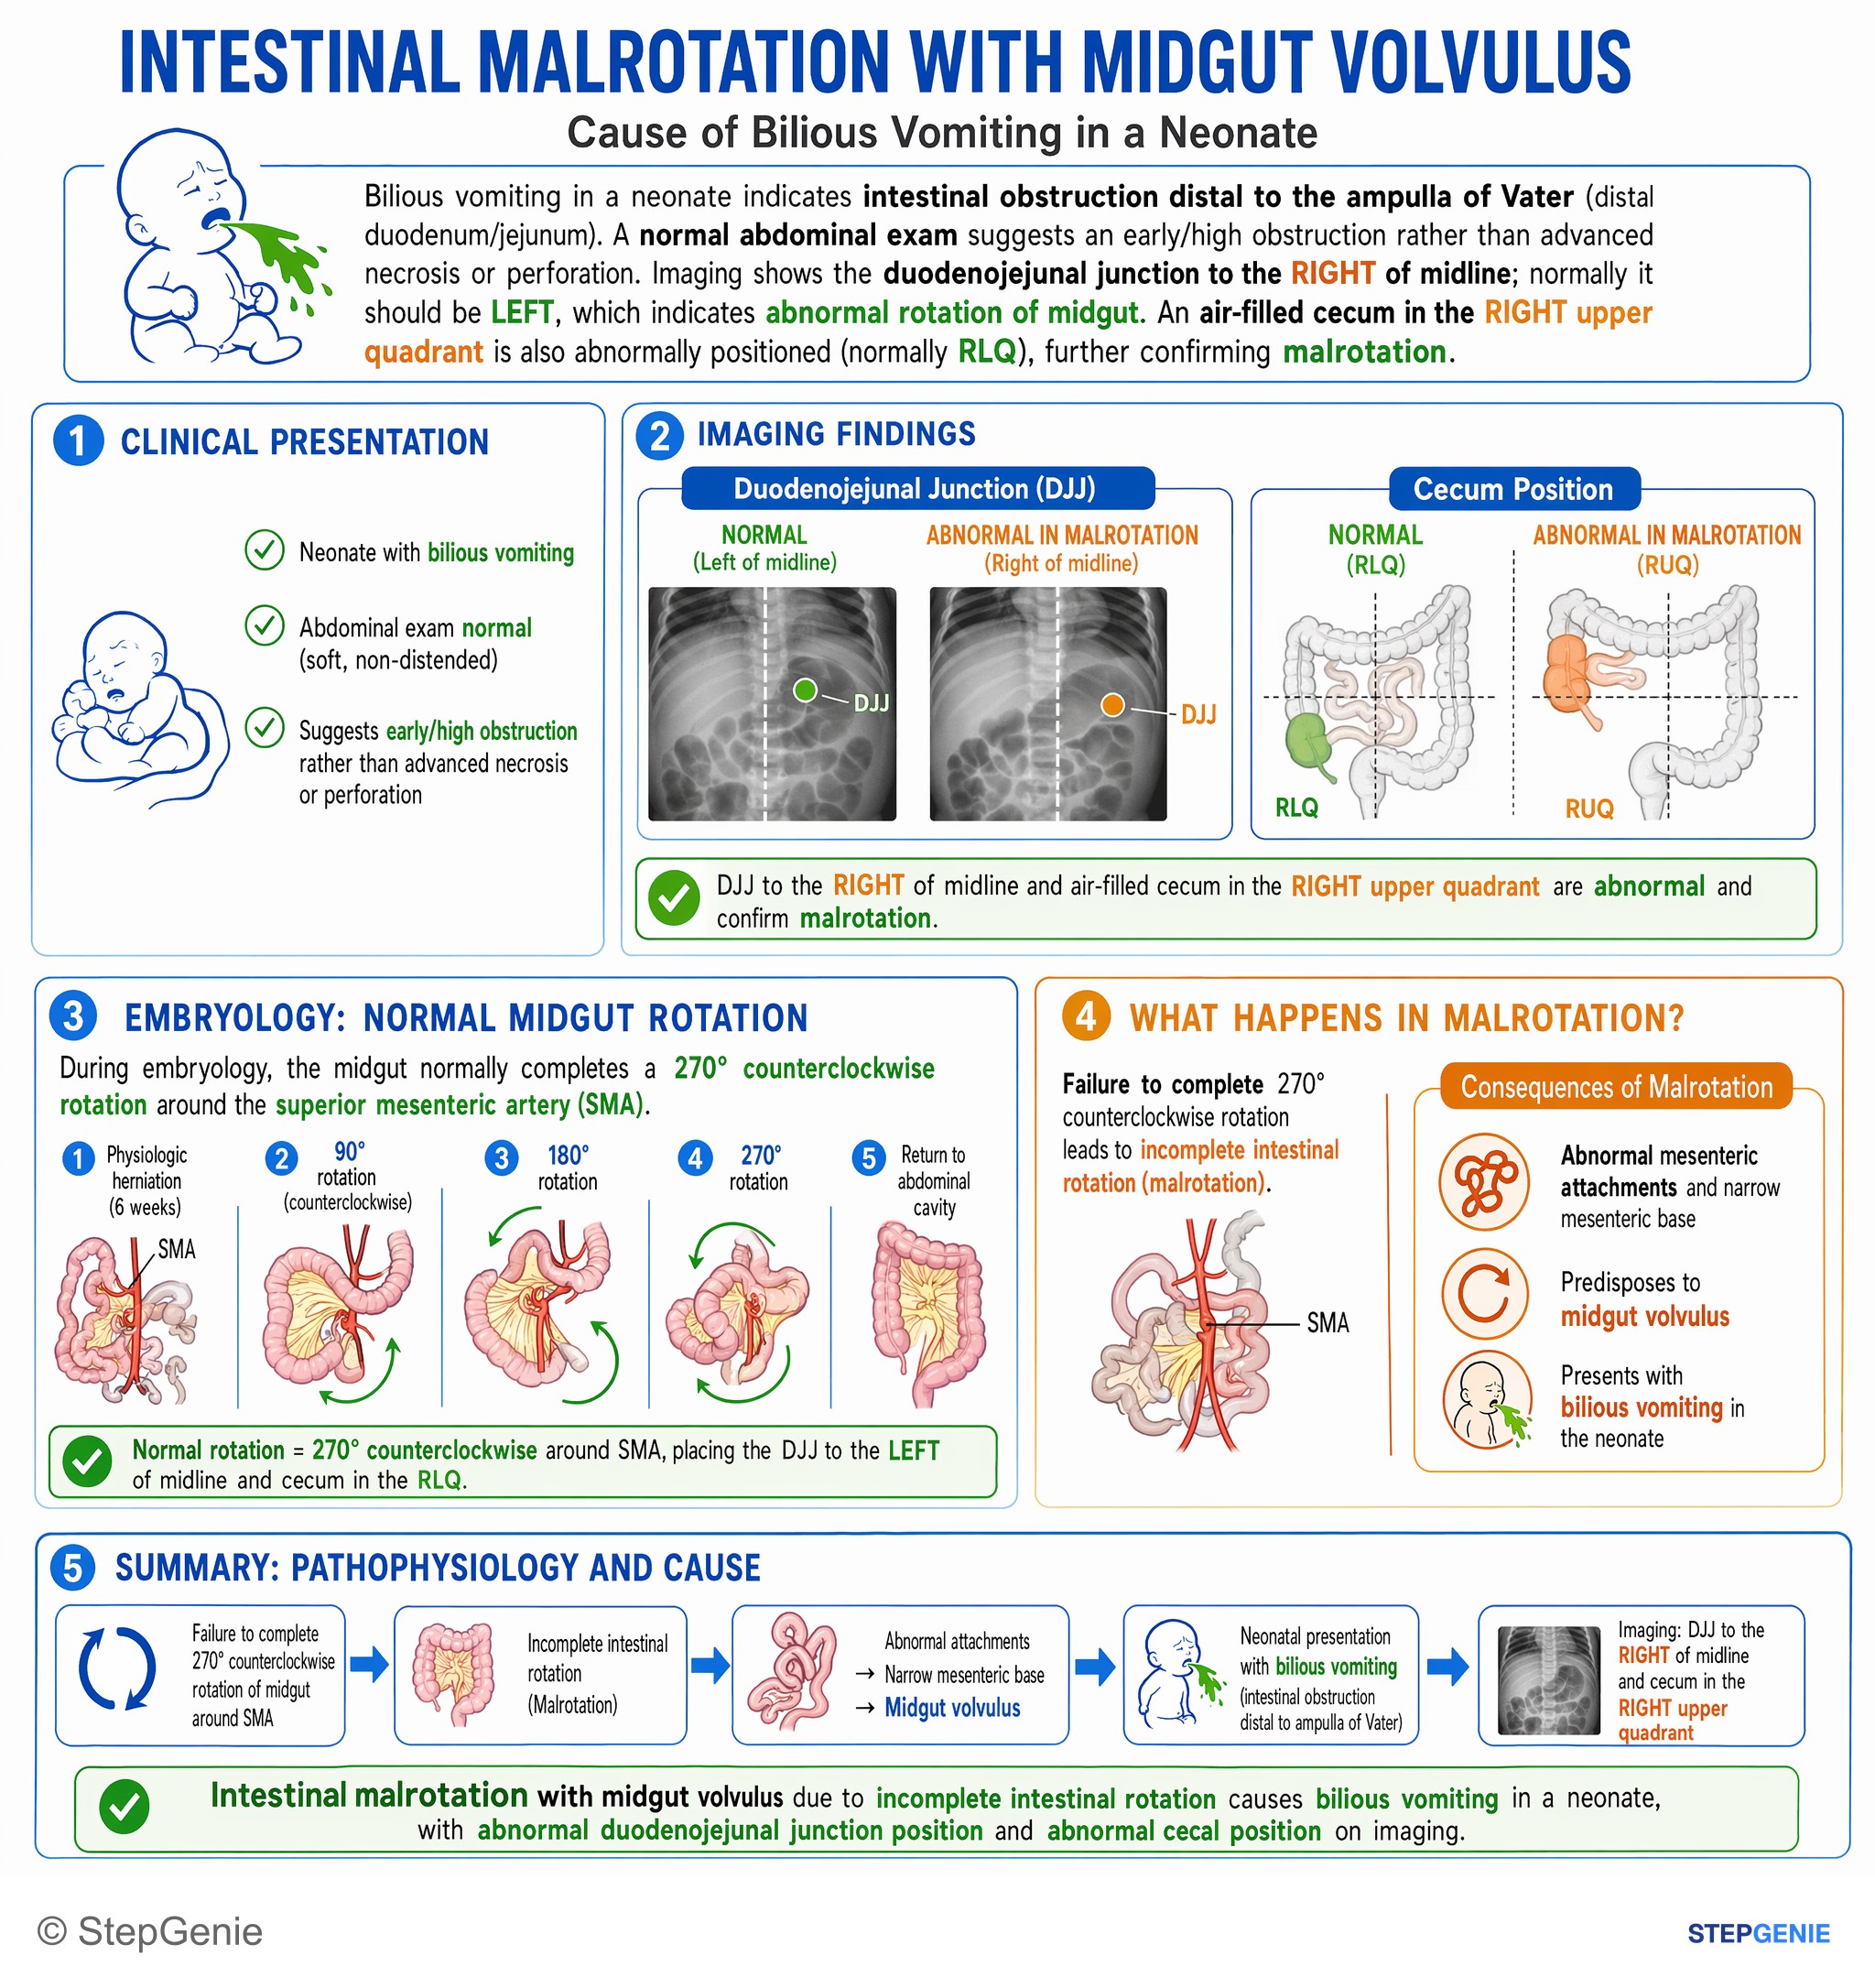
Intestinal malrotation with midgut volvulus from incomplete intestinal rotation causes bilious vomiting with abnormal duodenojejunal…
USMLE Step 1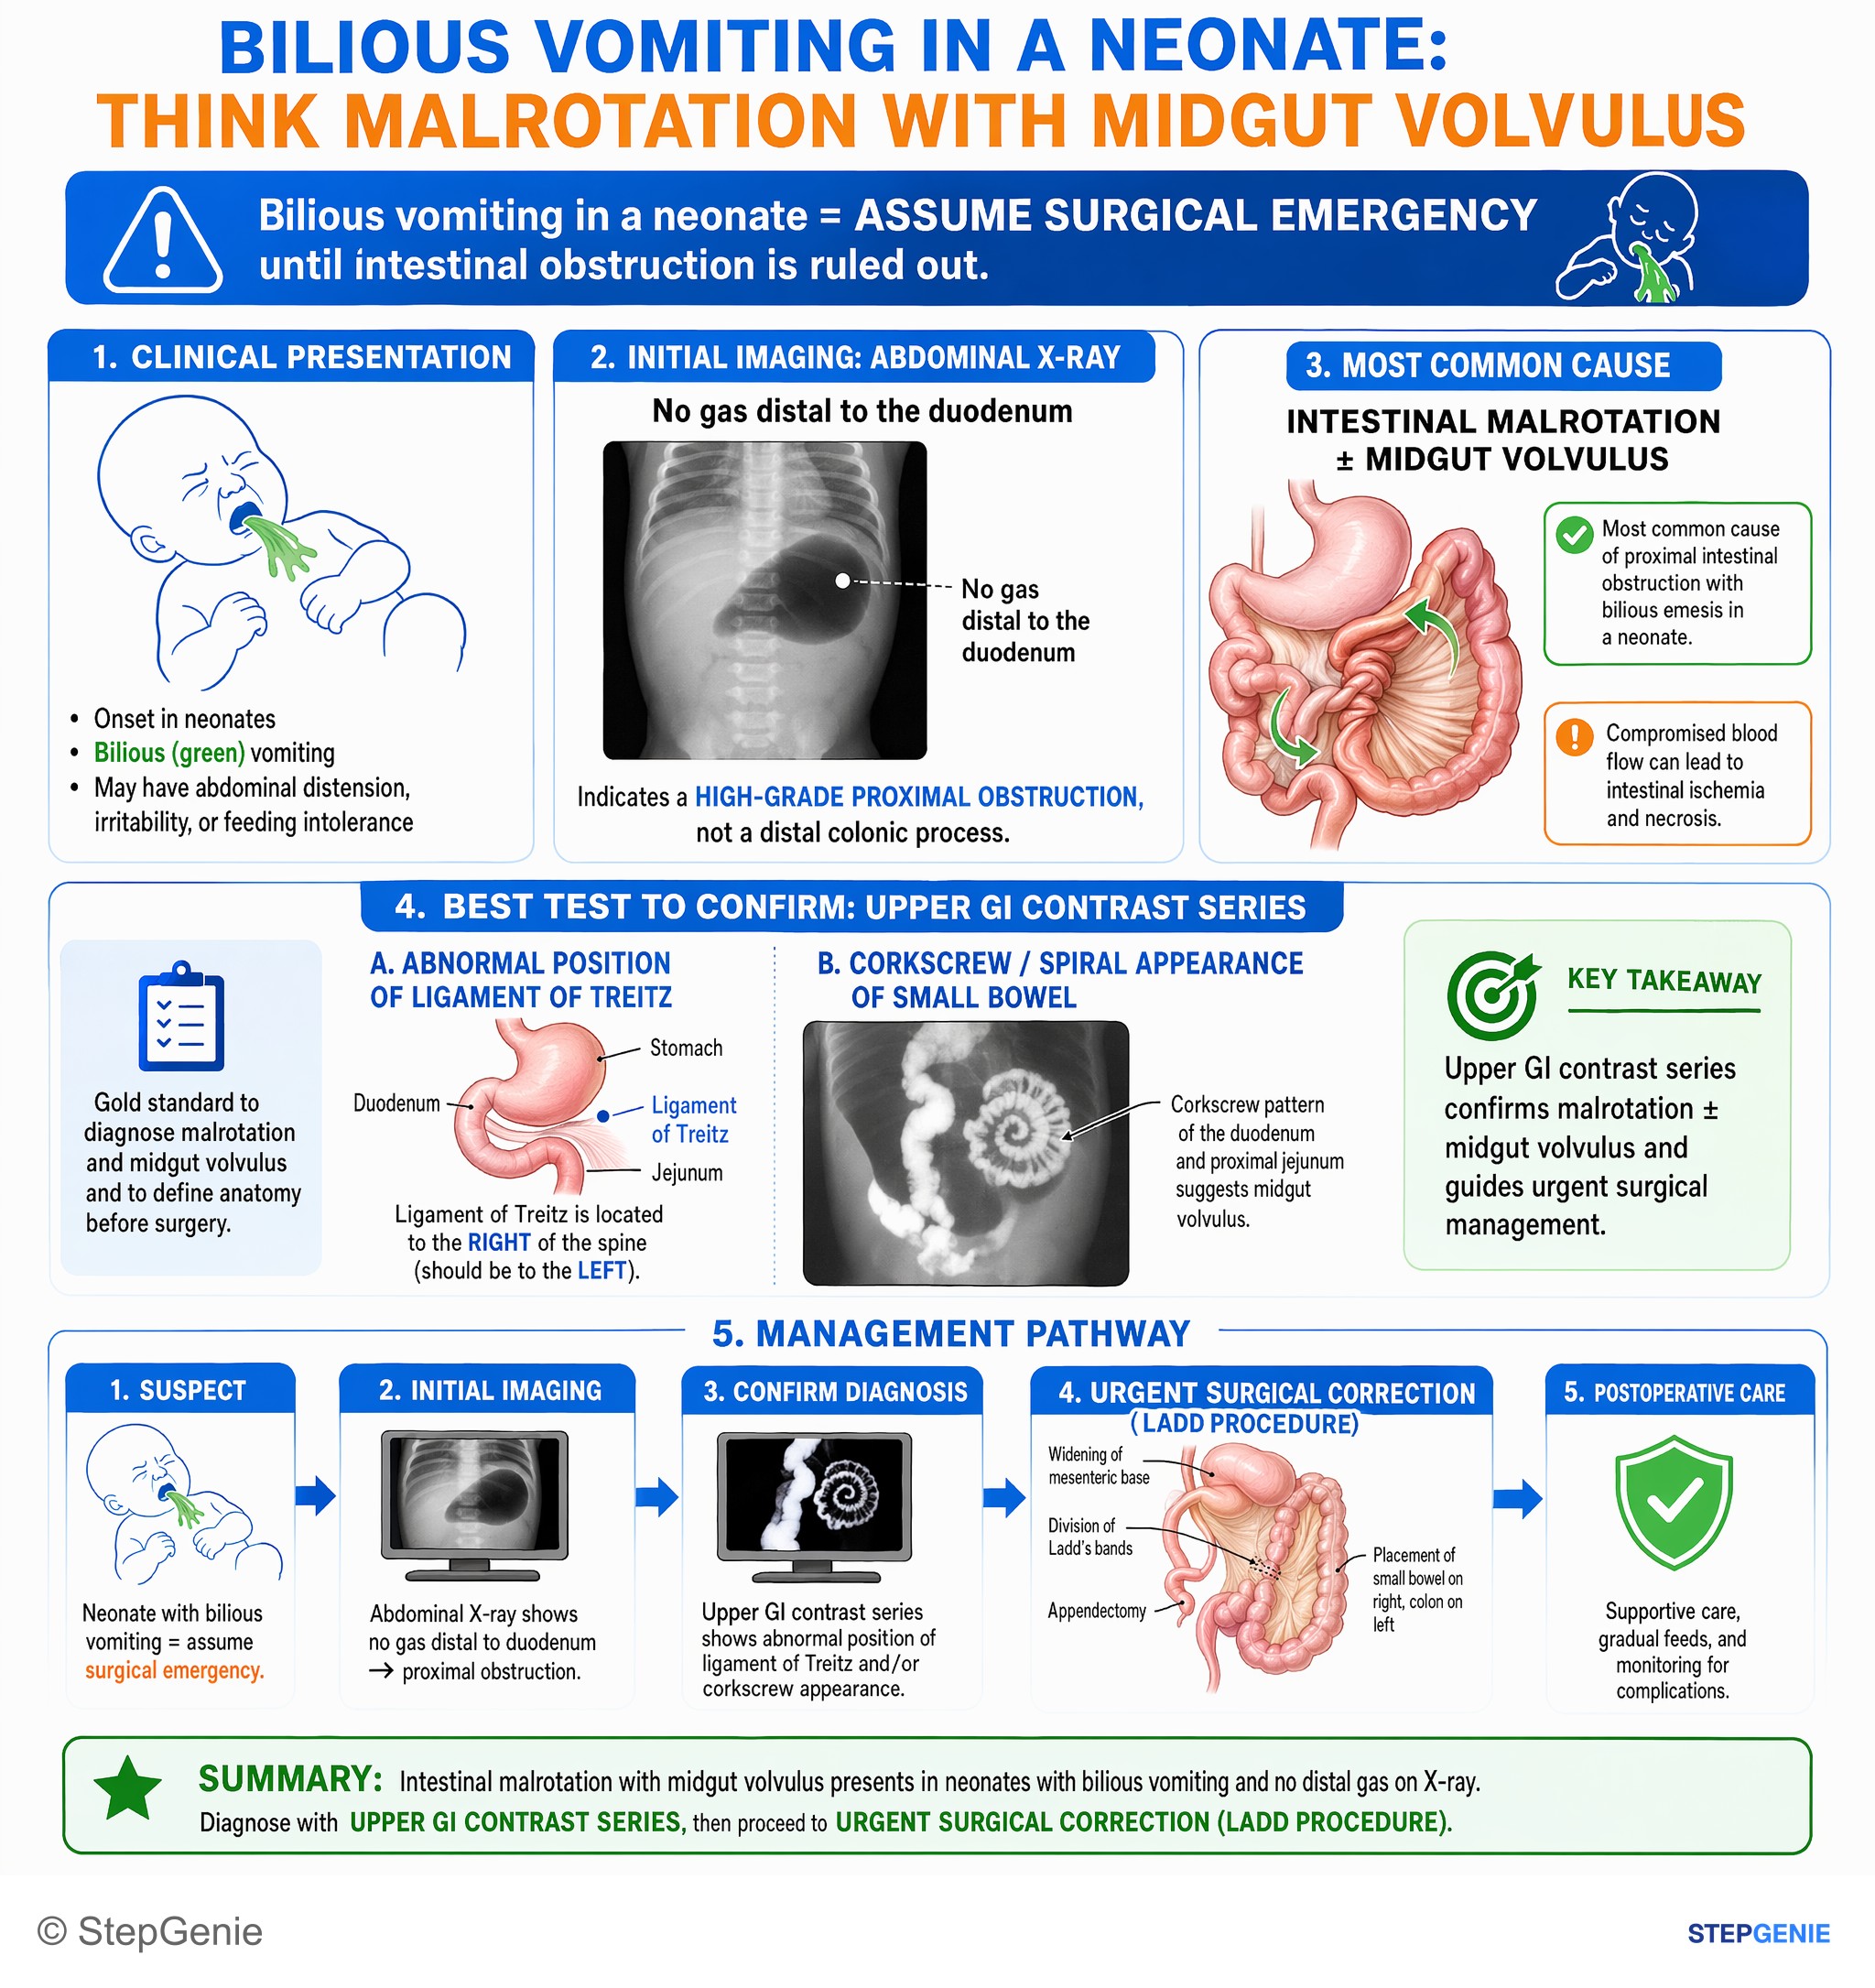
Intestinal malrotation with midgut volvulus presents in neonates with bilious vomiting and no distal gas; diagnose with upper GI contrast…
USMLE Step 2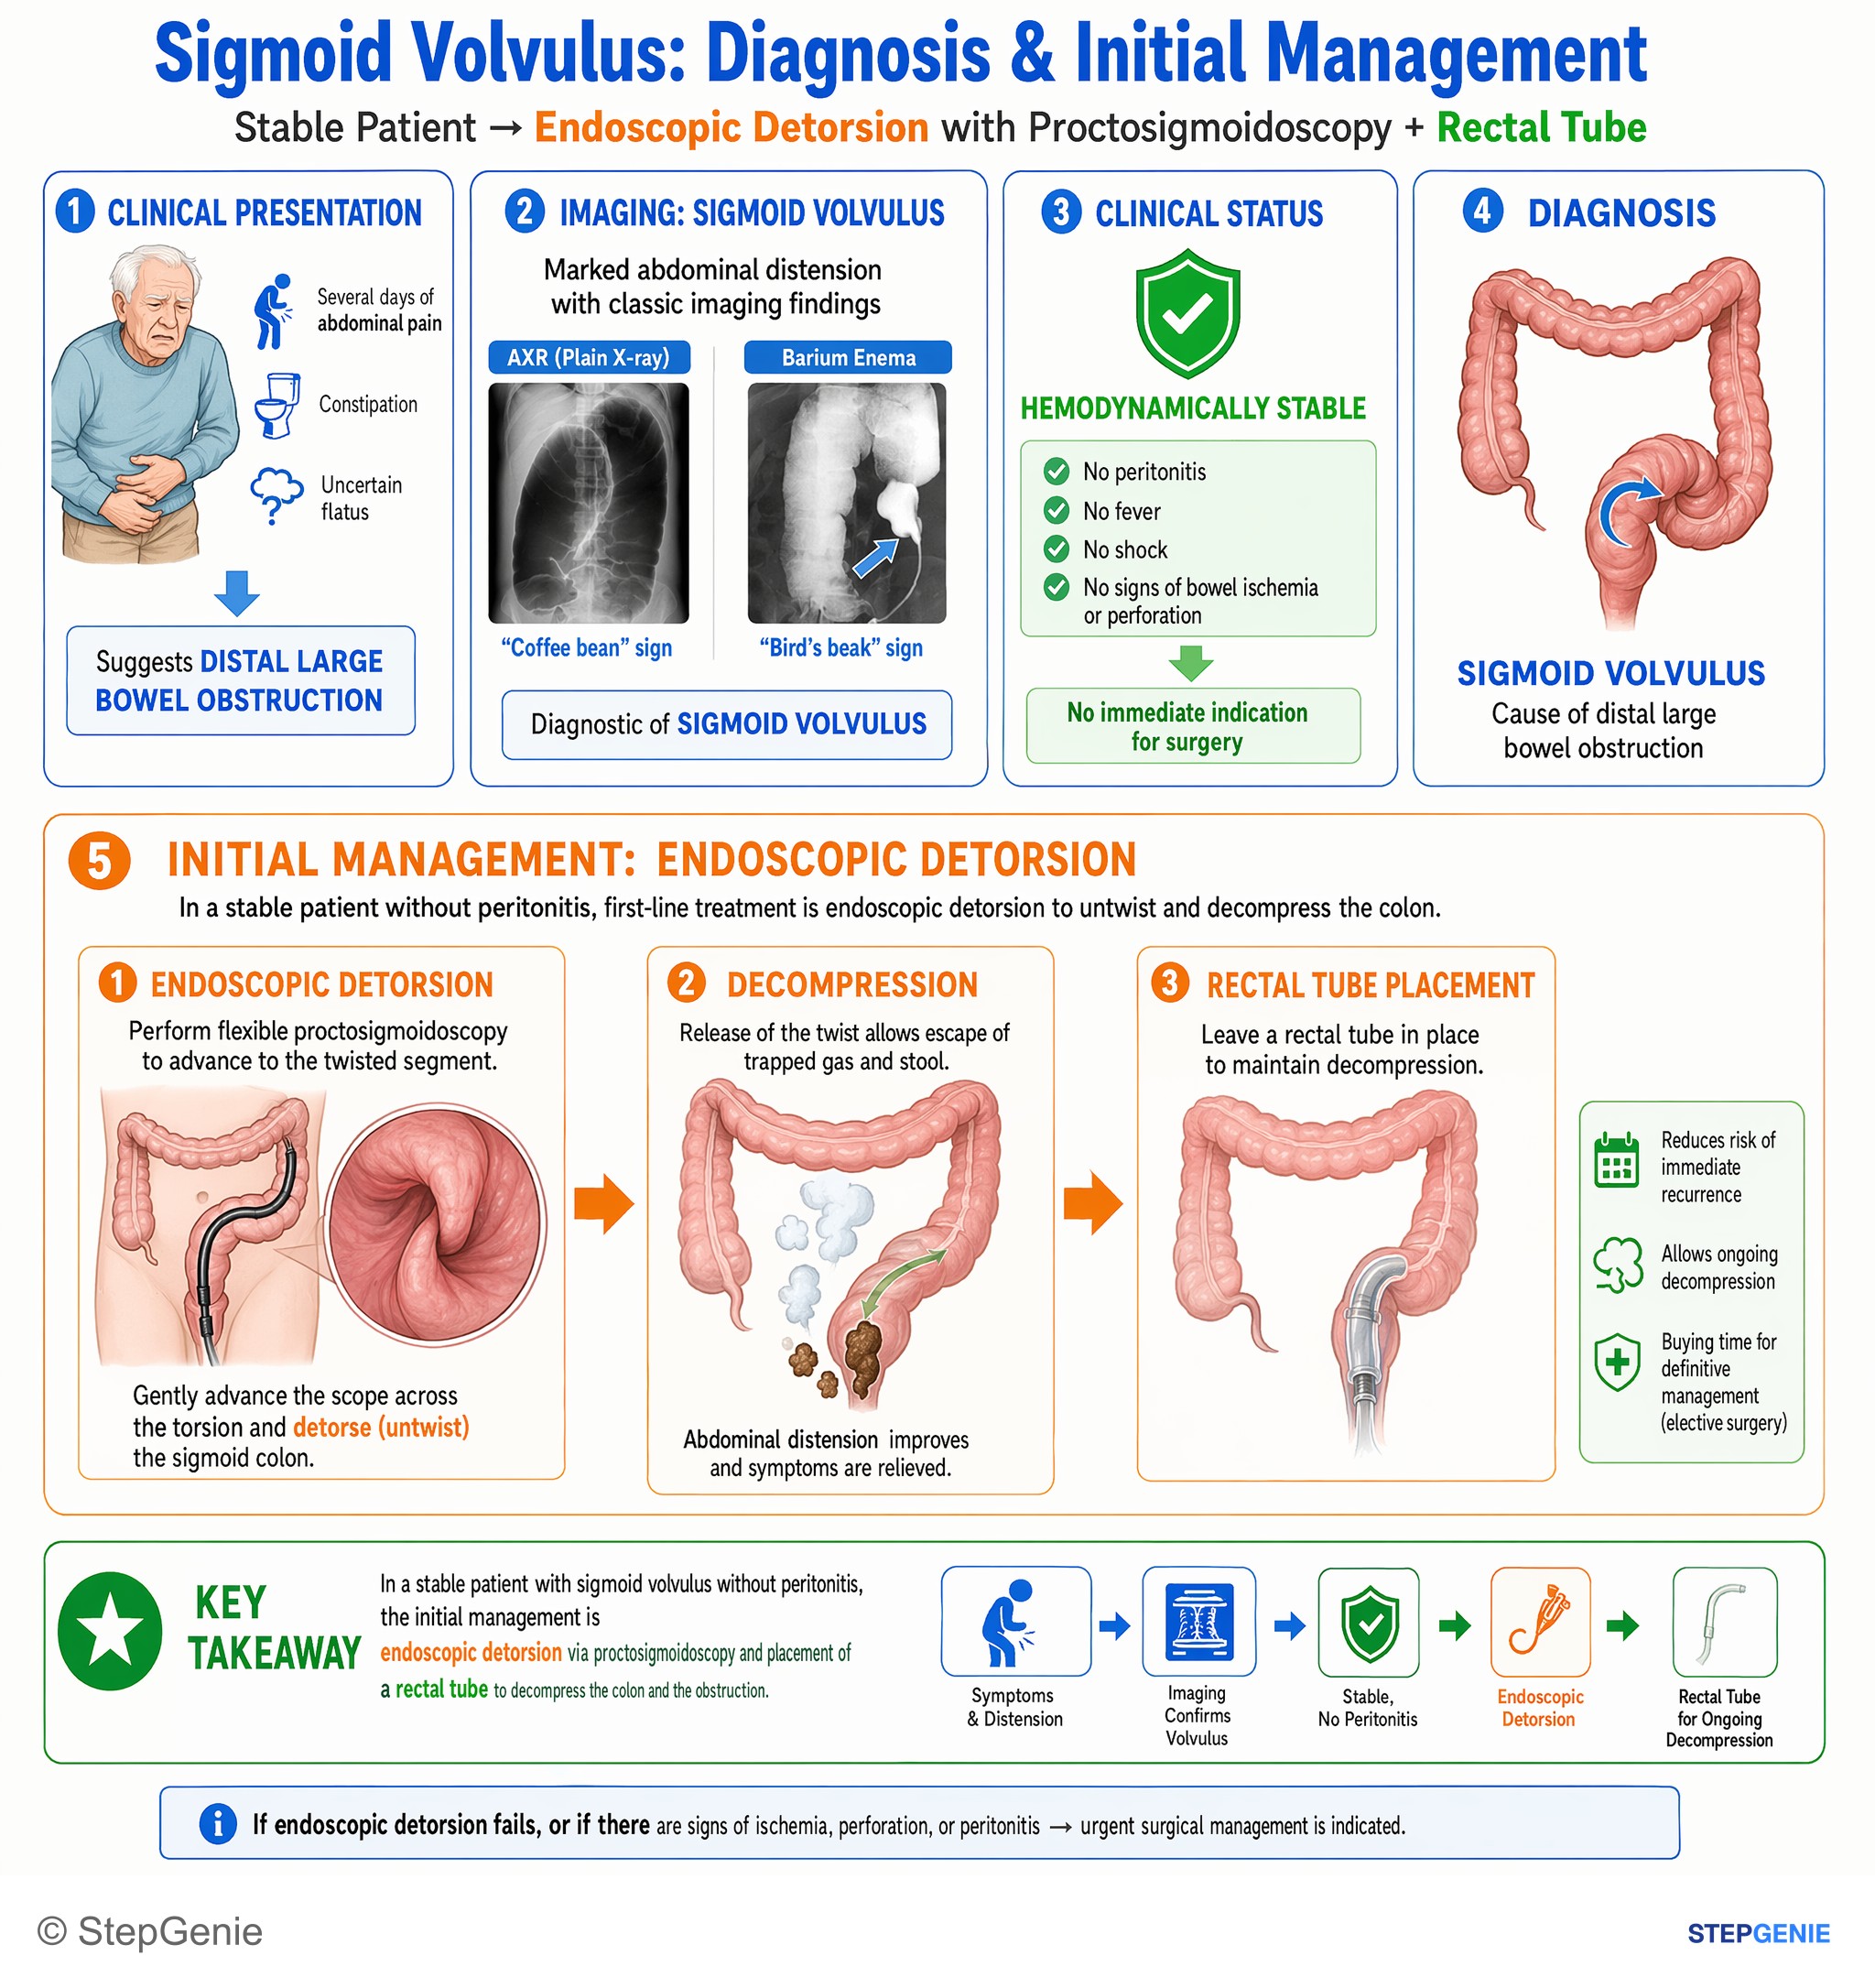
Sigmoid volvulus in a stable patient is initially managed with endoscopic detorsion via proctosigmoidoscopy and rectal tube placement to…
USMLE Step 2Frequently Asked Questions
What is the coffee bean sign?
The coffee bean sign is the plain-film appearance of sigmoid volvulus: a massively dilated, twisted sigmoid loop that projects toward the upper abdomen, sometimes above the transverse colon. It suggests the diagnosis, which CT can confirm with a whirl sign of twisted colon and mesentery, while a contrast enema shows a bird's beak at the point of the twist.
What is the first-line treatment for sigmoid volvulus?
If there is no peritonitis, perforation or hemodynamic instability, flexible endoscopy is used to assess colonic viability, detorse the loop and decompress the colon, and a decompression tube is left in place. Because recurrence after detorsion alone is 45 to 71%, WSES 2023 recommends sigmoid colectomy as early as possible, even during the same admission. Failed detorsion or a nonviable or perforated colon requires urgent resection.
How is cecal volvulus different from sigmoid volvulus?
Cecal volvulus accounts for about 25 to 40% of colonic volvulus and tends to affect somewhat younger women, while sigmoid volvulus accounts for 60 to 75% and mainly affects elderly men, many of them institutionalized. On imaging the dilated cecum sits in the mid-abdomen or left upper quadrant. Endoscopic reduction rarely works and is not recommended, so the ASCRS 2021 guideline prefers segmental resection.
Why is bilious vomiting in a newborn an emergency?
Green, bilious vomiting in an infant can signal malrotation with midgut volvulus, in which the small bowel twists on its narrow mesentery and loses its blood supply. Untreated, the midgut can infarct, leading to short bowel syndrome or death. After immediate evaluation and stabilization, an upper GI series showing the duodenojejunal junction to the right of the spine supports the diagnosis, and treatment is an emergency Ladd procedure.
How do you tell volvulus from Ogilvie syndrome?
Both cause massive colonic distension, but volvulus is a mechanical twist, with a coffee bean loop, a whirl sign on CT and a bird's beak on contrast enema. Ogilvie syndrome, or acute colonic pseudo-obstruction, dilates the colon without any mechanical cause. It is treated with supportive care and correction of predisposing conditions, then neostigmine with cardiac monitoring, then colonoscopic decompression if neostigmine fails or is contraindicated.