Gallstone ileus is one of those deceptively “simple” Step questions where the diagnosis is easy if you notice the one or two telling clues—then the test writers try to make you second-guess yourself with distractors that sound plausible (appendicitis? pancreatitis? SBO adhesions?). This post breaks down a classic vignette, nails the correct answer, and then explains why each wrong choice is wrong—because on test day, eliminating distractors is half the battle.
Tag: GI > Biliary & Pancreatic Disorders
The Clinical Vignette (Classic Q‑Bank Style)
A 78-year-old woman presents with 2 days of crampy abdominal pain, progressive abdominal distension, nausea, and several episodes of bilious vomiting. She has not passed flatus since yesterday. She reports intermittent right upper quadrant pain over the past year but never had surgery. Vitals: T 37.2°C, HR 102, BP 128/76. Abdomen is distended with high-pitched bowel sounds and mild diffuse tenderness. Labs show mild leukocytosis. CT abdomen shows small bowel obstruction with air in the biliary tree and an ectopic calcified mass in the distal ileum.
Question: Most likely underlying mechanism?
The Correct Answer: Gallstone Ileus from a Cholecystoenteric Fistula
Why it’s correct
This is mechanical small bowel obstruction caused by a gallstone that entered the GI tract through a biliary–enteric fistula (most commonly cholecystoduodenal). The stone then travels and typically lodges at a narrow point—classically the terminal ileum/ileocecal valve.
The high-yield imaging triad (Rigler triad)
On X-ray or CT, gallstone ileus is associated with:
| Finding | Why it happens |
|---|---|
| Small bowel obstruction | Stone obstructs lumen |
| Pneumobilia (air in biliary tree) | Fistula allows intestinal air into biliary system |
| Ectopic gallstone | Stone located outside gallbladder (often in ileum) |
Most common risk profile: older patient (often female) with prior biliary colic/cholecystitis history.
Pathophysiology in one sentence
Chronic inflammation from cholelithiasis → adhesions between gallbladder and bowel → erosion → fistula formation → large gallstone enters bowel → obstruction (usually terminal ileum).
How to Recognize It Fast (Step Pattern Recognition)
Clues that should jump out
- Elderly patient + SBO symptoms
- No prior abdominal surgery (so adhesions less likely)
- History suggestive of gallbladder disease
- Imaging with pneumobilia
- Obstruction at terminal ileum
Common exam twist: “Tumbling obstruction”
Symptoms may wax and wane as the stone intermittently obstructs then moves—intermittent crampy pain, episodic vomiting.
Management (What USMLE Expects)
Initial steps (like any SBO)
- IV fluids, electrolyte correction
- NG tube decompression if significant vomiting/distension
- Broad-spectrum antibiotics if concern for sepsis/perforation
Definitive treatment
- Enterolithotomy (surgical removal of the stone) is usually the immediate life-saving step.
Board nuance: Whether to also do cholecystectomy + fistula repair at the same time depends on stability/comorbidities. Many older patients get enterolithotomy alone initially.
Why Every Other Answer Choice Is Wrong (Systematic Distractor Breakdown)
Below are common Q-bank distractors and how to eliminate them quickly.
Distractor 1: Adhesive small bowel obstruction
Why it’s tempting: SBO symptoms + high-pitched bowel sounds.
Why it’s wrong here:
- Adhesions are most common cause of SBO in patients with prior abdominal surgery.
- This patient has no surgical history.
- Adhesions do not cause pneumobilia or an ectopic calcified mass.
When to pick adhesions: prior laparotomy/C-section/appendectomy + SBO without pneumobilia.
Distractor 2: Volvulus (sigmoid or cecal)
Why it’s tempting: elderly + abdominal distension + obstruction.
Why it’s wrong here:
- Volvulus classically causes large bowel obstruction, not distal ileal obstruction.
- Imaging would show:
- Sigmoid volvulus: “coffee bean” sign on abdominal X-ray
- Cecal volvulus: “kidney bean”/markedly dilated cecum, ectopic cecum
- Volvulus does not produce pneumobilia or an ectopic gallstone.
When to pick volvulus: massive distension, constipation, tympany, classic radiographic signs.
Distractor 3: Acute pancreatitis due to gallstones
Why it’s tempting: gallstones are involved; older patient with GI symptoms.
Why it’s wrong here:
- Pancreatitis is epigastric pain radiating to the back, often severe, better leaning forward.
- Labs: elevated lipase (and often amylase).
- Imaging: pancreatic inflammation/edema—not SBO with pneumobilia and ectopic stone.
When to pick pancreatitis: epigastric/back pain + lipase > 3× ULN.
Distractor 4: Acute cholecystitis
Why it’s tempting: RUQ pain history.
Why it’s wrong here:
- Cholecystitis presents with:
- RUQ pain, fever, leukocytosis
- Murphy sign
- It does not classically cause SBO with a stone in the ileum.
- Pneumobilia isn’t typical of uncomplicated cholecystitis (unless emphysematous cholecystitis—see below).
When to pick cholecystitis: RUQ pain + postprandial fatty food trigger + Murphy sign.
Distractor 5: Ascending cholangitis
Why it’s tempting: biliary disease in an elderly patient.
Why it’s wrong here:
- Cholangitis is infection behind an obstructing CBD stone → Charcot triad:
- fever, jaundice, RUQ pain
- Severe: Reynolds pentad adds hypotension + altered mental status.
- This vignette screams bowel obstruction, not jaundice/sepsis from biliary obstruction.
When to pick cholangitis: toxic patient + jaundice + RUQ pain; needs antibiotics + ERCP decompression.
Distractor 6: Emphysematous cholecystitis
Why it’s tempting: “air in biliary area” can confuse students.
Why it’s wrong here:
- Emphysematous cholecystitis is gas in the gallbladder wall/lumen from gas-forming organisms (often in diabetics).
- Presents with severe RUQ pain, fever, systemic toxicity.
- Pneumobilia in gallstone ileus is air in the biliary tree due to a fistula, plus SBO findings.
Quick differentiator:
- Gallstone ileus: pneumobilia + SBO + ectopic stone
- Emphysematous cholecystitis: gas in gallbladder wall + very sick patient
Distractor 7: Gallbladder carcinoma
Why it’s tempting: older patient + gallstone history.
Why it’s wrong here:
- Carcinoma presents with weight loss, persistent RUQ pain, jaundice, and possibly a palpable gallbladder if obstruction occurs.
- It does not typically cause pneumobilia + ectopic stone + mechanical SBO.
When to think about it: porcelain gallbladder, gallbladder mass, painless jaundice (less common than pancreatic cancer but still tested).
Distractor 8: Ileus (functional obstruction)
Why it’s tempting: “no bowel movement, distension.”
Why it’s wrong here:
- Ileus is decreased peristalsis → hypoactive/absent bowel sounds, diffuse bowel dilation without a transition point.
- This vignette has high-pitched bowel sounds and a mechanical obstruction on CT.
When to pick ileus: post-op patient, opioids, electrolyte abnormalities (esp hypokalemia), diffuse dilation.
Rapid-Fire High-Yield Pearls (USMLE Friendly)
- Gallstone ileus = mechanical SBO + pneumobilia + ectopic gallstone.
- Mechanism: chronic cholecystitis → cholecystoenteric fistula (often duodenum) → stone enters bowel.
- Most common site of impaction: terminal ileum/ileocecal valve.
- Elderly + no surgical history + SBO should trigger: hernia, malignancy, gallstone ileus—then use imaging clues.
- Management: stabilize like SBO → enterolithotomy (often first/only surgery in frail patients).
One-Liner to Remember
“Old woman + SBO + pneumobilia = gallstone ileus (fistula to bowel, stone stuck at ileocecal valve).”
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
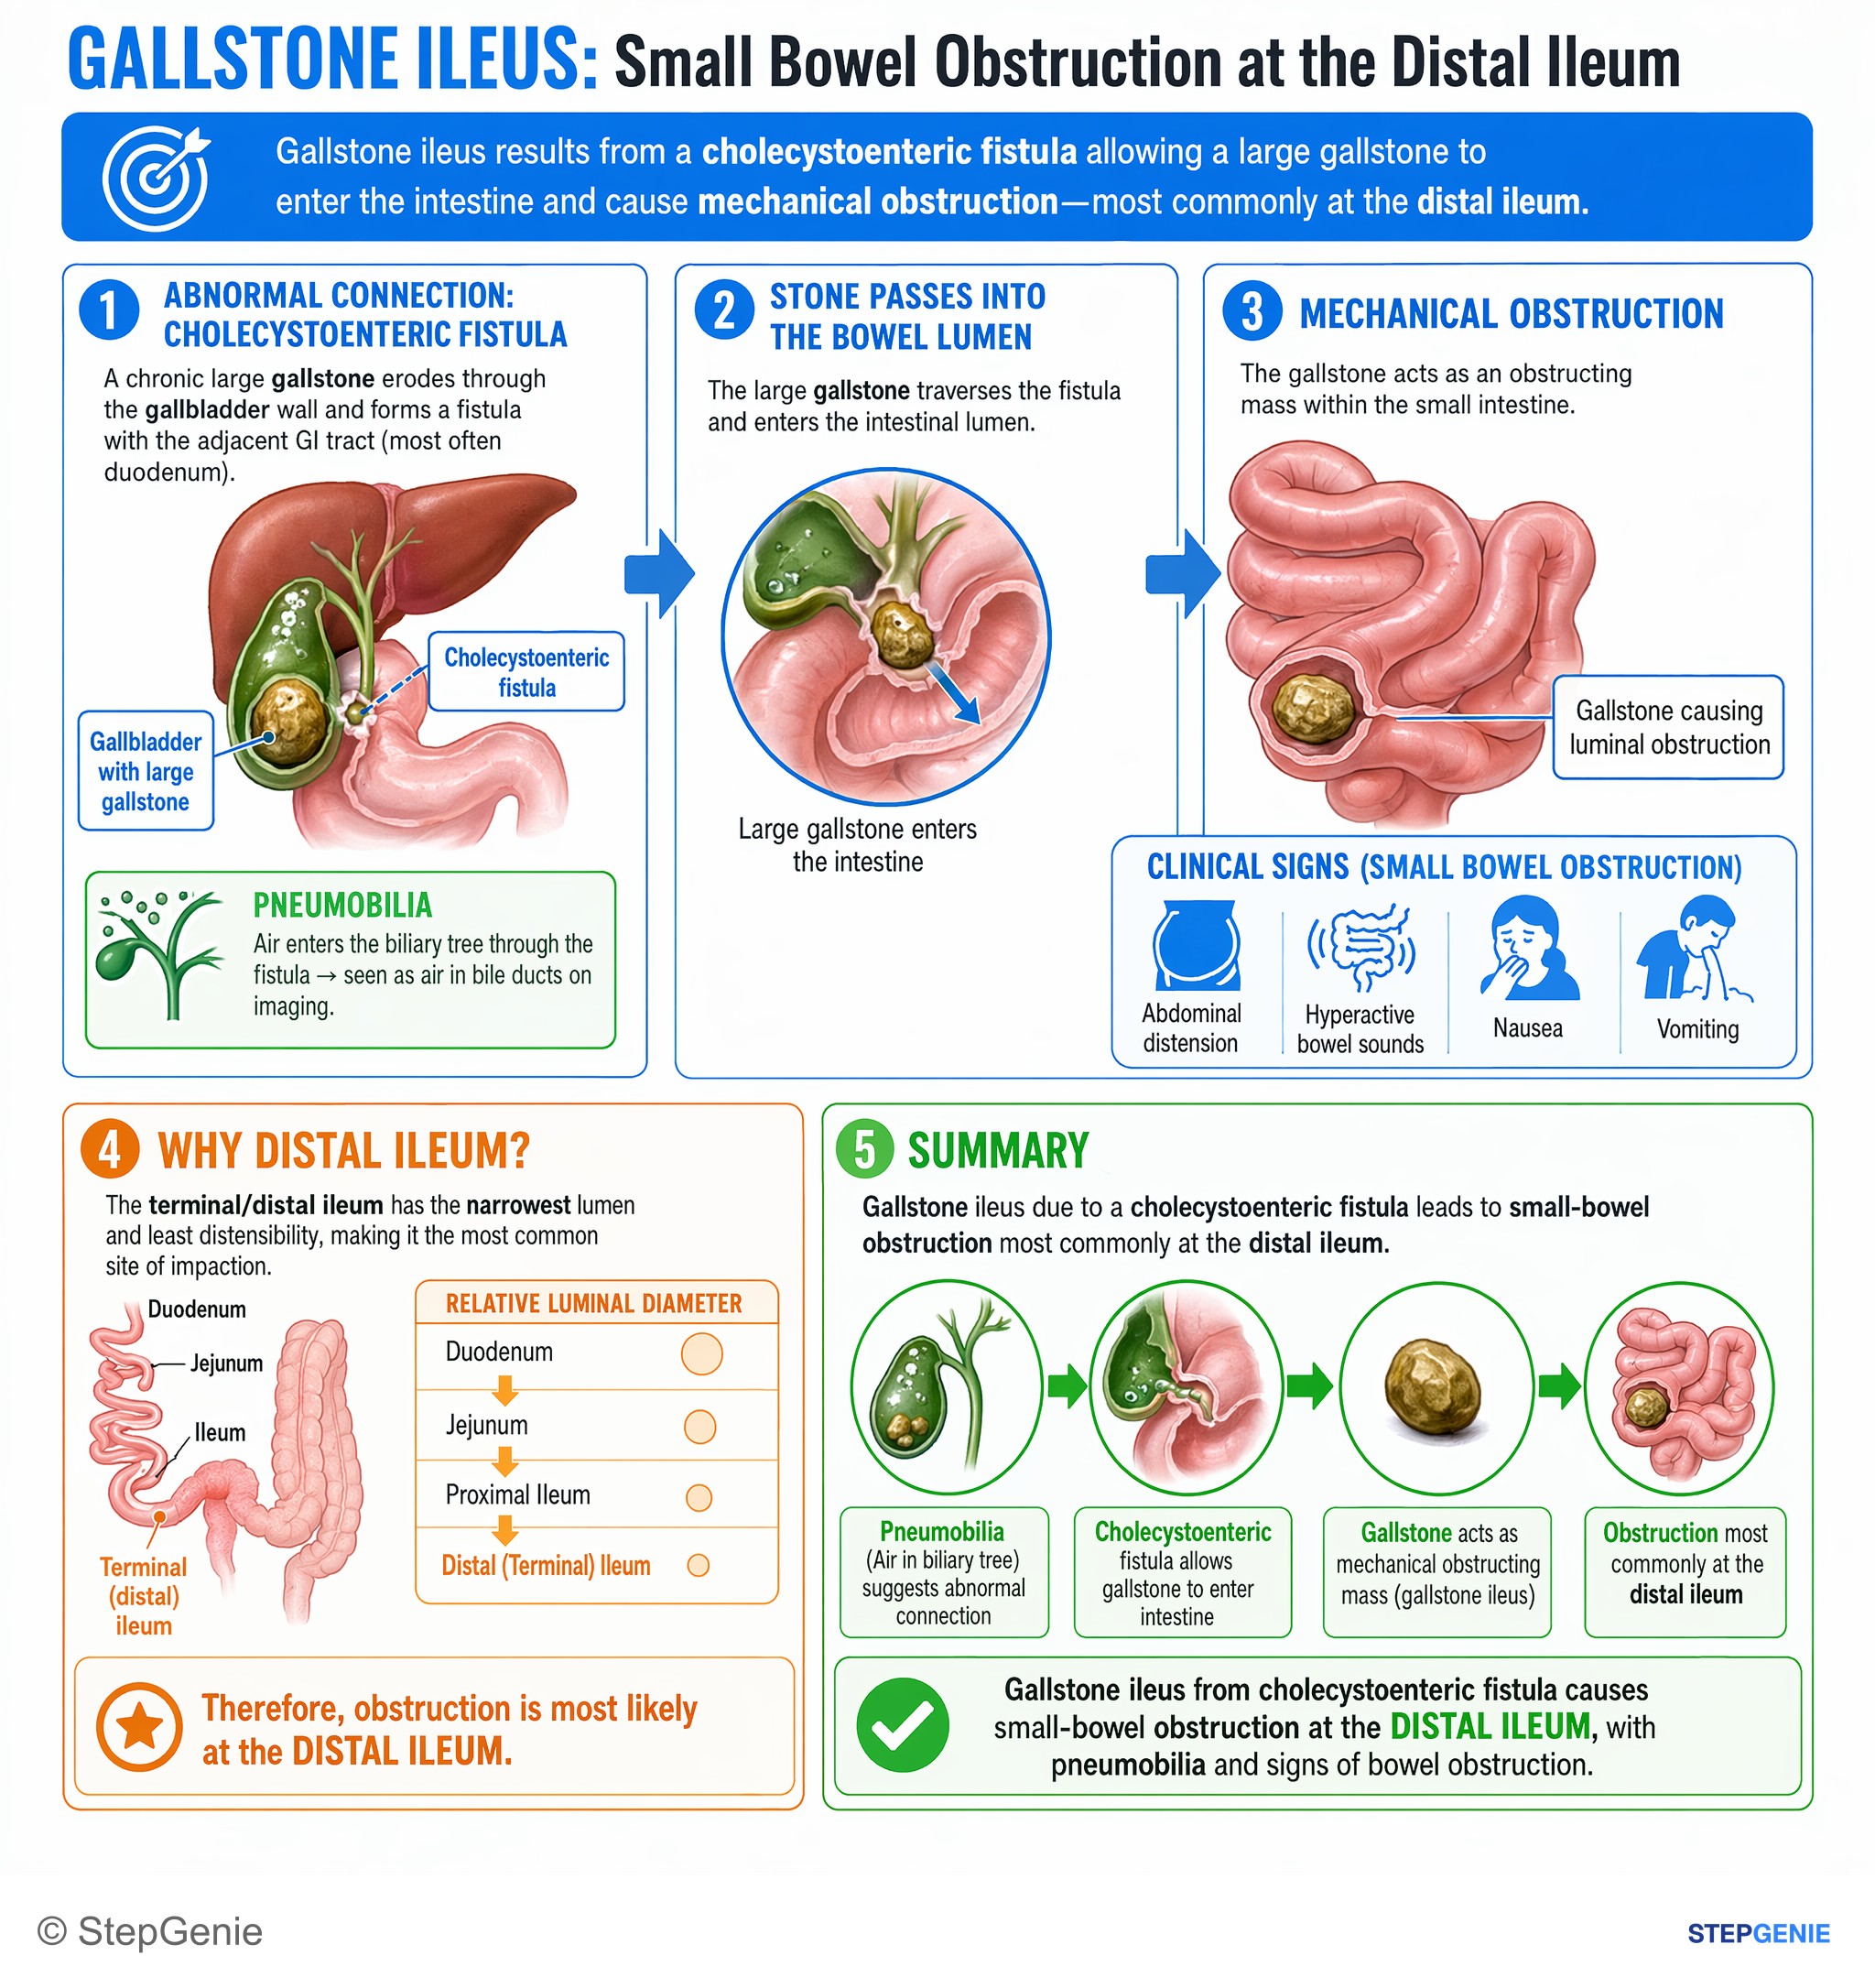
Gallstone ileus from cholecystoenteric fistula causes small-bowel obstruction at the distal ileum, with pneumobilia and signs of bowel…
USMLE Step 1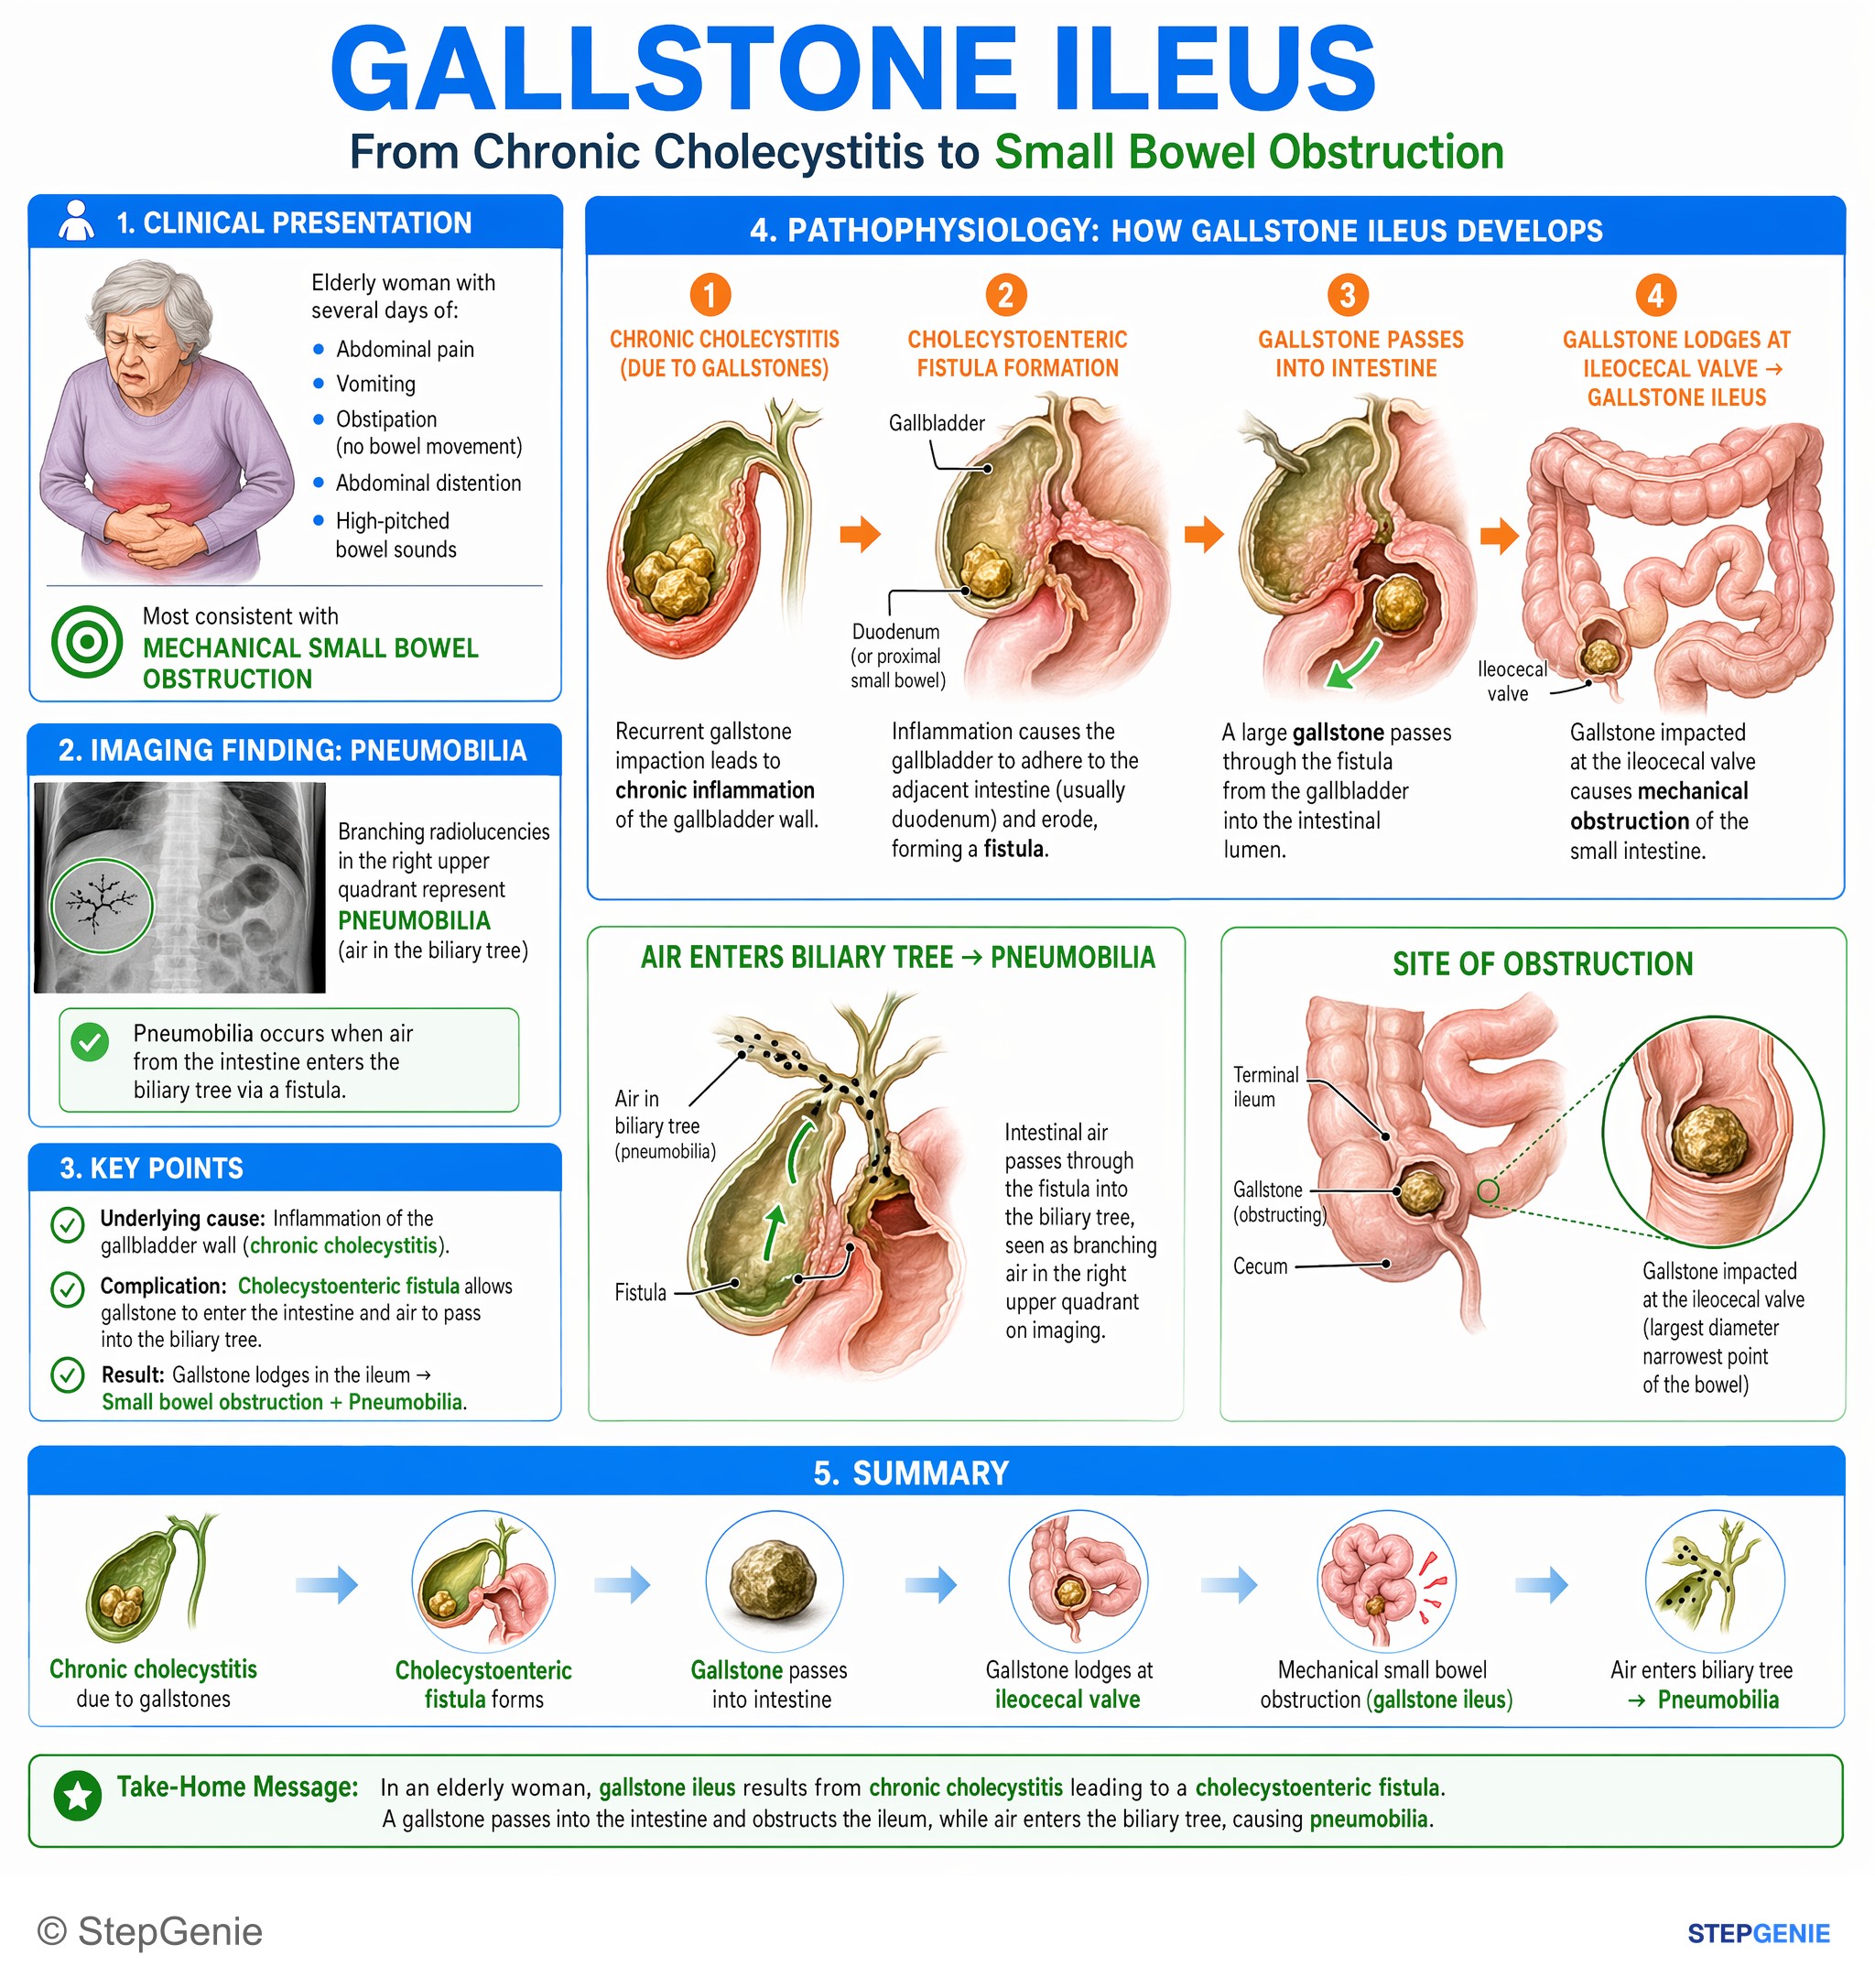
Gallstone ileus from chronic cholecystitis → cholecystoenteric fistula → gallstone obstructs ileum; air in biliary tree + small bowel…
USMLE Step 2Frequently Asked Questions
What is the underlying mechanism of gallstone ileus?
Gallstone ileus is caused by a biliary-enteric fistula that lets a large gallstone enter the intestinal lumen and mechanically obstruct the bowel. Chronic inflammation from cholelithiasis leads to adhesions between the gallbladder and bowel, then erosion and fistula formation, most commonly cholecystoduodenal. The stone usually lodges at a narrow point, classically the terminal ileum or ileocecal valve.
How do you recognize gallstone ileus on imaging?
Gallstone ileus is recognized by the Rigler triad: small bowel obstruction, pneumobilia, and an ectopic gallstone. The obstruction appears because the stone blocks the lumen, pneumobilia occurs because the fistula allows intestinal air into the biliary tree, and the ectopic stone is seen outside the gallbladder, often in the ileum. CT in the classic vignette shows all three findings together.
How do you tell gallstone ileus from adhesive small bowel obstruction on a test question?
Gallstone ileus is favored when an older patient has small bowel obstruction symptoms, no prior abdominal surgery, a history suggesting gallbladder disease, and imaging with pneumobilia plus an ectopic calcified stone. Adhesive small bowel obstruction is more likely after prior abdominal surgery and does not explain air in the biliary tree or a calcified mass in the distal ileum.
Why is the terminal ileum a classic site of obstruction in gallstone ileus?
The terminal ileum is a classic site because the gallstone tends to lodge at a narrow point in the bowel. After entering the GI tract through a cholecystoenteric fistula, the stone travels downstream until it reaches a relatively tight area, most classically the terminal ileum or ileocecal valve, where it causes mechanical small bowel obstruction.
What is the usual treatment approach for gallstone ileus?
Initial management is supportive small bowel obstruction care, followed by surgical stone removal as the definitive treatment. Patients should receive IV fluids, electrolyte correction, and NG tube decompression if vomiting or distension is significant, with broad-spectrum antibiotics if sepsis or perforation is a concern. The usual immediate life-saving operation is enterolithotomy, while cholecystectomy and fistula repair depend on the patient’s stability and comorbidities.