Ascending (acute) cholangitis is infection of an obstructed bile duct, most often from a common bile duct stone, with gut bacteria (E. coli, Klebsiella, Enterococcus) ascending into stagnant bile. Charcot triad (fever, right upper quadrant pain, jaundice) is specific but misses most cases, and Reynolds pentad adds hypotension and confusion. The Tokyo Guidelines 2018 (TG18), still the current edition, diagnose it by inflammation + cholestasis + imaging and grade it I-III by organ dysfunction. Treatment is IV antibiotics plus biliary drainage, usually ERCP: early for Grade II and urgent (once stabilized) for Grade III; ASGE suggests ERCP within 48 hours.
The vignette
A 71-year-old woman with known gallstones is brought to the emergency department with 2 days of fever, shaking chills and right upper quadrant pain; today she is confused. Temperature is 39.4°C (102.9°F), pulse 118/min and blood pressure 82/48 mm Hg. She has scleral icterus and right upper quadrant tenderness. Leukocyte count is 18,600/mm³, total bilirubin 5.6 mg/dL (direct 4.4 mg/dL), alkaline phosphatase 420 U/L, AST 170 U/L, ALT 205 U/L, and lipase is normal. Ultrasound shows gallstones and a common bile duct dilated to 12 mm, with no gallbladder wall thickening. Blood cultures are drawn, IV fluids and piperacillin-tazobactam are started, and norepinephrine is needed to keep her mean arterial pressure above 65 mm Hg.
Which is the most appropriate next step in management?
A. Urgent ERCP with biliary decompression B. Laparoscopic cholecystectomy C. HIDA scan (cholescintigraphy) D. MRCP E. Continue IV antibiotics alone and reassess in 48 hours F. Percutaneous cholecystostomy
Answer: A. Urgent ERCP with biliary decompression
Run her through TG18:
- A (systemic inflammation): fever >38°C with chills; WBC >10,000/mm³.
- B (cholestasis): bilirubin ≥2 mg/dL; alkaline phosphatase and transaminases >1.5 × the upper limit of normal.
- C (imaging): dilated common bile duct, with gallstones as the likely cause.
One item from each of A, B and C makes this a definite diagnosis. A vasopressor requirement (cardiovascular dysfunction) and confusion (neurologic dysfunction) make it Grade III (severe). TG18 says to support the circulation and drain the bile duct as soon as the patient's condition allows: antibiotics alone can't clear infected bile trapped behind a stone. ASGE (2021) prefers endoscopic drainage over percutaneous and suggests ERCP within 48 hours for cholangitis. ERCP can clear the duct in one session (sphincterotomy, stone extraction, stent) with success above 95% (Merck); in a patient too unstable for a full procedure, a stent alone decompresses first and the stone comes out later. If ERCP fails or can't be done, use percutaneous transhepatic biliary drainage (PTBD) or EUS-guided drainage.
Why every other answer is wrong
B. Laparoscopic cholecystectomy. Tempting because she has gallstones. But removing the gallbladder does not unblock the common bile duct, and she is in septic shock. Cholecystectomy comes after recovery, to prevent recurrence. When it's right: acute cholecystitis, where early cholecystectomy (within 24-48 hours) is favored if surgical risk is low.
C. HIDA scan. Cholescintigraphy asks one question: is the cystic duct patent? Nonfilling of the gallbladder suggests acute cholecystitis. It treats nothing, and this diagnosis is already definite. When it's right: suspected acute cholecystitis when ultrasound is equivocal.
D. MRCP. It shows common duct stones accurately and noninvasively, but it is purely diagnostic, and every hour spent imaging is an hour of undrained sepsis. When it's right: a stable patient with possible choledocholithiasis, to decide whether ERCP is needed.
E. Antibiotics alone, reassess in 48 hours. Most Grade I (mild) cholangitis does settle on antibiotics, and TG18 drains those patients only if they don't respond (about 24 hours) or need the stone treated. Grade II needs early drainage and Grade III needs urgent drainage; waiting 48 hours in shock is wrong.
F. Percutaneous cholecystostomy. It drains the gallbladder, while the infected bile is in the common duct, below the cystic duct. When it's right: acute cholecystitis in a patient too sick for surgery.
Recognize it: Charcot, Reynolds and TG18
| Tool | What it is | How to use it |
|---|---|---|
| Charcot triad | Fever/chills + RUQ pain + jaundice | Highly specific (~96%) but insensitive (~26%): its absence doesn't exclude cholangitis |
| Reynolds pentad | Charcot + hypotension + confusion | Septic, severe cholangitis: think urgent drainage |
| TG18 diagnostic criteria | A + B + C (below) | Suspected = A + (B or C); definite = A + B + C |
| TG18 domain | Items and thresholds |
|---|---|
| A. Systemic inflammation | A-1 fever >38°C and/or shaking chills; A-2 WBC <4,000 or >10,000/µL, CRP ≥1 mg/dL |
| B. Cholestasis | B-1 jaundice: total bilirubin ≥2 mg/dL; B-2 ALP, GGT, AST or ALT >1.5 × upper limit of normal |
| C. Imaging | C-1 biliary dilatation; C-2 the cause on imaging (stone, stricture, stent) |
The lab pattern is cholestatic (alkaline phosphatase, GGT, conjugated bilirubin) with leukocytosis. On ultrasound, Merck treats a common duct over 6 mm as dilated (over 10 mm after cholecystectomy).
TG18 severity grades and what each one changes
| Grade | Definition | Drainage |
|---|---|---|
| III (severe) | Any one organ dysfunction: hypotension needing dopamine ≥5 µg/kg/min or any norepinephrine; disturbance of consciousness; PaO₂/FiO₂ <300; oliguria or creatinine >2.0 mg/dL; PT-INR >1.5; platelets <100,000/mm³ | Urgent, as soon as organ support has stabilized the patient |
| II (moderate) | Any two of: WBC >12,000 or <4,000/mm³; fever ≥39°C; age ≥75; total bilirubin ≥5 mg/dL; albumin <0.7 × lower limit of normal | Early endoscopic or percutaneous drainage |
| I (mild) | Neither of the above | Antibiotics; drain if no response within about 24 hours or if a duct stone needs treating |
Our patient has Grade III features and also several Grade II features (fever ≥39°C, bilirubin ≥5 mg/dL, WBC >12,000); the higher grade wins.
Why it happens and which bugs
- Obstruction + infection. A blocked duct lets bacteria ascend from the duodenum into stagnant bile; infected bile under obstruction seeds the bloodstream, so the patient can slide into septic shock.
- Causes: choledocholithiasis (most cases; usually stones that formed in the gallbladder), benign or malignant strictures (pancreatic head cancer, cholangiocarcinoma, primary sclerosing cholangitis), blocked stents, parasites.
- Organisms in bile (TG18): E. coli (31-44%), Klebsiella (9-20%), Enterococcus (3-34%), Enterobacter, Pseudomonas, streptococci, and anaerobes (4-20%).
Antibiotics: what TG18 recommends
Take blood cultures before antibiotics, culture bile during drainage, and tailor the choice to the local antibiogram.
| Setting | Examples of TG18 empiric regimens |
|---|---|
| Community-acquired, Grade I-II | Ceftriaxone or cefotaxime (± metronidazole), ertapenem; Grade II also piperacillin-tazobactam or cefepime |
| Community-acquired Grade III, or healthcare-associated | Piperacillin-tazobactam, cefepime or ceftazidime ± metronidazole, or a carbapenem; add vancomycin for Enterococcus |
- Anaerobic coverage (eg, metronidazole) is needed when there is a biliary-enteric anastomosis.
- Ampicillin-sulbactam is not recommended where more than 20% of local E. coli are resistant (it has little activity left against E. coli in many regions); fluoroquinolones only when susceptibility is known or the patient has a β-lactam allergy.
- Duration: 4-7 days once the source is controlled; at least 2 weeks for enterococcal or streptococcal bacteremia, because of the endocarditis risk.
Organism-level review: Enterococcus and the antibiotic coverage hub.
Look-alikes: how the stem tells them apart
| Condition | Clues | Next step |
|---|---|---|
| Ascending cholangitis | Fever + jaundice + RUQ pain, cholestatic labs, dilated duct; may be septic | Antibiotics + ERCP |
| Choledocholithiasis without infection | Biliary pain and jaundice, cholestatic labs, no sepsis | ERCP stone clearance, then cholecystectomy |
| Acute cholecystitis | RUQ pain >6 hours, Murphy sign, low-grade fever; jaundice uncommon; wall thickening, pericholecystic fluid | Antibiotics + early cholecystectomy (cholecystitis tips) |
| Gallstone pancreatitis | Epigastric pain to the back; lipase >3 × upper limit | Supportive care; early ERCP only if cholangitis coexists; cholecystectomy before discharge if mild |
| Pancreatic head cancer | Obstructive jaundice with weight loss, Courvoisier sign (palpable gallbladder), new diabetes | Pancreas-protocol CT (pancreatic cancer) |
| Primary sclerosing cholangitis | Young man with ulcerative colitis, high ALP, p-ANCA, beaded ducts on MRCP | MRCP; about 40% develop bacterial cholangitis (PSC breakdown) |
How USMLE twists the stem
- No jaundice, Murphy sign, normal duct → cholecystitis, not cholangitis.
- Fever + jaundice → cholangitis until proven otherwise, even without pain.
- Stable, mild, improving on antibiotics → ERCP to clear the stone (ASGE: within 48 hours), then cholecystectomy; MRCP first only if the diagnosis is uncertain.
- Septic, confused, on pressors → organ support + antibiotics + urgent drainage.
- ERCP failed or not possible → PTBD or EUS-guided drainage.
- UC patient with recurrent fevers and cholestasis → PSC with bacterial cholangitis; watch for cholangiocarcinoma.
Key takeaways
- Cholangitis = obstruction + infection of the bile duct, most often a common duct stone.
- Charcot (fever, RUQ pain, jaundice) is specific but insensitive; Reynolds adds shock and confusion.
- TG18 definite diagnosis = inflammation (A) + cholestasis (B) + imaging (C).
- Grade III = any organ dysfunction; Grade II = two of WBC, fever ≥39°C, age ≥75, bilirubin ≥5, low albumin.
- Drain the duct: ERCP preferred (ASGE), within 48 hours; urgent once stabilized in Grade III; PTBD if ERCP fails.
- Antibiotics cover enteric gram-negatives (± anaerobes, ± Enterococcus); 4-7 days after source control.
- Cholecystectomy after recovery to prevent recurrence.
Sources
- Tokyo Guidelines 2018 (TG18): links to the free full texts of the TG18 papers — Japanese Society of Hepato-Biliary-Pancreatic Surgery (2018)
- Table 5, Diagnosis of Cholangitis: Tokyo Guidelines 2018 — Evaluation and Management of Gallstone-Related Diseases in Non-Pregnant Adults, Michigan Medicine, NCBI Bookshelf (2021)
- ASGE guideline on the management of cholangitis — Gastrointestinal Endoscopy (2021)
- Choledocholithiasis and Cholangitis — Merck Manual Professional Edition (2025)
- Cholangitis — StatPearls, NCBI Bookshelf (2023)
- Acute Cholecystitis — Merck Manual Professional Edition (2025)
- Primary Sclerosing Cholangitis (PSC) — Merck Manual Professional Edition (2026)
- Acute Pancreatitis — Merck Manual Professional Edition (2026)
- Pancreatic Cancer — Merck Manual Professional Edition (2025)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
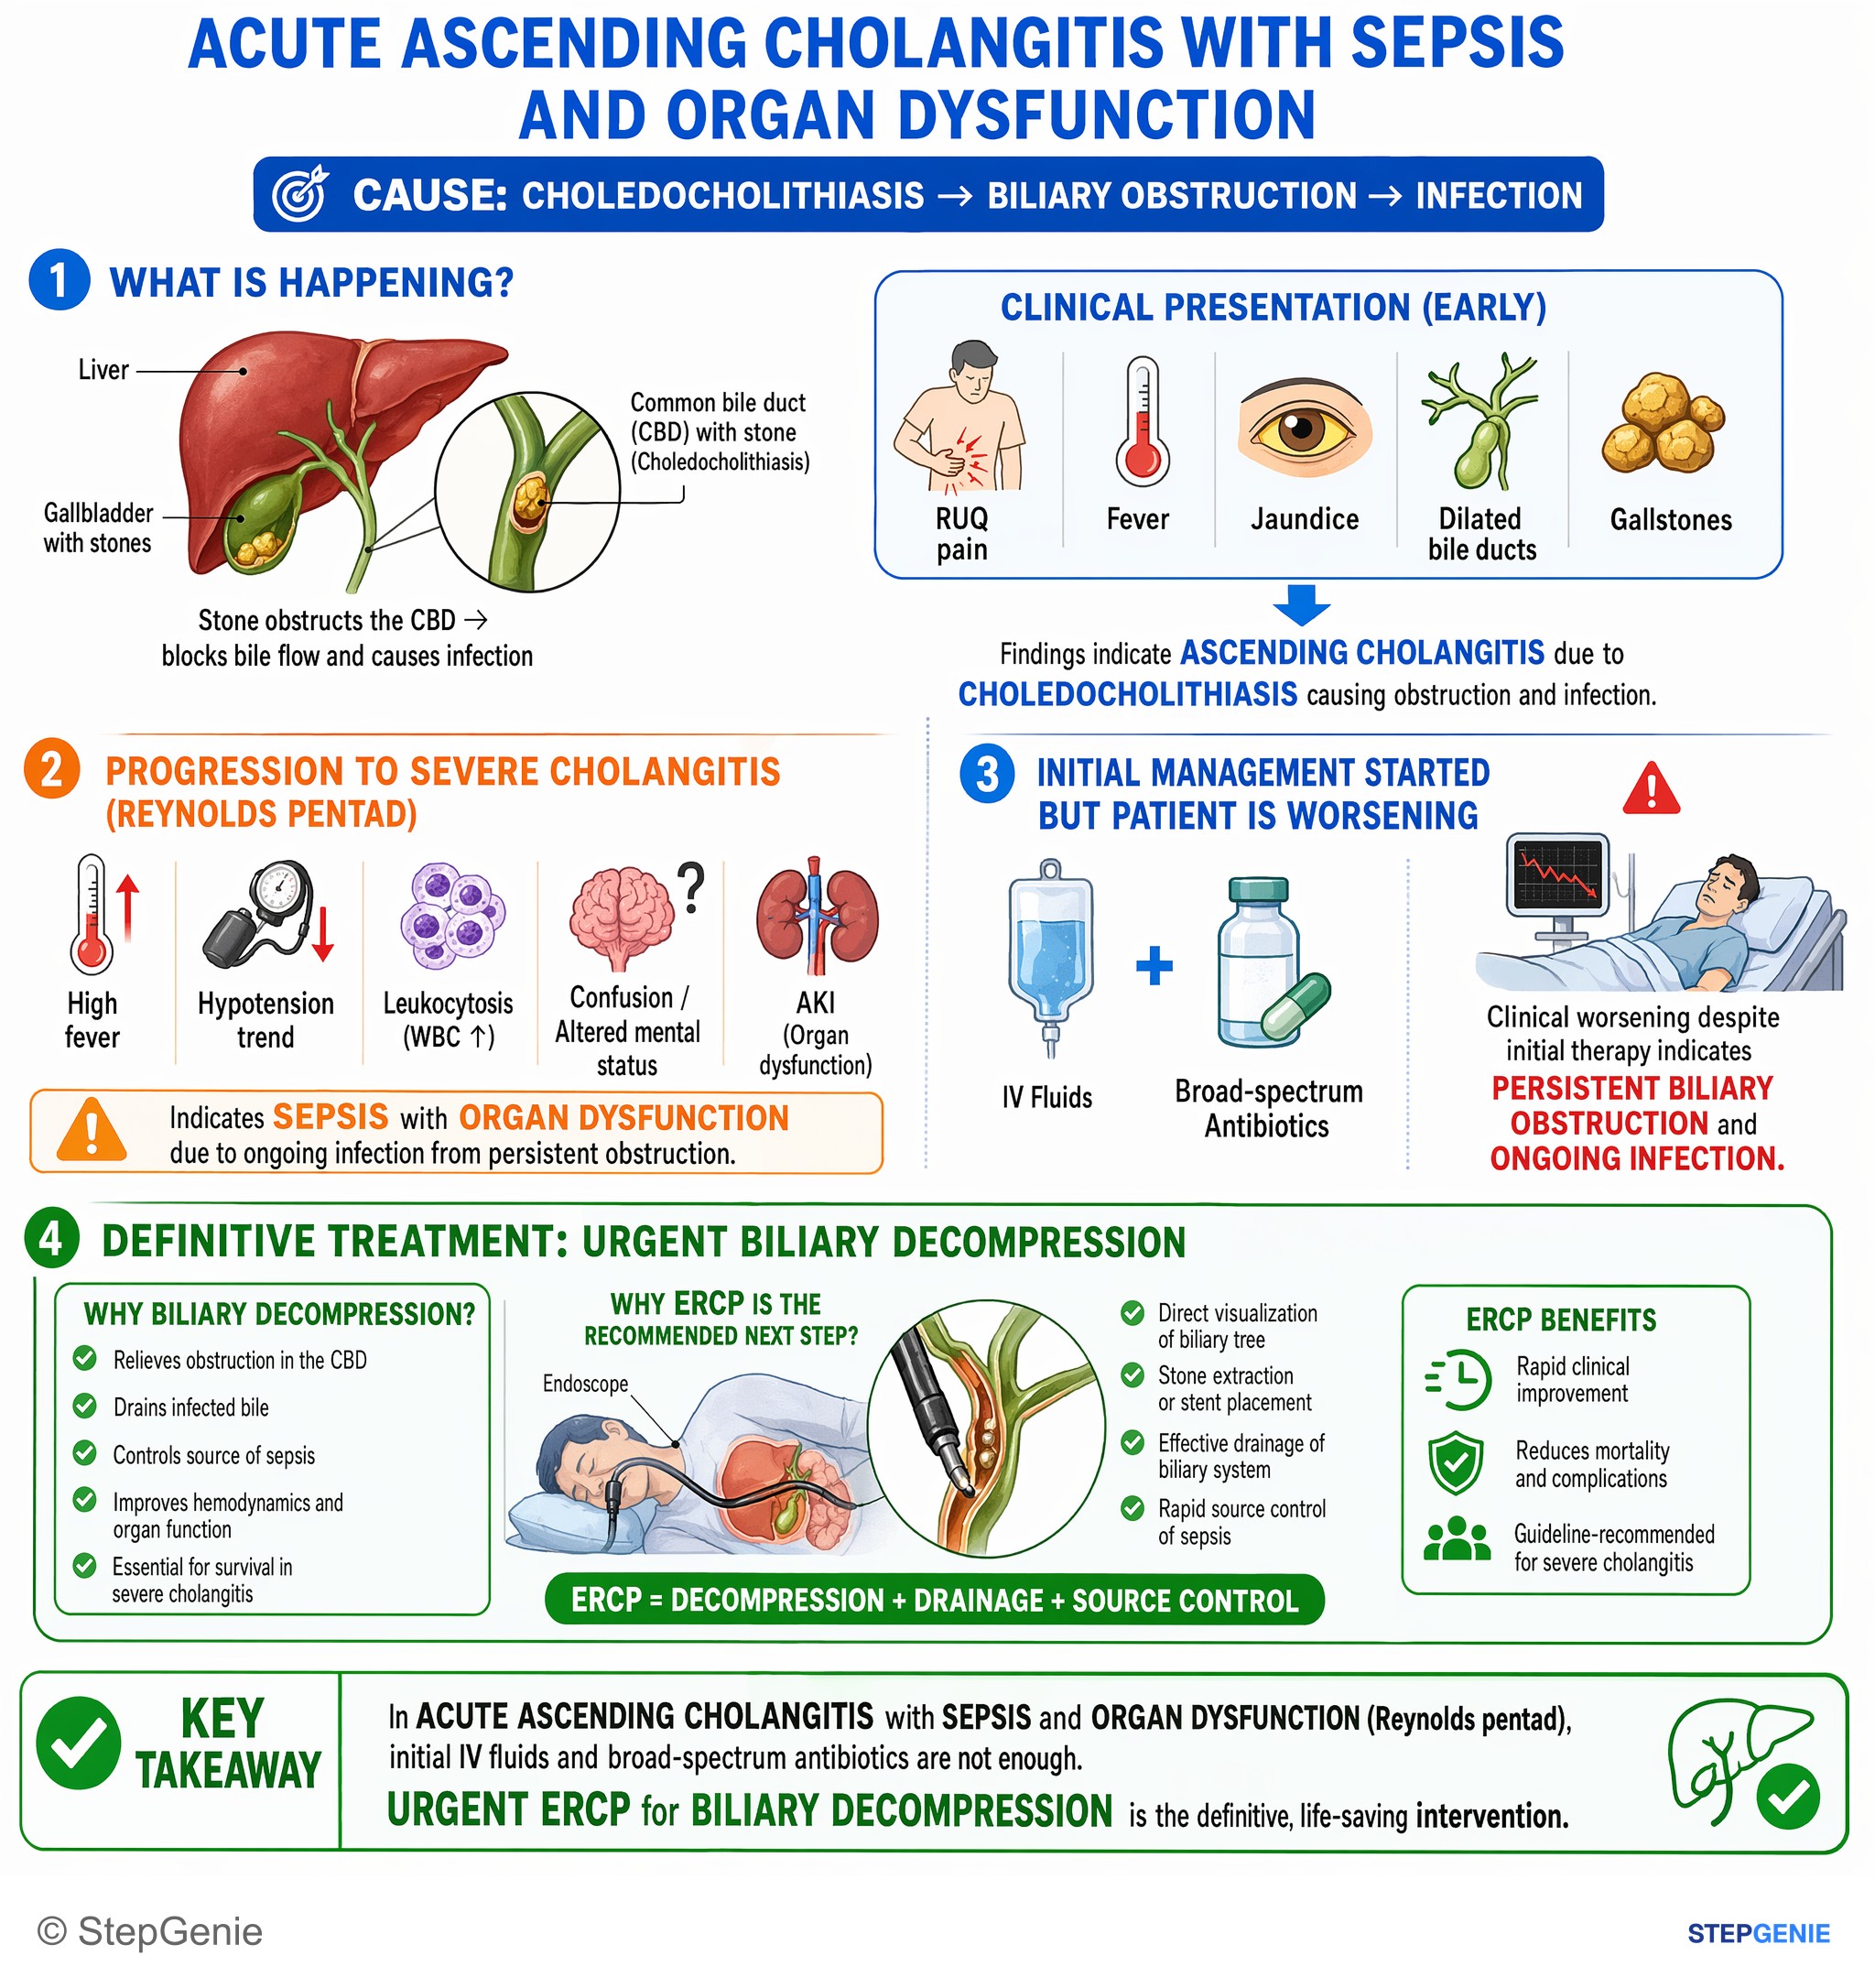
Acute ascending cholangitis with sepsis and organ dysfunction requires urgent ERCP for biliary decompression after initial…
USMLE Step 2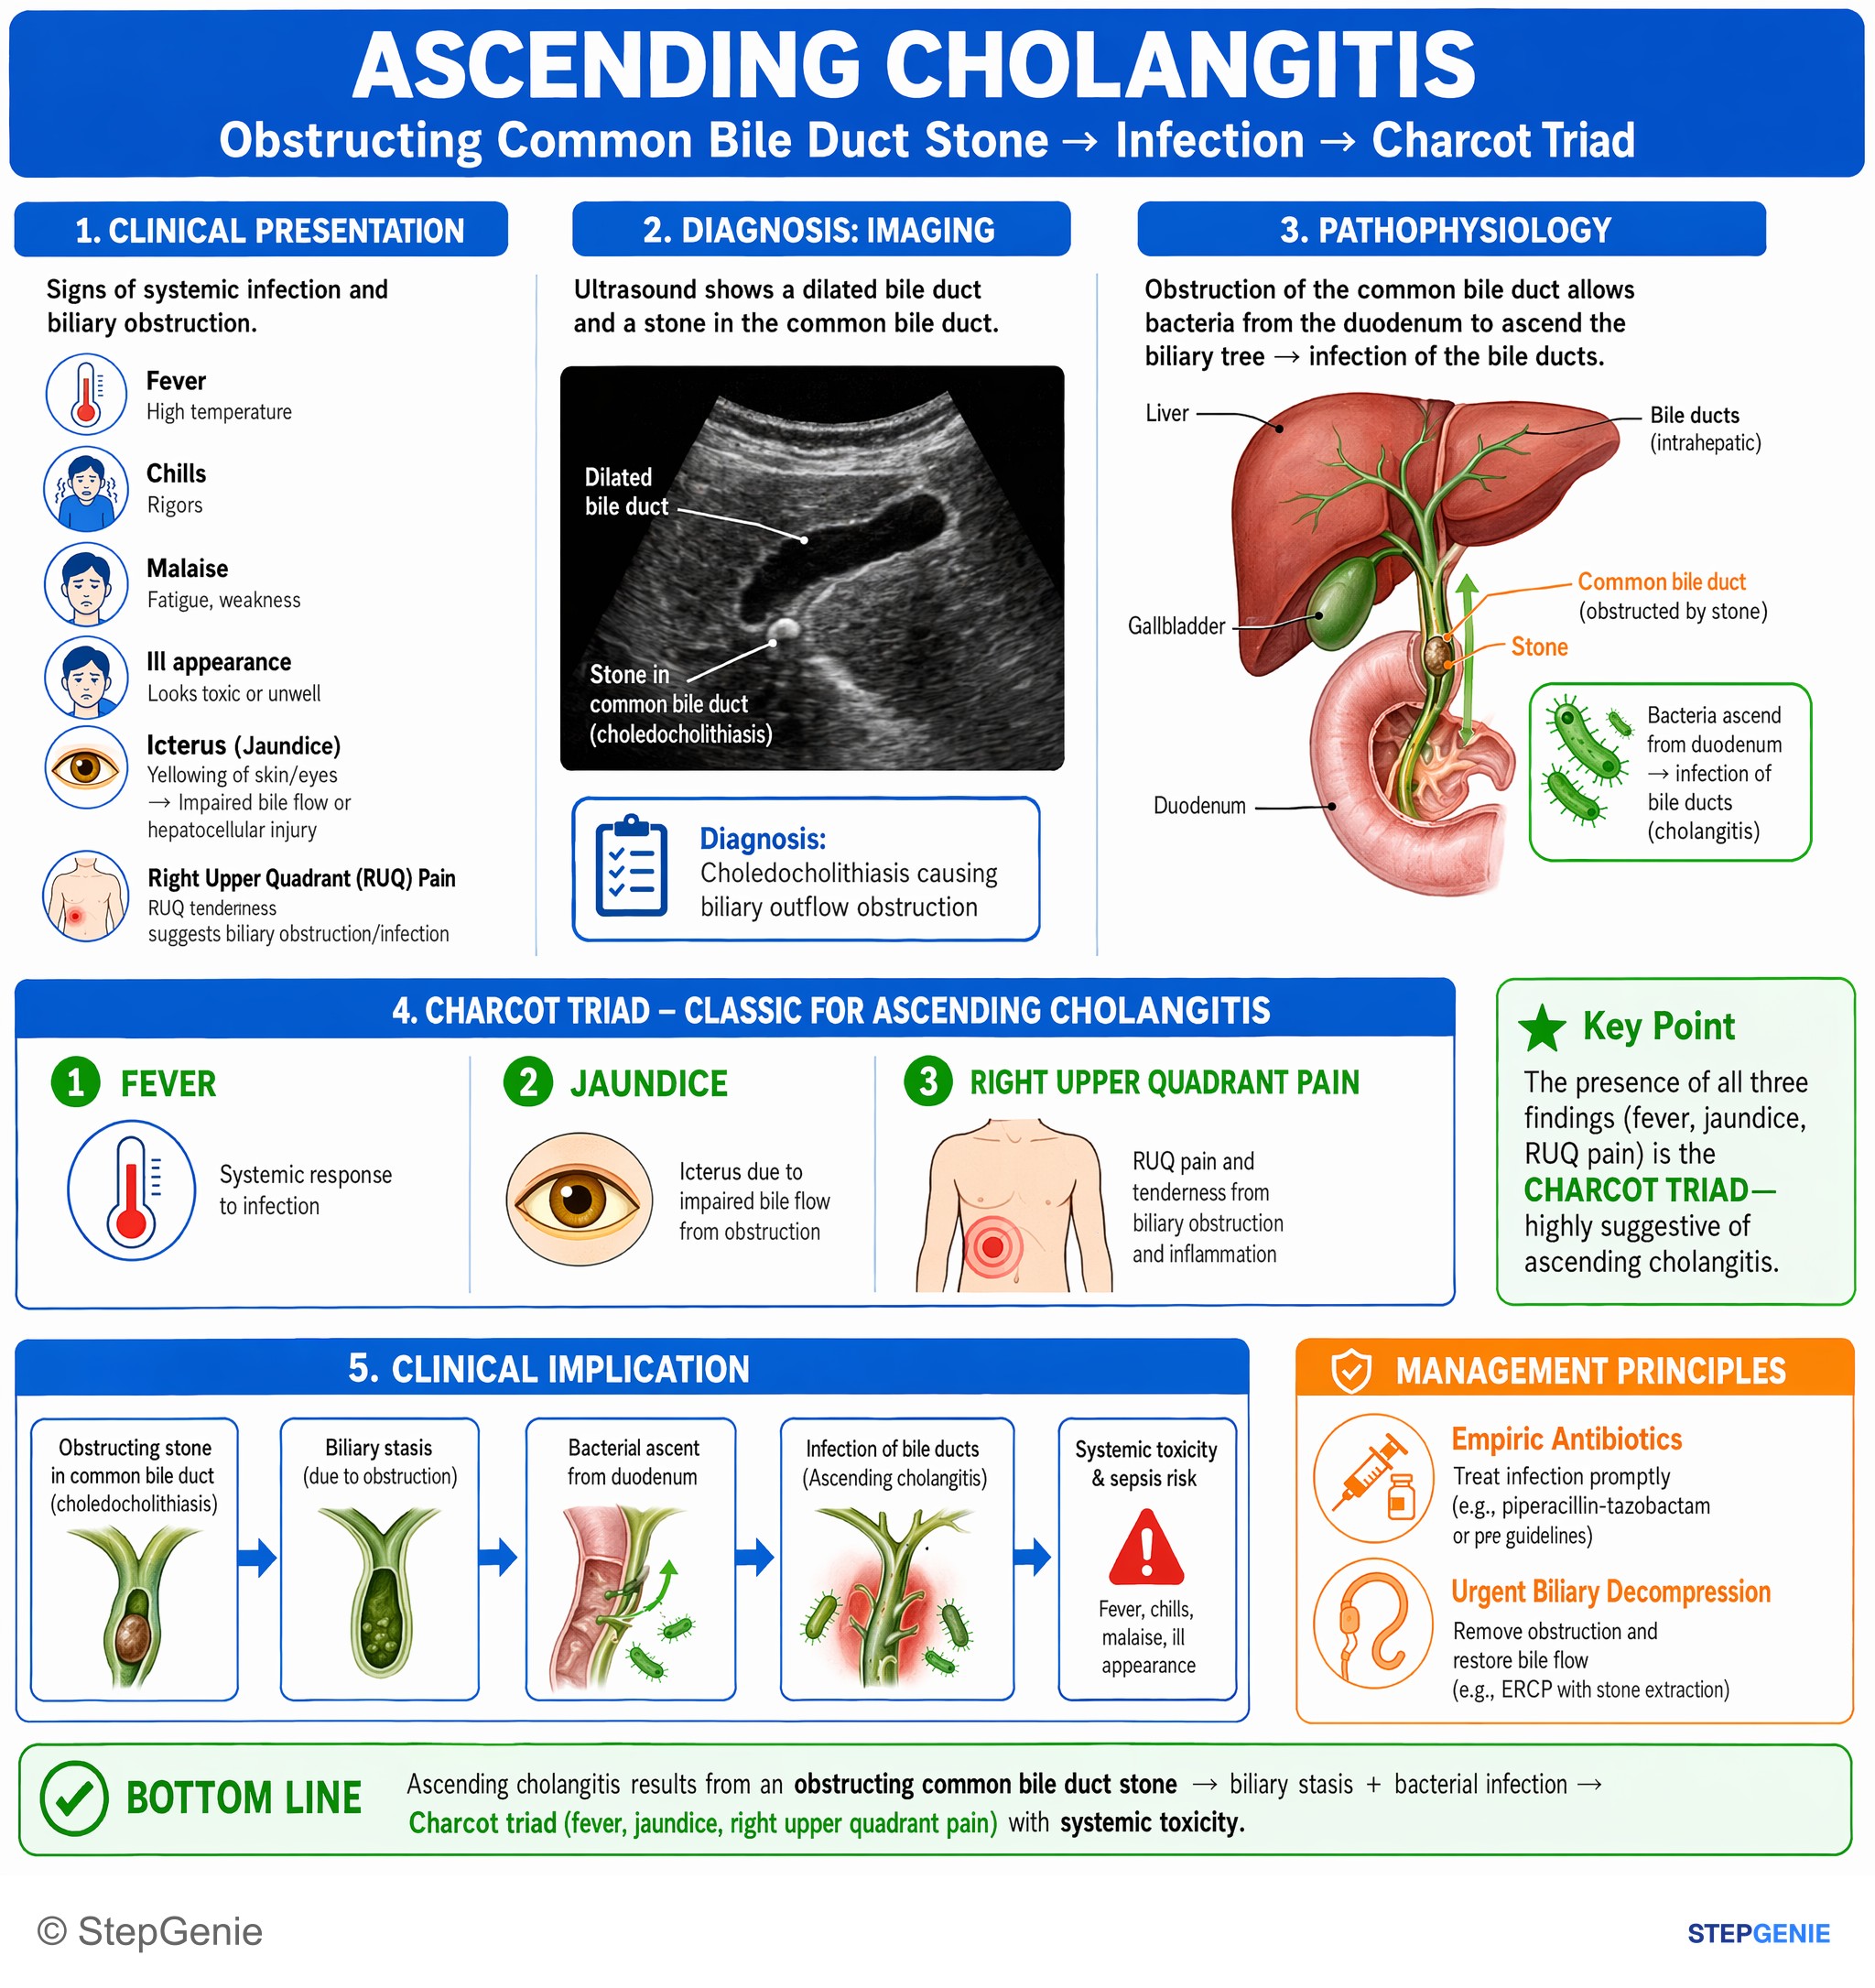
Ascending cholangitis from obstructing common bile duct stone → biliary stasis + infection → Charcot triad: fever, jaundice, right upper…
USMLE Step 1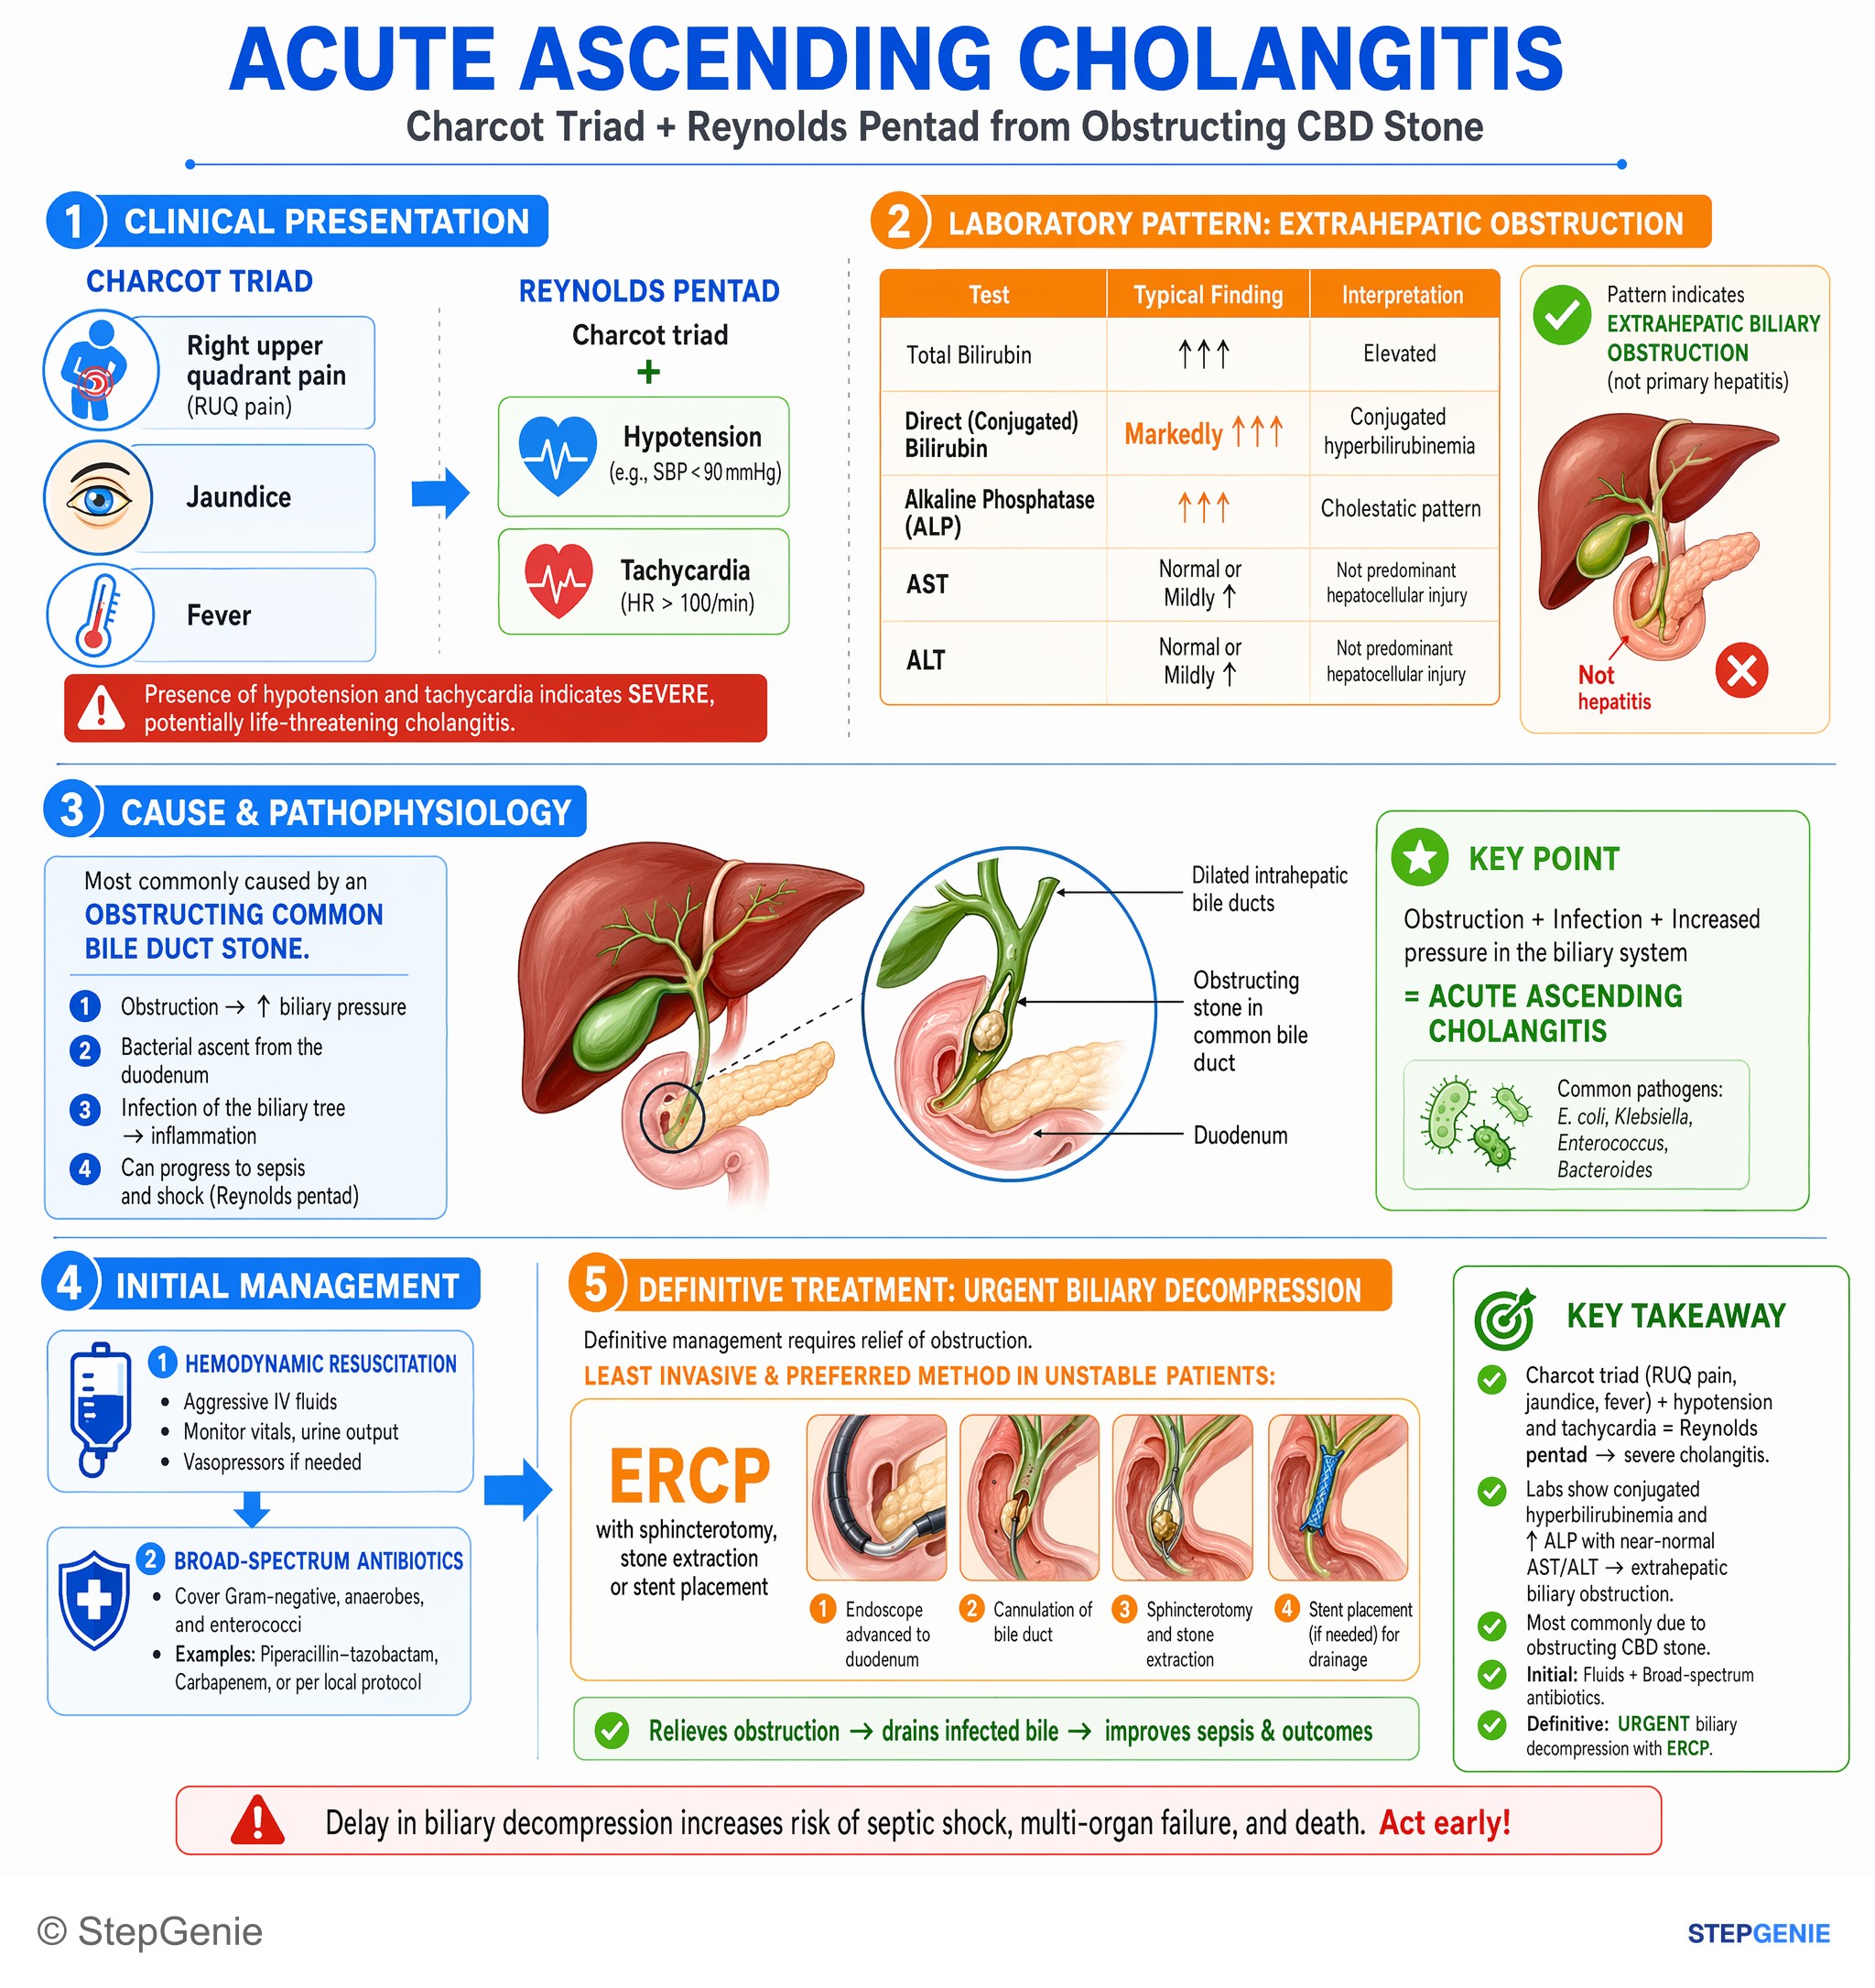
Acute ascending cholangitis (Charcot + Reynolds pentad) from obstructing stone needs urgent biliary decompression with ERCP after…
USMLE Step 2Frequently Asked Questions
What is the difference between Charcot triad and Reynolds pentad?
Charcot triad is fever with chills, right upper quadrant pain and jaundice, the classic picture of ascending cholangitis. It is highly specific (about 96%) but insensitive (about 26%), so many patients with cholangitis do not have all three. Reynolds pentad adds hypotension and altered mental status, which signals septic, severe cholangitis. A patient with Reynolds pentad needs resuscitation, IV antibiotics and urgent biliary drainage, usually by ERCP, once stabilized.
What are the Tokyo Guidelines 2018 criteria for acute cholangitis?
TG18 uses three domains. A is systemic inflammation: fever above 38°C or shaking chills, or a WBC below 4,000 or above 10,000 per microliter or CRP of 1 mg/dL or more. B is cholestasis: bilirubin of 2 mg/dL or more, or ALP, GGT, AST or ALT above 1.5 times the upper limit of normal. C is imaging: a dilated bile duct or a visible cause such as a stone, stricture or stent. One item from A plus B or C is suspected cholangitis; one from each is definite.
How is acute cholangitis graded under the Tokyo Guidelines?
Grade III (severe) means any organ dysfunction: hypotension needing dopamine at 5 µg/kg/min or more or any norepinephrine, impaired consciousness, PaO2/FiO2 below 300, oliguria or creatinine above 2.0 mg/dL, INR above 1.5, or platelets below 100,000. Grade II (moderate) means any two of: WBC above 12,000 or below 4,000, fever of 39°C or more, age 75 or older, bilirubin of 5 mg/dL or more, or low albumin. Everything else is Grade I (mild).
What is the best next step in a patient with ascending cholangitis?
After blood cultures, fluids and IV antibiotics, the key step is biliary drainage, usually ERCP with sphincterotomy and stone extraction or a stent. Under TG18, mild cases often settle on antibiotics and are drained if they don't respond, moderate cases get early drainage, and severe cases get urgent drainage as soon as organ support has stabilized them. ASGE suggests ERCP within 48 hours and prefers it to percutaneous drainage, which is the backup when ERCP fails.
Which antibiotics treat cholangitis, and for how long?
Empiric therapy covers enteric gram-negative rods. For mild to moderate community-acquired cases, TG18 lists options such as ceftriaxone or cefotaxime with or without metronidazole. Severe or healthcare-associated cases get piperacillin-tazobactam, cefepime or ceftazidime with or without metronidazole, or a carbapenem, plus vancomycin for Enterococcus. Anaerobic coverage is added if there is a biliary-enteric anastomosis. Treat for 4 to 7 days after the obstruction is drained, or at least 2 weeks for enterococcal or streptococcal bacteremia.
How do you tell cholangitis from acute cholecystitis on an exam?
Cholangitis is an infected, blocked common bile duct: fever, jaundice, a cholestatic lab pattern and a dilated duct, sometimes with shock or confusion, treated with antibiotics and ERCP. Acute cholecystitis is an inflamed gallbladder behind a blocked cystic duct: right upper quadrant pain lasting more than 6 hours, a positive Murphy sign, low-grade fever, gallbladder wall thickening or pericholecystic fluid, and usually no significant jaundice. It is treated with antibiotics and early cholecystectomy.