Hemochromatosis is one of those Step 1 “iron overload” topics that looks simple on the surface, but it’s packed with testable pathophysiology, classic symptom clusters, and lab-pattern recognition. If you can connect iron regulation (hepcidin/ferroportin) to organ deposition, you’ll be able to answer most hemochromatosis questions—even when they’re disguised.
Where Hemochromatosis Fits (GI → Hepatic Disorders)
Hemochromatosis is a systemic iron overload disorder that commonly presents as a hepatic disease on exams because the liver is a major iron storage site and a frequent site of injury (fibrosis → cirrhosis → hepatocellular carcinoma).
Step framing: Think “chronic iron deposition” → cirrhosis + diabetes + skin pigmentation + cardiomyopathy + hypogonadism/arthropathy.
Definition (What It Is)
Hemochromatosis is pathologic iron overload leading to tissue deposition of iron (hemosiderin) and progressive organ damage.
Types
- Primary (hereditary) hemochromatosis (HH)
- Usually due to HFE gene mutation (classically C282Y)
- Autosomal recessive
- Secondary iron overload
- Repeated transfusions (e.g., thalassemia major)
- Chronic hemolysis / ineffective erythropoiesis
- Certain anemias requiring transfusion support
High-yield distinction: Hereditary hemochromatosis = increased intestinal iron absorption; transfusional overload = iron loading from exogenous iron.
Core Pathophysiology (The “Why” That Drives Every Question)
Normal iron regulation in one line
The liver makes hepcidin, which inhibits ferroportin (the iron exporter) → decreases iron absorption from gut and decreases iron release from macrophages.
Hereditary hemochromatosis mechanism (Step 1 favorite)
- HFE mutation → inappropriately low hepcidin (or impaired hepcidin signaling)
- ↓ hepcidin → uninhibited ferroportin
- ↑ ferroportin activity → increased iron absorption from duodenum + increased iron release into plasma
- ↑ transferrin saturation → excess iron deposits in organs as hemosiderin
- Iron catalyzes free radical formation (Fenton chemistry) → oxidative damage, inflammation, fibrosis
Quick flow diagram
HFE mutation → ↓ hepcidin → ↑ ferroportin → ↑ iron absorption → ↑ transferrin saturation → iron deposition → organ dysfunction
Clinical Presentation (Classic Clues + How They Test It)
Hemochromatosis is often silent early and presents later with vague symptoms like fatigue, arthralgias, or abnormal LFTs. Boards love the “cluster” presentation.
Classic symptom cluster (know cold)
- Cirrhosis
- Diabetes mellitus (“bronze diabetes”)
- Skin hyperpigmentation (bronze/gray)
- Cardiomyopathy (often dilated) → arrhythmias, heart failure
- Hypogonadism (pituitary or gonadal iron deposition) → decreased libido, impotence, amenorrhea
- Arthropathy
- Classically involves 2nd and 3rd MCP joints (a favorite detail)
Physical/exam vignettes you’ll see
- Middle-aged patient with fatigue + arthralgia + “elevated liver enzymes”
- “Bronze” skin, new diabetes, and hepatomegaly
- Heart failure symptoms with endocrine changes
- Family history consistent with AR inheritance
Diagnosis (Pattern Recognition = Points)
First-line screening labs (Step 1/2 high yield)
Most commonly tested lab pattern:
| Finding | Hemochromatosis |
|---|---|
| Transferrin saturation | Increased (often earliest abnormality) |
| Ferritin | Increased |
| Serum iron | Increased |
| TIBC | Normal to decreased |
| LFTs | May be elevated |
| Genetic testing | HFE mutation (e.g., C282Y) |
Key memory hook: Hemochromatosis = high ferritin + high transferrin saturation.
What confirms it?
- HFE genetic testing is commonly used to confirm hereditary disease in the right clinical setting.
- MRI can quantify hepatic iron (noninvasive quantification).
- Liver biopsy may be used when diagnosis is uncertain or to stage fibrosis; shows:
- Prussian blue staining positive for iron
- Iron deposition in hepatocytes (classically periportal early)
Common Step trap: ferritin is an acute phase reactant
Ferritin can be elevated in inflammation, infection, malignancy. That’s why transferrin saturation is particularly useful for hemochromatosis pattern recognition.
Treatment (What Actually Fixes It)
Hereditary hemochromatosis
- Therapeutic phlebotomy is first-line
- Removes iron by removing RBC mass → mobilizes stored iron to make new RBCs
- Lifestyle counseling:
- Avoid excess iron supplementation
- Avoid excess vitamin C supplementation (can increase iron absorption)
- Limit alcohol (synergistic liver injury)
Secondary iron overload (e.g., transfusion-related)
- Iron chelation therapy
- Deferoxamine, deferasirox, or deferiprone (drug selection depends on context)
High-yield rule:
Primary HH → phlebotomy.
Transfusion overload → chelation (because anemia often prevents phlebotomy).
High-Yield Associations & Complications (Boards Love These)
1) Increased risk of hepatocellular carcinoma (HCC)
- Chronic iron injury → cirrhosis → HCC
- If you see: hemochromatosis + weight loss + RUQ pain + elevated AFP → think HCC.
2) “Bronze diabetes”
- Pancreatic iron deposition → β-cell dysfunction
- Skin pigmentation + diabetes + cirrhosis = classic triad-ish presentation
3) Cardiomyopathy + arrhythmias
- Can present with heart failure symptoms, palpitations, conduction abnormalities
4) Arthropathy (2nd/3rd MCP)
- Often an early complaint and a clue in stem
5) Endocrinopathies
- Hypogonadotropic hypogonadism (pituitary) or primary gonadal dysfunction
- Symptoms: impotence, decreased libido, amenorrhea
6) Infectious risk (very testable)
Iron-loving organisms thrive:
- Vibrio vulnificus (classically from raw oysters/seawater exposure)
- Yersinia enterocolitica
If the vignette is “raw oyster ingestion → severe sepsis in patient with iron overload,” this is the association they want.
Differentials You Must Separate From Hemochromatosis
Hemochromatosis vs Wilson disease (common confusion)
| Feature | Hemochromatosis | Wilson |
|---|---|---|
| Metal | Iron | Copper |
| Key labs | ↑ ferritin, ↑ transferrin saturation | ↓ ceruloplasmin, ↑ urinary copper |
| Major organs | Liver, pancreas, heart, skin, joints | Liver, brain (basal ganglia), cornea |
| Classic clue | Bronze diabetes, MCP arthropathy | Kayser–Fleischer rings, neuro/psych |
Hemochromatosis vs anemia of chronic disease (ACD)
ACD can have high ferritin, but typically:
- Low serum iron
- Low TIBC
- Low transferrin saturation
Hemochromatosis: iron measures trend up, especially transferrin saturation.
First Aid–Style Cross-References (How It’s Commonly Organized)
Use these as mental “tabs” when you’re flipping through First Aid:
- GI → Liver pathology: cirrhosis complications, HCC risk
- Heme/Onc → Iron studies: ferritin, transferrin saturation, TIBC patterns
- Endocrine: diabetes mellitus, hypogonadism
- Cardio: dilated cardiomyopathy/arrhythmias
- Micro: Vibrio vulnificus and Yersinia associations in iron overload states
(FA may place the core hemochromatosis blurb under liver disease or iron metabolism; either way, the question stems pull in multiple systems.)
USMLE-Style “If You See X, Think Y” Rapid Hits
- High transferrin saturation early → hereditary hemochromatosis is likely
- Cirrhosis + diabetes + bronze skin → iron overload until proven otherwise
- 2nd/3rd MCP pain in middle-aged patient + abnormal LFTs → HH clue
- Transfusion-dependent anemia + iron overload labs → treat with chelation
- Raw oysters + septic shock in iron overload patient → Vibrio vulnificus
- HH is autosomal recessive, often C282Y mutation in HFE
Quick Summary Table (Exam-Day Snapshot)
| Category | High-yield takeaways |
|---|---|
| Cause | HFE mutation (C282Y), AR → ↓ hepcidin → ↑ ferroportin → ↑ iron absorption |
| Main lab pattern | ↑ transferrin saturation, ↑ ferritin (often earliest is ↑ transferrin saturation) |
| Key organs | Liver (cirrhosis/HCC), pancreas (DM), heart (DCM/arrhythmias), skin (bronzing), joints (MCP), pituitary/gonads |
| Diagnosis | Iron studies → HFE genetic testing; MRI/biopsy as needed (Prussian blue) |
| Treatment | Phlebotomy (primary); chelation (secondary/transfusion) |
| Associations | Vibrio vulnificus, Yersinia enterocolitica, HCC risk |
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
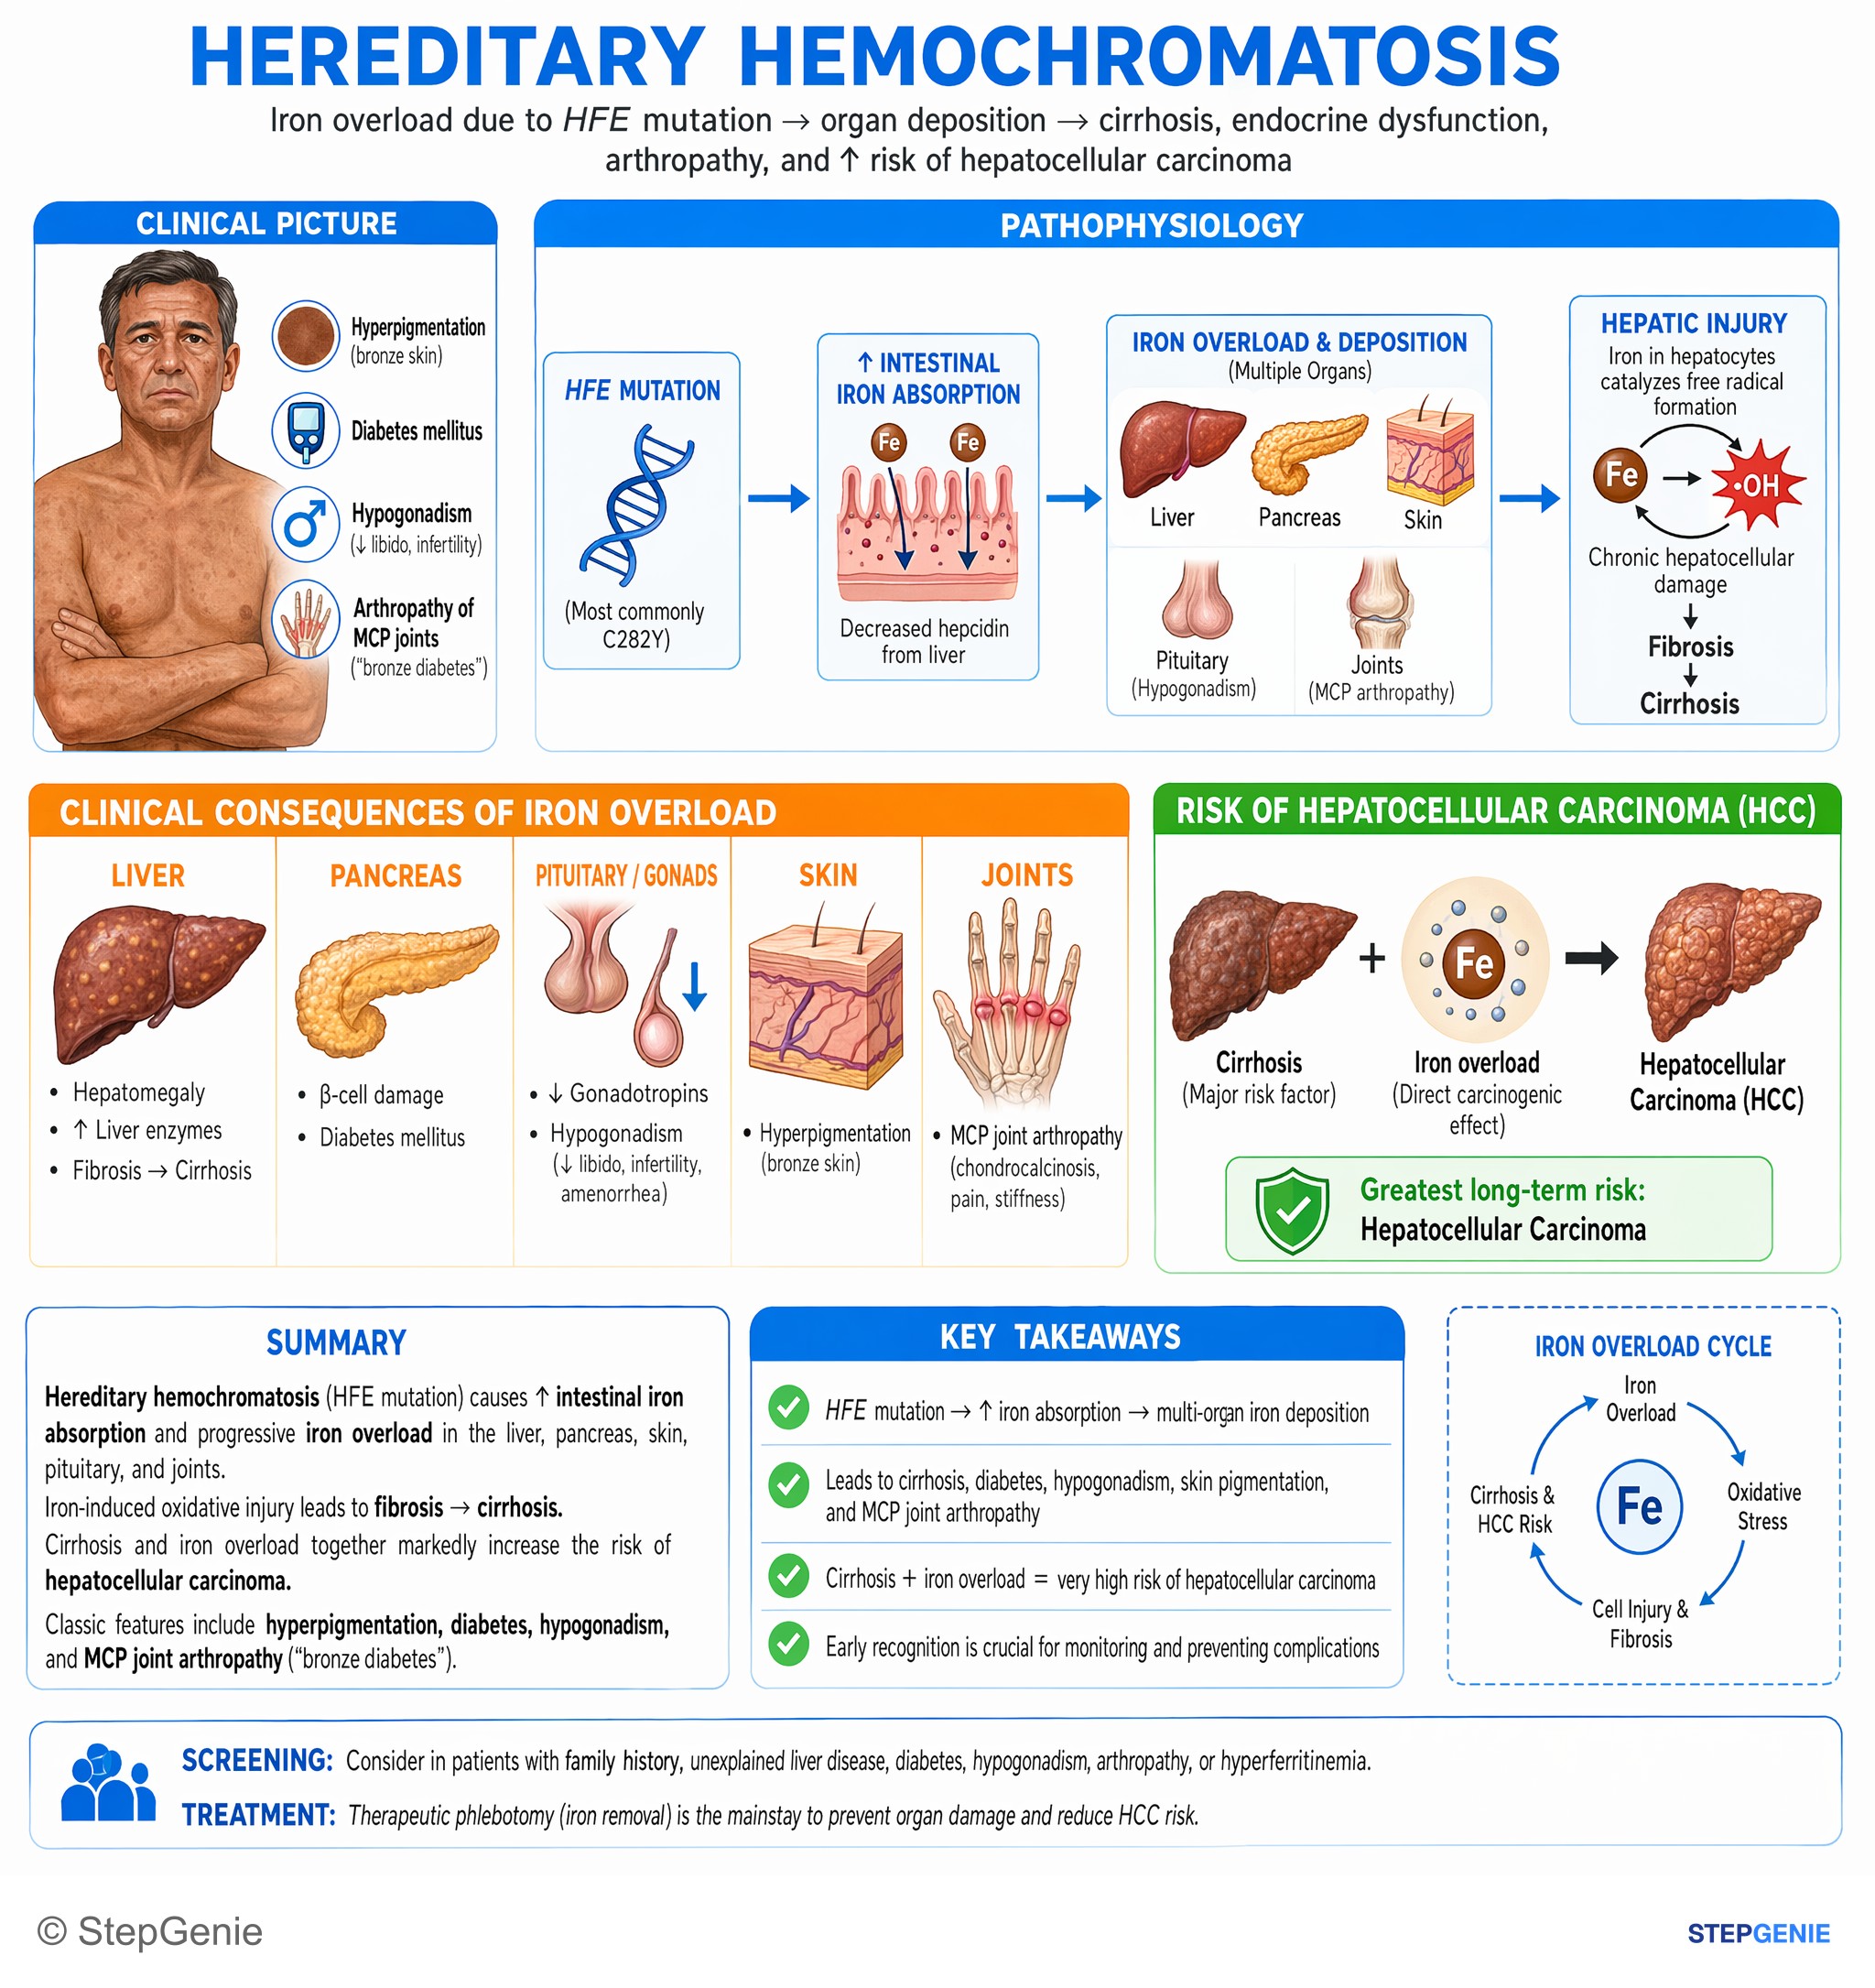
Hereditary hemochromatosis causes iron overload → cirrhosis, diabetes, hypogonadism, arthropathy → greatly increased risk of…
USMLE Step 1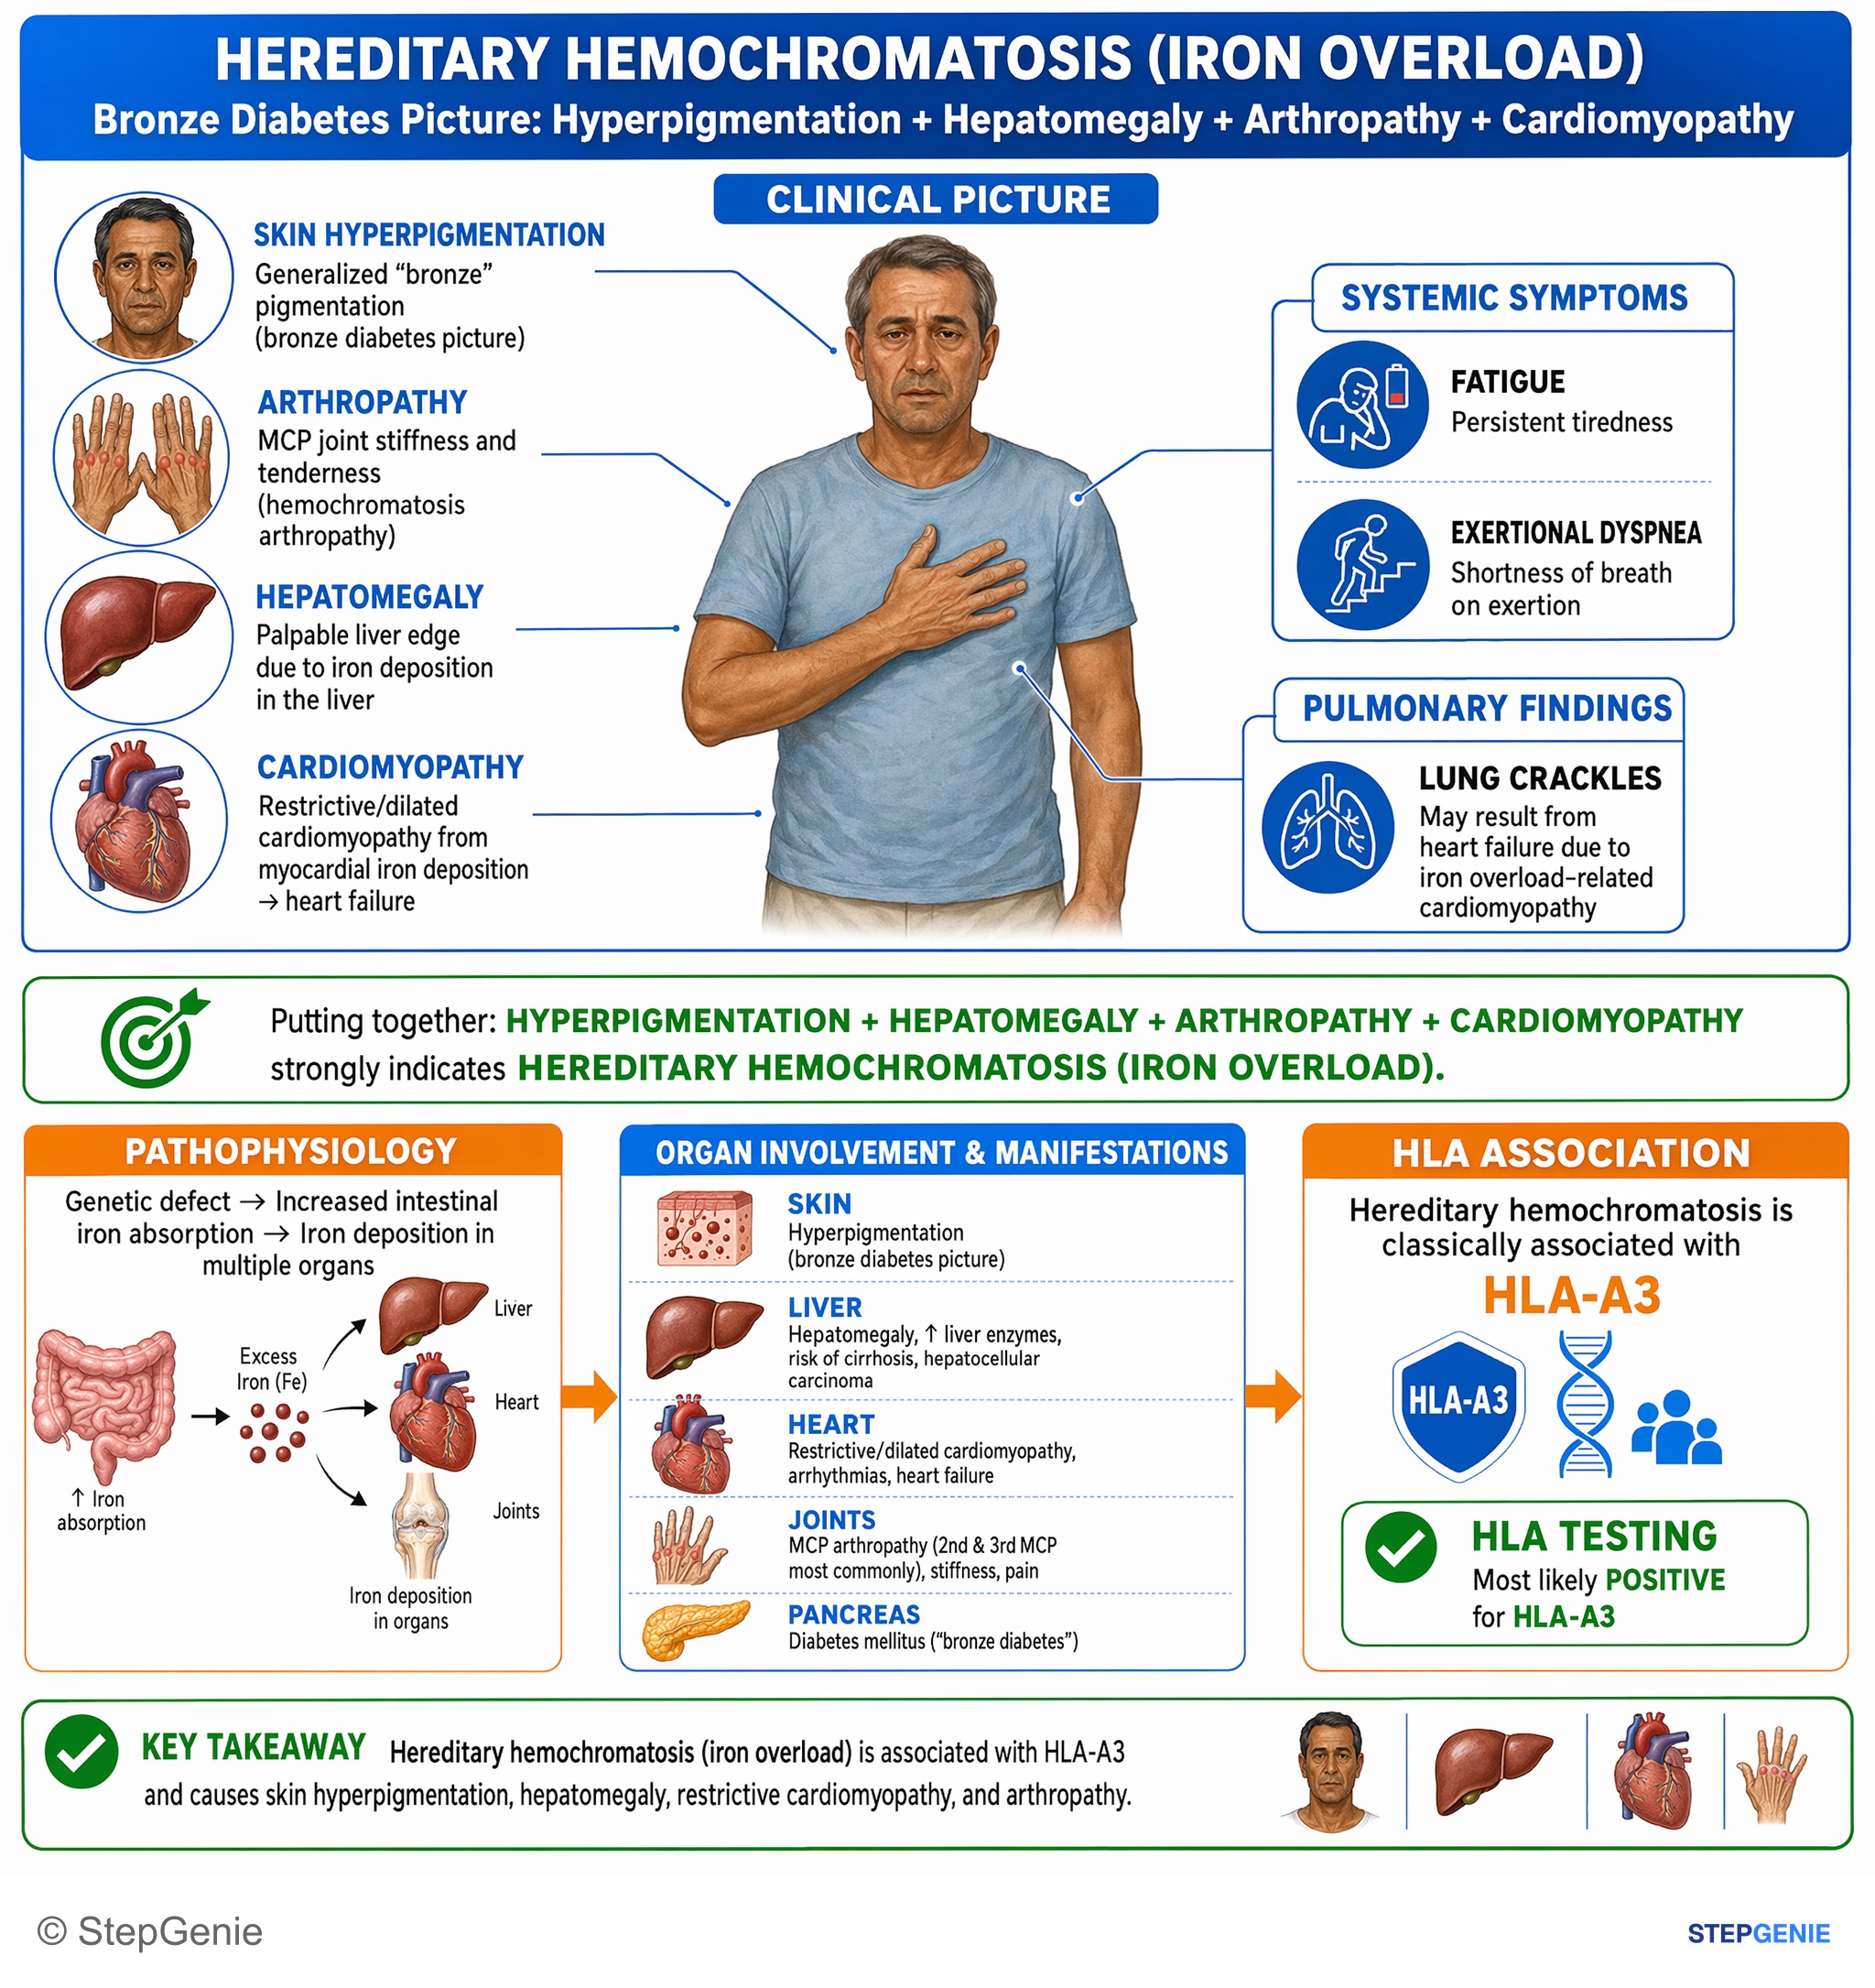
Hereditary hemochromatosis (iron overload) is associated with HLA-A3, causing skin hyperpigmentation, hepatomegaly, restrictive…
USMLE Step 1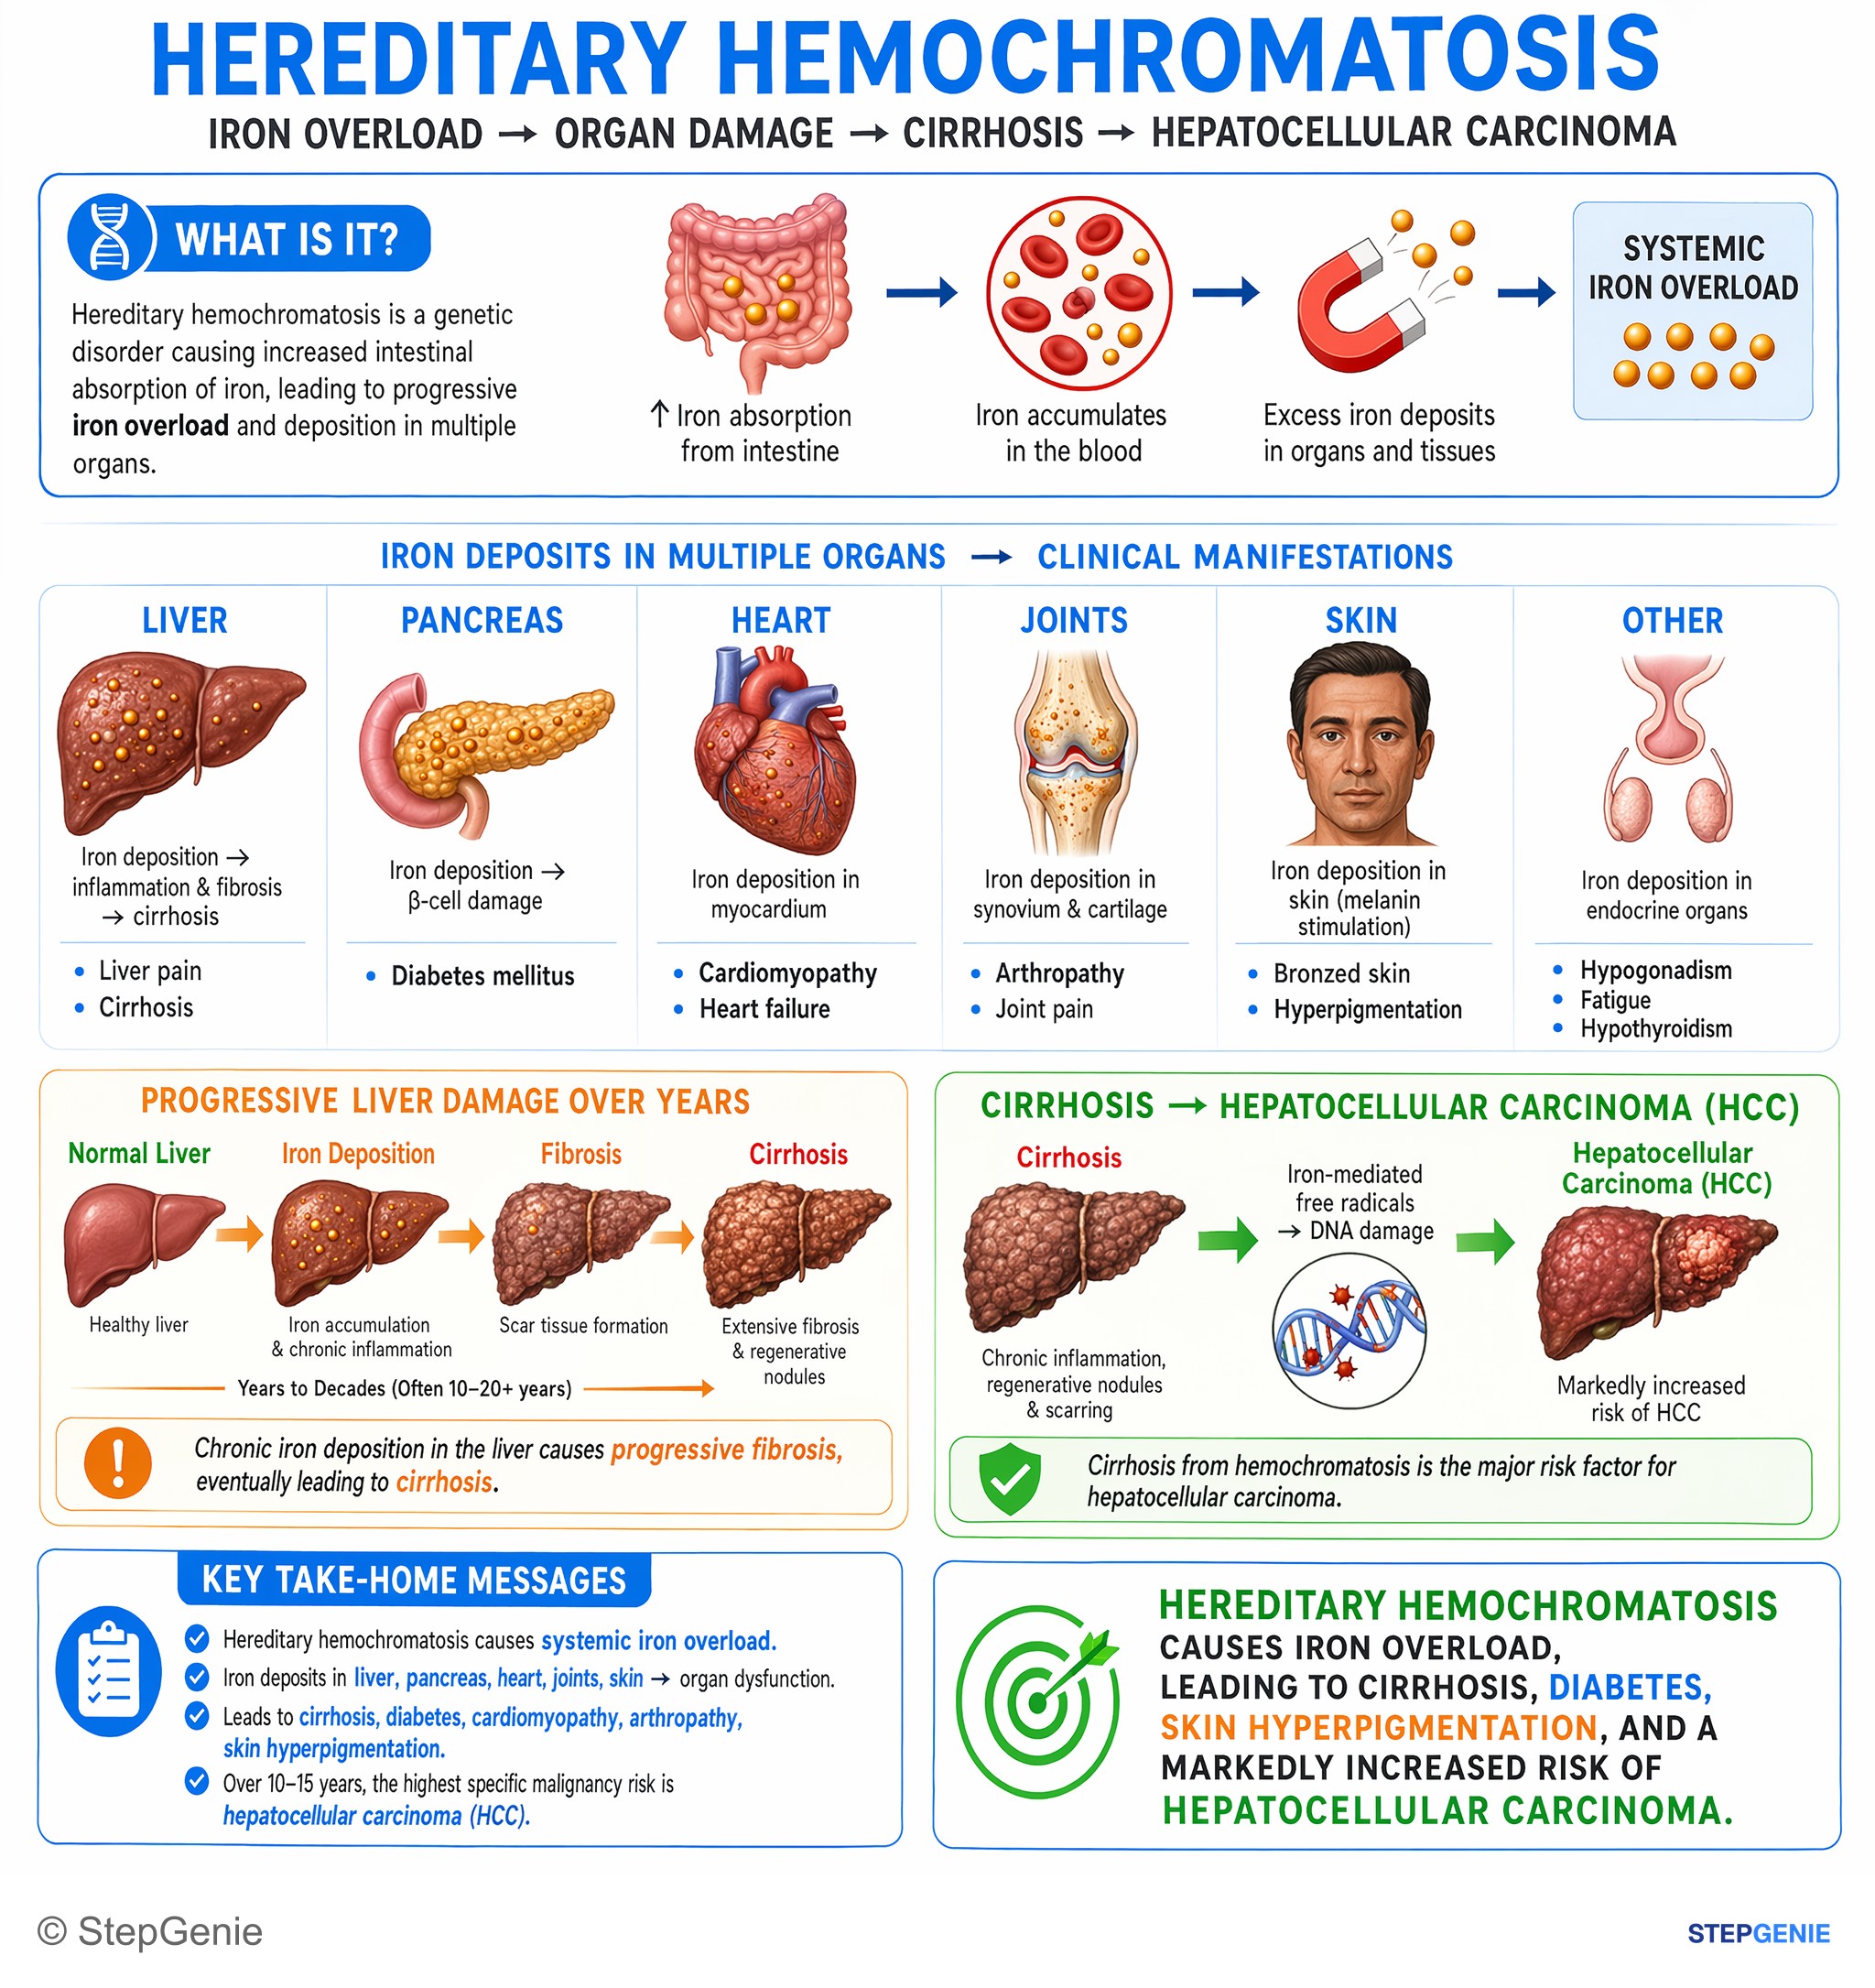
Hereditary hemochromatosis causes iron overload, leading to cirrhosis, diabetes, skin hyperpigmentation, and markedly increased risk of…
USMLE Step 1Frequently Asked Questions
Why does hereditary hemochromatosis cause iron overload?
Hereditary hemochromatosis causes iron overload because HFE mutation leads to inappropriately low hepcidin or impaired hepcidin signaling. Low hepcidin leaves ferroportin uninhibited, so more iron is absorbed from the duodenum and released into plasma from macrophages. The resulting rise in transferrin saturation causes iron to deposit in tissues as hemosiderin, leading to oxidative damage, inflammation, fibrosis, and organ dysfunction.
What is the classic presentation of hemochromatosis on exams?
The classic exam presentation is chronic iron deposition causing cirrhosis, diabetes, and skin hyperpigmentation, often with cardiomyopathy, hypogonadism, or arthropathy. Boards may also describe fatigue, arthralgias, abnormal liver enzymes, hepatomegaly, or heart failure symptoms. A favorite clue is arthropathy involving the 2nd and 3rd MCP joints, especially in a middle-aged patient with liver and endocrine findings.
What lab pattern suggests hemochromatosis?
The key lab pattern is increased transferrin saturation with increased ferritin. Serum iron is also increased, TIBC is normal to decreased, and liver enzymes may be elevated. Transferrin saturation is especially useful because ferritin can rise in inflammation, infection, or malignancy as an acute phase reactant, so high ferritin alone is less specific for recognizing hemochromatosis.
How is hereditary hemochromatosis confirmed?
Hereditary hemochromatosis is commonly confirmed with HFE genetic testing in the right clinical setting. MRI can noninvasively quantify hepatic iron, and liver biopsy may be used when the diagnosis is uncertain or when fibrosis staging is needed. On biopsy, Prussian blue staining is positive for iron, and iron deposition is classically seen in hepatocytes, often periportal early on.
What is the first-line treatment for hemochromatosis, and how is it different from transfusional iron overload?
First-line treatment for hereditary hemochromatosis is therapeutic phlebotomy. Removing red blood cell mass forces the body to mobilize stored iron to make new RBCs, lowering iron burden. In contrast, secondary iron overload from repeated transfusions is treated with iron chelation therapy such as deferoxamine, deferasirox, or deferiprone, because anemia often prevents phlebotomy in those patients.