Alpha-1 antitrypsin (A1AT) deficiency is one of those USMLE favorites because it’s one mutation with two organs—lungs and liver—and the exam loves asking you to connect the dots. Most people remember the emphysema, but Step questions often pivot to the hepatic story: misfolded protein gets trapped in hepatocytes, causing hepatitis, cirrhosis, and hepatocellular carcinoma (HCC). If you can explain why the liver is injured despite low serum A1AT, you’re already ahead.
Where this fits (GI → Hepatic Disorders)
A1AT deficiency is a genetic hepatic disorder where hepatocyte injury occurs due to protein misfolding and intracellular accumulation rather than immune attack or toxin-mediated injury.
High-yield framing:
- Liver disease = toxic gain-of-function (A1AT polymer accumulation in hepatocytes)
- Lung disease = loss-of-function (low A1AT → unchecked elastase activity)
Definition (Step-style)
Alpha-1 antitrypsin deficiency is an autosomal codominant disorder caused by mutations in SERPINA1, leading to:
- Low circulating A1AT, and
- Accumulation of misfolded A1AT in hepatocyte ER, causing liver injury.
Pathophysiology (the “why” that Step loves)
Normal role of A1AT
A1AT is a serine protease inhibitor produced mainly in the liver. In the lungs it inhibits:
- Neutrophil elastase (and other proteases)
What goes wrong in the liver
Certain mutant A1AT proteins (classically the Z allele) misfold and polymerize, getting stuck in the endoplasmic reticulum of hepatocytes.
Result: hepatocyte stress → inflammation → fibrosis → cirrhosis → ↑ risk of HCC.
Key paradox to memorize: Serum A1AT is low, yet liver cells are packed with A1AT.
Classic histology clue (very high yield)
- PAS-positive, diastase-resistant globules in hepatocytes
- PAS stains glycoproteins; diastase digests glycogen (so these are not glycogen).
Genetics and inheritance (quick but testable)
| Feature | High-yield detail |
|---|---|
| Inheritance | Autosomal codominant |
| Gene | SERPINA1 |
| Common severe phenotype | PiZZ (classically associated with worse disease) |
| Organ pattern | Liver + lung (but questions may isolate one) |
Codominant is a frequent NBME detail: heterozygotes can have intermediate levels and variable disease.
Clinical presentation (liver-focused)
Neonates/infants
- Prolonged neonatal jaundice
- Cholestasis
- Elevated AST/ALT
- Possible hepatomegaly
- Some develop progressive liver disease; others improve and present later
Children/adolescents
- Chronic hepatitis picture
- Failure to thrive (sometimes)
- Signs of evolving portal HTN in advanced cases
Adults
- Cirrhosis (may be cryptogenic at first glance)
- Portal hypertension complications:
- Ascites
- Variceal bleeding
- Splenomegaly/thrombocytopenia
- Increased risk of hepatocellular carcinoma
Association to remember: Liver disease can occur even without significant lung symptoms, especially early in life.
Diagnosis (what they’ll hand you in the vignette)
Step-style diagnostic clues
- Elevated transaminases + cholestasis in a newborn/child with PAS+ diastase-resistant globules
- Low serum A1AT level
- Family history of liver disease or early COPD (not required)
Practical diagnostic approach
- Serum A1AT level (screening)
- Phenotyping/genotyping (confirmatory; identifies alleles like Z)
- Liver biopsy (not always required clinically, but a classic test question)
- Shows PAS+ diastase-resistant cytoplasmic inclusions
Don’t get trapped: “low A1AT” is not the whole story
Low A1AT explains emphysema, but liver pathology is from ER retention (misfolded protein).
Treatment and management (Step-relevant)
Liver disease management
- Supportive care for hepatitis/cholestasis
- Treat cirrhosis complications (ascites, varices, encephalopathy) per standard protocols
- Avoid hepatotoxins (especially alcohol; be cautious with meds)
Definitive therapy for severe hepatic disease
- Liver transplantation
- Replaces the defective A1AT-producing hepatocytes
- Can correct low serum A1AT (important concept: transplant changes systemic A1AT production)
What about A1AT augmentation therapy?
- IV A1AT augmentation is used for selected lung disease patients
- It does not fix the hepatic ER-accumulation problem
High-yield associations and classic USMLE patterns
The “two-organ” stem
A1AT deficiency classically links:
- Panacinar emphysema (lower lobes, early-onset, worse with smoking)
- Cirrhosis/HCC (PAS+ diastase-resistant globules)
Step writers love to add:
- Young adult with COPD symptoms + abnormal LFTs
- Infant with cholestatic jaundice + family history of early emphysema
Smoking is a force multiplier (lung)
Smoking increases neutrophil elastase burden and can worsen outcomes—commonly tested as “why did symptoms happen so early?”
Histology trigger words
If you see:
- “PAS-positive, diastase-resistant globules”
- “misfolded proteins in ER” Think A1AT liver disease immediately.
Differential diagnosis (to avoid mix-ups)
| Condition | Key distinguishing clue |
|---|---|
| Wilson disease | Low ceruloplasmin, neuro/psych sx, Kayser–Fleischer rings |
| Hemochromatosis | ↑ transferrin saturation, bronze diabetes, cardiomyopathy; iron deposition |
| Viral hepatitis | Exposure risks; serologies; no PAS+ globules |
| Biliary atresia | Progressive jaundice in infancy; pale stools; requires Kasai procedure |
| NAFLD/NASH | Metabolic syndrome; macrovesicular steatosis, ballooning degeneration |
First Aid cross-references (high-yield map)
In First Aid for the USMLE Step 1, A1AT deficiency is typically cross-listed in:
- GI — Liver pathology (A1AT deficiency → cirrhosis; PAS+ globules)
- Respiratory — Emphysema (panacinar, lower lobes, early onset)
- Genetics (autosomal codominant inheritance pattern often mentioned)
Study tip: When you review the FA emphysema section, force yourself to add one line in your margin:
“Misfolded A1AT trapped in ER → liver damage (PAS+ diastase-resistant)”.
Rapid review: what to recall in 15 seconds
- Autosomal codominant SERPINA1 mutation
- Misfolded A1AT accumulates in hepatocyte ER
- PAS+ diastase-resistant globules
- Causes neonatal cholestasis, hepatitis, cirrhosis, HCC
- Definitive severe liver disease tx: liver transplant
- (Often paired with panacinar emphysema, lower lobes)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
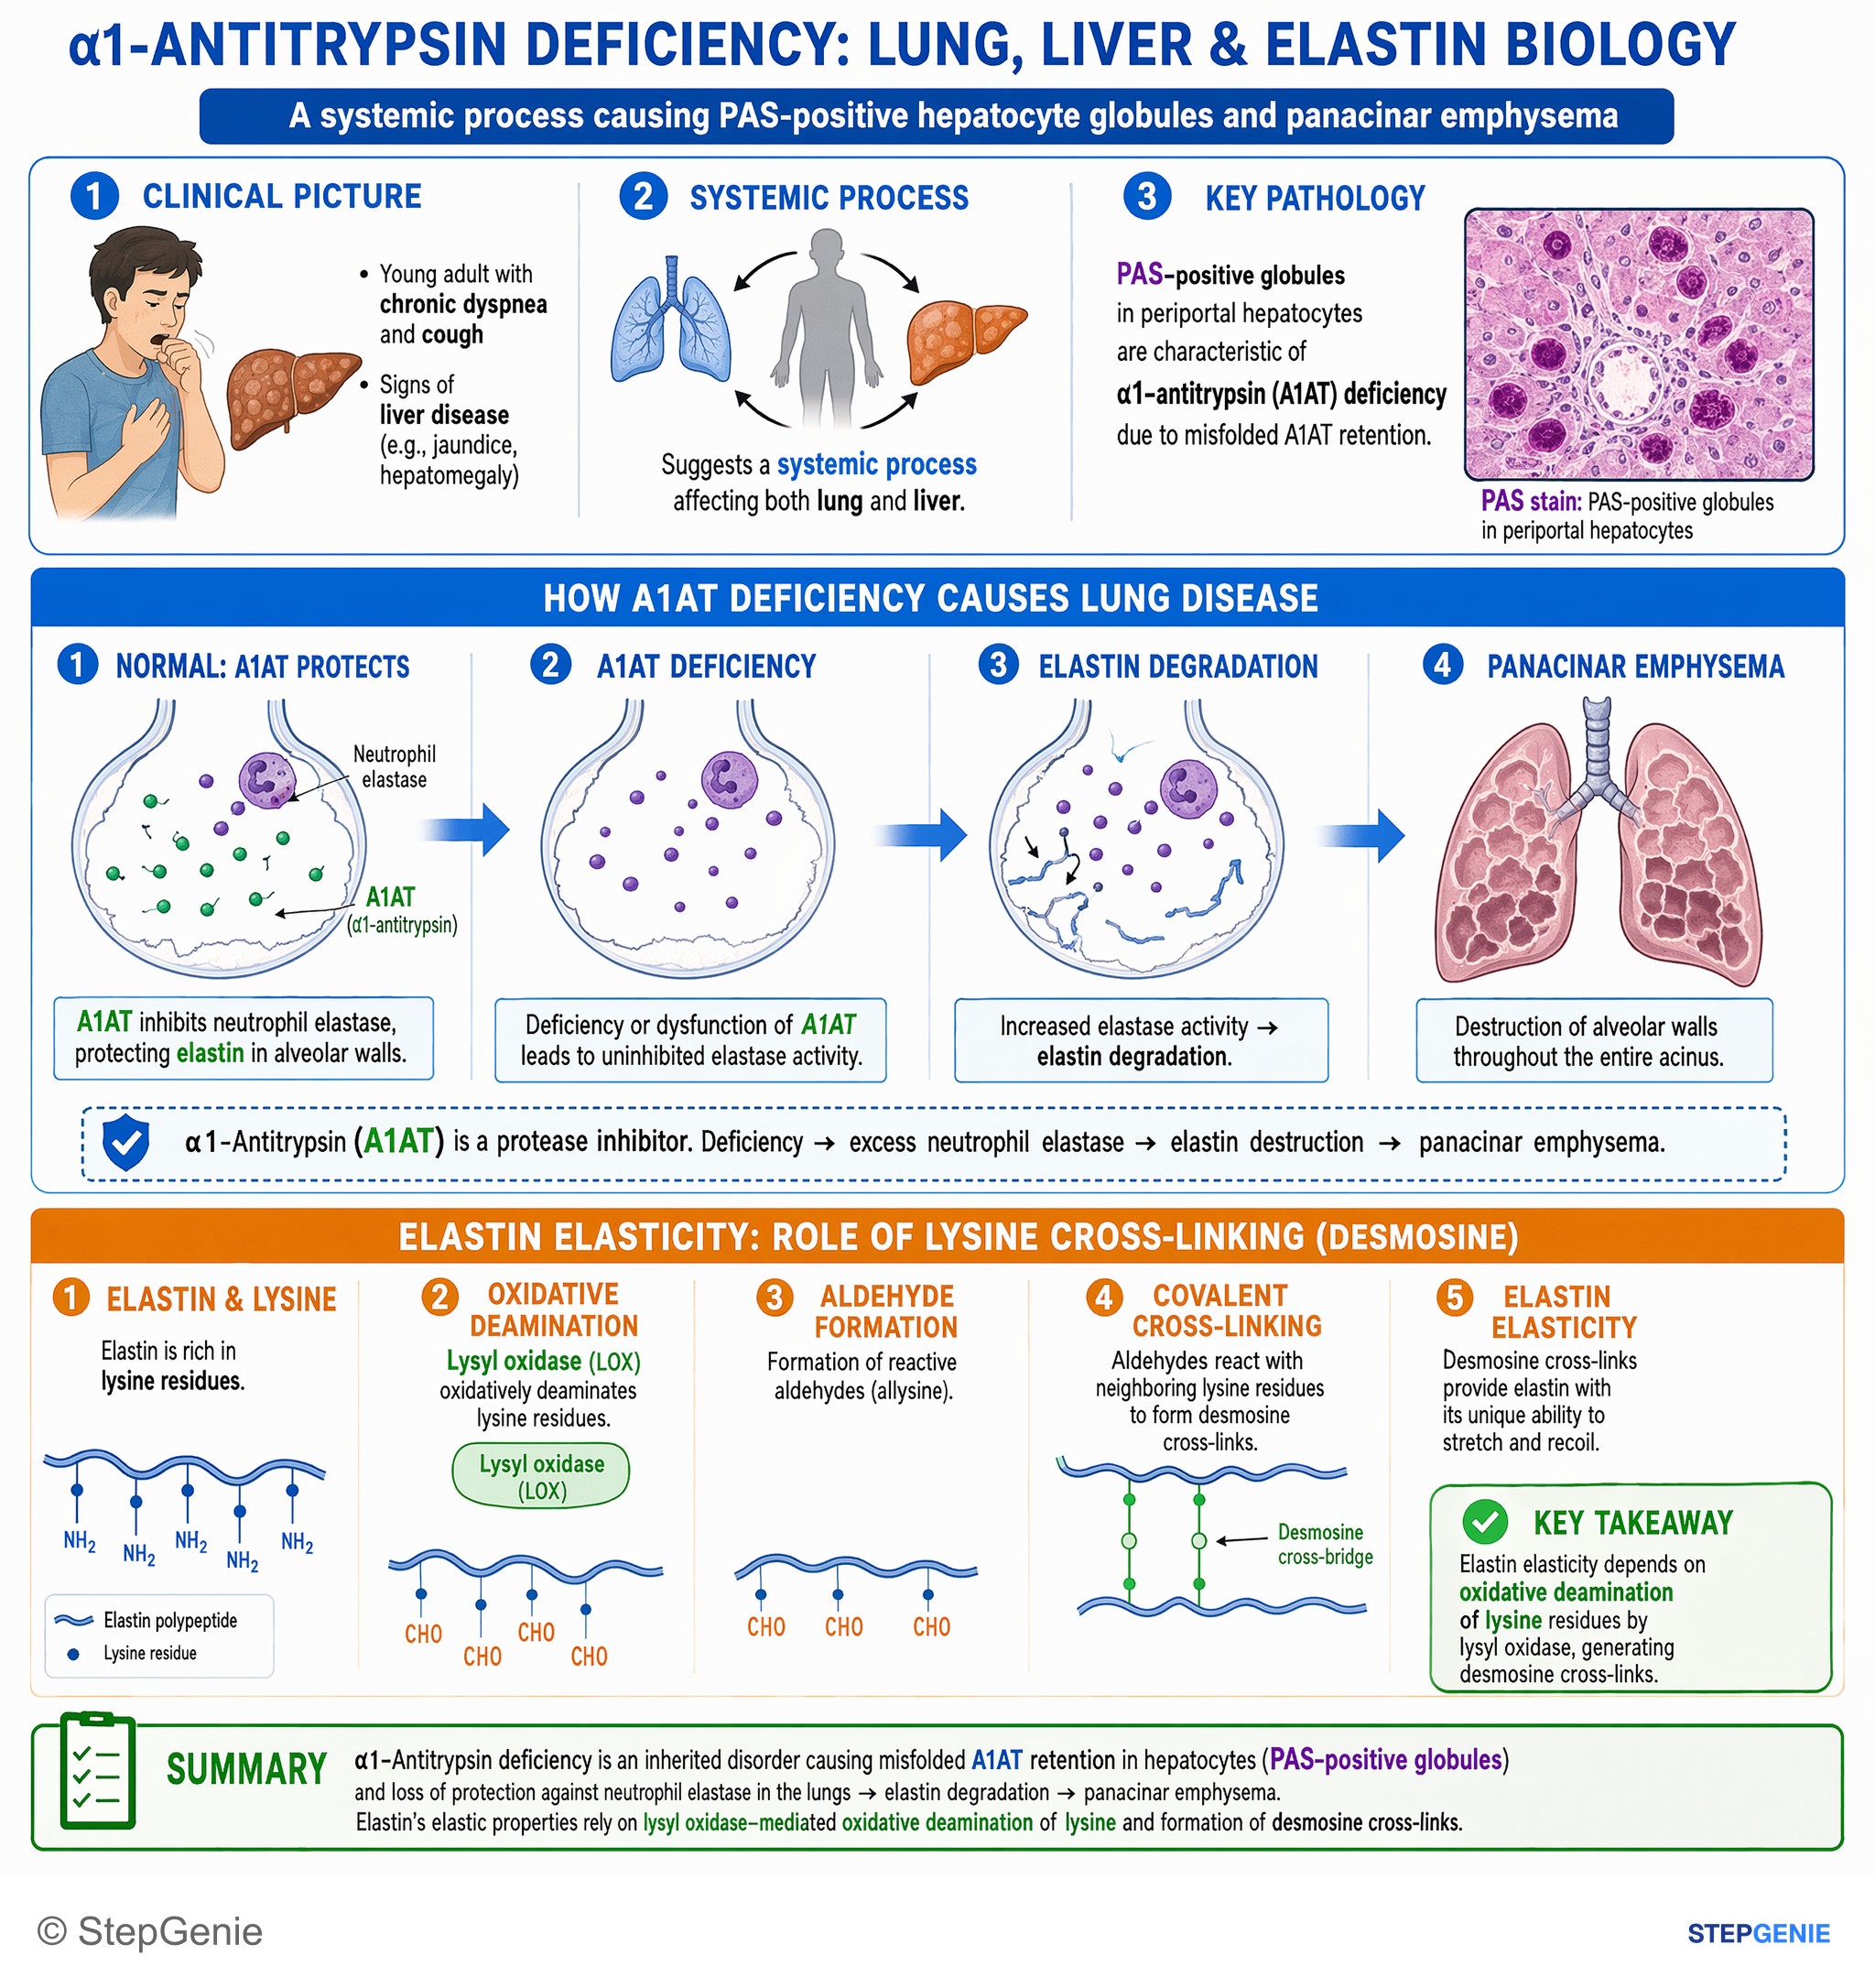
α1-antitrypsin deficiency causes PAS-positive hepatocyte globules and panacinar emphysema; elastin elasticity depends on oxidative…
USMLE Step 1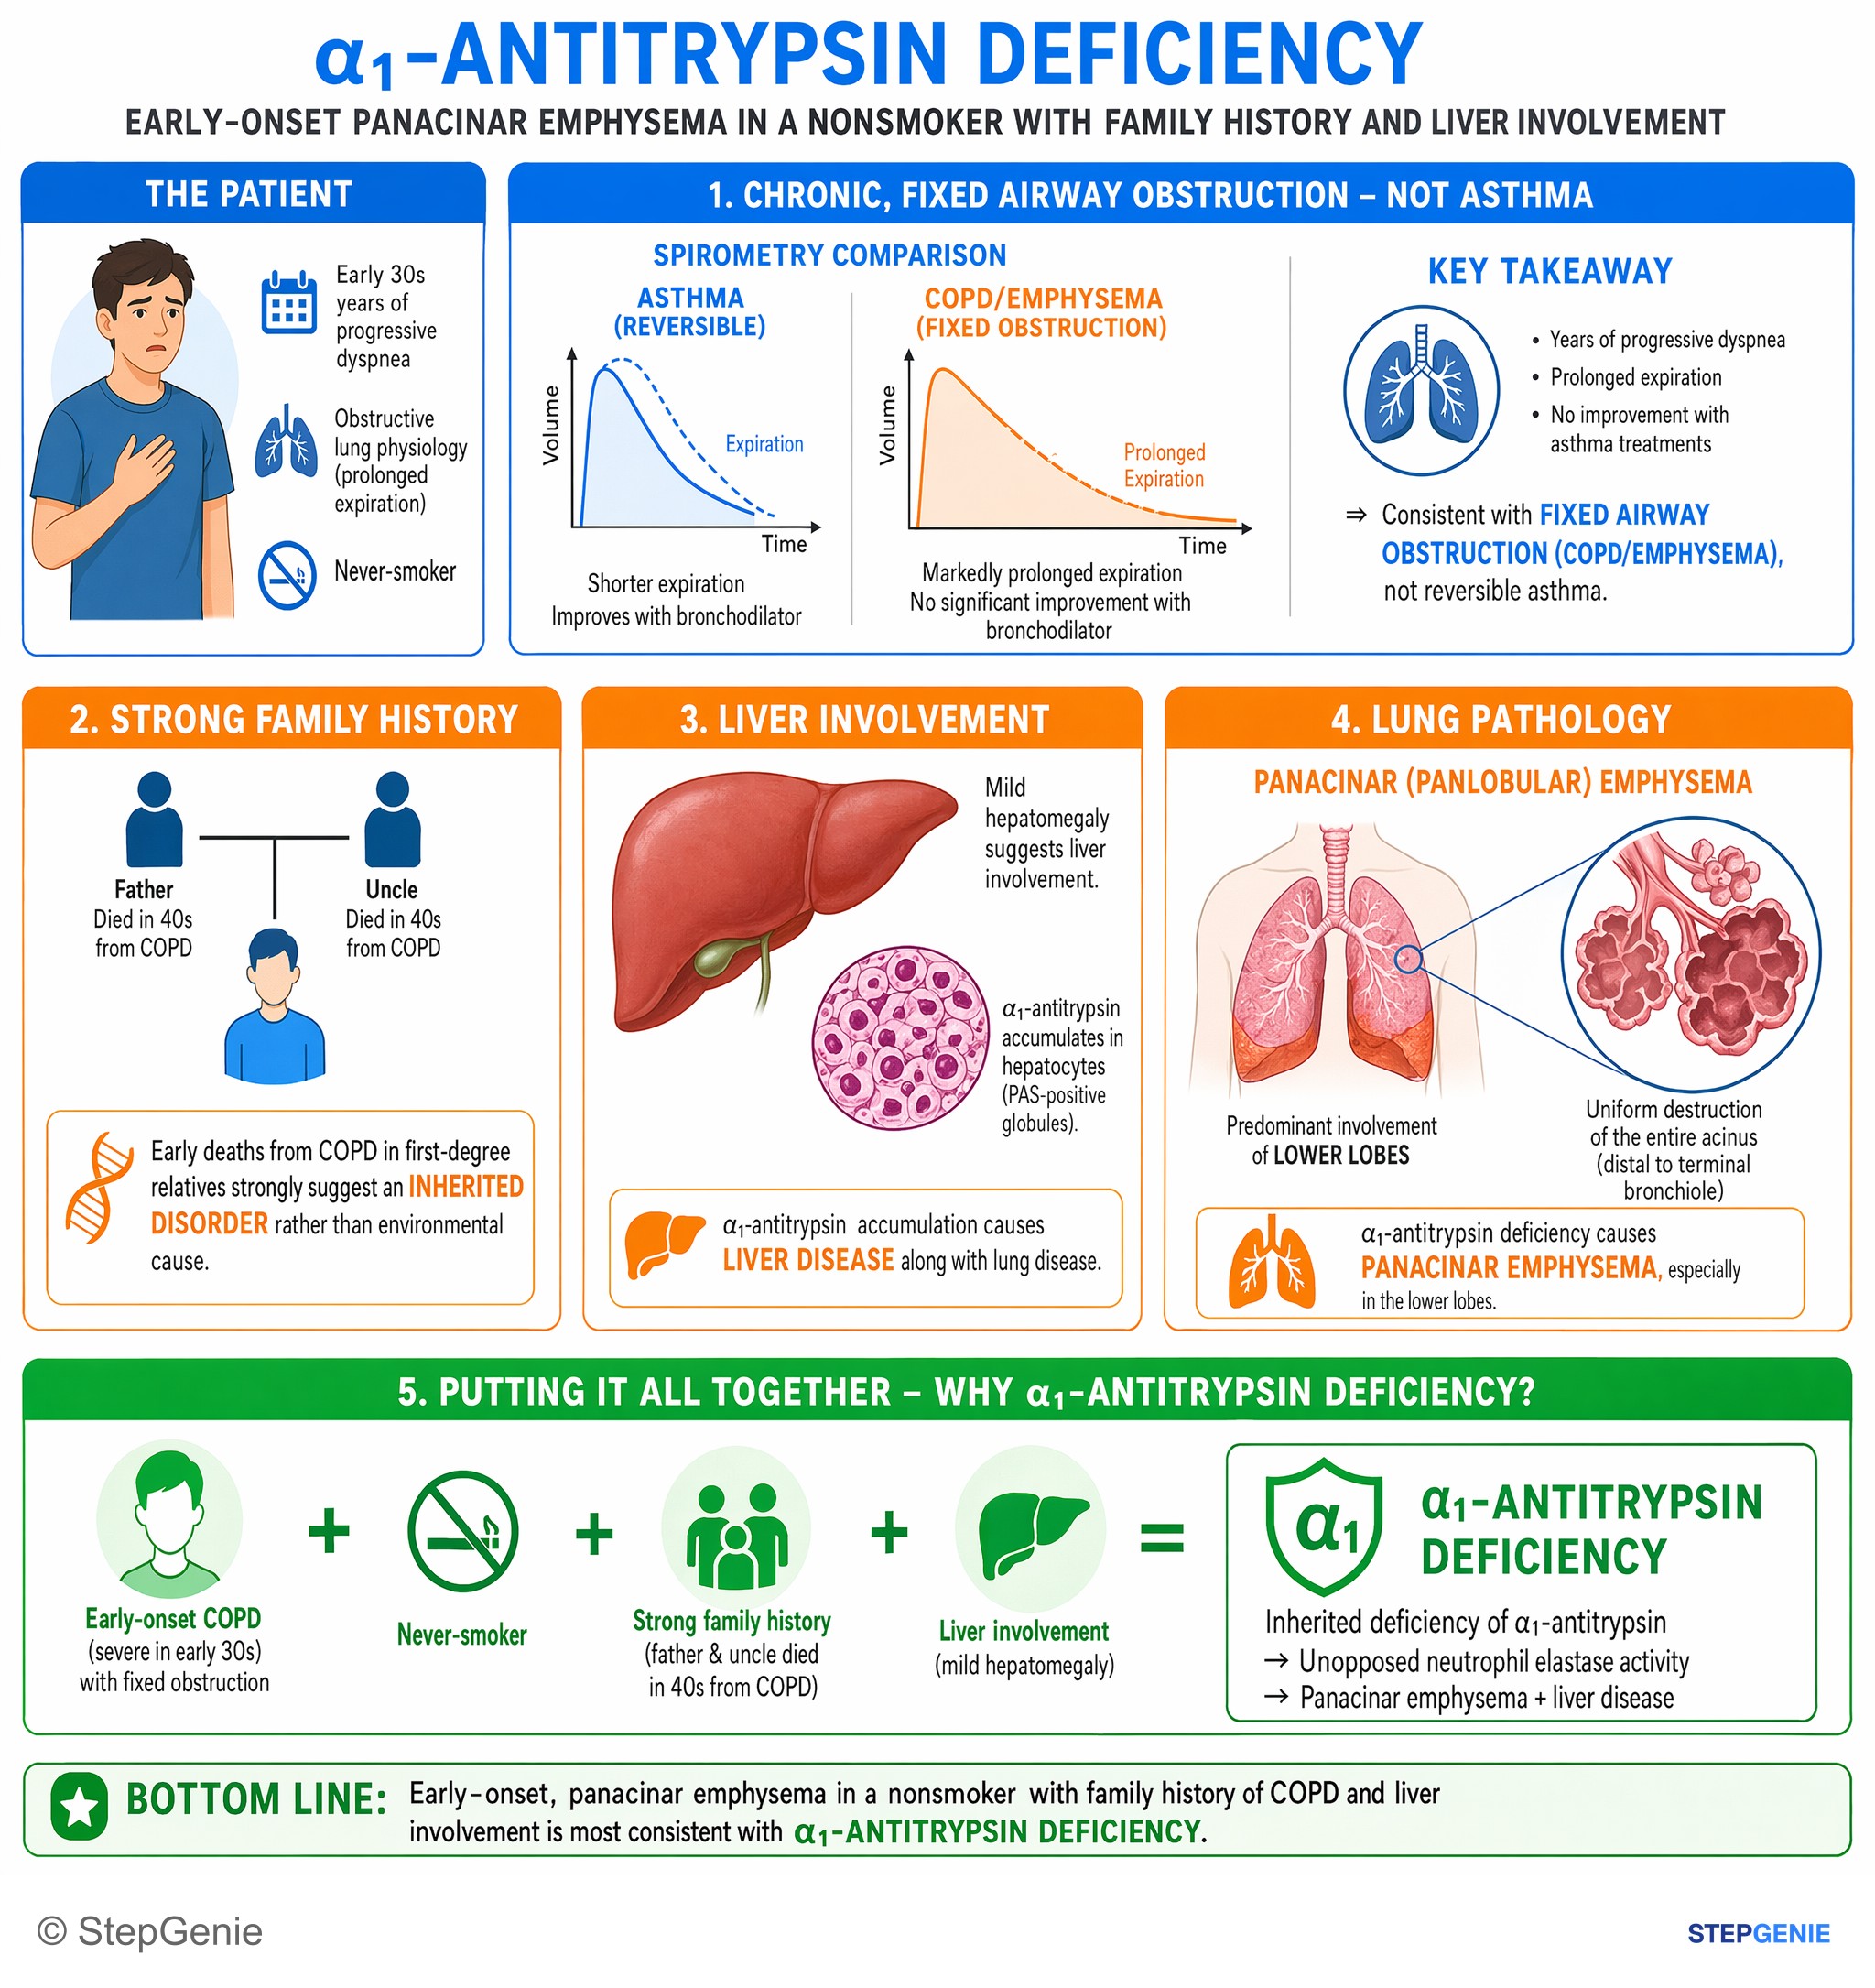
α1-antitrypsin deficiency → early-onset panacinar emphysema in a nonsmoker with family history of COPD and liver involvement.
USMLE Step 2Frequently Asked Questions
Why does alpha-1 antitrypsin deficiency cause liver injury even when serum A1AT is low?
Alpha-1 antitrypsin deficiency causes liver injury because misfolded A1AT accumulates inside hepatocytes, not because of the low serum level itself. Mutant A1AT, classically the Z allele, misfolds, polymerizes, and gets trapped in the endoplasmic reticulum of liver cells. This causes hepatocyte stress, inflammation, fibrosis, cirrhosis, and increases the risk of hepatocellular carcinoma.
What is the classic liver biopsy finding in alpha-1 antitrypsin deficiency?
The classic biopsy finding is PAS-positive, diastase-resistant globules in hepatocytes. This is a high-yield clue because PAS stains glycoproteins, while diastase digests glycogen, so the remaining globules are not glycogen. When a vignette mentions hepatocyte inclusions with this staining pattern, it strongly points to alpha-1 antitrypsin deficiency as the cause of liver disease.
How do you tell alpha-1 antitrypsin liver disease from Wilson disease or viral hepatitis?
Alpha-1 antitrypsin liver disease is suggested by low serum A1AT and PAS-positive, diastase-resistant hepatocyte globules. Wilson disease is distinguished by low ceruloplasmin, neuropsychiatric symptoms, and Kayser–Fleischer rings. Viral hepatitis is more associated with exposure risks and positive serologies, and it does not produce the PAS-positive globules that are classic for alpha-1 antitrypsin deficiency.
What is the definitive treatment for severe hepatic disease in alpha-1 antitrypsin deficiency?
Liver transplantation is the definitive treatment for severe hepatic disease in alpha-1 antitrypsin deficiency. It works by replacing the defective hepatocytes that produce the abnormal protein. This is an important Step-style concept because transplant can also correct the low serum A1AT level systemically, whereas IV A1AT augmentation therapy is used for selected lung disease and does not fix the hepatic accumulation problem.
How can alpha-1 antitrypsin deficiency present in infants versus adults?
In infants, alpha-1 antitrypsin deficiency often presents with prolonged neonatal jaundice, cholestasis, elevated AST and ALT, and possible hepatomegaly. In adults, it more often appears as cirrhosis, sometimes initially cryptogenic, with complications of portal hypertension such as ascites, variceal bleeding, and splenomegaly or thrombocytopenia. At any age, it also increases the risk of hepatocellular carcinoma.