A pancreatic pseudocyst is an encapsulated collection of amylase-rich pancreatic fluid whose wall is fibrous granulation tissue, not epithelium, which is why it is a "pseudo" cyst. Under the revised Atlanta classification it forms more than 4 weeks after interstitial edematous pancreatitis and contains only fluid; a mature collection that contains solid necrotic debris is walled-off necrosis (WON), not a pseudocyst. Many pseudocysts resolve on their own, so symptoms and complications, not size alone, decide drainage. When drainage is needed, the options are EUS-guided transmural drainage (cystogastrostomy), percutaneous drainage or surgery, chosen by location and local expertise.
The acronym: PSEUDOCYST
Each letter is one testable fact, roughly in the order a stem tells the story:
| Letter | Hook | What to remember |
|---|---|---|
| P | Post-pancreatitis | Follows acute interstitial edematous pancreatitis (gallstones, alcohol) or chronic pancreatitis; abdominal trauma can cause it, especially in children |
| S | Sac (lesser) | Lies beside the pancreas, often in the lesser sac behind the stomach, so it pushes on the stomach |
| E | Epithelium absent | Wall of fibrosed granulation tissue, no epithelial lining; true cysts and cystic neoplasms have one |
| U | Uniform fluid | Homogeneous fluid with no solid component; solid debris means walled-off necrosis |
| D | Delayed (over 4 weeks) | Before 4 weeks, a wall-less fluid collection is an acute peripancreatic fluid collection (APFC) |
| O | Obstruction and mass effect | Pain, bloating, early satiety, nausea and vomiting (stomach, duodenum); jaundice (bile duct); sometimes a palpable epigastric or left upper quadrant mass |
| C | Complications | Infection, hemorrhage from an eroded artery (pseudoaneurysm), rupture, splenic vein thrombosis |
| Y | Yields amylase | Aspirate is brown, with high amylase and lipase and low CEA; mucinous neoplasms have high CEA |
| S | Symptoms, not size | An asymptomatic, stable pseudocyst usually needs no drainage, even if large; many resolve |
| T | Transmural drainage | When drainage is needed: EUS-guided drainage through the stomach (cystogastrostomy) or duodenum; percutaneous and surgical routes are alternatives |
Picture it: a fake cyst (no lining) sitting behind the stomach, next to a calendar showing 4 weeks since the attack, squeezing the stomach like a water balloon. The attack itself is usually gallstones or alcohol (ACG 2024: gallstones 40-70%, alcohol 25-35% of acute pancreatitis); the stone side is covered in the cholelithiasis mnemonic.
Revised Atlanta: pseudocyst vs walled-off necrosis
The revised Atlanta classification (2012) sorts collections by time (under or over 4 weeks) and contents (fluid only, or fluid plus necrosis):
| Under 4 weeks (no mature wall) | Over 4 weeks (encapsulated) | |
|---|---|---|
| Interstitial edematous pancreatitis (fluid only) | Acute peripancreatic fluid collection (APFC): homogeneous fluid, no definable wall, confined by fascial planes; most resolve without intervention | Pancreatic pseudocyst: well circumscribed, round or oval, homogeneous fluid, fully encapsulated, no non-liquid component |
| Necrotizing pancreatitis (fluid + necrosis) | Acute necrotic collection (ANC): heterogeneous fluid and necrosis, not yet encapsulated | Walled-off necrosis (WON): mature, encapsulated collection with a well-defined inflammatory wall and both liquid and non-liquid contents |
What the table implies:
- True pseudocysts are uncommon after acute pancreatitis. The Atlanta authors call them "extremely rare" in acute pancreatitis; they are thought to arise from disruption of the main pancreatic duct or its branches, so pancreatic juice keeps leaking into one localized collection. Pseudocysts are also a recognized complication of chronic pancreatitis, and one can appear weeks after necrosectomy when a disconnected duct keeps leaking into the cavity.
- Debris changes the name. If solid necrotic material is visible in a mostly fluid cavity, it is WON. CT can miss debris, so MRI or ultrasound may be needed to confirm a collection is fluid only.
- Necrotizing pancreatitis occurs in about 5-10% of acute pancreatitis (Merck), and the fluid becomes infected in about one-third of patients with necrosis.
- Severity grading: a pseudocyst is a local complication, so the attack is at least moderately severe. Mild means no organ failure and no local or systemic complications; severe means organ failure persisting beyond 48 hours.
Pseudocyst vs cystic neoplasm: the "no epithelium" question
A cyst without a clear history of pancreatitis should make you think neoplasm, not pseudocyst. Features from the ACG pancreatic cyst guideline:
| Lesion | Typical patient and imaging | Cyst fluid |
|---|---|---|
| Pseudocyst | History of acute or chronic pancreatitis | Brown; high amylase and lipase, low CEA |
| Serous cystadenoma | About 75% women, 6th decade; microcystic "honeycomb" | Low CEA, low amylase and lipase |
| Mucinous cystic neoplasm | Almost exclusively women, 5th to 7th decade; body or tail; no duct communication | High CEA, variable amylase |
| IPMN | Men and women equally, 7th decade; communicates with the pancreatic duct | High CEA, high amylase |
Trap: high amylase alone doesn't prove a pseudocyst, because IPMNs communicate with the duct and can have it too. A low CEA plus a history of pancreatitis is the pseudocyst pattern. A cyst in an older adult with no pancreatitis history belongs in the pancreatic cancer differential.
Complications
| Complication | Clue in the stem | Why it matters |
|---|---|---|
| Infection | Fever, rising WBC, deterioration after stabilizing; gas in the collection on CT | An infected pseudocyst can become an abscess; it needs antibiotics and drainage |
| Hemorrhage | Sudden pain, falling hemoglobin, hypotension | Enzymes can erode a nearby artery into a pseudoaneurysm (the splenic artery is a classic site): an emergency |
| Rupture | Sudden severe abdominal pain, fainting, rapid heartbeat | A medical emergency: shock and hemorrhage can follow |
| Gastric outlet or duodenal obstruction | Early satiety, vomiting, weight loss | A classic indication for drainage |
| Bile duct compression | Jaundice | Another indication for drainage |
| Splenic vein thrombosis | Gastric varices, upper GI bleeding | The splenic vein runs behind the pancreas, so inflammation can clot it |
| Pancreatic duct disruption | Pancreatic ascites or pleural effusion | Seen with both acute and chronic pancreatitis |
When to drain, when to watch
- Watch: an asymptomatic pseudocyst, even a big one. ACG's cyst guideline says asymptomatic cysts diagnosed as pseudocysts on imaging and history need no treatment or further evaluation. Merck estimates about one-third resolve spontaneously.
- Size and time alone don't trigger drainage. The older teaching of draining any pseudocyst that lasts beyond 6 weeks and exceeds about 5-6 cm has softened: MedlinePlus says such pseudocysts may need treatment, but not necessarily when the person has no symptoms and the pseudocyst isn't growing.
- Drain when it is symptomatic (pain, early satiety, vomiting, weight loss, jaundice), infected, bleeding, enlarging rapidly, or likely to rupture. The last four are Merck's list; Radiopaedia adds persistent symptoms and mass effect such as gastric outlet or biliary obstruction.
- Wait for the wall. Drainage is timed for after the wall has matured, about 4 weeks or more. For necrotic collections, AGA advises avoiding debridement in the first 2 weeks and ideally waiting 4 weeks; ACG (2024) says to wait 4-6 weeks in stable necrosis.
- How: a pseudocyst bulging against the stomach or duodenum suits EUS-guided transmural drainage (through the stomach, a cystogastrostomy, or through the duodenum); percutaneous CT-guided drainage and surgical drainage into the stomach or small intestine are alternatives. For WON, AGA says endoscopic transmural drainage may be preferred because it avoids the risk of a pancreatocutaneous fistula, and lumen-apposing metal stents appear superior to plastic stents.
- No prophylactic antibiotics. Give antibiotics only for suspected or proven infection, choosing drugs that penetrate necrosis (carbapenems, quinolones, metronidazole).
The enzyme cascade that starts all of this, trypsinogen activated inside the gland, is covered in zymogen activation and pancreatitis, and the pseudocyst-prone chronic form in the chronic pancreatitis guide.
Practice question
A 46-year-old man was hospitalized 7 weeks ago with alcohol-associated acute pancreatitis; CT then showed interstitial edematous pancreatitis without necrosis. He now reports epigastric fullness, early satiety and vomiting after meals, with a 4-kg weight loss. He is afebrile, and vital signs are normal. There is a vague epigastric mass. Contrast-enhanced CT shows a 9-cm round, homogeneous fluid collection with a thin enhancing wall, no solid debris and no gas, compressing the posterior wall of the stomach. Which is the most appropriate management?
A. EUS-guided transmural drainage into the stomach B. Reassurance and repeat CT in 6 months C. IV meropenem D. Pancreaticoduodenectomy (Whipple procedure) E. Percutaneous fine-needle aspiration to confirm infection
Answer: A. A homogeneous, fully encapsulated collection more than 4 weeks after interstitial pancreatitis is a pseudocyst, and it is symptomatic (gastric outlet symptoms, weight loss). A mature pseudocyst abutting the stomach is well suited to endoscopic cystogastrostomy.
- B: observation suits asymptomatic pseudocysts; this one is obstructing the stomach.
- C: there are no signs of infection, and prophylactic antibiotics are not recommended.
- D: resection is for neoplasms; nothing here suggests a cystic tumor, and the history of pancreatitis with a homogeneous, thin-walled collection fits a pseudocyst.
- E: infection is presumed from gas in the collection or clinical deterioration, and routine FNA is unnecessary; here, nothing suggests infection.
Twist: had the CT shown heterogeneous contents with solid debris after necrotizing pancreatitis, the diagnosis would be walled-off necrosis, and management would follow the step-up approach (drainage, then necrosectomy if needed).
Key takeaways
- Pseudocyst = fluid-only, encapsulated collection with no epithelial lining, over 4 weeks after interstitial edematous pancreatitis (revised Atlanta).
- Under 4 weeks = APFC (no wall); necrotic debris = ANC or WON, never a pseudocyst.
- Fluid: high amylase, low CEA; a cyst with high CEA suggests a mucinous neoplasm.
- Complications: infection, hemorrhage from a pseudoaneurysm, rupture, gastric outlet or biliary obstruction, splenic vein thrombosis.
- Treat symptoms and complications, not size: observe asymptomatic pseudocysts; drain symptomatic, infected, bleeding or rapidly enlarging ones.
- Drainage routes, once the wall has matured: EUS-guided transmural (for a pseudocyst abutting the stomach or duodenum), percutaneous or surgical, chosen by location and expertise.
Sources
- Classification of acute pancreatitis 2012: revision of the Atlanta classification and definitions by international consensus — Gut (2013)
- Acute Pancreatitis — Merck Manual Professional Edition (2026)
- Chronic Pancreatitis — Merck Manual Professional Edition (2026)
- Pancreatic pseudocyst — MedlinePlus Medical Encyclopedia (2025)
- ACG Clinical Guideline: Diagnosis and Management of Pancreatic Cysts — American College of Gastroenterology (2018)
- Management of Pancreatic Necrosis: AGA Clinical Practice Update — American Gastroenterological Association (2019)
- ACG Guideline Highlights: Acute Pancreatitis — American College of Gastroenterology (2024)
- Pancreatic pseudocyst — Radiopaedia
- Splenic artery pseudoaneurysm — Radiopaedia
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
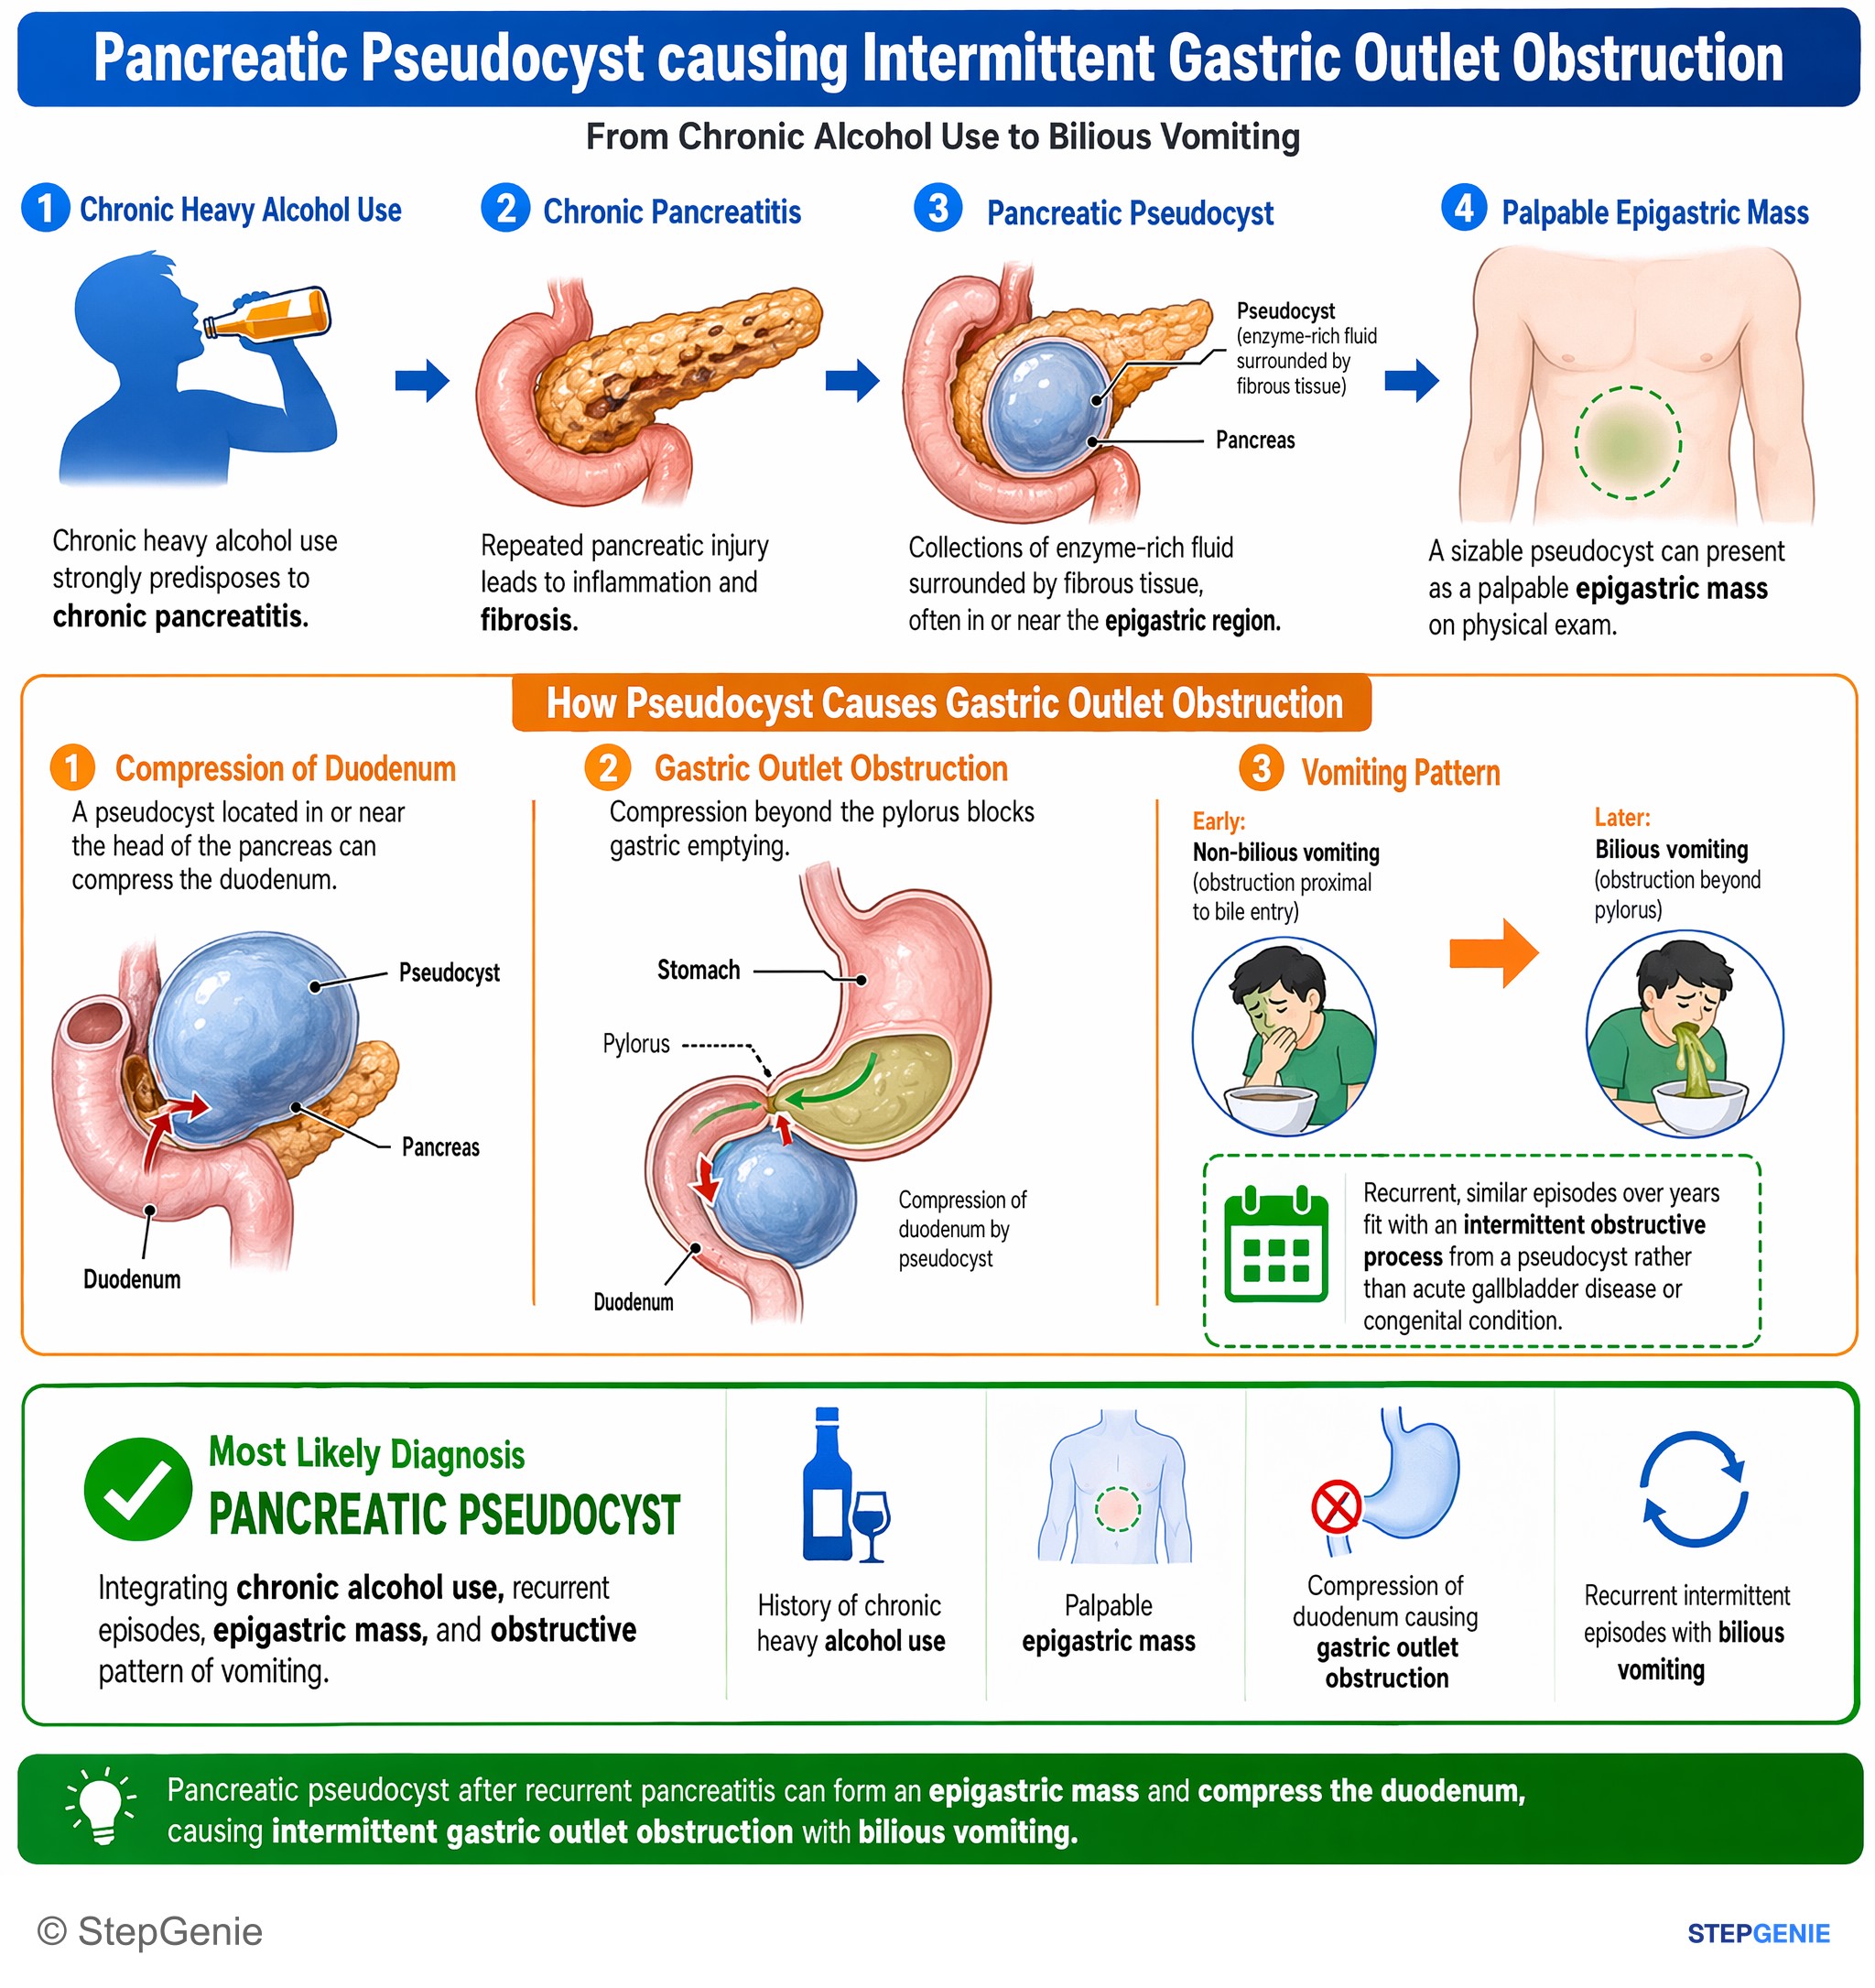
Pancreatic pseudocyst after recurrent pancreatitis can form an epigastric mass and compress the duodenum, causing intermittent gastric…
USMLE Step 2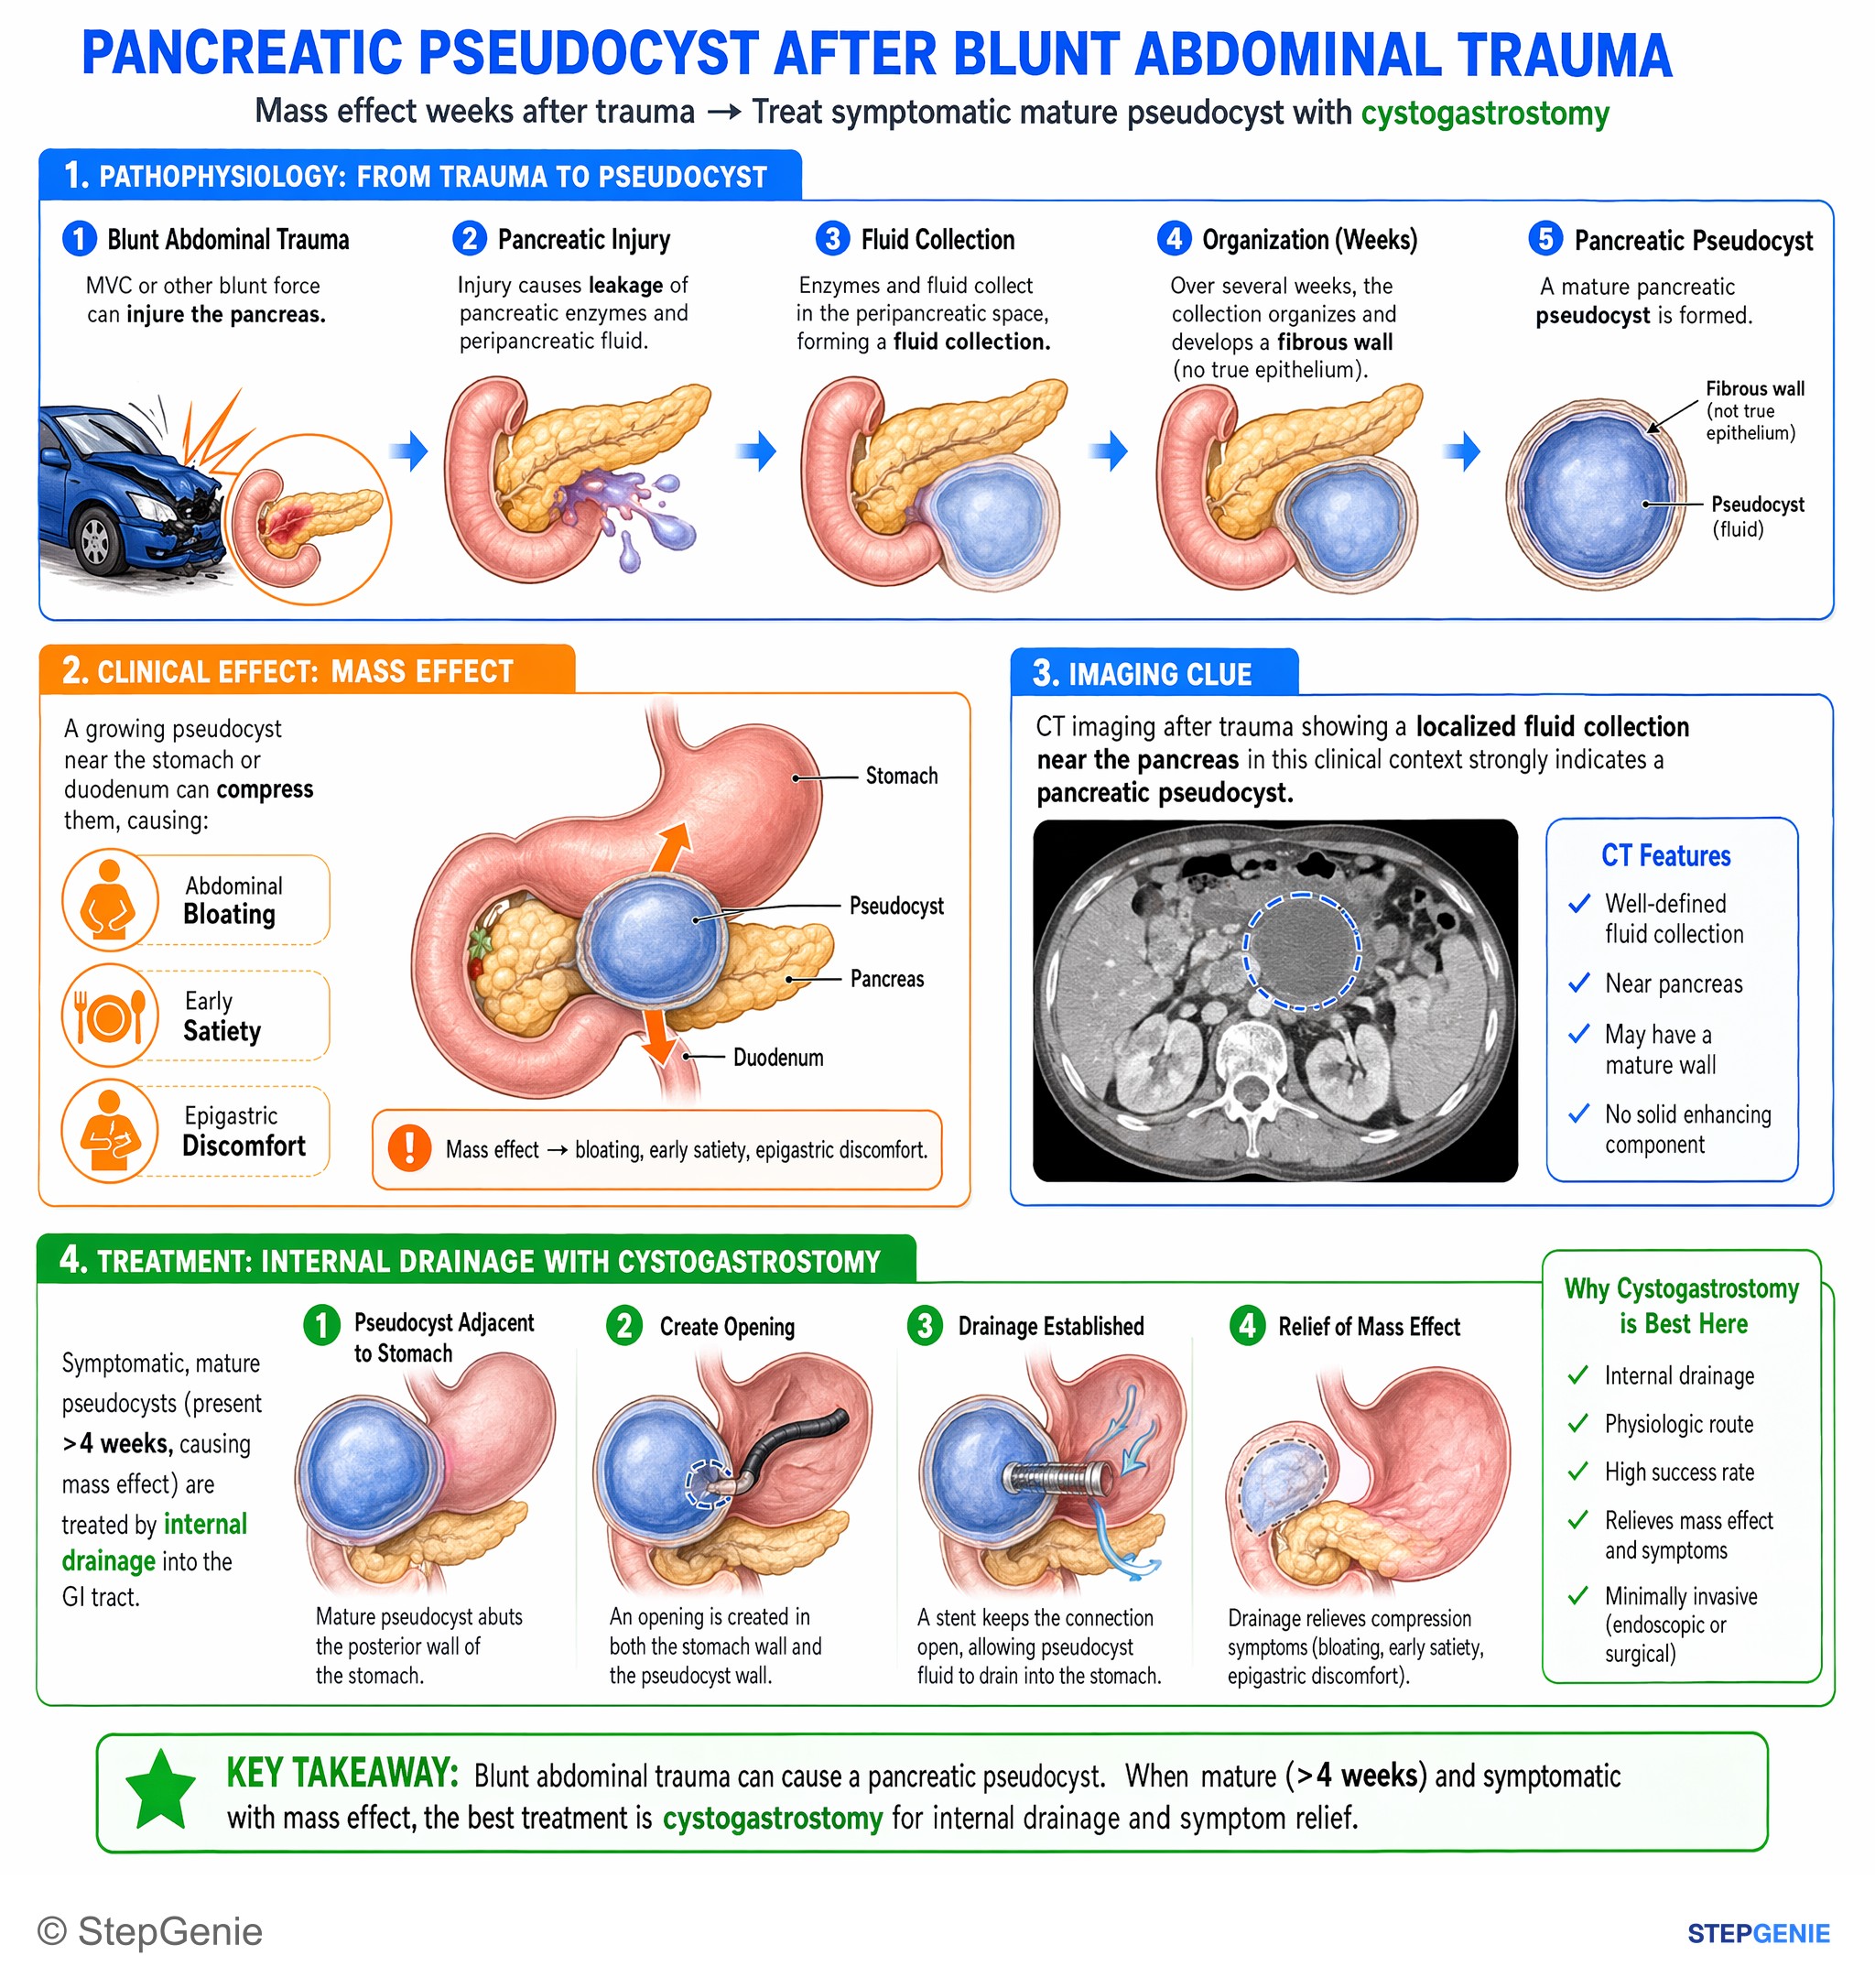
Pancreatic pseudocyst weeks after blunt trauma causes mass effect (bloating, early satiety); treat symptomatic mature pseudocyst with…
USMLE Step 2Frequently Asked Questions
What is a pancreatic pseudocyst and why is it called a pseudocyst?
A pancreatic pseudocyst is an encapsulated collection of amylase-rich pancreatic fluid that forms after pancreatitis. Its wall is made of fibrous granulation tissue rather than epithelium, so it is not a true cyst. Under the revised Atlanta classification it contains only fluid, with no solid necrotic material.
How long after pancreatitis does a pseudocyst form?
A pseudocyst is a collection that persists more than 4 weeks after the onset of interstitial edematous pancreatitis, by which time a mature wall has formed. A fluid collection in the first 4 weeks, without a defined wall, is called an acute peripancreatic fluid collection, and most of these resolve on their own. Pseudocysts can also develop in chronic pancreatitis and after abdominal trauma.
What is the difference between a pancreatic pseudocyst and walled-off necrosis?
Both are encapsulated collections that mature after about 4 weeks, but a pseudocyst contains only fluid and follows interstitial edematous pancreatitis, while walled-off necrosis contains both fluid and solid necrotic tissue and follows necrotizing pancreatitis. MRI or ultrasound may be needed to show debris that CT can miss. The distinction matters because walled-off necrosis may need a step-up approach of drainage followed, if necessary, by necrosectomy.
When does a pancreatic pseudocyst need to be drained?
Drainage is indicated when a pseudocyst causes symptoms such as pain, early satiety, vomiting, weight loss or jaundice, or when it is infected, bleeding, enlarging rapidly or likely to rupture. Asymptomatic, stable pseudocysts are usually observed even if large, because many resolve. When drainage is needed, the options are endoscopic ultrasound-guided drainage through the stomach or duodenum, percutaneous drainage and surgery, chosen by location and local expertise.
What are the complications of a pancreatic pseudocyst?
The main complications are infection, which can form an abscess; hemorrhage from a pseudoaneurysm of a nearby artery such as the splenic artery; rupture with shock; and compression of the stomach, duodenum or bile duct. Splenic vein thrombosis can cause gastric varices, and pancreatic duct disruption can cause pancreatic ascites or a pleural effusion. Sudden pain with signs of bleeding or shock is an emergency.
How is a pancreatic pseudocyst told apart from a cystic tumor of the pancreas?
A pseudocyst usually follows a clear episode of acute or chronic pancreatitis, and fluid sampled from it is typically brown with high amylase and lipase and a low CEA. Mucinous cystic neoplasms and IPMNs usually have a high CEA in the cyst fluid, while serous cystadenomas have low CEA and low amylase. A pancreatic cyst in someone with no history of pancreatitis should be evaluated as a possible neoplasm.