Nonalcoholic fatty liver disease (NAFLD) and nonalcoholic steatohepatitis (NASH) show up everywhere on USMLE because they connect metabolic syndrome ↔ liver injury ↔ cirrhosis/HCC risk. Here’s a quick, shareable way to lock in the essentials—especially the “what is it, who gets it, what does it look like, and why do we care?”
The 10-Second Mnemonic: “NASH is NASTY”
Think of NASH as the “inflamed, injuring” version of fatty liver.
NASH = NASTY
- N = NASH happens in Non-drinkers (or minimal alcohol; history matters)
- A = AST/ALT elevated (often mild–moderate; ALT can be > AST early)
- S = Steatohepatitis = Steatosis + inflammation
- T = Tender hepatomegaly / Two-hit concept (insulin resistance → fat → oxidative injury)
- Y = Yields fibrosis → cirrhosis → HCC risk
One-liner: NAFLD is fat in the liver; NASH is fat + inflammation that can scar.
Visual Device: The “Spectrum Slide” (NAFLD → NASH → Cirrhosis)
Picture a liver sliding down a metabolic hill:
| Stage | What’s in the liver? | Key idea | Why it matters |
|---|---|---|---|
| NAFLD (simple steatosis) | Fat (macrovesicular steatosis) | Often asymptomatic | Can be reversible with weight loss |
| NASH (steatohepatitis) | Fat + inflammation + hepatocyte injury (ballooning) | “Active” injury | Can progress to fibrosis/cirrhosis |
| Fibrosis/Cirrhosis | Scar tissue | Architectural distortion | Portal HTN, liver failure |
| HCC | Malignancy risk rises (esp with cirrhosis) | Screening considerations | Testable complication |
Memory hook:
“Fat is quiet. Fat + fire scars.” (NAFLD quiet; NASH = fire/inflammation → fibrosis)
Who Gets It? (Classic USMLE Risk Cluster)
Think: “NAFLD rides with metabolic syndrome.”
- Obesity
- Type 2 diabetes
- Hypertriglyceridemia/dyslipidemia
- Insulin resistance
- Often HTN as part of the syndrome
USMLE clue: patient with BMI↑, A1c↑, triglycerides↑ and mild transaminitis.
What Do Labs and Imaging Look Like?
High-yield patterns
- Mild–moderate AST/ALT elevation
- Classically ALT > AST in many NAFLD/NASH cases (contrast: alcoholic liver disease often AST:ALT ≥ 2)
- Ultrasound: “bright” liver = hepatic steatosis
- Definitive distinction NAFLD vs NASH: biopsy
- NASH shows ballooning degeneration, inflammation, and may show Mallory-Denk bodies (not exclusive to alcohol)
Board trap: Imaging can tell you “fatty liver,” but it can’t reliably tell NAFLD vs NASH—biopsy is the classic differentiator.
Pathophysiology (Just Enough for Step)
The core idea
- Insulin resistance → increased fatty acid delivery/synthesis in liver → steatosis
- Oxidative stress, mitochondrial dysfunction, cytokines → inflammation + hepatocyte injury
- Injury → fibrosis (and potentially cirrhosis)
If you like formulas: insulin resistance raises hepatic triglyceride accumulation—then inflammation makes it clinically dangerous.
Complications You Must Recognize
- Progression to cirrhosis
- Portal hypertension consequences (ascites, varices, splenomegaly)
- Hepatocellular carcinoma (HCC) risk increases, especially once cirrhosis develops
- Increased cardiovascular risk (common real-world cause of mortality in NAFLD patients)
Management (USMLE Practical Takeaways)
First-line = lifestyle
- Weight loss (can improve steatosis and inflammation)
- Diet + exercise
- Optimize diabetes and lipids
Medication notes (testable nuance)
- No single “magic pill” for everyone; focus is metabolic control.
- In select patients, insulin-sensitizing strategies may be considered, but Step questions usually want:
“Lifestyle modification + treat metabolic syndrome.”
Quick Differentials: Don’t Get Tricked
| Condition | Key clue | Classic AST/ALT pattern |
|---|---|---|
| NAFLD/NASH | Metabolic syndrome, minimal alcohol | Often ALT ≥ AST (variable) |
| Alcoholic liver disease | Heavy alcohol use; macrocytosis | AST:ALT ≥ 2, values usually < 300 |
| Viral hepatitis | Risk factors; very high transaminases possible | AST/ALT can be very high |
| Hemochromatosis | Bronze diabetes, arthropathy | Variable; iron studies abnormal |
Shareable Summary Card (Copy/Paste)
- NAFLD = fat
- NASH = fat + inflammation → fibrosis → cirrhosis/HCC
- Risk factors: obesity, T2DM, hypertriglyceridemia (metabolic syndrome)
- Dx: US shows fatty liver; biopsy distinguishes NASH
- Tx: weight loss + manage metabolic syndrome
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
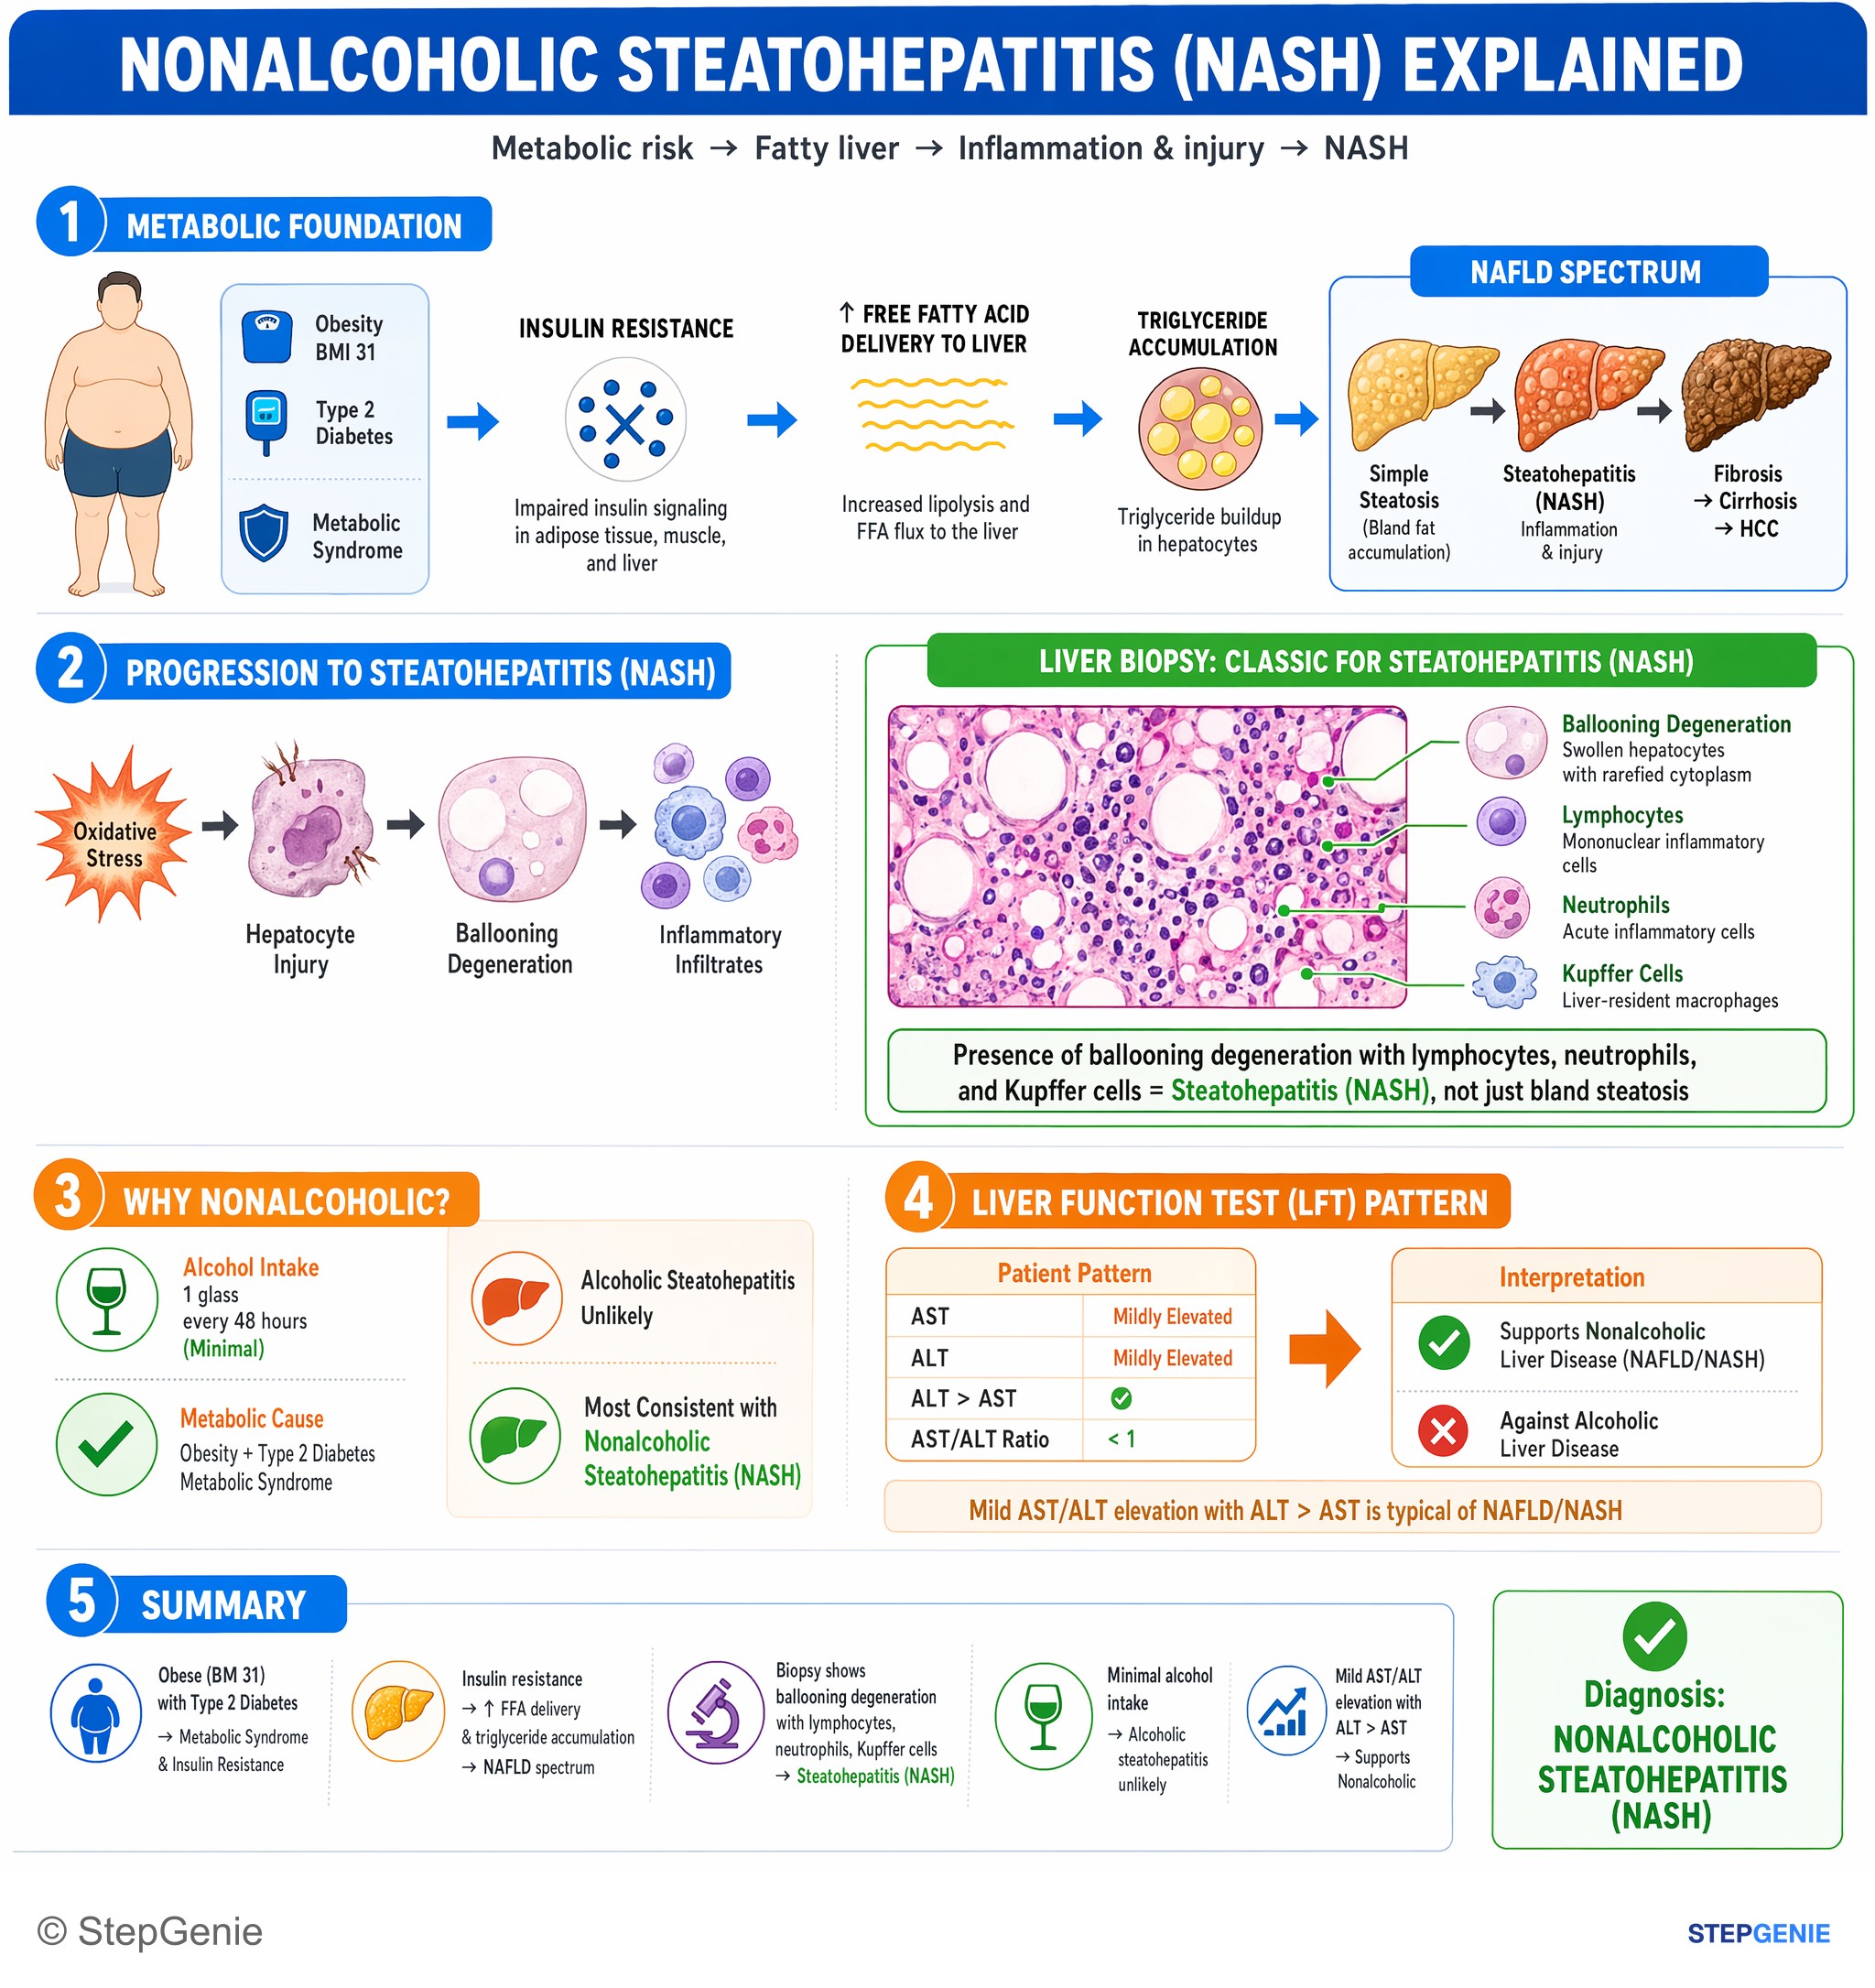
Nonalcoholic steatohepatitis (NASH): obese diabetic with minimal alcohol use, mild AST/ALT elevation, ballooning degeneration and…
USMLE Step 2Frequently Asked Questions
What is the difference between NAFLD and NASH?
NAFLD is simple fat accumulation in the liver, while NASH is fat plus inflammation and hepatocyte injury that can scar. NAFLD is often asymptomatic and may be reversible with weight loss, but NASH represents active liver injury. NASH can progress to fibrosis, cirrhosis, and increased hepatocellular carcinoma risk, which is why the distinction matters clinically and on exams.
Who usually gets NAFLD or NASH?
NAFLD and NASH are classically seen in patients with metabolic syndrome. The typical risk cluster includes obesity, type 2 diabetes, hypertriglyceridemia or dyslipidemia, insulin resistance, and often hypertension. A common exam clue is a patient with elevated BMI, elevated A1c, high triglycerides, and mild transaminitis, especially when alcohol use is minimal or absent.
How do you tell NAFLD or NASH from alcoholic liver disease on exams?
The key clues are alcohol history, metabolic syndrome, and the AST/ALT pattern. NAFLD and NASH usually occur in non-drinkers or people with minimal alcohol use and often show ALT greater than or equal to AST. Alcoholic liver disease is linked to heavy alcohol use, may have macrocytosis, and classically shows an AST to ALT ratio of at least 2, with values usually under 300.
Can ultrasound distinguish NAFLD from NASH?
No, ultrasound can show fatty liver but cannot reliably distinguish NAFLD from NASH. On imaging, hepatic steatosis may appear as a bright liver, which tells you fat is present. The classic definitive way to separate simple steatosis from steatohepatitis is biopsy, because NASH shows ballooning degeneration, inflammation, and sometimes Mallory-Denk bodies.
What is the first-line treatment for NAFLD or NASH?
First-line treatment is lifestyle modification with weight loss, diet, exercise, and management of metabolic syndrome. Weight loss can improve both steatosis and inflammation, making it the main practical treatment focus. Step-style questions usually emphasize controlling diabetes and lipids rather than looking for a single medication, since there is no universal magic pill for all patients.