Hepatocellular carcinoma (HCC) is one of those Step questions where you either see the pattern instantly… or you drown in lab values and liver buzzwords. The “5-second rule” approach is about recognizing HCC fast from a few high-yield clues: who gets it, what it secretes, what it looks like, and what it does.
The 5-Second Rule (HCC)
If you see cirrhosis + a liver mass + elevated AFP, think:
Hepatocellular carcinoma — primary liver cancer arising in chronically inflamed/cirrhotic liver, classically marked by elevated AFP and arterial enhancement on imaging.
One-Liner You Can Memorize
HCC = “Cirrhosis patient with weight loss + RUQ pain + ↑AFP + arterial enhancing liver mass.”
The Visual / Mnemonic Device: “A.F.P. in a C.I.R.C.L.E.”
Picture a CIRCLE (cirrhosis) drawn around a liver, with AFP stamped in the center like a “cancer seal.”
C.I.R.C.L.E. = HCC risk + presentation
- C = Cirrhosis (biggest overall risk factor)
- I = Infection (HBV, HCV)
- R = Risk toxins (aflatoxin)
- C = Clinical: weight loss, RUQ pain, hepatomegaly
- L = Labs: ↑ AFP
- E = Enhancement: arterial enhancement on contrast imaging
If the vignette gives you cirrhosis + cancer symptoms, your brain should auto-fill AFP and arterial enhancement.
High-Yield Risk Factors (USMLE Favorites)
Major etiologies that set up HCC
- Chronic Hepatitis B (HBV)
- Key Step twist: HBV can cause HCC even without cirrhosis (via DNA integration/oncogenic effects)
- Chronic Hepatitis C (HCV)
- Usually via cirrhosis
- Cirrhosis from any cause, especially:
- Alcohol-related liver disease
- NAFLD/NASH (increasingly tested)
High-yield “classic” association
- Aflatoxin (Aspergillus flavus)
- Found in moldy peanuts/grains
- Synergizes with HBV
- Classically associated with p53 mutation
How It Presents (What the Stem Wants You to Notice)
Common board-style clues:
- Constitutional symptoms: weight loss, fatigue, anorexia
- RUQ pain or abdominal fullness
- Hepatomegaly ± worsening ascites
- Signs of decompensated cirrhosis in the background:
- Variceal bleed, jaundice, encephalopathy, ascites
Paraneoplastic clue (sometimes tested)
- Hypoglycemia (tumor glucose consumption/IGF production)
- Erythrocytosis (EPO production) — less common but fair game
The Two Fastest Diagnostic Anchors
1) AFP
- AFP is associated with HCC, but:
- Not perfectly sensitive/specific
- Mild AFP elevations can occur in chronic hepatitis/cirrhosis
- Very high AFP + mass in at-risk patient = strong signal for HCC
2) Imaging pattern: arterial enhancement
HCC lesions are typically arterially supplied, so on contrast imaging they show:
- Arterial phase hyperenhancement
- Often washout in the portal venous/delayed phase
Screening: Who Gets Watched (and How)
Boards love screening because it’s concrete:
High-risk patients (esp. cirrhosis) → ultrasound every 6 months
Often combined with AFP, depending on guideline/setting.
Who counts as high risk?
- All cirrhosis (regardless of cause)
- Many chronic HBV patients even without cirrhosis (risk-stratified by age/ethnicity/family history)
Differentials You Must Not Confuse (Quick Table)
| Condition | Classic setting | Key clue | AFP? |
|---|---|---|---|
| Hepatocellular carcinoma | Cirrhosis, HBV/HCV, aflatoxin | Arterial enhancement, systemic symptoms | ↑ AFP (often) |
| Cholangiocarcinoma | PSC, liver flukes (SE Asia), biliary disease | Obstructive jaundice, biliary strictures | Usually not AFP |
| Metastatic liver lesions | Known primary cancer (colon, breast, lung) | Multiple lesions common | No AFP pattern |
| Hepatic hemangioma | Incidental | Peripheral nodular enhancement | No |
Step pro-tip: If they say PSC + UC and a biliary tree issue → think cholangiocarcinoma, not HCC.
The 5-Second Exam Script (Say This in Your Head)
- Does the patient have cirrhosis or viral hepatitis?
- Do they have RUQ pain/weight loss/decompensation?
- Is AFP elevated?
- Does imaging show arterial enhancement (± washout)?
→ HCC.
Ultra-High-Yield Takeaways (What You Want on Test Day)
- #1 risk factor: cirrhosis (any cause)
- HBV can cause HCC without cirrhosis
- Aflatoxin (moldy grains/peanuts) → p53
- Marker: AFP
- Imaging: arterial phase enhancement (often with washout)
- Screen high-risk patients: ultrasound q6 months
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
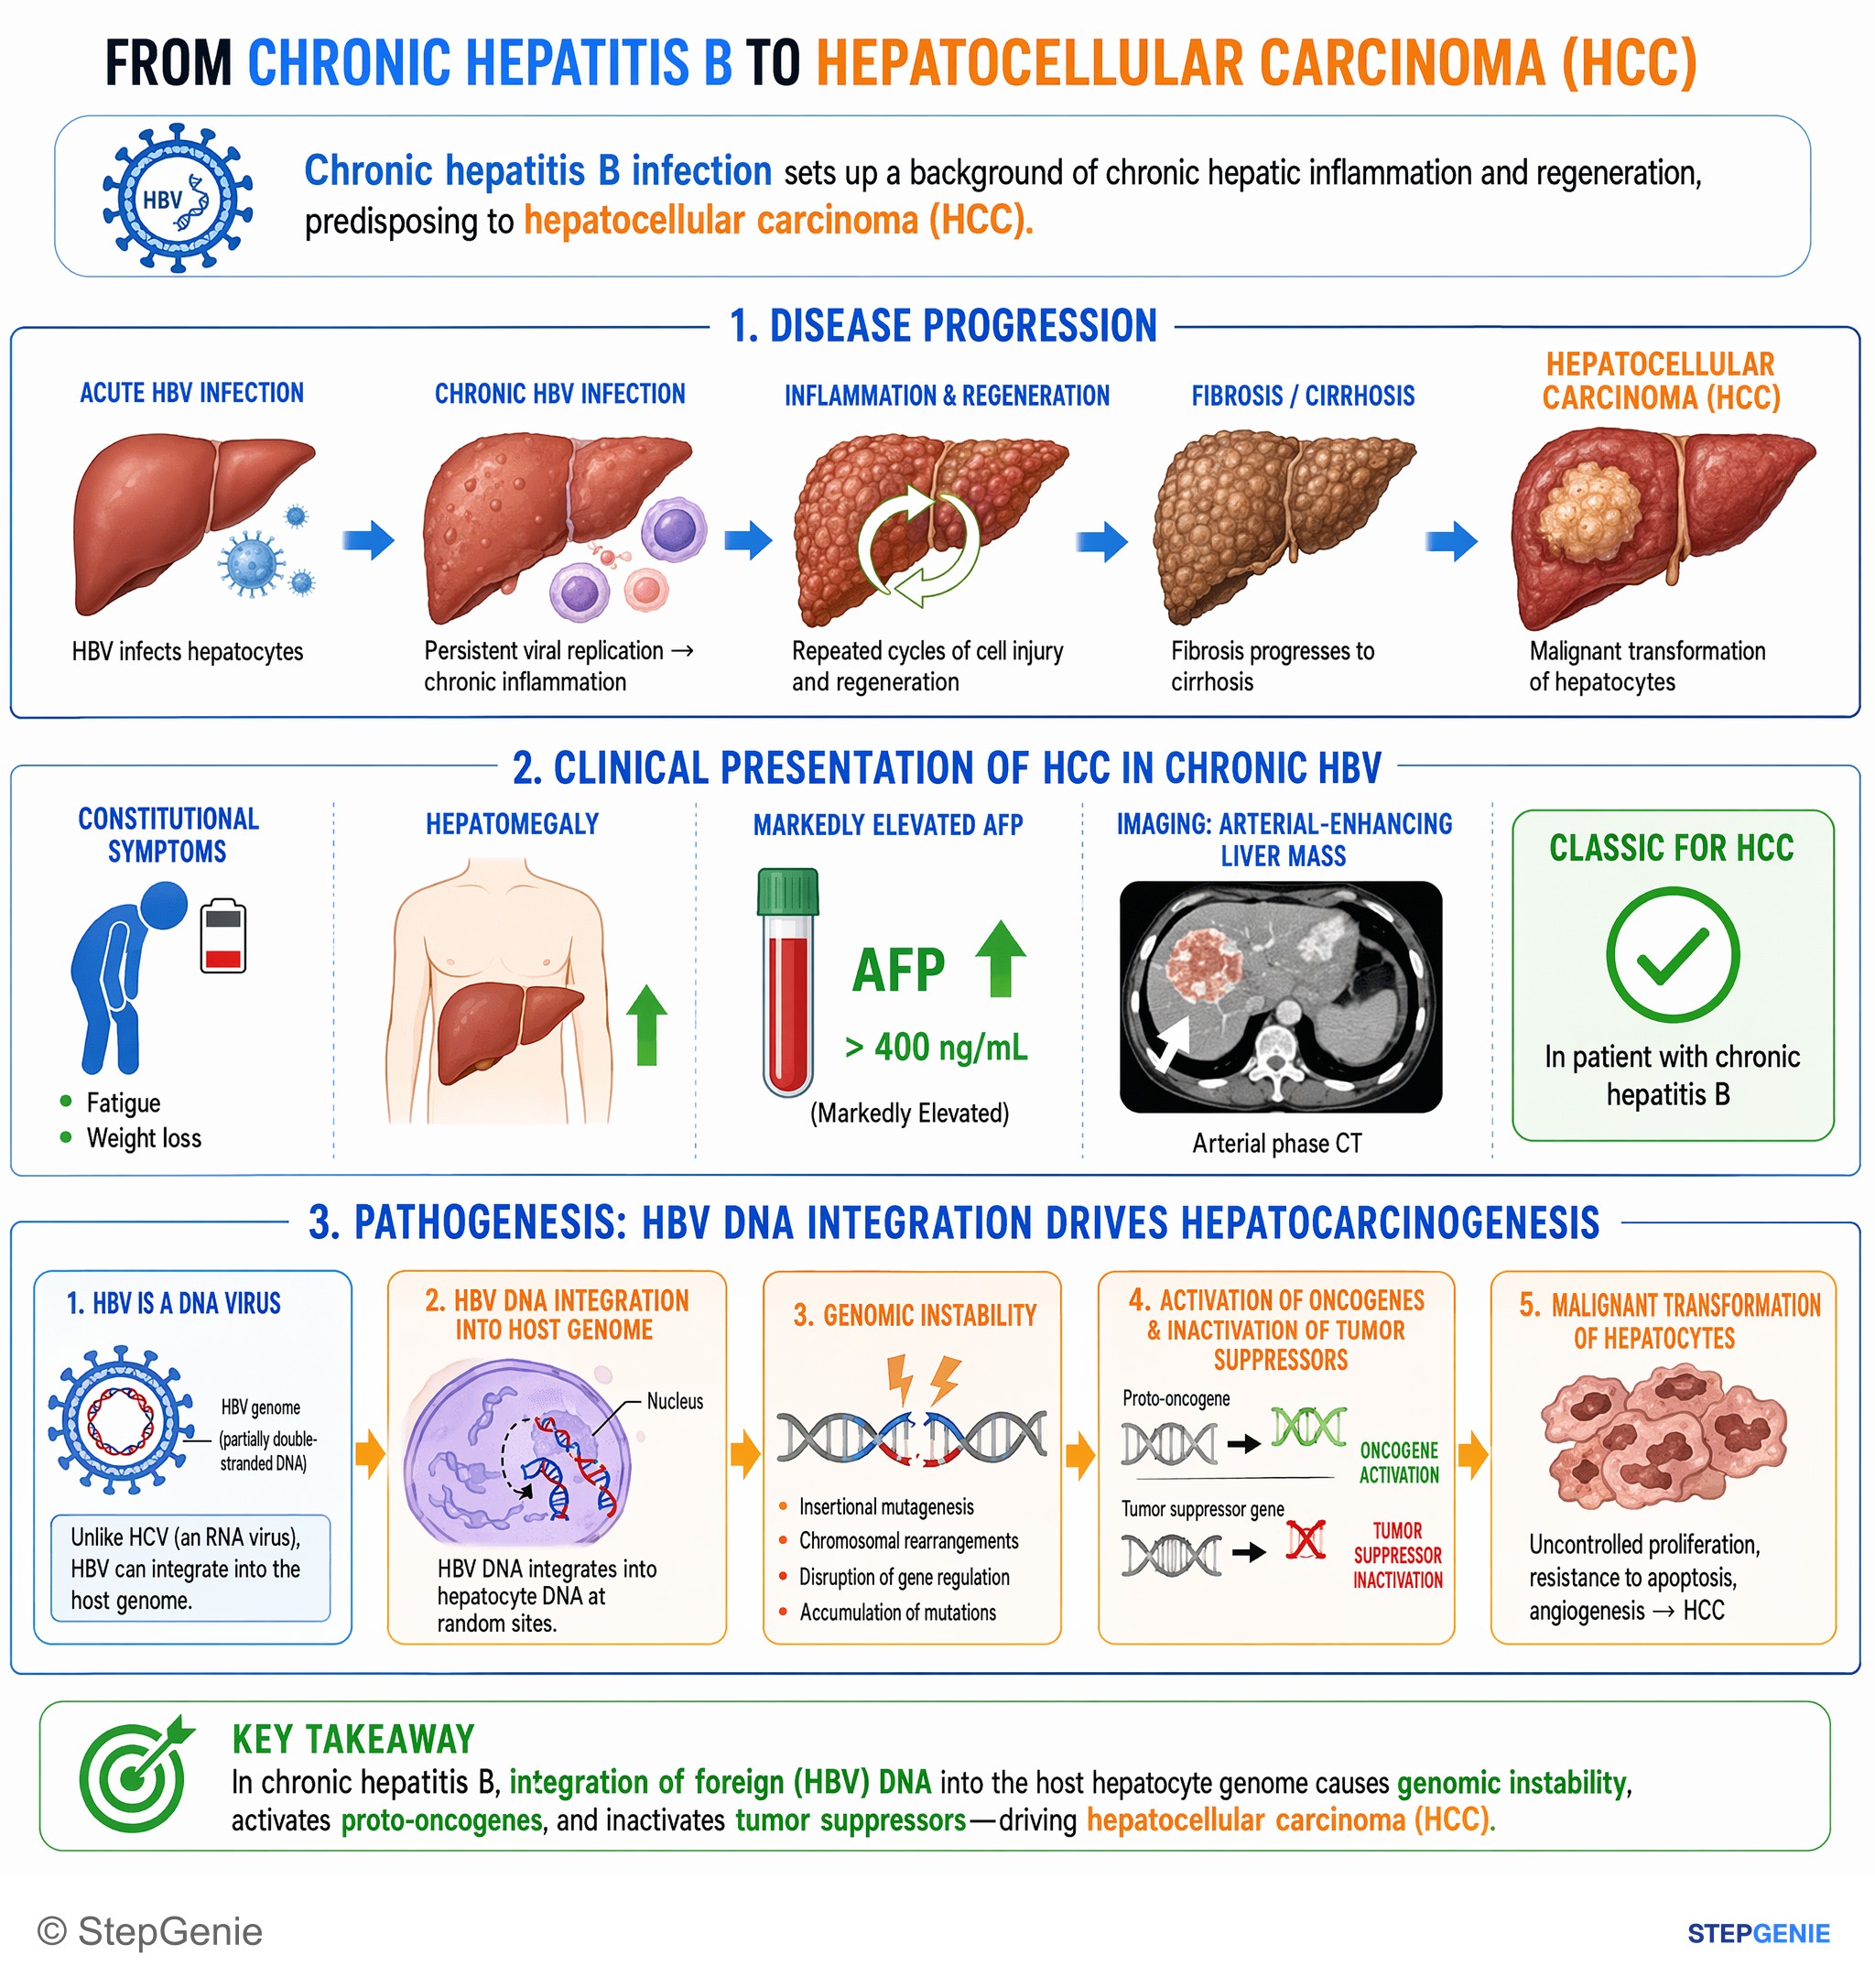
Hepatocellular carcinoma in chronic hepatitis B arises via HBV DNA integration causing genomic instability and oncogene activation in…
USMLE Step 1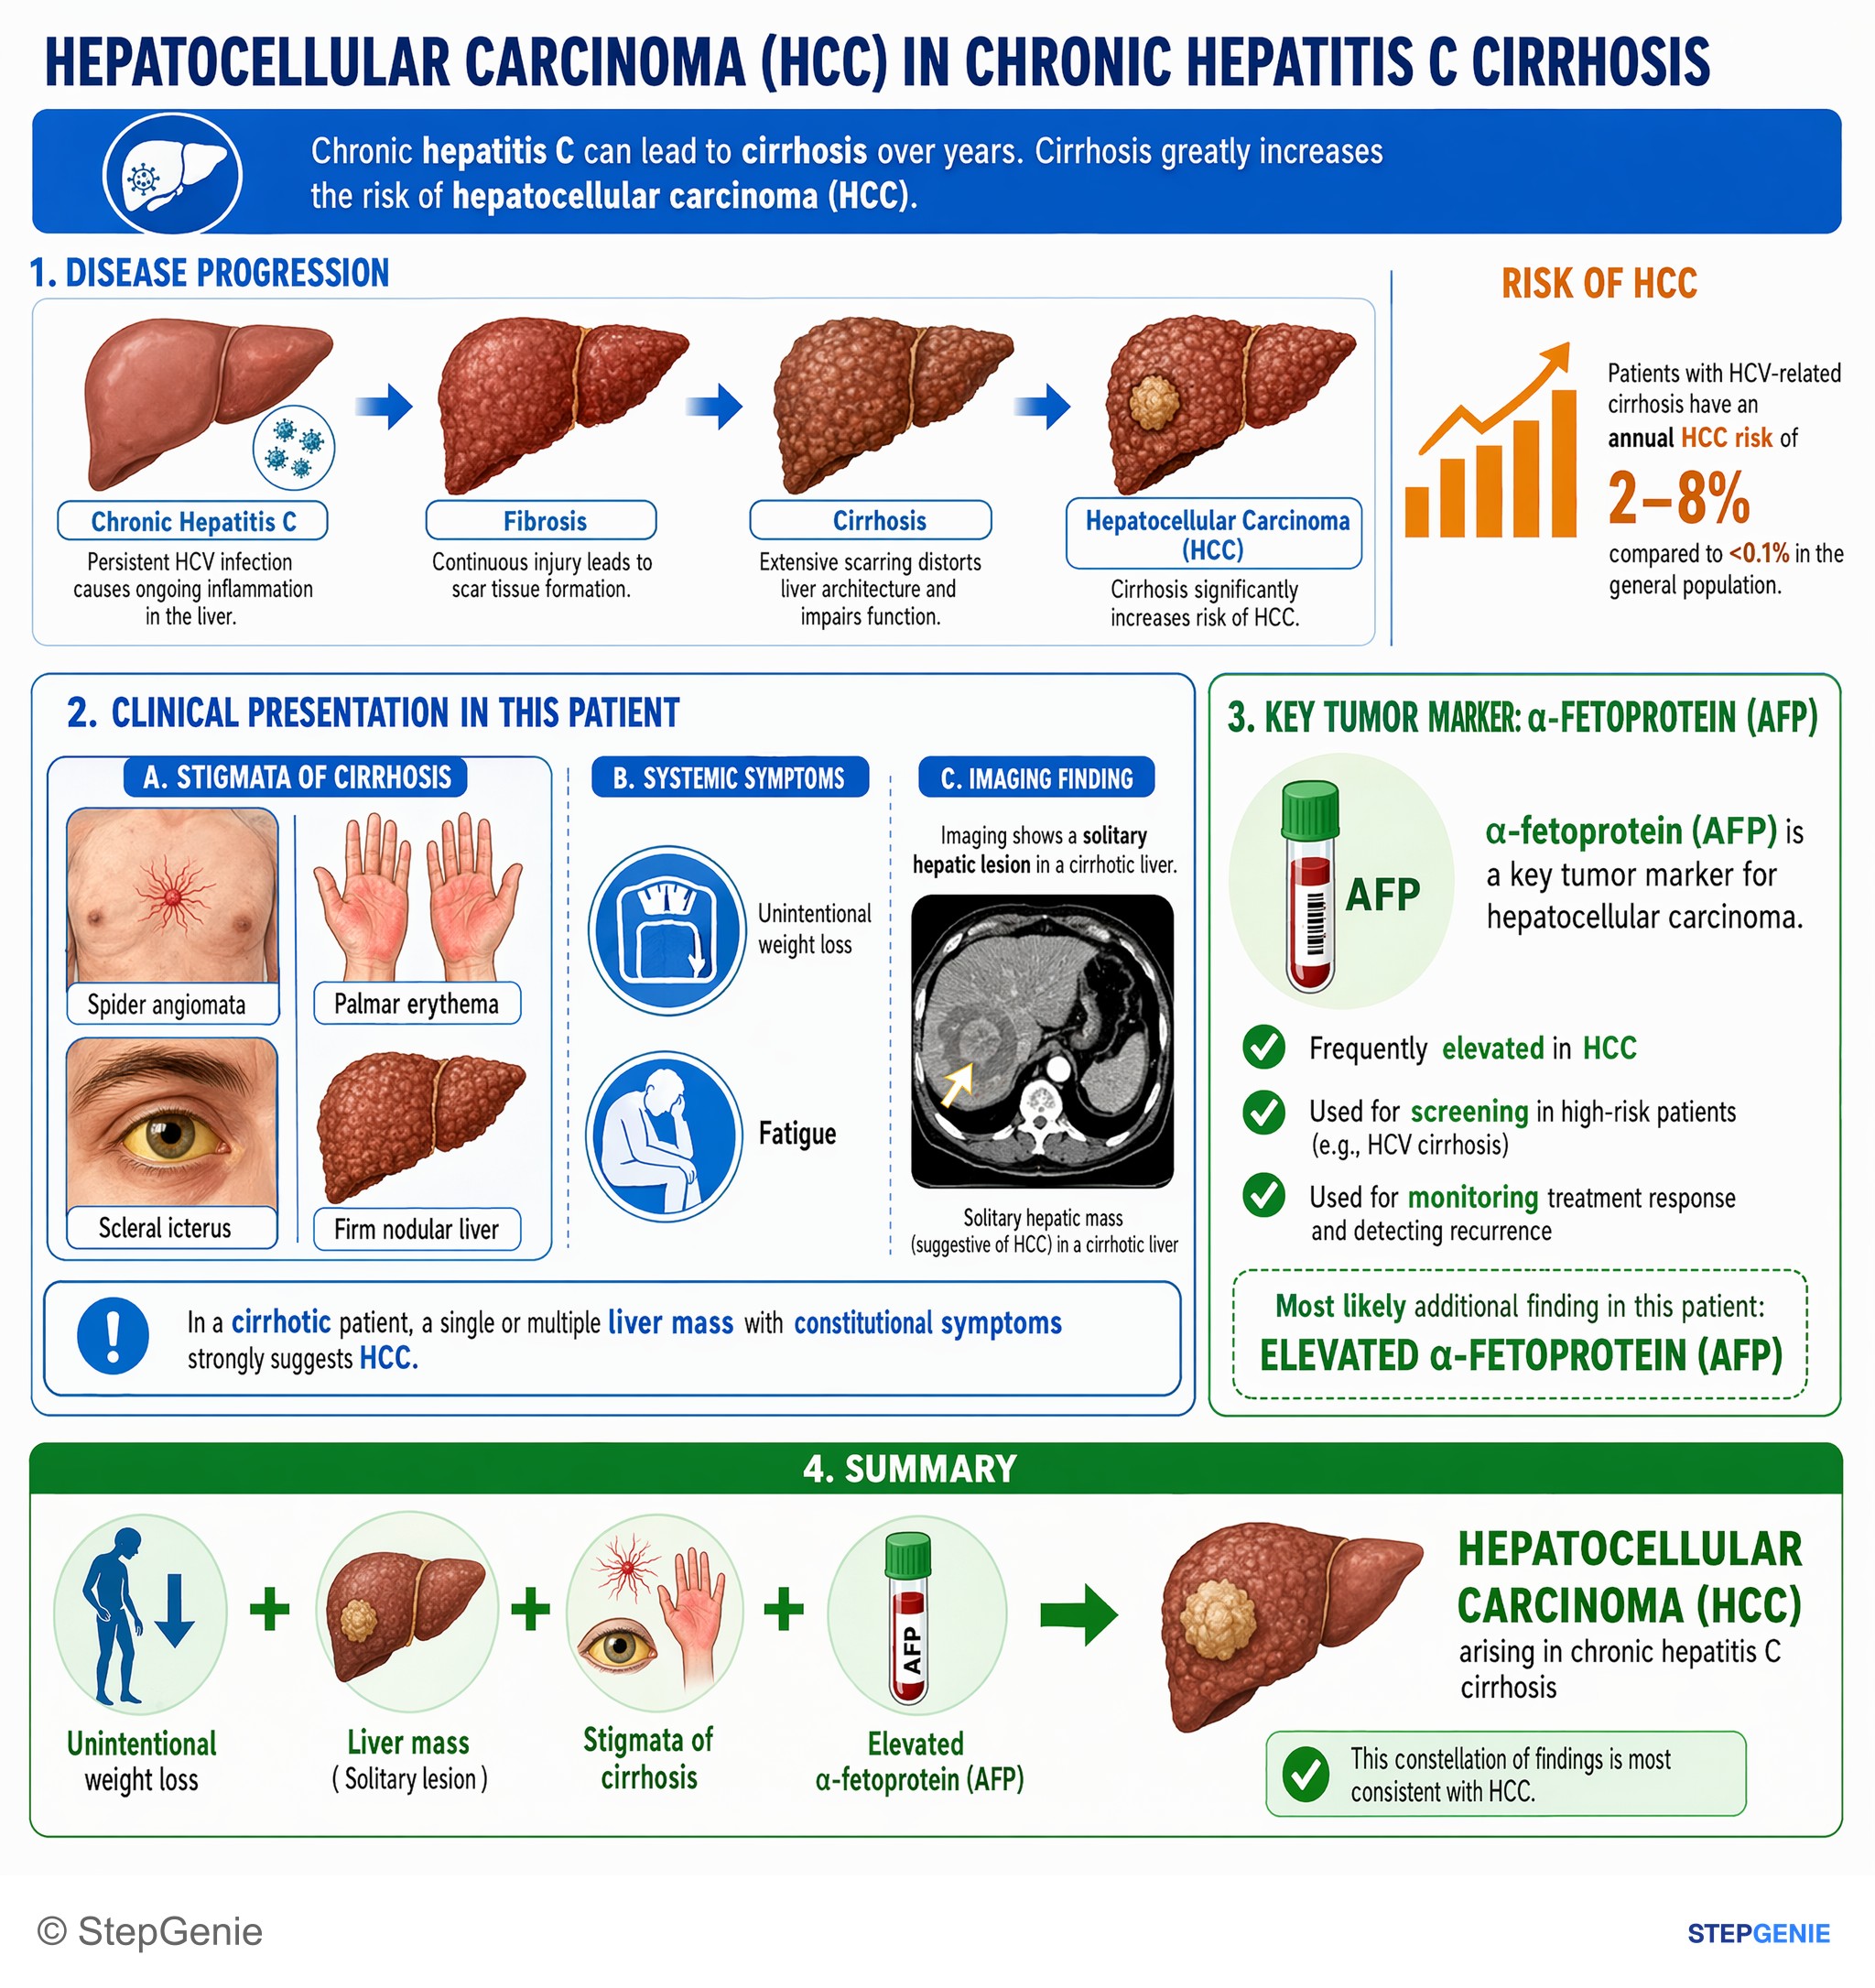
Hepatocellular carcinoma arising in chronic hepatitis C cirrhosis presents with weight loss, liver mass, stigmata of cirrhosis, and…
USMLE Step 1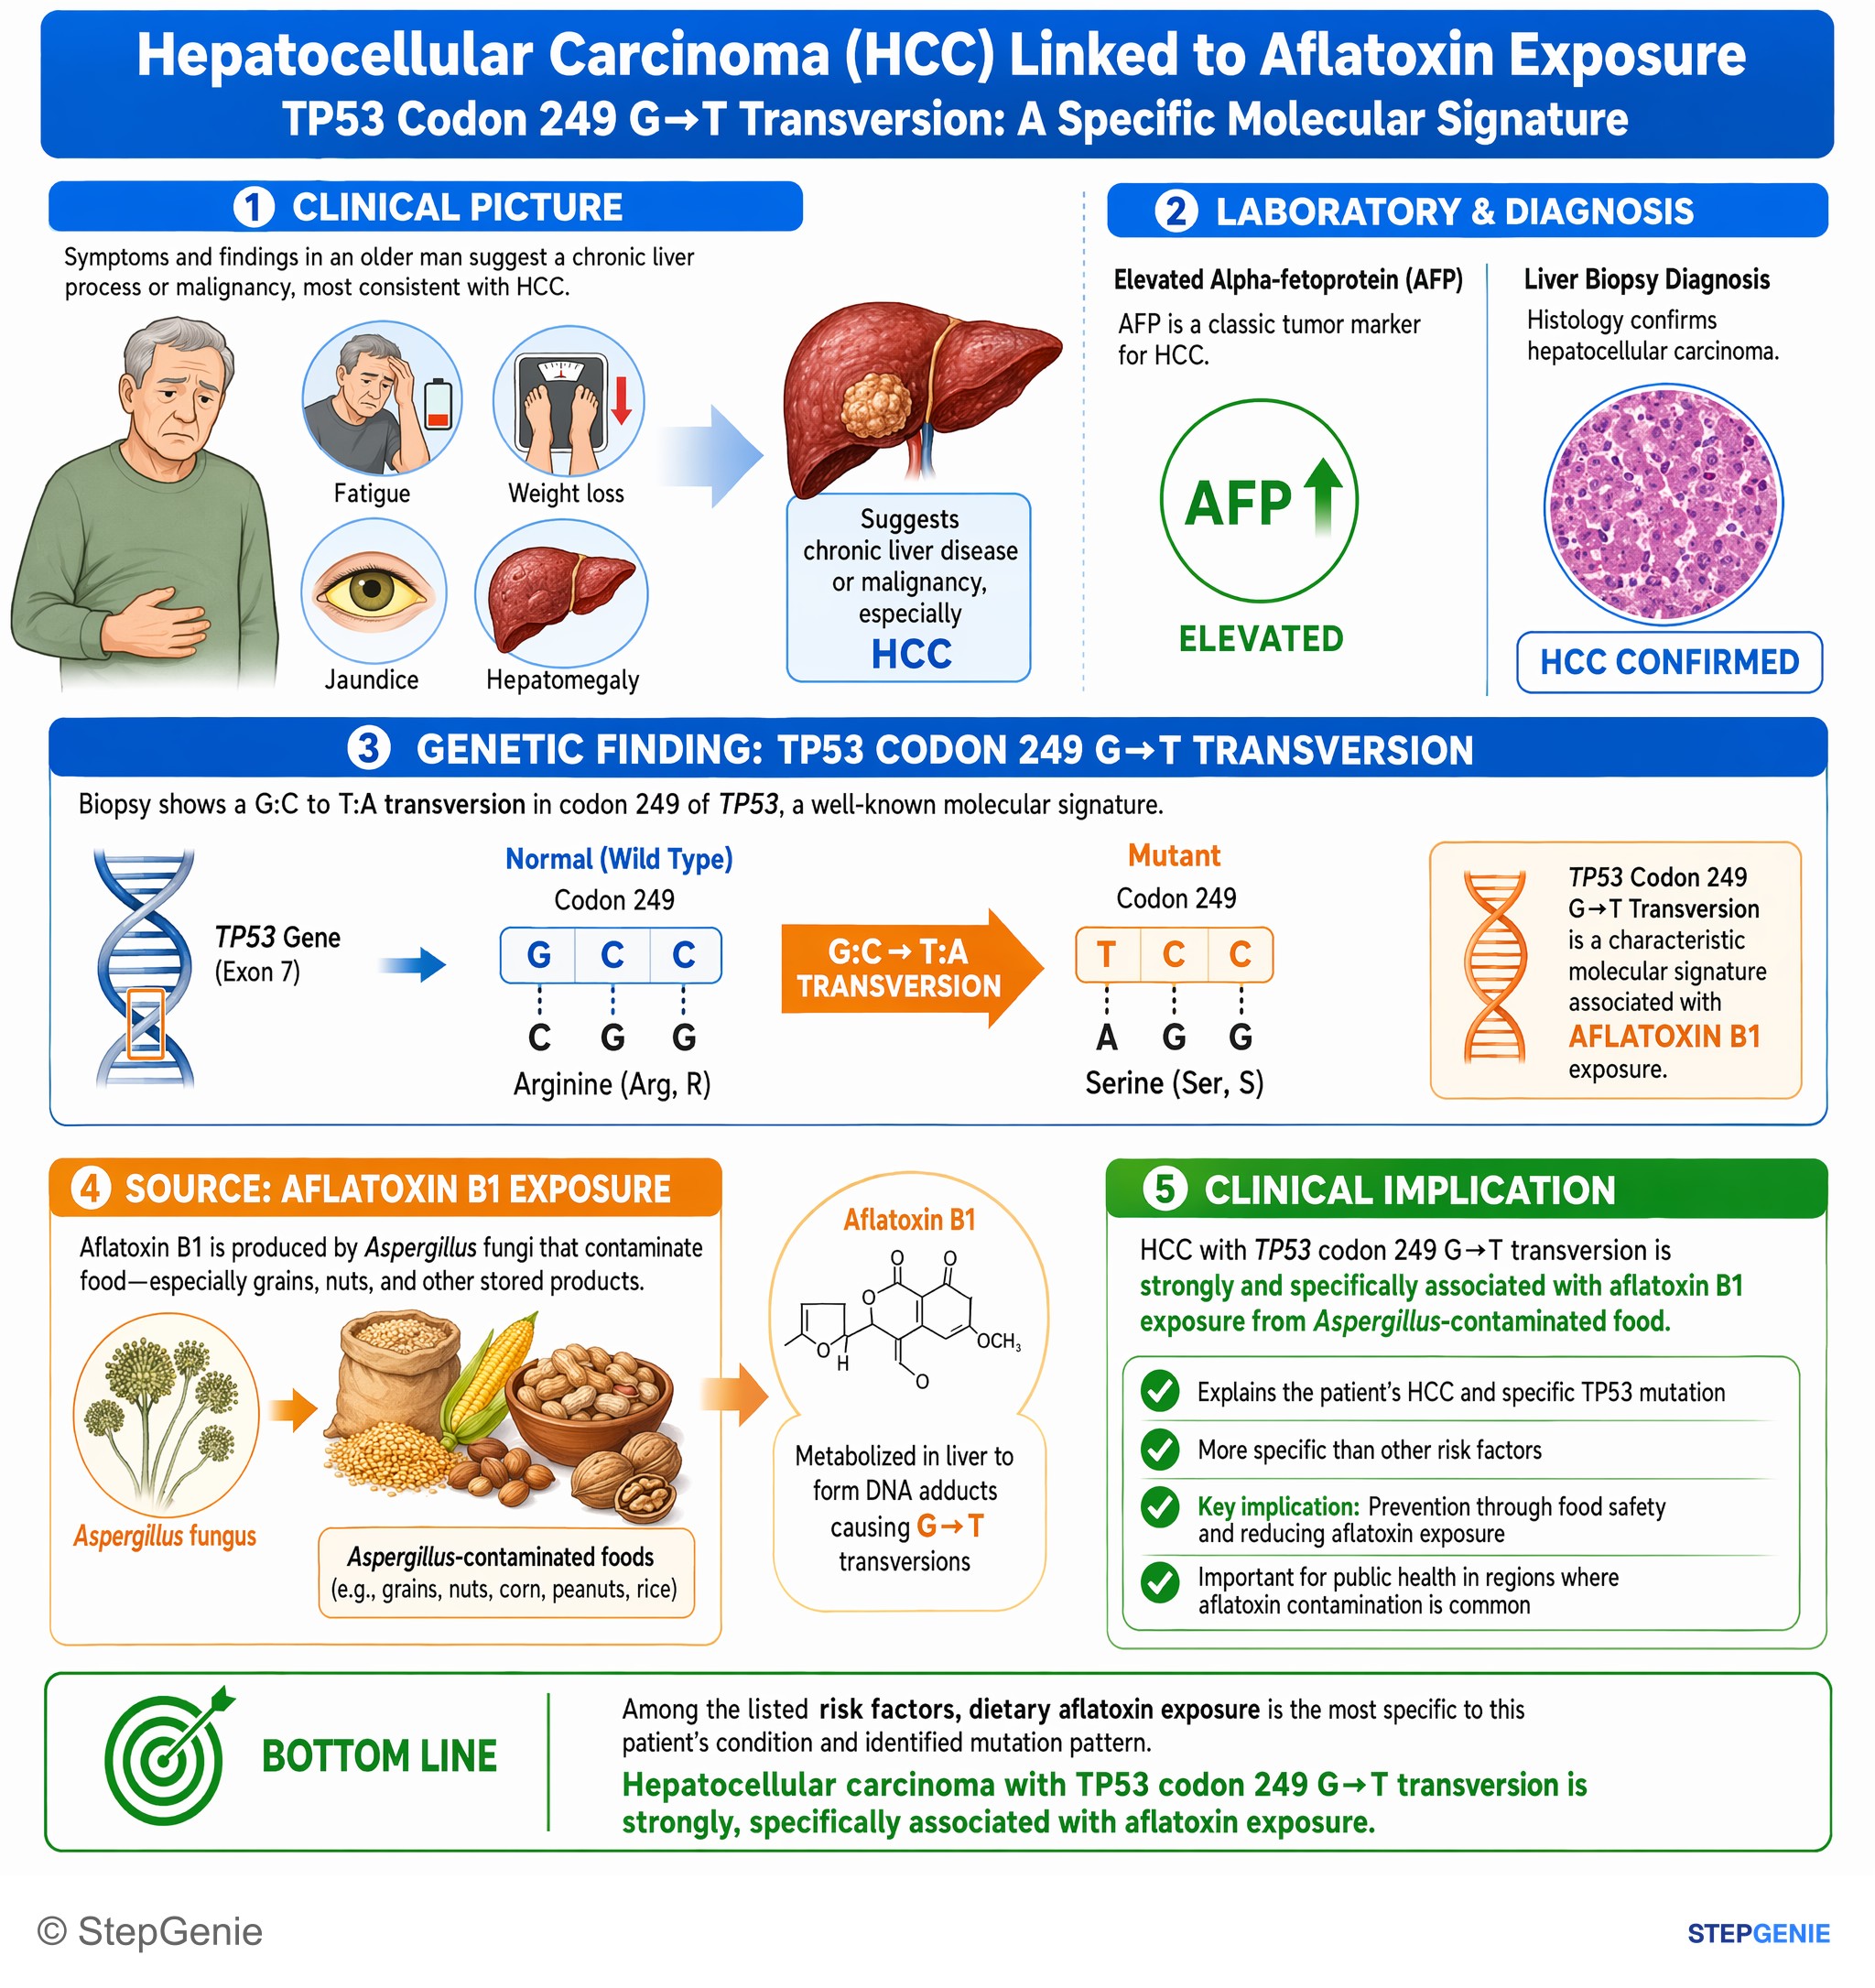
Hepatocellular carcinoma with TP53 codon 249 G→T transversion is strongly, specifically associated with aflatoxin exposure…
USMLE Step 1Frequently Asked Questions
What are the fastest clues that point to hepatocellular carcinoma on a question stem?
The fastest clues are cirrhosis, a liver mass, and elevated AFP, especially with weight loss or right upper quadrant pain. Hepatocellular carcinoma is a primary liver cancer that classically arises in a chronically inflamed or cirrhotic liver. On imaging, it typically shows arterial phase enhancement, often with washout later, which makes that pattern highly recognizable on exams.
Can hepatitis B cause hepatocellular carcinoma even without cirrhosis?
Yes, chronic hepatitis B can cause hepatocellular carcinoma even without cirrhosis. The key board-style twist is that HBV has oncogenic effects through DNA integration, so it does not always need the intermediate step of cirrhosis. In contrast, hepatitis C more often leads to hepatocellular carcinoma through the development of cirrhosis.
How do you tell hepatocellular carcinoma from cholangiocarcinoma or metastatic liver lesions?
Hepatocellular carcinoma is suggested by cirrhosis or viral hepatitis, elevated AFP, systemic symptoms, and arterial enhancement of the liver lesion. Cholangiocarcinoma is more associated with PSC, liver flukes, biliary disease, obstructive jaundice, and biliary strictures, and it usually does not show an AFP pattern. Metastatic liver lesions are more likely when there is a known primary cancer and multiple liver lesions.
Why is AFP helpful in diagnosing hepatocellular carcinoma, and what are its limits?
AFP is helpful because elevated AFP in an at-risk patient with a liver mass is a strong signal for hepatocellular carcinoma. However, AFP is not perfectly sensitive or specific. Mild AFP elevations can also occur in chronic hepatitis or cirrhosis, so the marker is most useful when combined with the clinical setting and the characteristic imaging pattern of arterial enhancement.
Who should be screened for hepatocellular carcinoma, and how is screening done?
High-risk patients, especially those with cirrhosis, should be screened with ultrasound every 6 months. Screening is often combined with AFP depending on the guideline or setting. High-risk groups include all patients with cirrhosis regardless of cause, and many patients with chronic hepatitis B even without cirrhosis, based on risk factors such as age, ethnicity, and family history.