Toxoplasma gondii is one of those Step bugs that keeps showing up in “random” places—brain rings, congenital infections, and AIDS patients with neuro symptoms. The good news: it’s extremely pattern-based. If you can see the pattern, you can usually answer the question in under 10 seconds.
The Visual Hack (Mnemonic You Can Picture)
“TOXO = CAT + RAW MEAT + RING”
Picture this scene:
- A cat sitting on a raw steak
- Next to a brain MRI with ring-enhancing lesions
- And a pregnant patient standing nearby
That single image ties together the high-yield triad:
| Visual cue | USMLE translation |
|---|---|
| Cat | Definitive host = cats (oocysts in feces) |
| Raw meat | Tissue cysts in undercooked meat (esp. pork/lamb) |
| Ring | Ring-enhancing brain lesions in AIDS (reactivation) |
One-Liner (Answer-Choice Ready)
Toxoplasma gondii is a cat-associated protozoan that causes congenital disease and reactivates in AIDS to produce multiple ring-enhancing brain lesions.
What the Exam Actually Tests (High-Yield Core)
Transmission (know the two classic routes)
- Cat feces (oocysts) → cleaning litter box, gardening/soil exposure
- Undercooked meat (tissue cysts) → especially pork and lamb
Step tip: If they mention cat litter or undercooked meat and then neuro/congenital findings, your reflex should be toxo.
Classic Clinical Presentations
1) AIDS / Immunocompromised (Reactivation)
- Multiple ring-enhancing lesions (often basal ganglia/corticomedullary junction)
- Headache, seizures, focal neuro deficits
- Usually CD4 < 100
High-yield differentiator:
- Toxo → multiple ring-enhancing lesions + cat exposure
- Primary CNS lymphoma → often single ring-enhancing lesion, EBV+, can be periventricular
Reality check: both can be ring-enhancing on Step—use clinical context (CD4, EBV, number of lesions, empiric response).
2) Congenital Toxoplasmosis
Classic triad:
- Chorioretinitis
- Hydrocephalus
- Intracranial calcifications (often diffuse)
Compare (frequently tested):
| Congenital infection | Calcifications |
|---|---|
| Toxo | Diffuse intracranial calcifications |
| CMV | Periventricular calcifications |
Extra clues they love:
- Exposure in pregnancy: cat litter, raw/undercooked meat
- Baby with seizures, vision problems, macrocephaly
Diagnosis (What They Expect You to Pick)
Serology
- Toxoplasma IgM → suggests acute/recent infection (esp. pregnancy workup)
- IgG → past exposure (many adults have it)
In AIDS with ring lesions
- Often diagnosed clinically + imaging, then treat empirically
- If no improvement, think alternate diagnosis (e.g., lymphoma)
Treatment & Prophylaxis (Super High-Yield)
Treatment (active disease)
Pyrimethamine + sulfadiazine + leucovorin
- Leucovorin (folinic acid) is added to prevent bone marrow suppression from pyrimethamine.
If sulfa allergy: substitute clindamycin for sulfadiazine.
Prophylaxis in HIV
- TMP-SMX prophylaxis helps prevent toxoplasmosis (and PCP)
- Classically used when CD4 < 100 and Toxo IgG positive (reactivation risk)
The “Score Points Fast” Micro ID Tags
- Protozoan (Apicomplexan)
- Definitive host: cat
- Infectious forms: oocysts (feces), tissue cysts (meat)
- Neuro tropism → brain abscesses in immunocompromised
Lightning Review (What to Recall Under Time Pressure)
- Cat litter / raw meat → toxo exposure
- AIDS + seizures + multiple ring-enhancing lesions → toxo reactivation
- Congenital triad: chorioretinitis + hydrocephalus + diffuse intracranial calcifications
- Tx: pyrimethamine + sulfadiazine + leucovorin
- Prophylaxis: TMP-SMX (CD4 < 100 + IgG+)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
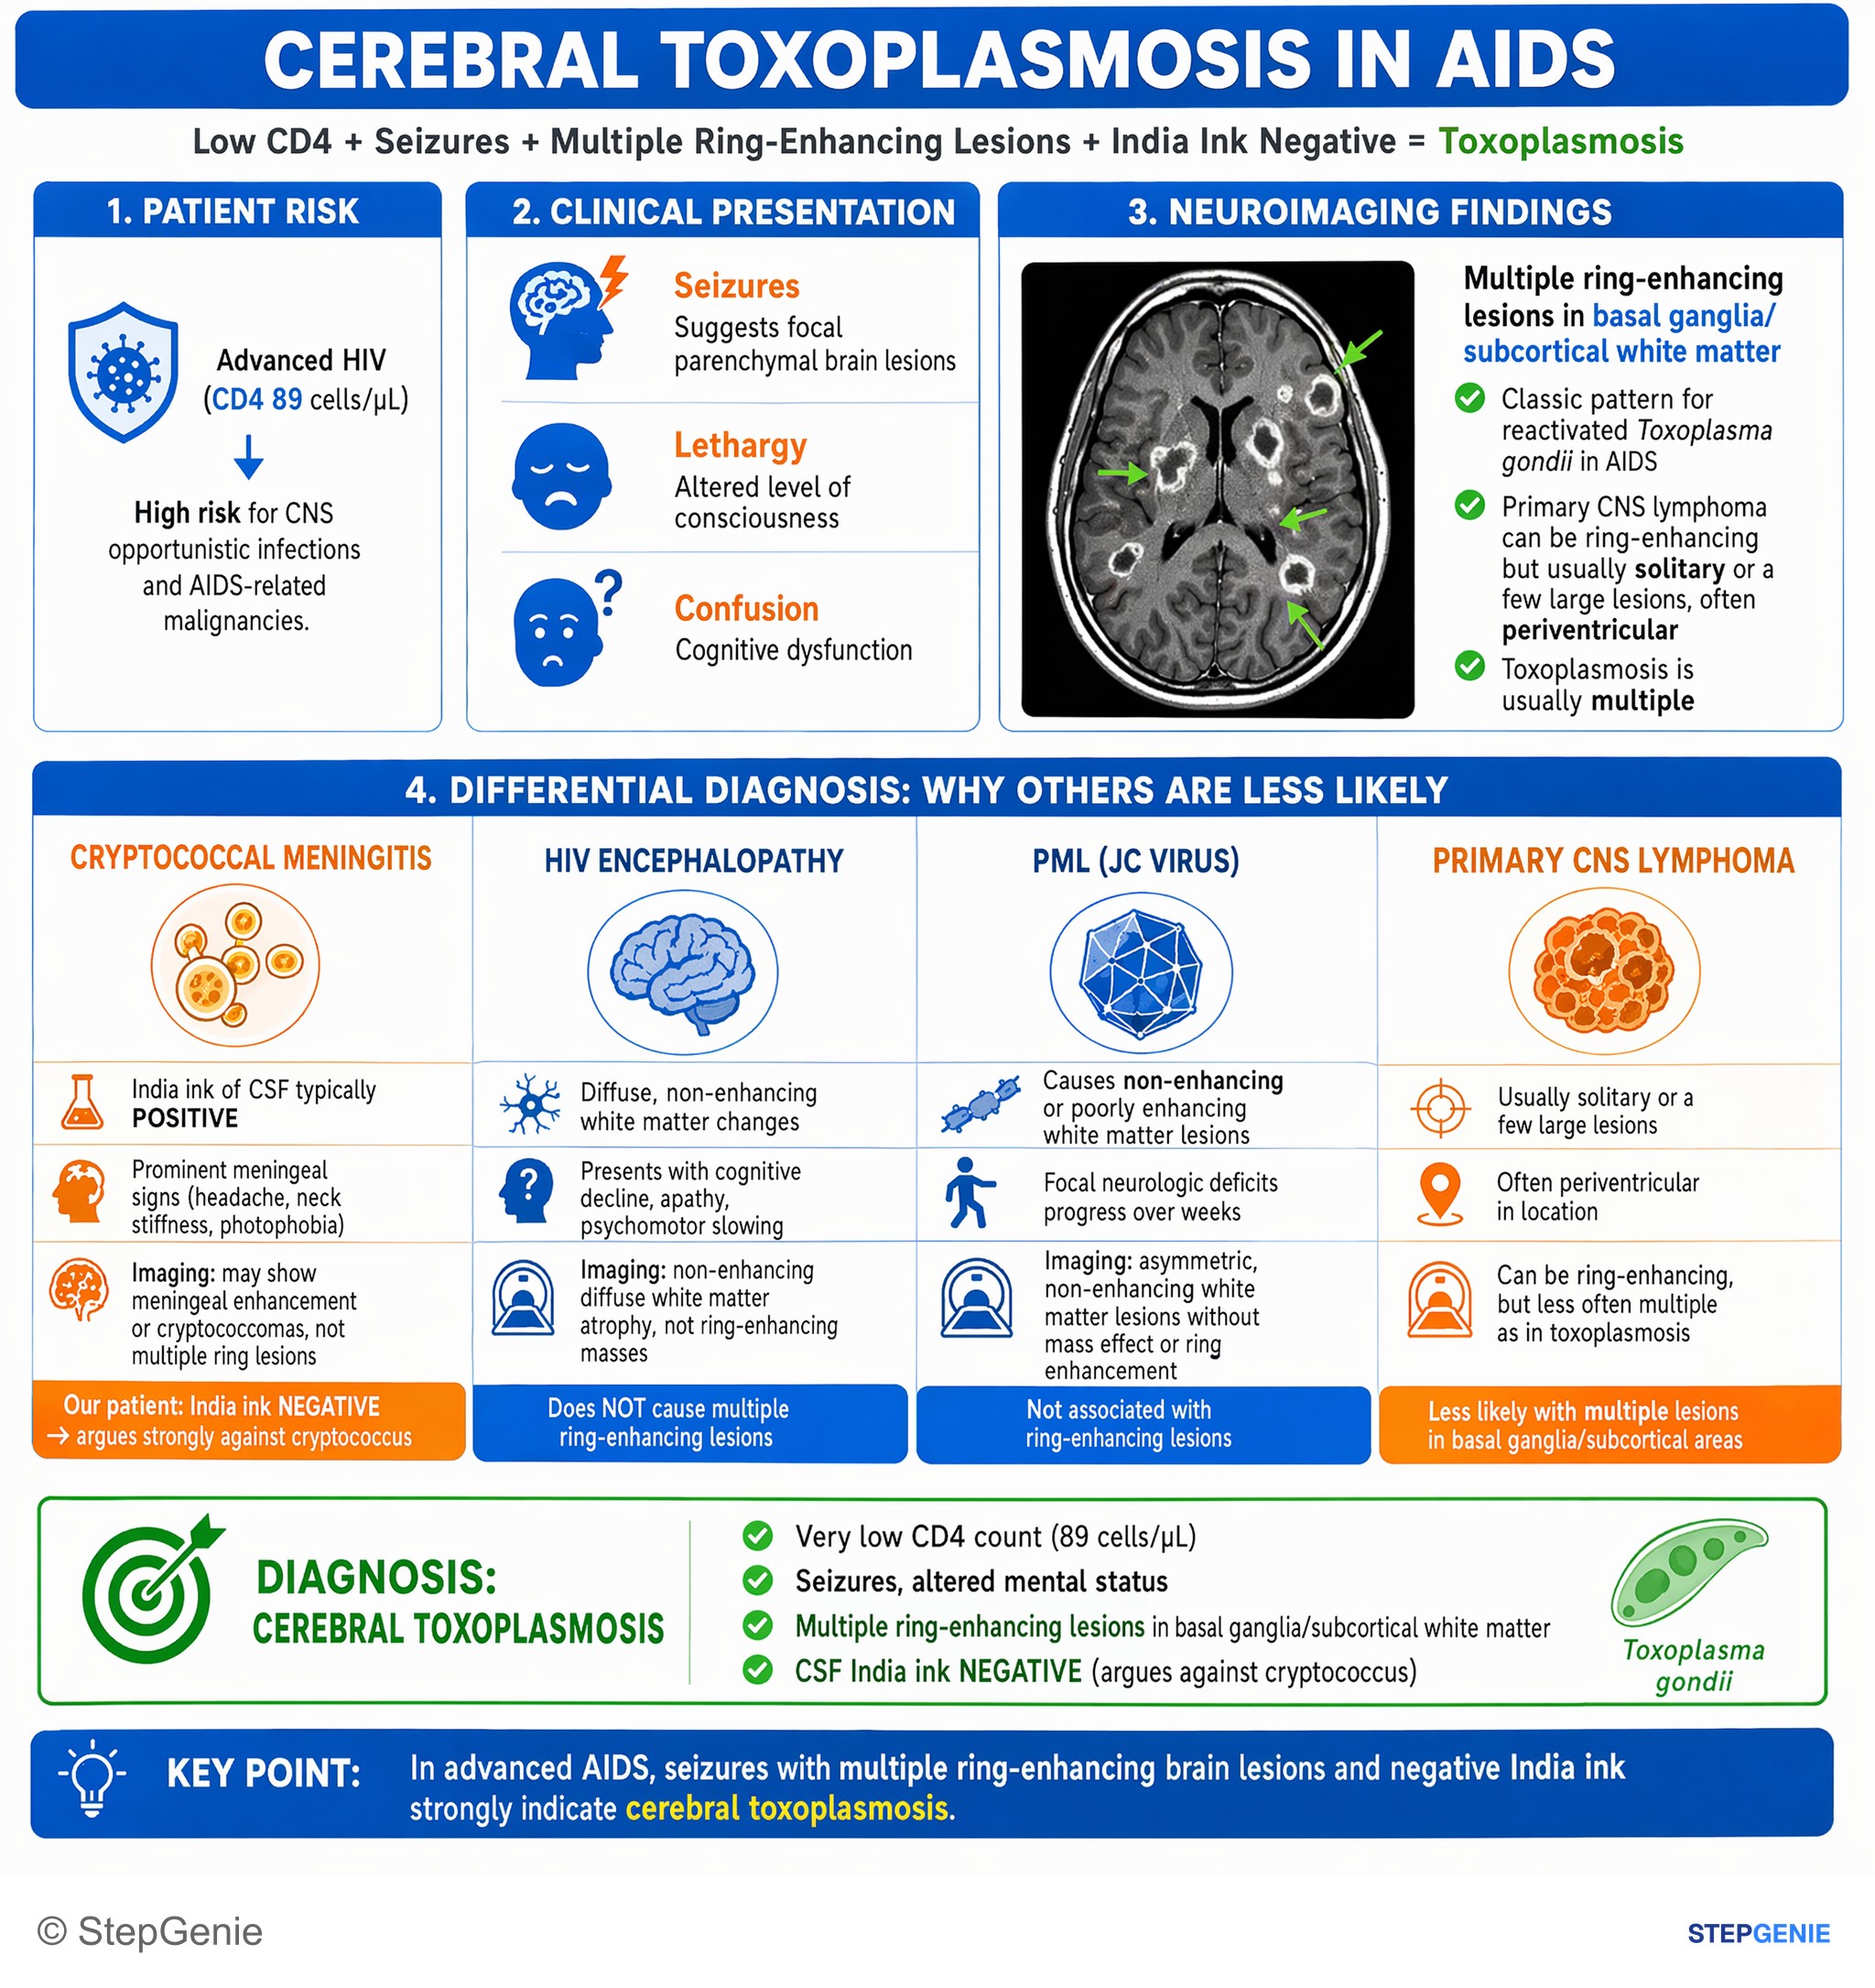
Cerebral toxoplasmosis in AIDS: very low CD4, seizures/AMS, multiple ring-enhancing lesions in basal ganglia; CSF India ink negative…
USMLE Step 2Frequently Asked Questions
How is Toxoplasma gondii usually transmitted on exam questions?
Toxoplasma gondii is classically transmitted by cat feces or undercooked meat. The cat route involves oocysts in feces, so clues like cleaning a litter box or gardening with soil exposure point to toxoplasmosis. The meat route involves tissue cysts, especially in pork and lamb. When those exposures appear with neurologic or congenital findings, toxoplasmosis should be high on the differential.
How do you tell toxoplasmosis from primary CNS lymphoma in an AIDS patient with ring-enhancing brain lesions?
Toxoplasmosis usually causes multiple ring-enhancing brain lesions, while primary CNS lymphoma is often a single ring-enhancing lesion. Toxo questions also may include cat exposure and severe immunosuppression, often with CD4 below 100. Primary CNS lymphoma is associated with EBV positivity and can be periventricular. If a patient with presumed toxoplasmosis does not improve with empiric treatment, an alternate diagnosis such as lymphoma becomes more likely.
What is the congenital toxoplasmosis triad?
The classic congenital toxoplasmosis triad is chorioretinitis, hydrocephalus, and diffuse intracranial calcifications. Exam stems may also include maternal exposure to cat litter or raw or undercooked meat during pregnancy. Babies can present with seizures, vision problems, and macrocephaly. A key comparison is that toxoplasmosis causes diffuse intracranial calcifications, whereas congenital CMV is associated with periventricular calcifications.
What is the first-line treatment for active toxoplasmosis?
The first-line treatment for active toxoplasmosis is pyrimethamine plus sulfadiazine plus leucovorin. Leucovorin, also called folinic acid, is added to reduce bone marrow suppression caused by pyrimethamine. If the patient has a sulfa allergy, clindamycin can be substituted for sulfadiazine. In AIDS patients with ring-enhancing lesions, diagnosis is often made clinically with imaging and treatment may be started empirically.
When do you give TMP-SMX prophylaxis for toxoplasmosis in HIV?
TMP-SMX prophylaxis is classically used in HIV patients with CD4 below 100 who are Toxoplasma IgG positive. The reason is that a positive IgG suggests prior exposure, so severe immunosuppression increases the risk of reactivation. This prophylaxis is high yield because it helps prevent both toxoplasmosis and Pneumocystis pneumonia, making it an important association to recognize on exams.